Anterior pituitary questions love to hide in plain sight: a vague postpartum history, a pituitary macroadenoma with bitemporal hemianopsia, or a medication that quietly alters dopamine tone. If you can instantly recall what the anterior pituitary makes, how it’s regulated, and what “kills” it, you’ll grab easy points on Step 1 and Step 2.
Tip #1: Lock in the “What” with one clean mnemonic (and a visual)
The hormones: FLAT PEG
- FSH
- LH
- ACTH
- TSH
- Prolactin
- Endorphins (from POMC; testable tie-in with ACTH)
- GH
Quick “visual” map (high-yield layout)
Think of the anterior pituitary as two teams:
Tropic hormones (target other endocrine glands):
- TSH → thyroid
- ACTH → adrenal cortex
- FSH/LH → gonads
Direct-acting:
- Prolactin → breast (milk production)
- GH → liver (IGF-1) + many tissues
One-liner:
Most anterior pituitary hormones are tropic (they stimulate other glands), while prolactin and GH act more directly on tissues.
USMLE pearls
- POMC cleavage → ACTH and MSH: explains hyperpigmentation in primary adrenal insufficiency (Addison) and sometimes ectopic ACTH.
- TSH is a glycoprotein, like FSH, LH, hCG (classic association).
Tip #2: Master regulation with the “Dopamine is the brake” rule
If you remember just one regulatory fact, make it this:
Dopamine tonically inhibits prolactin
- Hypothalamus → dopamine → inhibits prolactin
- Suckling → ↓ dopamine → ↑ prolactin
One-liner:
Prolactin is the only anterior pituitary hormone under predominant tonic inhibition (dopamine).
Rapid regulation table (memorize-worthy)
| Anterior pituitary hormone | Hypothalamic regulator(s) | High-yield “exam behavior” |
|---|---|---|
| Prolactin | ↓ by dopamine, ↑ by TRH | Stalk effect (↓ dopamine delivery) → ↑ prolactin |
| TSH | ↑ by TRH, ↓ by somatostatin | Primary hypothyroid → ↑ TRH can also ↑ prolactin |
| ACTH | ↑ by CRH | Cushing disease vs ectopic ACTH vs adrenal tumor patterns |
| GH | ↑ by GHRH, ↓ by somatostatin | Acromegaly: ↑ IGF-1; glucose suppresses GH in normal physiology |
| FSH/LH | ↑ by GnRH (pulsatile) | Continuous GnRH → downregulation → ↓ FSH/LH (e.g., leuprolide) |
USMLE pearls
- Pituitary stalk compression (macroadenoma) classically causes:
- ↑ prolactin (loss of dopamine inhibition)
- ± decreased other pituitary hormones (due to mass effect)
- Antipsychotics (D2 blockers) → hyperprolactinemia → galactorrhea, amenorrhea, infertility, decreased libido.
- TRH increases prolactin: primary hypothyroidism can present with galactorrhea + amenorrhea due to ↑ TRH → ↑ prolactin.
Tip #3: Predict lesions with one vascular fact (and two “can’t-miss” syndromes)
Key anatomy: the anterior pituitary depends on portal blood
The anterior pituitary is supplied mainly by the hypothalamic–hypophyseal portal system, making it vulnerable when blood flow drops.
One-liner:
Anterior pituitary is “portal-dependent,” so ischemia hits it hard—think postpartum hemorrhage → Sheehan syndrome.
Two high-yield clinical hitters
Sheehan syndrome (postpartum pituitary infarction)
- Trigger: severe postpartum hemorrhage
- Mechanism: enlarged pituitary in pregnancy + hypoperfusion → ischemic necrosis
- Classic findings:
- Failure to lactate (↓ prolactin) = early clue
- Amenorrhea (↓ FSH/LH)
- Hypothyroid symptoms (↓ TSH)
- Adrenal insufficiency symptoms (↓ ACTH)
Pituitary adenoma patterns
- Prolactinoma: most common functional pituitary adenoma
- Symptoms: galactorrhea, amenorrhea/infertility, hypogonadism
- Tx: cabergoline or bromocriptine (dopamine agonists)
- Macroadenoma mass effect:
- Bitemporal hemianopsia (optic chiasm compression)
- Headaches
- “Stalk effect” → mild/moderate ↑ prolactin
USMLE pearls
- Prolactin level can help distinguish:
- Very high prolactin often suggests prolactinoma
- Mild–moderate elevation can be stalk effect or meds
- Pituitary apoplexy (hemorrhage into adenoma): sudden headache + vision changes + hormonal collapse (Step 2 favorite emergency vignette).
15-second recap (shareable)
- FLAT PEG = anterior pituitary hormones (tropic vs direct-acting helps organize).
- Dopamine inhibits prolactin (stalk effect, antipsychotics, hypothyroid via TRH).
- Portal blood supply makes anterior pituitary ischemia-prone → Sheehan postpartum; macroadenomas → bitemporal hemianopsia.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
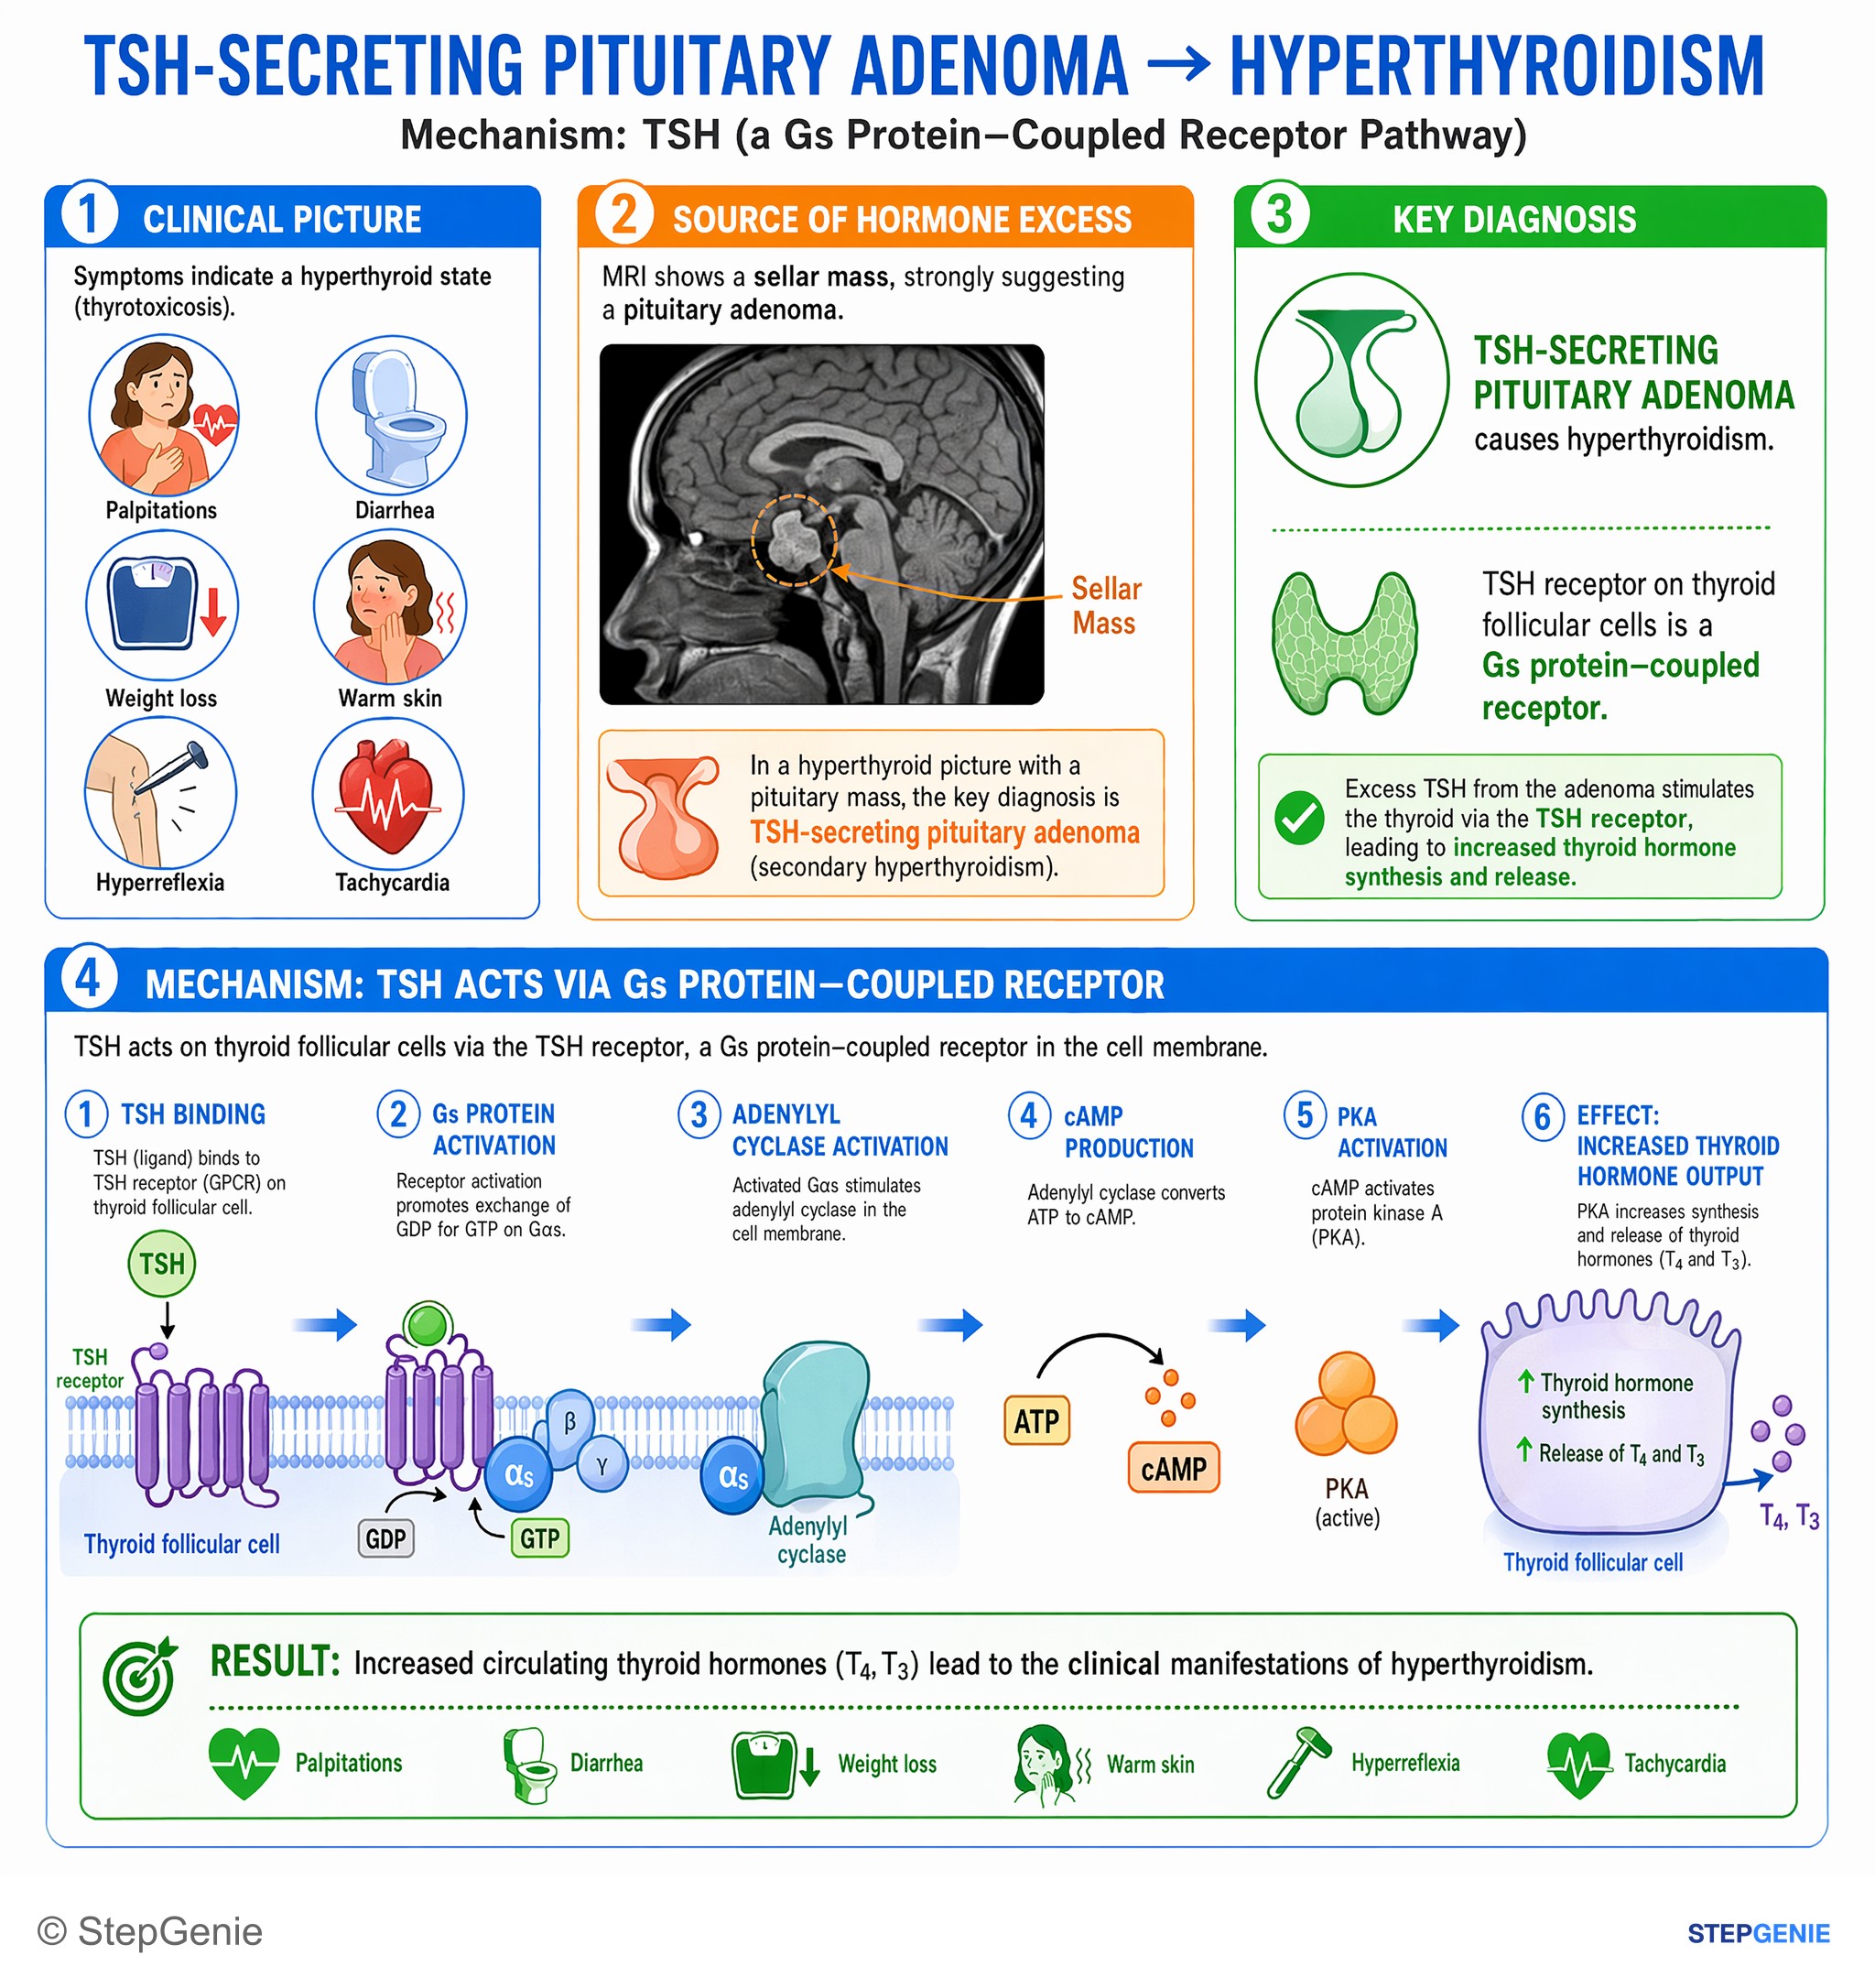
TSH-secreting pituitary adenoma causes hyperthyroidism; TSH receptor on thyroid follicular cells is a Gs protein–coupled receptor.
USMLE Step 1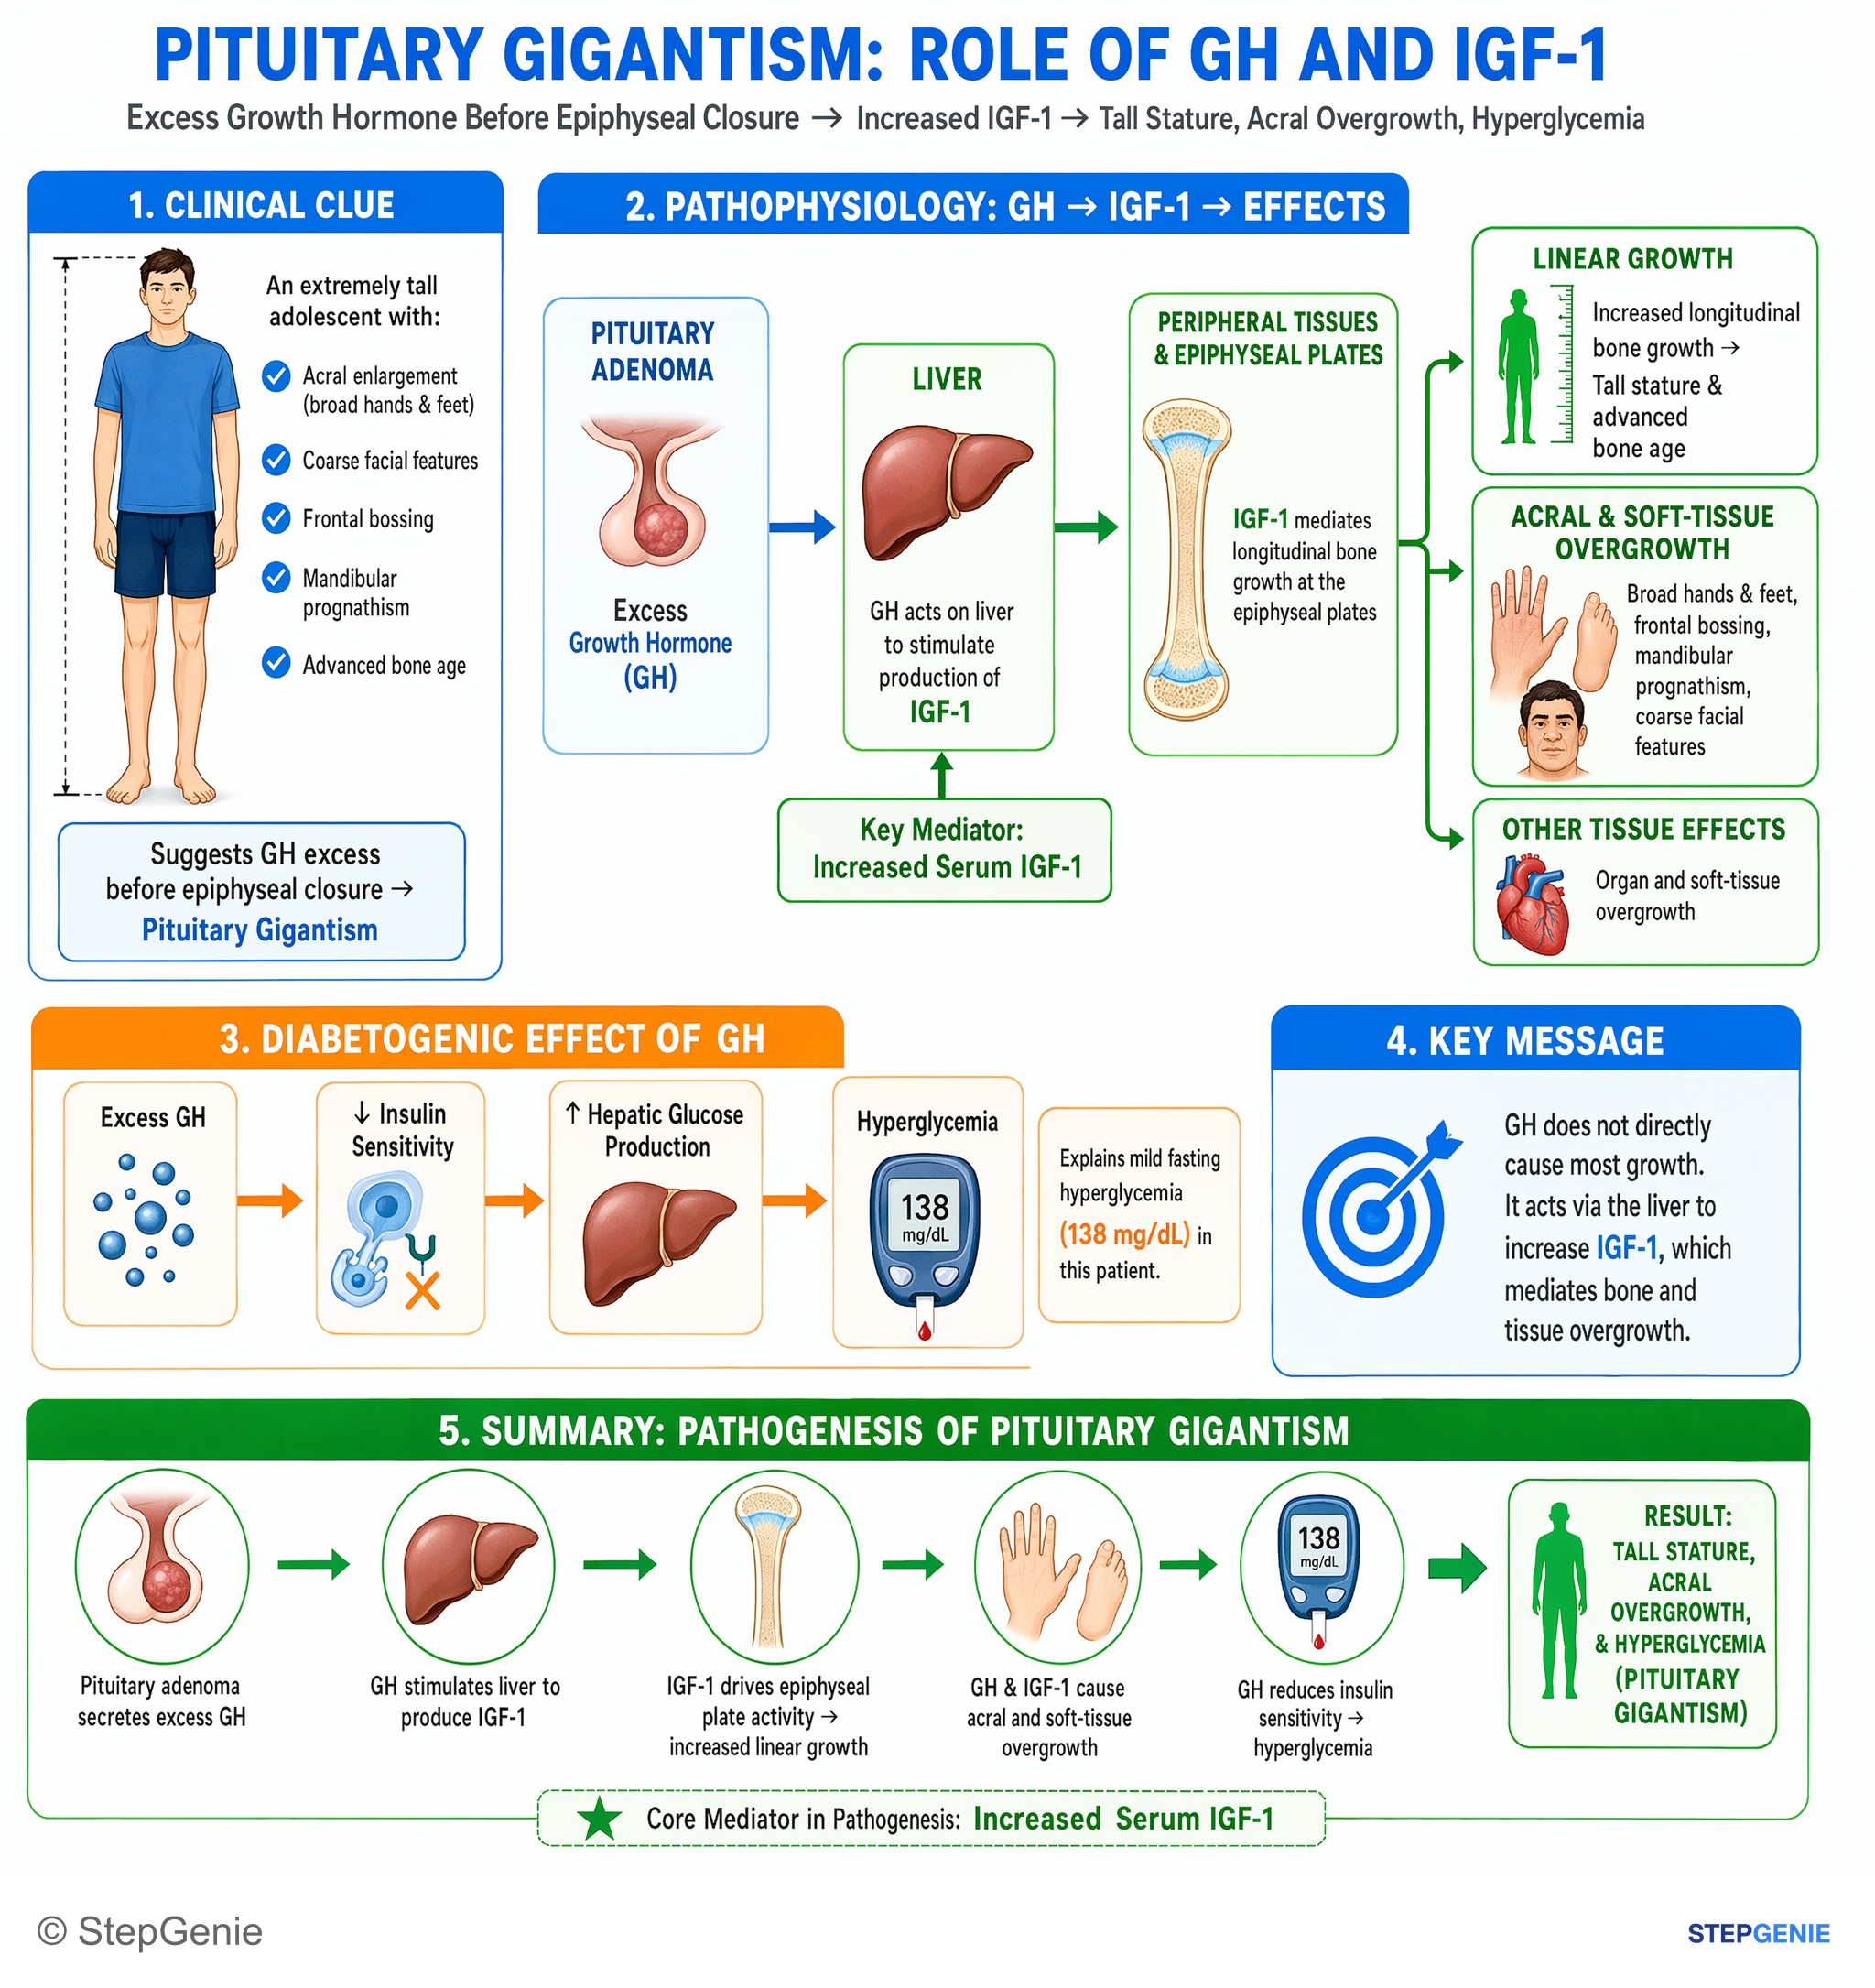
Pituitary gigantism from excess GH → ↑ IGF-1 (liver) before epiphyseal closure → tall stature, acral overgrowth, hyperglycemia.
USMLE Step 1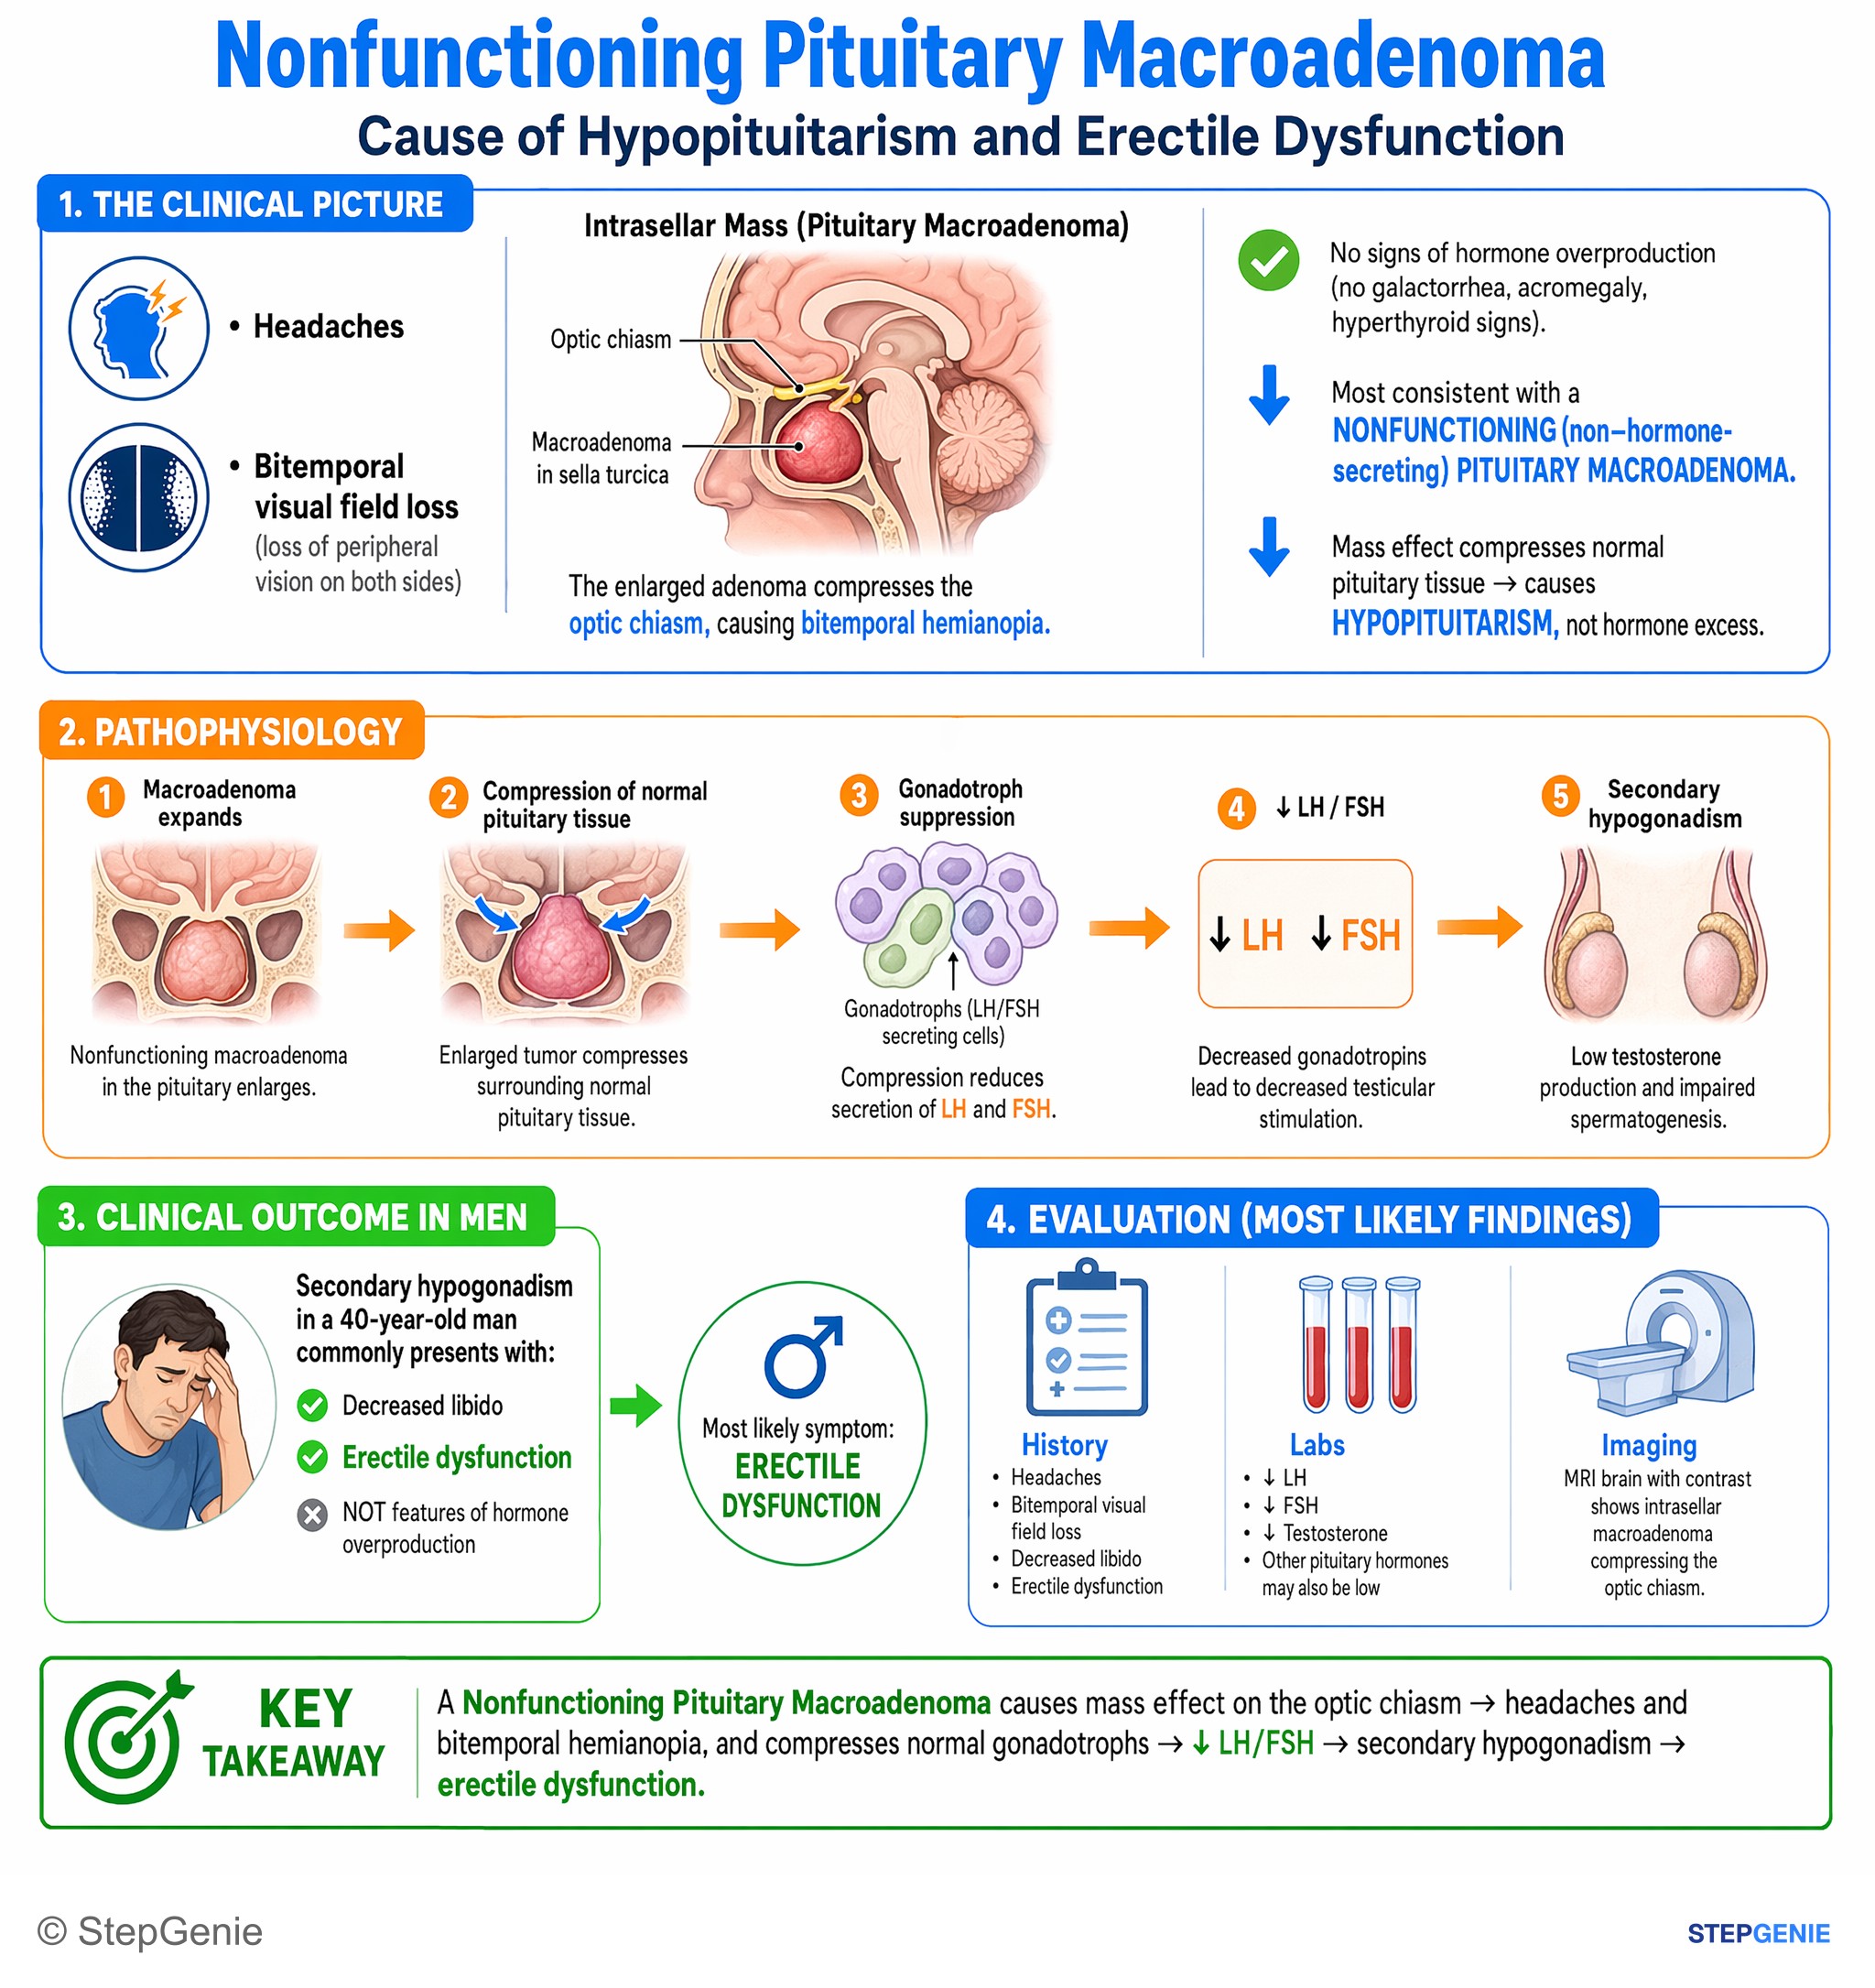
Nonfunctioning pituitary macroadenoma compresses normal gonadotrophs → ↓LH/FSH → hypogonadism with erectile dysfunction, headaches, and…
USMLE Step 2Frequently Asked Questions
What hormones does the anterior pituitary make, and which ones are tropic versus direct-acting?
The anterior pituitary makes FSH, LH, ACTH, TSH, prolactin, endorphins, and GH. Most are tropic hormones that stimulate other endocrine glands, including TSH to the thyroid, ACTH to the adrenal cortex, and FSH/LH to the gonads. Prolactin and GH are the main direct-acting hormones, with prolactin promoting milk production and GH acting through the liver via IGF-1 and on many tissues.
Why does pituitary stalk compression cause high prolactin?
Pituitary stalk compression raises prolactin because dopamine normally tonically inhibits prolactin release. When a macroadenoma or other lesion reduces dopamine delivery through the stalk, that inhibitory brake is lost and prolactin increases. This stalk effect can also occur with mass effect on the pituitary, and the same basic principle explains why D2-blocking antipsychotics can cause hyperprolactinemia.
How can primary hypothyroidism cause galactorrhea and amenorrhea?
Primary hypothyroidism can cause galactorrhea and amenorrhea because increased TRH stimulates prolactin release. Prolactin is increased by TRH, so when TRH rises in primary hypothyroidism, prolactin can rise as well. That hyperprolactinemia can present with galactorrhea and menstrual dysfunction, making this an important endocrine association to recognize on exams.
Why is the anterior pituitary vulnerable to ischemia after severe postpartum hemorrhage?
The anterior pituitary is especially vulnerable because it depends mainly on the hypothalamic-hypophyseal portal blood supply. When severe postpartum hemorrhage causes hypoperfusion, the enlarged pituitary in pregnancy can undergo ischemic necrosis, producing Sheehan syndrome. A classic early clue is failure to lactate from low prolactin, followed by amenorrhea, hypothyroid symptoms, and adrenal insufficiency symptoms from loss of other anterior pituitary hormones.
How do you tell prolactinoma from stalk effect on a pituitary question?
Prolactin level and the overall pattern help distinguish them. Very high prolactin often points to a prolactinoma, which is the most common functional pituitary adenoma and can cause galactorrhea, amenorrhea or infertility, and hypogonadism. Mild to moderate prolactin elevation suggests stalk effect or medications instead. Macroadenomas also commonly produce headaches and bitemporal hemianopsia from optic chiasm compression.