Average-risk adults start colorectal cancer (CRC) screening at age 45 and continue through 75 (USPSTF 2021: grade B at 45-49, grade A at 50-75), then decide individually at 76-85. Options are a yearly FIT or high-sensitivity guaiac test, a multitarget stool DNA test every 1-3 years (every 3 years per ACS), CT colonography or flexible sigmoidoscopy every 5 years, or colonoscopy every 10 years, and any abnormal non-colonoscopy test must be followed by colonoscopy (ACS: preferably within 6 months of a positive stool or blood test). High-risk people follow different rules: a first-degree relative with CRC or an advanced adenoma before 60 means colonoscopy every 5 years from age 40, or 10 years before the relative's diagnosis if that is earlier. What changed by October 2026: the USPSTF recommendation is still the May 2021 version, but the American Cancer Society's May 2026 update added a stool RNA test and lists blood-based tests (such as Shield) only as a non-preferred option for people who decline or don't complete stool tests and visual exams.
The flowchart, step by step
Step 1. Symptoms or signs? Rectal bleeding, iron deficiency anemia, a change in bowel habits or a positive prior test is not screening. Go straight to diagnostic colonoscopy; the USPSTF recommendation covers asymptomatic adults only. Right-sided cancers may show up only as fatigue from anemia (see iron deficiency anemia).
Step 2. Average or increased risk? The USPSTF recommendation does not apply to anyone with prior CRC or adenomatous polyps, inflammatory bowel disease, or a known hereditary syndrome (Lynch, FAP). Family history moves you to the high-risk branch (Step 6).
Step 3. Average risk: check the age.
| Age | USPSTF 2021 | ACS 2026 / USMSTF 2022 |
|---|---|---|
| 45-49 | Screen (grade B) | Screen |
| 50-75 | Screen (grade A) | Screen (through 75 if life expectancy >10 years) |
| 76-85 | Selectively (grade C): health, prior screening, preference | Individualize |
| >85 | Evidence lacking; competing mortality likely outweighs benefit | Don't screen |
Step 4. Pick one strategy (table below). The best test is the one the patient will actually complete.
Step 5. Positive stool, blood, CT colonography or sigmoidoscopy result → colonoscopy. Don't repeat the stool test to "confirm" it. After a positive stool or blood test, ACS asks for colonoscopy preferably within 6 months; screening isn't finished until that colonoscopy is done.
Step 6. Increased risk → earlier, more frequent, usually colonoscopy (high-risk table below).
Step 7. Set the next interval by test, or by what the colonoscopy found (polyp surveillance is not screening).
Average-risk options and intervals
| Test | Interval | Strength | Catch |
|---|---|---|---|
| FIT (fecal immunochemical test) | Every year | Home test, no bowel prep; USMSTF tier 1 | Must repeat yearly |
| High-sensitivity guaiac FOBT | Every year | Home test | Must repeat yearly |
| Multitarget stool DNA (sDNA-FIT, eg, Cologuard) | Every 1-3 years (USPSTF); every 3 years (ACS, USMSTF) | More sensitive for cancer than FIT | Lower specificity: more false positives and follow-up colonoscopies |
| Multitarget stool RNA (mt-sRNA) | Every 3 years (ACS 2026) | FDA-approved 2024 for average risk, 45+ | Newer test |
| Colonoscopy | Every 10 years | Finds and removes polyps; USMSTF tier 1 | Bowel prep; rare bleeding or perforation |
| CT colonography | Every 5 years | Images the whole colon | Radiation, incidental extracolonic findings; polyps still need colonoscopy |
| Flexible sigmoidoscopy | Every 5 years (or every 10 + yearly FIT) | Direct look at the distal colon | Misses the proximal colon |
| Blood test (cell-free DNA, eg, Shield) | Not preferred (ACS 2026) | Simple blood draw | Misses most precancerous lesions |
Why blood tests are second-line: in the ECLIPSE trial of a cell-free DNA blood test (summarized by NCI), it detected 83% of cancers but only 13% of advanced precancerous lesions, so it does little to prevent cancer. The FDA approved Shield in July 2024 for average-risk adults aged 45 or older; the label says a positive result needs colonoscopy and the test does not replace surveillance colonoscopy in high-risk people. ACS lists blood tests only for people who decline or don't complete the preferred tests, and the USPSTF 2021 recommendation does not include serum tests.
The high-risk branch
| Situation | Start | Test and interval | Source |
|---|---|---|---|
| One FDR with CRC or advanced adenoma diagnosed <60, or 2+ FDRs at any age | Age 40 or 10 years before the youngest affected relative's diagnosis, whichever is earlier | Colonoscopy every 5 years | USMSTF 2017; ACG 2021 |
| One FDR diagnosed at ≥60 | Age 40 | Average-risk options and intervals | USMSTF 2017 |
| Ulcerative colitis (beyond proctitis) or Crohn colitis | About 8 years after disease onset | Surveillance colonoscopy every 1-5 years, set by risk | Merck |
| Colitis with primary sclerosing cholangitis | At diagnosis (don't wait 8 years) | Surveillance colonoscopy | Merck |
| Lynch syndrome | In the 20s | Colonoscopy every 1-2 years | Merck |
| FAP (relatives at risk) | Genetic testing; if unavailable, sigmoidoscopy from age 10-12 | Yearly; colectomy soon after diagnosis | Merck |
| Attenuated FAP | Late teens or early 20s | Colonoscopy every 1-2 years | Merck |
| Prior advanced adenoma (≥10 mm, villous, or high-grade dysplasia) | After polypectomy | Colonoscopy in 3 years (surveillance) | Merck |
FDR = first-degree relative (parent, sibling, child). Compare the two big syndromes in the Lynch vs FAP table and the FAP cheat sheet.
- Lynch syndrome: autosomal dominant DNA mismatch repair defect (MLH1, MSH2, MSH6, PMS2, EPCAM); 70-80% lifetime CRC risk, mostly proximal colon, cancers in the mid-40s; also endometrial and ovarian cancer.
- FAP: autosomal dominant APC mutation; ≥100 adenomas; cancer before 40 in nearly all untreated patients.
- IBD: Crohn colitis carries the same cancer risk as UC of the same extent and duration; isolated proctitis rarely needs surveillance. Review the Crohn vs UC breakdown.
What changed by October 2026
- USPSTF: no new final recommendation; the May 18, 2021 statement (screen at 45-75, selectively at 76-85) is current.
- ACS (May 27, 2026): start at 45, continue through 75 with life expectancy >10 years, individualize at 76-85, stop after 85; preferred tests are FIT or high-sensitivity gFOBT yearly, mt-sDNA or mt-sRNA every 3 years, colonoscopy every 10 years, CT colonography or sigmoidoscopy every 5 years; blood tests are an option only for people who decline or don't complete the preferred tests; positive stool or blood tests need colonoscopy, preferably within 6 months.
- FDA approvals in 2024: an mt-sRNA stool test (ColoSense, May), the Shield blood test (July) and a next-generation stool DNA test (Cologuard Plus, October).
- Exam framing: USMLE answers still hinge on 45, FIT yearly, colonoscopy every 10 years, positive test → colonoscopy, and the family-history rule.
Polyps: the Step 1 crossover
- Adenomatous polyps (tubular, tubulovillous, villous) are precursors; so are sessile serrated lesions (screening aims to remove both). Hyperplastic polyps are nonadenomatous.
- Advanced adenoma = ≥10 mm, villous histology or high-grade dysplasia: higher risk of progression, and it counts like cancer in an FDR's history.
- Large villous adenoma can cause secretory diarrhea and hypokalemia.
- Right-sided cancers often present with anemia and fatigue; left-sided cancers with obstruction or colicky pain; rectal cancers with bleeding at defecation.
Practice question
A 41-year-old man asks about colon cancer screening. His father was diagnosed with colorectal cancer at age 52; there is no other family history of cancer. He has no symptoms and has never been screened. Which recommendation is most appropriate?
A. Colonoscopy now, repeated every 5 years B. Annual FIT starting now C. Colonoscopy at age 45, repeated every 10 years D. Colonoscopy at age 42, repeated every 5 years E. Blood-based cell-free DNA test now, repeated every 3 years F. CT colonography at age 45, repeated every 5 years
Answer: A. A first-degree relative diagnosed before 60 means colonoscopy every 5 years starting at 40 or 10 years before the relative's diagnosis (42), whichever is earlier: 40. He is already 41, so he is due now.
- B: FIT is an average-risk strategy; this family history calls for colonoscopy.
- C: that is the average-risk schedule (start 45, every 10 years).
- D: 42 is "10 years before," but the rule takes whichever age is earlier.
- E: blood tests are approved for average-risk adults only, are not preferred even then, and miss most advanced precancerous lesions.
- F: CT colonography is an average-risk option; it does not replace colonoscopy in high-risk people.
Key takeaways
- Average risk: start at 45, screen through 75, individualize 76-85.
- FIT yearly, stool DNA every 1-3 years, CT colonography or sigmoidoscopy every 5, colonoscopy every 10.
- Any positive non-colonoscopy test → colonoscopy (ACS: preferably within 6 months after a positive stool or blood test).
- Symptoms = diagnostic colonoscopy, not screening.
- FDR with CRC or advanced adenoma <60 (or 2 FDRs): colonoscopy every 5 years from 40 or 10 years before the youngest diagnosis, whichever is earlier.
- IBD colitis: surveillance after ~8 years; PSC: from diagnosis. Lynch: colonoscopy every 1-2 years from the 20s. FAP: yearly sigmoidoscopy from 10-12, then colectomy.
- 2026: USPSTF unchanged since 2021; ACS added blood tests as a non-preferred option.
Sources
- Colorectal Cancer: Screening — U.S. Preventive Services Task Force final recommendation (2021)
- American Cancer Society Updates Colorectal Cancer Screening Guideline — ACS Pressroom (2026)
- American Cancer Society Guideline for Colorectal Cancer Screening — American Cancer Society (2026)
- Colorectal Cancer Screening: Recommendations for Physicians and Patients From the U.S. Multi-Society Task Force on Colorectal Cancer — Gastroenterology (2017)
- Updates on Age to Start and Stop Colorectal Cancer Screening: Recommendations From the U.S. Multi-Society Task Force on Colorectal Cancer — Gastroenterology (2022)
- Colorectal Cancer Screening — Merck Manual Professional Edition (2025)
- Colorectal Cancer Screening (PDQ), Health Professional Version — National Cancer Institute (2026)
- Shield premarket approval P230009 — U.S. Food and Drug Administration (2024)
- Ulcerative Colitis — Merck Manual Professional Edition (2026)
- Lynch Syndrome — Merck Manual Professional Edition (2025)
- Familial Adenomatous Polyposis — Merck Manual Professional Edition (2025)
- Polyps of the Colon and Rectum — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
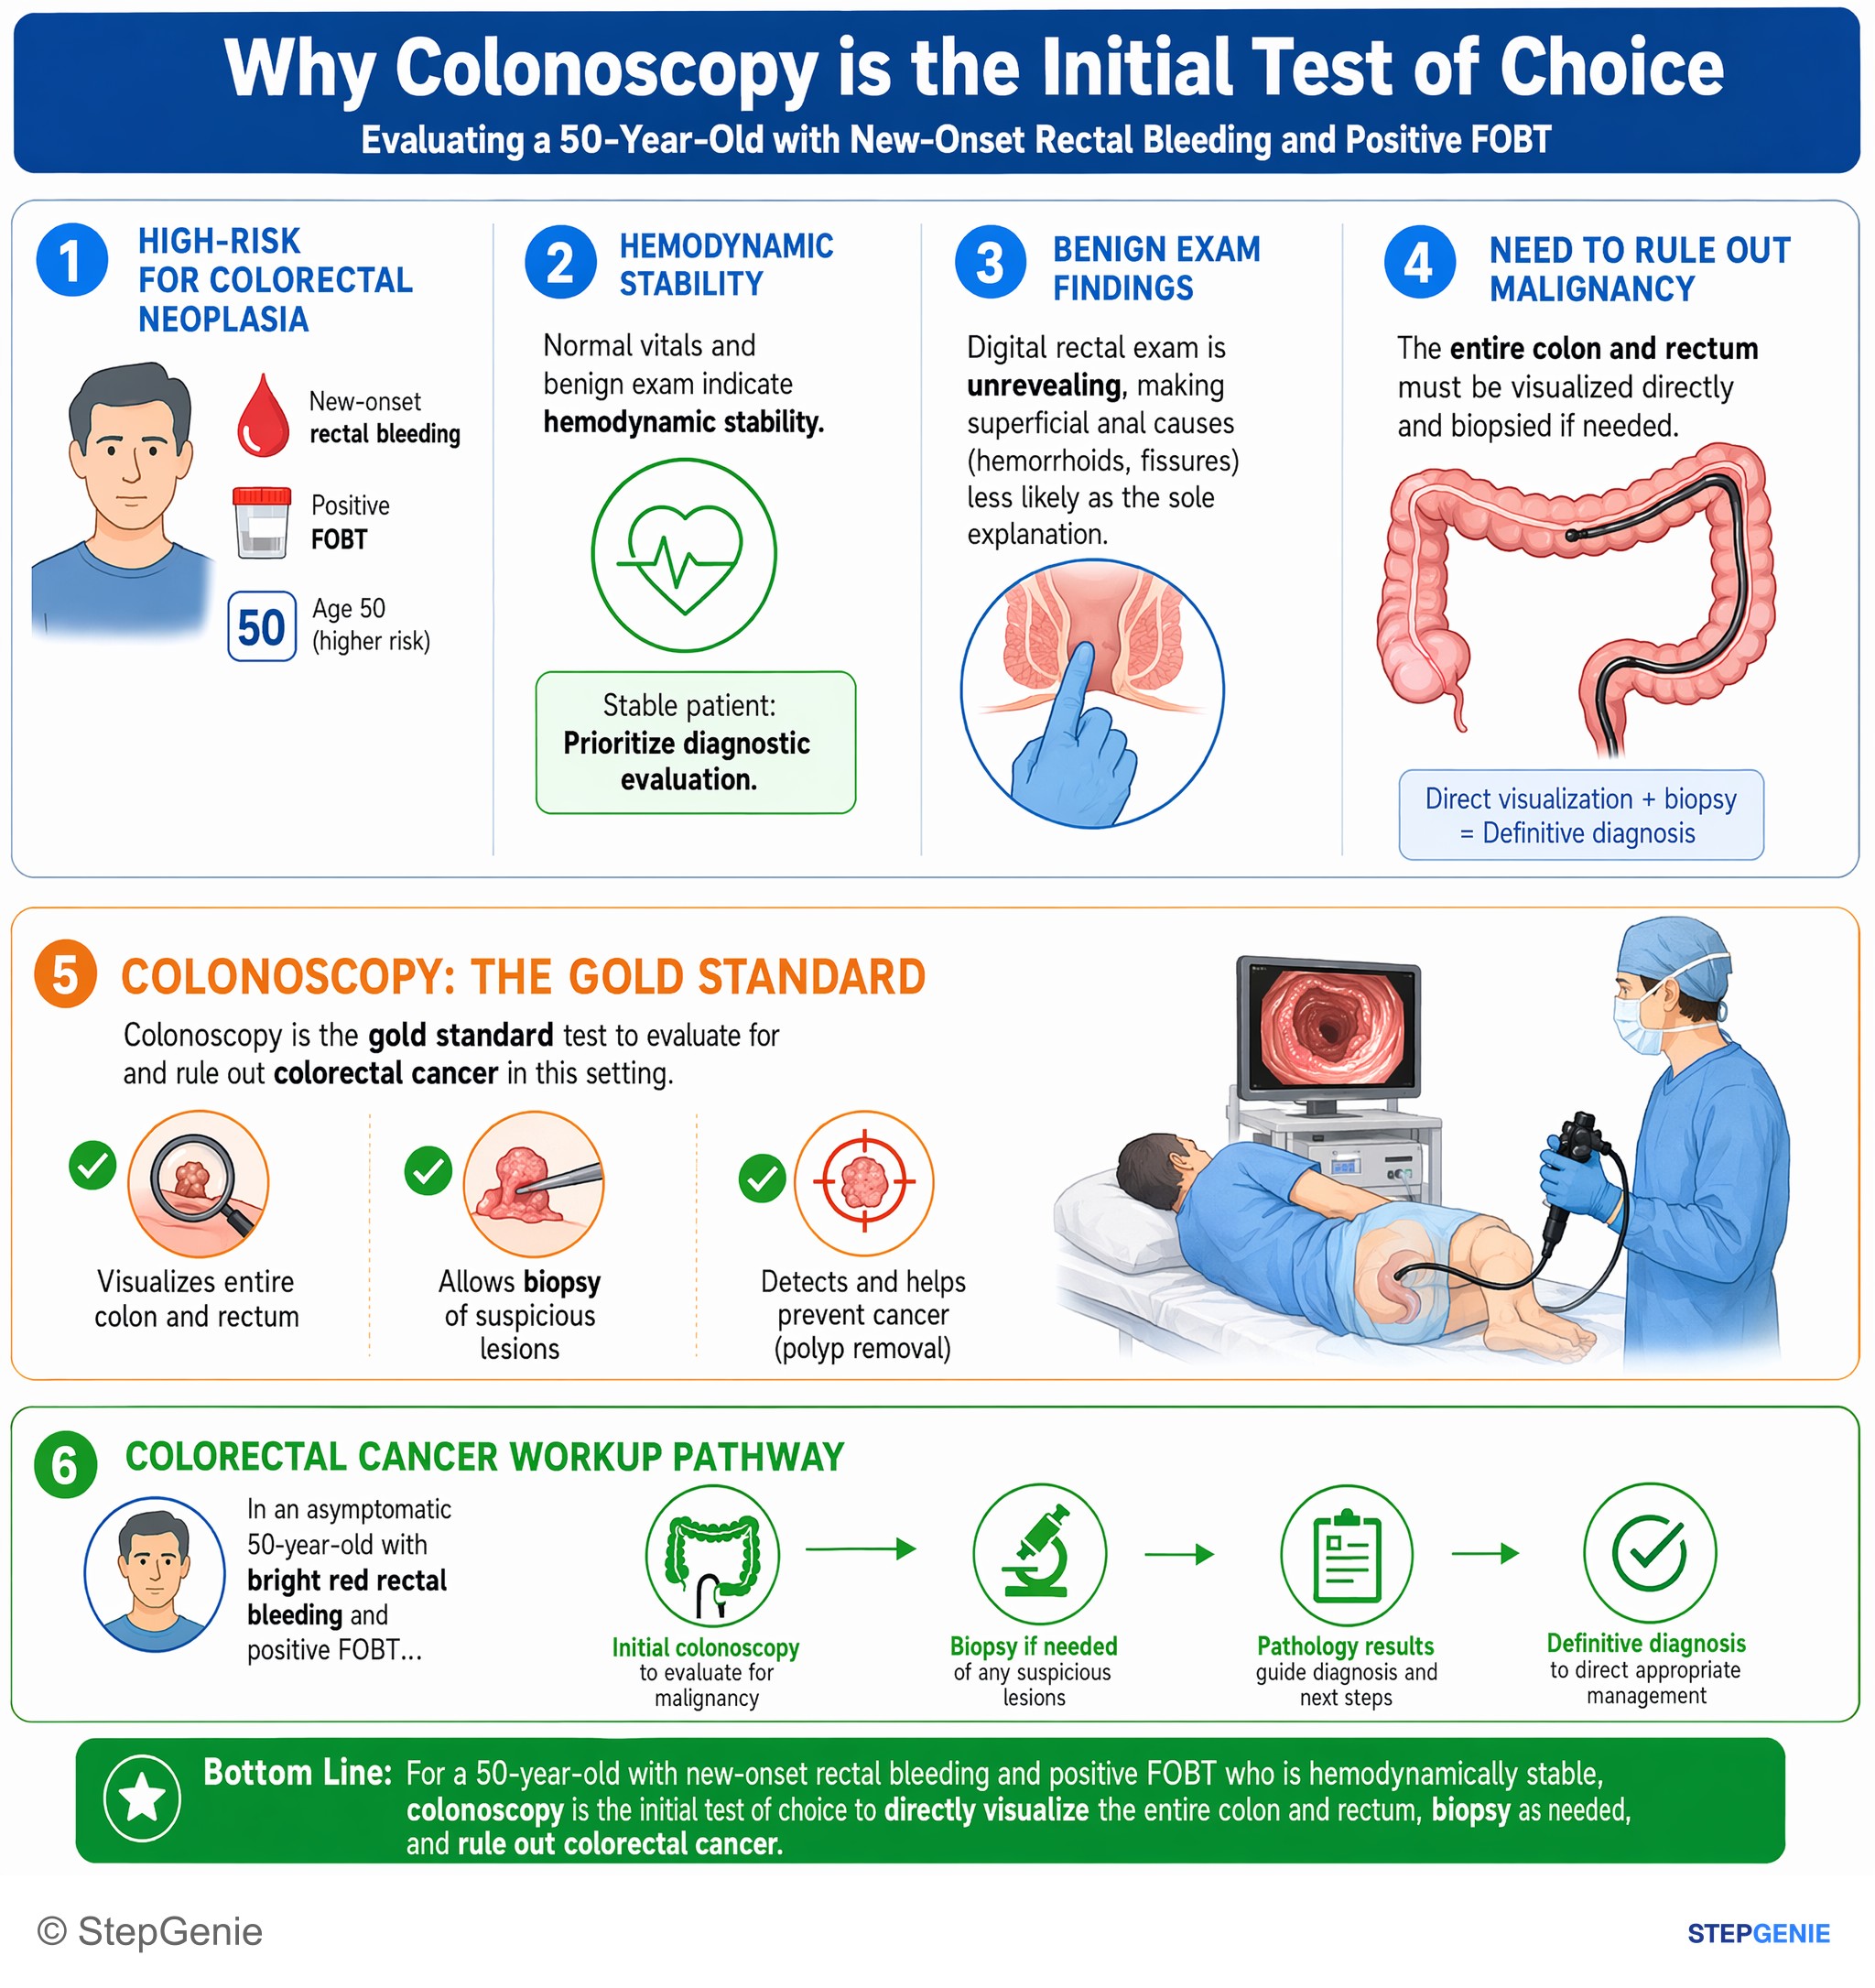
Colorectal cancer workup in an asymptomatic 50-year-old with bright red rectal bleeding and positive FOBT requires initial colonoscopy to…
USMLE Step 2Frequently Asked Questions
At what age should colorectal cancer screening start?
Adults at average risk should start at age 45. The USPSTF (2021) gives screening a grade B recommendation at ages 45 to 49 and a grade A recommendation at 50 to 75. From 76 to 85 the decision is individual, based on health, life expectancy, prior screening and preference. The American Cancer Society (2026) and the US Multi-Society Task Force advise against screening after 85. People with a strong family history, IBD or a hereditary syndrome start earlier.
How often do you need a FIT, stool DNA test or colonoscopy?
FIT and high-sensitivity guaiac stool tests are done every year. The multitarget stool DNA test is repeated every 1 to 3 years according to the USPSTF, or every 3 years according to the American Cancer Society. CT colonography and flexible sigmoidoscopy are repeated every 5 years, and a normal colonoscopy every 10 years in average-risk adults. Any positive result from a test other than colonoscopy must be followed by a colonoscopy.
What should happen after a positive FIT or Cologuard test?
A positive stool test (FIT, guaiac test or stool DNA test), blood test, CT colonography or sigmoidoscopy should be followed by colonoscopy. After a positive stool or blood test, the American Cancer Society says the colonoscopy should preferably happen within 6 months. Do not repeat the stool test to confirm it and do not jump to staging scans. The USPSTF stresses that screening only delivers its benefit when abnormal results are followed through to colonoscopy.
When should screening start if a parent had colon cancer?
If a first-degree relative (parent, sibling or child) had colorectal cancer or an advanced adenoma diagnosed before age 60, or two first-degree relatives were affected at any age, the US Multi-Society Task Force recommends colonoscopy every 5 years starting at age 40 or 10 years before the youngest relative's diagnosis, whichever is earlier. With a single relative diagnosed at 60 or older, start average-risk screening at age 40.
Is a blood test like Shield an acceptable colon cancer screening test?
The FDA approved the Shield cell-free DNA blood test in 2024 for average-risk adults aged 45 and older. The American Cancer Society's May 2026 guideline lists blood tests only for people who decline or don't complete the preferred stool tests or visual exams, because they are less sensitive than stool tests for precancerous lesions and early cancers. In the ECLIPSE trial, a cell-free DNA blood test found about 83% of cancers but only 13% of advanced precancerous lesions. The 2021 USPSTF recommendation does not include blood tests. A positive result needs colonoscopy.
When do people with IBD, Lynch syndrome or FAP need colonoscopy?
Patients with ulcerative colitis beyond the rectum or Crohn colitis start surveillance colonoscopy about 8 years after disease onset, repeated every 1 to 5 years depending on risk; patients with primary sclerosing cholangitis start at diagnosis. Lynch syndrome carriers need colonoscopy every 1 to 2 years starting in their 20s. Relatives at risk for FAP get genetic testing or, if unavailable, yearly sigmoidoscopy from age 10 to 12, and colectomy soon after diagnosis.