Small bowel obstruction (SBO) is one of those “classic” GI presentations where USMLE questions test not just recognition—but triage, imaging choices, and the ability to separate mechanical obstruction from ileus and ischemia. The trick is that the distractors often represent real diagnoses with overlapping symptoms. If you learn to make each answer choice “earn” its spot, your accuracy (and speed) jumps.
Tag: GI > Intestinal Disorders
The Clinical Vignette (Q-bank style)
A 58-year-old man presents with 24 hours of crampy abdominal pain, progressive abdominal distension, nausea, and multiple episodes of bilious vomiting. He has not passed flatus since yesterday. He had an open appendectomy 10 years ago. Vitals: T 37.2°C, HR 104, BP 122/76. Exam: distended abdomen with diffuse tenderness, no rebound. Bowel sounds are high-pitched and “tinkling.” Labs show mild hypokalemia. Upright abdominal radiograph demonstrates multiple dilated loops of small bowel with air–fluid levels and paucity of gas in the colon.
Question: What is the most likely cause of his condition?
Answer choices:
A. Postoperative adhesions
B. Volvulus of the sigmoid colon
C. Acute pancreatitis
D. Incarcerated femoral hernia
E. Mesenteric ischemia
Stepwise Approach (How to think like the test-writer)
1) Is this obstruction, ileus, or something else?
Clues favoring mechanical SBO:
- Crampy (colicky) abdominal pain
- High-pitched/tinkling bowel sounds (early)
- Bilious vomiting (proximal obstruction)
- Obstipation (no flatus/stool) suggests complete obstruction
- X-ray: dilated small bowel loops + air–fluid levels + minimal colonic gas
2) What’s the most common cause in adults?
In the US, the most common cause of SBO in adults is postoperative adhesions.
The Correct Answer: A. Postoperative adhesions
Why it fits best
- Prior abdominal surgery is the biggest giveaway (appendectomy counts—any laparotomy can seed adhesions).
- Adhesions cause extrinsic compression or kinking of small bowel → mechanical obstruction.
- Imaging described is highly consistent with SBO.
High-yield facts (USMLE favorites)
- Most common causes of SBO in adults (rough order):
- Adhesions (most common overall)
- Hernias (especially if no prior surgery)
- Tumors (more common in large bowel obstruction, but can cause SBO)
- Air–fluid levels and dilated small bowel on upright films are classic.
- Small bowel diameter is often remembered as abnormal when >3 cm (rule-of-thumb).
Now, Why Each Distractor Matters
B. Volvulus of the sigmoid colon
Why it’s tempting: distension + obstruction picture.
Why it’s wrong here:
- Sigmoid volvulus causes a large bowel obstruction (LBO) pattern.
- Imaging classically shows a “coffee bean” sign (massively dilated colon) and often colonic dilation proximal to the twist.
- Symptoms can include constipation/obstipation, but vomiting is typically later than in SBO.
High-yield compare/contrast
- SBO: early vomiting, central abdominal distension, dilated small bowel, paucity of colonic gas
- LBO (sigmoid volvulus): more marked abdominal distension, later vomiting, dilated colon
C. Acute pancreatitis
Why it’s tempting: nausea/vomiting and abdominal pain.
Why it’s wrong here:
- Pancreatitis pain is classically epigastric, may radiate to the back, and is often constant (not colicky).
- Pancreatitis can cause a paralytic ileus, but ileus is functional, not mechanical—bowel sounds are typically decreased, and imaging shows diffuse bowel dilation (small and large), not the classic SBO pattern.
High-yield hook:
- Sentinel loop (localized ileus) can occur near an inflamed pancreas, but this vignette describes multiple dilated small bowel loops and tinkling sounds → mechanical SBO.
D. Incarcerated femoral hernia
Why it’s tempting: hernias are a major SBO cause.
Why it’s wrong in this vignette:
- The case gives a strong alternative cause—prior abdominal surgery, pointing to adhesions as most likely.
- Also, the stem doesn’t mention a groin mass or localized groin pain.
But don’t ignore it clinically:
Hernias are a high-yield SBO cause—especially in patients without prior surgery (“virgin abdomen”).
Femoral hernia pearls (USMLE):
- More common in women
- Higher risk of incarceration/strangulation than inguinal hernias
- Located below the inguinal ligament and medial to the femoral vein
E. Mesenteric ischemia
Why it’s tempting: tachycardia and abdominal pain can raise concern for ischemia.
Why it’s wrong here:
- Mesenteric ischemia presents with pain out of proportion to exam findings, often with metabolic acidosis (elevated lactate).
- It is not primarily an “air–fluid levels SBO” diagnosis—though late ischemia can lead to ileus and peritonitis.
- This stem emphasizes mechanical obstruction features (tinkling sounds, prior surgery, SBO radiograph pattern).
High-yield ischemia red flags:
- Severe abdominal pain + relatively benign early exam
- Atrial fibrillation or embolic risk (acute arterial occlusion)
- Postprandial pain + weight loss (chronic mesenteric ischemia)
- Bloody diarrhea can occur (especially with ischemic colitis)
Key Imaging & Management: What Step 1 vs Step 2 loves
Imaging quick hits
| Scenario | Best next step (typical) | What you’re looking for |
|---|---|---|
| Suspected SBO, stable | CT abdomen/pelvis with IV contrast | Transition point, cause, complications (ischemia/perforation) |
| Initial quick screen | Upright abdominal X-ray | Air–fluid levels, dilated small bowel, low colonic gas |
| Concern for strangulation/ischemia | CT with IV contrast (urgent) | Bowel wall thickening, pneumatosis, portal venous gas, reduced enhancement |
Management framework (high yield)
First steps (most uncomplicated SBO):
- NPO
- IV fluids + electrolyte correction (hypokalemia is common from vomiting)
- NG tube decompression if significant vomiting/distension
- Serial abdominal exams
When to call surgery emergently Think strangulation or perforation:
- Fever, leukocytosis
- Continuous (not colicky) severe pain
- Peritoneal signs (rebound/guarding)
- Tachycardia/hypotension
- Metabolic acidosis / elevated lactate
- CT signs of ischemia (pneumatosis, poor enhancement)
Rapid-Fire High-Yield Takeaways (the “why every choice matters” version)
- SBO = adhesions until proven otherwise (especially with prior surgery).
- Hernia is the big alternative, especially in a virgin abdomen—always examine the groin.
- Tinkling/high-pitched bowel sounds suggest mechanical obstruction (early); ileus tends toward hypoactive sounds.
- Early vomiting points more toward SBO; later vomiting can be LBO.
- Red flags for ischemia/strangulation change management from conservative to urgent surgery.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
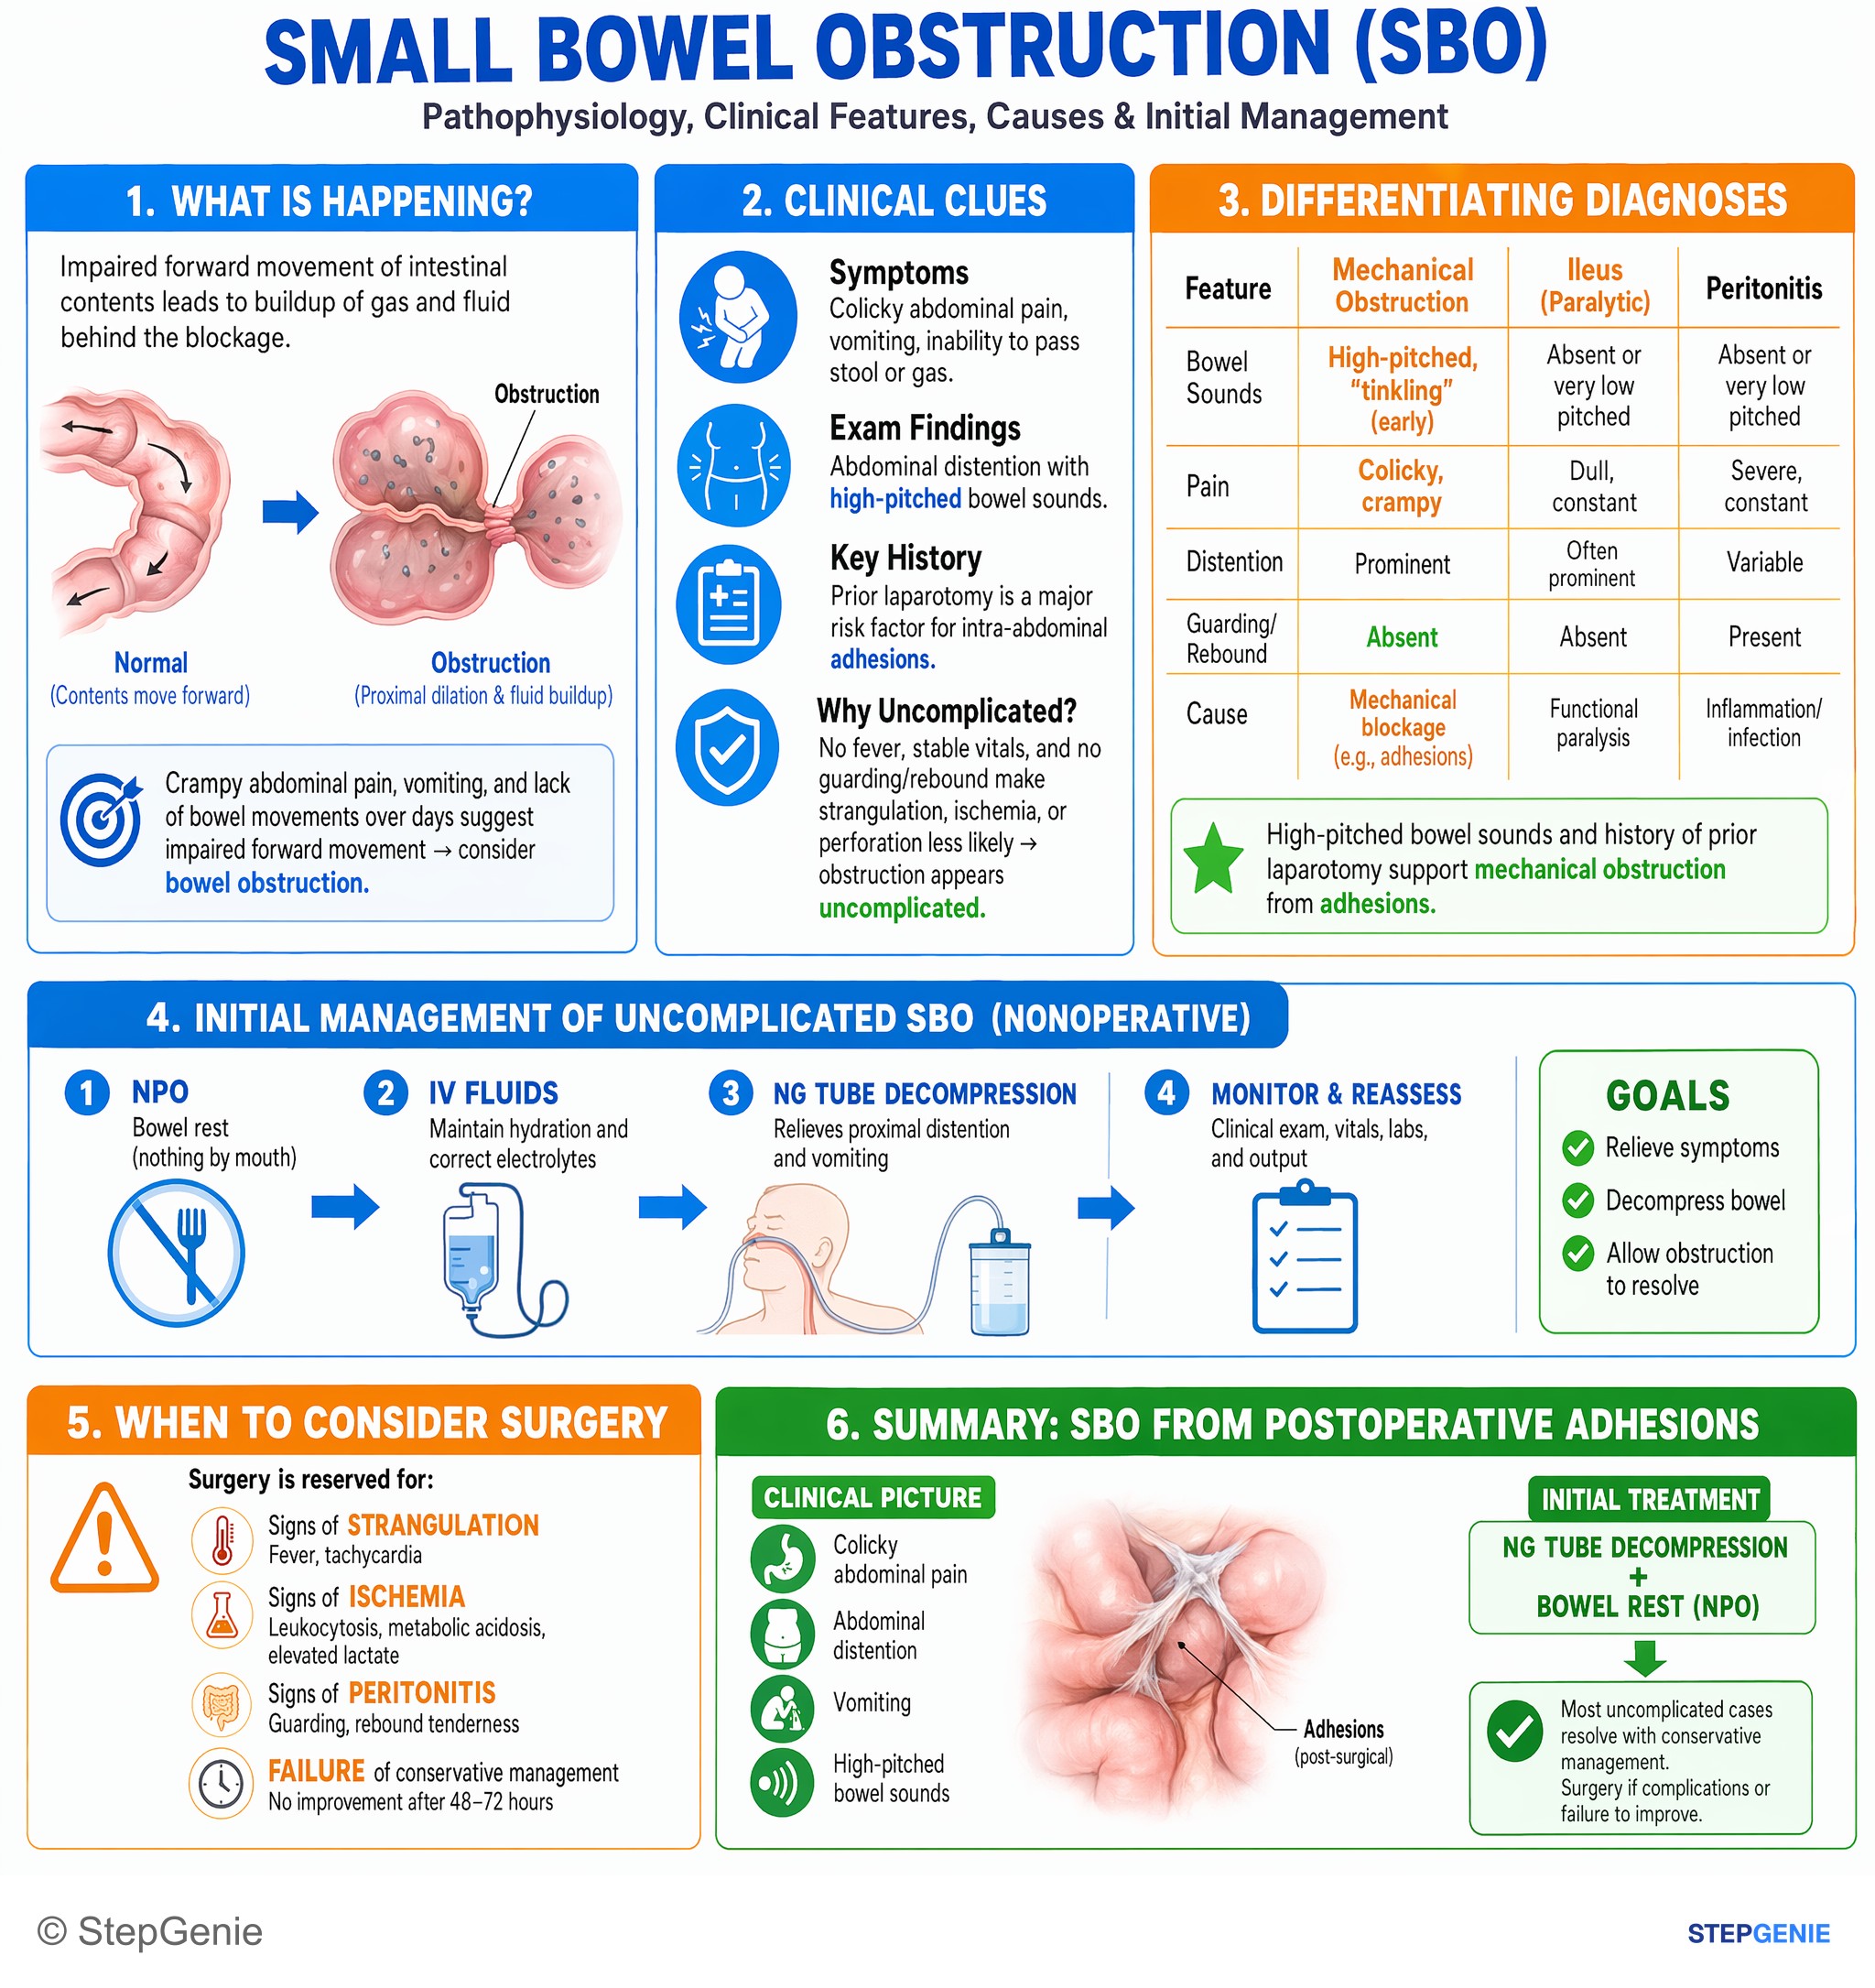
Small bowel obstruction from postoperative adhesions: colicky pain, distention, vomiting, high-pitched sounds → treat initially with NG…
USMLE Step 2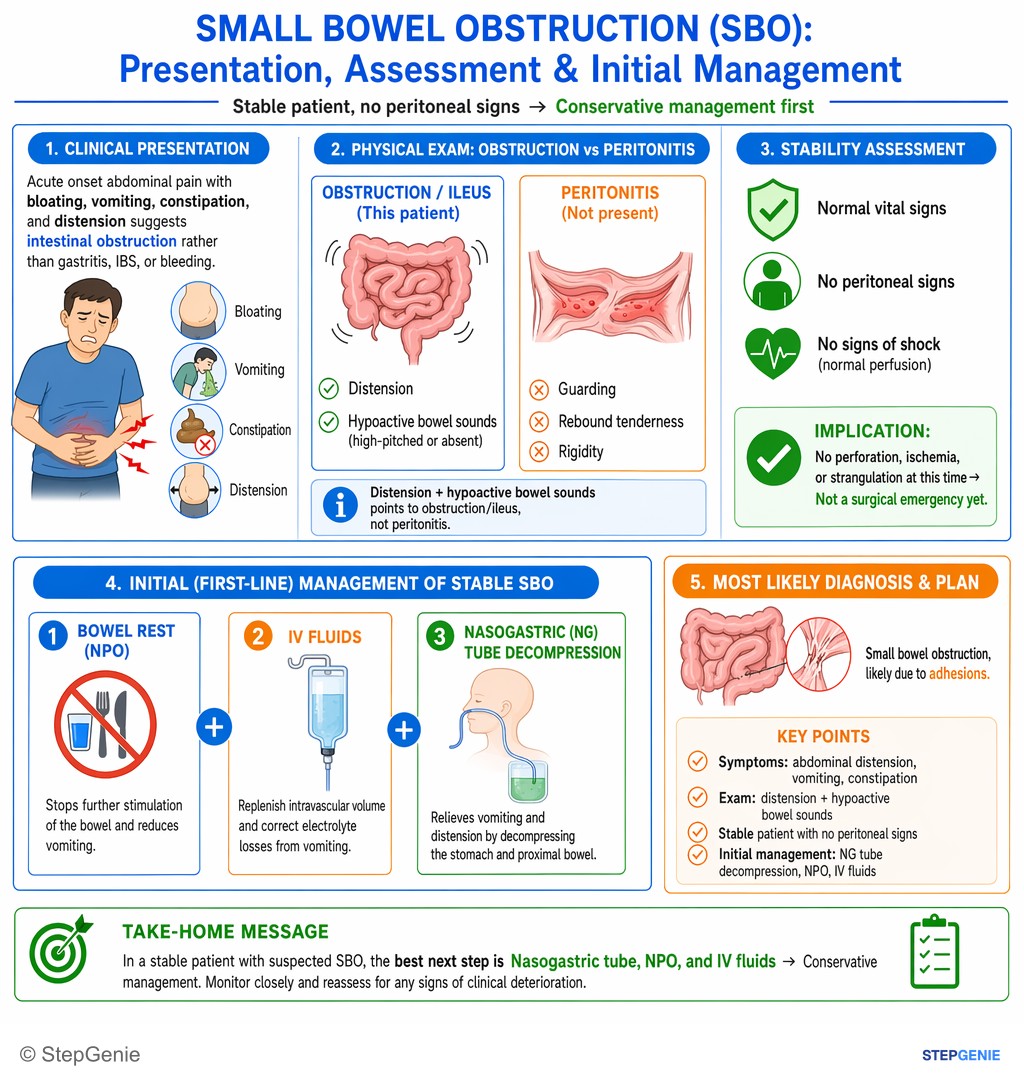
Small bowel obstruction from likely adhesions: abdominal distension, vomiting, constipation → initial management is NG tube decompression…
USMLE Step 2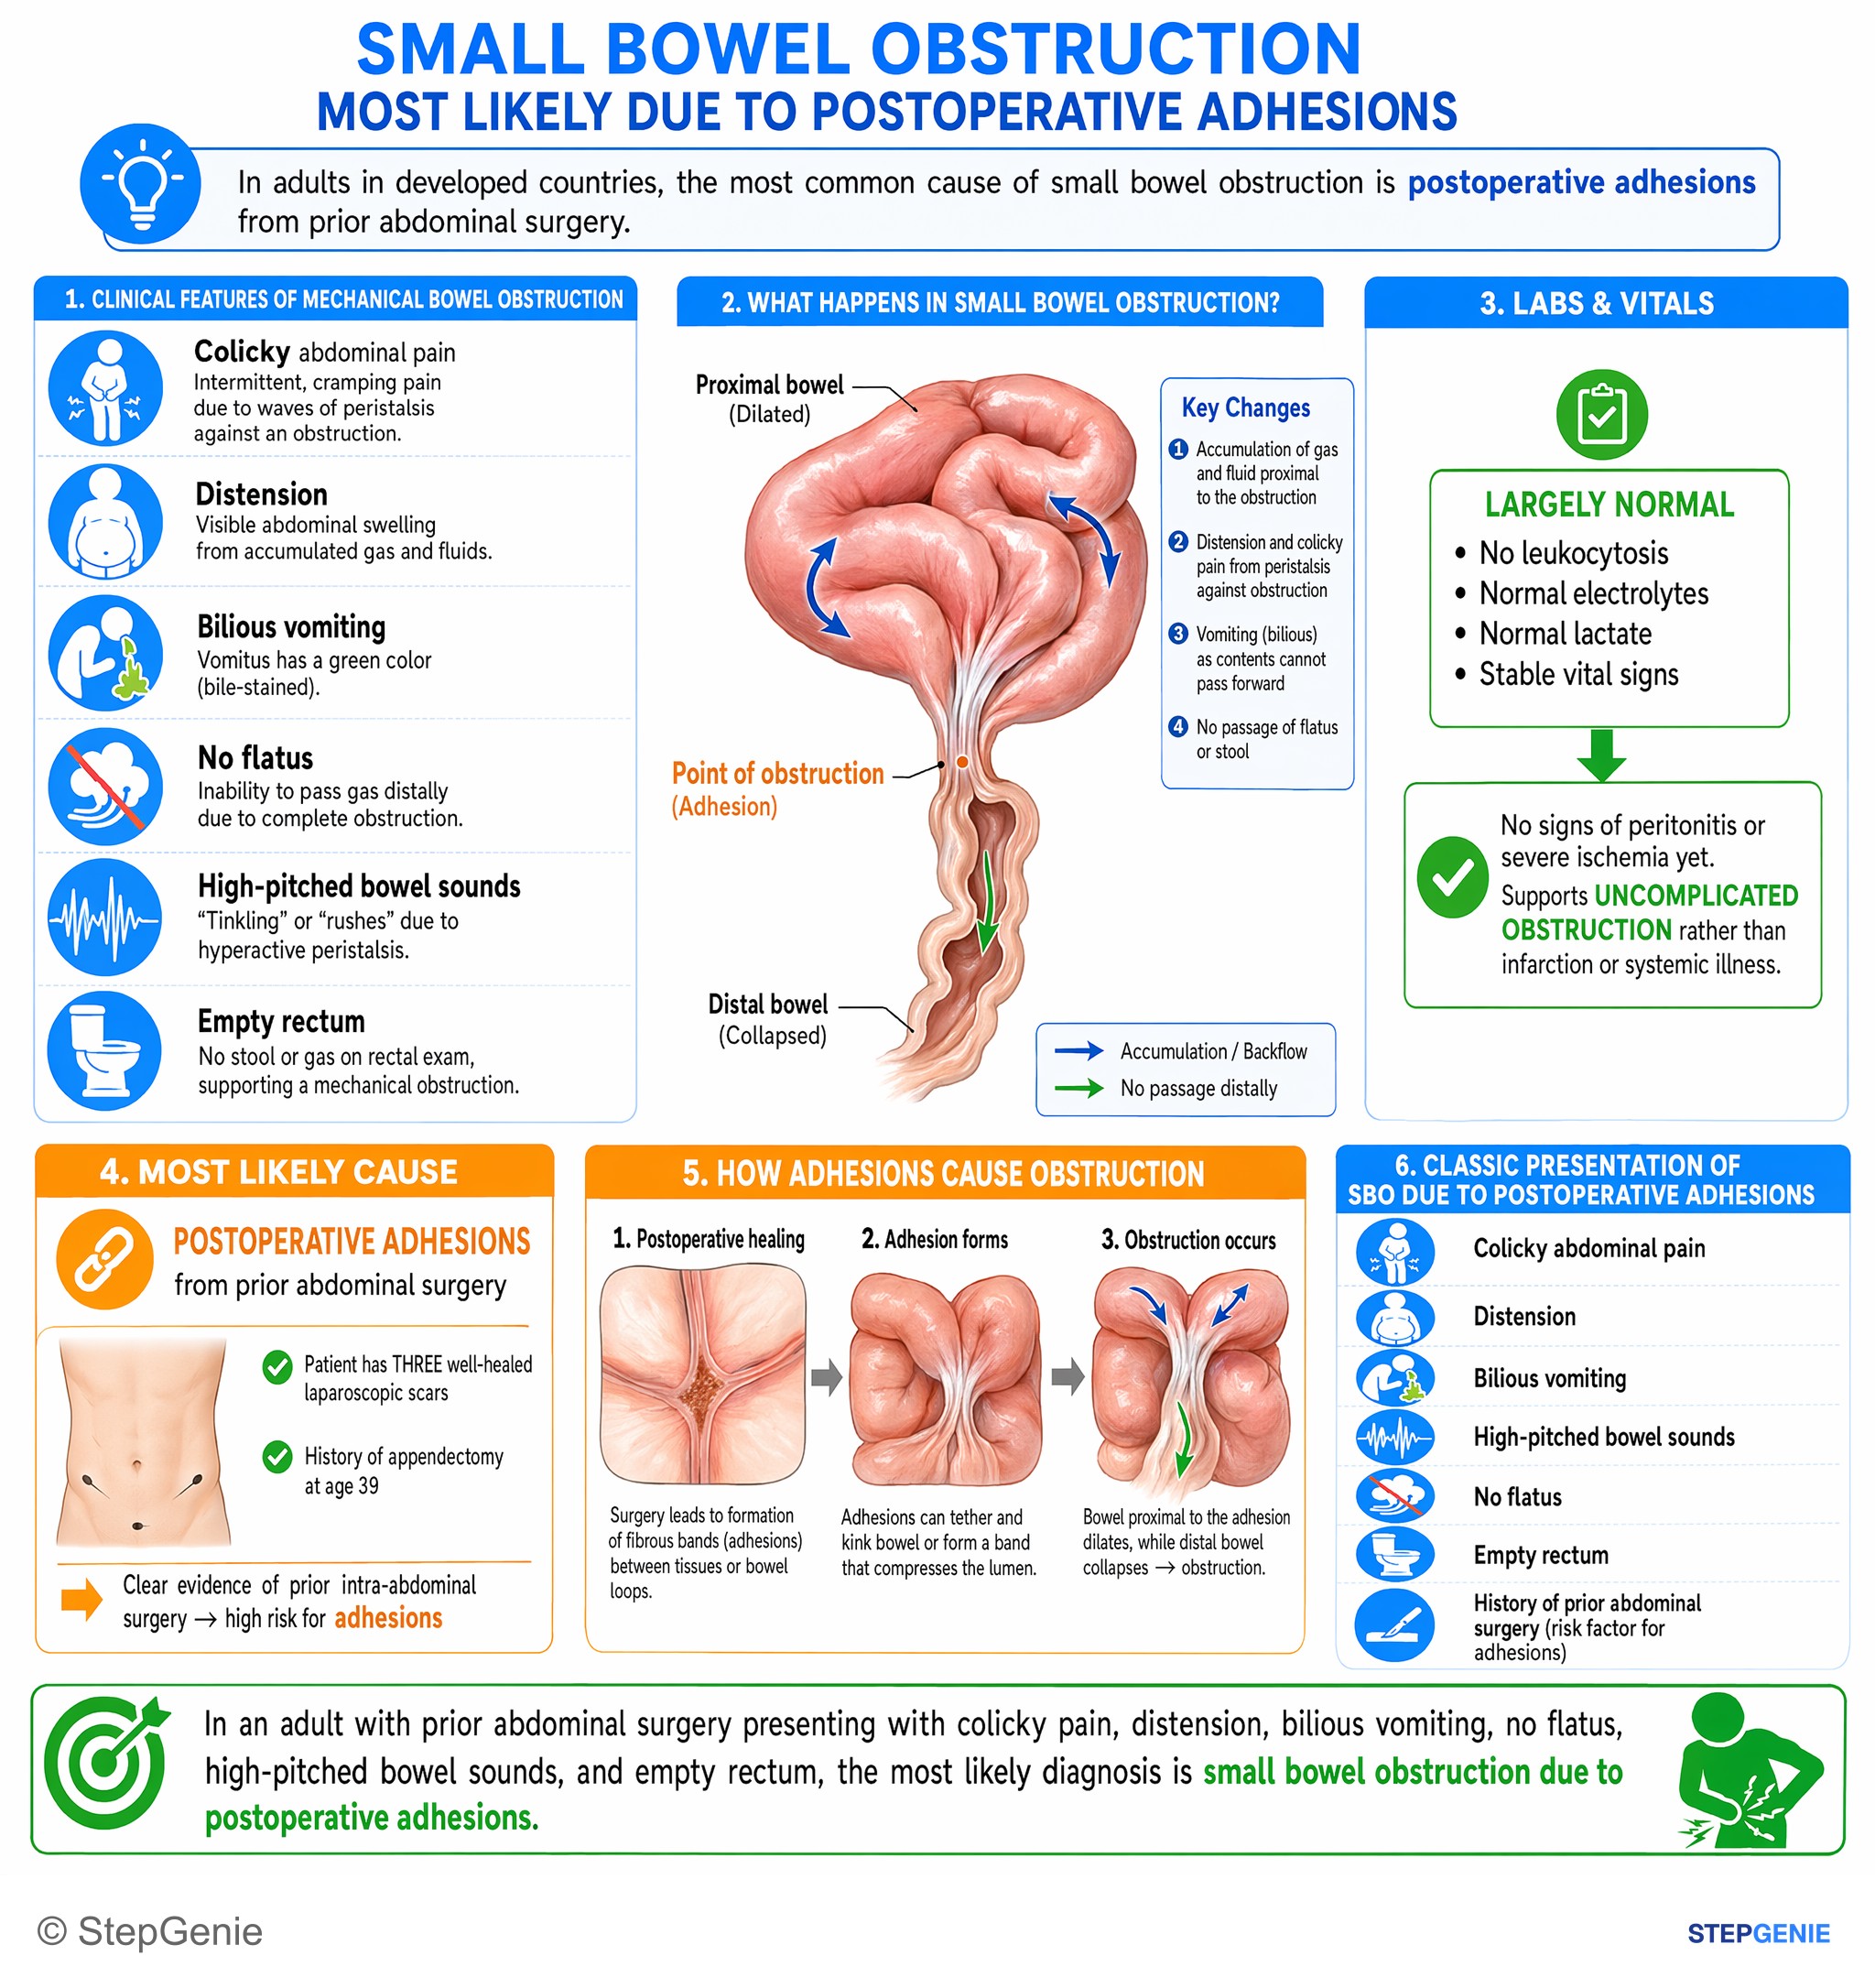
Small bowel obstruction from postoperative adhesions presents with colicky pain, distension, bilious vomiting, high-pitched bowel sounds…
USMLE Step 2Frequently Asked Questions
What is the most common cause of small bowel obstruction in adults?
Postoperative adhesions are the most common cause of small bowel obstruction in adults in the United States. Prior abdominal surgery is a major clue because any laparotomy, including an appendectomy, can lead to adhesions that kink or externally compress the small bowel and produce a mechanical obstruction pattern.
How do you tell mechanical small bowel obstruction from ileus on exam and imaging?
Mechanical small bowel obstruction is suggested by crampy colicky pain, high-pitched or tinkling bowel sounds, bilious vomiting, obstipation, and radiographs showing dilated small bowel loops with air–fluid levels and little colonic gas. Ileus is functional rather than mechanical, usually has decreased bowel sounds, and tends to cause diffuse dilation of both small and large bowel instead of the classic SBO pattern.
How do you tell small bowel obstruction from sigmoid volvulus on a test question?
Small bowel obstruction usually causes earlier vomiting, central abdominal distension, dilated small bowel, and paucity of colonic gas. Sigmoid volvulus is a large bowel obstruction pattern, with more marked abdominal distension, vomiting that tends to occur later, and imaging that classically shows a massively dilated colon with a coffee bean sign.
When should you think hernia instead of adhesions as the cause of small bowel obstruction?
You should think more strongly about hernia when a patient has small bowel obstruction without prior abdominal surgery. Hernias are a major cause of SBO, but a history of previous laparotomy makes adhesions the most likely cause. Exam clues that would support hernia include a groin mass or localized groin pain, which are not present in the vignette described.
What imaging test is usually the best next step if you suspect small bowel obstruction and the patient is stable?
CT abdomen and pelvis with IV contrast is typically the best next step in a stable patient with suspected small bowel obstruction. It helps identify the transition point, the underlying cause, and complications such as ischemia or perforation. An upright abdominal X-ray can be a quick initial screen for air–fluid levels, dilated small bowel, and low colonic gas.