Irritable bowel syndrome (IBS) is one of those Step “gotcha” diagnoses: the stem feels like inflammatory bowel disease (IBD) or infection, but the absence of red flags and the pattern of pain related to defecation quietly points you to a functional disorder. The trick is that on USMLE, you’re not just picking the right answer—you’re proving why every other answer is wrong.
Tag: GI > Intestinal Disorders
The Clinical Vignette (Q-bank style)
A 28-year-old woman comes to clinic for 8 months of intermittent crampy lower abdominal pain. The pain occurs at least 1 day per week and is often relieved after a bowel movement. She reports alternating episodes of diarrhea and constipation. She feels bloated and says her stools sometimes look “mucusy,” but she denies blood in the stool. No fever, nighttime symptoms, or unintentional weight loss. She has no family history of colon cancer or IBD. Exam is normal. Basic labs including CBC and CRP are normal.
Which of the following is the most likely diagnosis?
A. Crohn disease
B. Ulcerative colitis
C. Irritable bowel syndrome
D. Celiac disease
E. Colon cancer
F. Lactose intolerance
G. Microscopic colitis
Correct Answer: C. Irritable Bowel Syndrome
Why this is IBS (and why Step loves it)
IBS is a functional bowel disorder defined by recurrent abdominal pain plus bowel habit changes, without structural disease.
High-yield diagnostic anchor: Rome IV criteria (USMLE-friendly version)
Recurrent abdominal pain on average ≥ 1 day/week in the last 3 months, associated with ≥ 2 of:
- Related to defecation (often improves after BM)
- Change in stool frequency
- Change in stool form
Supportive clues in this vignette:
- Alternating constipation and diarrhea (IBS-M, mixed type)
- Bloating and mucus in stool can occur in IBS
- Normal CBC/CRP, benign exam
- No alarm features (see below)
Alarm features (red flags) that argue against IBS
If these show up, you should think “not IBS until proven otherwise,” and often pursue colonoscopy and further workup:
- GI bleeding (hematochezia, melena) or iron-deficiency anemia
- Nocturnal diarrhea/pain waking from sleep
- Unintentional weight loss, fever
- Family history of colon cancer or IBD
- New onset after age 50 (varies by guideline, but Step uses older age as concerning)
- Elevated inflammatory markers (CRP/ESR), abnormal fecal calprotectin
Management (high yield)
First-line is symptom-targeted:
- Diet: Low FODMAP, trigger avoidance; soluble fiber (psyllium) helps some patients
- IBS-D: loperamide (diarrhea), bile acid binders in select cases; rifaximin or eluxadoline sometimes
- IBS-C: polyethylene glycol; secretagogues (lubiprostone, linaclotide)
- Pain/bloating: antispasmodics; low-dose TCAs (IBS-D) or SSRIs (IBS-C, comorbid anxiety/depression)
- Psych: gut–brain axis is real—stress management, CBT can improve symptoms
Key Step point: IBS is not a diagnosis of exclusion if the presentation fits and there are no alarm features, but you should still consider minimal screening labs depending on the stem (CBC, CRP, celiac serologies).
Why Each Distractor Is Wrong (and how to spot it fast)
A. Crohn disease
Why it tempts you: abdominal pain + diarrhea in a young adult.
Why it’s wrong here:
- Crohn is inflammatory, so you expect red flags: weight loss, fever, fatigue, anemia
- Often non-bloody diarrhea, but commonly has elevated CRP/ESR, possible perianal disease
- May have nocturnal symptoms
- Extraintestinal manifestations (uveitis, erythema nodosum, arthritis) may show up
Classic Crohn clues (memorize):
- “Skip lesions,” transmural inflammation → fistulas, strictures
- Terminal ileum involvement → B12 deficiency, bile acid diarrhea
- Cobblestoning on endoscopy, creeping fat on imaging
B. Ulcerative colitis
Why it tempts you: bowel habit changes, cramps.
Why it’s wrong here:
- UC classically causes bloody diarrhea and urgency/tenesmus
- Inflammation is continuous starting at the rectum
- Labs may show anemia, elevated inflammatory markers in active disease
Classic UC clues:
- Mucosal/submucosal inflammation
- Pseudopolyps
- Primary sclerosing cholangitis association
- Toxic megacolon risk
USMLE shortcut: Blood + urgency + continuous disease = UC.
D. Celiac disease
Why it tempts you: diarrhea, bloating.
Why it’s wrong here:
- Celiac typically causes chronic diarrhea, steatorrhea, weight loss, iron deficiency anemia, dermatitis herpetiformis
- Less likely to present as alternating diarrhea/constipation with pain relieved by BM
- Often has nutritional deficiencies (iron, folate), abnormal serologies
High-yield:
- IgA anti–tissue transglutaminase (tTG) and total IgA level
- Biopsy: villous atrophy, crypt hyperplasia, intraepithelial lymphocytes
- Associated with HLA-DQ2/DQ8
E. Colon cancer
Why it tempts you: change in bowel habits.
Why it’s wrong here:
- Age is young and there are no alarm symptoms (blood, weight loss, anemia)
- Colon cancer typically shows occult bleeding → iron deficiency anemia, or overt hematochezia (distal), plus progressive symptoms
High-yield patterns:
- Right-sided: occult bleeding, anemia
- Left-sided: obstructive symptoms, “pencil-thin” stools (classic teaching), hematochezia
Step reminder: IBS does not cause anemia.
F. Lactose intolerance
Why it tempts you: bloating + diarrhea.
Why it’s wrong here:
- Symptoms occur after lactose ingestion, improve with avoidance
- Typically watery diarrhea, gas, bloating—not chronic recurrent abdominal pain meeting Rome criteria with alternating constipation
High-yield test:
- Hydrogen breath test (↑ hydrogen due to colonic bacterial fermentation)
Clue to pick lactose intolerance: “Every time I drink milk/ice cream…”
G. Microscopic colitis
Why it tempts you: chronic diarrhea with normal labs/exam.
Why it’s wrong here:
- Typically watery, non-bloody diarrhea that can be persistent and may occur at night
- More common in older adults, often associated with medications (NSAIDs, PPIs, SSRIs) and autoimmune disease
- Diagnosis requires colon biopsy—gross colonoscopy may look normal
High-yield pathology:
- Collagenous colitis: thickened subepithelial collagen band
- Lymphocytic colitis: increased intraepithelial lymphocytes
How to Lock IBS in Under Exam Pressure
3-step mental checklist
- Does the pain relate to bowel movements? (improves or worsens with defecation)
- Is there a pattern change in stool frequency/form? (diarrhea, constipation, or both)
- Any alarm features? If no → IBS rises to the top.
Mini-table: IBS vs IBD vs Infection
| Feature | IBS | IBD (Crohn/UC) | Infectious colitis |
|---|---|---|---|
| Inflammation markers (CRP/ESR) | Normal | Often elevated | Often elevated |
| Blood in stool | No (not typical) | Common (especially UC) | Possible |
| Nocturnal symptoms | Uncommon | Can occur | Can occur |
| Weight loss/fever | No | Possible/common | Possible |
| Colonoscopy | Normal | Abnormal | May show colitis depending on organism |
High-Yield Pearls You’ll Actually Use on Step
- IBS = pain + bowel habit change + no red flags.
- Mucus in stool can occur in IBS; blood is a red flag until proven otherwise.
- Normal CRP (and/or low fecal calprotectin) supports IBS over IBD in question stems.
- Rome IV is the framework: recurrent pain ≥ 1 day/week, plus stool changes/defecation association.
- Always scan for alarm features—they’re the test writer’s way of telling you to leave IBS and pursue organic disease.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
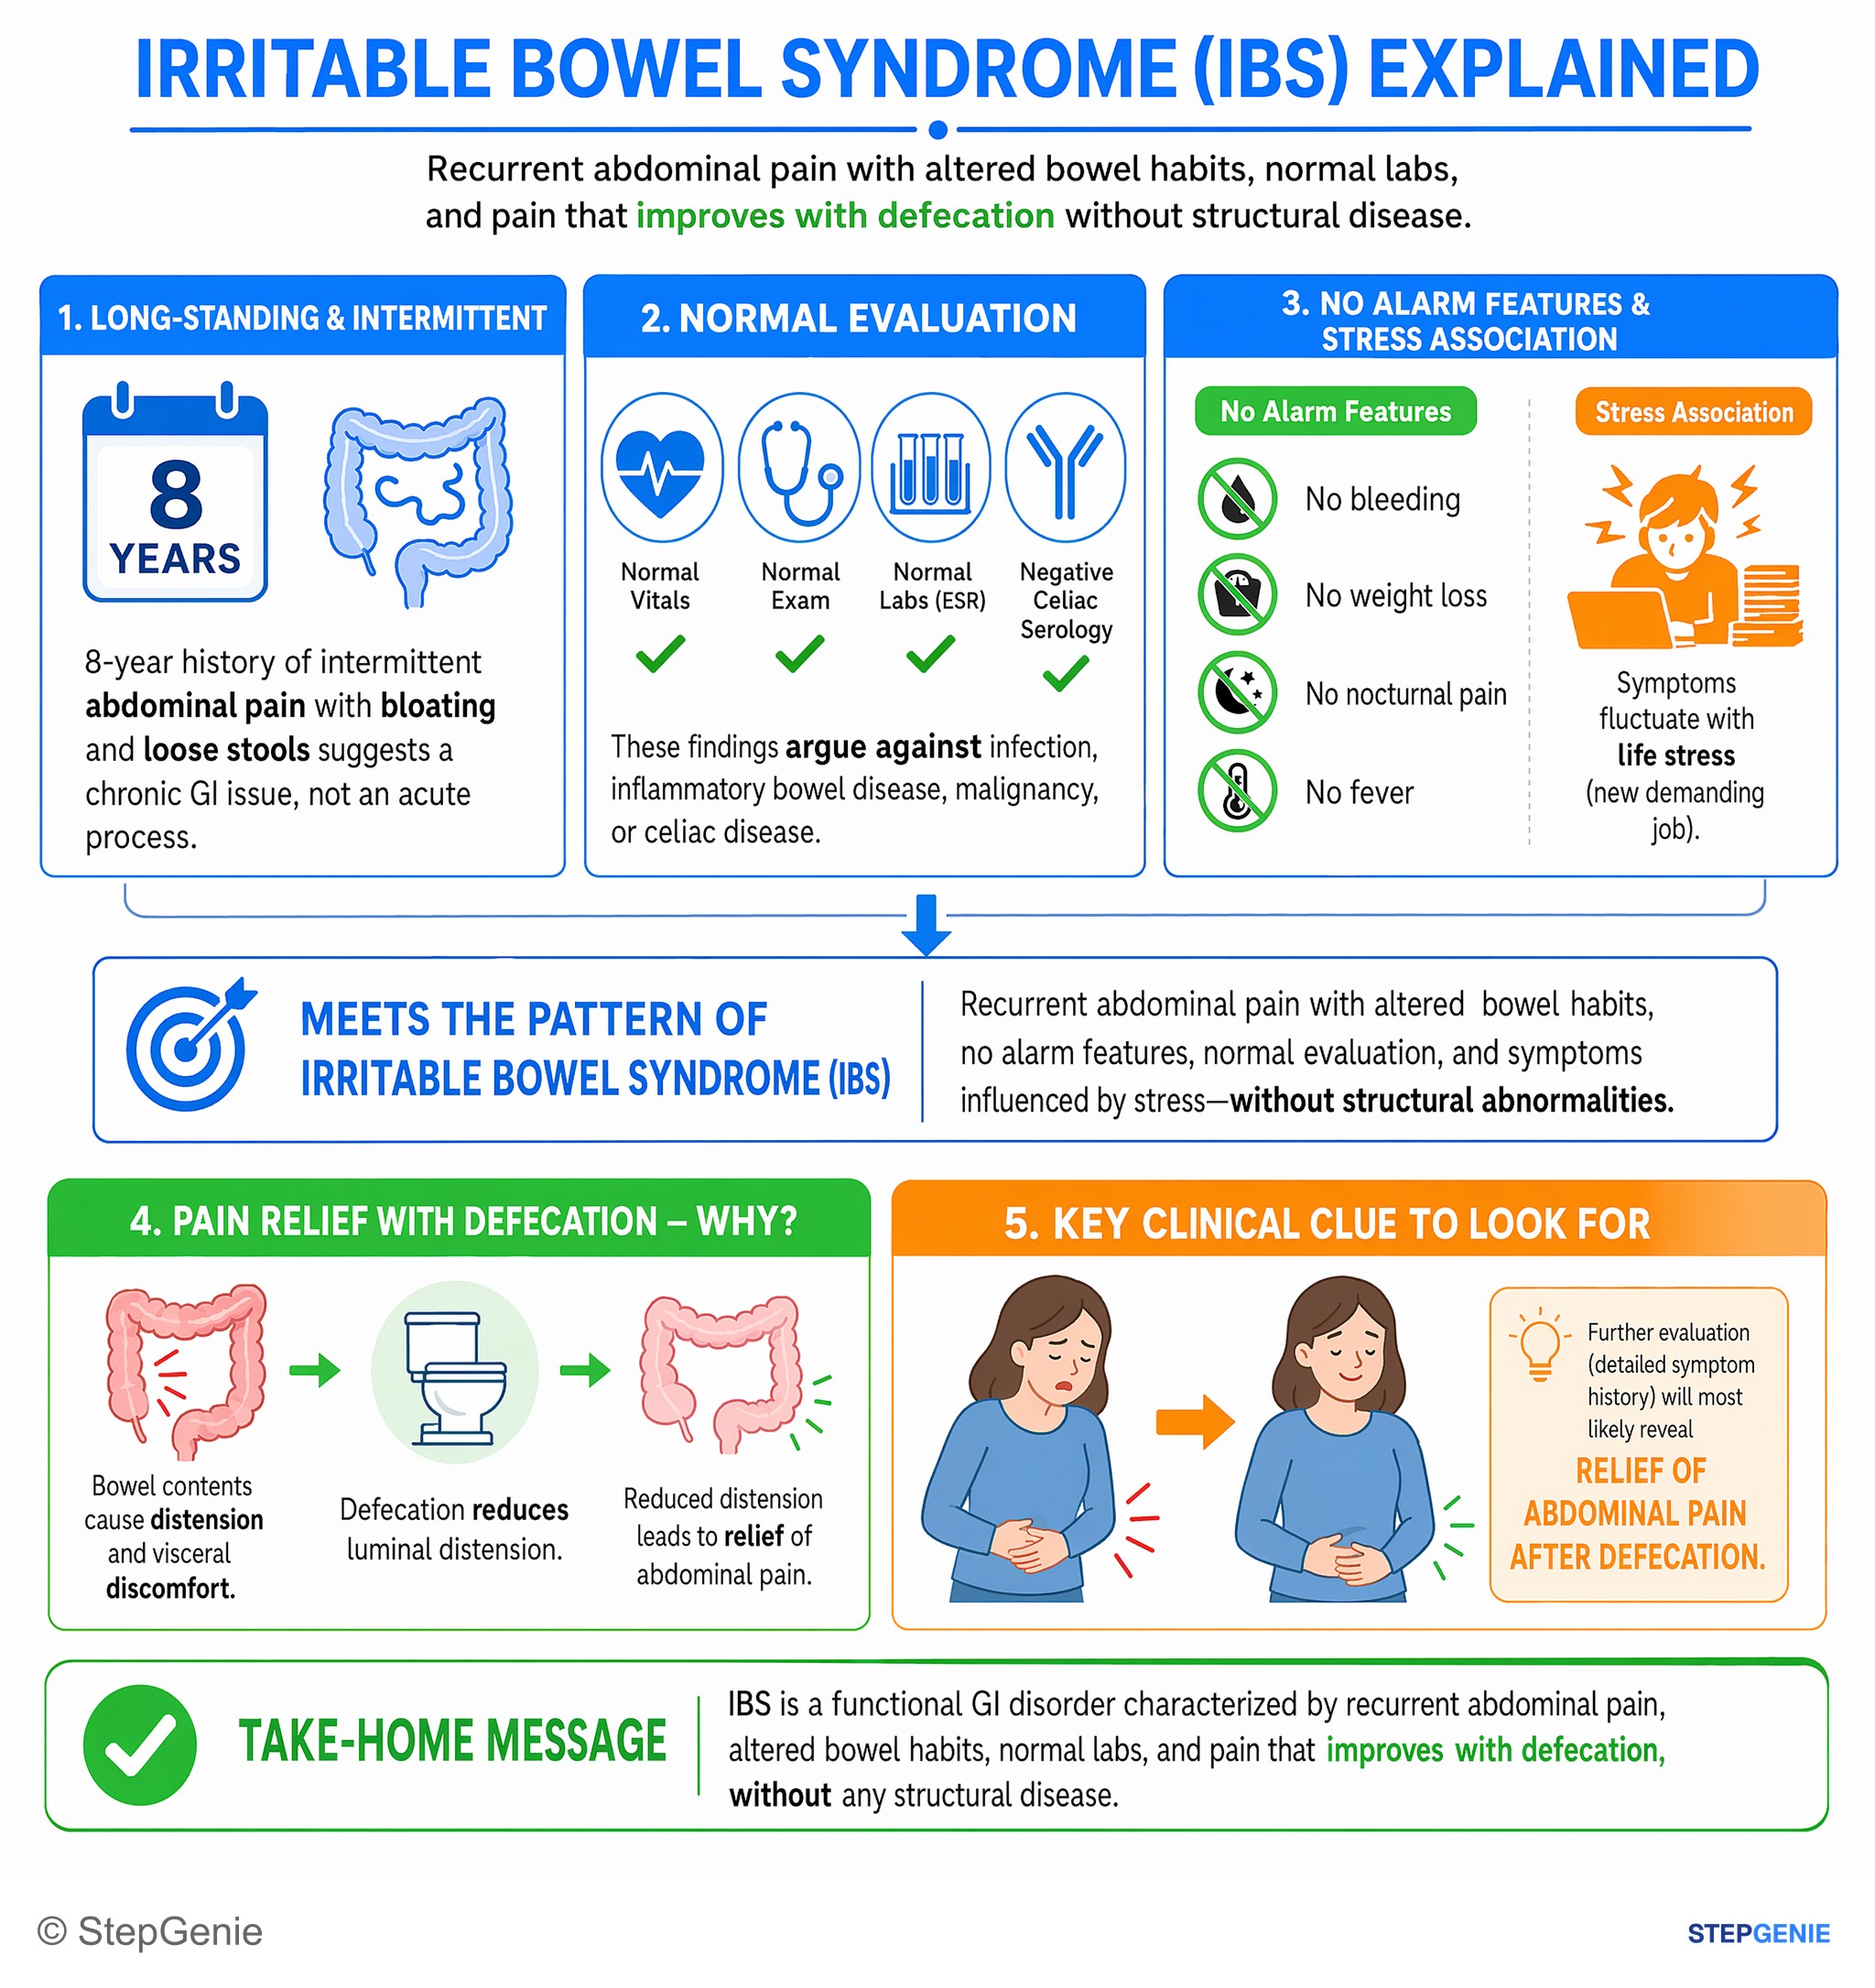
Irritable bowel syndrome (IBS) causes recurrent abdominal pain with altered bowel habits, normal labs, and pain that improves with…
USMLE Step 2Frequently Asked Questions
How do you tell irritable bowel syndrome from inflammatory bowel disease on a question stem?
Irritable bowel syndrome is suggested by recurrent abdominal pain linked to defecation and changes in stool frequency or form, with no structural disease and no red flags. Inflammatory bowel disease is more likely when the stem includes weight loss, fever, anemia, elevated inflammatory markers, nocturnal symptoms, blood in the stool, or other inflammatory features such as perianal disease or extraintestinal manifestations.
What are the Rome IV criteria clues for IBS that are high-yield for Step questions?
The key clue is recurrent abdominal pain occurring at least 1 day per week, associated with at least two features: relation to defecation, change in stool frequency, and change in stool form. A classic stem may also mention alternating constipation and diarrhea, bloating, mucus in the stool, a normal exam, and normal basic labs such as CBC and CRP.
What red flags argue against irritable bowel syndrome?
Red flags against irritable bowel syndrome include GI bleeding, iron-deficiency anemia, nocturnal diarrhea or pain that wakes the patient, unintentional weight loss, fever, family history of colon cancer or inflammatory bowel disease, older age at new onset, and elevated inflammatory markers or abnormal fecal calprotectin. These findings suggest you should think beyond IBS and often pursue more workup, including colonoscopy.
Why is ulcerative colitis less likely than IBS in a patient with crampy abdominal pain and bowel habit changes?
Ulcerative colitis is less likely because it classically causes bloody diarrhea, urgency, and tenesmus, with inflammatory findings rather than a functional pattern. IBS fits better when pain is often relieved by bowel movements, bowel habits alternate between diarrhea and constipation, and there is no blood, fever, weight loss, or abnormal inflammatory labs. On exams, blood plus urgency points more toward ulcerative colitis.
What is the first-line management for irritable bowel syndrome?
First-line management for irritable bowel syndrome is symptom-targeted treatment. Diet changes such as a low FODMAP approach, trigger avoidance, and soluble fiber like psyllium help some patients. Additional therapy depends on subtype and symptoms, including loperamide for IBS-D, polyethylene glycol for IBS-C, antispasmodics for pain or bloating, and stress management or CBT because the gut-brain axis can affect symptoms.