Intussusception is one of those “classic” pediatric GI diagnoses that shows up everywhere—yet it’s easy to miss if you don’t anchor on the right triad and imaging clue. On test day, the vignette often feels straightforward… until the answer choices start tempting you with other causes of abdominal pain, vomiting, or bleeding. Let’s break it down the way a good Q-bank explanation should: why the correct answer is correct and why every distractor is wrong.
Clinical Vignette (USMLE-Style)
A 9-month-old boy is brought to the ED for episodes of severe crying and drawing his knees to his chest. Between episodes, he appears tired but calm. He has vomited twice and had one diaper with dark red, mucoid stool. On exam, he is mildly lethargic; abdomen is soft with mild tenderness. A “sausage-shaped” mass is palpated in the right upper quadrant. Abdominal ultrasound demonstrates a target sign.
Most likely diagnosis?
A. Malrotation with volvulus
B. Hirschsprung disease
C. Meckel diverticulum
D. Intussusception
E. Hypertrophic pyloric stenosis
✅ Correct Answer: D. Intussusception
Tag: GI > Intestinal Disorders
Why Intussusception Is Correct
The pathophysiology you’re expected to know
Intussusception = telescoping of a proximal bowel segment into a distal segment (classically ileum into colon). This drags mesentery with it → venous congestion → edema → ischemia → bleeding.
High-yield clinical pattern
Think:
- Intermittent, severe colicky abdominal pain (child draws knees up)
- Vomiting (can become bilious later)
- “Currant jelly” stools = blood + mucus from ischemic mucosa
- Sausage-shaped mass (often RUQ) and sometimes Dance sign (empty RLQ)
Key imaging + management
- Ultrasound: target sign (aka donut sign)
- Air or contrast enema: diagnostic and therapeutic (reduces the bowel)
- If peritonitis, perforation, or unstable: surgery
Common associations (USMLE favorites):
- Often idiopathic in infants/toddlers due to lymphoid hyperplasia (e.g., after viral illness; Peyer patch enlargement).
- In older children, consider a pathologic lead point (e.g., Meckel diverticulum, polyp, lymphoma).
Answer Choices: Why the Distractors Are Wrong (and What They Actually Describe)
A. Malrotation with volvulus
Why it tempts you: vomiting + abdominal pain in an infant.
Why it’s wrong here: intussusception pain is episodic and there’s currant jelly stool + target sign.
What malrotation/volvulus looks like instead:
- Acute onset bilious vomiting in a neonate/infant = surgical emergency
- Rapid progression to ischemia, shock
- Imaging clue: upper GI series shows corkscrew or abnormal position of the duodenojejunal junction
- Can have bloody stools, but the vignette usually screams bilious emesis + toxic rather than intermittent “fine between episodes.”
High-yield pearl: Bilious vomiting in a neonate is malrotation/volvulus until proven otherwise.
B. Hirschsprung disease
Why it tempts you: pediatric bowel obstruction is a broad bucket.
Why it’s wrong here: Hirschsprung is about failure to pass meconium + chronic constipation, not episodic colicky pain with currant jelly stool.
What Hirschsprung looks like:
- Newborn who doesn’t pass meconium within 48 hours
- Abdominal distension, vomiting (can be bilious)
- Explosive stool after rectal exam
- Path: aganglionosis of submucosal (Meissner) and myenteric (Auerbach) plexuses → tonic contraction
- Diagnosis: rectal suction biopsy (no ganglion cells, increased AChE)
- Imaging: transition zone on contrast enema
C. Meckel diverticulum
Why it tempts you: painless bleeding in kids is a big Meckel buzzword, and Meckel can be a lead point for intussusception.
Why it’s wrong here: this vignette emphasizes intermittent pain + target sign—that’s intussusception. If Meckel were the primary diagnosis, the question would usually center the bleeding pattern and diagnostic test.
What Meckel looks like:
- Painless lower GI bleeding (maroon/red) in a young child
- Ectopic gastric mucosa → ulceration/bleeding
- Diagnosis: Technetium-99m pertechnetate scan (“Meckel scan”)
- Rule of 2s (still worth knowing):
- 2% of population
- within 2 feet of ileocecal valve
- 2 inches long
- presents <2 years
- 2 types ectopic tissue (gastric, pancreatic)
Bridge concept: Meckel can be a lead point → predispose to intussusception, especially in older children.
E. Hypertrophic pyloric stenosis
Why it tempts you: vomiting in an infant.
Why it’s wrong here: pyloric stenosis causes nonbilious projectile vomiting and no bloody/mucoid stool. Also, the timing is classically a bit older than newborn but typically 2–8 weeks, not 9 months.
What pyloric stenosis looks like:
- Nonbilious projectile vomiting after feeds
- Hungry baby (“hungry vomiter”)
- Olive-shaped mass in epigastrium
- Visible peristalsis
- Labs: hypochloremic metabolic alkalosis (loss of HCl) + possible hypokalemia
- Ultrasound: thickened pylorus
- Management: fluids/electrolyte correction → pyloromyotomy
Rapid-Fire High-Yield Table
| Diagnosis | Age / Timing | Hallmark Clues | Vomiting | Stool | Best Test / Key Finding | Treatment |
|---|---|---|---|---|---|---|
| Intussusception | 6–36 months (often) | Episodic colicky pain, sausage mass, lethargy | ± (can become bilious) | Currant jelly | US: target sign | Air/contrast enema (or surgery if unstable) |
| Malrotation + volvulus | Neonate/infant | Sudden severe illness, abdominal pain/distension | Bilious | ± blood | Upper GI: corkscrew/abnormal DJ junction | Emergent surgery |
| Hirschsprung | Newborn | No meconium in 48 hr, distension | ± bilious | constipation/enterocolitis | Rectal biopsy: no ganglion cells | Surgery |
| Meckel diverticulum | Child | Painless bleeding | Usually none | Maroon/red | Tc-99m Meckel scan | Resection if symptomatic |
| Pyloric stenosis | 2–8 weeks | Projectile vomiting, olive mass | Nonbilious | normal | US: thickened pylorus | Pyloromyotomy |
Test-Day “If You See This, Think That”
- Intermittent screaming + knees-to-chest + target sign → Intussusception
- Bilious vomiting + sick infant → Volvulus
- Painless GI bleeding → Meckel
- Nonbilious projectile vomiting + alkalosis → Pyloric stenosis
- No meconium + distension + explosive stool on DRE → Hirschsprung
Wrap-Up: The Board-Style Takeaway
Intussusception is a diagnosis you win by recognizing the pattern: episodic colicky pain, currant jelly stool, and target sign on ultrasound. Then you lock it in with management: air/contrast enema is often both diagnostic and therapeutic. The distractors are predictable—but only if you know what their “signature” presentations look like and how they differ from the classic intussusception story.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
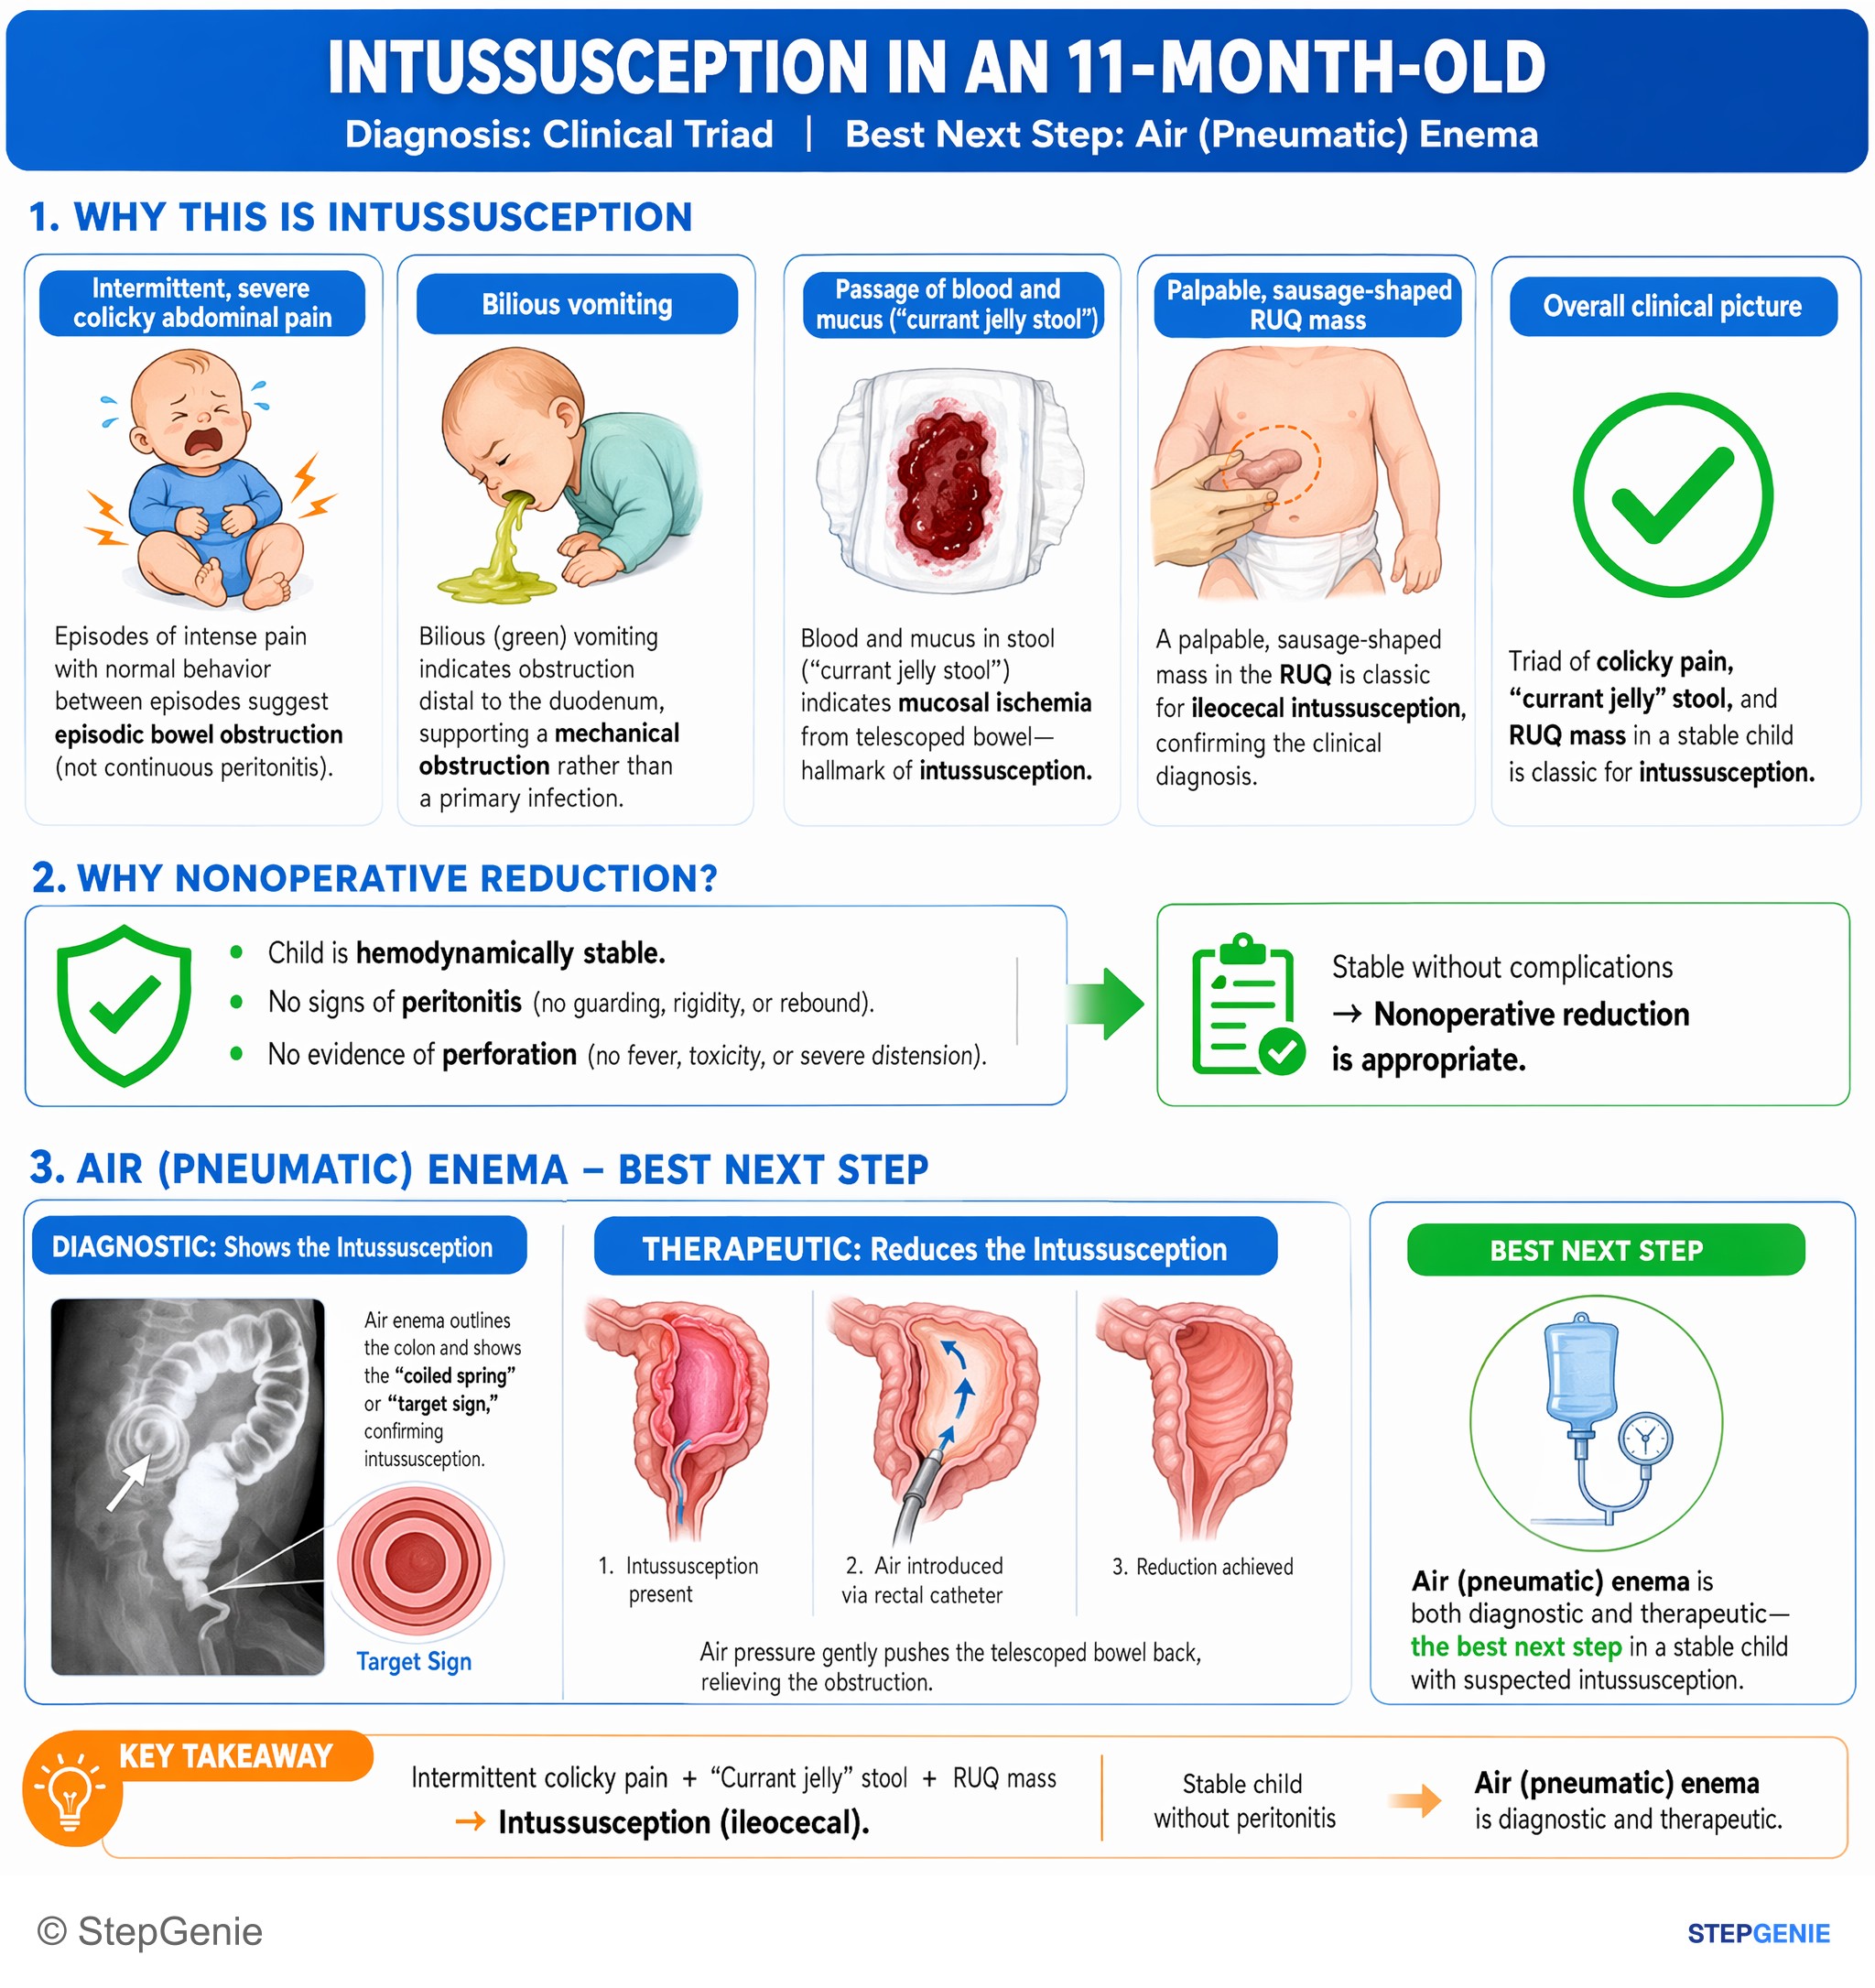
Intussusception in a stable child with classic triad (colicky pain, “currant jelly” stool, RUQ mass) is diagnosed and treated with air…
USMLE Step 2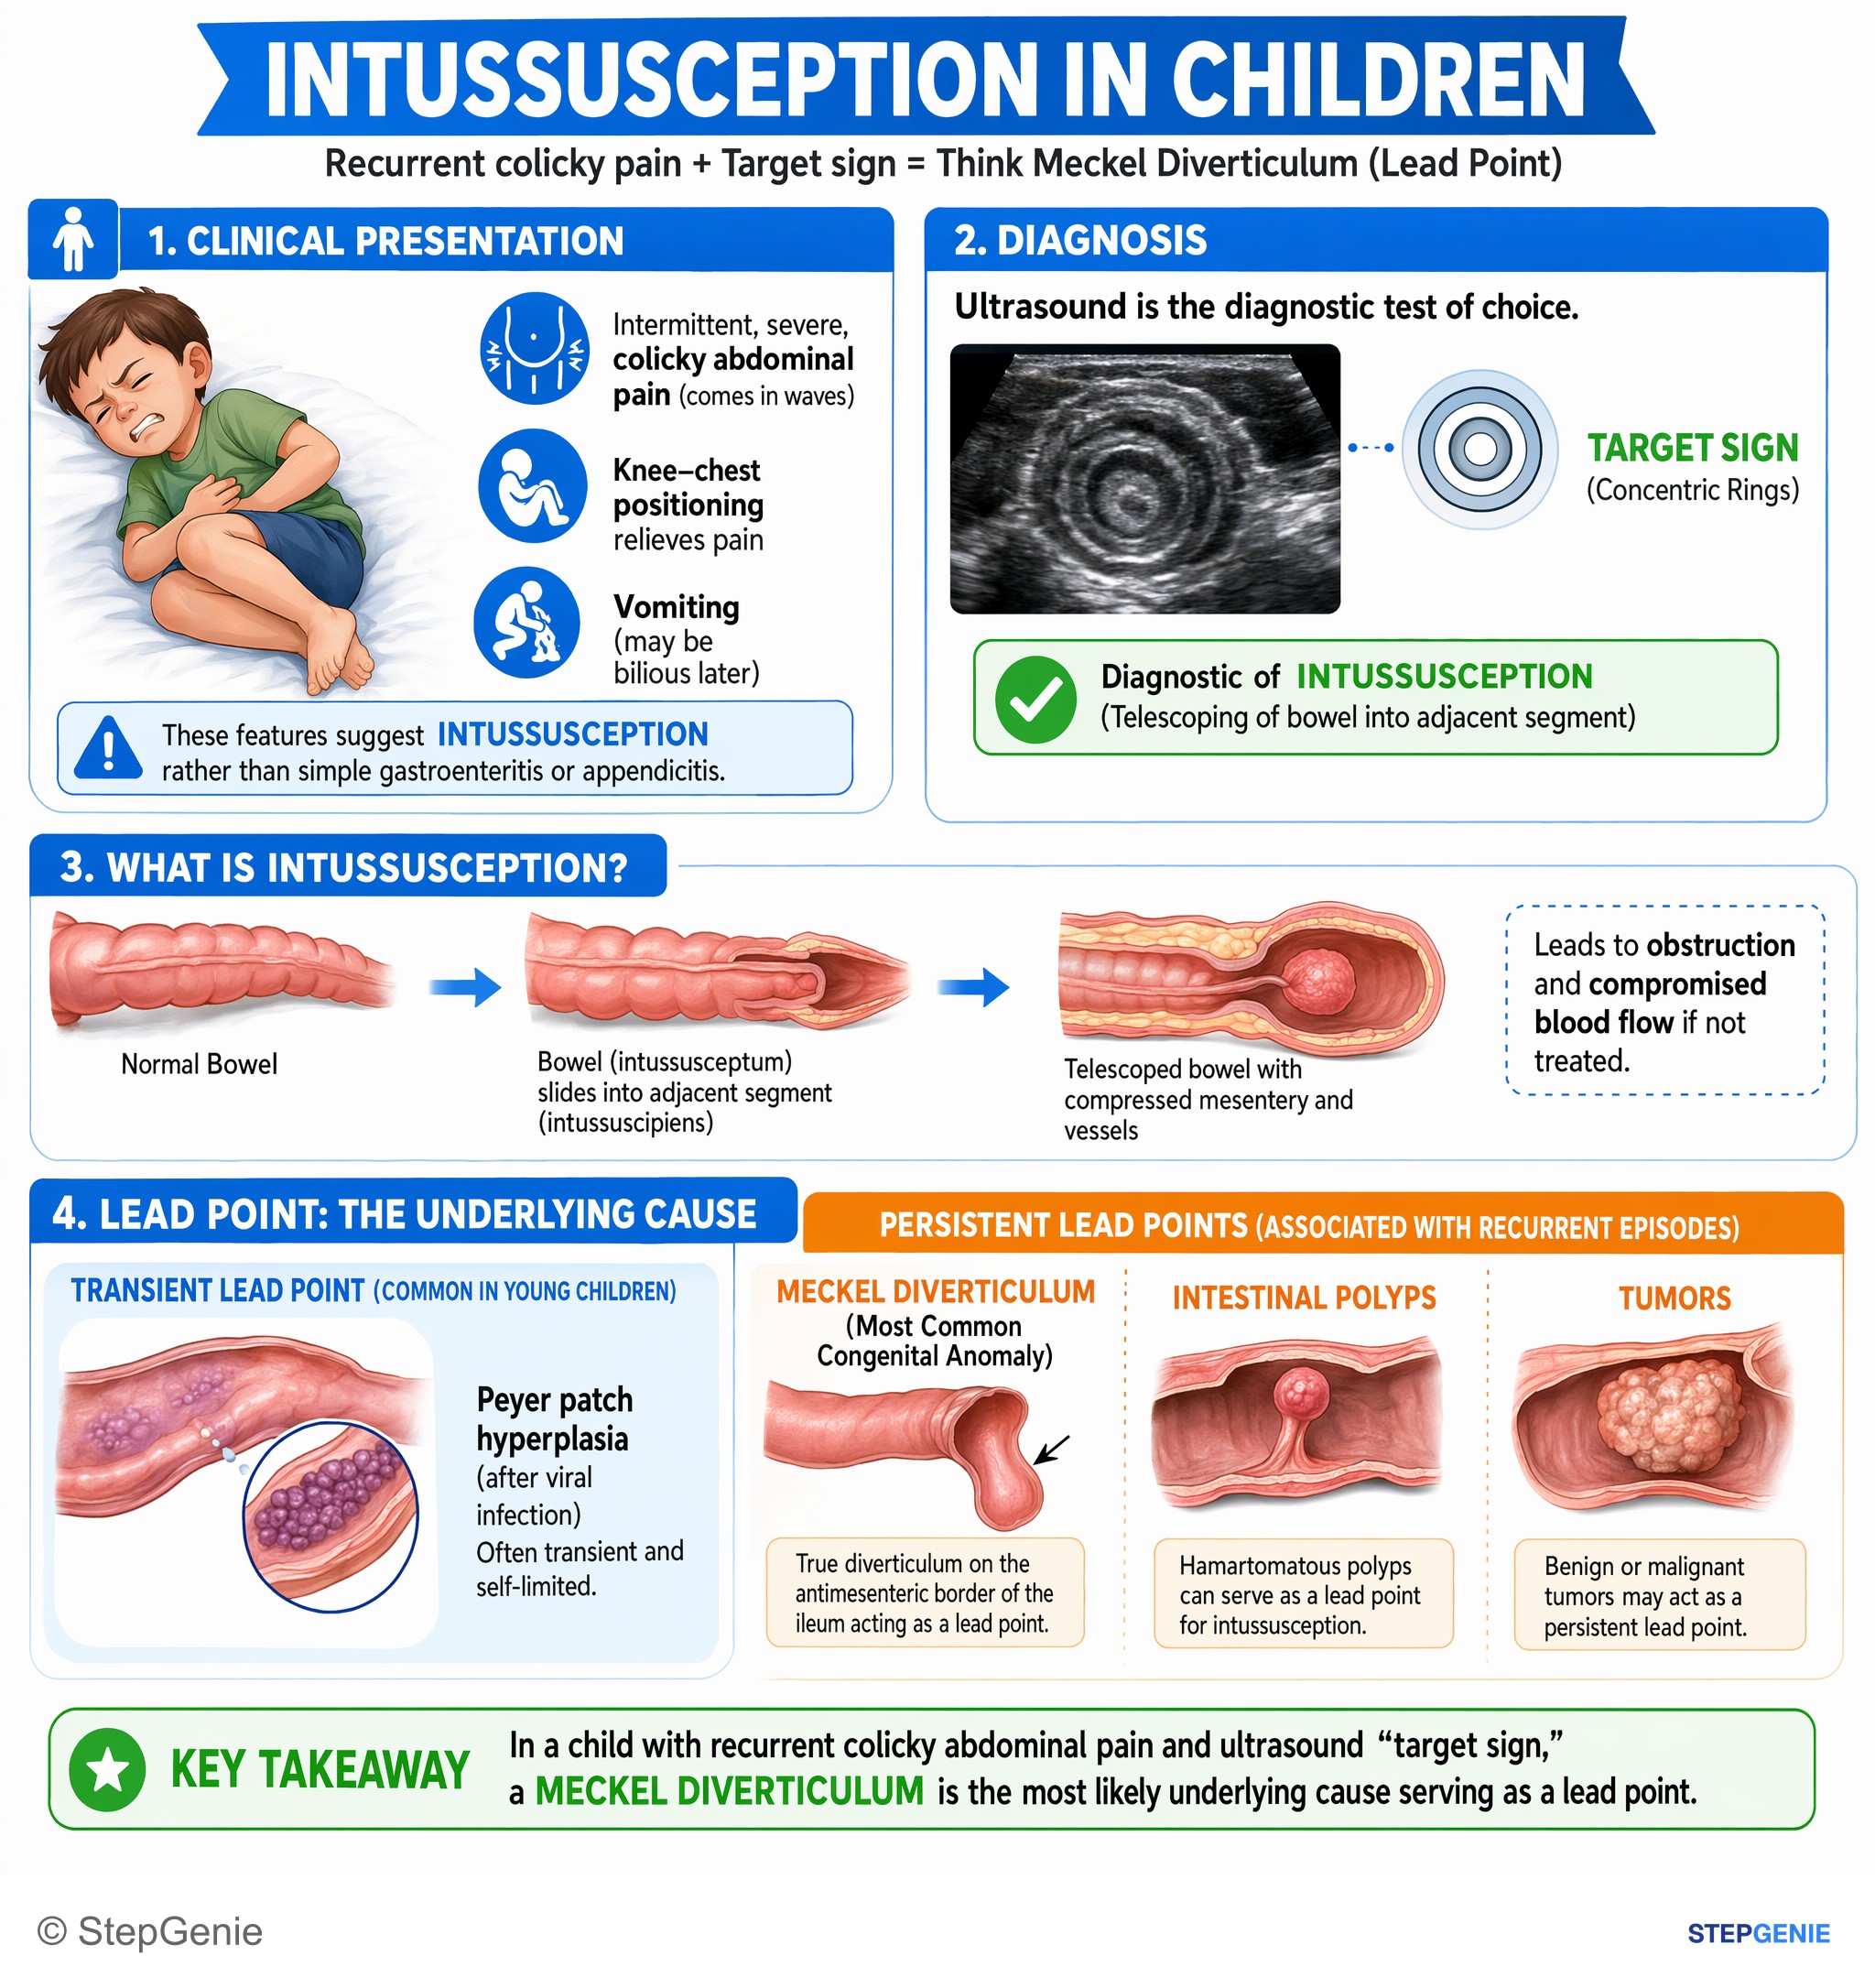
Intussusception in a child with recurrent colicky pain and target sign is often due to a Meckel diverticulum acting as a lead point.
USMLE Step 1Frequently Asked Questions
What is the classic presentation of intussusception in an infant?
The classic presentation is intermittent severe colicky abdominal pain, vomiting, and currant jelly stool. Infants often draw their knees to the chest during painful episodes and may seem tired or calm between them. Other high-yield clues include a sausage-shaped mass, often in the right upper quadrant, and lethargy from the bowel telescoping process that causes venous congestion, edema, ischemia, and bleeding.
Why does intussusception cause currant jelly stool?
Intussusception causes currant jelly stool because telescoping of bowel drags mesentery with it and leads to venous congestion, edema, and ischemia. The ischemic mucosa then bleeds, and the blood mixes with mucus to produce the dark red, mucoid stool described as currant jelly. This bleeding pattern is a classic clue that helps distinguish intussusception from other pediatric GI conditions.
What imaging finding points to intussusception, and what is the first treatment?
The key imaging finding is a target sign on abdominal ultrasound, and the first treatment in a stable patient is an air or contrast enema. The enema is both diagnostic and therapeutic because it can reduce the telescoped bowel. If the child has peritonitis, perforation, or is unstable, surgery is indicated instead of enema reduction.
How do you tell intussusception from malrotation with volvulus on a test question?
Intussusception is suggested by episodic pain, currant jelly stool, and a target sign on ultrasound, whereas malrotation with volvulus usually presents with acute bilious vomiting and a much more toxic or rapidly worsening picture. Malrotation with volvulus is a surgical emergency, especially in a neonate, and the classic imaging clue is an upper GI series showing a corkscrew appearance or abnormal duodenojejunal junction position.
How is intussusception different from Meckel diverticulum in a child with GI bleeding?
Intussusception usually causes intermittent colicky pain with vomiting and currant jelly stool, while Meckel diverticulum classically causes painless lower GI bleeding in a young child. Meckel bleeding is due to ectopic gastric mucosa causing ulceration, and the usual diagnostic test is a technetium-99m pertechnetate scan. Meckel can also act as a pathologic lead point that predisposes an older child to intussusception.