You just finished a GI question and you know it’s IBD… but the answer choices are designed to punish pattern recognition without precision. Crohn disease vs ulcerative colitis (UC) is one of those “looks easy, tests hard” topics: the stem gives you 2–3 clues, and every distractor is there because it shares one feature but misses the defining one. Let’s break it down the way Q-banks want you to think.
The Clinical Vignette (Q-Bank Style)
A 24-year-old woman presents with 6 months of intermittent abdominal pain and nonbloody diarrhea. She reports unintentional weight loss and fatigue. Exam shows mild tenderness in the right lower quadrant. Labs reveal microcytic anemia and elevated CRP. Colonoscopy shows skip lesions and cobblestoning. Biopsy demonstrates transmural inflammation with noncaseating granulomas.
Question: Which complication is this patient most at risk for?
Answer choices:
A. Toxic megacolon
B. Colorectal adenocarcinoma risk proportional to disease duration and extent
C. Strictures and fistulas
D. Primary sclerosing cholangitis
E. Antibodies against neutrophil cytoplasmic antigens (p-ANCA)
First, Identify the Diagnosis (Don’t Skip This Step)
This is Crohn disease.
Why? High-yield clues:
- RLQ pain → terminal ileum involvement is common
- Weight loss + microcytic anemia → malabsorption/iron deficiency (ileal disease can also impair bile acid resorption)
- Skip lesions + cobblestoning on endoscopy
- Transmural inflammation + noncaseating granulomas on biopsy
Key differentiator: Crohn is transmural and can involve anywhere mouth → anus with skip lesions. UC is mucosal/submucosal and starts in the rectum with continuous spread proximally.
Correct Answer: C. Strictures and fistulas
Crohn’s hallmark is transmural inflammation, which predisposes to:
- Fistulas (enteroenteric, enterovesical → recurrent UTIs/pneumaturia, enterocutaneous, perianal)
- Strictures → obstruction (especially terminal ileum)
- Abscesses
- Perianal disease (fissures, fistulas, skin tags)
Why transmural inflammation matters
When inflammation extends through the full bowel wall thickness, it promotes:
- Deep linear ulcers
- Fibrosis and narrowing (strictures)
- Tract formation between loops/organs (fistulas)
Why Each Distractor Is Wrong (and What It’s Testing)
A. Toxic megacolon
Why it’s tempting: It’s a classic IBD emergency.
Why it’s wrong here: Toxic megacolon is much more associated with UC (and can also occur with infectious colitis like C. difficile).
High-yield facts:
- Definition: acute colonic dilation + systemic toxicity
- Risk factors: severe colitis, hypokalemia, anticholinergics/opioids
- Management basics: bowel rest, IV steroids if IBD-related, antibiotics, surgical consult
Board-style tip: If the stem screams bloody diarrhea + severe systemic toxicity + markedly dilated colon, think UC (or infectious colitis) before Crohn.
B. Colorectal adenocarcinoma risk proportional to disease duration and extent
Why it’s tempting: IBD increases colon cancer risk.
Why it’s wrong here: This phrasing is most classically tested with UC, because UC is:
- Continuous colitis beginning in the rectum
- Primarily colonic involvement (large surface area chronically inflamed)
Crohn can increase colorectal cancer risk too if the colon is extensively involved, but the classic USMLE association is UC.
High-yield facts:
- Cancer risk increases with:
- Duration (often emphasized after ~8–10 years of colitis)
- Extent (pancolitis > left-sided)
- Primary sclerosing cholangitis (PSC) further increases risk
- Surveillance colonoscopy is emphasized in long-standing colitis.
D. Primary sclerosing cholangitis
Why it’s tempting: It’s a famous IBD association.
Why it’s wrong here: PSC is strongly associated with UC (more than Crohn).
High-yield PSC facts (very testable):
- Inflammation and fibrosis of intra/extrahepatic bile ducts → multifocal strictures
- Cholestatic labs: ↑ALP, ↑bilirubin
- Imaging: “beading” on ERCP/MRCP
- Increased risk of:
- Cholangiocarcinoma
- Gallbladder carcinoma
- Colorectal cancer (especially with concomitant UC)
Board-style tip: UC + elevated ALP + pruritus/jaundice → PSC until proven otherwise.
E. p-ANCA
Why it’s tempting: Serologies are often paired with IBD.
Why it’s wrong here: p-ANCA is associated with UC, while ASCA (anti-Saccharomyces cerevisiae antibodies) is associated with Crohn.
High-yield caveat: These antibodies are not diagnostic and are not required to make the diagnosis. They’re most useful as “pattern recognition” clues in question stems.
| Feature | Crohn Disease | Ulcerative Colitis |
|---|---|---|
| Distribution | Anywhere mouth → anus | Colon only |
| Pattern | Skip lesions | Continuous from rectum |
| Depth | Transmural | Mucosal/submucosal |
| Endoscopy | Cobblestoning, linear ulcers | Erythematous friable mucosa, pseudopolyps |
| Complications | Fistulas, strictures, abscesses, perianal disease | Toxic megacolon, severe bleeding |
| Histology | Noncaseating granulomas (not always) | Crypt abscesses, mucosal inflammation |
| Smoking | Worsens Crohn | Often protective (don’t recommend smoking) |
| Serology | ASCA | p-ANCA |
| Cancer risk | Increased if colonic involvement | Increased; correlates with duration/extent |
The “One-Liner” Rules That Save You on Test Day
If you’re stuck between Crohn and UC, ask:
- Is the rectum involved?
- UC: yes, always starts at the rectum
- Crohn: may spare rectum
- Is it continuous or patchy?
- UC: continuous
- Crohn: skip lesions
- Is the complication transmural?
- Fistulas/strictures/abscess → Crohn
- Toxic megacolon → UC
- Is there malabsorption?
- Terminal ileum Crohn → bile acid loss → watery diarrhea; possible fat-soluble vitamin issues
- UC is mucosal and colonic → less classic for malabsorption/weight loss (though can occur in severe disease)
Extra High-Yield Associations Q-Banks Love
Crohn (terminal ileum) complications you should recall fast
- Bile acid malabsorption → watery diarrhea
- Calcium oxalate kidney stones
- Less bile salt reabsorption → fat binds calcium → oxalate absorbed → stones
- Vitamin B12 deficiency (terminal ileum absorption site)
- Gallstones (impaired bile acid recycling)
UC “classic” clues
- Bloody diarrhea, urgency, tenesmus
- Left-sided pain more common (distal disease)
- Backwash ileitis can occur, but UC is still primarily colonic
- Pseudopolyps (regenerating mucosa)
Takeaway: Why Every Answer Choice Matters
This question isn’t really asking “What is Crohn?”—it’s asking whether you understand the mechanistic consequence of transmural inflammation. The distractors are high-yield UC associations (toxic megacolon, PSC, p-ANCA, classic CRC risk framing) meant to trap you if you stop at “IBD.”
When you force yourself to explain why each distractor is wrong, you’re training the exact skill Step 1 and Step 2 reward: selecting the best answer among close cousins.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
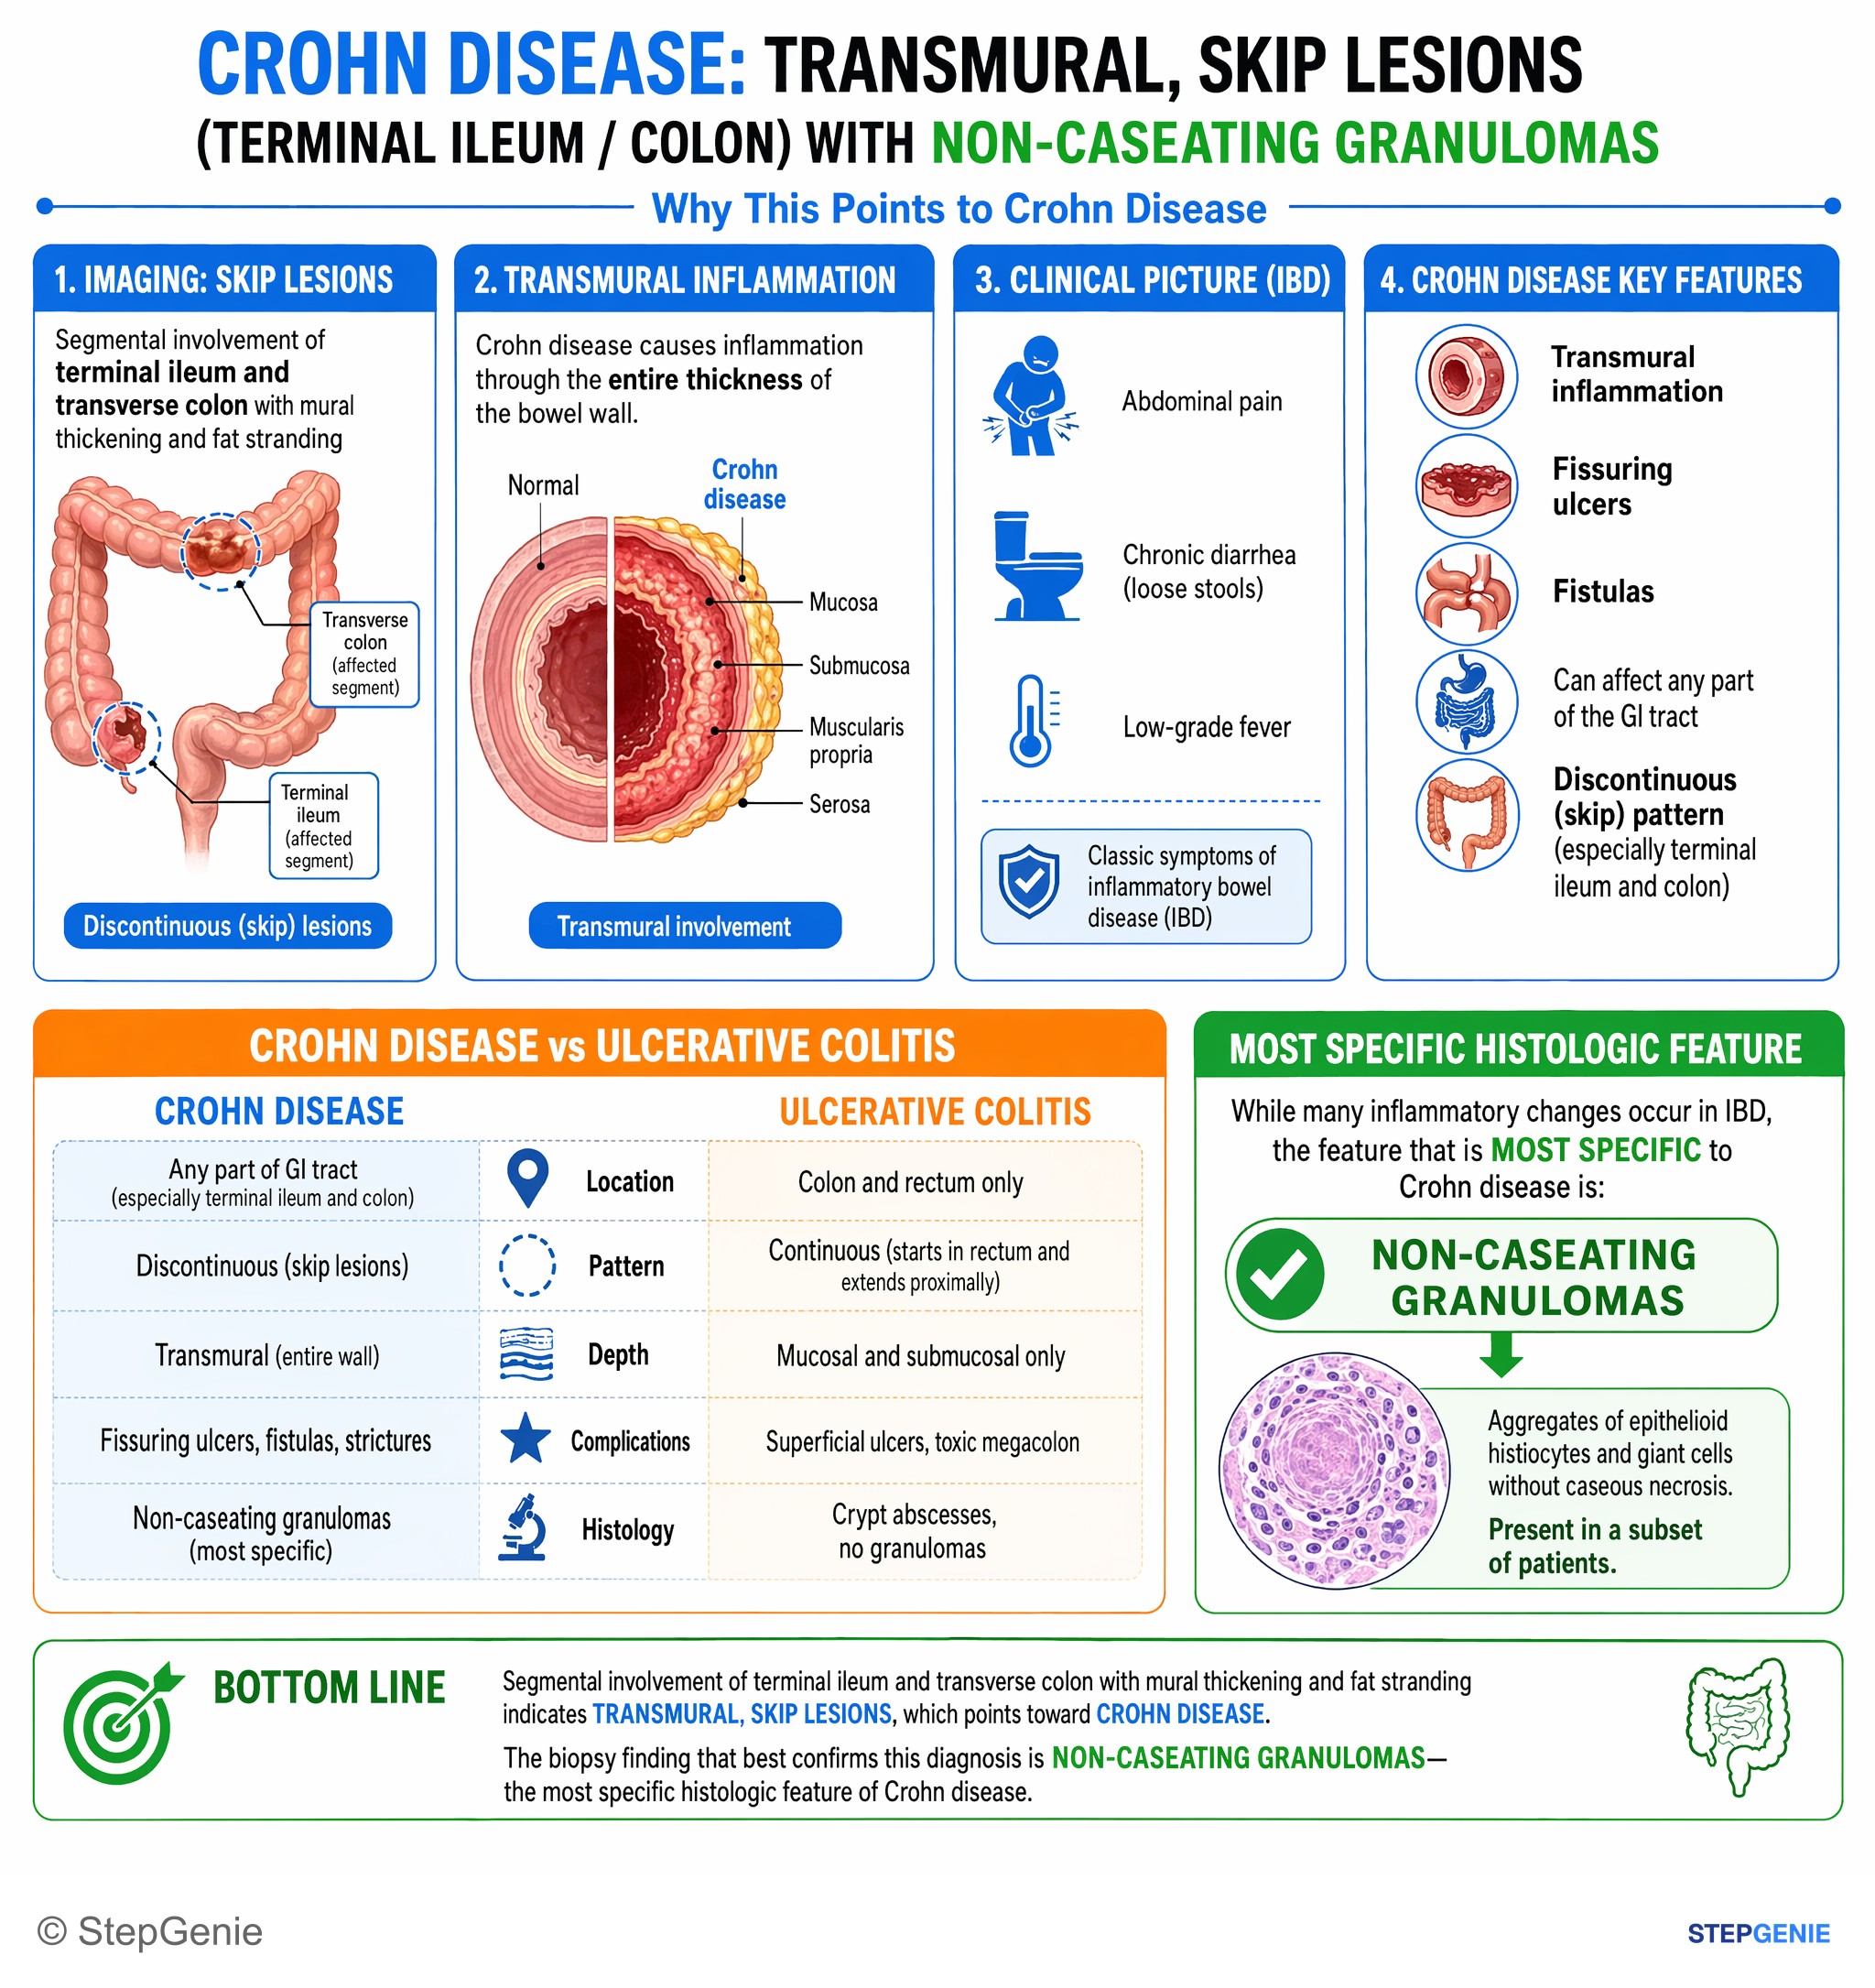
Crohn disease: transmural, skip lesions (terminal ileum/colon) with non-caseating granulomas—most specific histologic feature.
USMLE Step 1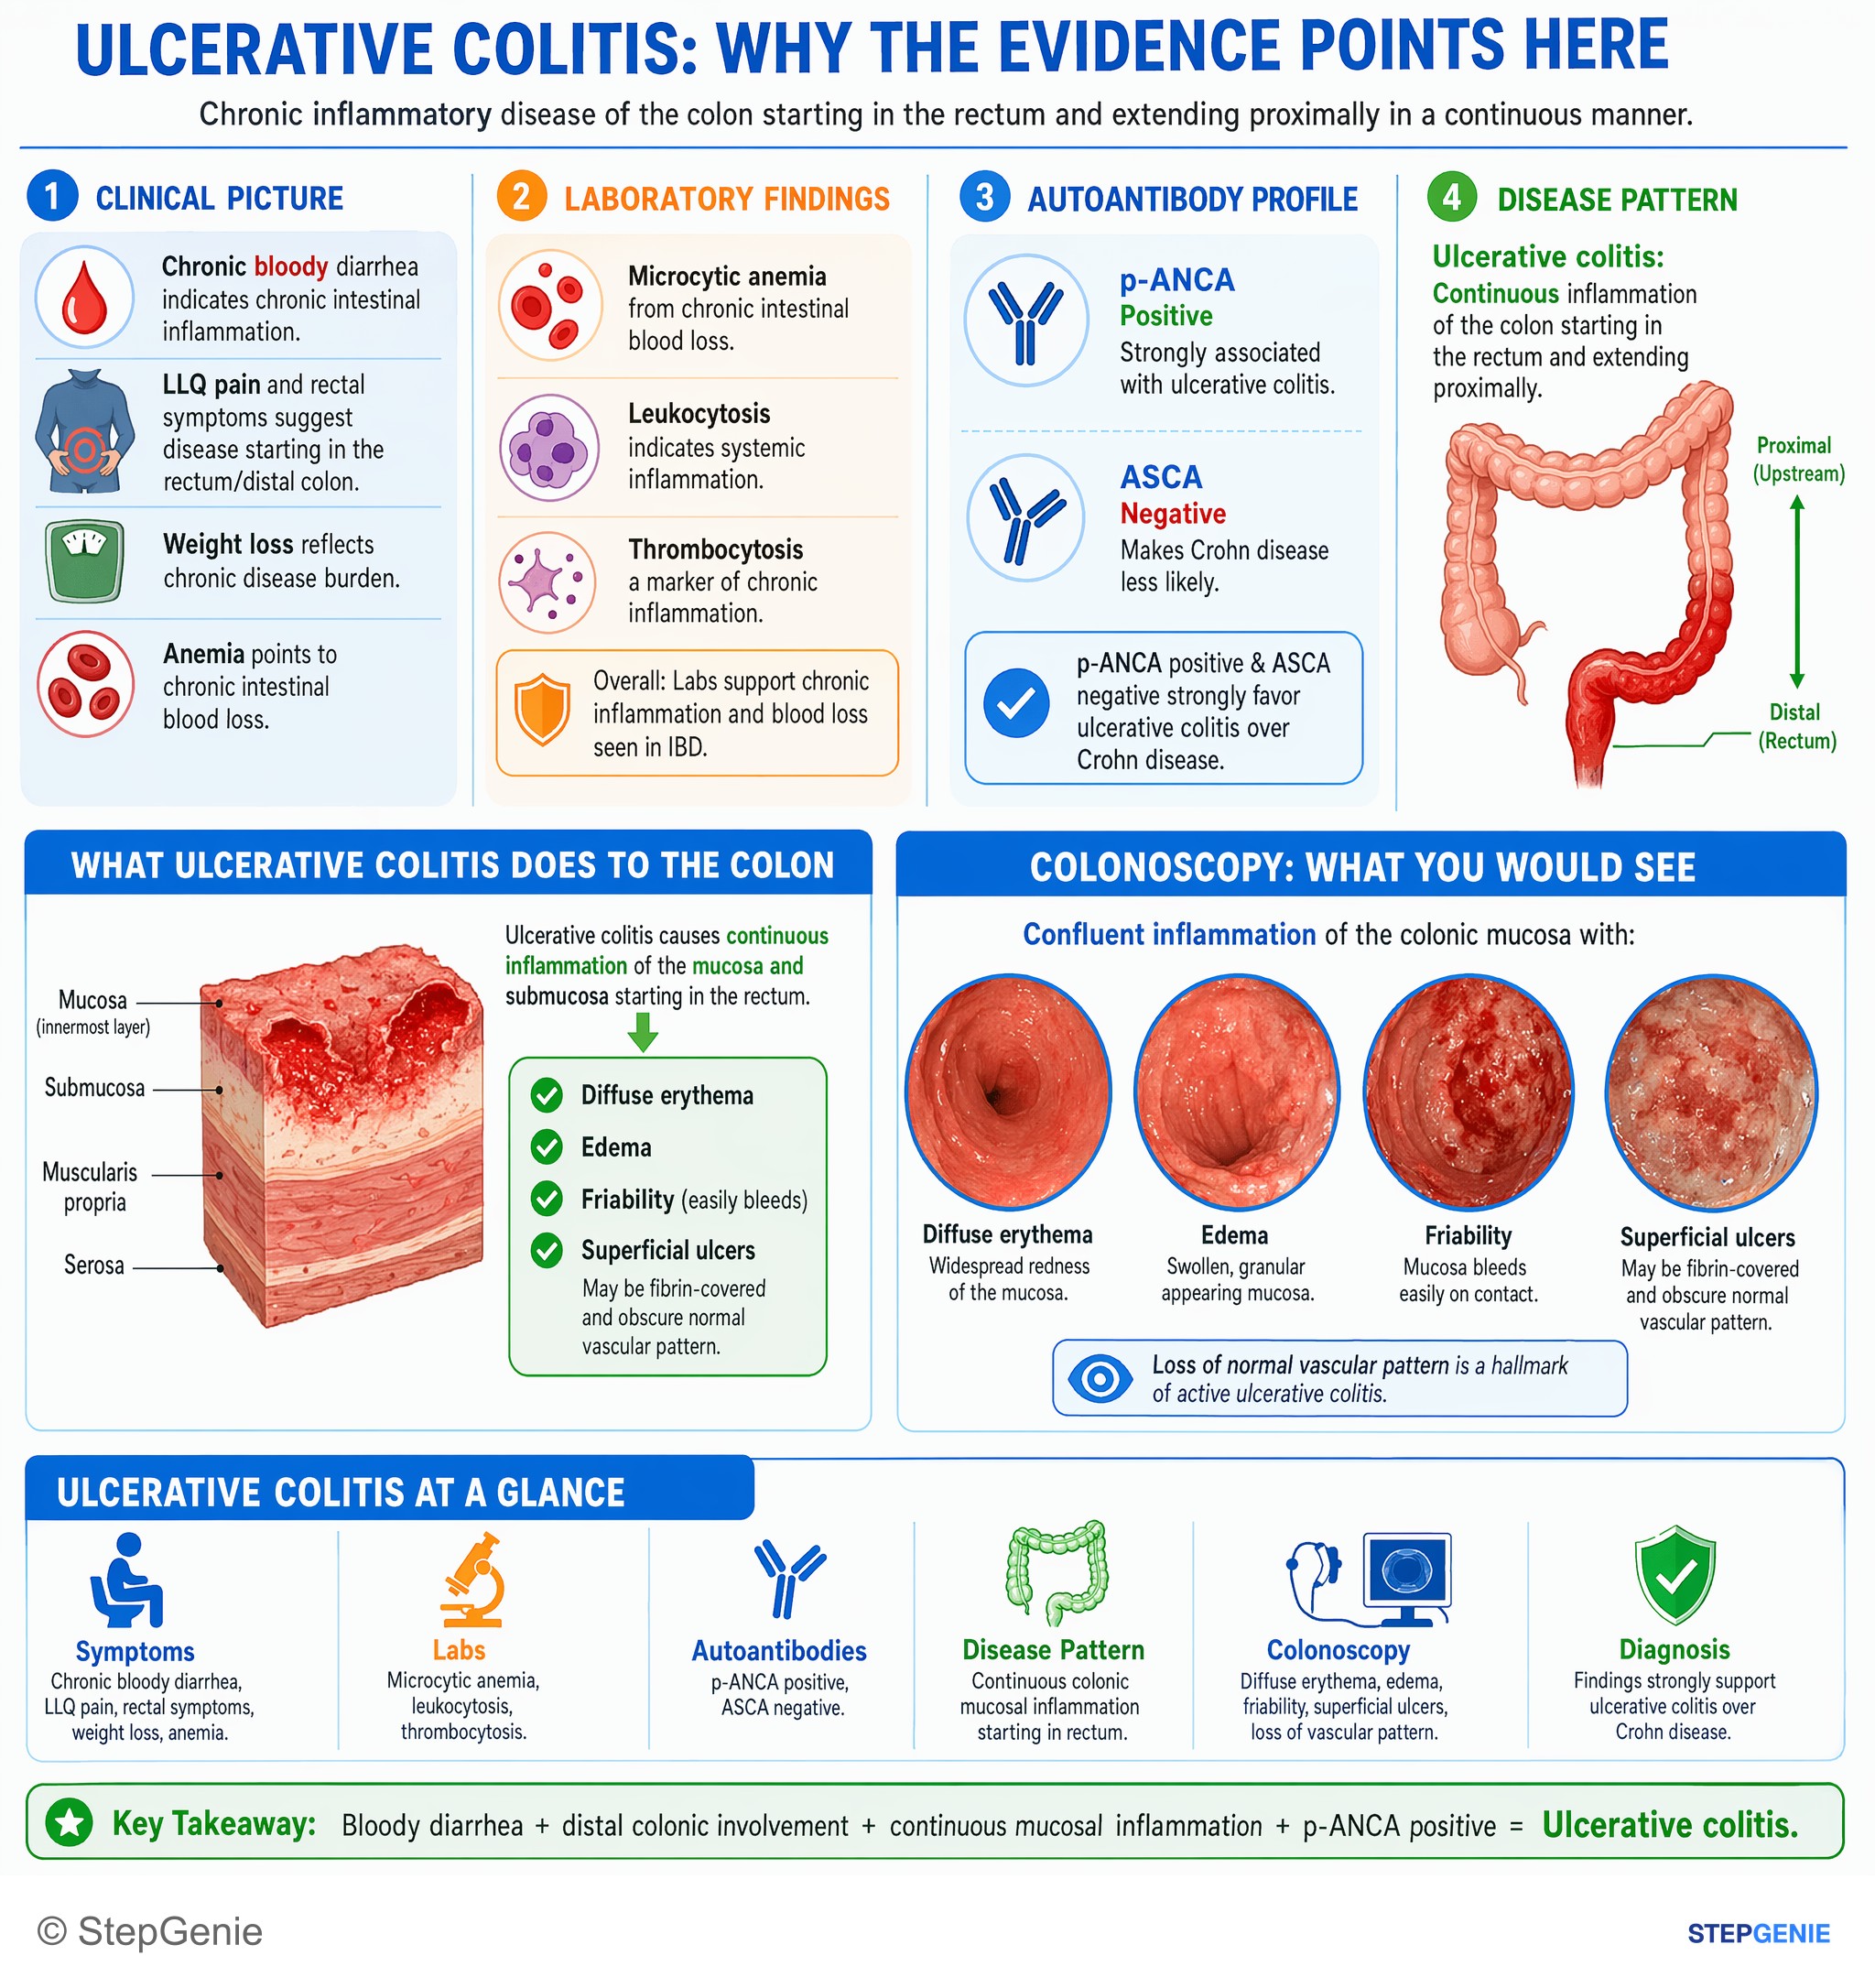
Ulcerative colitis: continuous colonic mucosal inflammation, bloody diarrhea, weight loss, positive p-ANCA; colonoscopy shows diffuse…
USMLE Step 1Frequently Asked Questions
How do you tell Crohn disease from ulcerative colitis on a question stem?
The fastest way is to compare distribution, depth, and pattern. Crohn disease can involve anywhere from mouth to anus, has skip lesions, and causes transmural inflammation. Ulcerative colitis is limited to the colon, starts in the rectum, and spreads continuously proximally with mucosal and submucosal inflammation. Endoscopic clues like cobblestoning favor Crohn, while a continuous colitis pattern favors UC.
Why does Crohn disease cause fistulas and strictures?
Crohn disease causes fistulas and strictures because its inflammation is transmural, meaning it extends through the full thickness of the bowel wall. That deep inflammation promotes linear ulcers, fibrosis, and narrowing, which lead to strictures. It also allows abnormal tracts to form between bowel loops or nearby organs, producing fistulas such as enteroenteric, enterovesical, enterocutaneous, and perianal fistulas.
Why is toxic megacolon more associated with ulcerative colitis than Crohn disease?
Toxic megacolon is classically associated much more with ulcerative colitis than with Crohn disease. On exams, a stem with bloody diarrhea, severe systemic toxicity, and a markedly dilated colon should push you toward UC or infectious colitis like C. difficile. It is defined by acute colonic dilation with systemic toxicity and is a classic IBD emergency tested as a UC complication.
Which antibody pattern goes with Crohn disease versus ulcerative colitis?
Crohn disease is associated with ASCA, while ulcerative colitis is associated with p-ANCA. These serologies are useful as pattern-recognition clues in question stems, but they are not diagnostic and are not required to make the diagnosis. If an answer choice offers p-ANCA, that points more toward UC than Crohn in the classic board-style association.
What clues in a vignette point to Crohn disease involving the terminal ileum?
Right lower quadrant pain, weight loss, microcytic anemia, skip lesions, cobblestoning, and noncaseating granulomas point toward Crohn disease with terminal ileum involvement. Right lower quadrant pain suggests terminal ileal disease, while weight loss and microcytic anemia reflect malabsorption and iron deficiency. Transmural inflammation on biopsy is another defining clue that helps distinguish Crohn disease from ulcerative colitis.