Familial adenomatous polyposis (FAP) is an autosomal dominant cancer syndrome caused by a germline APC mutation on chromosome 5q21: hundreds to thousands of adenomas carpet the colon and rectum from adolescence (median onset age 16), and nearly every untreated patient develops colorectal cancer by about age 40. Carriers need yearly colonoscopy from age 10-15, then prophylactic colectomy once the polyps can no longer be managed endoscopically, plus lifelong upper endoscopy from age 20-25 for duodenal adenomas. Attenuated FAP gives fewer (average about 30), mostly right-sided adenomas and later cancer; MUTYH-associated polyposis looks similar but is autosomal recessive, and Lynch syndrome causes cancer with few polyps.
The one-liner: APC and β-catenin
Germline APC mutation → the normal allele is lost in a colonic cell (second hit) → β-catenin is no longer broken down → Wnt target genes drive proliferation → adenomas → carcinoma.
- APC is a tumor suppressor. Its main job is to control β-catenin levels in the Wnt pathway. Most FAP mutations produce a truncated protein that cannot help degrade β-catenin.
- Same first step as sporadic cancer. APC loss is one of the earliest events in the chromosomal instability pathway, which later adds KRAS mutations and losses at 18q and 17p (TP53). Other gatekeeper genes are compared in oncogenes vs tumor suppressors.
- Inheritance: autosomal dominant, but about 25% of patients have a de novo mutation, so a negative family history does not rule FAP out.
- Frequency: about 1 in 7,000 to 1 in 22,000 live births (NCI PDQ).
Classic vs attenuated FAP
| Classic FAP | Attenuated FAP (AFAP) | |
|---|---|---|
| Adenomas | Over 100, often thousands, carpeting colon and rectum | Fewer: average about 30 (from a few to hundreds) |
| Where | Whole colon and rectum | Mostly right colon, so colonoscopy, not sigmoidoscopy |
| Onset | Median age 16; 15% by age 10, 75% by 20, 90% by 30 | Mid-to-late 20s |
| Colorectal cancer | Nearly all untreated patients, usually by about 40 | Later; average age at diagnosis 56 |
| APC mutation site | Middle of the gene (codons 169-1249; 1250-1464 gives the densest carpeting) | 5′ end (up to exon 4), exon 9 or 3′ end |
| CHRPE | About 75% | Usually absent |
| Colon surveillance (NCI PDQ) | Colonoscopy from age 10-15 (NCCN), conventionally every year | Colonoscopy every 1-2 years from the late teens (NCCN) |
Extracolonic features: Gardner, Turcot and the rest
| Feature | How common (NCI PDQ) | What to know |
|---|---|---|
| Duodenal and periampullary adenomas | 80-100% of patients; duodenal cancer 4-12% lifetime | The biggest cancer risk left after colectomy; upper endoscopy from age 20-25 |
| Desmoid tumors | About 10% (range 8-38%) | Locally aggressive, non-metastasizing fibromatosis, often intra-abdominal (mesenteric); about 80% of intra-abdominal desmoids follow surgery; in some series the second most common cause of death after colorectal cancer |
| Fundic gland polyps | Up to about 60% | Stomach body and fundus; long considered benign, but dysplasia can occur |
| CHRPE | About 75% | Flat, dark retinal spots, often multiple or bilateral, present from early childhood |
| Osteomas, epidermoid cysts, dental anomalies | Common | The "Gardner" findings |
| Papillary thyroid cancer (cribriform-morular type) | 1-2% | Thyroid ultrasound from the late teens, every 2-5 years if normal |
| Hepatoblastoma | About 1.6% | Young children; consider AFP, liver exam and ultrasound every 3-6 months until age 5 |
| Brain tumors (about 80% medulloblastoma) | 1-2% lifetime | Mostly in childhood; the APC form of Turcot syndrome |
Name the variants:
- Gardner syndrome = FAP + osteomas (skull, mandible) + soft-tissue tumors (epidermoid cysts, desmoids) + dental anomalies. It is the same APC disease, and NCI calls the term essentially obsolete in clinical practice, but exams still use it. Hook: a gardener digs up bones, teeth and lumps.
- Turcot syndrome = colonic polyposis or cancer + a brain tumor, and it is really two diseases: APC → medulloblastoma (FAP); mismatch repair genes → glioblastoma (Lynch). Hook: Turcot = turban, a tumor under it. The tumor itself is covered in the medulloblastoma mnemonic.
Screening and surveillance (current guidance)
| Who or what | Start | How often |
|---|---|---|
| Child of an APC carrier | Test for the family variant in childhood; testing minors is justified because surveillance starts early | One-time test |
| APC carrier, colon (classic FAP) | Age 10-15 | Colonoscopy every year until colectomy |
| Relative who tests negative for the family variant | Average-risk age | Average-risk screening |
| Duodenum (upper endoscopy) | Age 20-25; earlier if relatives had duodenal cancer or heavy duodenal polyposis | Every 3-5 years with no polyps, shortening by Spigelman stage to expert endoscopy every 3-6 months at stage IV |
| Thyroid ultrasound | Late teens | Every 2-5 years if normal |
| Hepatoblastoma (consider) | Birth | Every 3-6 months until age 5 |
Sources differ slightly: Merck, drawing on the 2015 ACG guideline, suggests annual sigmoidoscopy from age 10-12 for at-risk relatives when genetic testing is unavailable, upper endoscopy from 25-30 and yearly thyroid ultrasound, while the table follows the NCCN schedule as summarized in NCI's PDQ (2025). The general age-based schedule is in the colorectal cancer screening flowchart.
Prophylactic colectomy
- Once polyps appear, colectomy is the only effective way to prevent colorectal cancer, and prophylactic surgery improves survival (NCI PDQ). Merck advises colectomy soon after diagnosis; NCI notes that timing is individualized by polyp number, size, histology and symptoms, and may be delayed a few years in patients diagnosed very early.
| Operation | Best for | Afterward |
|---|---|---|
| Restorative proctocolectomy with ileal pouch-anal anastomosis (IPAA) | Dense rectal polyposis | Yearly pouch endoscopy: adenomas can form in the pouch and anal transition zone |
| Total colectomy with ileorectal anastomosis (IRA) | Milder disease: fewer than 1,000 colonic and fewer than 20 rectal adenomas | Lifelong rectal surveillance, because rectal cancer risk remains |
| Total proctocolectomy with end ileostomy | Low rectal cancer, or when a pouch is not possible | No rectal mucosa left at risk |
- After colectomy: continue upper endoscopy for duodenal and ampullary adenomas and watch for desmoids, which often appear after abdominal surgery.
- NSAIDs: sulindac and celecoxib reduce polyp size and number, but no drug is FDA-approved for FAP chemoprevention (celecoxib's approval was voluntarily withdrawn), and NSAIDs do not replace colectomy.
FAP vs MUTYH-associated polyposis vs Lynch syndrome
| FAP and AFAP | MUTYH-associated polyposis (MAP) | Lynch syndrome | |
|---|---|---|---|
| Gene | APC (5q21), tumor suppressor | Biallelic MUTYH: base excision repair of oxidative DNA damage | MLH1, MSH2, MSH6, PMS2 or EPCAM: mismatch repair |
| Inheritance | Autosomal dominant | Autosomal recessive: each sibling has a 25% risk | Autosomal dominant |
| Polyps | Over 100 (classic) or about 30 (AFAP) adenomas | Usually resembles AFAP; serrated and hyperplastic polyps also occur | Few: polyps appear younger but not in greater numbers |
| Colorectal cancer | Nearly certain without colectomy | High lifetime risk (estimates vary widely); often right-sided | About 3% of all CRC; 60-70% right-sided; microsatellite instability; fast adenoma-to-cancer progression |
| Extracolonic clues | Duodenal adenomas, desmoids, CHRPE, osteomas, thyroid cancer, hepatoblastoma, medulloblastoma | Duodenal adenomas, less often and later than in FAP | Endometrium (most common), ovary, stomach, small bowel, ureter and renal pelvis, sebaceous tumors, glioblastoma |
| Colon screening | Classic: yearly from 10-15; AFAP: every 1-2 years from the late teens | Colonoscopy every 1-2 years from no later than 25-30 | Colonoscopy every 1-2 years from 20-25 (MLH1, MSH2, EPCAM) or every 1-3 years from 30-35 (MSH6, PMS2) |
The hamartomatous syndromes are a different family: Peutz-Jeghers (STK11; lip and buccal pigmented macules) and juvenile polyposis (SMAD4 or BMPR1A). Lynch syndrome gets its own breakdown in the Lynch syndrome comparison table.
Practice question
A 17-year-old boy is evaluated for 3 months of intermittent rectal bleeding. His father died of colon cancer at age 38. He has a firm, painless bony swelling of the mandible and several epidermoid cysts on his back, and funduscopy shows multiple flat, darkly pigmented retinal lesions. Colonoscopy shows several hundred adenomatous polyps carpeting the colon and rectum. Which molecular change most directly explains how his polyps form?
A. Accumulation of β-catenin that is no longer targeted for degradation B. Loss of DNA mismatch repair with microsatellite instability C. Failure of base excision repair of oxidative DNA damage D. Loss of the STK11 serine-threonine kinase E. A constitutively active KRAS GTPase
Answer: A. Hundreds of adenomas, a father with colon cancer at 38, Gardner findings (mandibular osteoma, epidermoid cysts) and CHRPE mean FAP. The germline APC defect leaves β-catenin undegraded, so Wnt signaling drives adenoma formation.
- B. Mismatch repair loss: Lynch syndrome causes cancer with few polyps, not hundreds, and lacks osteomas and CHRPE.
- C. Base excision repair failure: MUTYH-associated polyposis is autosomal recessive and usually attenuated; an affected parent plus Gardner features points to dominant APC disease.
- D. STK11 loss: Peutz-Jeghers syndrome causes hamartomatous polyps and pigmented macules on the lips and buccal mucosa.
- E. Activated KRAS: a later, acquired step in adenoma-to-carcinoma progression, not the inherited defect that starts the polyps.
Next steps: plan prophylactic colectomy (dense rectal polyposis favors proctocolectomy with IPAA), begin upper endoscopy by age 20-25 and offer his siblings testing for the family APC variant.
Key takeaways
- FAP = autosomal dominant germline APC mutation (5q21) → β-catenin builds up → over 100 adenomas from the teens → colorectal cancer in nearly all untreated patients by about 40.
- Test at-risk children for the family variant; carriers get yearly colonoscopy from age 10-15, and relatives who test negative return to average-risk screening.
- Prophylactic colectomy is the only effective prevention (IPAA for dense rectal polyps, IRA for milder disease); NSAIDs are not a substitute.
- After colectomy, the main threats are duodenal and periampullary cancer (upper endoscopy from 20-25) and desmoid tumors.
- Gardner = FAP + osteomas, soft-tissue tumors and dental anomalies; Turcot = polyposis + brain tumor (APC → medulloblastoma; mismatch repair → glioblastoma).
- AFAP: about 30 mostly right-sided adenomas, later cancer, usually no CHRPE. MAP: biallelic MUTYH, autosomal recessive. Lynch: mismatch repair defect, few polyps, MSI, endometrial cancer.
Sources
- Genetics of Colorectal Cancer (PDQ) – Health Professional Version — National Cancer Institute (2025)
- Familial Adenomatous Polyposis — Merck Manual Professional Edition (2025)
- Familial adenomatous polyposis — MedlinePlus Genetics
- APC gene — MedlinePlus Genetics
- MUTYH-associated polyposis — MedlinePlus Genetics
- Lynch syndrome — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
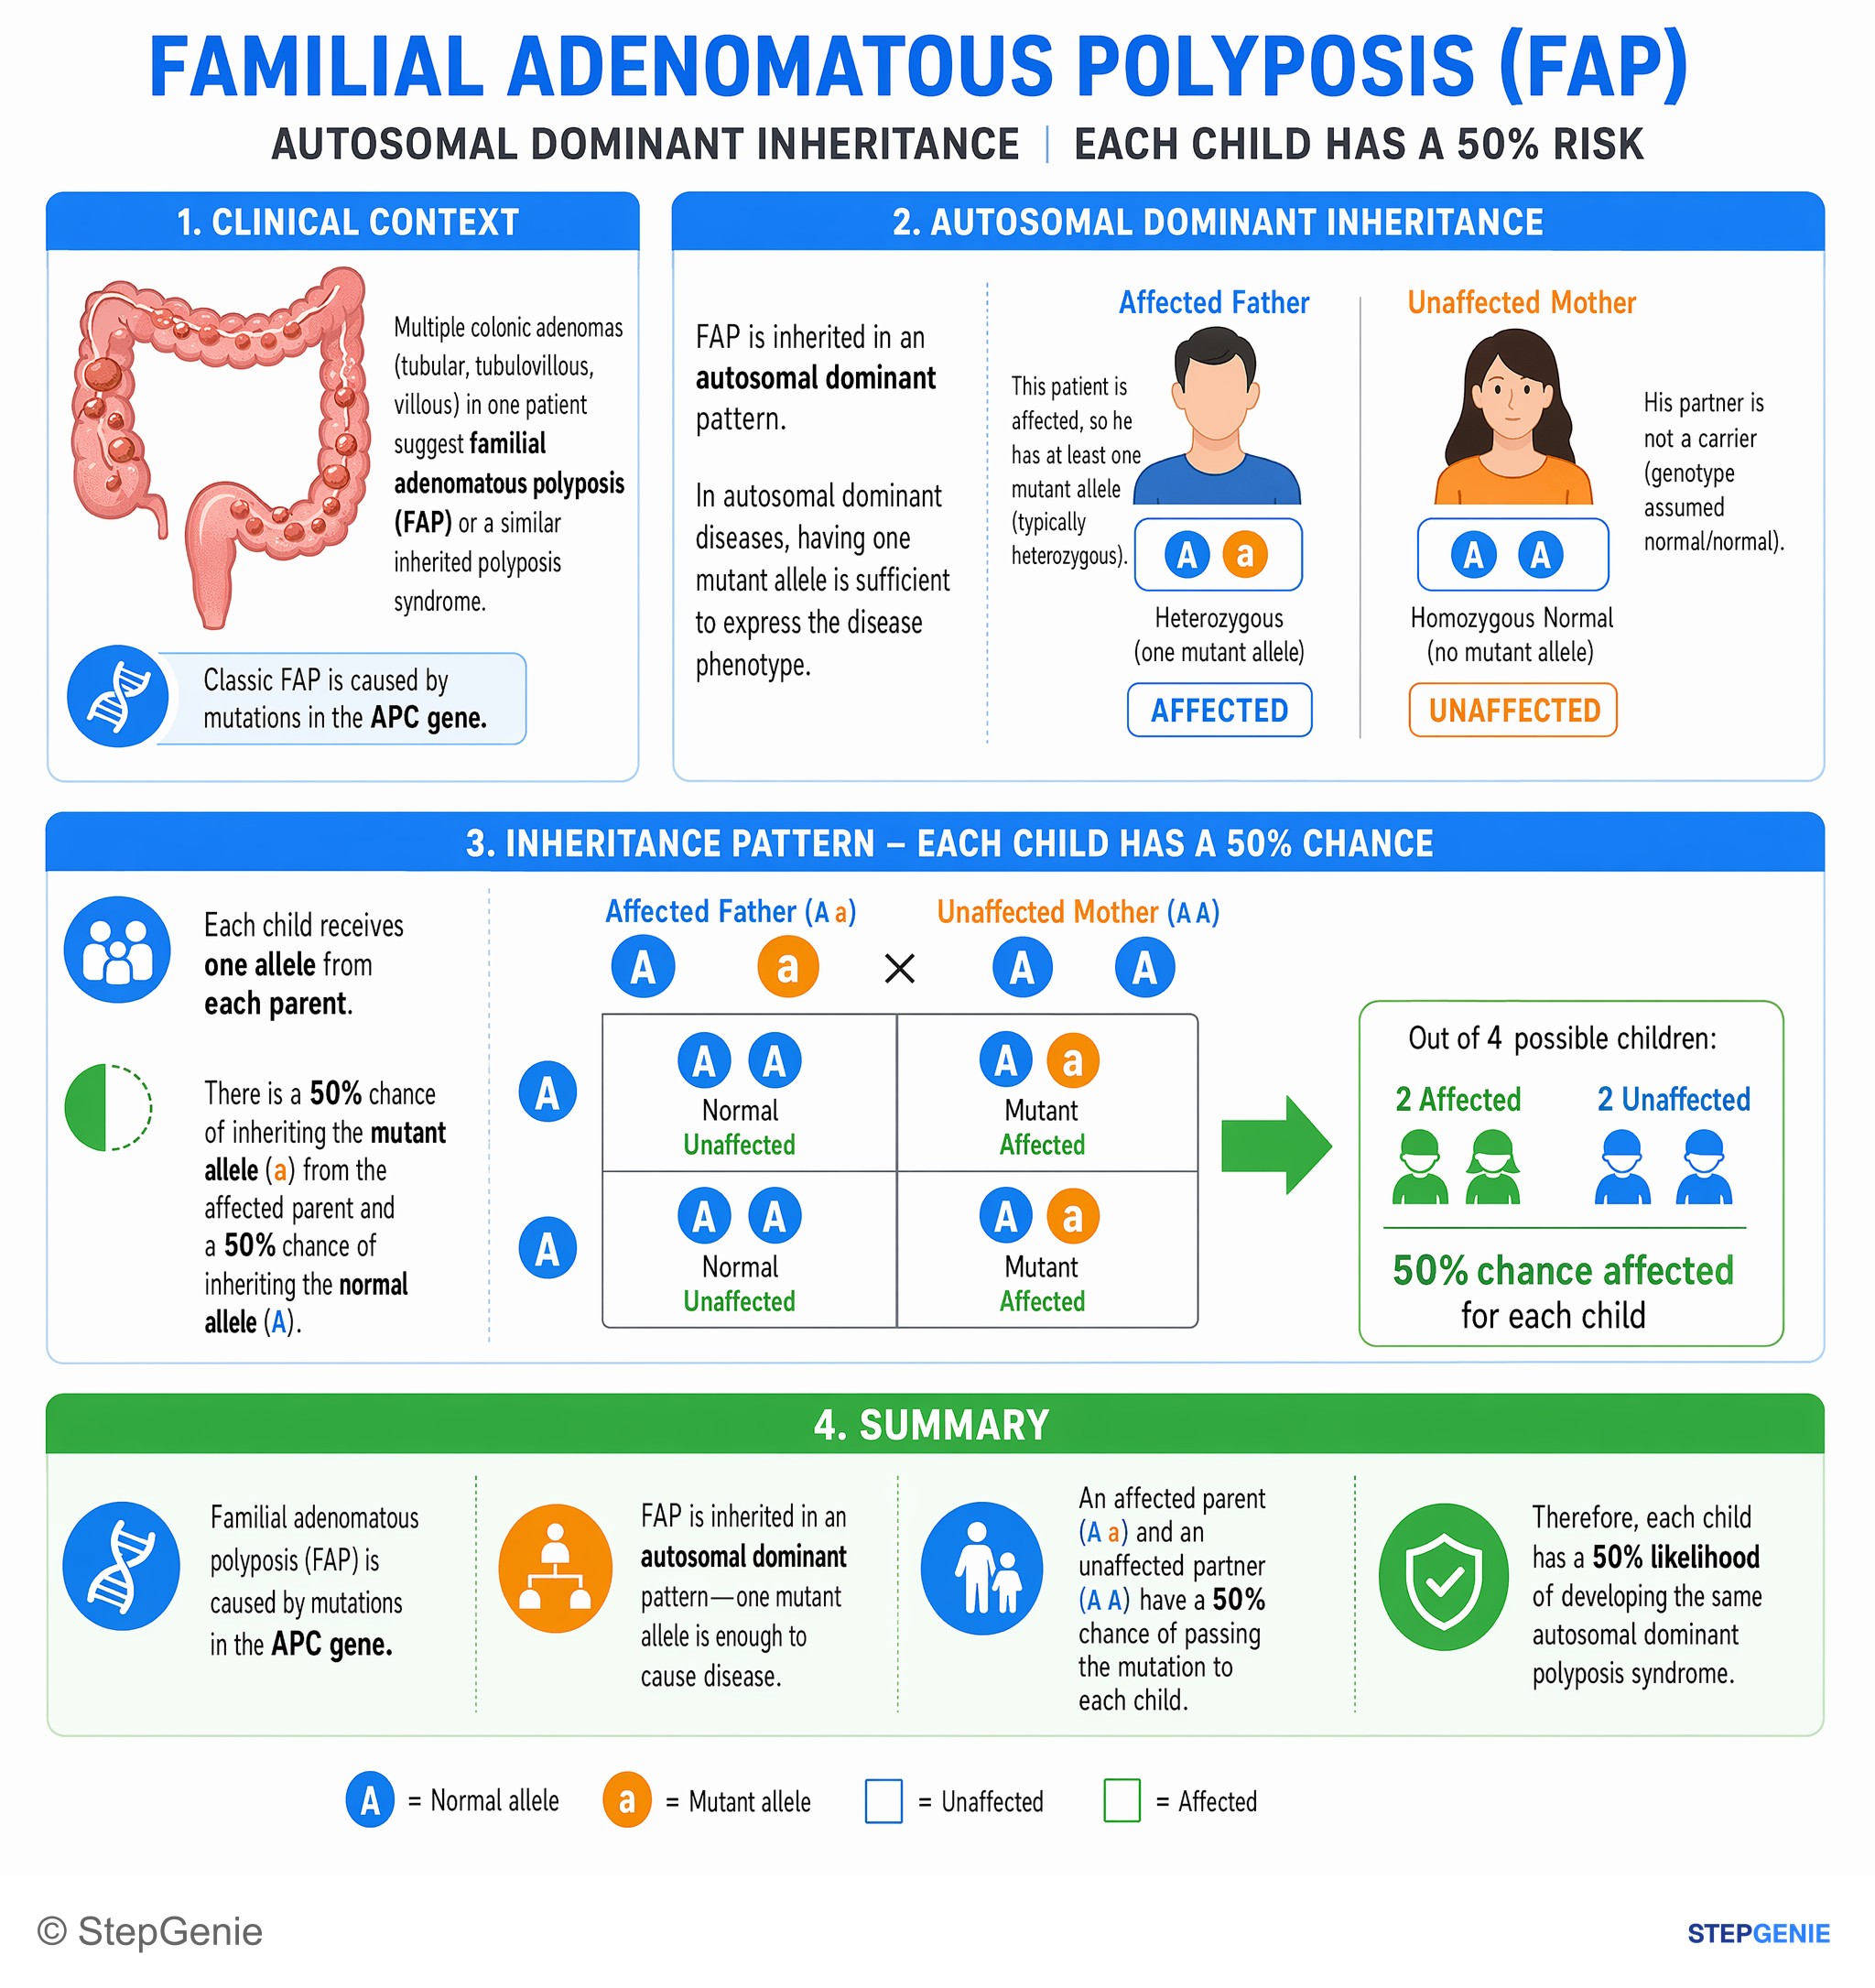
Familial adenomatous polyposis is autosomal dominant; each child of an affected parent has a 50% chance of inheriting the mutation if the…
USMLE Step 1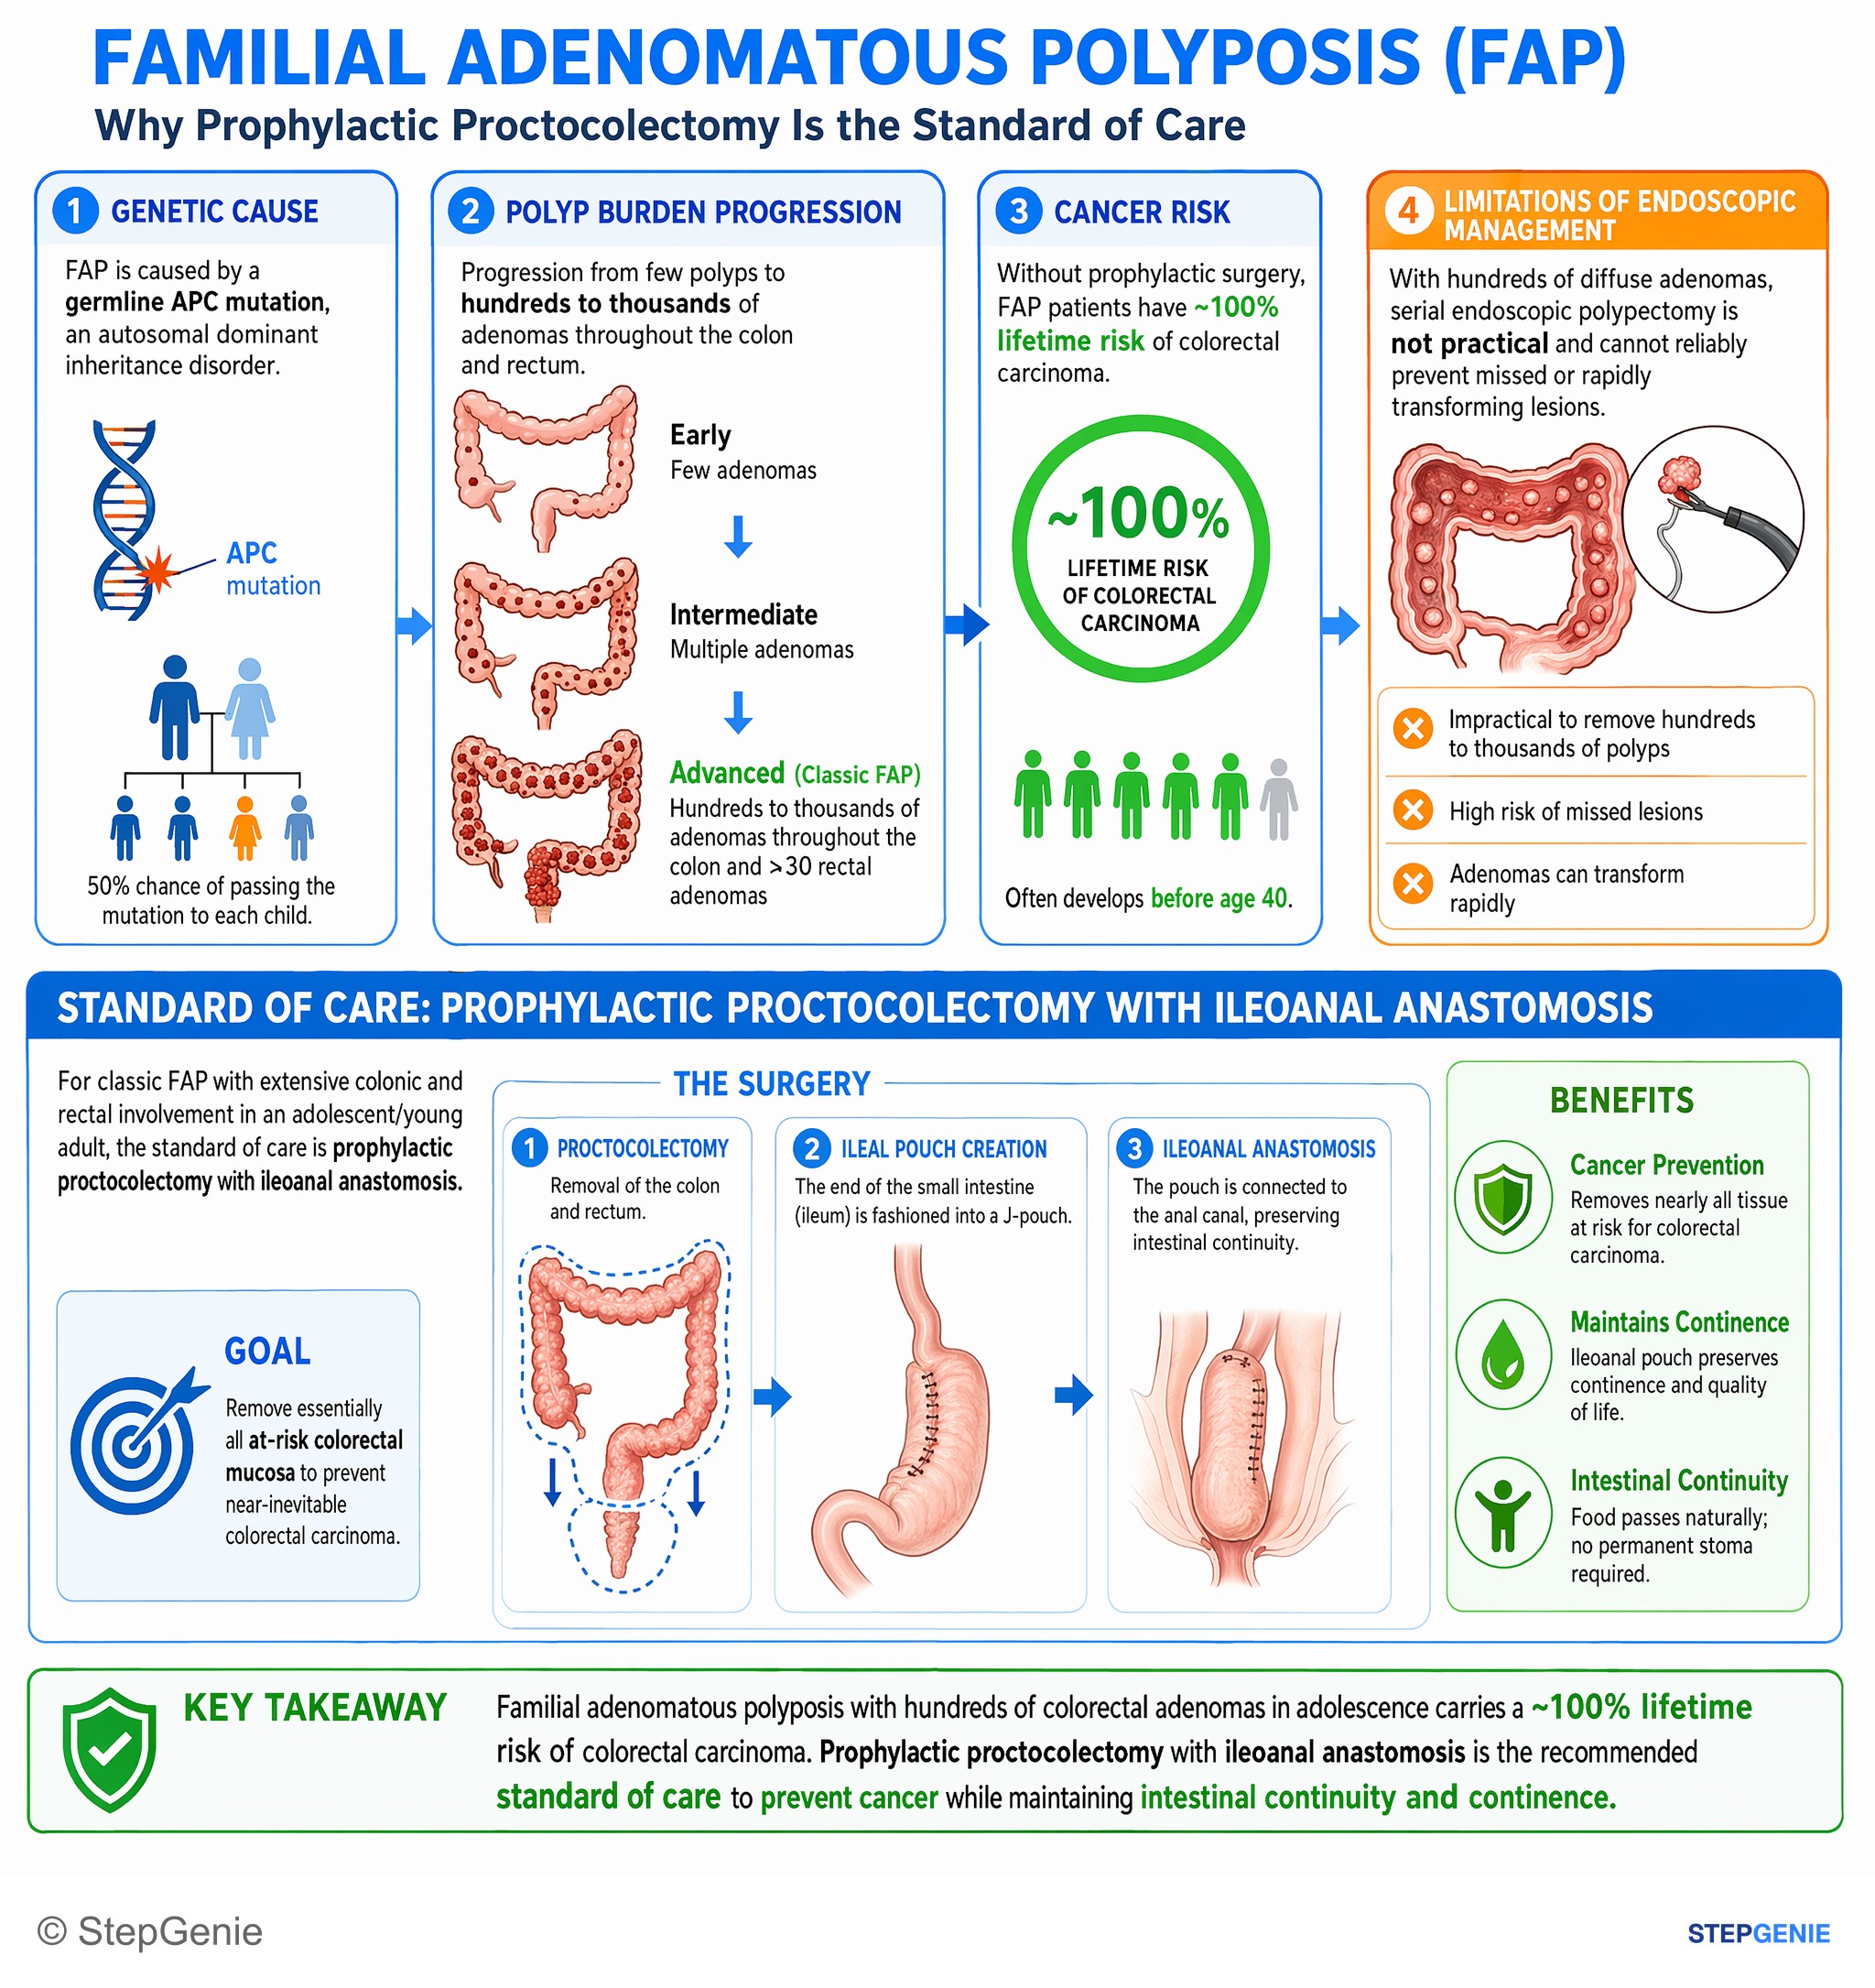
Familial adenomatous polyposis with hundreds of colorectal adenomas in adolescence requires prophylactic proctocolectomy to prevent…
USMLE Step 2Frequently Asked Questions
What gene is mutated in familial adenomatous polyposis?
FAP is caused by a germline mutation in APC, a tumor suppressor gene on chromosome 5q21 that normally helps break down beta-catenin in the Wnt signaling pathway. It is inherited in an autosomal dominant pattern, although about 25% of patients have a new (de novo) mutation. When the remaining normal APC copy is lost in a colon cell, beta-catenin builds up and adenomas form.
At what age should screening for FAP start?
Children who carry the family APC variant, and at-risk children who have not been tested, start colonoscopy between ages 10 and 15 (the NCCN range cited by the National Cancer Institute) and conventionally repeat it every year. Upper endoscopy for duodenal adenomas starts at age 20 to 25, and thyroid ultrasound in the late teens. Relatives who test negative for the family variant follow average-risk screening.
What is the difference between classic FAP and attenuated FAP?
Classic FAP produces more than 100, often thousands, of adenomas starting in adolescence, and nearly all untreated patients develop colorectal cancer by about age 40. Attenuated FAP produces fewer adenomas (about 30 on average), mostly in the right colon and appearing in the mid-to-late 20s, and cancer is diagnosed at an average age of 56. People with attenuated FAP usually lack CHRPE and are screened with colonoscopy every 1 to 2 years from the late teens.
When is colectomy done for FAP, and which operation is used?
Once polyps are too numerous or advanced to control endoscopically, prophylactic colectomy is the only effective way to prevent colorectal cancer; the timing is individualized by polyp number, size, histology and symptoms. Proctocolectomy with an ileal pouch-anal anastomosis is chosen when the rectum is densely involved, while colectomy with ileorectal anastomosis suits milder disease with fewer than 20 rectal adenomas. Either way, the remaining rectum or pouch needs lifelong endoscopic surveillance.
What are Gardner syndrome and Turcot syndrome?
Gardner syndrome is FAP with prominent osteomas, soft-tissue tumors such as epidermoid cysts and desmoids, and dental anomalies. It is caused by the same APC mutations, so the name is now largely historical. Turcot syndrome is colonic polyposis or cancer with a brain tumor: APC mutations go with medulloblastoma, whereas mismatch repair gene mutations (Lynch syndrome) go with glioblastoma.
How is FAP different from Lynch syndrome and MUTYH-associated polyposis?
FAP is autosomal dominant, caused by APC mutations, and produces hundreds to thousands of adenomas. Lynch syndrome is also autosomal dominant but is caused by mismatch repair gene mutations, produces few polyps, shows microsatellite instability and carries a high risk of endometrial cancer. MUTYH-associated polyposis is autosomal recessive, caused by variants in both copies of the base excision repair gene MUTYH, and usually looks like attenuated FAP.