Pancreatic cancer is one of those Step 1 topics that shows up in deceptively simple vignettes—painless jaundice, weight loss, a smoker with new-onset diabetes, or migratory thrombophlebitis—and you’re expected to instantly localize the tumor, name the risk factor, and predict the next diagnostic step. This post is your high-yield, mechanism-first roadmap to mastering it.
Quick Definition (Step-Style)
Pancreatic cancer usually refers to pancreatic ductal adenocarcinoma (PDAC)—a malignant tumor arising from the exocrine ducts of the pancreas.
- Most common type: Ductal adenocarcinoma
- Typical location: Head of the pancreas (clinically important because of biliary obstruction)
- Big picture: late presentation → early metastasis → poor prognosis
First Aid cross-reference: GI Pathology → Pancreas → Pancreatic carcinoma (check the Pancreas section + cancer risk factors pages in your edition)
High-Yield Anatomy: Why “Head” Tumors Cause Jaundice
The common bile duct runs through/adjacent to the head of the pancreas before entering the duodenum. So a mass in the pancreatic head can compress the bile duct → extrahepatic (obstructive) cholestasis.
Classic consequence
- Painless jaundice + dark urine + pale stools + pruritus
- Palpable, nontender gallbladder from back-up (Courvoisier sign)
Pathophysiology (What Step 1 Actually Tests)
Cell of origin + precursor lesions
Pancreatic ductal adenocarcinoma often arises from PanIN lesions (pancreatic intraepithelial neoplasia) via stepwise genetic hits.
Key molecular associations (high yield)
A classic progression you’ll see tested:
| Gene | Role | HY association |
|---|---|---|
| KRAS | Oncogene (signal transduction) | Early event; promotes proliferation |
| CDKN2A (p16) | Tumor suppressor (cell cycle brake) | Loss → unchecked G1→S |
| TP53 | Tumor suppressor (DNA damage response) | Late event; genomic instability |
| SMAD4 (DPC4) | TGF-β signaling tumor suppression | Loss → growth disinhibition |
First Aid cross-reference: General Path → Oncogenes & Tumor Suppressor Genes + GI Path → Pancreas
Tumor markers (board-appropriate nuance)
- CA 19-9: often elevated in pancreatic adenocarcinoma
- Useful for tracking response/recurrence, not a screening test (imperfect sensitivity/specificity)
- Can be falsely low in patients who are Lewis antigen negative (rare but classically testable)
Risk Factors & Associations (Memorize These)
Major risk factors (HY)
- Smoking (biggest modifiable risk factor)
- Chronic pancreatitis (especially alcohol-related or hereditary)
- Age (older adults)
- Diabetes mellitus (new-onset or worsening—can be a clue and sometimes a consequence)
- Obesity
Genetic syndromes (Step favorites)
- BRCA2 mutation → increased pancreatic cancer risk
- Peutz-Jeghers syndrome (STK11) → increased pancreatic cancer risk (and other GI malignancies)
- Hereditary pancreatitis (PRSS1) → increased risk over time
First Aid cross-reference: GI Path → Pancreas + Genetics → Cancer syndromes
Clinical Presentation: Classic Vignette Patterns
1) Tumor in the head: obstructive jaundice picture
- Painless jaundice
- Pruritus
- Dark urine (conjugated bilirubin is water-soluble)
- Clay-colored stools
- Palpable gallbladder (Courvoisier sign)
- Weight loss, anorexia
2) Tumor in body/tail: “silent until late”
- Less likely to cause jaundice early
- Presents with:
- Abdominal/back pain
- Weight loss
- Early metastasis signs
3) Paraneoplastic/hypercoagulable clues
- Trousseau syndrome: migratory superficial thrombophlebitis (hypercoagulable state)
- Unprovoked DVT/PE in an older patient → think malignancy
4) New-onset diabetes in an older adult
- Especially with weight loss and smoking history
- Pancreatic cancer can impair endocrine function or drive systemic inflammation/insulin resistance
Diagnosis (Step 1 + Step 2 Workflow)
Labs: cholestatic pattern if obstructing bile duct
- ↑ Direct (conjugated) bilirubin
- ↑ ALP, ↑ GGT
- Mild ↑ AST/ALT possible
Imaging: what’s typically “next best”
- Contrast-enhanced CT (pancreatic protocol) is commonly used for detection and staging.
- Ultrasound may be used early in jaundice workups to detect biliary dilation, but CT is key for pancreas detail.
- Endoscopic ultrasound (EUS) with biopsy is often used for tissue diagnosis.
ERCP: when it matters
- Can help with biliary decompression/stenting in obstructive jaundice
- May be used diagnostically, but often thought of as therapeutic in modern algorithms
Gross & Histology (Board-Recognizable)
Gross findings
- Firm, ill-defined mass, often in head of pancreas
- Can cause biliary obstruction
Histology
- Adenocarcinoma with glandular structures
- Desmoplastic stroma (dense fibrous tissue reaction—classically mentioned)
First Aid cross-reference: GI Path → Pancreas (histology clues)
Treatment (What You Need for Boards)
Curative intent (if localized and resectable)
- Surgical resection
- Whipple procedure (pancreaticoduodenectomy) for tumors in the head
- Often combined with adjuvant chemotherapy (and sometimes radiation depending on case)
Unresectable/metastatic disease
- Systemic chemotherapy (regimens vary)
- Palliation
- Biliary stenting to relieve jaundice/pruritus
- Pain management, nutritional support
Prognosis (know the headline)
- Overall poor because most cases present late.
- If you see “painless jaundice + weight loss” on a test, assume malignancy until proven otherwise.
High-Yield Differentials (Don’t Get Tricked)
| Condition | Key clue | How it differs from pancreatic adenocarcinoma |
|---|---|---|
| Chronic pancreatitis | Recurrent epigastric pain, calcifications, malabsorption | Pain often longstanding; not typically painless jaundice |
| Pancreatic neuroendocrine tumor (e.g., insulinoma, gastrinoma) | Hormone symptoms (hypoglycemia, refractory ulcers) | Different cell origin; different syndromic associations (MEN1) |
| Cholangiocarcinoma | Biliary tree primary tumor | May present similarly with obstructive jaundice; location differs |
| Gallstone obstruction | Colicky RUQ pain, transient obstruction | Painful; often episodic; stones on imaging |
| Pancreatic pseudocyst | After pancreatitis; elevated amylase; cystic lesion | Post-inflammatory, not malignant; mass effect possible but context is key |
HY “If You See This, Think Pancreatic Cancer” Associations
Ultra-classic cues
- Painless jaundice + palpable gallbladder → tumor in head
- Migratory thrombophlebitis (Trousseau) → mucin-producing adenocarcinoma (pancreas is a classic)
- Smoker + weight loss + epigastric pain radiating to back
- New-onset diabetes in an older adult with systemic symptoms
Biochem tie-in
- Obstructive jaundice → conjugated hyperbilirubinemia → dark urine, pale stool, ↑ALP/↑GGT
Rapid Review Table (Last-Minute Step 1 Crunch)
| Category | Must-know facts |
|---|---|
| Most common type | Pancreatic ductal adenocarcinoma |
| Most common location | Head of pancreas |
| Key presentation | Painless jaundice, weight loss |
| Major risk factor | Smoking |
| Genetics | KRAS, p16, TP53, SMAD4 |
| Marker | CA 19-9 (monitoring, not screening) |
| Hypercoagulability | Trousseau syndrome |
| Diagnosis | CT (pancreatic protocol), EUS biopsy |
| Treatment | Whipple if resectable; chemo/palliation if not |
| Prognosis | Poor (late detection) |
First Aid Cross-Reference Checklist (Use This to Anchor Your Review)
When you’re flipping through First Aid, make sure you can connect pancreatic cancer to:
- Obstructive jaundice physiology (bilirubin handling, cholestasis labs)
- Oncogene/tumor suppressor gene list (KRAS, p53, p16, SMAD4)
- Cancer-associated thrombosis (Trousseau)
- Chronic pancreatitis complications (increased cancer risk)
- CA 19-9 clinical use (trend marker)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
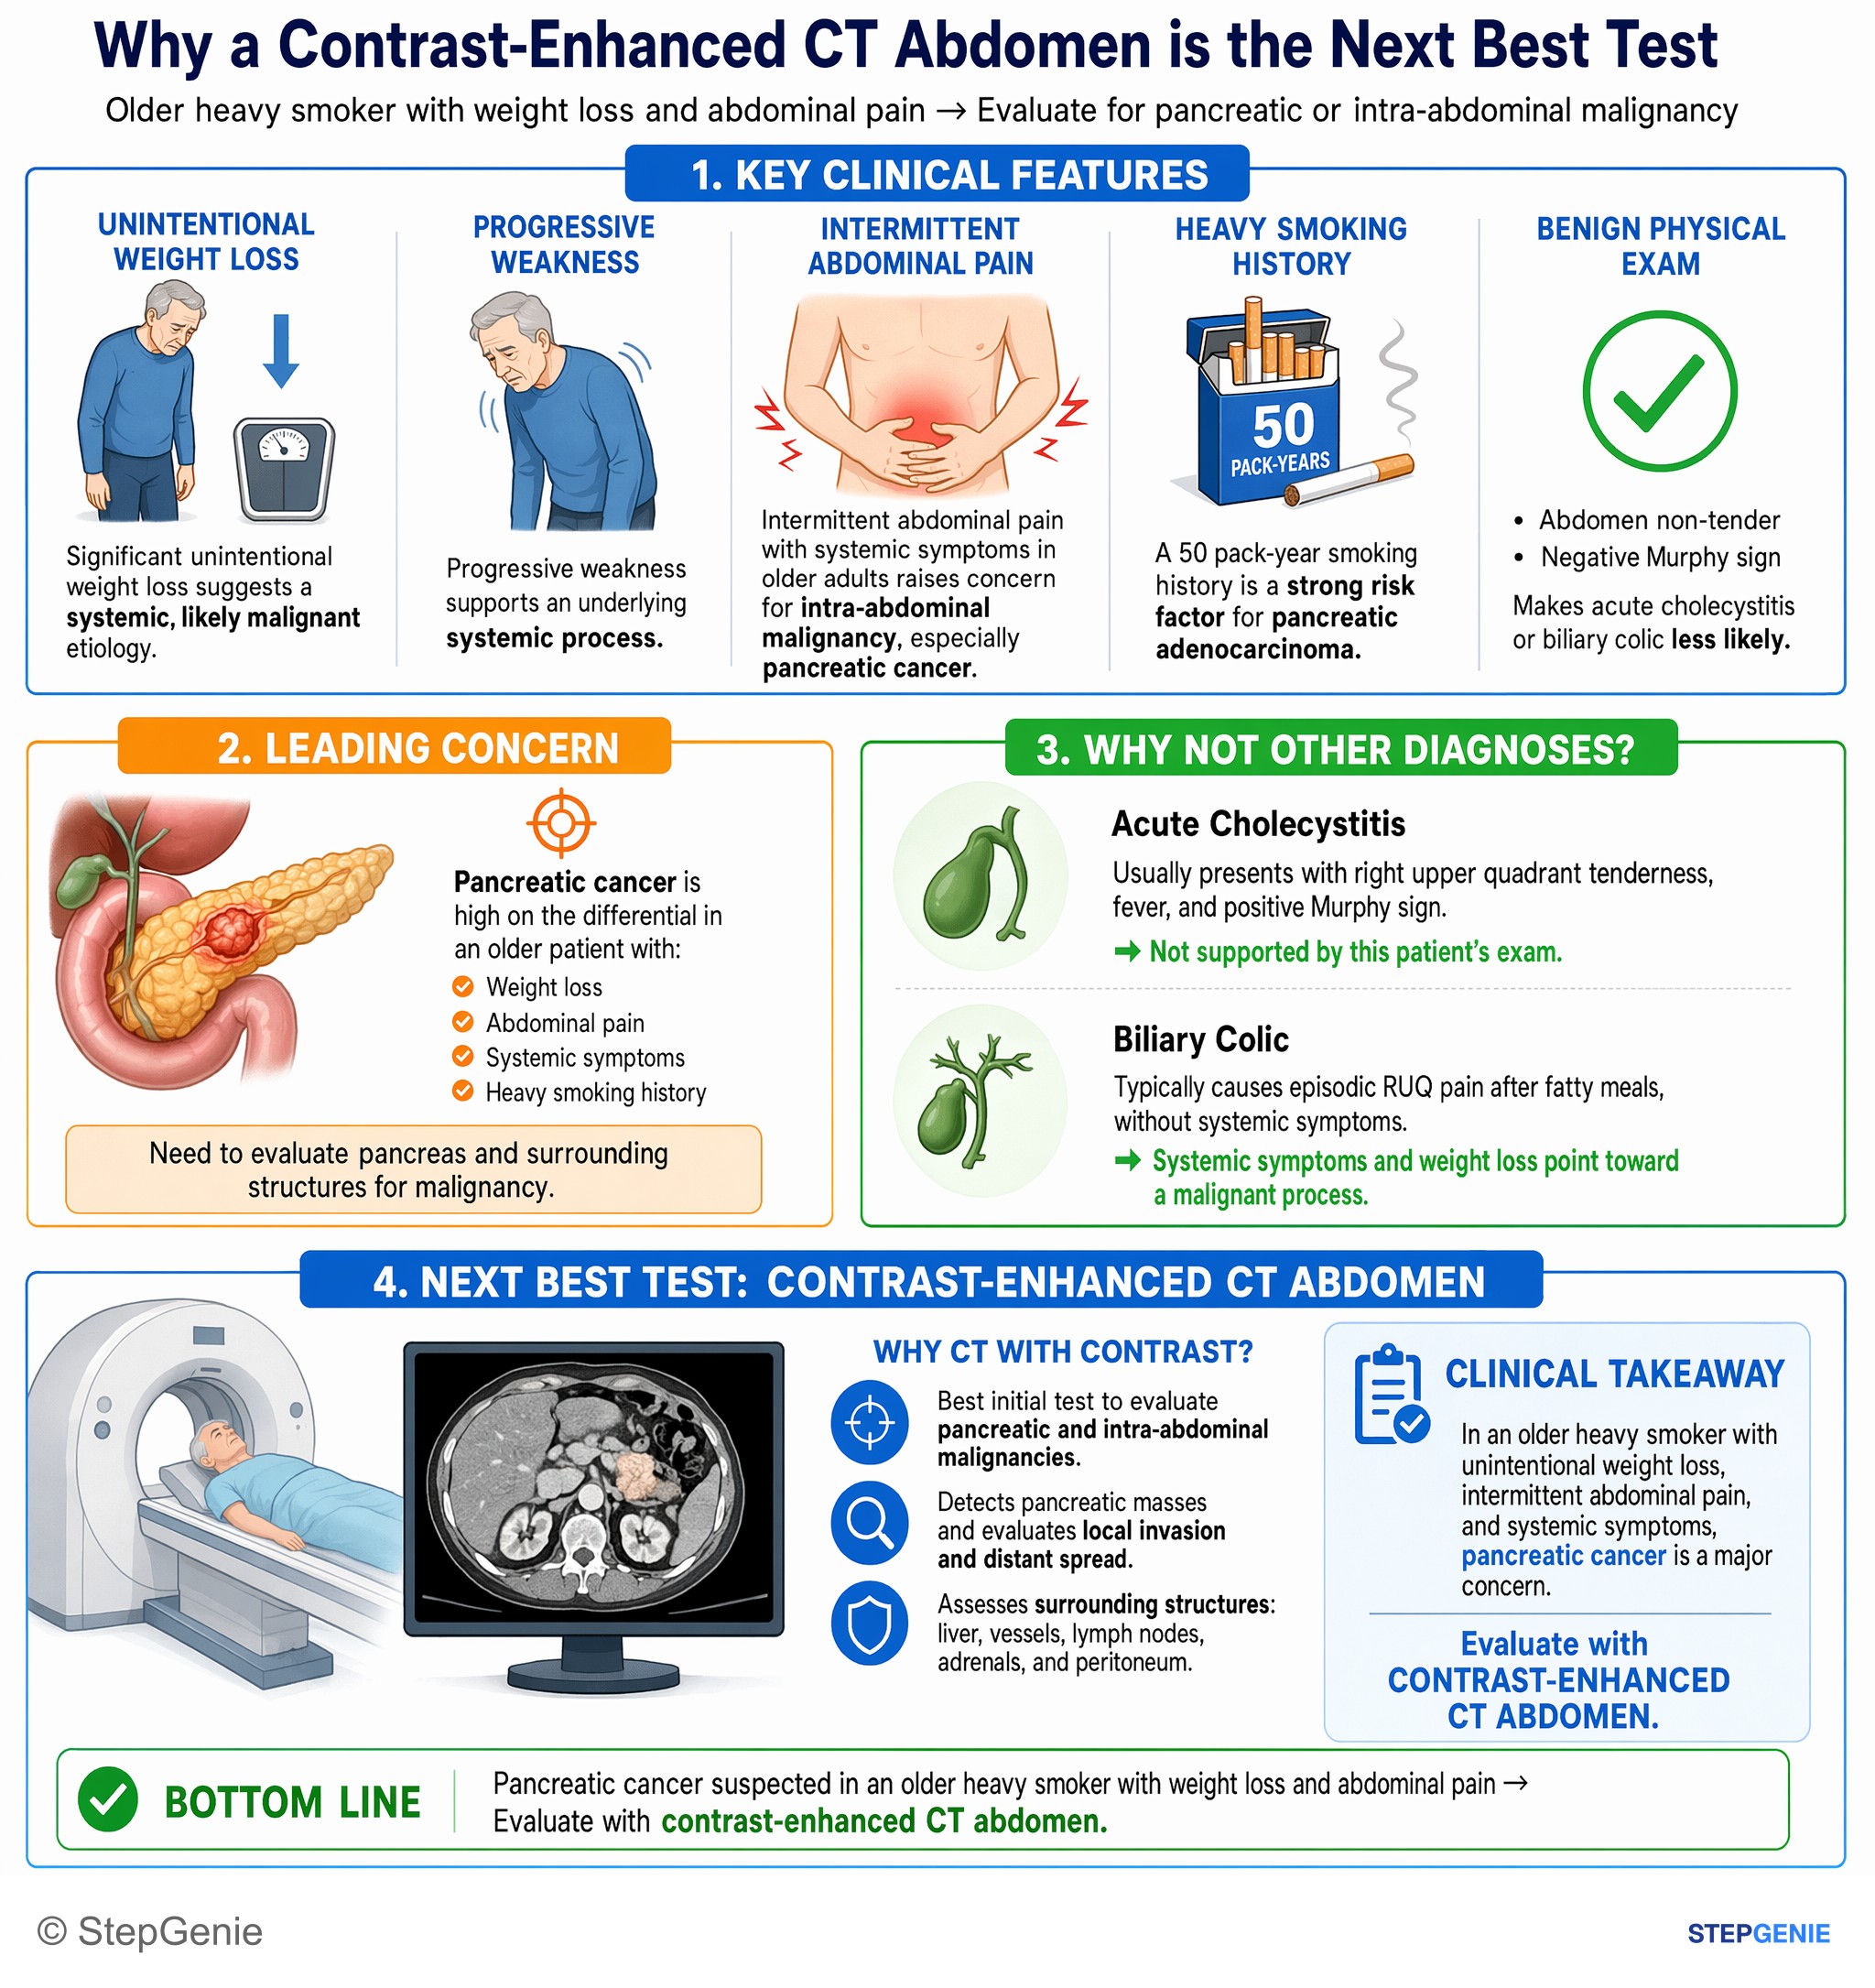
Pancreatic cancer suspected in an older heavy smoker with weight loss and abdominal pain → evaluate with contrast-enhanced CT abdomen.
USMLE Step 2Frequently Asked Questions
Why does pancreatic cancer in the head of the pancreas cause painless jaundice?
A tumor in the pancreatic head can cause painless obstructive jaundice by compressing the common bile duct. The bile duct runs through or adjacent to the head of the pancreas before entering the duodenum, so a mass there blocks bile flow and produces extrahepatic cholestasis. Classic clues include dark urine, pale or clay-colored stools, pruritus, and sometimes a palpable, nontender gallbladder called Courvoisier sign.
What are the classic Step 1 clues for pancreatic adenocarcinoma?
The classic clues are painless jaundice, weight loss, smoking history, new-onset diabetes, and migratory thrombophlebitis. Pancreatic ductal adenocarcinoma often appears in straightforward vignettes that expect recognition of these findings. Head tumors cause obstructive jaundice, while body or tail tumors are more likely to present later with abdominal or back pain and signs of early metastasis rather than jaundice.
How do you tell pancreatic head cancer from body or tail cancer on a vignette?
Pancreatic head cancer usually presents with obstructive jaundice, while body or tail cancer is more silent early and presents later with pain and weight loss. A head lesion can compress the common bile duct, causing painless jaundice, dark urine, pale stools, pruritus, and sometimes a palpable gallbladder. Body or tail tumors are less likely to cause jaundice early and more often show abdominal or back pain instead.
What is the next best imaging test for suspected pancreatic cancer?
Contrast-enhanced CT with a pancreatic protocol is commonly the key next imaging test for detecting and staging pancreatic cancer. Ultrasound may be used early in a jaundice workup to look for biliary dilation, but CT provides the important pancreatic detail. Endoscopic ultrasound with biopsy is often used for tissue diagnosis, and ERCP is especially useful for biliary decompression or stenting in obstructive jaundice.
Is CA 19-9 used to screen for pancreatic cancer?
No, CA 19-9 is not used as a screening test for pancreatic cancer. Although it is often elevated in pancreatic adenocarcinoma, it is more useful for tracking treatment response or recurrence because its sensitivity and specificity are imperfect. It can also be falsely low in patients who are Lewis antigen negative, which is a classic limitation to remember for exams.