Cholangiocarcinoma is one of those Step 1 “biliary tree” diagnoses that loves to masquerade as more common causes of obstructive jaundice—until you zoom in on the risk factors (PSC, liver flukes), the imaging (biliary strictures), and the tumor marker patterns. If you can quickly separate cholangiocarcinoma from pancreatic adenocarcinoma, gallstones, and hepatocellular carcinoma (HCC), you’ll pick up easy points on both vignettes and pathology questions.
Definition (What it is)
Cholangiocarcinoma is a malignant tumor of the biliary epithelium (cholangiocytes) arising from:
- Intrahepatic bile ducts
- Extrahepatic bile ducts
- Perihilar region (Klatskin tumor) at the hepatic duct confluence (right + left hepatic ducts)
Core concept: It’s a bile duct cancer, not a hepatocyte cancer (that’s HCC).
Where it fits on your Step “map” (First Aid cross-reference)
In First Aid terms, you’ll see cholangiocarcinoma show up under:
- GI pathology → liver & biliary tract tumors
- Association with PSC and ulcerative colitis
- Parasitic infection association (Clonorchis/Opisthorchis)
If you’re using FA as your spine: mentally link it to the pages where PSC, UC, Charcot triad, and cholestatic labs are discussed.
Pathophysiology (How it happens)
Cholangiocarcinoma classically arises in the setting of chronic inflammation and cholestasis, which drives:
- Repeated epithelial injury
- Bile duct fibrosis/strictures
- Dysplasia → carcinoma
High-yield risk factors (memorize these)
Most testable associations:
- Primary sclerosing cholangitis (PSC)
- Strongly associated with ulcerative colitis
- Causes multifocal strictures (“beading”) and sets up chronic injury
- Liver flukes
- Clonorchis sinensis (East Asia)
- Opisthorchis viverrini (SE Asia)
Chronic infestation → chronic inflammation → malignancy
- Fibropolycystic liver disease (e.g., choledochal cysts, Caroli disease)
- Thorotrast exposure (historical radiographic contrast; rare but classic board fact)
- Hepatolithiasis (intrahepatic stones; more common in some Asian populations)
Step framing: If a vignette gives PSC + UC + obstructive jaundice, cholangiocarcinoma should jump near the top.
Anatomy + “Klatskin tumor” pearl
Perihilar (Klatskin) tumors
- Located at the bifurcation of the common hepatic duct
- Often cause painless obstructive jaundice
- May be harder to stent/drain due to location at the confluence
Board-style clue: “Perihilar mass” or “bile duct confluence” + cholestatic labs = Klatskin.
Clinical presentation (How it shows up)
Most presentations are due to biliary obstruction.
Common symptoms/signs
- Painless jaundice
- Pruritus (bile salt deposition)
- Dark urine (conjugated bilirubin)
- Pale/clay-colored stools
- Weight loss, anorexia
- RUQ discomfort (less common than in gallstone disease)
Cholangitis can occur (especially with obstruction)
If obstruction becomes infected, you can get:
- Charcot triad: fever + jaundice + RUQ pain
- Reynolds pentad: Charcot triad + hypotension + altered mental status
Step trap: Charcot triad classically screams ascending cholangitis, but the underlying obstruction can be a stone or a tumor (including cholangiocarcinoma).
Labs (pattern recognition)
Think cholestatic.
| Lab | Expected trend | Why it matters |
|---|---|---|
| Alkaline phosphatase (ALP) | ↑↑ | Cholestasis marker |
| GGT | ↑ | Confirms biliary source of ↑ALP |
| Direct (conjugated) bilirubin | ↑ | Obstruction prevents excretion |
| AST/ALT | mild ↑ | Can be variable, usually not the main feature |
Tumor markers
- CA 19-9: often elevated (not specific; also pancreatic adenocarcinoma)
- CEA: may be elevated (nonspecific)
High-yield nuance: Tumor markers are supportive, not diagnostic—Step questions like to see cholestatic labs + imaging findings + risk factors.
Diagnosis (What to order and what you’ll see)
First-line imaging (often vignette-based)
- RUQ ultrasound
- Can show biliary ductal dilation (suggests obstruction)
- May not directly visualize the tumor depending on location
Better characterization
- MRCP (noninvasive): maps biliary tree, identifies strictures/obstruction pattern
- ERCP (invasive): diagnostic + therapeutic
- Brush cytology/biopsy
- Stenting to relieve obstruction
“Classic” imaging description
- Multifocal strictures and dilation may be present when PSC coexists (“beading”), but cholangiocarcinoma itself can present as:
- A dominant stricture
- A mass lesion
- Progressive obstruction
Tissue diagnosis
- Often via ERCP brushings/biopsy, sometimes EUS-guided sampling depending on location.
Pathology (what they can test)
- Adenocarcinoma arising from biliary epithelium
- Desmoplastic stroma is common in many GI adenocarcinomas (board-friendly word)
- Can produce mucin (variable)
Big picture: It’s an epithelial malignancy—contrast with HCC (malignant hepatocytes) and neuroendocrine tumors.
Treatment (Step 1/2 level)
Management depends heavily on resectability and location.
Potentially curative
- Surgical resection if localized and technically resectable
- In select perihilar cases: liver transplant protocols may be considered (highly specialized)
Palliative/adjunctive
- Biliary drainage/stenting (often via ERCP) to relieve cholestasis and pruritus
- Chemotherapy (e.g., gemcitabine-based regimens) and sometimes radiation depending on staging and protocols
- Symptom control:
- Cholestyramine for pruritus (binds bile acids)
- Fat-soluble vitamin supplementation if prolonged cholestasis (A, D, E, K)
Step 2 clinical angle: Many patients present late → focus is often on relieving obstruction and managing complications (cholangitis, malabsorption, pruritus).
Prognosis (what to remember)
- Often diagnosed late
- Prognosis is generally poor, especially if unresectable or metastatic
- Earlier detection is more likely in patients under surveillance for PSC
High-yield associations & classic vignette triggers
1) PSC + UC → cholangiocarcinoma
- Middle-aged man with UC history
- Progressive cholestatic labs, pruritus, painless jaundice
- Imaging shows strictures (often described with PSC context)
2) Liver flukes → cholangiocarcinoma
- Immigrant/traveler from endemic region
- RUQ pain or jaundice + cholestatic labs
- History of raw/undercooked fish (classically discussed for Clonorchis)
3) Obstructive jaundice differential sorting
Use this quick discriminator:
| Condition | Classic clue | Typical key association |
|---|---|---|
| Cholangiocarcinoma | Painless jaundice, cholestatic labs, biliary strictures/mass | PSC, UC, flukes |
| Pancreatic adenocarcinoma | Painless jaundice + Courvoisier sign (nontender palpable gallbladder) | Smoking, chronic pancreatitis |
| Choledocholithiasis | Episodic RUQ pain, postprandial, may trigger pancreatitis | Gallstones, biliary colic |
| Ascending cholangitis | Fever + jaundice + RUQ pain (Charcot triad) | Obstruction + infection |
| HCC | Cirrhosis + weight loss, RUQ pain, ↑AFP | HBV/HCV, alcohol, aflatoxin |
Rapid-fire USMLE “must know” bullets
- Cholangiocarcinoma = bile duct adenocarcinoma.
- PSC is the classic predisposing condition, and PSC is strongly associated with ulcerative colitis.
- Presents with obstructive jaundice: ↑ALP, ↑GGT, ↑direct bilirubin, pruritus.
- CA 19-9 can be elevated, but it’s not specific.
- MRCP maps strictures; ERCP can diagnose and relieve obstruction (stent).
- Klatskin tumor = perihilar cholangiocarcinoma at the hepatic duct confluence.
- Think about cholangitis as a complication when obstruction becomes infected.
Mini self-check (vignette practice)
A 45-year-old man with long-standing ulcerative colitis develops progressive pruritus and painless jaundice. Labs show markedly elevated ALP and direct bilirubin. MRCP shows multifocal stricturing and a dominant stricture near the hepatic duct confluence. What cancer is he at highest risk for?
→ Cholangiocarcinoma (Klatskin-type location suggested).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
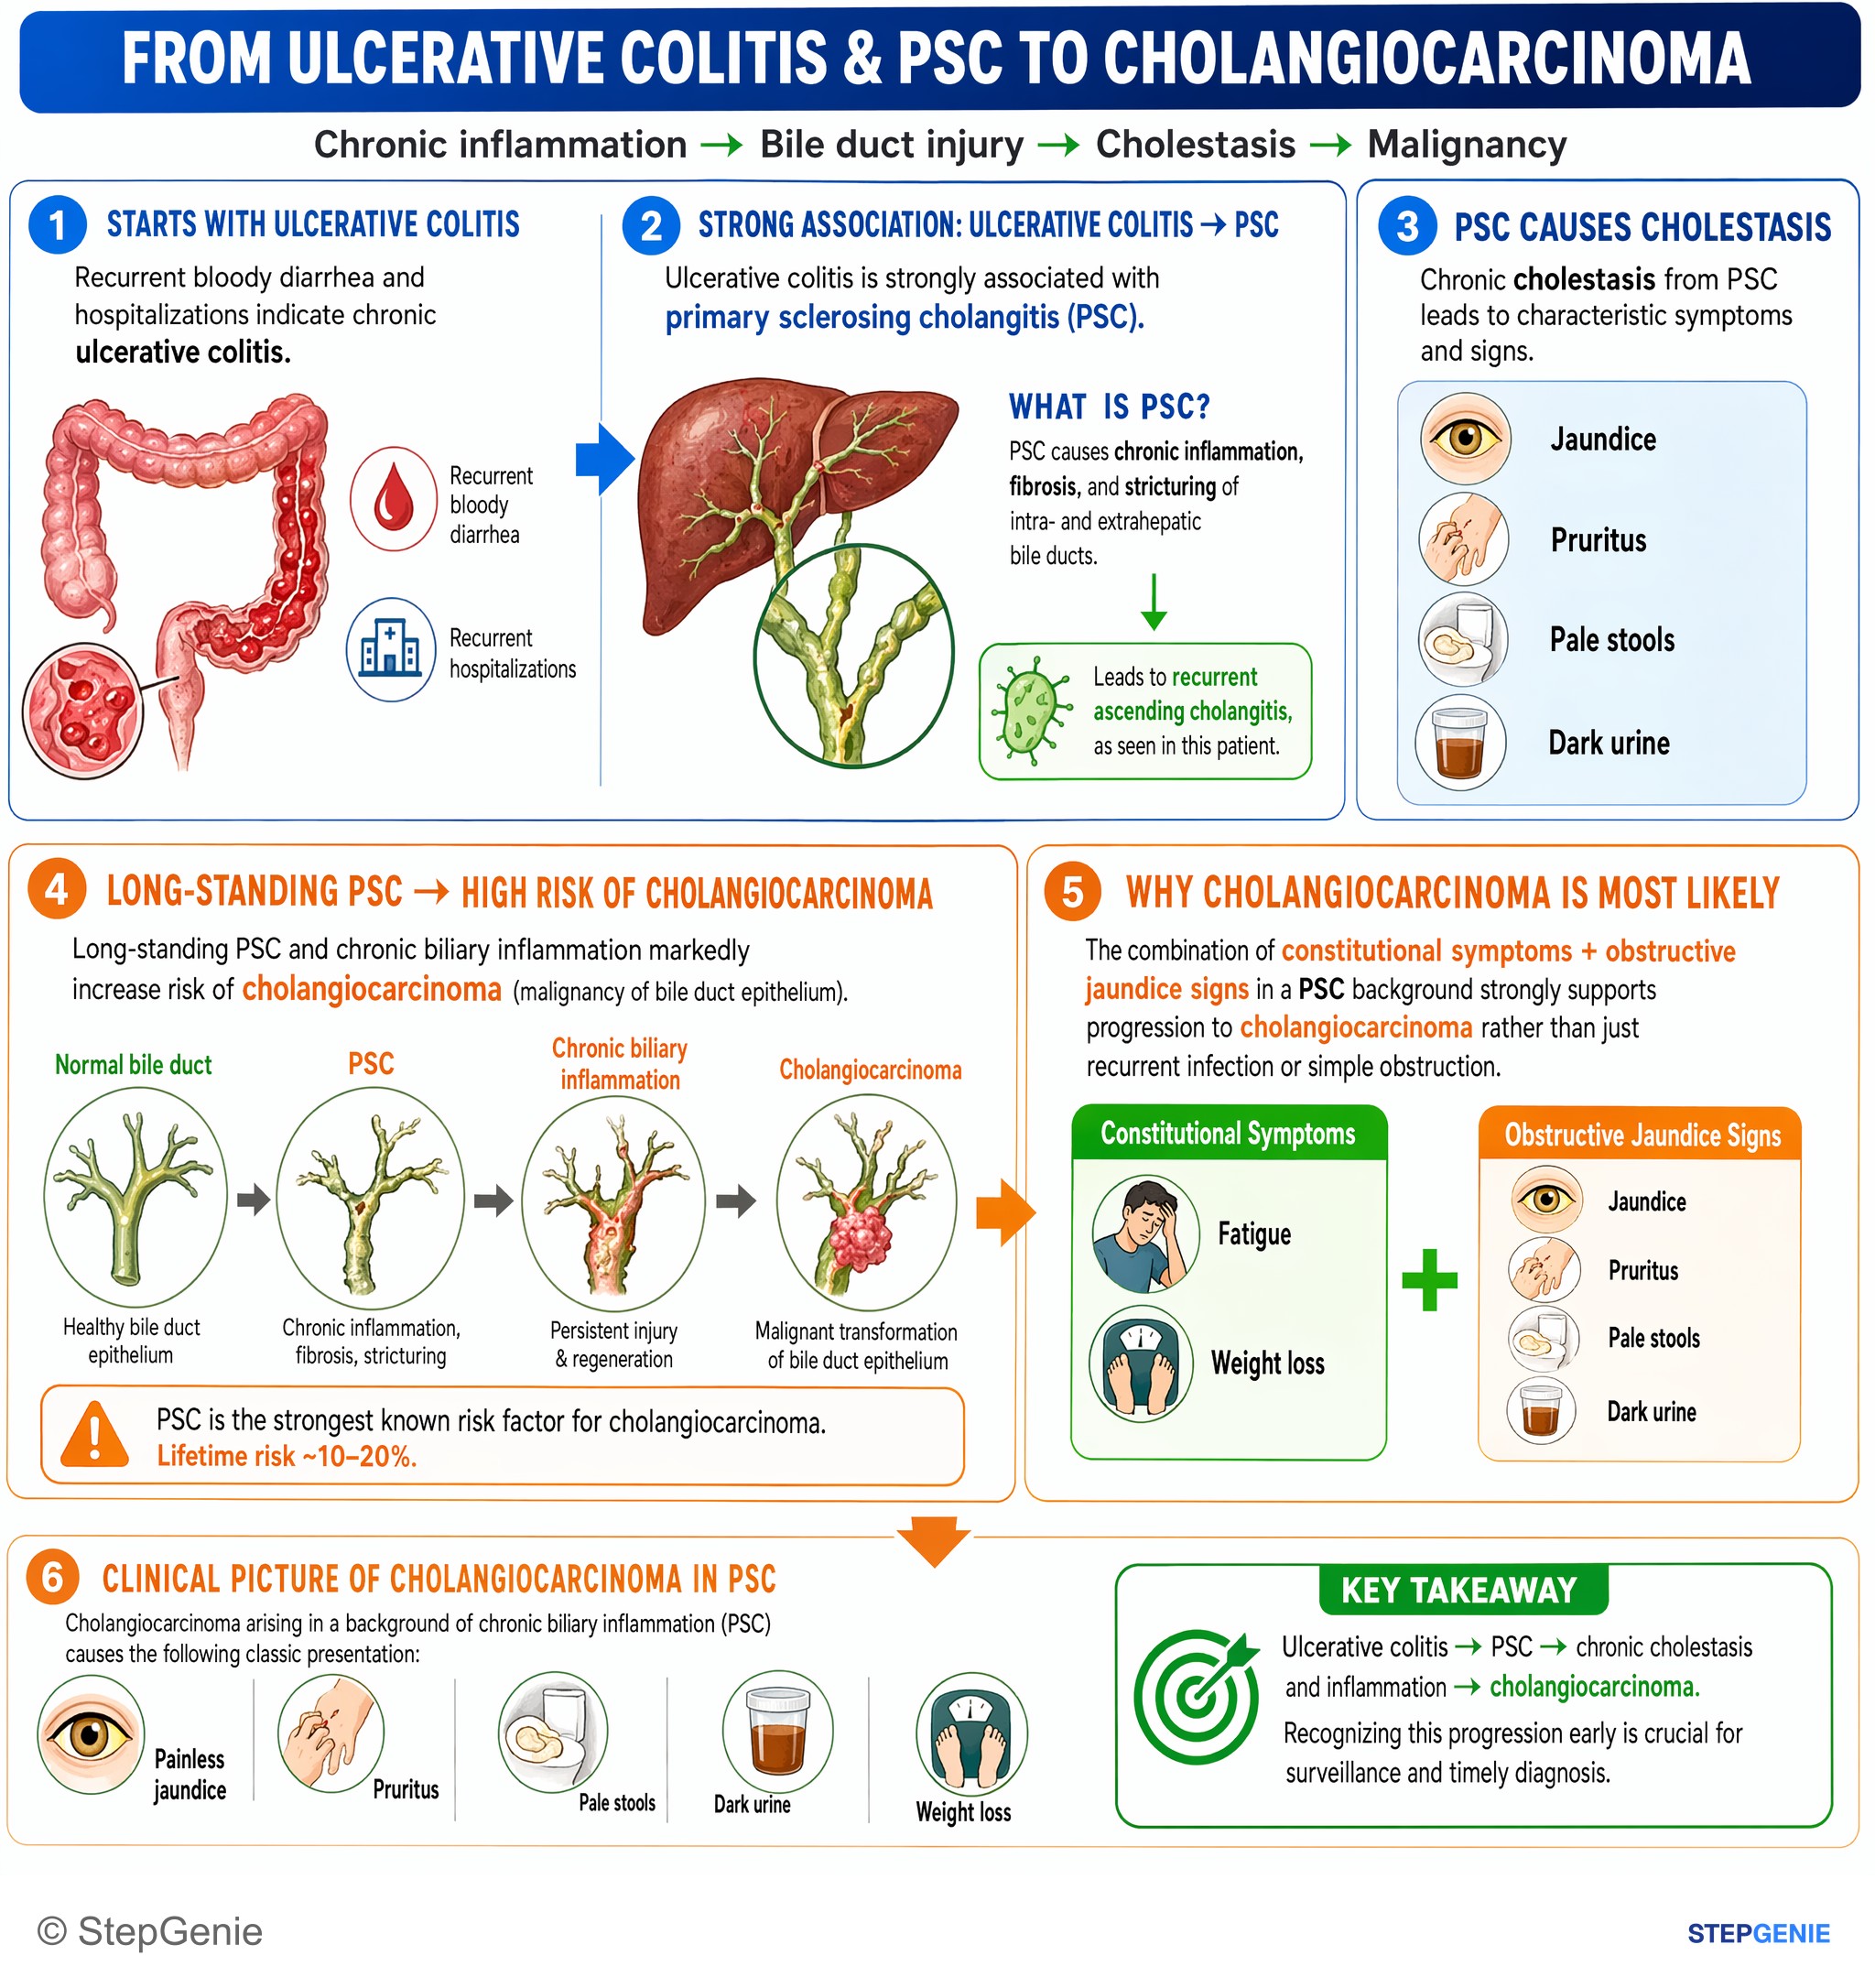
Cholangiocarcinoma arising in a background of chronic biliary inflammation (PSC) causes painless jaundice, pruritus, pale stools, dark…
USMLE Step 2Frequently Asked Questions
How do you tell cholangiocarcinoma from hepatocellular carcinoma on Step 1?
The key distinction is the cell of origin: cholangiocarcinoma is a malignant tumor of the biliary epithelium, while hepatocellular carcinoma is a cancer of hepatocytes. On exam questions, cholangiocarcinoma fits better when the vignette emphasizes obstructive jaundice, cholestatic labs, biliary strictures on imaging, and risk factors such as primary sclerosing cholangitis, ulcerative colitis, or liver fluke infection.
Why does primary sclerosing cholangitis increase the risk of cholangiocarcinoma?
Primary sclerosing cholangitis increases the risk because chronic inflammation and cholestasis repeatedly injure the bile duct epithelium. That ongoing injury leads to fibrosis and strictures, then dysplasia, and eventually carcinoma. This is especially testable when PSC appears together with ulcerative colitis and obstructive jaundice, which should strongly raise suspicion for cholangiocarcinoma.
What are the classic symptoms and lab findings of cholangiocarcinoma?
Cholangiocarcinoma usually presents with painless obstructive jaundice and a cholestatic lab pattern. Common symptoms include pruritus, dark urine, pale or clay-colored stools, weight loss, and sometimes right upper quadrant discomfort. Laboratory studies typically show markedly elevated alkaline phosphatase, elevated GGT, increased direct bilirubin, and only mild AST and ALT elevation, reflecting biliary obstruction rather than primary hepatocyte injury.
What imaging findings suggest cholangiocarcinoma?
Findings that suggest cholangiocarcinoma include biliary ductal dilation on right upper quadrant ultrasound and strictures or obstruction on MRCP or ERCP. The tumor may appear as a dominant stricture, a mass lesion, or progressive obstruction. If primary sclerosing cholangitis coexists, multifocal strictures and dilation can create a beading pattern, which is another high-yield clue in biliary disease questions.
What is a Klatskin tumor and how does it present?
A Klatskin tumor is a perihilar cholangiocarcinoma located at the bifurcation of the common hepatic duct, where the right and left hepatic ducts meet. It classically presents with painless obstructive jaundice and cholestatic laboratory abnormalities. Its location at the bile duct confluence also makes it more difficult to stent or drain, which is a useful board-style anatomical pearl.