Lynch syndrome (hereditary nonpolyposis colorectal cancer, HNPCC) is the most common inherited colorectal cancer syndrome: an autosomal dominant germline defect in a DNA mismatch repair (MMR) gene (MLH1, MSH2, MSH6 or PMS2) or an EPCAM deletion that silences MSH2, so its tumors show microsatellite instability (MSI). It accounts for about 3% of colorectal cancers, which tend to be right-sided and arise from few polyps, and it also causes endometrial cancer (the most common extracolonic cancer) plus ovarian, gastric, small bowel, urothelial, hepatobiliary, pancreatic, brain and sebaceous tumors. Universal tumor screening with immunohistochemistry (IHC) or MSI testing has largely replaced the Amsterdam II and revised Bethesda criteria, and carriers start colonoscopy every 1-2 years at age 20-25 (MLH1, MSH2, EPCAM) or every 1-3 years at 30-35 (MSH6, PMS2) (NCCN 2024, via NCI).
Lynch vs FAP vs MUTYH-associated polyposis
| Lynch syndrome (HNPCC) | FAP | MUTYH-associated polyposis (MAP) | |
|---|---|---|---|
| Gene | MLH1, MSH2, MSH6, PMS2 (mismatch repair); EPCAM deletion silences MSH2 | APC (5q21), tumor suppressor in Wnt/β-catenin signaling | MUTYH: base excision repair of oxidative DNA damage |
| Inheritance | Autosomal dominant, incomplete penetrance | Autosomal dominant | Autosomal recessive |
| Pathway | Microsatellite instability | Chromosomal instability (APC loss first) | Base excision repair failure; acquired KRAS variants common |
| Polyps | Few adenomas: they appear younger, not in greater numbers | Hundreds to thousands from the teens (median onset 16) | Usually 10 to hundreds, often resembling attenuated FAP |
| Colorectal cancer | Risk depends on the gene (table below); 60-70% right-sided; fast adenoma-to-carcinoma progression | Nearly all untreated patients, by about age 40 | High lifetime risk (estimates vary widely); often right-sided and synchronous |
| Extracolonic | Endometrium, ovary, stomach, small bowel, ureter and renal pelvis, hepatobiliary, pancreas, brain (glioblastoma), sebaceous tumors | Duodenal adenomas, desmoids, CHRPE, osteomas, thyroid cancer, hepatoblastoma, medulloblastoma | Duodenal polyps; breast, ovarian, endometrial and bladder cancers reported, excess risk unclear |
| Colonoscopy (NCCN via NCI) | From 20-25 every 1-2 y, or 30-35 every 1-3 y, by gene | From age 10-15 | Every 1-2 y, starting no later than 25-30 |
| Colectomy | Surveillance instead; extended colectomy often favored if a younger carrier develops cancer | Prophylactic, timing individualized | When the adenoma burden can't be controlled endoscopically |
Stem shortcuts: FAP = a teenager with a carpet of polyps; Lynch = a 40-something with a right-sided cancer and a mother with endometrial cancer; MAP = many adenomas in siblings with unaffected parents. More in the familial adenomatous polyposis guide.
Mismatch repair, MSI and the two-hit rule
- What MMR does. MMR proteins fix base-base mismatches and small insertion or deletion loops that form when the polymerase slips on short repeats (microsatellites) during replication. MSH2 pairs with MSH6 (MutSα) to recognize the error; MLH1 pairs with PMS2 (MutLα) to guide excision of the faulty strand. The other repair systems are compared in the DNA repair mechanisms cheat sheet.
- Two hits. Carriers inherit one faulty allele in every cell; a tumor arises once the second allele is lost, so normal tissue still stains for MMR proteins and only the tumor loses them. Not every carrier develops cancer (incomplete penetrance).
- MSI. Without MMR, microsatellites gain or lose repeat units, and the tumor is MSI-high. Histology clues: tumor-infiltrating lymphocytes, a Crohn-like reaction, mucinous or signet-ring differentiation and a medullary growth pattern.
- EPCAM. A deletion at the 3′ end of EPCAM, just upstream of MSH2, causes read-through methylation of the MSH2 promoter, so MSH2 is silenced even though its sequence is normal.
- Treatment payoffs. MSI-high colorectal cancers have better stage-for-stage survival, get no benefit from adjuvant 5-FU alone, and respond to PD-1 blockade; pembrolizumab became first-line therapy for metastatic MSI-high/dMMR disease after the KEYNOTE-177 trial.
- CMMRD trap. Inheriting faulty copies of the same MMR gene from both parents (constitutional MMR deficiency, most often PMS2) causes childhood brain tumors and blood cancers, café-au-lait spots and GI cancers sometimes before 20.
Amsterdam II and revised Bethesda
| Amsterdam II (1999) | Revised Bethesda (2004) | |
|---|---|---|
| Purpose | Define Lynch families; all criteria must be met | Choose colorectal tumors for MSI testing; any one criterion is enough |
| Criteria | 3-2-1-0 rule: 3 or more relatives with a Lynch cancer (colorectal, endometrium, small bowel, ureter or renal pelvis), one a first-degree relative of the other two; 2 generations affected; 1 diagnosed before 50; 0 FAP; tumors confirmed by pathology | Colorectal cancer before 50; synchronous or metachronous Lynch tumors at any age; MSI-high histology before 60; colorectal or Lynch cancer in a first-degree relative before 50; colorectal or Lynch cancer in 2 or more first- or second-degree relatives at any age |
| Weakness | Nearly half of Amsterdam families have no detectable variant, and many carriers don't meet it | Still misses about 30% of Lynch families, and was inconsistently used |
NCI now calls clinical criteria obsolete for people with cancer: universal tumor testing is more sensitive, because many carriers are diagnosed after 50 and have less striking family histories. Criteria and prediction models such as PREMM5 still help triage unaffected relatives.
Universal tumor screening: reading the IHC
Every newly diagnosed colorectal cancer, whatever the patient's age or family history, should have its tumor tested by IHC or MSI (AGA 2015), and universal testing of endometrial cancers is also recommended (NCI). IHC is usually first because the missing protein points to the gene. Hook: the big partner takes the small one down. Losing MLH1 or MSH2 destabilizes its partner (PMS2 or MSH6), but losing PMS2 or MSH6 removes only that protein.
| IHC pattern | Most likely cause | Next step |
|---|---|---|
| MLH1 + PMS2 lost | MLH1 germline variant, or sporadic MLH1 promoter hypermethylation (more likely at older ages) | Tumor BRAF V600E and/or MLH1 methylation testing; if present, sporadic; if absent, germline testing |
| MSH2 + MSH6 lost | MSH2 germline variant, or an EPCAM deletion | Germline MSH2, adding EPCAM if negative |
| MSH6 alone lost | MSH6 | Germline MSH6 |
| PMS2 alone lost | PMS2 (occasionally MLH1) | Germline PMS2, then MLH1 if negative |
| All four retained | MMR-proficient tumor | Usually stop, but normal IHC misses some MSH6 carriers; a strong family history still merits genetic evaluation |
- Sporadic MSI cancer: about 10-15% of sporadic colorectal cancers are MSI-high from somatic MLH1 promoter hypermethylation, usually in older patients via the serrated pathway. BRAF V600E is found in about 68% of them and very rarely, if ever, in Lynch cancers, so a BRAF-mutant tumor points away from Lynch.
- Unexplained MMR loss with negative germline testing is often somatic biallelic inactivation ("Lynch-like"), a sporadic mechanism found by tumor sequencing.
- A germline hit triggers cascade testing of relatives; relatives who test negative return to average-risk screening.
Associated cancers and risk by gene
| Gene | Colorectal cancer (lifetime) | Endometrial cancer (lifetime) | Colonoscopy (NCCN 2024) |
|---|---|---|---|
| MLH1 | 41-50% | 34-54% | Age 20-25 (or 2-5 y before the earliest family case if it was before 25), every 1-2 y |
| MSH2 | 35-56% | 21-51% | Same as MLH1 |
| EPCAM | About 75% by 70 in one European study | Lower (12% in that study), depending on the deletion | Managed like MSH2 |
| MSH6 | 10-22% | 16-49% | Age 30-35 (or 2-5 y before the earliest family case if it was before 30), every 1-3 y |
| PMS2 | About 10% | About 24% | Same as MSH6 |
Figures are NCI's gene-specific estimates; about 1 in 279 people carries a Lynch variant.
- Endometrium is the sentinel. It is the most common extracolonic cancer, affects at least one woman in about half of Lynch families, and is the first cancer in about half of women carriers.
- Other sites (NCI risk ranges to age 70): ovary 3.4-22%, stomach 0.2-13%, urinary tract (transitional cell carcinoma of ureter, renal pelvis and bladder) up to about 25%, small bowel up to 12%, plus pancreas, hepatobiliary tract and brain.
- Muir-Torre syndrome: sebaceous adenomas, sebaceous carcinomas and keratoacanthomas plus visceral cancer; more often MSH2.
- Turcot syndrome: colon cancer + glioblastoma = MMR genes (Lynch); polyposis + medulloblastoma = APC (FAP).
Prevention beyond the colonoscope
- Endometrium and ovary: risk-reducing hysterectomy with bilateral salpingo-oophorectomy prevents both cancers; in one series, none occurred after surgery versus 33% endometrial and 5.5% ovarian cancer without it. Endometrial biopsy every 1-2 years from 30-35 can be considered; transvaginal ultrasound is neither sensitive nor specific.
- Stomach and duodenum: upper endoscopy with random gastric biopsies from 30-40, repeated every 2-4 years (NCCN).
- Urinary tract: consider yearly urinalysis from 30-35 in MSH2 carriers (especially men) or with a family history of urothelial cancer.
- Aspirin: in the CAPP2 trial, 600 mg daily reduced colorectal cancer, and guidelines recommend that carriers consider daily aspirin.
- If cancer develops: after segmental colectomy, metachronous cancer reached 16% at 10 years and 41% at 20 years in one registry, so younger carriers are often offered extended (total or subtotal) colectomy.
Practice question
A 42-year-old woman has a moderately differentiated adenocarcinoma of the cecum resected; colonoscopy showed only one other small adenoma. Her mother had endometrial cancer at 48, and her mother's brother had cancer of the ureter. Routine IHC of the tumor shows absent MSH2 and MSH6 with retained MLH1 and PMS2. Which is the most appropriate next step?
A. Genetic counseling and germline testing for MSH2, adding EPCAM if negative B. Tumor testing for BRAF V600E C. Germline APC testing D. Germline MLH1 testing E. No further testing, because universal screening applies only to patients under 50
Answer: A. Loss of the MSH2/MSH6 pair points to a germline MSH2 variant (or an EPCAM deletion silencing MSH2); her family also meets Amsterdam II (three relatives with Lynch cancers across two generations, one diagnosed before 50).
- B: BRAF and MLH1 methylation testing sort out MLH1/PMS2 loss, where sporadic hypermethylation is common; they don't apply here.
- C: APC causes FAP, with hundreds to thousands of adenomas; she had one.
- D: a germline MLH1 defect removes MLH1 and PMS2, which are present.
- E: universal screening applies to every colorectal cancer regardless of age.
Then: cascade testing of her relatives, colonoscopy every 1-2 years for carriers, discussion of risk-reducing hysterectomy and salpingo-oophorectomy, and consideration of daily aspirin.
Key takeaways
- Lynch = autosomal dominant MMR defect (MLH1, MSH2, MSH6, PMS2, or EPCAM silencing MSH2) → MSI-high tumors, about 3% of colorectal cancer.
- Few polyps, right colon, fast progression; endometrial cancer is the most common extracolonic cancer and often the first.
- IHC pairs: MLH1 goes with PMS2, MSH2 with MSH6; MLH1 loss → check BRAF V600E or MLH1 methylation before germline testing.
- Amsterdam II = 3-2-1-0; revised Bethesda selects tumors for testing; both have given way to universal tumor screening.
- Colonoscopy: from 20-25 every 1-2 years (MLH1, MSH2, EPCAM); from 30-35 every 1-3 years (MSH6, PMS2).
- vs FAP (APC, hundreds to thousands of polyps, colonoscopy from 10-15, prophylactic colectomy) and MAP (MUTYH, autosomal recessive).
Sources
- Genetics of Colorectal Cancer (PDQ) – Health Professional Version — National Cancer Institute (2025)
- Lynch syndrome — MedlinePlus Genetics
- Lynch Syndrome (Hereditary Nonpolyposis Colorectal Carcinoma) — Merck Manual Professional Edition (2025)
- Diagnosis and Management of Lynch Syndrome: AGA Institute Guideline — American Gastroenterological Association (2015)
- MUTYH-associated polyposis — MedlinePlus Genetics
- Familial Adenomatous Polyposis — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
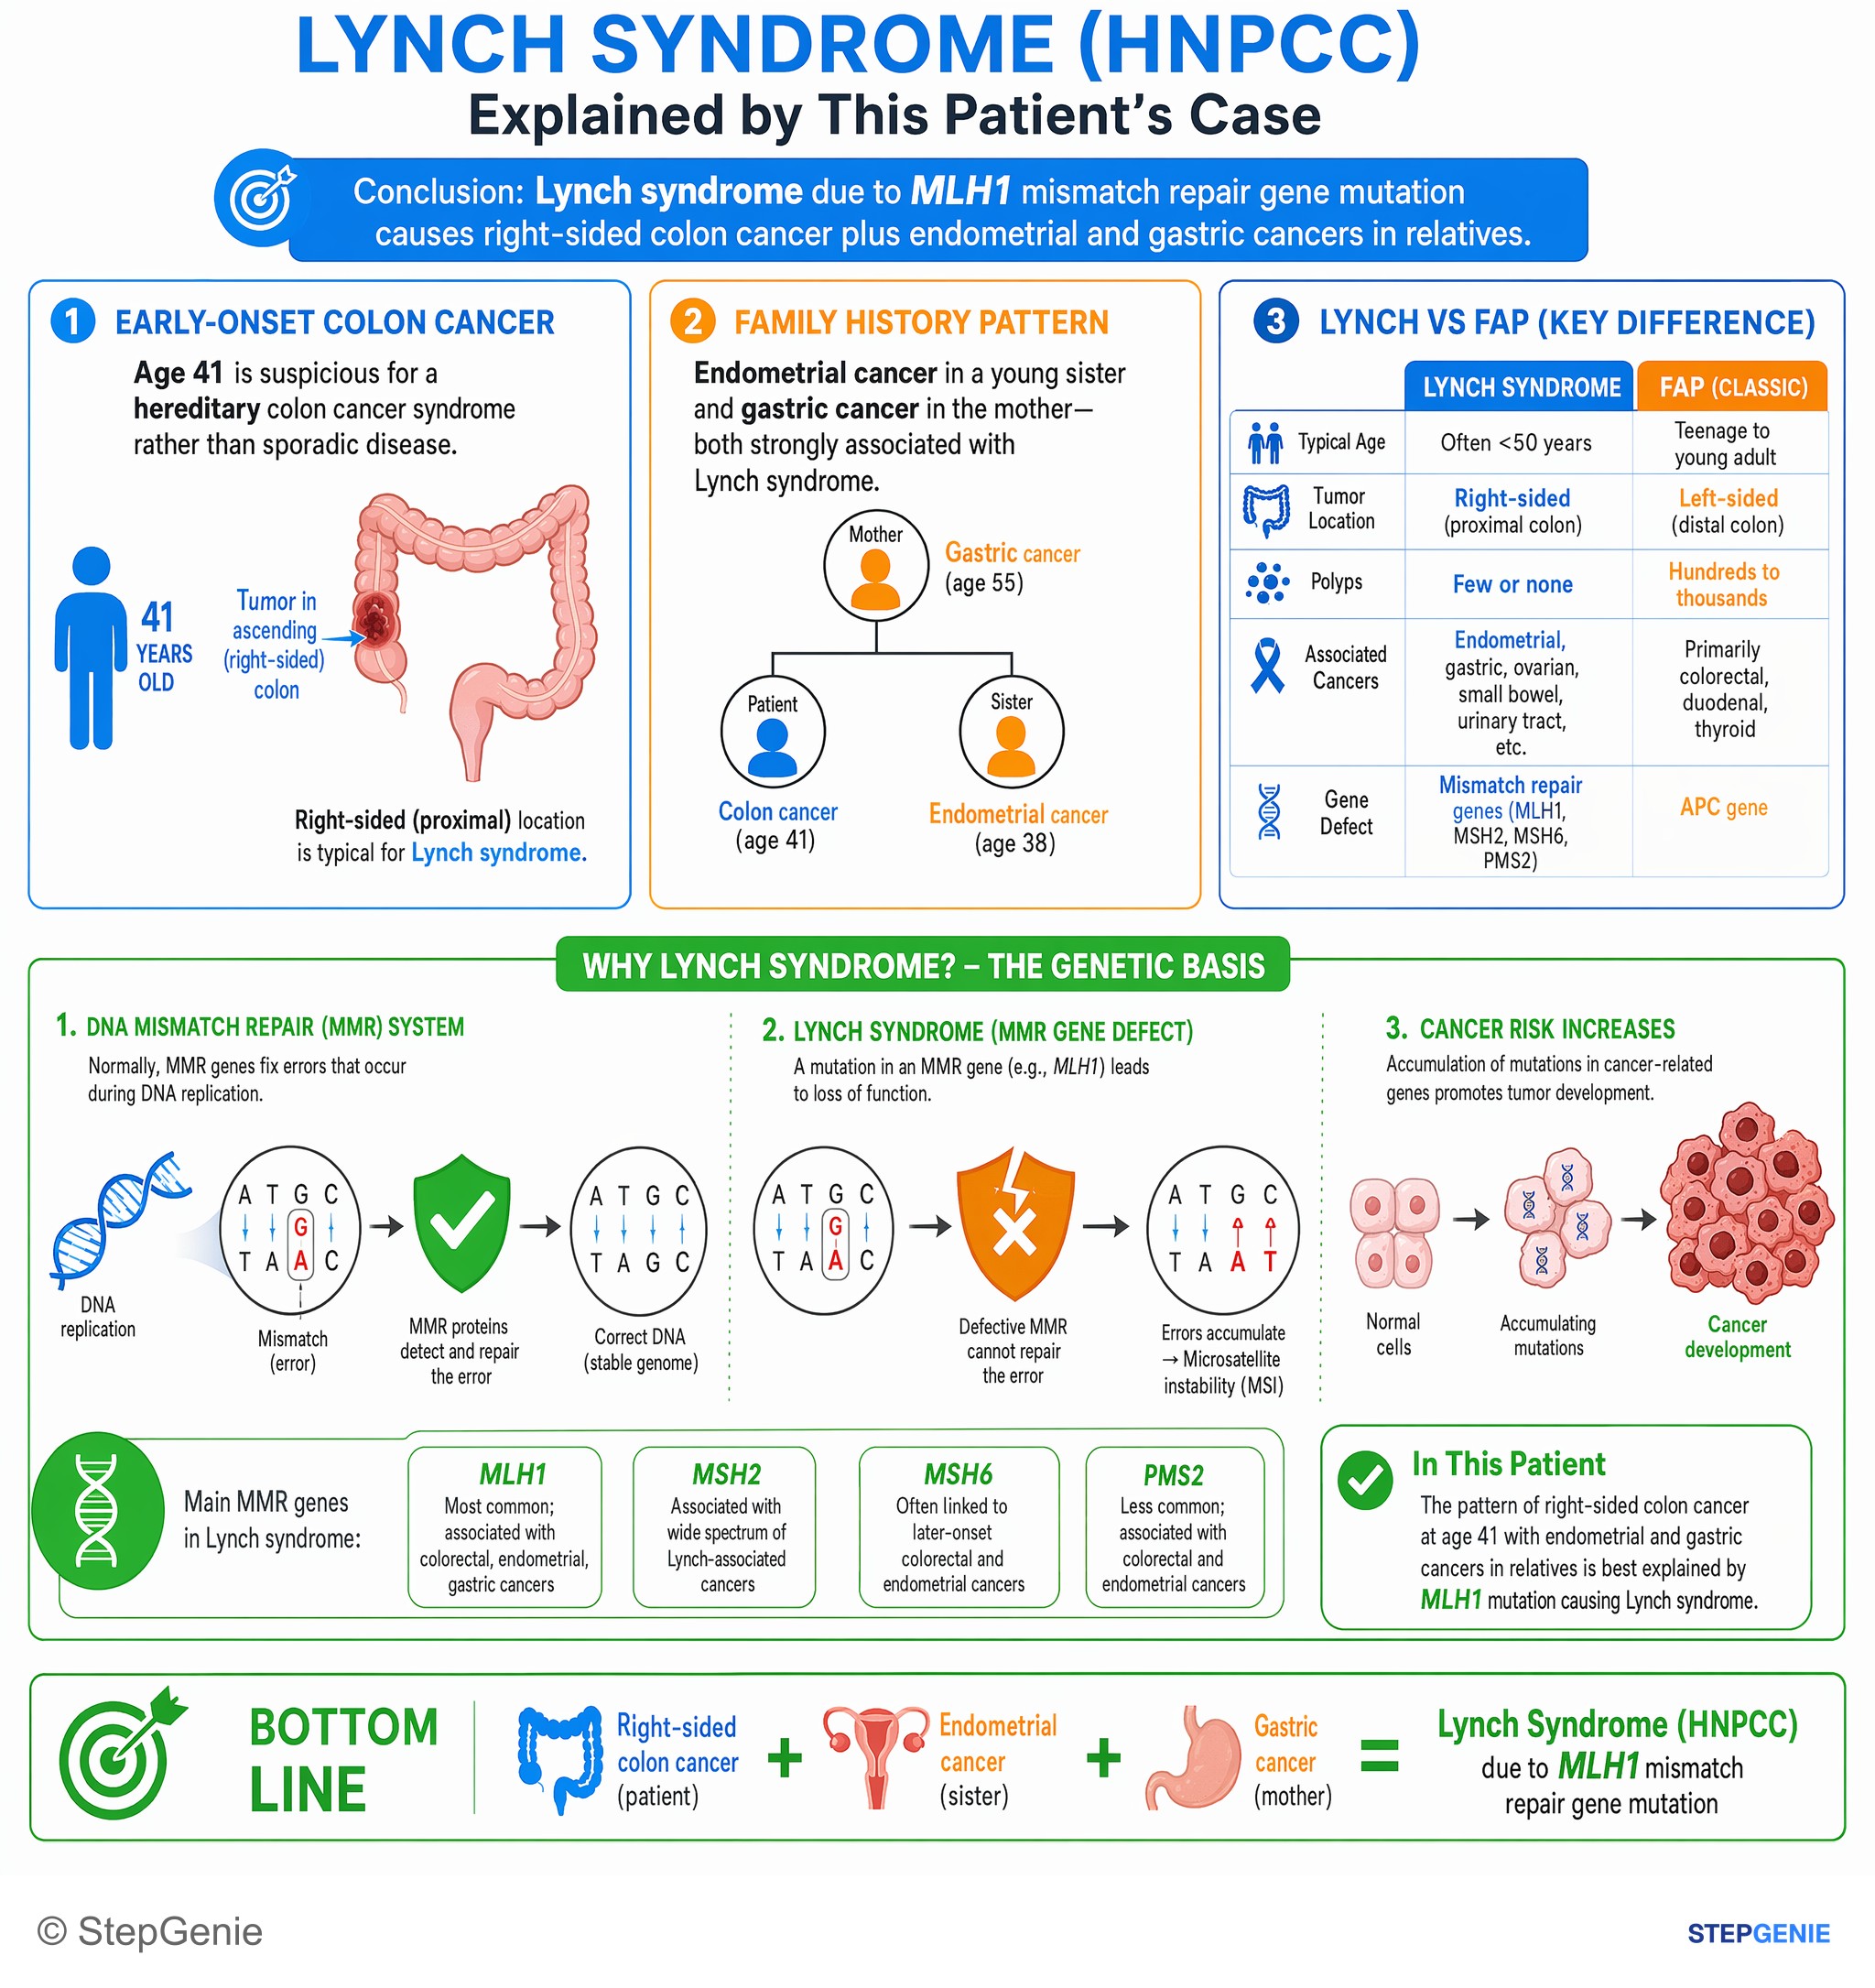
Lynch syndrome (HNPCC) due to MLH1 mismatch repair gene mutation causes right-sided colon cancer plus endometrial and gastric cancers in…
USMLE Step 1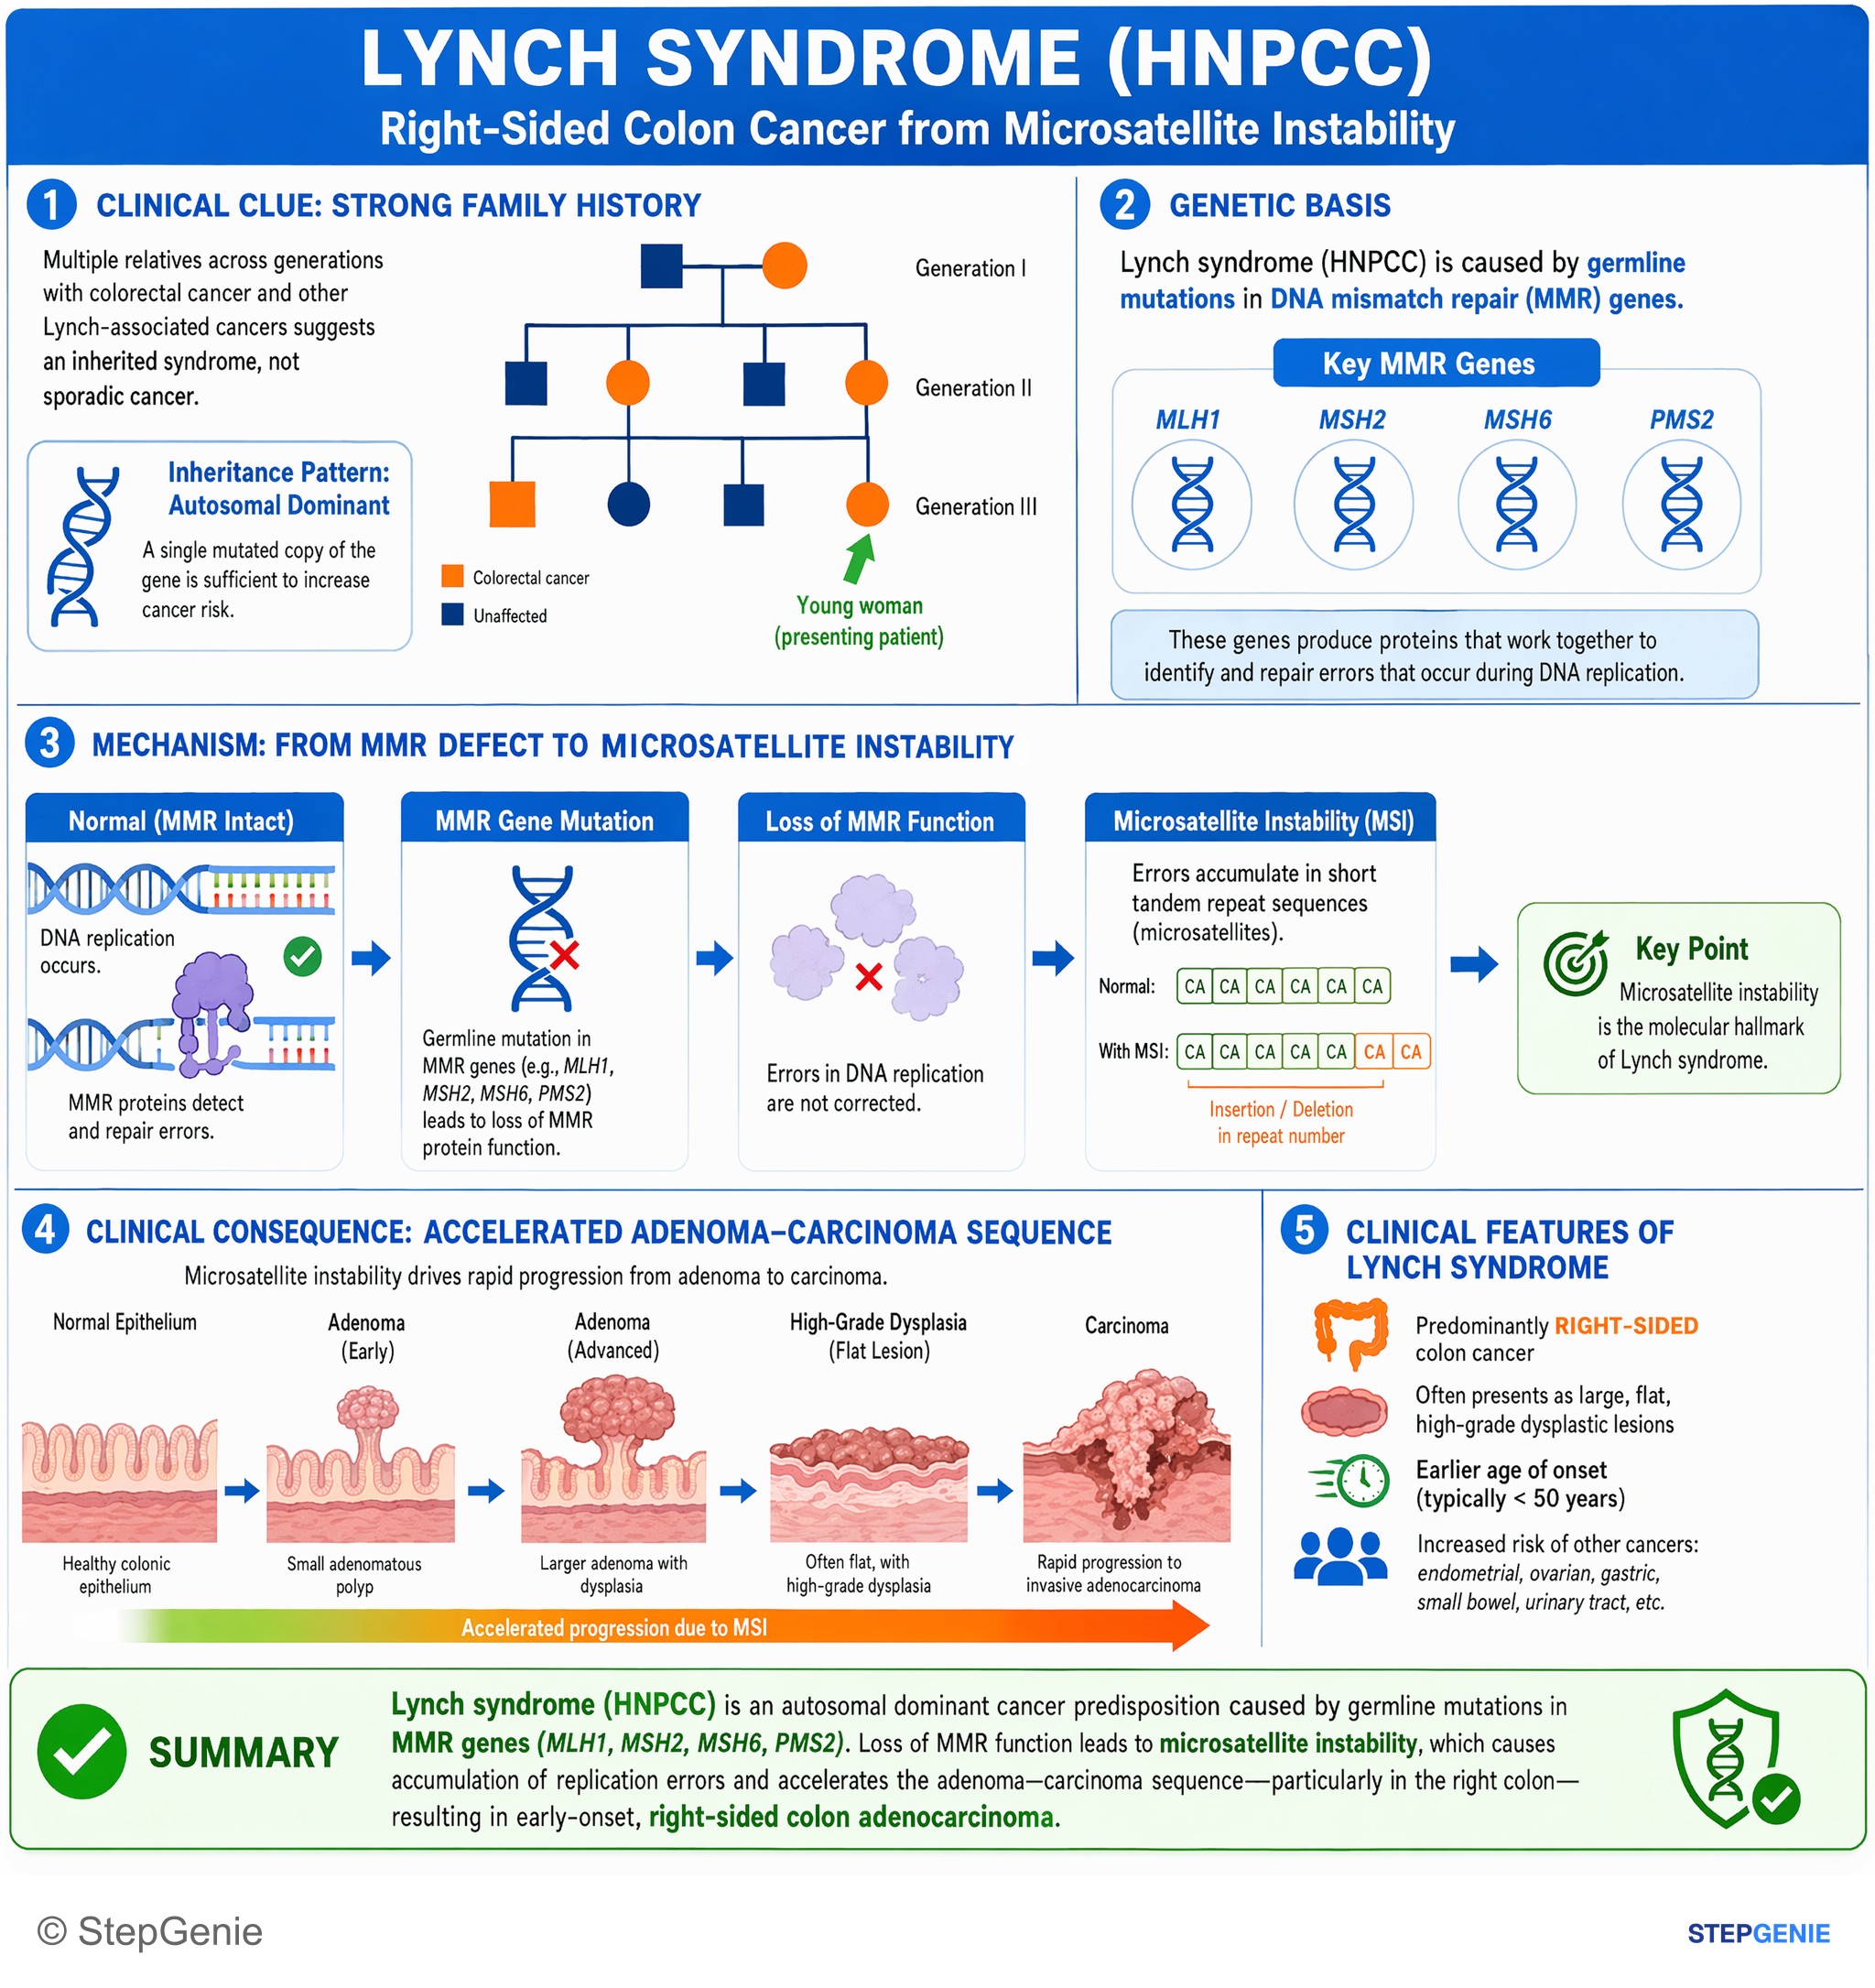
Lynch syndrome (HNPCC) causes right-sided colon adenocarcinoma from microsatellite instability due to mismatch repair gene mutations and…
USMLE Step 1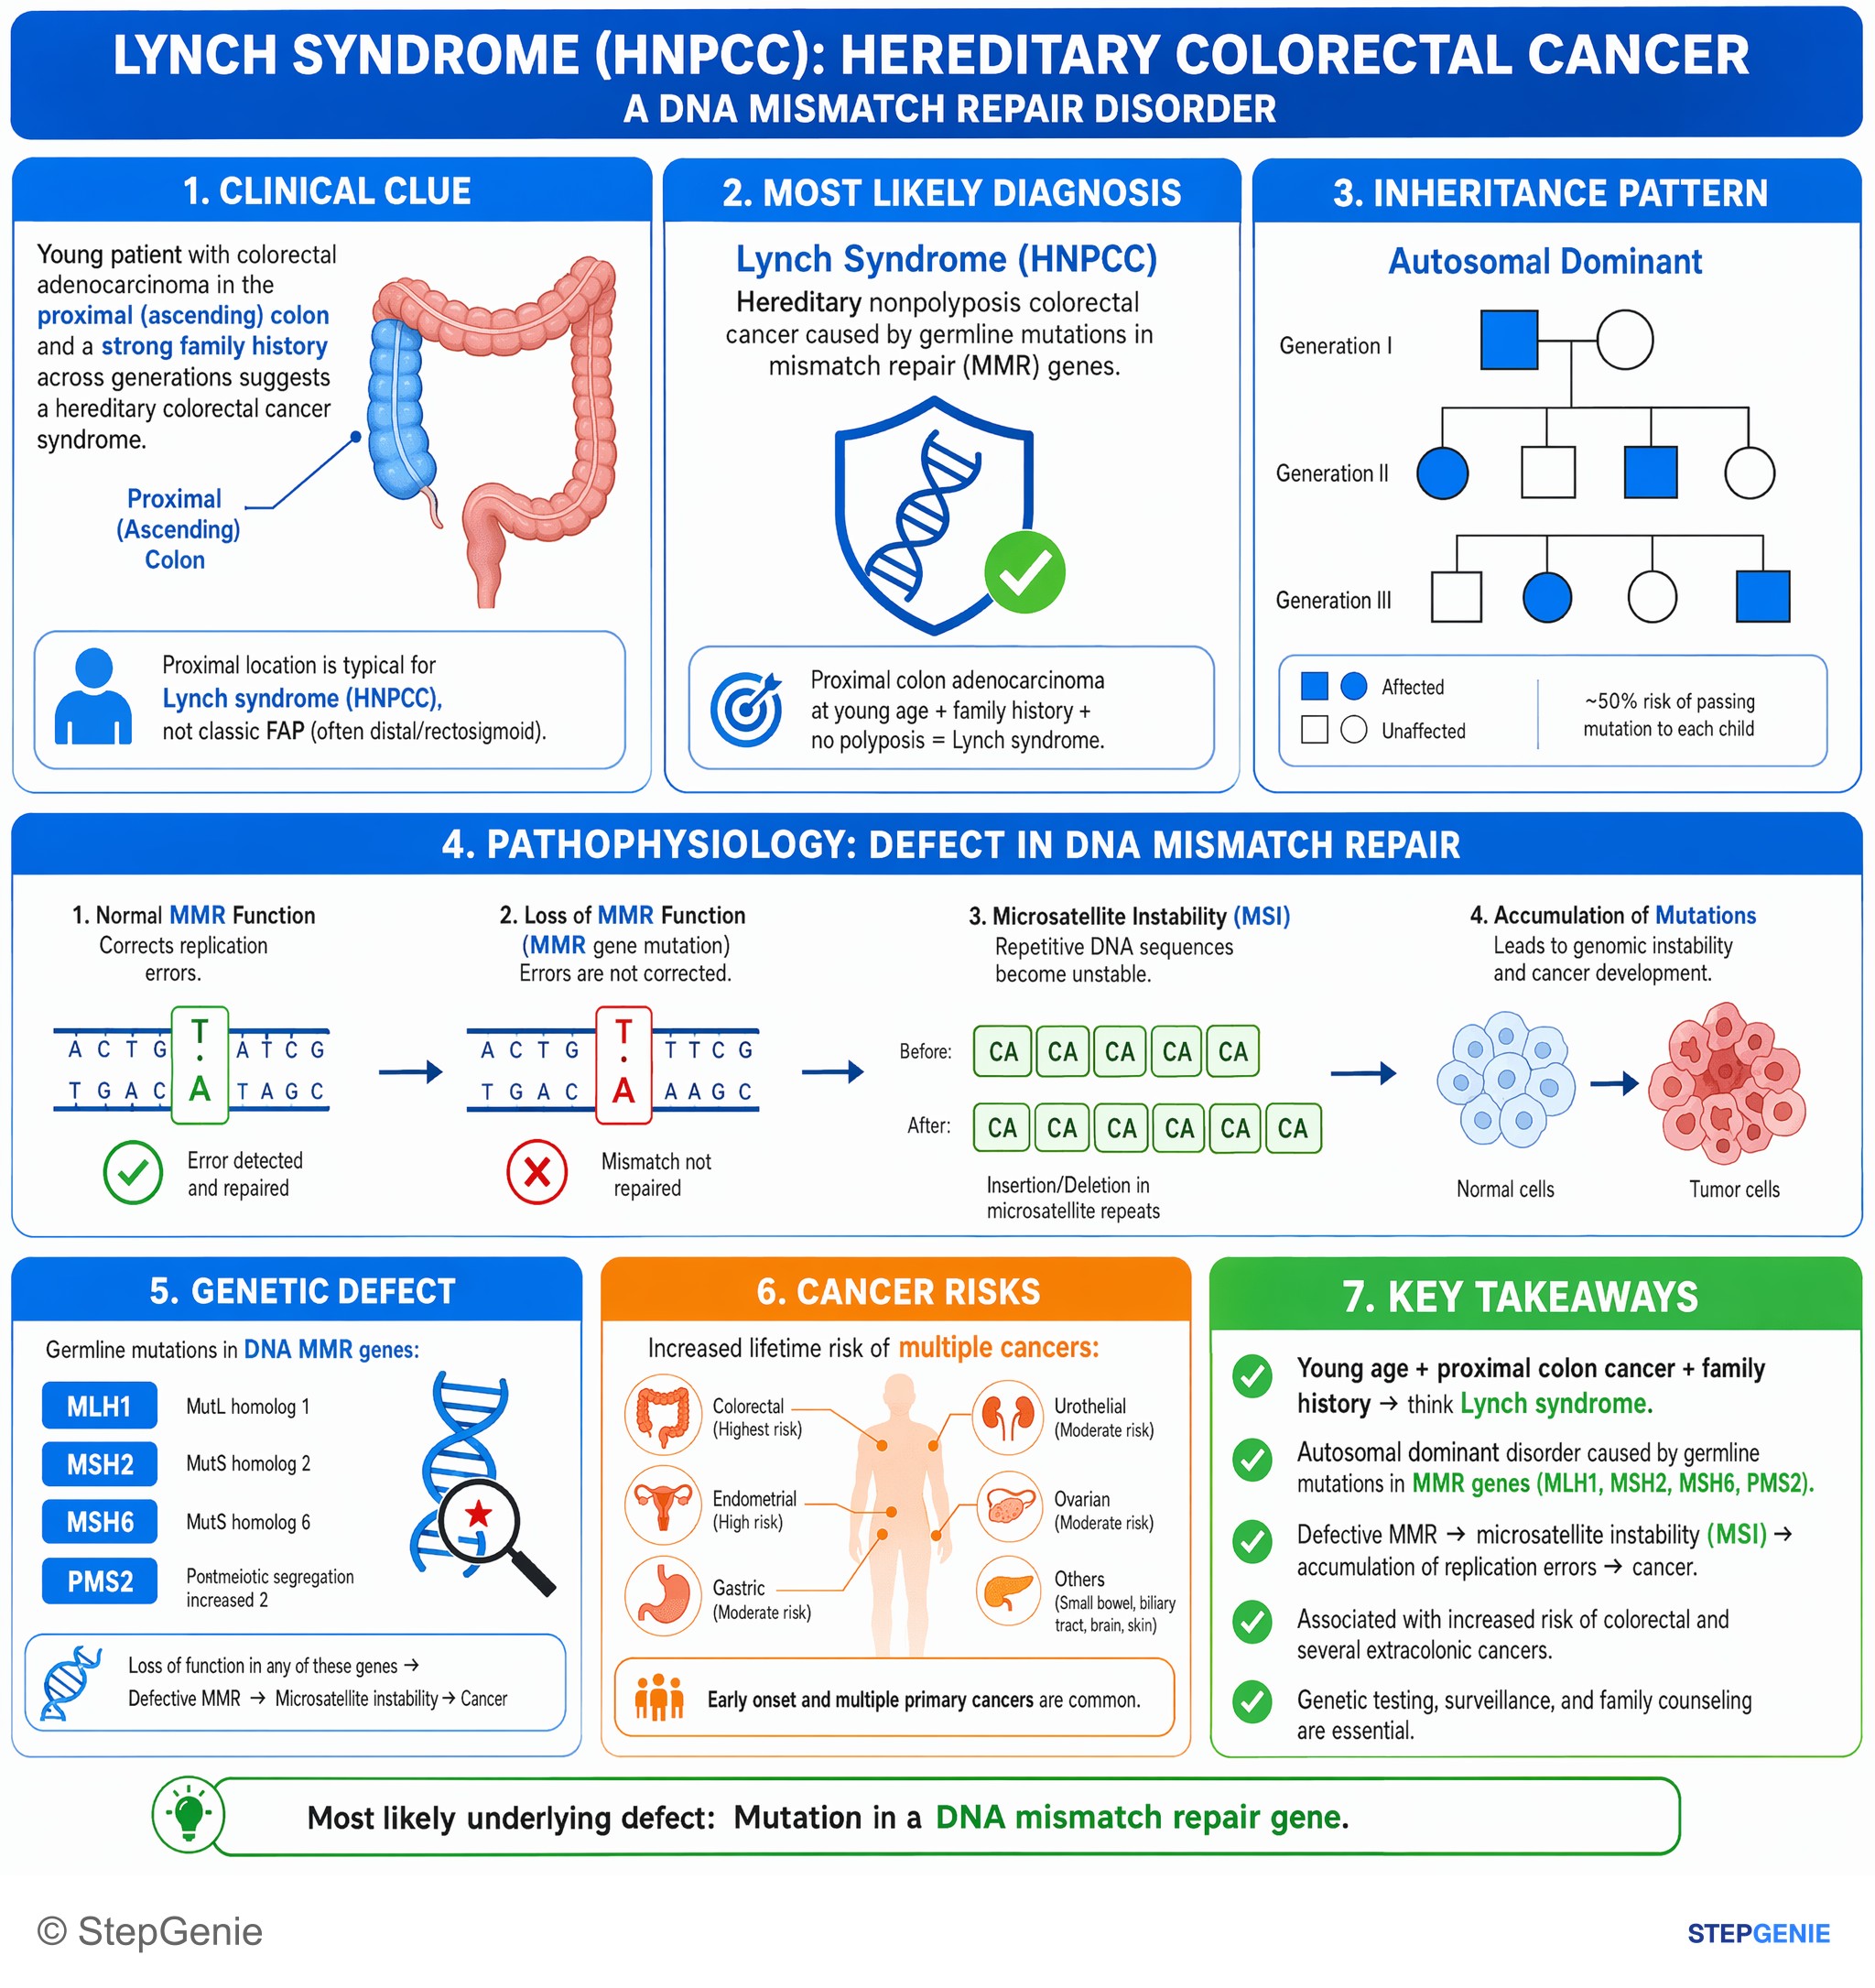
Hereditary nonpolyposis colorectal cancer (Lynch syndrome) from germline mismatch repair gene mutation → proximal colon adenocarcinoma at…
USMLE Step 1Frequently Asked Questions
What genes cause Lynch syndrome?
Lynch syndrome is caused by a germline pathogenic variant in one of the DNA mismatch repair genes MLH1, MSH2, MSH6 or PMS2, or by a deletion in EPCAM that silences the neighboring MSH2 gene. It is inherited in an autosomal dominant pattern with incomplete penetrance. MLH1 and MSH2 carriers have the highest cancer risks, while MSH6 and PMS2 carriers have lower risks and later onset.
What is the difference between Lynch syndrome and FAP?
Both are autosomal dominant, but FAP is caused by APC variants and produces hundreds to thousands of colorectal adenomas from the teenage years, so prophylactic colectomy is standard. Lynch syndrome is caused by mismatch repair defects, produces few polyps and causes microsatellite-unstable cancers of the colon (often right-sided), endometrium and other organs. Lynch syndrome is managed with colonoscopy every 1 to 3 years rather than prophylactic colectomy.
What are the Amsterdam II criteria for Lynch syndrome?
Amsterdam II requires at least three relatives with a Lynch-associated cancer (colorectal, endometrial, small bowel, ureter or renal pelvis), one of whom is a first-degree relative of the other two, affecting at least two generations, with at least one diagnosis before age 50 and FAP excluded. A common memory aid is the 3-2-1-0 rule. The criteria miss many carriers, so universal tumor testing is now preferred for people with cancer.
How is Lynch syndrome screened for in people with colorectal cancer?
The tumor of every newly diagnosed colorectal cancer is tested by immunohistochemistry for the four mismatch repair proteins or by microsatellite instability testing. Loss of MLH1 and PMS2 is followed by BRAF V600E or MLH1 promoter methylation testing, because sporadic hypermethylation is common, while other abnormal patterns lead to germline genetic testing. A confirmed germline variant prompts testing of relatives.
When should colonoscopy start in Lynch syndrome?
Under the 2024 NCCN schedule summarized by the National Cancer Institute, carriers of MLH1, MSH2 or EPCAM variants start colonoscopy at age 20 to 25 (or 2 to 5 years before the earliest colorectal cancer in the family if it was before 25) and repeat it every 1 to 2 years. MSH6 and PMS2 carriers start at 30 to 35 (or 2 to 5 years before the earliest family case if it was before 30) and repeat it every 1 to 3 years.
What cancers are associated with Lynch syndrome besides colon cancer?
Endometrial cancer is the most common extracolonic cancer and is the first cancer in about half of women carriers. Other associated cancers include ovarian, stomach, small bowel, urinary tract (ureter and renal pelvis), hepatobiliary, pancreatic and brain cancers, typically glioblastoma. Sebaceous skin tumors and keratoacanthomas define the Muir-Torre variant.