You know the feeling: you’re cruising through a GI question block, see “young patient + liver disease,” and suddenly every answer choice feels plausible. Wilson disease is a classic example where the correct diagnosis hinges on one or two high-yield clues—and where the distractors are basically a checklist of other hepatic disorders you must be able to separate on Step 1/2.
Tag: GI > Hepatic Disorders
The Clinical Vignette (Q-bank style)
A 19-year-old presents with several months of fatigue, abdominal discomfort, and new mood changes with irritability and declining school performance. Exam shows mild jaundice and a fine tremor. Labs: AST/ALT moderately elevated, total bilirubin elevated, INR mildly prolonged. Hemoglobin is low with increased reticulocytes. Slit-lamp exam shows brownish corneal rings.
Question: Which finding most strongly supports the diagnosis?
Answer choices:
A. Increased serum ceruloplasmin
B. Decreased serum ceruloplasmin
C. Positive antimitochondrial antibodies (AMA)
D. Markedly elevated alkaline phosphatase (ALP) with pruritus
E. Increased transferrin saturation and ferritin
The Correct Answer: B. Decreased serum ceruloplasmin
Why Wilson disease fits
Wilson disease is a disorder of copper transport due to ATP7B mutation (autosomal recessive). The liver can’t properly excrete copper into bile or incorporate copper into ceruloplasmin, so copper builds up—first in the liver, then spills into the brain, cornea, and other tissues.
Key vignette clues (high-yield)
- Young age + hepatic disease (often teens/young adults)
- Neuro/psych symptoms: tremor, dystonia, parkinsonism, personality change, depression
- Hemolytic anemia (Coombs-negative) can occur due to free copper–mediated oxidative damage
- Kayser–Fleischer rings (copper in Descemet membrane)
What you’d expect in Wilson disease
| Test | Expected finding | Why it happens |
|---|---|---|
| Serum ceruloplasmin | Low | impaired incorporation of copper into ceruloplasmin and increased degradation |
| 24-hour urinary copper | High | copper spills into urine |
| Hepatic copper | High | copper accumulation in liver |
| Serum copper | Often low total but high free copper | total tracks with ceruloplasmin; free copper rises |
| Eye exam | Kayser–Fleischer rings | corneal copper deposition |
Step-friendly treatment pearls
- Chelation: penicillamine (or trientine)
- Reduce absorption: zinc (induces metallothionein in enterocytes → traps copper)
- Definitive: liver transplant (curative for hepatic failure; corrects copper handling)
Why Each Distractor Is Wrong (and what it’s trying to test)
A. Increased serum ceruloplasmin
This is basically the “inverse-Wilson” trap.
- Wilson disease: ceruloplasmin is typically decreased.
- When ceruloplasmin can be increased: it’s an acute-phase reactant, so it can rise with inflammation, infection, pregnancy, estrogen use.
- Important nuance: a normal ceruloplasmin doesn’t completely rule out Wilson (especially in inflammatory states), but an increased ceruloplasmin doesn’t support it.
Board takeaway: If the vignette screams Wilson, the test that “supports” it is low ceruloplasmin and/or high urine copper, not high ceruloplasmin.
C. Positive antimitochondrial antibodies (AMA)
This choice is pointing at Primary Biliary Cholangitis (PBC).
PBC hallmarks
- Middle-aged woman
- Cholestatic pattern: ALP, GGT
- Pruritus, fatigue
- AMA positive
- Associated with other autoimmune disease (e.g., Sjögren, thyroid disease)
Why it doesn’t fit this vignette
- Age is too young for typical PBC
- Vignette emphasizes neuropsychiatric symptoms + hemolysis + KF rings, not autoimmune cholestasis
USMLE trick:
- PBC = AMA
- PSC = p-ANCA and IBD association
D. Markedly elevated alkaline phosphatase (ALP) with pruritus
This is the “cholestasis” lure: think PBC, PSC, biliary obstruction, certain drug-induced cholestasis.
Cholestatic vs hepatocellular patterns
- Cholestatic: ALP (and GGT) disproportionately elevated → itching, pale stools, dark urine
- Hepatocellular: AST/ALT disproportionately elevated → hepatocyte injury
Why it’s wrong here Wilson can present with various patterns, but the vignette’s signature is copper overload features (neuro + KF rings + hemolysis). “Marked ALP elevation with pruritus” is much more classic for cholestatic diseases.
Extra high-yield pearl: In PSC, cholangiography shows “beading” from strictures and dilation.
E. Increased transferrin saturation and ferritin
This is testing Hereditary Hemochromatosis (iron overload), usually due to HFE mutation (commonly C282Y).
Hemochromatosis classic findings
- Elevated transferrin saturation (often the earliest lab clue)
- Elevated ferritin
- Cirrhosis, diabetes (“bronze diabetes”), cardiomyopathy, hypogonadism, arthropathy
- Typically presents later than Wilson (often middle age)
Why it doesn’t fit
- Vignette’s neuropsychiatric symptoms + KF rings + hemolytic anemia are not the hemochromatosis vibe.
- Age (19) pushes you toward Wilson much more strongly.
Treatment contrast (easy points):
- Hemochromatosis → phlebotomy (or chelation if can’t)
- Wilson → penicillamine/trientine + zinc
Rapid-Fire “Wilson vs Everyone” Differentials
Wilson vs Autoimmune Hepatitis
- Autoimmune hepatitis: young woman, other autoimmune features, anti–smooth muscle and/or ANA, high IgG
- Wilson: KF rings, neuro symptoms, hemolysis, low ceruloplasmin, high urine copper
Wilson vs PSC/PBC
- PSC/PBC: cholestatic labs (ALP), pruritus
- Wilson: neuro/psych + hemolysis + copper studies
Wilson vs Viral hepatitis
- Viral: exposures, prodrome, very high AST/ALT possible
- Wilson: weird combo of liver + brain + eyes
Test-Day Strategy: How to Lock Wilson Quickly
If you see any 2 of the following, your Wilson antenna should go up:
- Young patient with unexplained liver disease/cirrhosis
- Neuro (tremor, dystonia, parkinsonism) or psych changes
- Coombs-negative hemolytic anemia
- Kayser–Fleischer rings
Then pick supporting tests:
- Low ceruloplasmin
- High 24-hour urinary copper
- High hepatic copper content
High-Yield Summary (what to remember in 15 seconds)
- Wilson = ATP7B (AR) → impaired copper excretion into bile + impaired ceruloplasmin loading
- Findings: liver disease + neuro/psych + KF rings + Coombs-negative hemolysis
- Labs: low ceruloplasmin, high urine copper, high hepatic copper
- Tx: penicillamine/trientine, zinc, transplant if severe
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
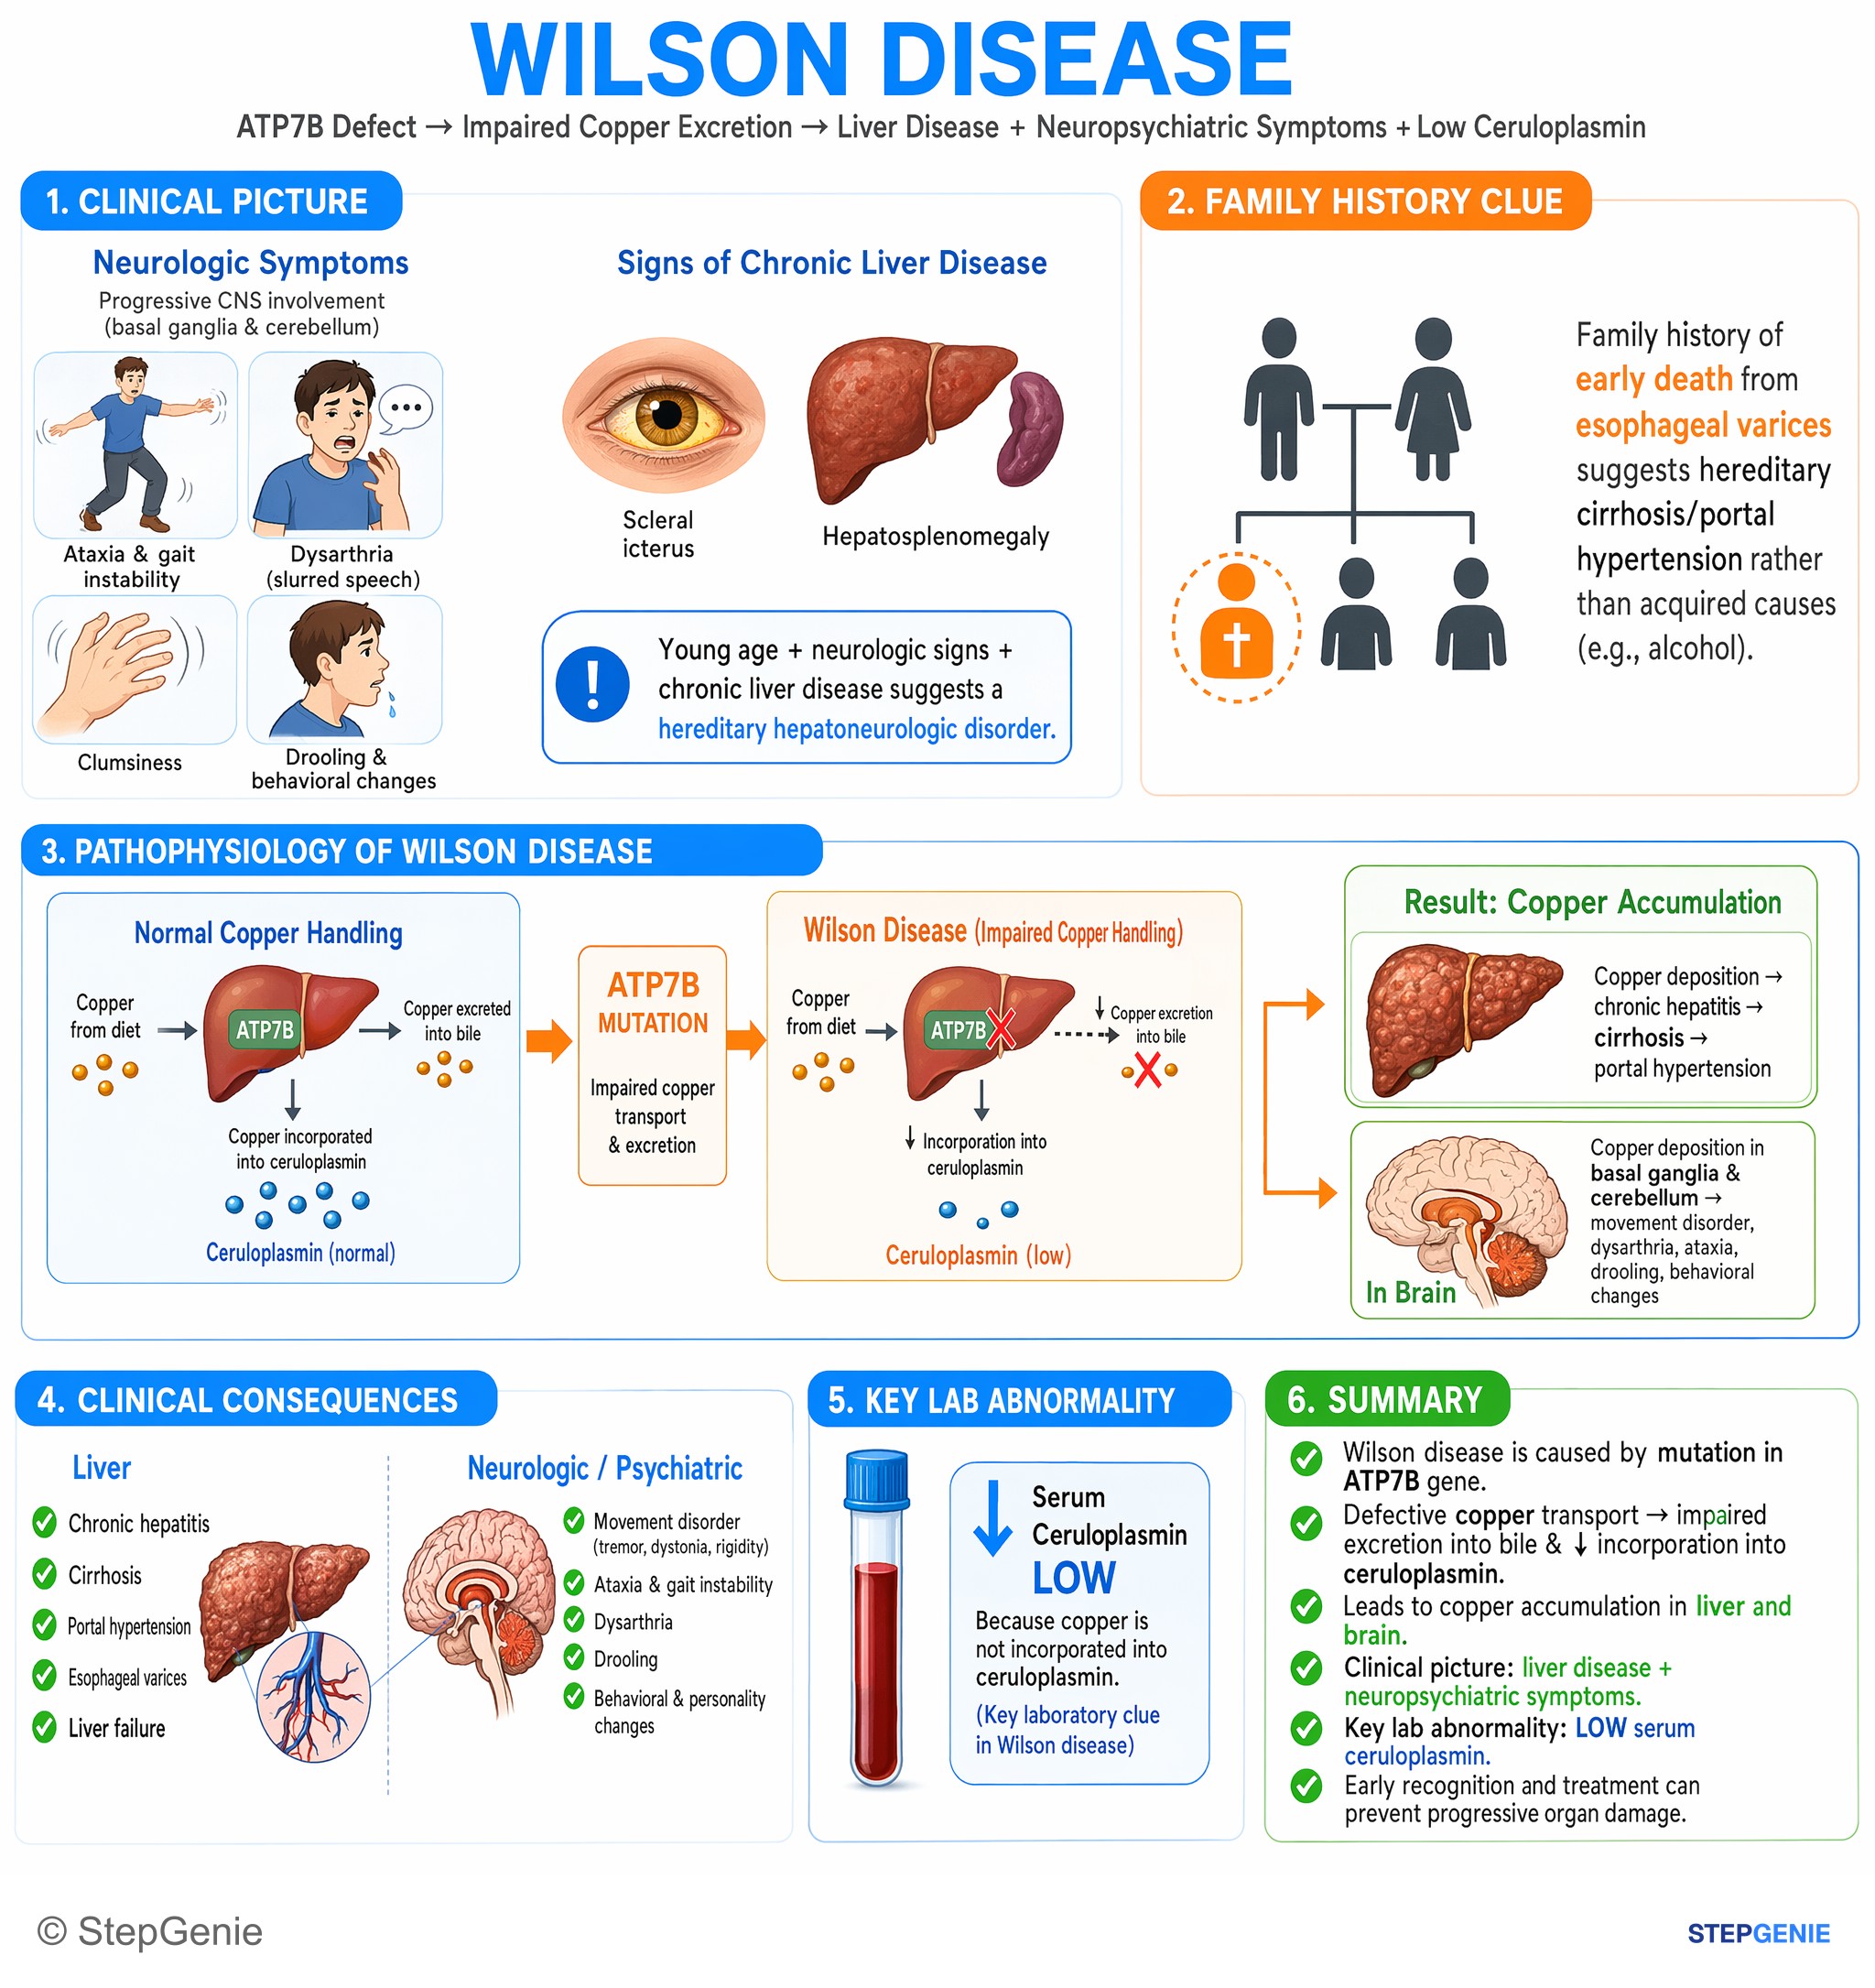
Wilson disease: ATP7B defect causes impaired copper excretion, leading to liver disease + neuropsychiatric symptoms and low serum…
USMLE Step 1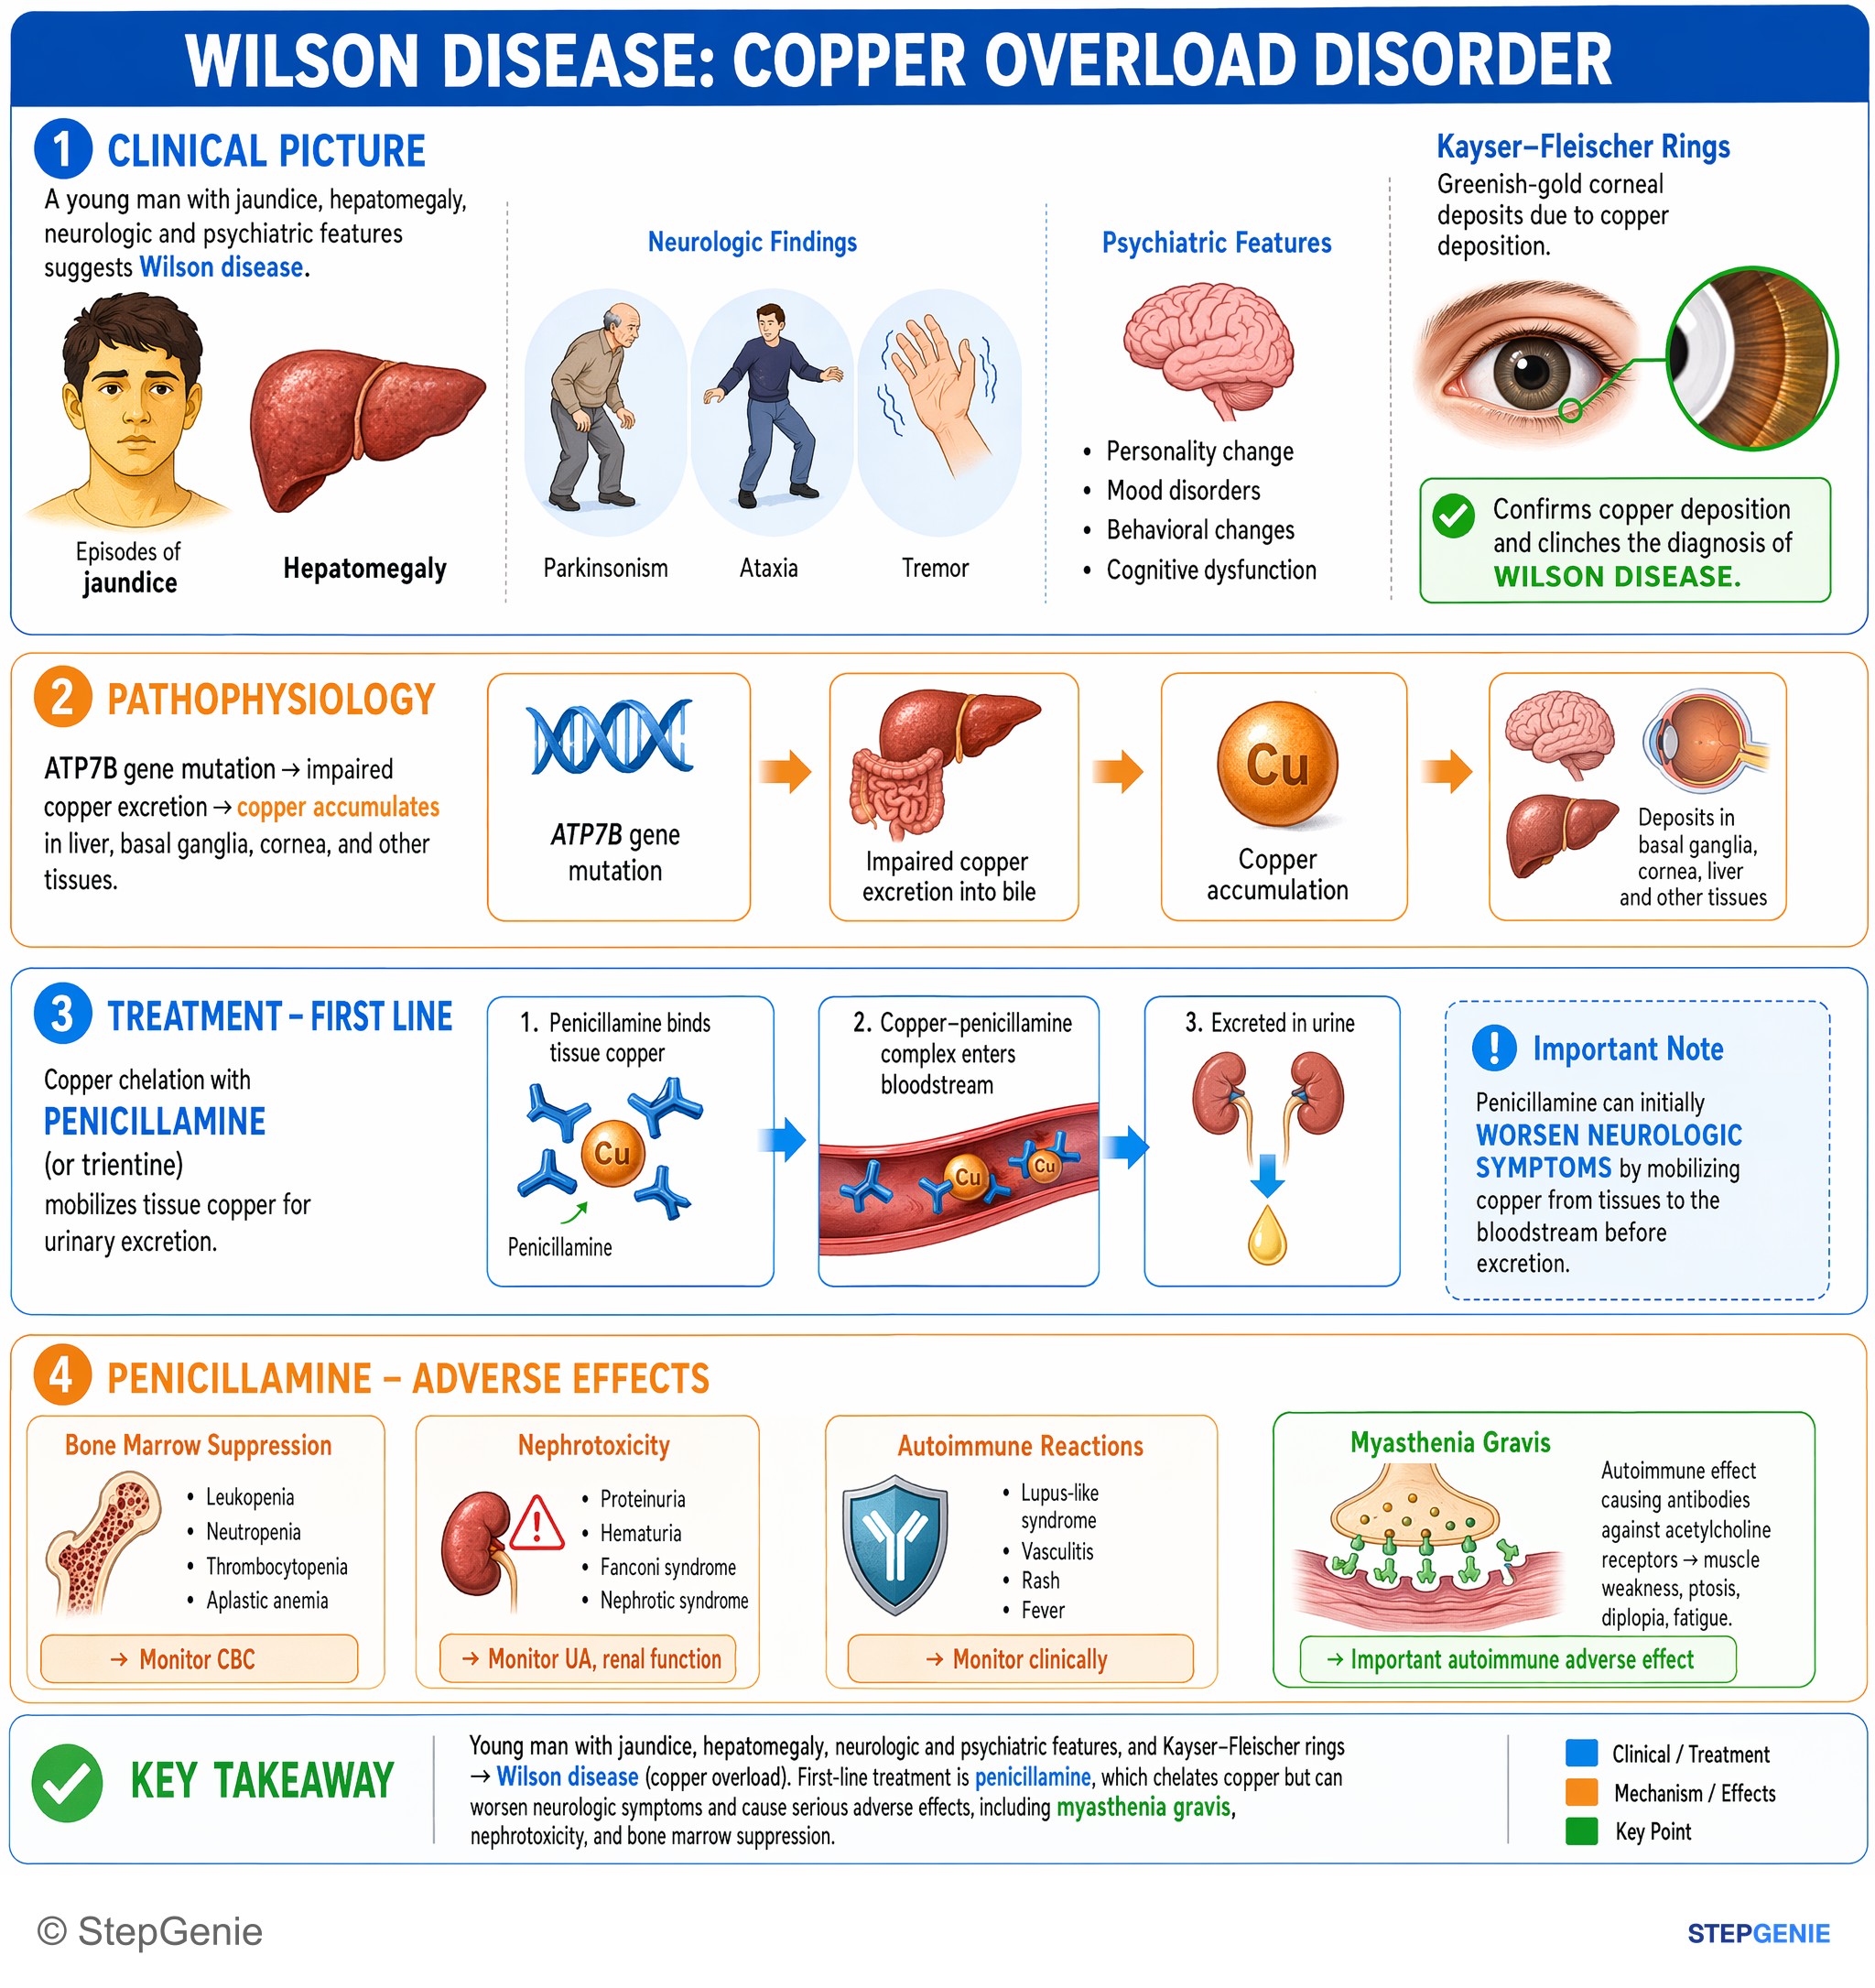
Wilson disease treated with penicillamine; chelation can cause worsening neurologic symptoms and autoimmune effects like myasthenia gravis…
USMLE Step 1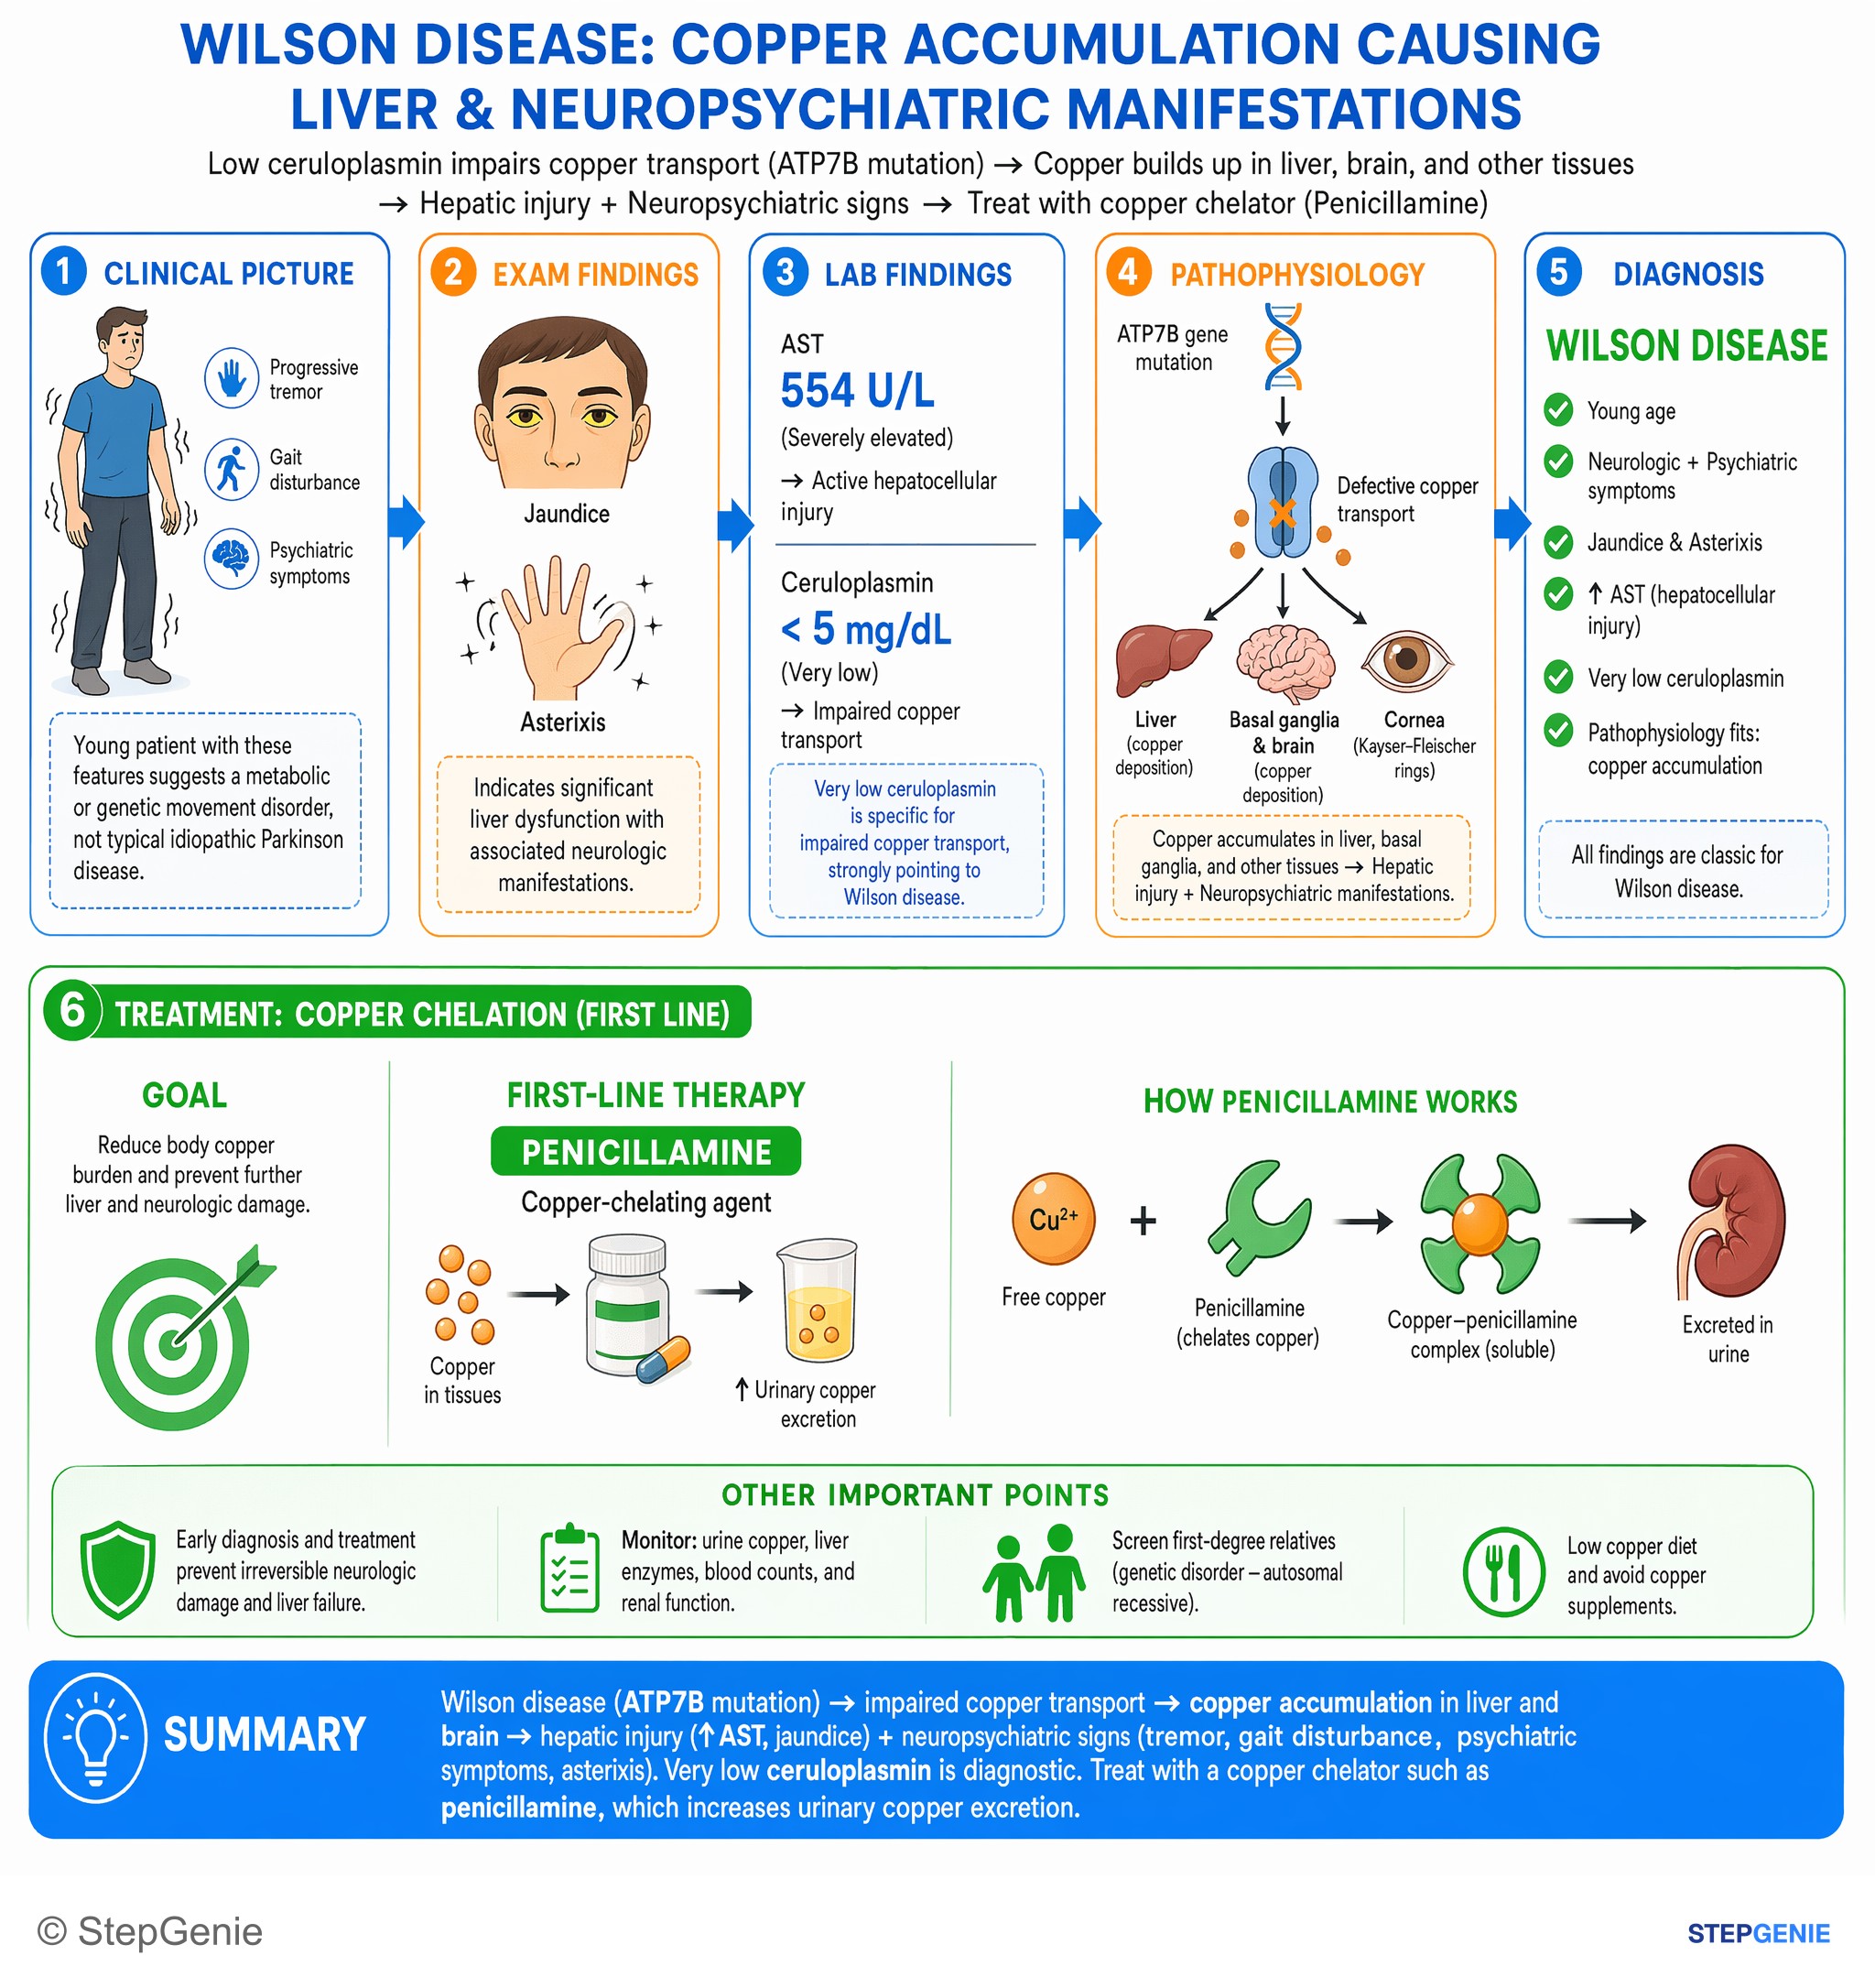
Wilson disease from copper accumulation (low ceruloplasmin) causes hepatic injury + neuropsychiatric signs; treat with copper chelator…
USMLE Step 2Frequently Asked Questions
What finding most strongly supports Wilson disease in a young patient with liver disease and neuropsychiatric symptoms?
Decreased serum ceruloplasmin most strongly supports Wilson disease. Wilson disease is caused by an ATP7B mutation that impairs copper incorporation into ceruloplasmin and copper excretion into bile, so ceruloplasmin is typically low. In a young patient with hepatic dysfunction, tremor or mood changes, hemolytic anemia, and Kayser–Fleischer rings, low ceruloplasmin fits the underlying copper transport defect.
Why does Wilson disease cause neurologic symptoms, Kayser–Fleischer rings, and hemolytic anemia?
Wilson disease causes these findings because copper accumulates in multiple tissues. The ATP7B defect prevents normal biliary copper excretion and incorporation into ceruloplasmin, so copper first builds up in the liver and then deposits in the brain and cornea, producing neuropsychiatric symptoms and Kayser–Fleischer rings. Free copper can also cause Coombs-negative hemolytic anemia through oxidative damage.
How do you tell Wilson disease from primary biliary cholangitis or other cholestatic liver diseases?
Wilson disease is distinguished by copper overload clues rather than a cholestatic pattern. Wilson classically presents in teens or young adults with hepatic disease plus neuropsychiatric symptoms, hemolysis, Kayser–Fleischer rings, low ceruloplasmin, and high urinary copper. Cholestatic diseases such as primary biliary cholangitis more often show markedly elevated alkaline phosphatase, pruritus, and in PBC, positive antimitochondrial antibodies.
How do you tell Wilson disease from hereditary hemochromatosis on a vignette?
Wilson disease is favored when a young patient has liver disease with neuropsychiatric changes, Kayser–Fleischer rings, and hemolytic anemia. Hereditary hemochromatosis instead points to iron overload, with increased transferrin saturation and ferritin, and classically presents later with findings such as cirrhosis, diabetes, cardiomyopathy, hypogonadism, or arthropathy. Age 19 strongly pushes the diagnosis toward Wilson disease rather than hemochromatosis.
What are the expected copper studies and treatment for Wilson disease?
Wilson disease typically shows low serum ceruloplasmin, high 24-hour urinary copper, high hepatic copper, and often low total serum copper but high free copper. These abnormalities reflect impaired copper handling from ATP7B dysfunction. Treatment includes copper chelation with penicillamine or trientine, reduction of copper absorption with zinc, and liver transplant as a definitive, curative option for hepatic failure.