Primary biliary cholangitis (PBC) is one of those “classic” Step diseases that’s easy to recognize in isolation—but Q-bank writers rarely give it to you in isolation. They’ll mix symptoms (fatigue, pruritus), sneak in labs (cholestatic pattern), and then tempt you with distractors that are almost right. This post walks through a PBC-style vignette and—most importantly—why every answer choice matters.
Clinical Vignette (Q-bank style)
A 49-year-old woman comes to clinic for months of fatigue and diffuse itching. She has no abdominal pain, fevers, or recent travel. PMH is notable for Hashimoto thyroiditis. She does not drink alcohol. Exam shows excoriations on the arms and trunk and mild scleral icterus. Labs:
| Test | Value |
|---|---|
| ALP | 620 U/L (high) |
| GGT | elevated |
| AST/ALT | mildly elevated |
| Total bilirubin | 2.1 mg/dL (high) |
| INR | normal |
| Anti-mitochondrial Ab | positive |
RUQ ultrasound shows no gallstones and no dilation of intrahepatic or extrahepatic bile ducts.
Question: What is the most likely diagnosis?
A. Primary biliary cholangitis
B. Primary sclerosing cholangitis
C. Autoimmune hepatitis
D. Choledocholithiasis
E. Secondary biliary cholangitis
Stepwise Approach: What are they actually testing?
1) Pattern recognition: cholestatic vs hepatocellular
- Cholestatic pattern = disproportionately high ALP (and usually GGT) relative to AST/ALT
- Hepatocellular pattern = disproportionately high AST/ALT relative to ALP
This patient screams cholestasis: very high ALP + pruritus + mild jaundice.
2) Intrahepatic vs extrahepatic obstruction
- RUQ ultrasound: no ductal dilation → argues against a big extrahepatic blockage (e.g., stone, pancreatic head cancer).
- That pushes you toward intrahepatic cholestasis (PBC, drugs, infiltrative disease, pregnancy, etc.).
3) Antibody clue + demographics
- Middle-aged woman + other autoimmune disease + anti-mitochondrial antibodies → PBC
Correct Answer: A. Primary biliary cholangitis (PBC)
Core pathophysiology (high-yield)
- Autoimmune destruction of intrahepatic bile ducts → chronic cholestasis → progressive fibrosis → cirrhosis
- Classic association: anti-mitochondrial antibodies (AMA) (often directed against pyruvate dehydrogenase complex)
- Think: intrahepatic small ducts are the main target
Key clinical features
- Pruritus (often early)
- Fatigue (often prominent)
- Jaundice later
- RUQ discomfort can occur, but severe colicky pain is not typical.
Labs & diagnostic clues
- ALP up (cholestatic)
- GGT up supports hepatobiliary source of ALP
- AMA positive (big Step hint)
- Hypercholesterolemia can occur (cholestasis-related)
- Imaging (US) often unremarkable early aside from excluding obstruction
Complications to remember for USMLE
- Fat-soluble vitamin deficiency (A, D, E, K) due to impaired bile flow
- Example: vitamin K deficiency → ↑PT/INR (may appear later)
- Osteopenia/osteoporosis (vitamin D deficiency + cholestasis)
- Cirrhosis → portal HTN, ascites, varices
- Increased risk for hepatocellular carcinoma once cirrhotic
Treatment (Step-friendly)
- Ursodeoxycholic acid (ursodiol): improves bile flow and labs; slows progression
- Obeticholic acid for inadequate response/intolerance (common testable add-on)
- Cholestyramine for pruritus (bile acid sequestrant)
- End-stage disease → liver transplant
Quick pruritus pearl: Cholestatic itching is mediated in part by bile acids—cholestyramine is the classic board answer.
Why the Other Answer Choices Are Wrong (and how they trick you)
B. Primary sclerosing cholangitis (PSC)
Why it’s tempting: Also cholestatic. Also autoimmune-adjacent. Also causes pruritus/jaundice.
Why it’s wrong here:
- PSC is classically:
- Male
- Associated with ulcerative colitis
- Involves intrahepatic and extrahepatic bile ducts
- Imaging hallmark: MRCP/ERCP shows “beading” (multifocal strictures and dilation)
- Antibody association: p-ANCA can be positive (not as specific as AMA for PBC)
High-yield PSC extras:
- Increased risk of cholangiocarcinoma
- Increased risk of colon cancer in UC patients
- May have recurrent cholangitis episodes
Exam move: If they mention UC + cholestatic labs + beading → PSC, not PBC.
C. Autoimmune hepatitis
Why it’s tempting: Female with autoimmune history and elevated transaminases.
Why it’s wrong here:
- Autoimmune hepatitis is hepatocellular, not cholestatic:
- Markedly elevated AST/ALT (often in the hundreds to thousands)
- ALP is not the main feature
- Antibodies:
- Anti–smooth muscle antibody (type 1)
- ANA may also be positive
- Biopsy classic: interface hepatitis with plasma cells
High-yield treatment:
- Corticosteroids (e.g., prednisone) ± azathioprine
Exam move: If AST/ALT dominate and autoantibodies are ANA/ASMA → autoimmune hepatitis.
D. Choledocholithiasis
Why it’s tempting: Obstructive jaundice picture can cause pruritus + cholestatic labs.
Why it’s wrong here:
- Ultrasound shows no bile duct dilation and no stones.
- Choledocholithiasis often presents with colicky RUQ pain, sometimes radiating to the back/right shoulder.
- If complicated:
- Ascending cholangitis: fever + jaundice + RUQ pain (Charcot triad), possibly hypotension/confusion (Reynolds pentad)
- Gallstone pancreatitis: epigastric pain + ↑lipase
Exam move: Extrahepatic obstruction typically → dilated ducts on ultrasound.
E. Secondary biliary cholangitis
Why it’s tempting: “Cholangitis” plus cholestatic labs might make you think inflammation of bile ducts.
Why it’s wrong here:
- Secondary biliary cholangitis is due to prolonged obstruction or injury to bile ducts, such as:
- Surgical injury/stricture
- Recurrent stones causing chronic obstruction
- Ischemic injury, AIDS cholangiopathy (rare)
- You’d expect a history suggesting obstruction/instrumentation and often imaging abnormalities.
Exam move: If the stem hands you an inciting obstruction or iatrogenic injury, then consider secondary biliary cholangitis.
High-Yield “PBC vs PSC” Table (classic Step differentiator)
| Feature | PBC | PSC |
|---|---|---|
| Typical patient | Middle-aged woman | Middle-aged man |
| Ducts involved | Intrahepatic (small ducts) | Intrahepatic + extrahepatic |
| Antibodies | AMA (anti-mitochondrial) | p-ANCA (association) |
| Major association | Other autoimmune diseases (e.g., thyroid disease, Sjögren) | Ulcerative colitis |
| Imaging | Often normal early; no obstruction | MRCP/ERCP: beading |
| Cancer risk | HCC risk once cirrhotic | Cholangiocarcinoma (+ colon ca in UC) |
| First-line disease therapy | Ursodiol | No definitive med; manage complications; transplant in advanced disease |
Test-Day Takeaways (what to memorize)
- PBC = autoimmune destruction of intrahepatic bile ducts in women, AMA+, cholestatic labs (ALP↑), pruritus + fatigue, treat with ursodiol, pruritus improves with cholestyramine.
- If the ducts are dilated, think extrahepatic obstruction (stone, cancer) first.
- PSC = UC + beading + cholangiocarcinoma risk.
- Autoimmune hepatitis = AST/ALT dominant + ASMA/ANA + interface hepatitis.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
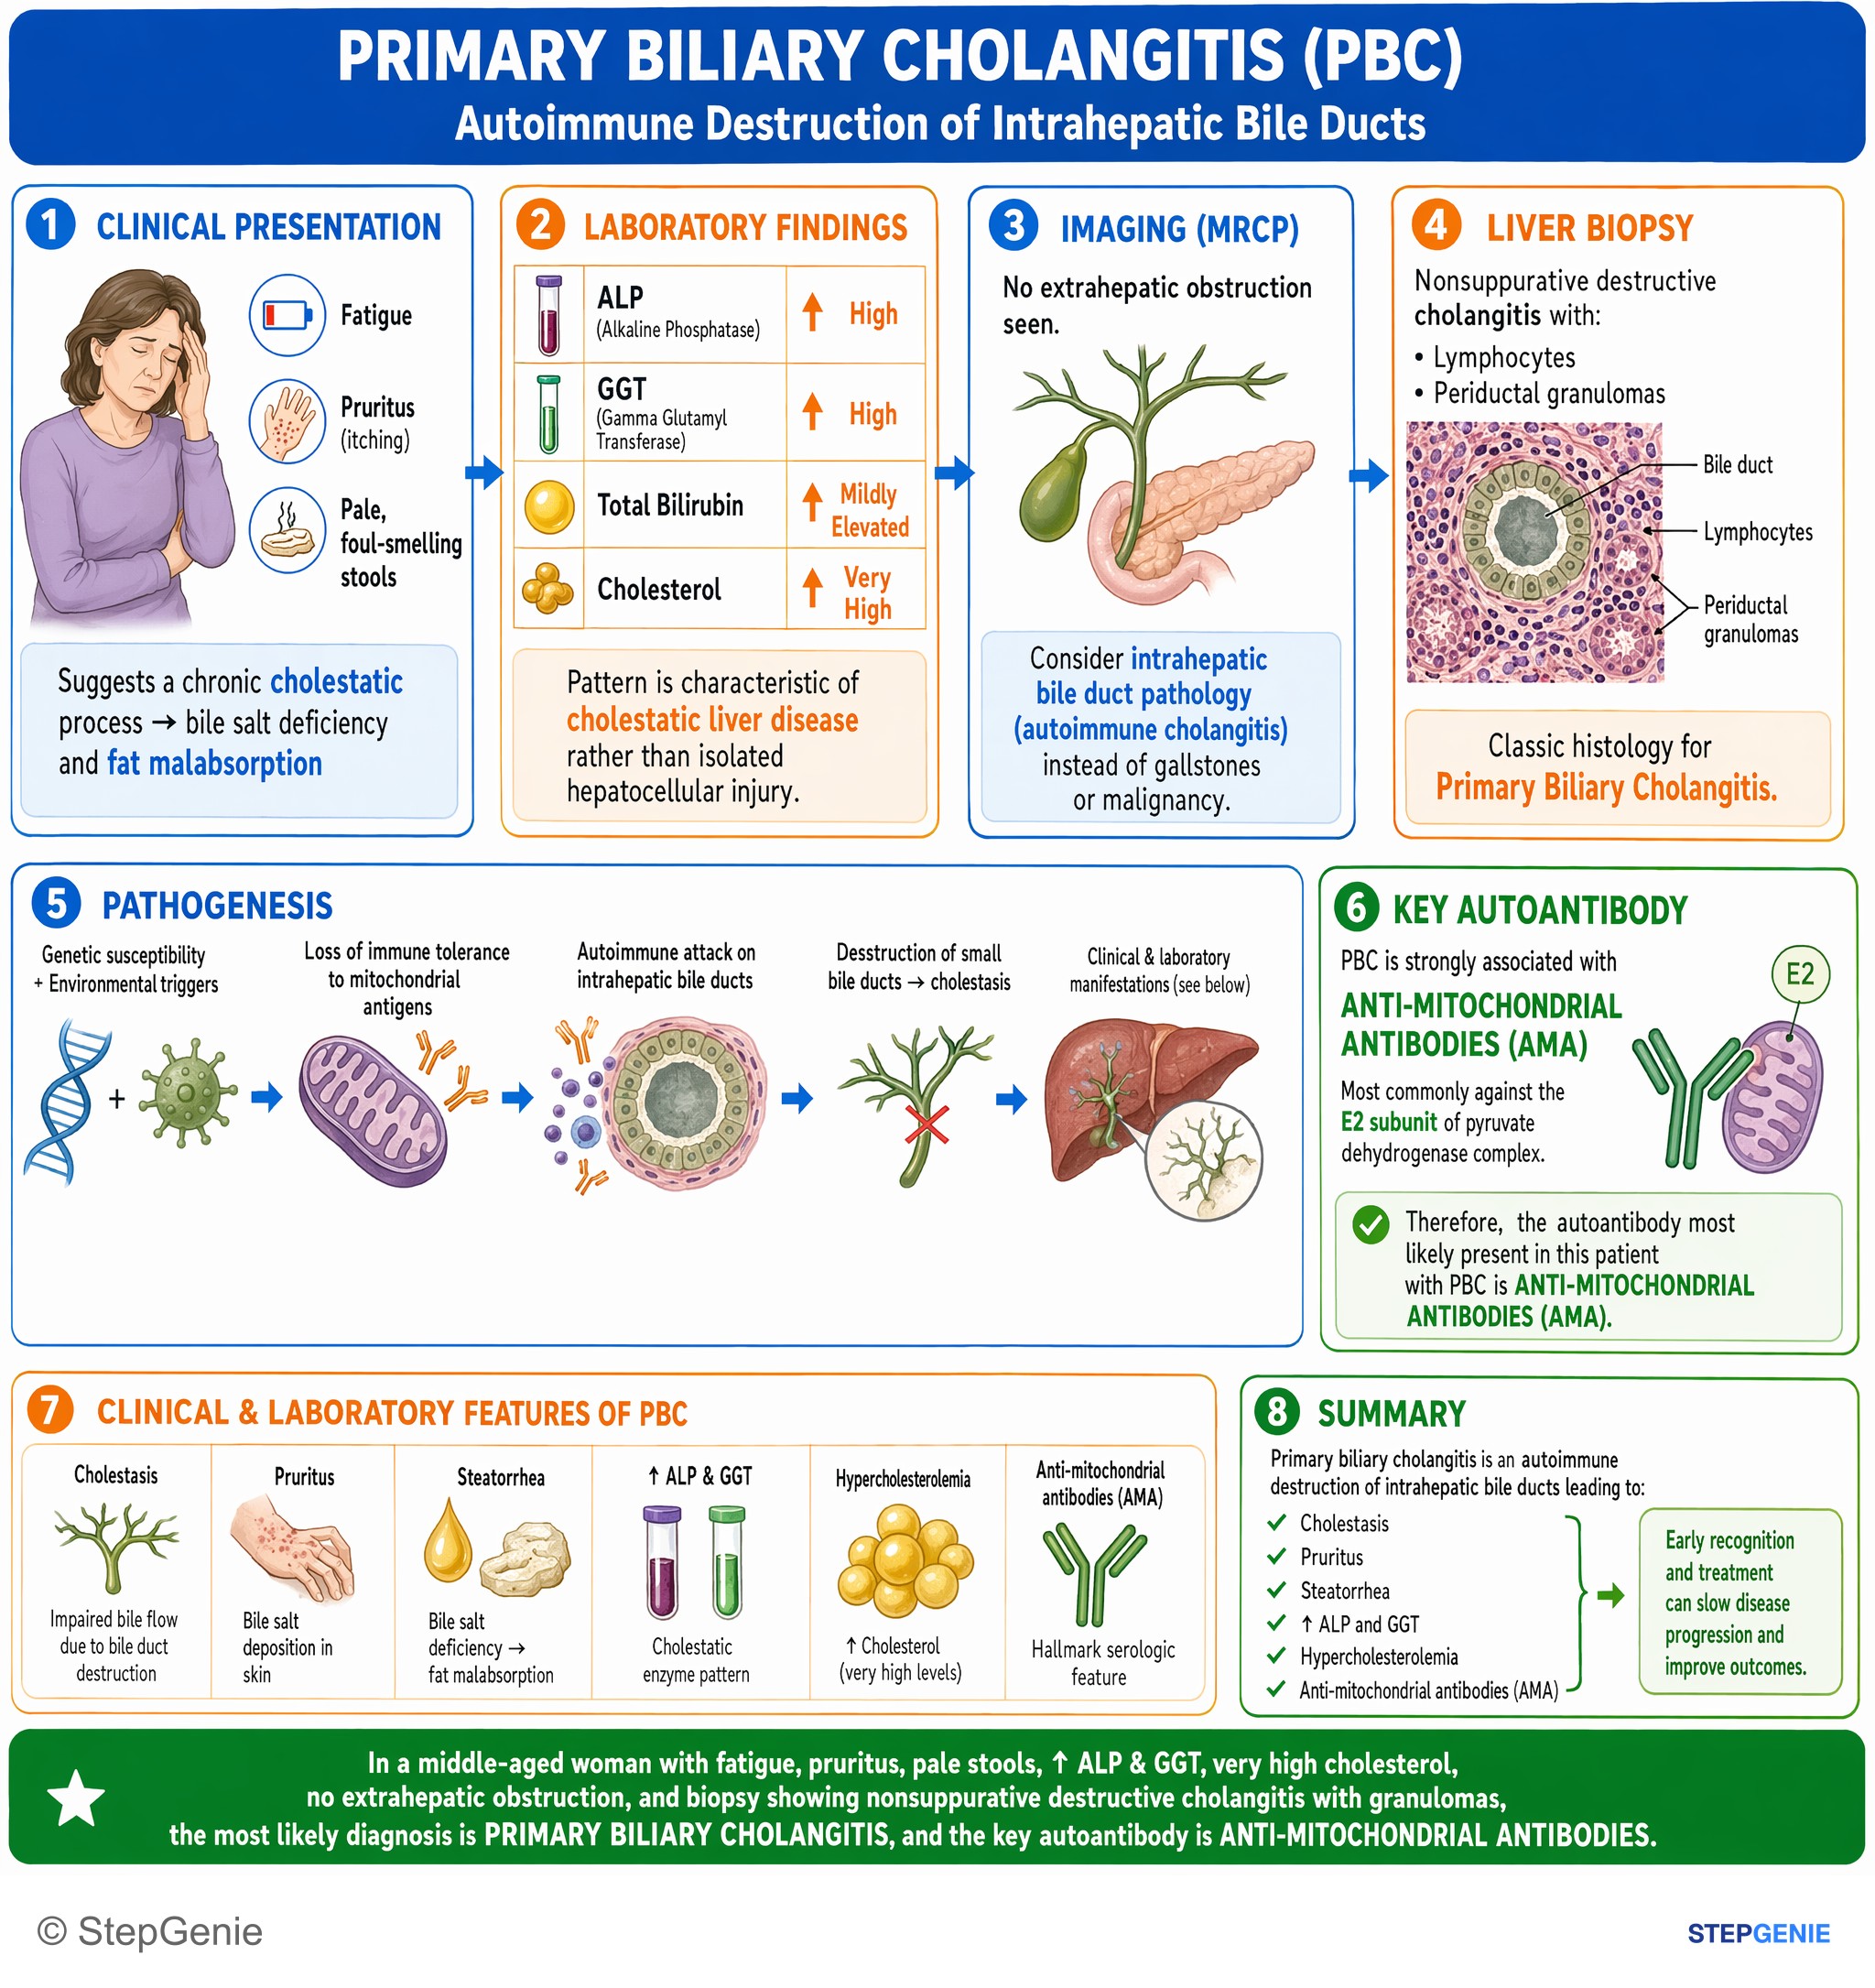
Primary biliary cholangitis causes autoimmune destruction of intrahepatic bile ducts → cholestasis, pruritus, steatorrhea, ↑ALP…
USMLE Step 1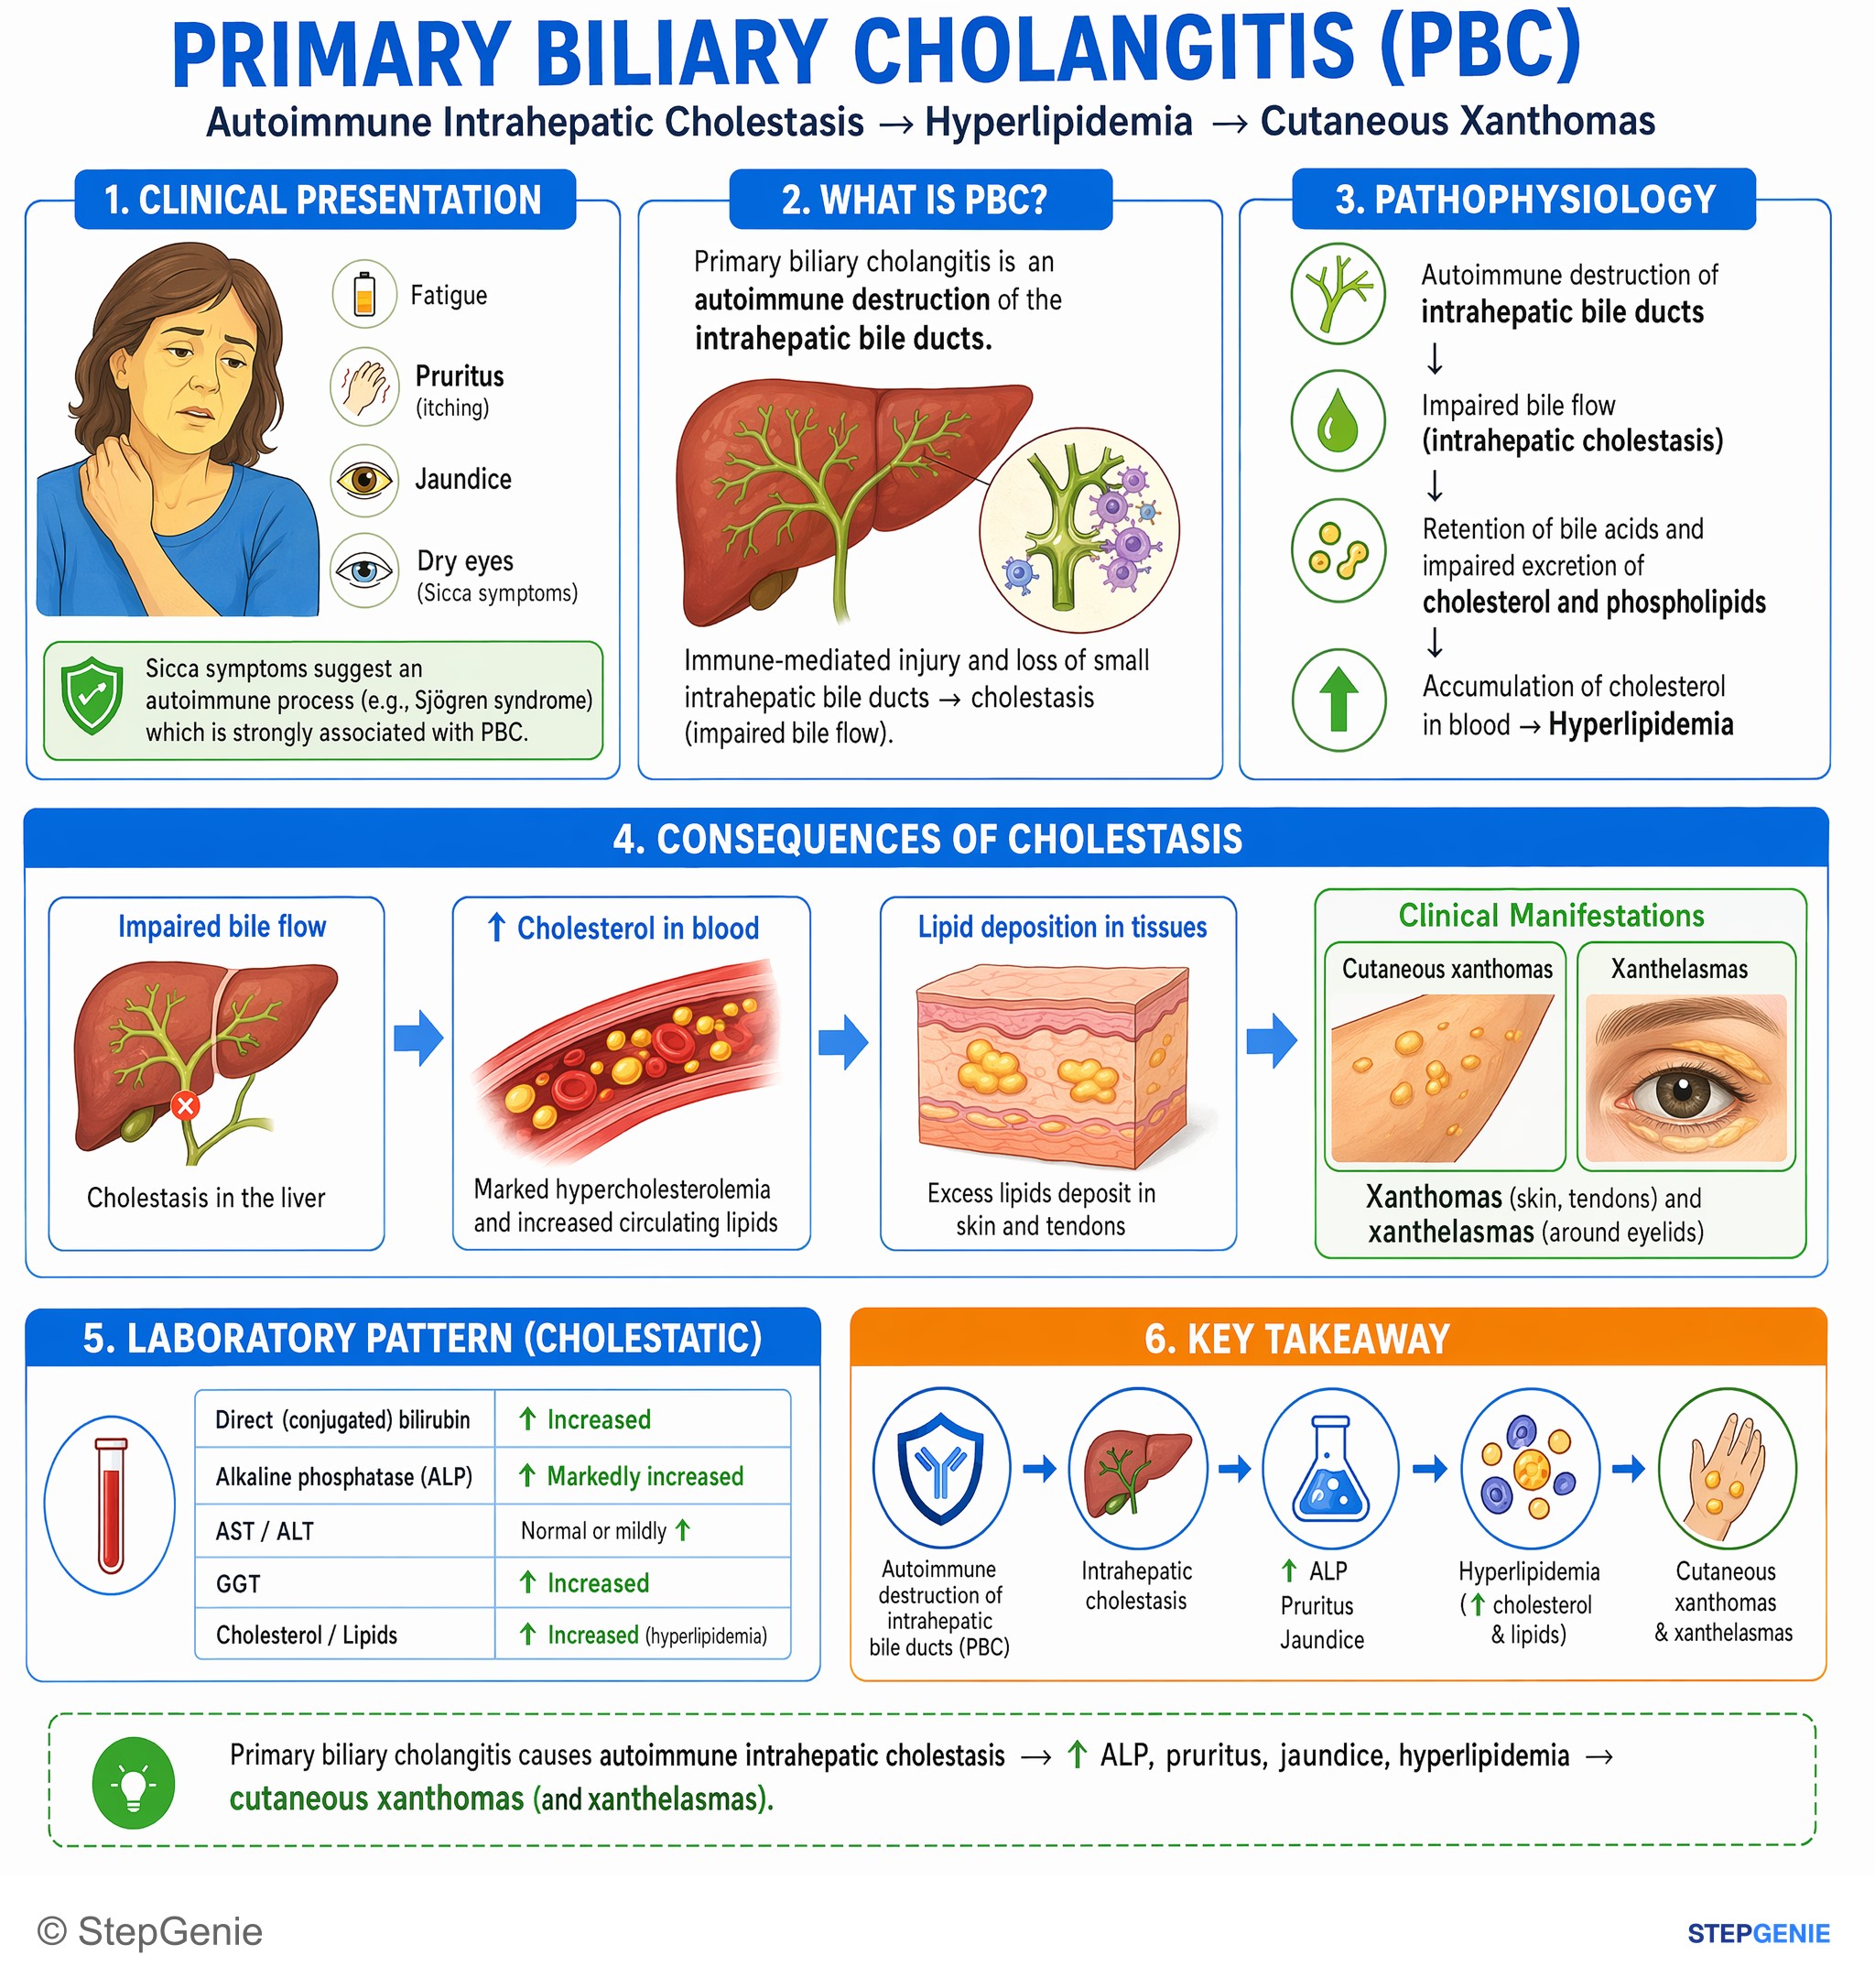
Primary biliary cholangitis causes autoimmune intrahepatic cholestasis → ↑alkaline phosphatase, pruritus, jaundice, hyperlipidemia →…
USMLE Step 1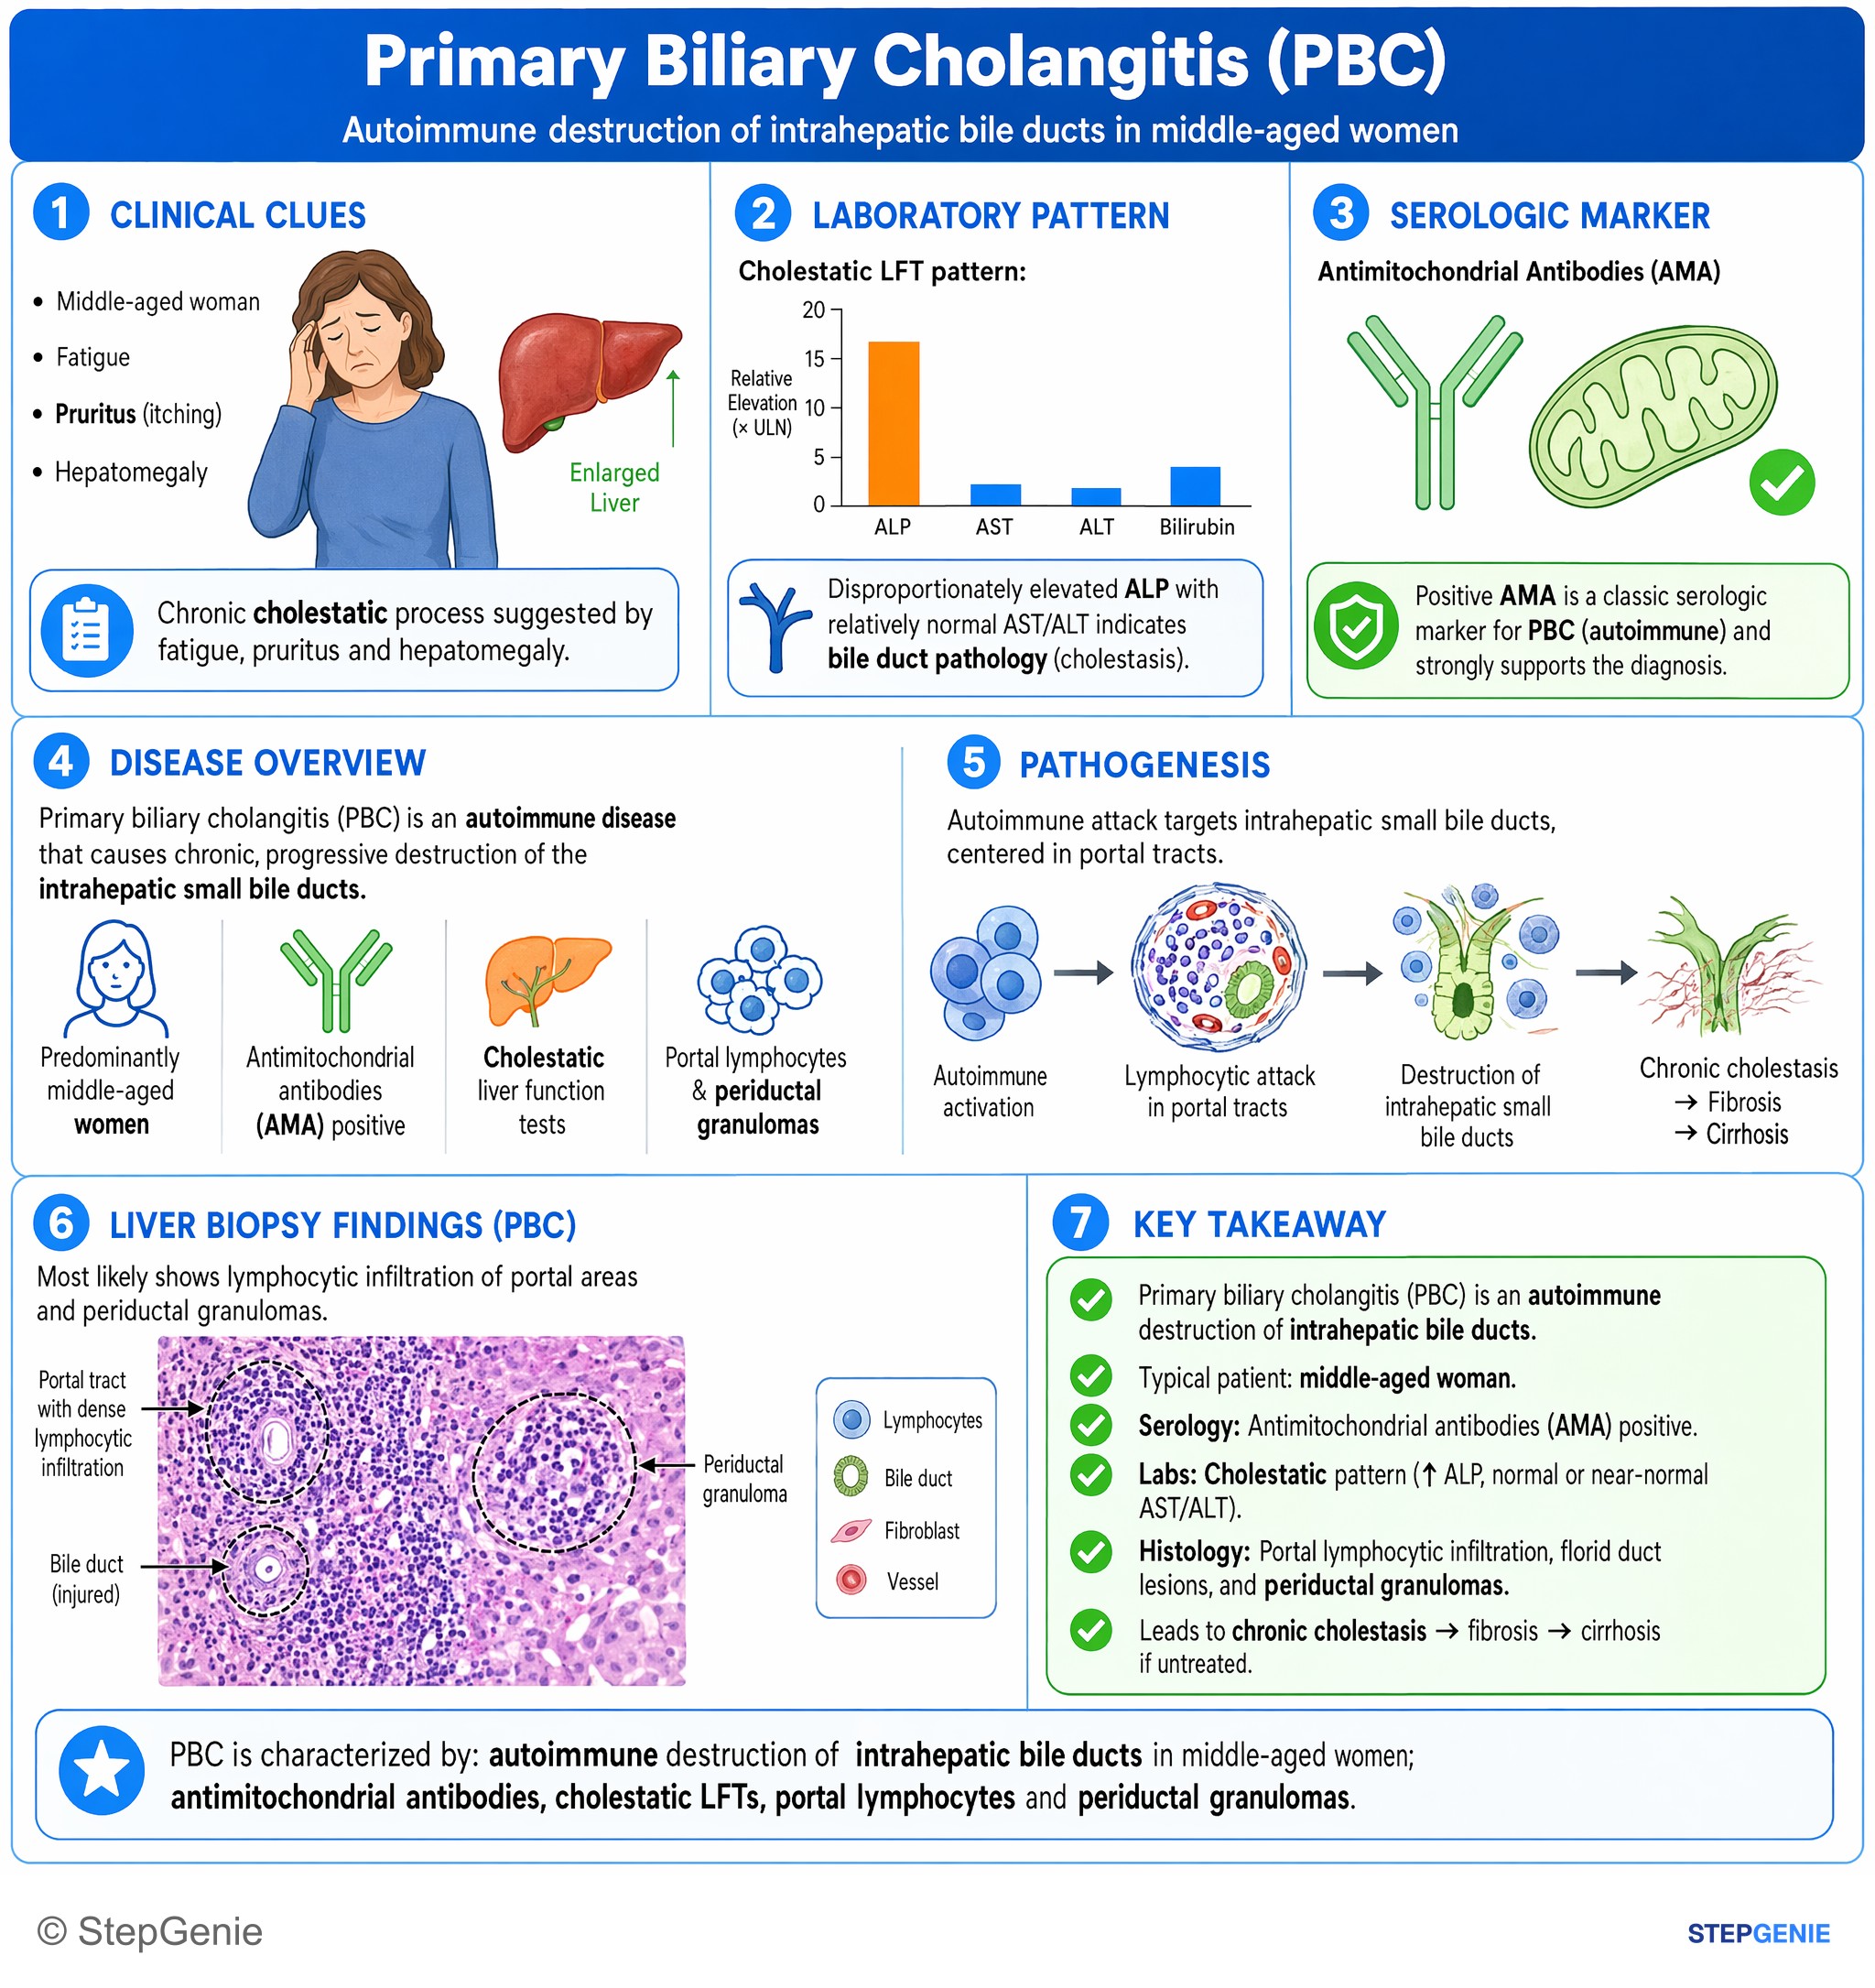
Primary biliary cholangitis: autoimmune destruction of intrahepatic bile ducts in middle-aged women; antimitochondrial antibodies…
USMLE Step 1Frequently Asked Questions
How do you recognize primary biliary cholangitis on a vignette?
Primary biliary cholangitis is suggested by a cholestatic pattern in a middle-aged woman with pruritus, fatigue, and positive anti-mitochondrial antibodies. The typical lab pattern is markedly elevated alkaline phosphatase and GGT with only mild AST and ALT elevation. An ultrasound without bile duct dilation points away from a large extrahepatic obstruction and supports an intrahepatic cholestatic process like PBC.
Why does primary biliary cholangitis cause pruritus and later cirrhosis?
Primary biliary cholangitis causes pruritus and progressive liver disease because autoimmune destruction of intrahepatic bile ducts leads to chronic cholestasis. Impaired bile flow contributes to itching, and cholestatic itching is mediated in part by bile acids. Over time, persistent cholestasis can cause progressive fibrosis and eventually cirrhosis, with complications such as portal hypertension, ascites, and varices.
How do you tell primary biliary cholangitis from primary sclerosing cholangitis?
Primary biliary cholangitis is favored when a middle-aged woman has autoimmune history, positive anti-mitochondrial antibodies, and intrahepatic cholestasis without duct dilation. Primary sclerosing cholangitis is classically seen in men, is associated with ulcerative colitis, and involves both intrahepatic and extrahepatic ducts. Its imaging hallmark is beading on MRCP or ERCP, and p-ANCA may be positive rather than AMA.
How do you tell primary biliary cholangitis from autoimmune hepatitis?
Primary biliary cholangitis is cholestatic, while autoimmune hepatitis is hepatocellular. In PBC, alkaline phosphatase and GGT are disproportionately elevated and anti-mitochondrial antibodies are a major clue. In autoimmune hepatitis, AST and ALT are the dominant abnormalities, often much higher, and the antibody pattern is anti-smooth muscle antibody and sometimes ANA. Biopsy classically shows interface hepatitis with plasma cells in autoimmune hepatitis.
What is the first-line treatment for primary biliary cholangitis, and what helps the itching?
Ursodeoxycholic acid, also called ursodiol, is the first-line treatment for primary biliary cholangitis. It improves bile flow and labs and slows disease progression. For persistent itching, cholestyramine is the classic board-style answer because it is a bile acid sequestrant used for cholestatic pruritus. Obeticholic acid is used when there is inadequate response or intolerance, and liver transplant is considered in end-stage disease.