Nonalcoholic fatty liver disease (NAFLD) and its inflammatory cousin, nonalcoholic steatohepatitis (NASH), show up in Q-banks because they’re high-yield, common, and packed with distractor traps (alcohol, viral hepatitis, hemochromatosis, Wilson, PBC/PSC). The key is learning to read the vignette like a checklist: risk factors → labs pattern → imaging/biopsy → what the question is actually asking.
Tag: GI > Hepatic Disorders
The Clinical Vignette
A 52-year-old woman comes to clinic for fatigue. She has type 2 diabetes mellitus and obesity (BMI 34). She drinks alcohol “only on holidays.” Vitals are normal. Exam shows central adiposity; no jaundice or ascites. Labs:
| Test | Result |
|---|---|
| AST | 68 U/L |
| ALT | 92 U/L |
| Alk phos | 92 U/L |
| Total bilirubin | 0.8 mg/dL |
| Platelets | 230k/µL |
| Hepatitis B surface antigen | Negative |
| Hepatitis C antibody | Negative |
Ultrasound shows increased hepatic echogenicity (“bright liver”) consistent with fatty infiltration.
Question: Which of the following best describes the underlying pathogenesis of her liver disease?
A. Accumulation of triglycerides in hepatocytes due to insulin resistance causing increased lipolysis and hepatic de novo lipogenesis
B. Autoimmune destruction of intrahepatic bile ducts leading to cholestasis
C. Iron deposition from increased intestinal absorption due to HFE mutation
D. Copper accumulation due to impaired biliary excretion
E. Alcohol-induced oxidative injury with a high NADH/NAD⁺ ratio leading to steatosis
Step-by-Step: What This Vignette Is Screaming
1) Risk factors
- Obesity + type 2 diabetes = metabolic syndrome = NAFLD/NASH risk
- Alcohol use is minimal (important because alcoholic liver disease is the classic distractor)
2) Lab pattern
- Mild-to-moderate transaminitis
- Often ALT > AST early in NAFLD/NASH (not a strict rule, but common)
- Normal bilirubin and alk phos argues against cholestatic processes (PBC/PSC)
3) Imaging clue
- “Bright liver” on ultrasound = hepatic steatosis
- Imaging can detect fat, but cannot reliably distinguish NAFLD vs NASH (that distinction is biopsy-based)
Correct Answer: A. Insulin Resistance → Steatosis (NAFLD/NASH Pathogenesis)
NAFLD is essentially the hepatic manifestation of metabolic syndrome.
High-yield pathogenesis (board-friendly version)
Insulin resistance drives:
- Increased lipolysis in adipose tissue → more free fatty acids delivered to liver
- Increased hepatic de novo lipogenesis
- Decreased fatty acid oxidation and impaired VLDL export (contributes)
Result: triglyceride accumulation in hepatocytes (steatosis).
NAFLD vs NASH (do not blur these)
- NAFLD (simple steatosis): fat in liver with minimal inflammation
- NASH: steatosis plus hepatocyte injury and inflammation (ballooning degeneration); can progress to fibrosis → cirrhosis → HCC
Biopsy is the classic way to distinguish NASH from simple steatosis:
- Ballooning degeneration
- Lobular inflammation
- +/- Mallory-Denk bodies (not exclusive to alcohol)
High-yield clinical associations
- Obesity, T2DM, dyslipidemia
- Can present with fatigue, RUQ discomfort, or be asymptomatic
- Often found on incidental labs (mild transaminitis)
One-liner worth memorizing
NAFLD/NASH = insulin resistance → fatty liver; NASH is the one that scars.
Why Each Distractor Is Wrong (and When It Would Be Right)
B. Autoimmune destruction of intrahepatic bile ducts (Primary biliary cholangitis, PBC)
Why it’s wrong here:
- PBC is a cholestatic disease → expect high alkaline phosphatase, pruritus, fatigue
- This patient’s alk phos is normal, and ultrasound suggests steatosis
When it would be right:
- Middle-aged woman with pruritus, fatigue
- Elevated alk phos
- Antimitochondrial antibody (AMA) positive
- Granulomatous destruction of intrahepatic bile ducts
Board tip:
If the stem emphasizes itching + alk phos, your reflex should be PBC/PSC, not NAFLD.
C. Iron deposition due to HFE mutation (Hereditary hemochromatosis)
Why it’s wrong here:
- Hemochromatosis can cause elevated AST/ALT, but the vignette points strongly to metabolic syndrome + fatty liver on ultrasound
- No mention of bronze diabetes, arthropathy, cardiomyopathy, or hypogonadism
When it would be right:
- Elevated transferrin saturation (often earliest) and high ferritin
- HFE mutation (classically C282Y)
- Findings: cirrhosis, diabetes, cardiomyopathy, arthropathy (MCP joints), skin hyperpigmentation
Micro-path tie-in:
Iron deposition in organs → oxidative damage → fibrosis/cirrhosis.
D. Copper accumulation due to impaired biliary excretion (Wilson disease)
Why it’s wrong here:
- Wilson is typically younger (teens–30s)
- Would expect neuro/psych symptoms, hemolysis, or Kayser–Fleischer rings depending on presentation
- This patient’s risk profile screams metabolic syndrome
When it would be right:
- Young person with hepatitis/cirrhosis + neurologic/psychiatric symptoms
- Labs: low ceruloplasmin, increased urinary copper
- Eye: Kayser–Fleischer rings
- Liver biopsy: increased hepatic copper
High-yield nuance:
Wilson can present as acute liver failure with Coombs-negative hemolytic anemia.
E. Alcohol-induced oxidative injury with high NADH/NAD⁺ ratio (Alcohol-associated fatty liver)
Why it’s wrong here:
- The stem explicitly downplays alcohol intake
- Lab pattern in alcoholic liver disease often shows AST > ALT with ratio ≥ 2:1 (AST/ALT both usually < 500)
When it would be right:
- Significant alcohol use history
- Labs: AST:ALT ≥ 2, elevated GGT can support alcohol use
- Path: increased NADH shifts metabolism toward lipogenesis → hepatic steatosis
- Severe form: alcoholic hepatitis with fever, tender hepatomegaly, jaundice; can have Mallory-Denk bodies and neutrophils
Trap alert:
Mallory-Denk bodies can be seen in both alcoholic hepatitis and NASH—don’t let that be your deciding factor. Use the history and lab pattern.
High-Yield NAFLD/NASH Facts You’ll Get Tested On
Typical lab/imaging patterns
- Mild-moderate AST/ALT elevation (often ALT > AST early)
- Normal or mildly elevated alk phos
- Ultrasound: hyperechoic “bright” liver
- Biopsy confirms NASH and stages fibrosis
Progression and outcomes
- NAFLD can progress to NASH; NASH can progress to cirrhosis
- Cirrhosis complications apply: portal HTN, varices, ascites, encephalopathy
- Increased risk of hepatocellular carcinoma (especially once cirrhotic; can occur in NAFLD-related disease)
Management (Step 2-relevant framing)
- Weight loss and lifestyle modification are cornerstone
- Control metabolic risk factors: glucose, lipids, BP
- Avoid hepatotoxins (including alcohol) and review meds
- Consider fibrosis risk stratification (you’ll see this concept clinically)
Q-Bank Strategy: How to “Win” NAFLD/NASH Questions
When you see obesity/T2DM + mild transaminitis, ask:
- Is the pattern hepatocellular (AST/ALT) or cholestatic (alk phos)?
- Any strong alternate etiology clues?
- Viral risk → hep B/C testing
- Heavy alcohol → AST/ALT ratio ≥ 2
- Neuro psych + young → Wilson
- High iron studies → hemochromatosis
- Itching + AMA/alk phos → PBC
- Are they asking diagnosis, pathogenesis, or confirmatory test?
- NAFLD suggested by imaging + risk factors
- NASH requires biopsy to prove inflammation/ballooning/fibrosis
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
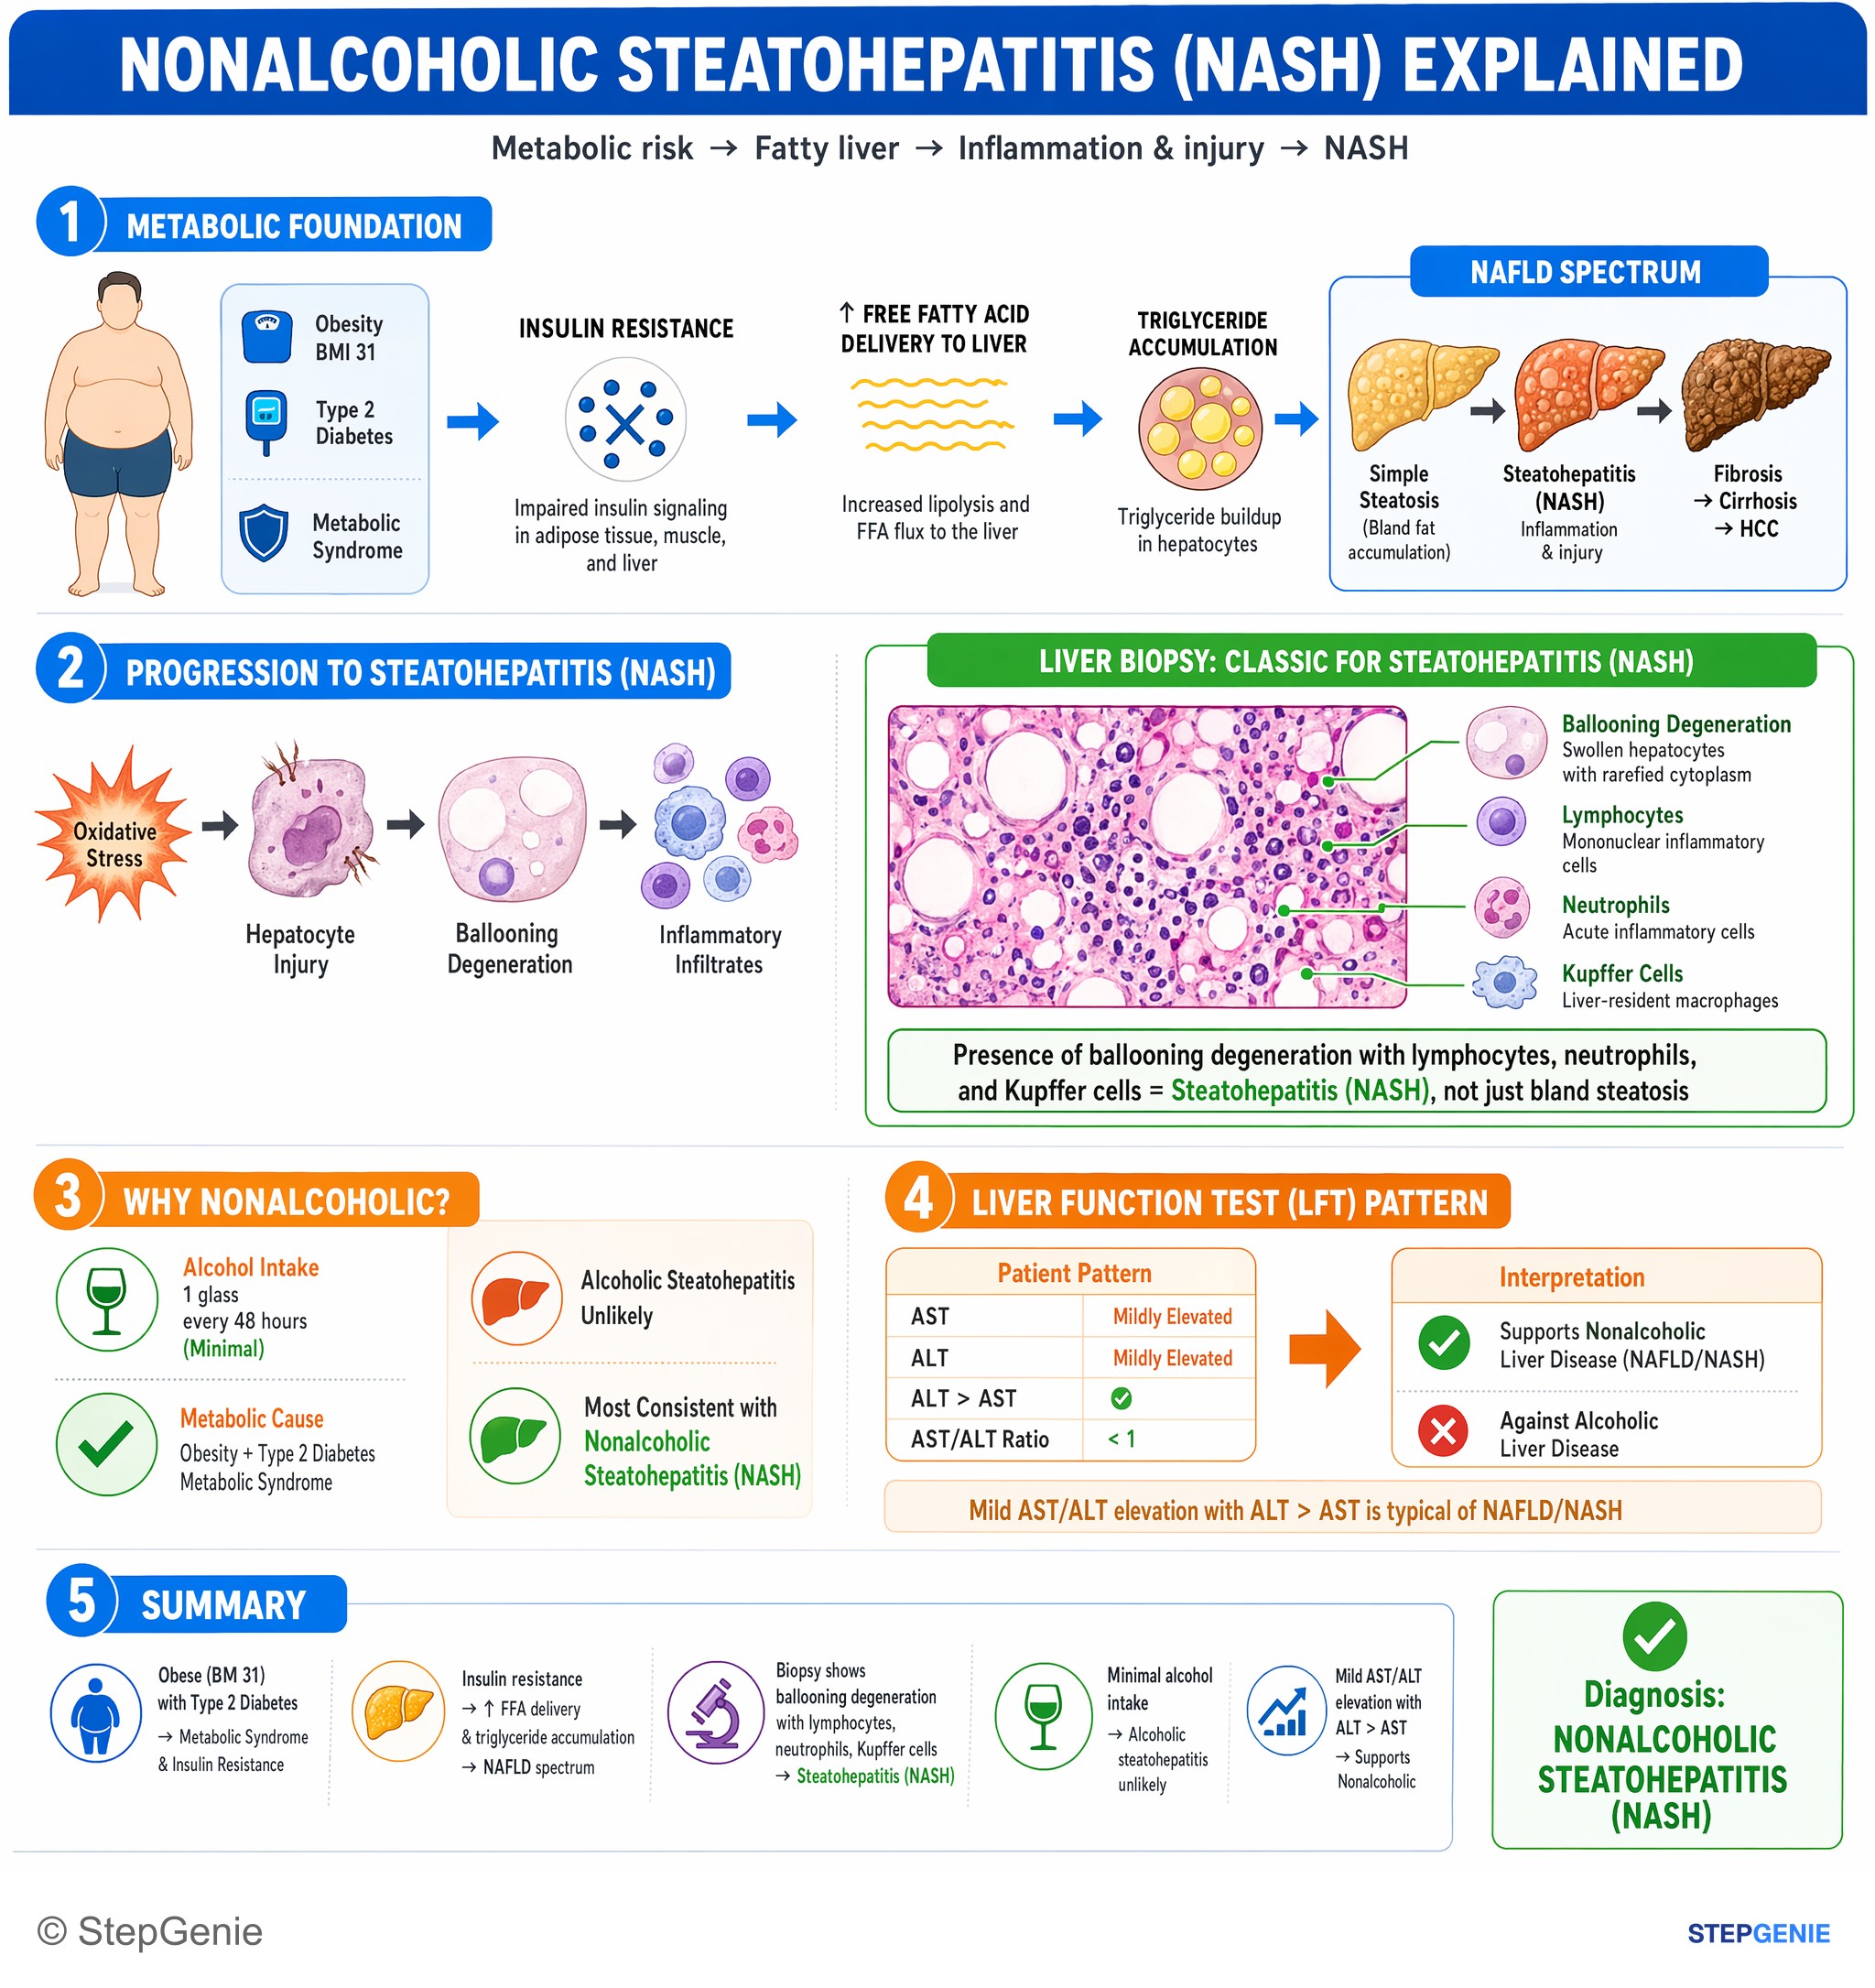
Nonalcoholic steatohepatitis (NASH): obese diabetic with minimal alcohol use, mild AST/ALT elevation, ballooning degeneration and…
USMLE Step 2Frequently Asked Questions
Why does insulin resistance cause fatty liver in NAFLD/NASH?
Insulin resistance causes triglycerides to accumulate in hepatocytes. It increases lipolysis in adipose tissue so more free fatty acids are delivered to the liver, and it also increases hepatic de novo lipogenesis. Decreased fatty acid oxidation and impaired VLDL export can contribute as well, producing the steatosis seen in NAFLD and NASH.
How do you tell NAFLD/NASH from alcoholic liver disease on a vignette?
NAFLD/NASH is suggested by obesity, type 2 diabetes, and minimal alcohol use, often with mild transaminitis and ALT greater than AST early on. Alcohol-associated liver disease is more likely when the history shows significant alcohol use and the labs show AST greater than ALT, often with a ratio of at least 2:1. The alcohol stem may also mention elevated GGT or alcoholic hepatitis features.
What does a bright liver on ultrasound mean, and can it tell NAFLD from NASH?
A bright liver on ultrasound means hepatic steatosis, or fatty infiltration of the liver. Ultrasound can detect fat, but it cannot reliably distinguish simple NAFLD from NASH. That distinction is classically made by biopsy, which shows steatosis plus hepatocyte injury and inflammation in NASH, including ballooning degeneration and lobular inflammation.
How do you distinguish NAFLD/NASH from PBC on labs and clinical clues?
NAFLD/NASH usually presents with mild transaminitis in a patient with metabolic syndrome, while bilirubin and alkaline phosphatase may be normal. Primary biliary cholangitis is a cholestatic disease, so the stem tends to emphasize pruritus, fatigue, and an elevated alkaline phosphatase. A middle-aged woman with itching and cholestatic labs should push you toward PBC rather than fatty liver disease.
Why is NASH more dangerous than simple NAFLD?
NASH is more dangerous because it includes hepatocyte injury and inflammation in addition to steatosis. Simple NAFLD is fat in the liver with minimal inflammation, but NASH can progress to fibrosis, cirrhosis, and hepatocellular carcinoma. A useful board-style distinction is that NAFLD is fatty liver from insulin resistance, while NASH is the form that scars.