Hemochromatosis questions are classic “looks like liver disease, but the real clue is systemic” vignettes. The trick is to spot the pattern (iron overload + end-organ damage) and then prove it by using each answer choice to rule in/rule out competing hepatic disorders.
Tag: GI > Hepatic Disorders
The Vignette (Q-bank style)
A 52-year-old man comes to clinic for fatigue and decreased libido. He has chronic joint pain in his hands and was recently told he has “borderline diabetes.” He drinks alcohol socially. Exam shows mild hepatomegaly and hyperpigmented skin. Labs:
- AST 68 U/L, ALT 62 U/L
- Alk phos 110 U/L (normal)
- Total bilirubin 1.1 mg/dL (normal)
- Ferritin: high
- Serum iron: high
- TIBC: low
- Transferrin saturation: 78%
Which of the following is the most likely underlying mechanism?
A. Mutation causing increased intestinal iron absorption
B. Autoimmune destruction of intrahepatic bile ducts
C. Accumulation of misfolded alpha-1 antitrypsin in hepatocytes
D. Defective copper excretion into bile
E. Inflammation and fibrosis centered on central veins due to chronic alcohol use
Correct Answer: A. Mutation causing increased intestinal iron absorption
This is hereditary hemochromatosis (HH): unregulated iron absorption leading to progressive iron deposition in organs.
Why it fits (pattern recognition + confirmatory labs)
Symptoms/Findings to anchor on:
- Fatigue (nonspecific but common)
- Decreased libido / hypogonadism (pituitary or gonadal iron deposition)
- “Borderline diabetes” (pancreatic iron deposition → “bronze diabetes”)
- Arthropathy (classically 2nd and 3rd MCP joints)
- Hyperpigmentation (“bronze” skin)
- Hepatomegaly (iron deposition in liver → fibrosis/cirrhosis, ↑HCC risk)
Labs that seal it:
- ↑ transferrin saturation (often the earliest abnormality; typically >45%)
- ↑ ferritin (reflects iron stores; can also rise with inflammation)
- ↑ serum iron + ↓ TIBC → high saturation
Pathophysiology (the mechanism behind A)
Most cases are due to HFE mutation (classically C282Y) → decreased hepcidin signaling (functionally) → increased ferroportin activity → increased iron export from enterocytes/macrophages → increased intestinal iron absorption and elevated circulating iron.
High-yield hepcidin rule:
- Hepcidin decreases iron in the blood.
- Low hepcidin (or hepcidin resistance) → more iron enters circulation.
Step-relevant associations
- Complications: cirrhosis, hepatocellular carcinoma, cardiomyopathy, diabetes, arthropathy, hypogonadism
- Diagnosis approach (common test logic):
- Screen with transferrin saturation
- Confirm with HFE genetic testing
- Liver biopsy if staging fibrosis is needed (or unclear diagnosis)
- Treatment: phlebotomy (first-line); chelation (e.g., deferasirox) if phlebotomy not possible
Why Every Other Answer Choice Is Wrong (and what it would look like)
B. Autoimmune destruction of intrahepatic bile ducts
This describes: Primary biliary cholangitis (PBC)
What you’d expect instead:
- Cholestatic pattern: ↑ alkaline phosphatase (often much higher than AST/ALT)
- Pruritus, fatigue, jaundice
- Anti-mitochondrial antibodies (AMA) positive
- Middle-aged women are typical
Why it’s wrong here: Alk phos is normal-ish, and the vignette screams iron overload systemic disease (diabetes + hyperpigmentation + MCP arthropathy + high transferrin saturation).
C. Accumulation of misfolded alpha-1 antitrypsin in hepatocytes
This describes: Alpha-1 antitrypsin (A1AT) deficiency
What you’d expect instead:
- Liver disease + early emphysema (panacinar, lower lobes), especially in a smoker
- Possible neonatal jaundice or adult cirrhosis
- PAS-positive, diastase-resistant globules on biopsy (Step classic)
Why it’s wrong here: No pulmonary clue, and iron studies (especially very high transferrin saturation) point away from A1AT and toward HH.
D. Defective copper excretion into bile
This describes: Wilson disease (ATP7B mutation)
What you’d expect instead:
- Younger patient (often teens/20s)
- Hepatic disease + neuro/psych symptoms (tremor, dystonia, personality changes)
- Low ceruloplasmin, increased urinary copper
- Kayser–Fleischer rings
Why it’s wrong here: Age and symptom cluster (diabetes, bronze skin, MCP arthropathy) align with HH. Also, Wilson is a copper problem—iron studies wouldn’t show iron overload.
E. Inflammation and fibrosis centered on central veins due to chronic alcohol use
This describes: Alcohol-associated liver disease, especially alcoholic hepatitis/cirrhosis
What you’d expect instead:
- AST:ALT ≥ 2:1 (both usually <300 in alcoholic hepatitis)
- Macrocytosis, thrombocytopenia, signs of portal HTN in advanced disease
- Risk factors: heavy daily alcohol use
Why it’s wrong here: The vignette gives a systemic iron overload phenotype and iron studies that fit HH. Alcohol can raise ferritin, but transferrin saturation ~78% strongly favors true iron overload rather than inflammation alone.
Quick Comparison Table (High-Yield Hepatic Distractors)
| Disorder | Hallmark Symptoms | Key Labs/Tests | Pattern |
|---|---|---|---|
| Hereditary hemochromatosis | “Bronze diabetes,” arthropathy (MCP), hypogonadism, cardiomyopathy | ↑ transferrin saturation, ↑ ferritin; HFE mutation | Hepatocellular (often mild early) |
| PBC | Pruritus, fatigue, jaundice (middle-aged women) | ↑ Alk phos, AMA+ | Cholestatic |
| A1AT deficiency | Liver disease + early emphysema | Low A1AT level; PAS+ globules | Mixed/hepatocellular |
| Wilson | Liver + neuro/psych; KF rings | ↓ ceruloplasmin, ↑ urine copper | Variable |
| Alcohol-associated liver disease | Heavy drinking, RUQ pain, systemic inflammation | AST>ALT (≥2), macrocytosis | Hepatocellular |
USMLE High-Yield Takeaways (What to memorize)
- Best screening clue for HH: Transferrin saturation >45% (often earliest)
- Ferritin is an acute-phase reactant → can be high from inflammation, but high saturation is the “real deal” overload signal
- HH classic constellation:
- Cirrhosis (→ HCC risk)
- Diabetes
- Cardiomyopathy
- Arthropathy (MCP)
- Hypogonadism
- Hyperpigmentation
- Treatment: serial phlebotomy (and screen first-degree relatives)
Final Test-Day Tip: Use the Iron Panel Like a Weapon
When the stem hints systemic disease + liver involvement, glance at the iron studies:
- HH: ↑ iron, ↓ TIBC, ↑ saturation, ↑ ferritin
- Iron deficiency: ↓ iron, ↑ TIBC, ↓ ferritin
- Anemia of chronic disease: ↓ iron, ↓ TIBC, ↑ ferritin
If you see very high transferrin saturation, start thinking hemochromatosis—even if the question is “about the liver.”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
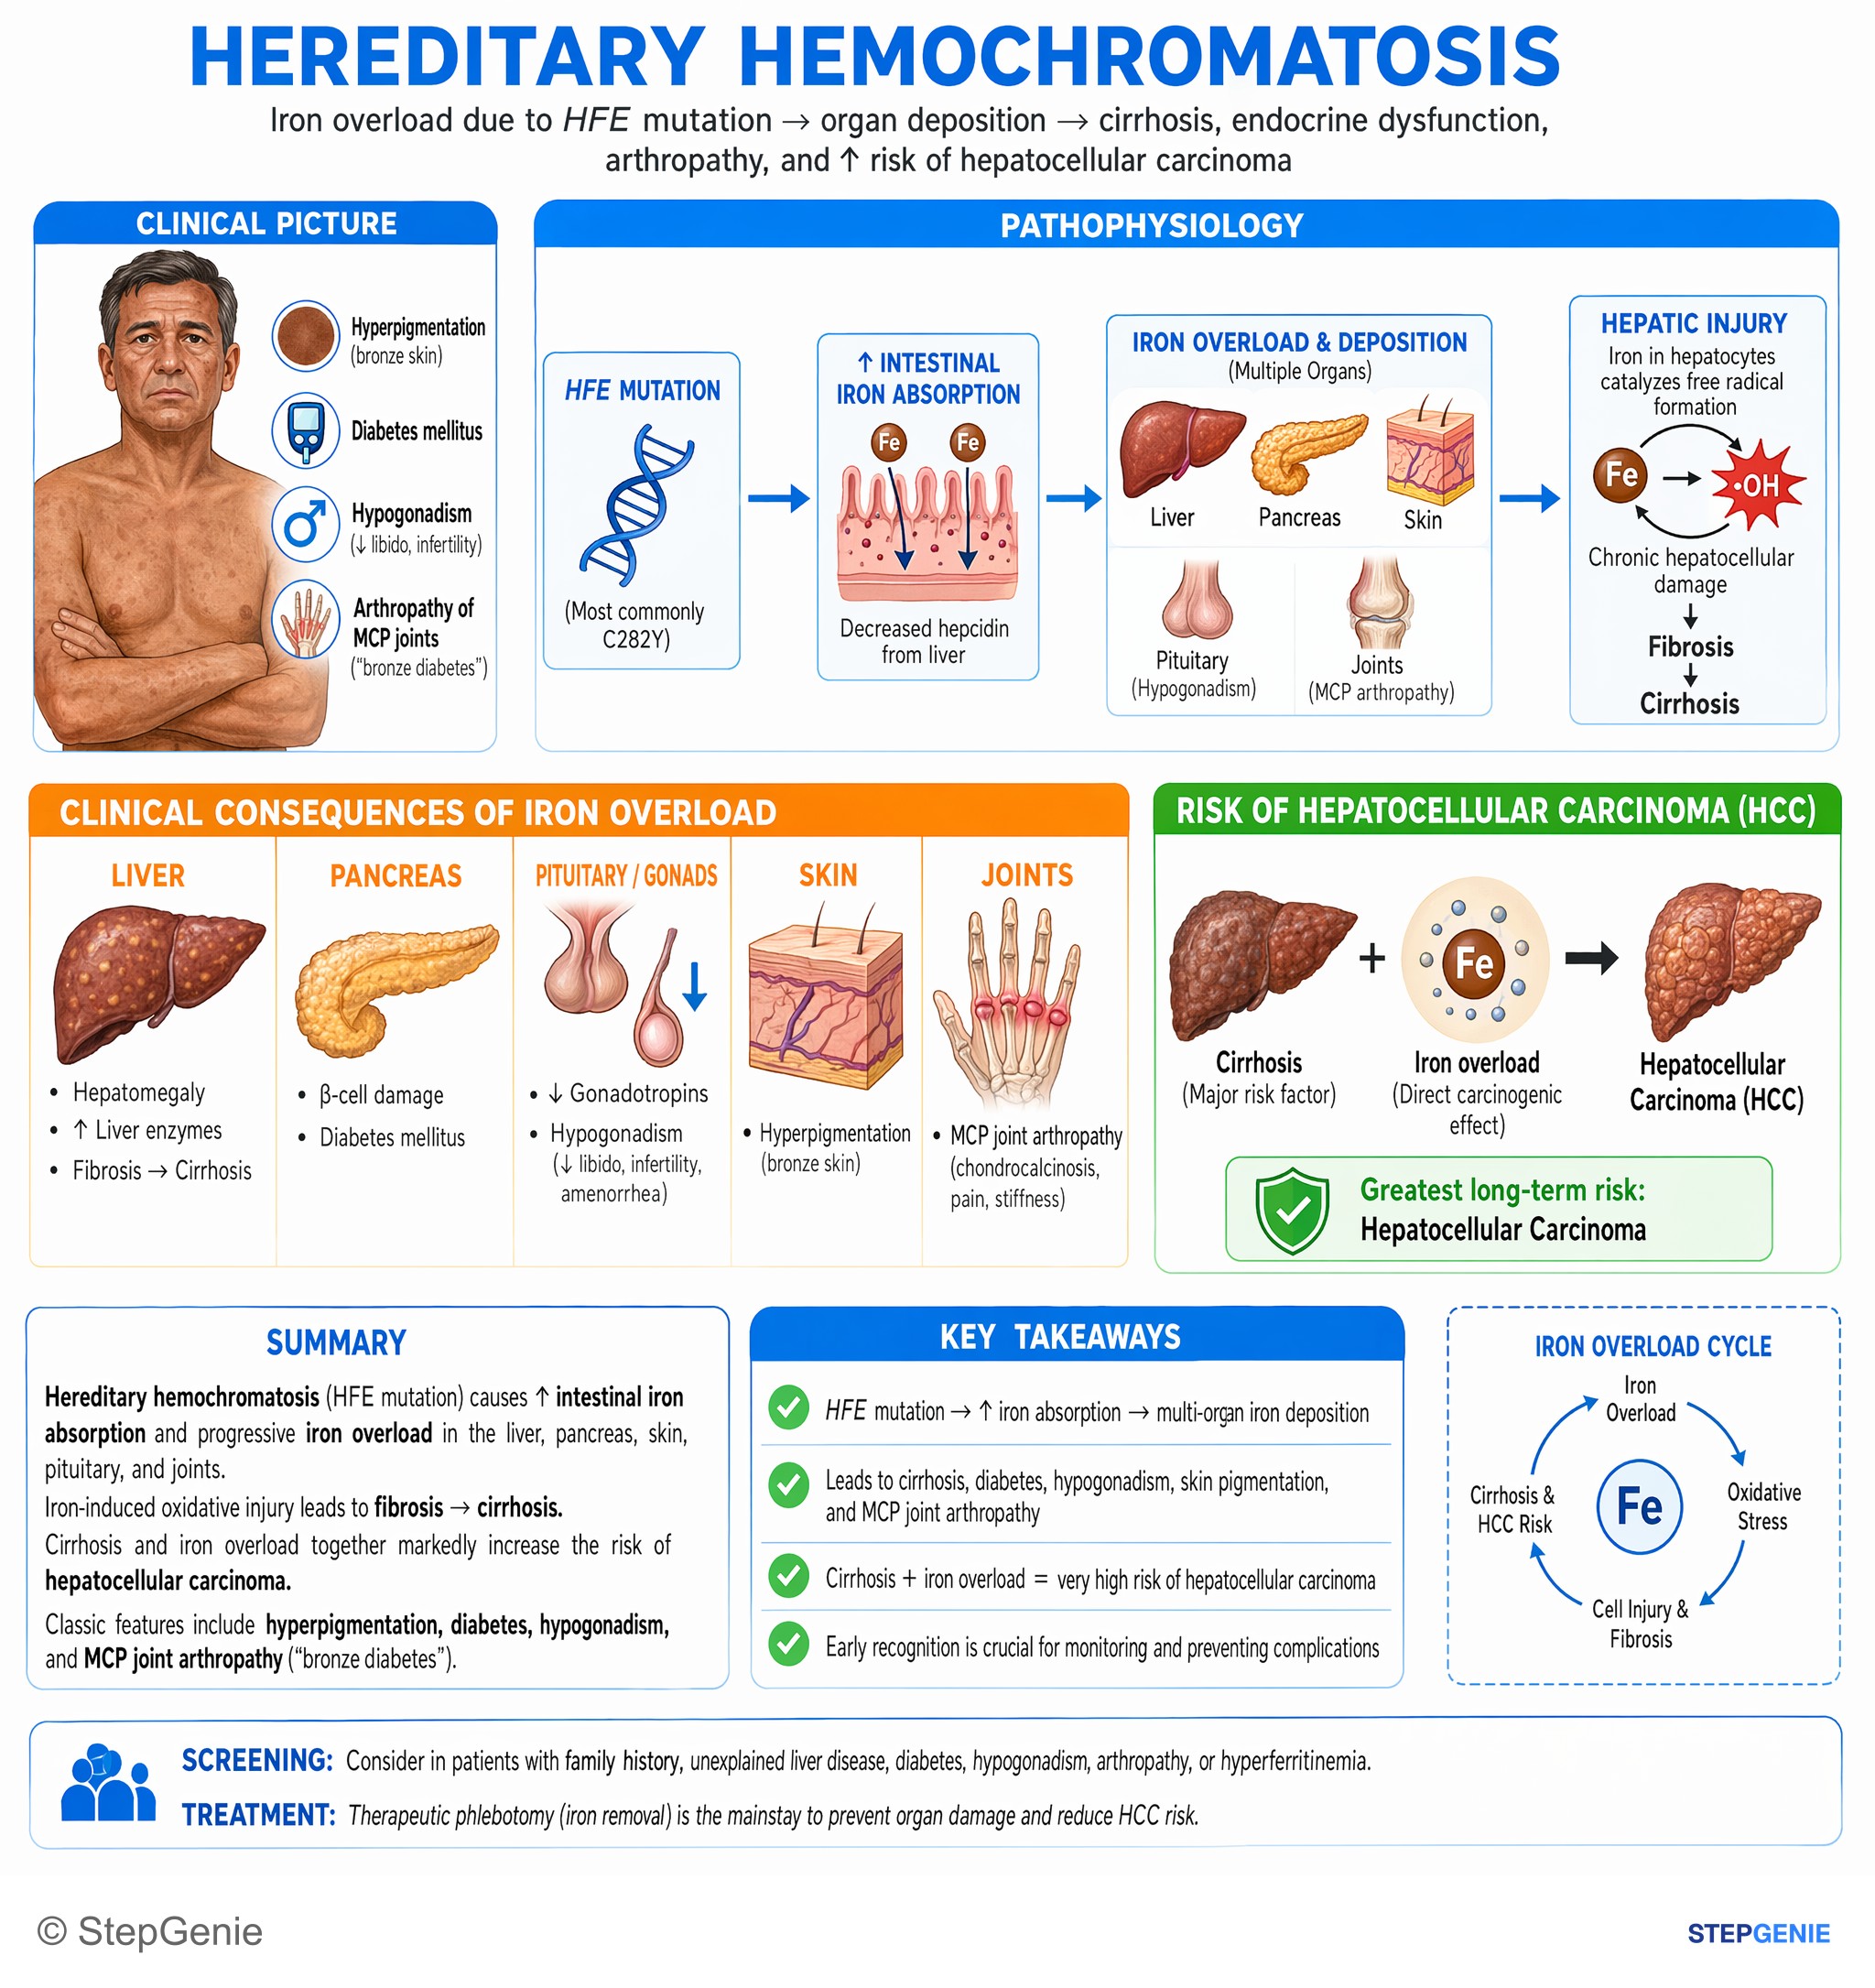
Hereditary hemochromatosis causes iron overload → cirrhosis, diabetes, hypogonadism, arthropathy → greatly increased risk of…
USMLE Step 1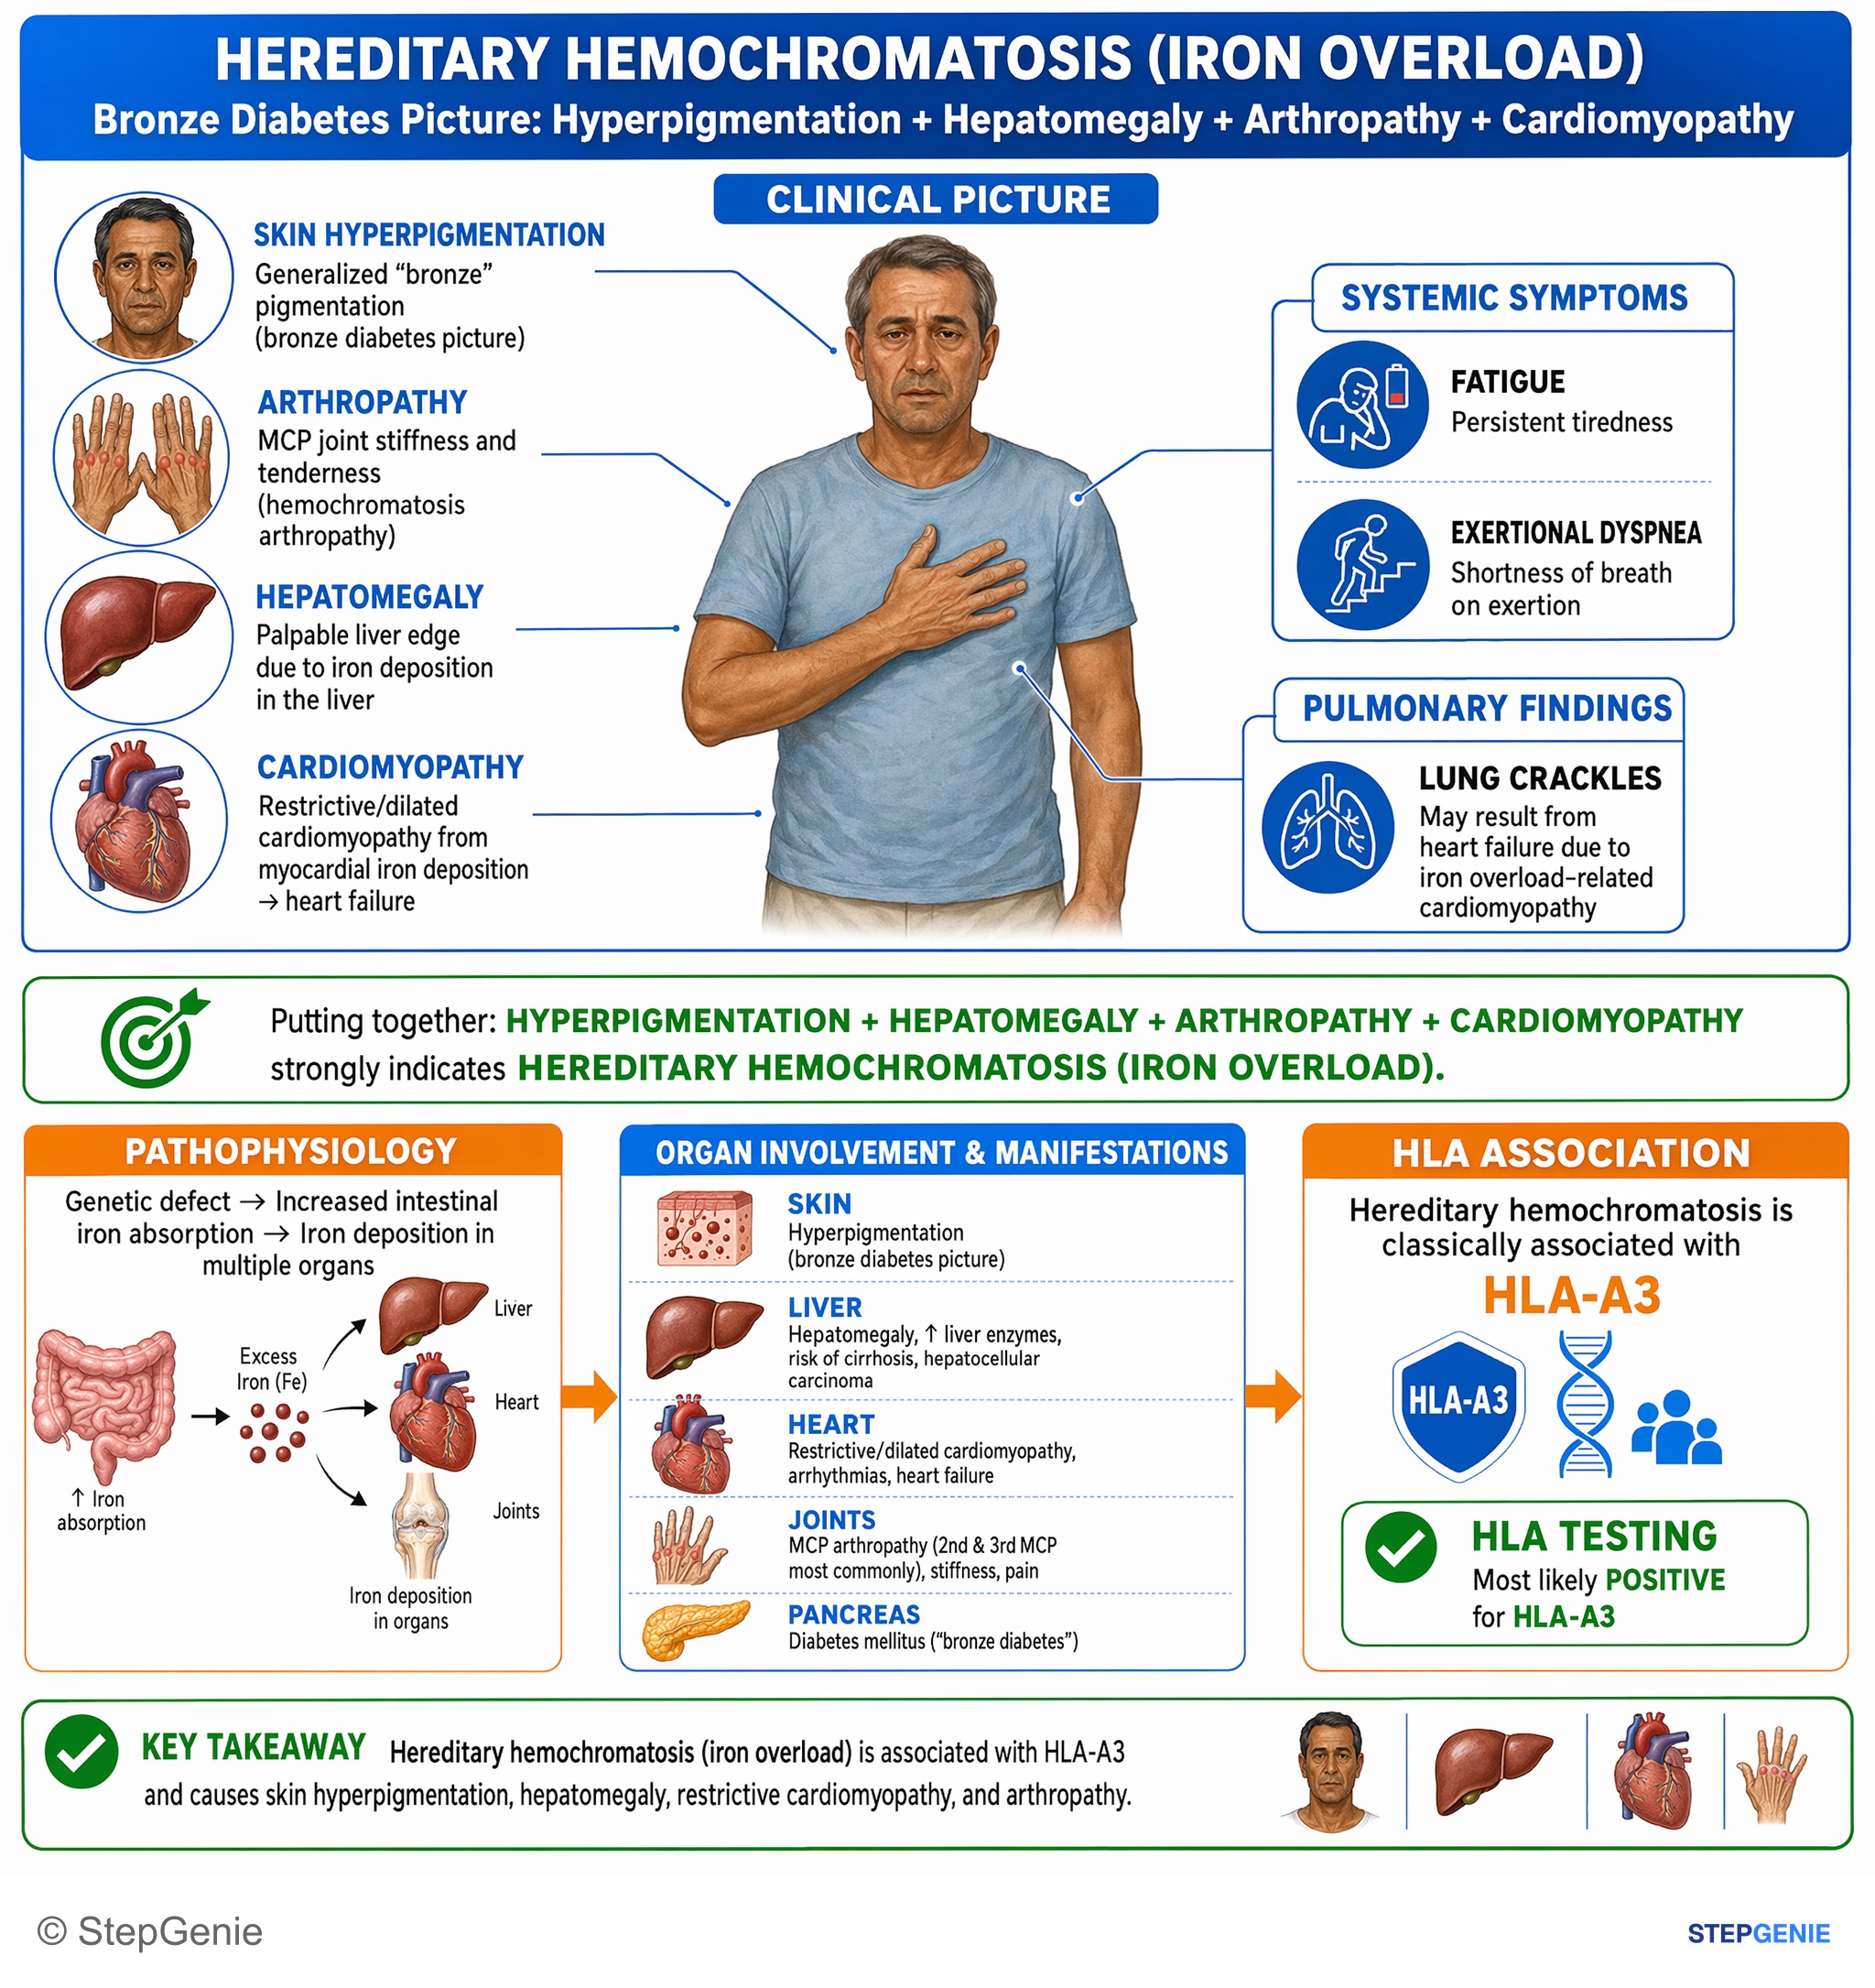
Hereditary hemochromatosis (iron overload) is associated with HLA-A3, causing skin hyperpigmentation, hepatomegaly, restrictive…
USMLE Step 1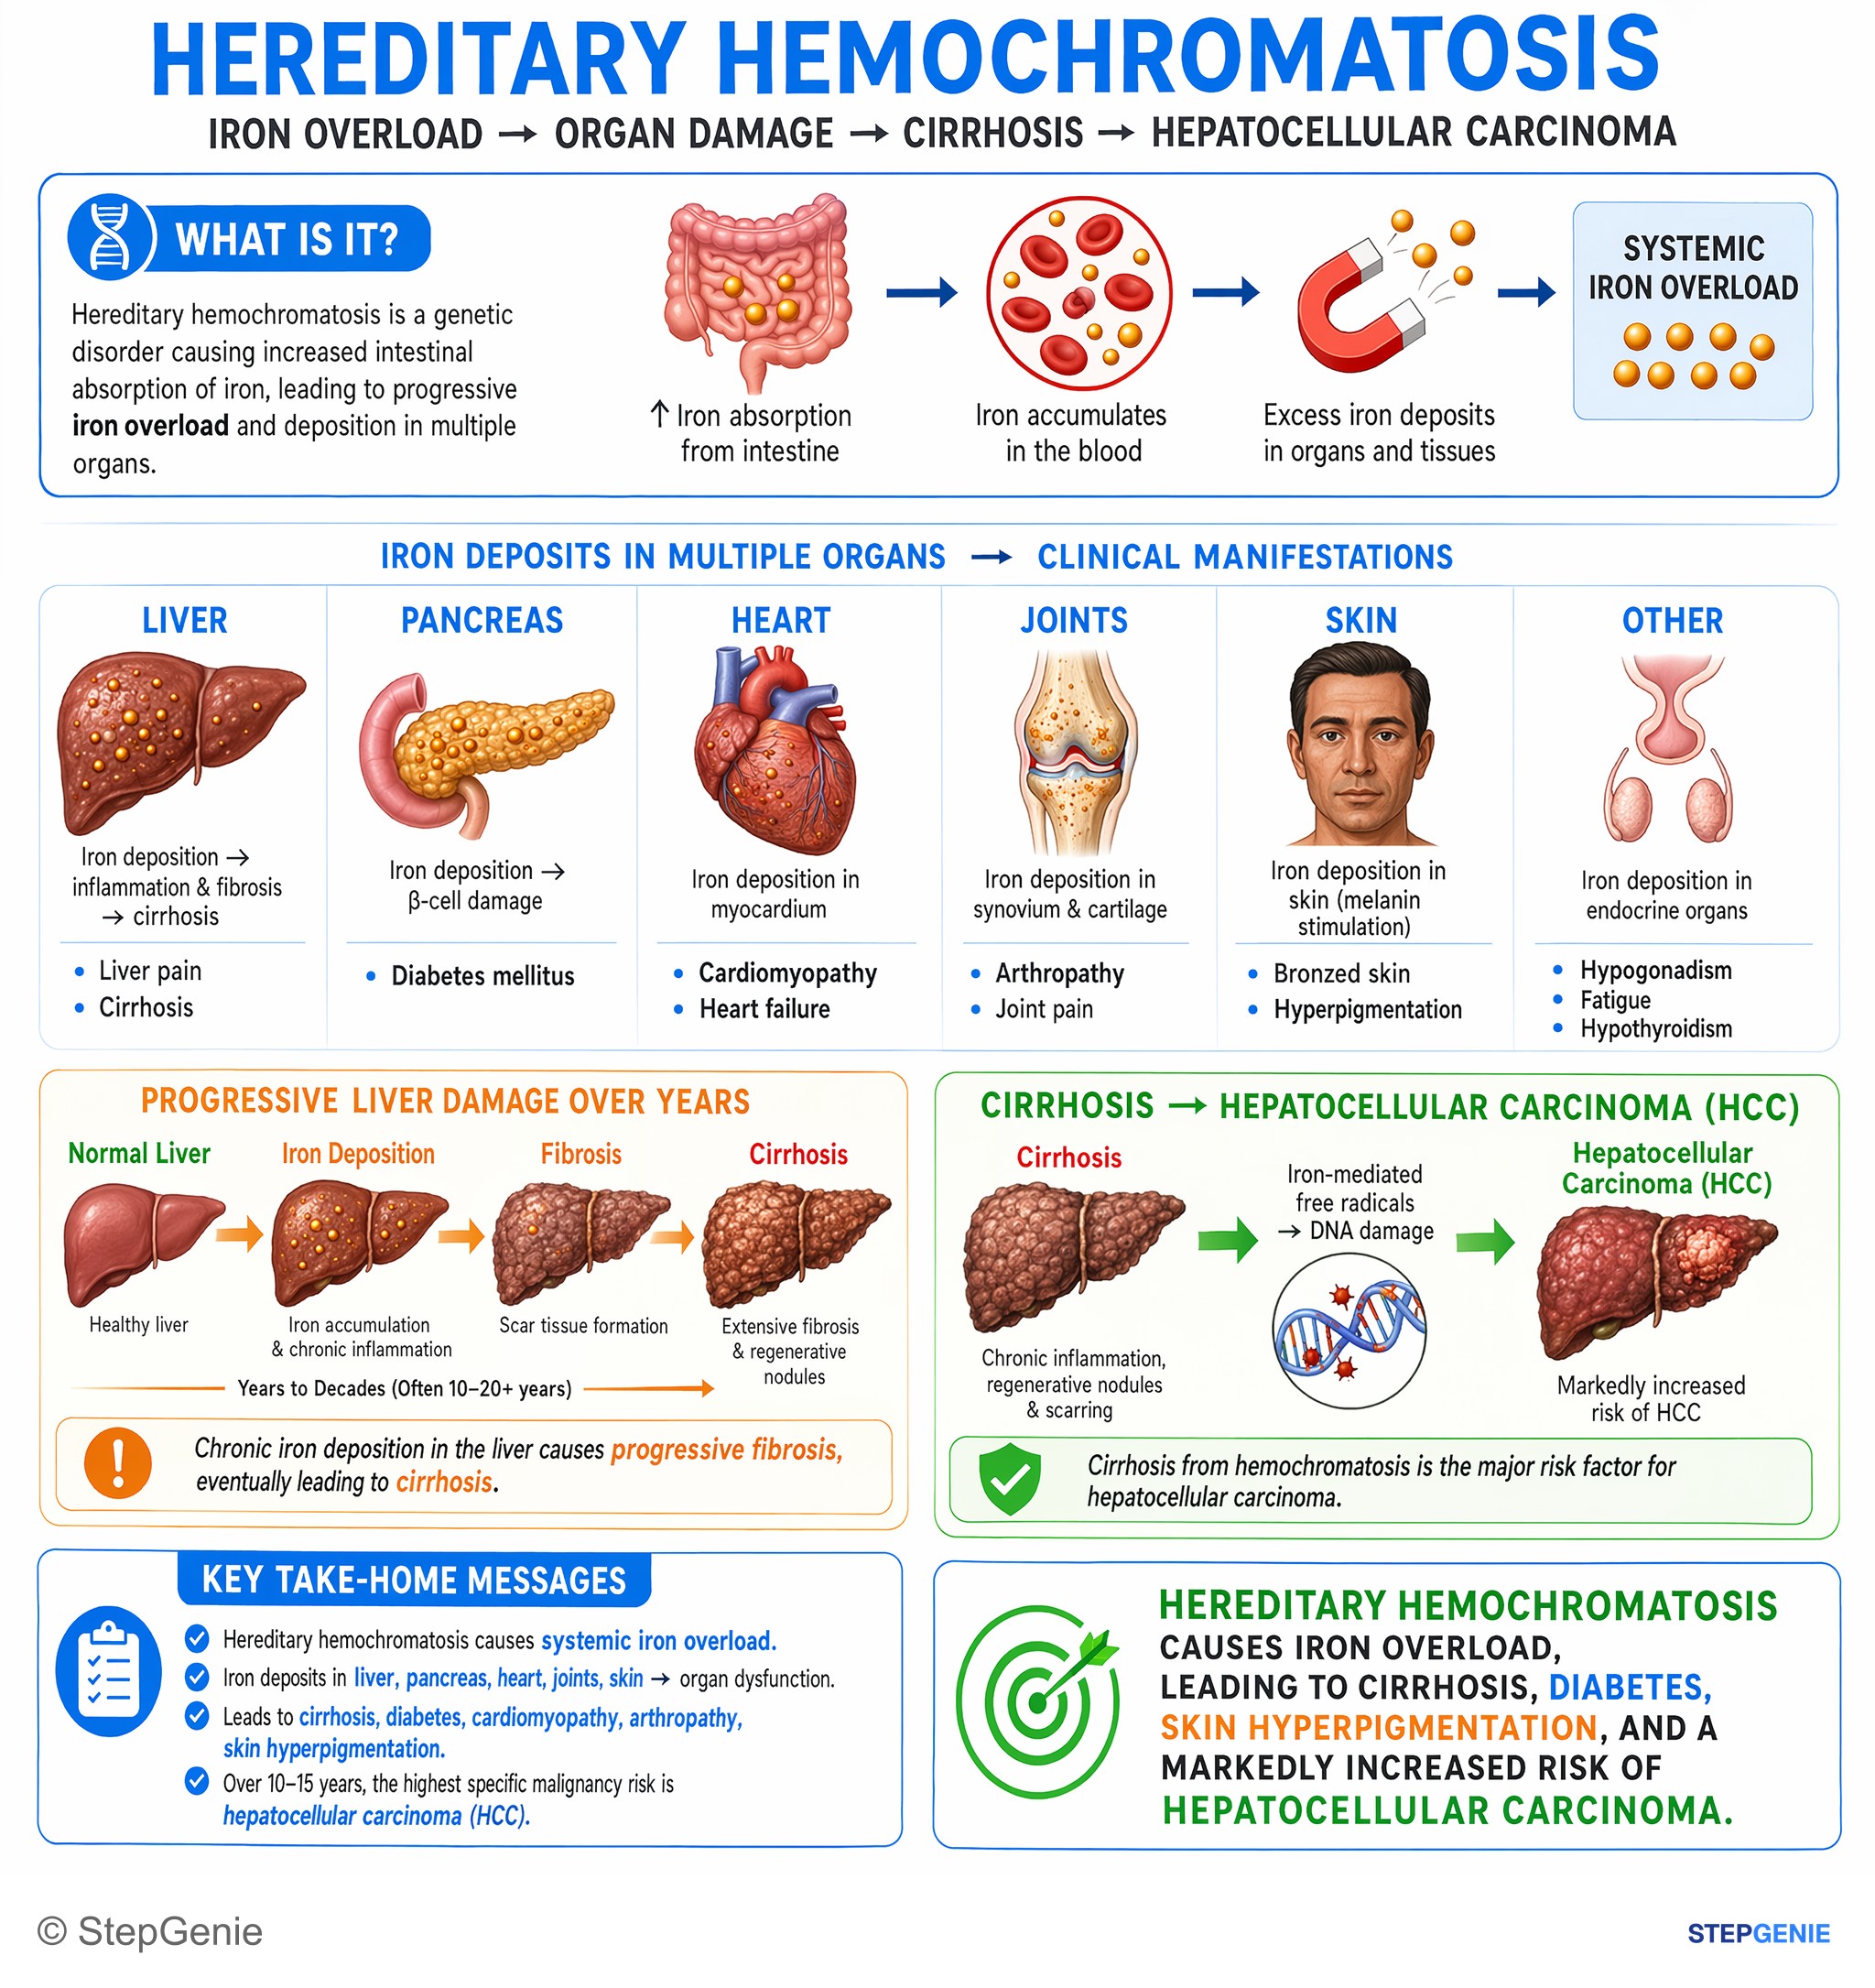
Hereditary hemochromatosis causes iron overload, leading to cirrhosis, diabetes, skin hyperpigmentation, and markedly increased risk of…
USMLE Step 1Frequently Asked Questions
Why does hereditary hemochromatosis cause high transferrin saturation and low TIBC?
Hereditary hemochromatosis causes high transferrin saturation and low TIBC because it leads to increased intestinal iron absorption and elevated circulating iron. Most cases involve an HFE mutation with decreased hepcidin signaling, which increases ferroportin activity and allows more iron to enter the blood from enterocytes and macrophages. The resulting pattern is high serum iron, low TIBC, high ferritin, and markedly increased transferrin saturation.
How do you tell hereditary hemochromatosis from primary biliary cholangitis on a vignette?
Hereditary hemochromatosis is suggested by systemic iron overload signs and iron studies, while primary biliary cholangitis is suggested by a cholestatic pattern. Hemochromatosis classically presents with fatigue, diabetes, hyperpigmentation, hepatomegaly, hypogonadism, and MCP arthropathy, along with high transferrin saturation and ferritin. Primary biliary cholangitis more often shows pruritus, jaundice, markedly elevated alkaline phosphatase, positive anti-mitochondrial antibodies, and typically affects middle-aged women.
What clinical clues point to hereditary hemochromatosis instead of alcoholic liver disease?
The strongest clues are systemic iron overload findings rather than a pure alcohol pattern. Hereditary hemochromatosis presents with features like hyperpigmented skin, borderline diabetes, decreased libido, MCP joint arthropathy, and hepatomegaly, plus iron studies showing very high transferrin saturation. Alcohol-associated liver disease more typically has heavy daily alcohol use, AST greater than ALT in a 2:1 pattern, macrocytosis, thrombocytopenia, and advanced signs of portal hypertension.
What is the first-line treatment for hereditary hemochromatosis?
The first-line treatment for hereditary hemochromatosis is phlebotomy. This fits the disease mechanism, because hereditary hemochromatosis causes progressive iron deposition in organs from increased intestinal iron absorption. Chelation therapy, such as deferasirox, is used when phlebotomy is not possible. On diagnostic questions, transferrin saturation is used for screening, HFE genetic testing helps confirm the diagnosis, and liver biopsy is reserved for fibrosis staging or unclear cases.
What is the earliest lab abnormality in hereditary hemochromatosis?
An increased transferrin saturation is often the earliest lab abnormality in hereditary hemochromatosis. It is a key screening clue for iron overload and is typically greater than 45%. Ferritin is also usually elevated, but ferritin can rise in inflammatory states as well, so the combination of high serum iron, low TIBC, and high transferrin saturation is especially helpful for recognizing true iron overload.