Budd–Chiari syndrome is one of those “classic triad” pathologies that shows up in Q-banks disguised as something more common—like alcoholic cirrhosis, heart failure, or portal hypertension from chronic liver disease. The trick on exams isn’t just recognizing the diagnosis; it’s proving why it’s not the other tempting choices.
Tag: GI > Hepatic Disorders
The Clinical Vignette (Q-bank style)
A 32-year-old woman presents with progressive abdominal distension and right upper quadrant pain for 1 week. She has nausea and early satiety. Exam shows tense ascites, tender hepatomegaly, and mild scleral icterus. Vitals are stable. Labs show mild transaminitis and elevated bilirubin. Ultrasound reveals ascites and an enlarged liver. Doppler ultrasound demonstrates absent flow in the hepatic veins.
Question: What is the most likely underlying cause?
Correct Answer: Budd–Chiari Syndrome (Hepatic Vein Outflow Obstruction)
What it is
Budd–Chiari syndrome = obstruction of hepatic venous outflow, usually due to thrombosis of hepatic veins (or IVC near hepatic vein drainage). The liver becomes congested, hepatocytes become ischemic, and portal pressures rise—fast.
The presentation you should memorize
Triad (high-yield):
- Abdominal pain (often RUQ)
- Ascites
- Hepatomegaly (often tender)
This triad is especially high-yield when it appears acutely/subacutely.
Why Doppler matters
- Doppler ultrasound is often the first “confirmatory” test in vignettes.
- Key clue: reduced/absent hepatic venous flow or hepatic vein thrombosis.
What causes it (USMLE favorites)
Think hypercoagulable states:
| Etiology | Examples |
|---|---|
| Myeloproliferative neoplasms | Polycythemia vera (often via JAK2), essential thrombocythemia |
| Pregnancy / estrogen | Pregnancy, OCPs |
| Malignancy | HCC, renal cell carcinoma (can extend into IVC), other prothrombotic cancers |
| Inherited thrombophilias | Factor V Leiden, protein C/S deficiency, antithrombin deficiency |
| Inflammatory/systemic | Antiphospholipid syndrome |
Most commonly tested association: young woman + OCPs or myeloproliferative disorder.
Core pathophysiology (how to reason it out)
Venous outflow obstruction causes:
- Hepatic sinusoidal congestion → hepatomegaly and RUQ pain
- Portal hypertension develops rapidly → ascites
- Ischemic injury → transaminitis (can be mild or marked depending on acuity)
Treatment principles (Step 2 style)
- Anticoagulation (often lifelong if an underlying thrombophilia)
- Treat underlying cause (e.g., stop OCPs, manage MPN)
- TIPS (transjugular intrahepatic portosystemic shunt) for refractory ascites/portal HTN
- Thrombolysis/thrombectomy in selected acute cases
- Liver transplant if fulminant hepatic failure or decompensation despite therapy
Why Every Answer Choice Matters (Systematic Distractor Breakdown)
Below are the common “look-alikes” Q-banks love to offer.
Distractor 1: Cirrhosis from Alcohol Use Disorder (Portal HTN from Chronic Liver Disease)
Why it’s tempting: Ascites + abnormal LFTs screams cirrhosis for many students.
Why it’s wrong here:
- Budd–Chiari is typically acute or subacute with painful hepatomegaly
- Alcoholic cirrhosis is usually chronic, often with:
- stigmata (spider angiomas, palmar erythema, gynecomastia)
- long history of heavy alcohol use
- more consistent synthetic dysfunction (low albumin, high INR)
High-yield distinction:
Cirrhosis = architectural distortion + portal HTN over time.
Budd–Chiari = blocked outflow → congestion and ascites fast.
Distractor 2: Right-Sided Heart Failure (Congestive Hepatopathy)
Why it’s tempting: “Hepatic congestion” and “painful hepatomegaly” can overlap.
Why it’s wrong here:
- Right-sided HF should come with systemic venous congestion:
- JVD
- peripheral edema
- hepatojugular reflux
- pulmonary HTN history, RV heave, etc.
- Doppler clue in the stem is specific: absent hepatic vein flow suggests thrombosis/outflow obstruction, not just backup pressure.
High-yield buzzword:
Right HF → congestive hepatopathy and sometimes “nutmeg liver” pathology, but hepatic veins are not typically thrombosed.
Distractor 3: Portal Vein Thrombosis
Why it’s tempting: Thrombosis + ascites/portal HTN features.
Why it’s wrong here:
- Portal vein thrombosis is prehepatic portal HTN—you’d expect:
- splenomegaly
- varices
- ascites possible
- But tender hepatomegaly + hepatic vein flow abnormalities point away from portal vein thrombosis.
High-yield comparison table
| Feature | Budd–Chiari | Portal Vein Thrombosis |
|---|---|---|
| Site | Hepatic veins / IVC | Portal vein |
| Key clue | Absent hepatic venous flow | Portal vein clot; hepatic veins usually patent |
| Hepatomegaly | Common, tender | Variable |
| Classic triad | Pain + ascites + hepatomegaly | Portal HTN signs (splenomegaly/varices) |
Distractor 4: Acute Viral Hepatitis (A, B, E)
Why it’s tempting: RUQ discomfort + jaundice + transaminitis.
Why it’s wrong here:
- Viral hepatitis classically causes marked AST/ALT elevation (often in the hundreds to thousands), plus systemic symptoms:
- malaise, anorexia
- nausea/vomiting
- sometimes fever
- It does not typically cause tense ascites early.
- Doppler showing absent hepatic vein flow doesn’t fit.
High-yield:
Acute hepatitis = hepatocyte injury → very high transaminases.
Budd–Chiari = congestion/ischemia + portal HTN signs (ascites).
Distractor 5: Spontaneous Bacterial Peritonitis (SBP)
Why it’s tempting: Ascites + abdominal discomfort.
Why it’s wrong here:
- SBP is usually in a patient with known cirrhosis and ascites and presents with:
- fever
- diffuse abdominal pain/tenderness
- encephalopathy or worsening renal function
- Diagnosis is by paracentesis: ascitic PMNs .
- SBP is an infection complication of ascites—not the primary cause of hepatic vein outflow obstruction.
High-yield management:
SBP → empiric 3rd-gen cephalosporin (e.g., cefotaxime/ceftriaxone) and often albumin depending on creatinine/bilirubin.
Distractor 6: Hepatocellular Carcinoma (HCC)
Why it’s tempting: Liver enlargement + ascites + abnormal LFTs.
Why it’s wrong here (in this vignette):
- HCC typically arises in the setting of chronic liver disease (HBV, HCV, cirrhosis).
- Symptoms are more indolent: weight loss, malaise, worsening decompensation.
- However—important nuance: malignancy can cause Budd–Chiari via hypercoagulability or IVC obstruction. Q-banks will usually signal cancer with weight loss, chronic symptoms, HBV/HCV history, markedly elevated AFP, or a liver mass.
High-yield:
HCC risk: HBV can cause HCC even without cirrhosis.
Exam-Day Pattern Recognition: What Should Make You Say “Budd–Chiari”?
Red flags in the stem
- Acute/subacute ascites
- RUQ pain
- Tender hepatomegaly
- Known risk for thrombosis:
- pregnancy/OCPs
- JAK2/myeloproliferative disease
- malignancy
- thrombophilia
Key diagnostic tools
- Doppler ultrasound (first-line in many questions)
- CT/MR venography (confirmatory in some vignettes)
High-Yield Takeaways (Quick Hit List)
- Budd–Chiari = hepatic vein thrombosis/outflow obstruction
- Triad: abdominal pain + ascites + hepatomegaly (often tender)
- Think hypercoagulability (MPN/JAK2, OCPs, pregnancy, malignancy)
- Doppler: reduced/absent hepatic vein flow
- Treat with anticoagulation, address cause; TIPS or transplant if severe
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
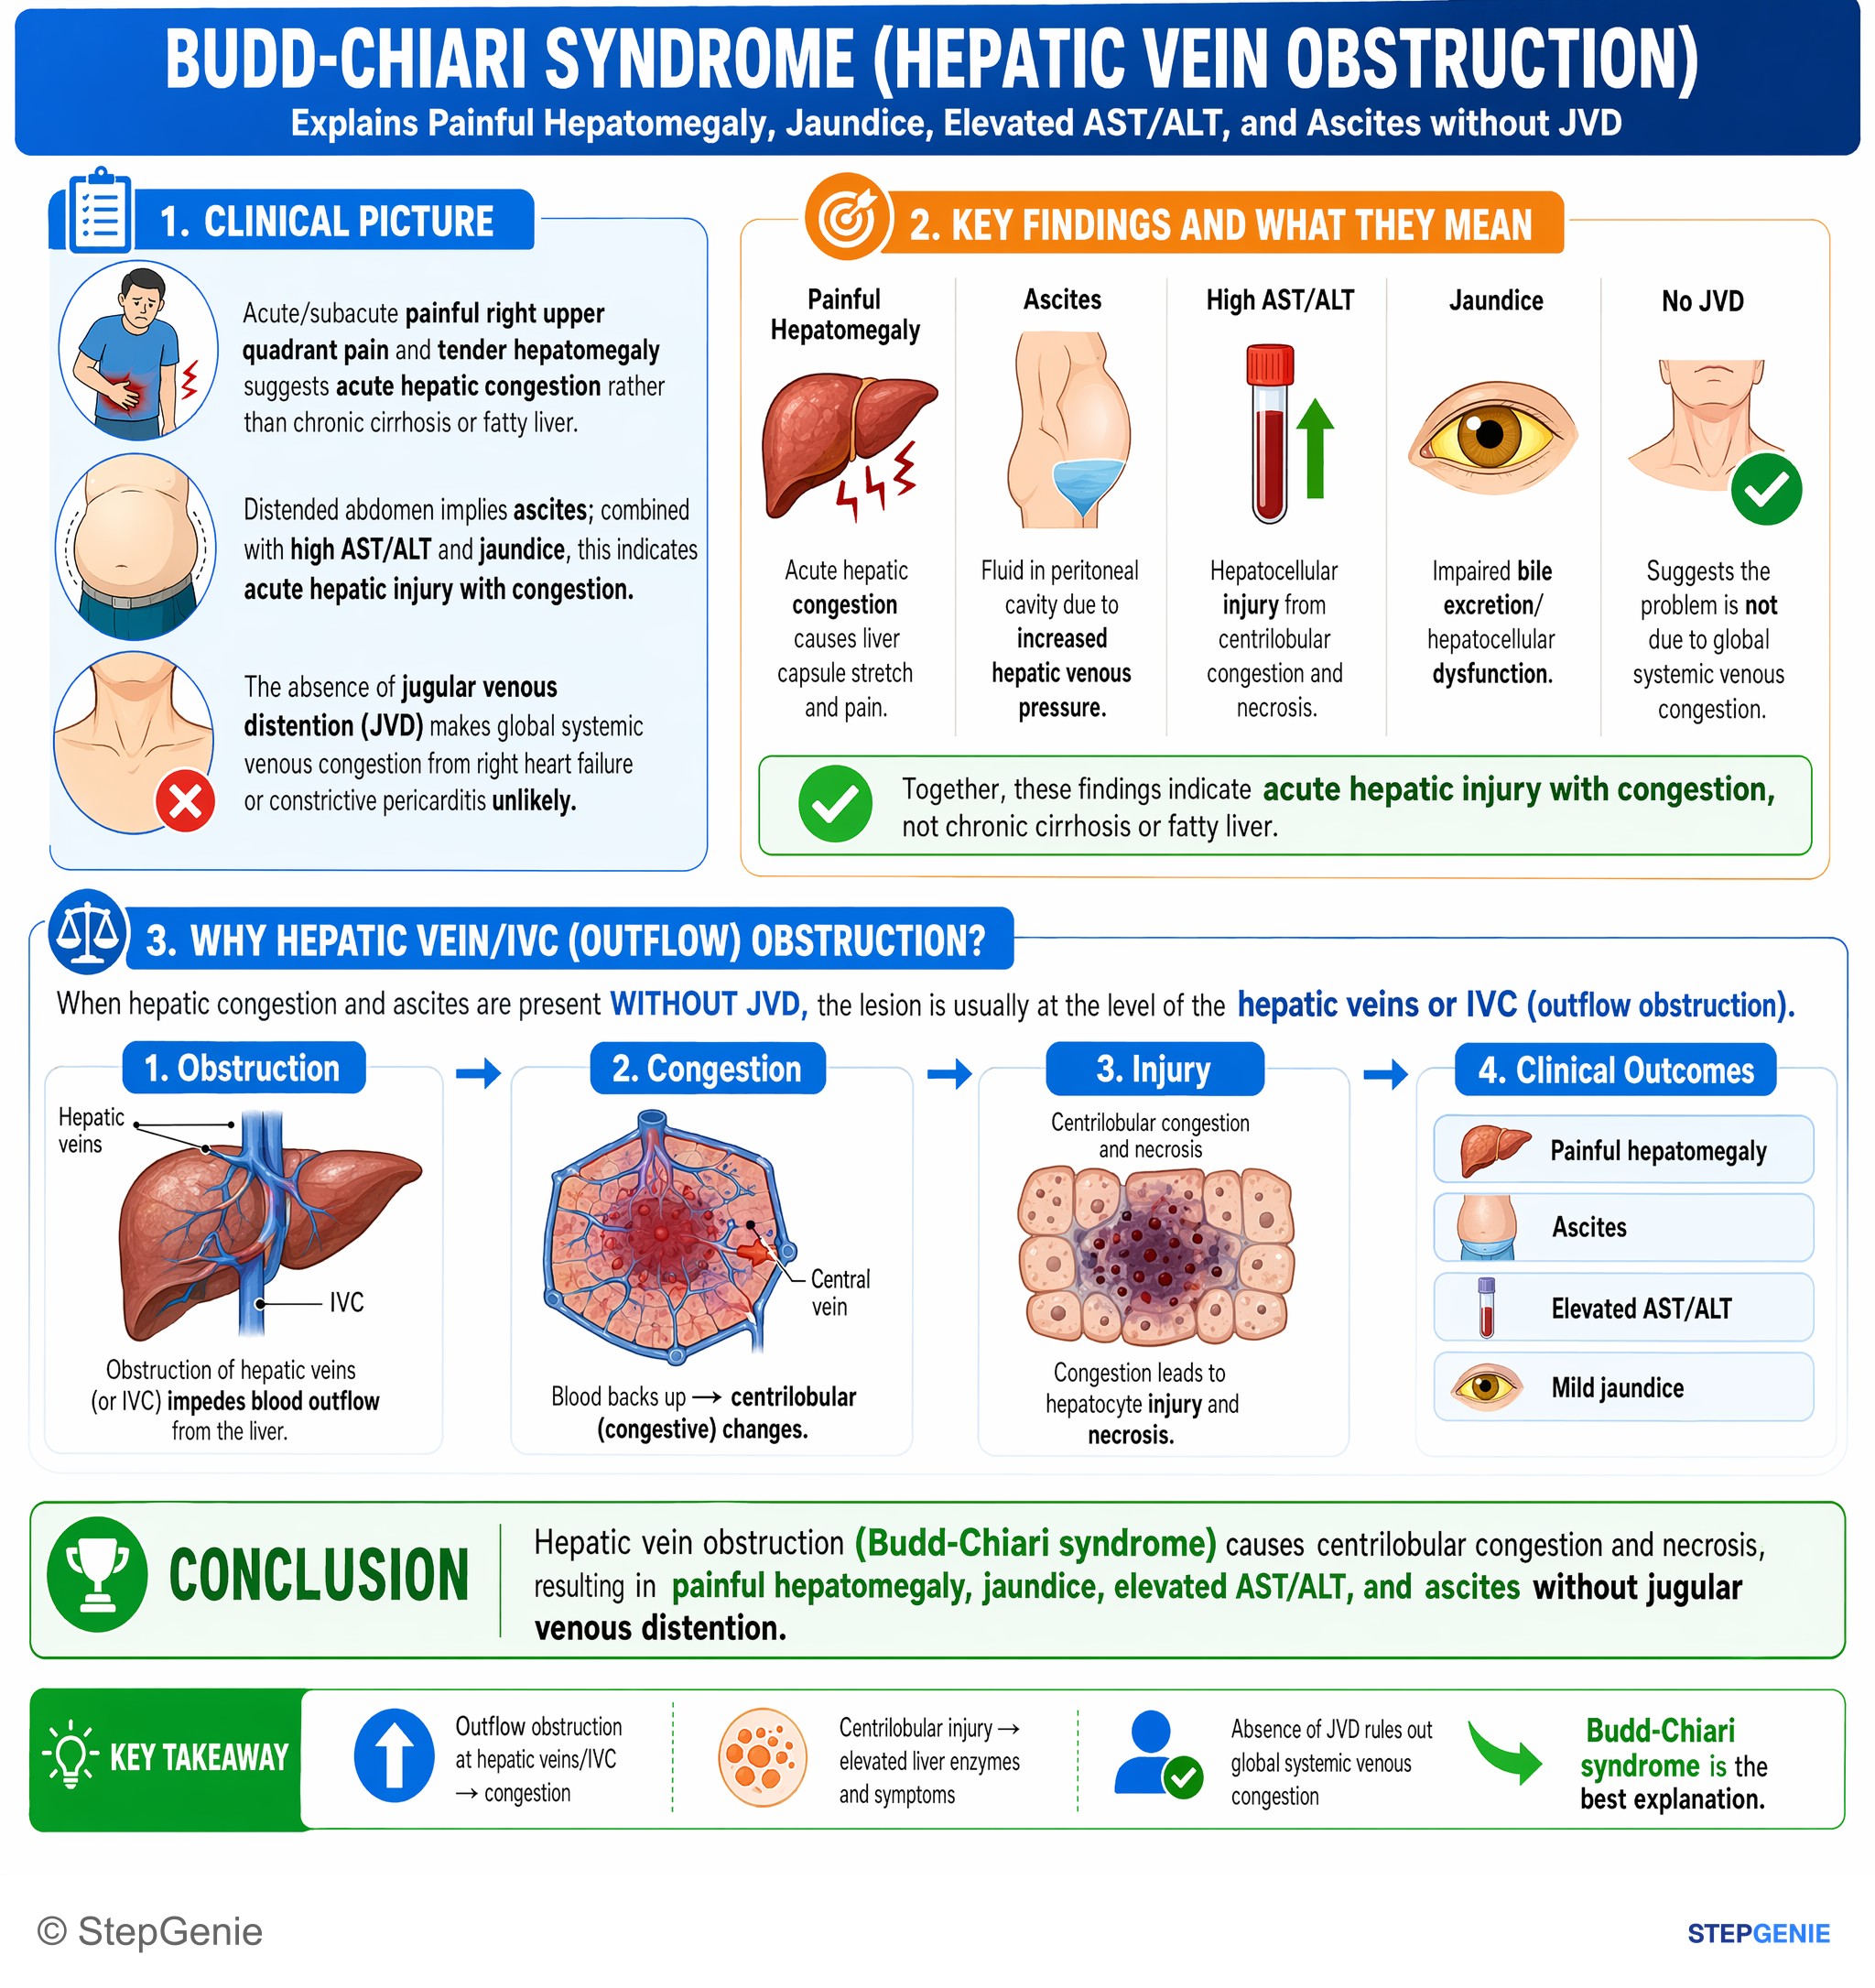
Budd-Chiari syndrome from hepatic vein obstruction causes painful hepatomegaly, jaundice, elevated AST/ALT, and ascites without jugular…
USMLE Step 1Frequently Asked Questions
What is the classic triad of Budd-Chiari syndrome that should make you think of hepatic vein outflow obstruction?
The classic triad is abdominal pain, ascites, and hepatomegaly. It is especially high-yield when it appears acutely or subacutely, such as right upper quadrant pain with tense ascites and a tender enlarged liver. This pattern points to hepatic venous outflow obstruction causing congestion, rising portal pressure, and liver injury rather than a more chronic liver disease process.
Why does Budd-Chiari syndrome cause ascites and right upper quadrant pain?
Budd-Chiari syndrome causes ascites and right upper quadrant pain because hepatic venous outflow is obstructed, usually by thrombosis of the hepatic veins. The blocked outflow produces hepatic sinusoidal congestion, which leads to hepatomegaly and pain, while portal pressures rise rapidly and cause ascites. Ischemic injury to hepatocytes can also produce transaminitis and elevated bilirubin.
How do you tell Budd-Chiari syndrome from portal vein thrombosis on a vignette?
Budd-Chiari syndrome is suggested by absent hepatic venous flow on Doppler and by tender hepatomegaly with the triad of pain, ascites, and hepatomegaly. Portal vein thrombosis is a prehepatic cause of portal hypertension and more strongly suggests splenomegaly and varices. In portal vein thrombosis, the portal vein is clotted, while the hepatic veins are usually patent rather than obstructed.
How do you distinguish Budd-Chiari syndrome from right-sided heart failure or alcoholic cirrhosis?
Budd-Chiari syndrome is usually acute or subacute and features painful hepatomegaly with Doppler evidence of absent hepatic vein flow. Right-sided heart failure should also show systemic venous congestion such as JVD, peripheral edema, or hepatojugular reflux, and the hepatic veins are not typically thrombosed. Alcoholic cirrhosis is usually chronic, with stigmata of liver disease, heavy alcohol history, and more consistent synthetic dysfunction.
What are the most commonly tested causes and treatment principles for Budd-Chiari syndrome?
The most tested causes are hypercoagulable states, especially a young woman using OCPs or a myeloproliferative disorder such as polycythemia vera. Other listed causes include pregnancy, malignancy, inherited thrombophilias, and antiphospholipid syndrome. Treatment principles are anticoagulation, treating the underlying cause, TIPS for refractory ascites or portal hypertension, selected thrombolysis or thrombectomy, and liver transplant for fulminant failure or persistent decompensation.