A good Q-bank question on alpha-1 antitrypsin (A1AT) deficiency doesn’t just test whether you remember “panacinar emphysema + cirrhosis.” The liver presentation is where test writers love to hide the ball—because the pathophys is not “too little protease inhibition in the liver.” Instead, it’s a toxic gain-of-function problem: misfolded A1AT gets trapped inside hepatocytes and injures them. Let’s walk through a classic vignette and then dismantle every answer choice like you would on test day.
Clinical vignette (GI > Hepatic Disorders)
A 6-week-old infant is brought in for persistent jaundice and poor weight gain. Exam shows mild hepatomegaly. Labs: elevated total and direct bilirubin, increased AST/ALT. The mother says a paternal uncle had “early lung disease” despite never smoking. Liver biopsy shows PAS-positive, diastase-resistant cytoplasmic globules within hepatocytes.
Question: What is the underlying mechanism causing this patient’s liver disease?
The correct answer: Misfolded A1AT accumulates in the ER of hepatocytes
What’s actually happening
- Most high-yield genotype: PiZZ (severe deficiency)
- Mutant A1AT is misfolded → polymerizes → retained in the rough ER of hepatocytes
- This retention causes ER stress, hepatocyte injury, inflammation, and over time:
- Neonatal hepatitis/cholestasis
- Cirrhosis
- Hepatocellular carcinoma (HCC) risk increases
The pathology buzzwords
- PAS-positive, diastase-resistant globules in hepatocytes
- PAS highlights glycoproteins (A1AT is a glycoprotein)
- Diastase-resistant = not glycogen (diastase digests glycogen)
Why it’s high-yield
A1AT deficiency is one of those “two-organ” diseases:
- Liver disease = protein misfolding/retention (toxic accumulation)
- Lung disease = loss of antiprotease activity (unopposed elastase)
Quick memory hook: “Z” protein gets “Ztuck” in the liver.
What you should say out loud on NBME-style questions
- Liver problem is from intracellular accumulation, not from low serum A1AT.
- Lung problem is from low A1AT in alveoli → elastase wins.
Table: A1AT deficiency — liver vs lung mechanisms
| Organ | Mechanism | Key finding | Clinical outcomes |
|---|---|---|---|
| Liver | Misfolded A1AT retained in ER (toxic gain-of-function) | PAS+ diastase-resistant globules | Neonatal cholestasis, hepatitis, cirrhosis, HCC |
| Lung | Low A1AT → uninhibited neutrophil elastase (loss-of-function) | Panacinar emphysema, lower lobes | COPD at young age, worse with smoking |
Now, why every distractor is tempting (and why it’s wrong)
Below are common answer choices that show up in A1AT liver vignettes and what they’re actually describing.
Distractor 1: “Unopposed neutrophil elastase destroys alveolar walls”
Why it tempts you: A1AT deficiency is famous for emphysema.
Why it’s wrong here: That mechanism explains lung disease, not hepatic injury. The vignette is screaming liver:
- Infant cholestasis
- Hepatomegaly
- PAS+ diastase-resistant globules in hepatocytes
When it would be correct: Adult with early COPD, panacinar emphysema, worse in smokers; CXR hyperinflation; PFT obstructive.
Distractor 2: “Impaired bilirubin conjugation due to decreased UDP-glucuronyltransferase”
What it describes: Physiologic jaundice of the newborn, Gilbert, Crigler-Najjar
Why it’s wrong here:
- This patient has direct (conjugated) hyperbilirubinemia + hepatocellular injury (↑AST/ALT)
- A1AT deficiency causes cholestasis/hepatitis, not an isolated conjugation enzyme issue
High-yield contrast
- Unconjugated bilirubin problems: no bilirubin in urine, risk kernicterus (severe cases)
- Conjugated bilirubin problems: dark urine, cholestasis picture
Distractor 3: “Autoimmune destruction of intrahepatic bile ducts”
What it describes: Primary biliary cholangitis (PBC)
Why it’s tempting: PBC is a classic cholestatic liver disease.
Why it’s wrong here:
- PBC typically in middle-aged women, pruritus, fatigue
- Labs: markedly elevated ALP, positive anti-mitochondrial antibody
- Histology: florid duct lesion (granulomatous destruction of bile ducts)
Clue in vignette that points away: PAS+ globules in hepatocytes = protein accumulation disorder, not immune bile duct injury.
Distractor 4: “Onion-skin periductal fibrosis due to inflammation of bile ducts”
What it describes: Primary sclerosing cholangitis (PSC)
Why it’s tempting: Another high-yield cholestatic disease.
Why it’s wrong here:
- PSC classically linked to ulcerative colitis
- MRCP/ERCP: beading of intra/extrahepatic ducts
- Histology: onion-skin fibrosis
- Increased risk: cholangiocarcinoma
Clue in vignette that points away: Infant presentation + PAS+ diastase-resistant globules doesn’t fit PSC.
Distractor 5: “Copper accumulation due to defective ATP7B”
What it describes: Wilson disease
Why it’s tempting: Wilson causes hepatitis/cirrhosis in young patients.
Why it’s wrong here:
- Wilson hallmark findings:
- Neuro/psych symptoms
- Kayser-Fleischer rings
- Labs: low ceruloplasmin, increased hepatic copper
- Histology is not PAS+ diastase-resistant globules; you’d think about copper stains (rhodanine) and steatosis.
Age nuance: Wilson can show up in kids/teens, but the lung-family-history clue and PAS+ globules push A1AT hard.
Distractor 6: “Trapping of misfolded proteins in the ER leading to hepatocyte injury”
This is the correct one, but it sometimes appears phrased as:
- “Abnormal protein folding with ER retention”
- “Accumulation of mutant protein in hepatocytes”
- “Decreased secretion of A1AT from the liver”
If you see ER retention + PAS+ diastase-resistant globules, you’re basically done.
High-yield rapid review: what USMLE likes to ask
1) Genetics/biochem angle
- A1AT is a serine protease inhibitor (serpin)
- Mutation → misfolding → polymerization
- Inheritance is commonly taught as autosomal codominant pattern of expression (serum levels vary by allele)
2) Histology angle
- PAS-positive, diastase-resistant globules in hepatocytes (classic board phrase)
3) Clinical angle: timing and presentation
- Infants: cholestasis, jaundice, hepatitis, hepatomegaly, failure to thrive
- Adults: cirrhosis, HCC risk
- Lungs (often later): panacinar emphysema, lower lobes; worse with smoking
4) Lab pattern reminders
- Don’t overcomplicate the pattern: A1AT liver disease can show mixed hepatocellular/cholestatic labs, especially in infants.
- The “tell” is the biopsy finding + lung history.
Test-day strategy: how to lock it in fast
When you see:
- Young patient + liver disease AND
- Family history of early emphysema OR
- PAS+ diastase-resistant globules
Think:
- A1AT made in liver
- Mutant protein can’t be secreted
- Accumulation injures hepatocytes
- Low circulating A1AT → lung damage
One-liner takeaway
A1AT liver disease is caused by ER retention of misfolded A1AT (PAS+ diastase-resistant globules), while lung disease is caused by low A1AT allowing elastase-mediated alveolar destruction.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
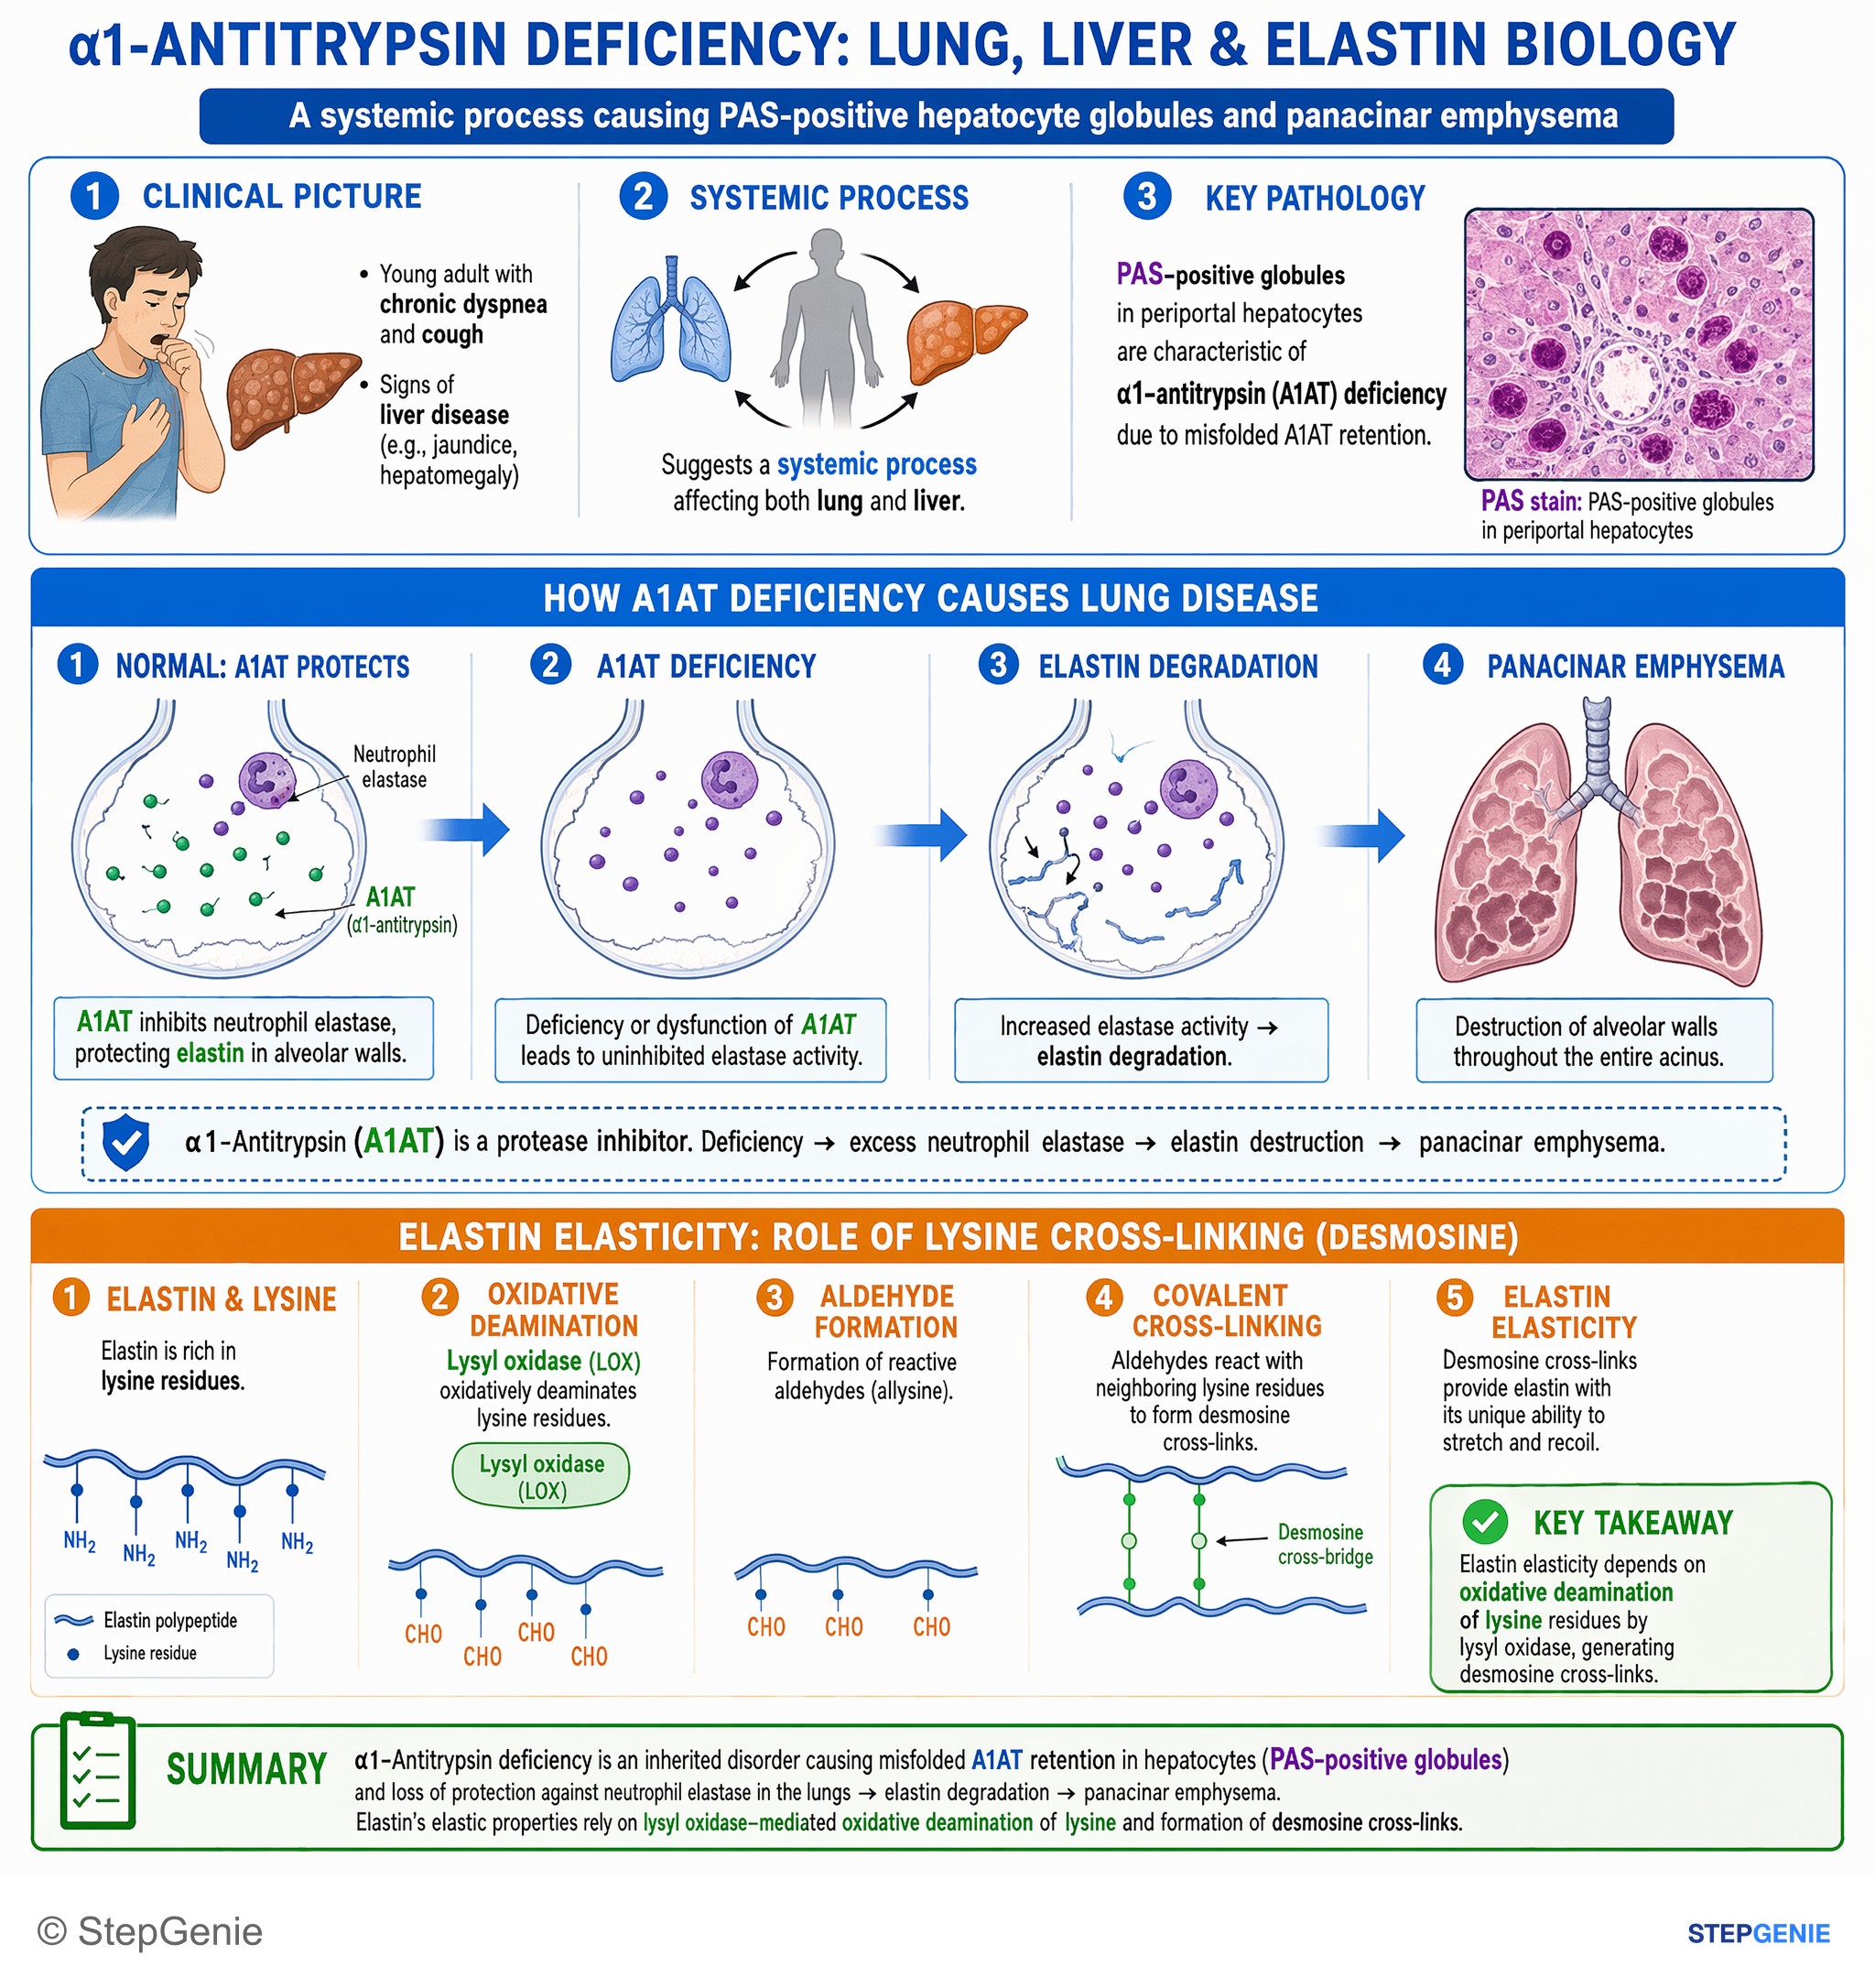
α1-antitrypsin deficiency causes PAS-positive hepatocyte globules and panacinar emphysema; elastin elasticity depends on oxidative…
USMLE Step 1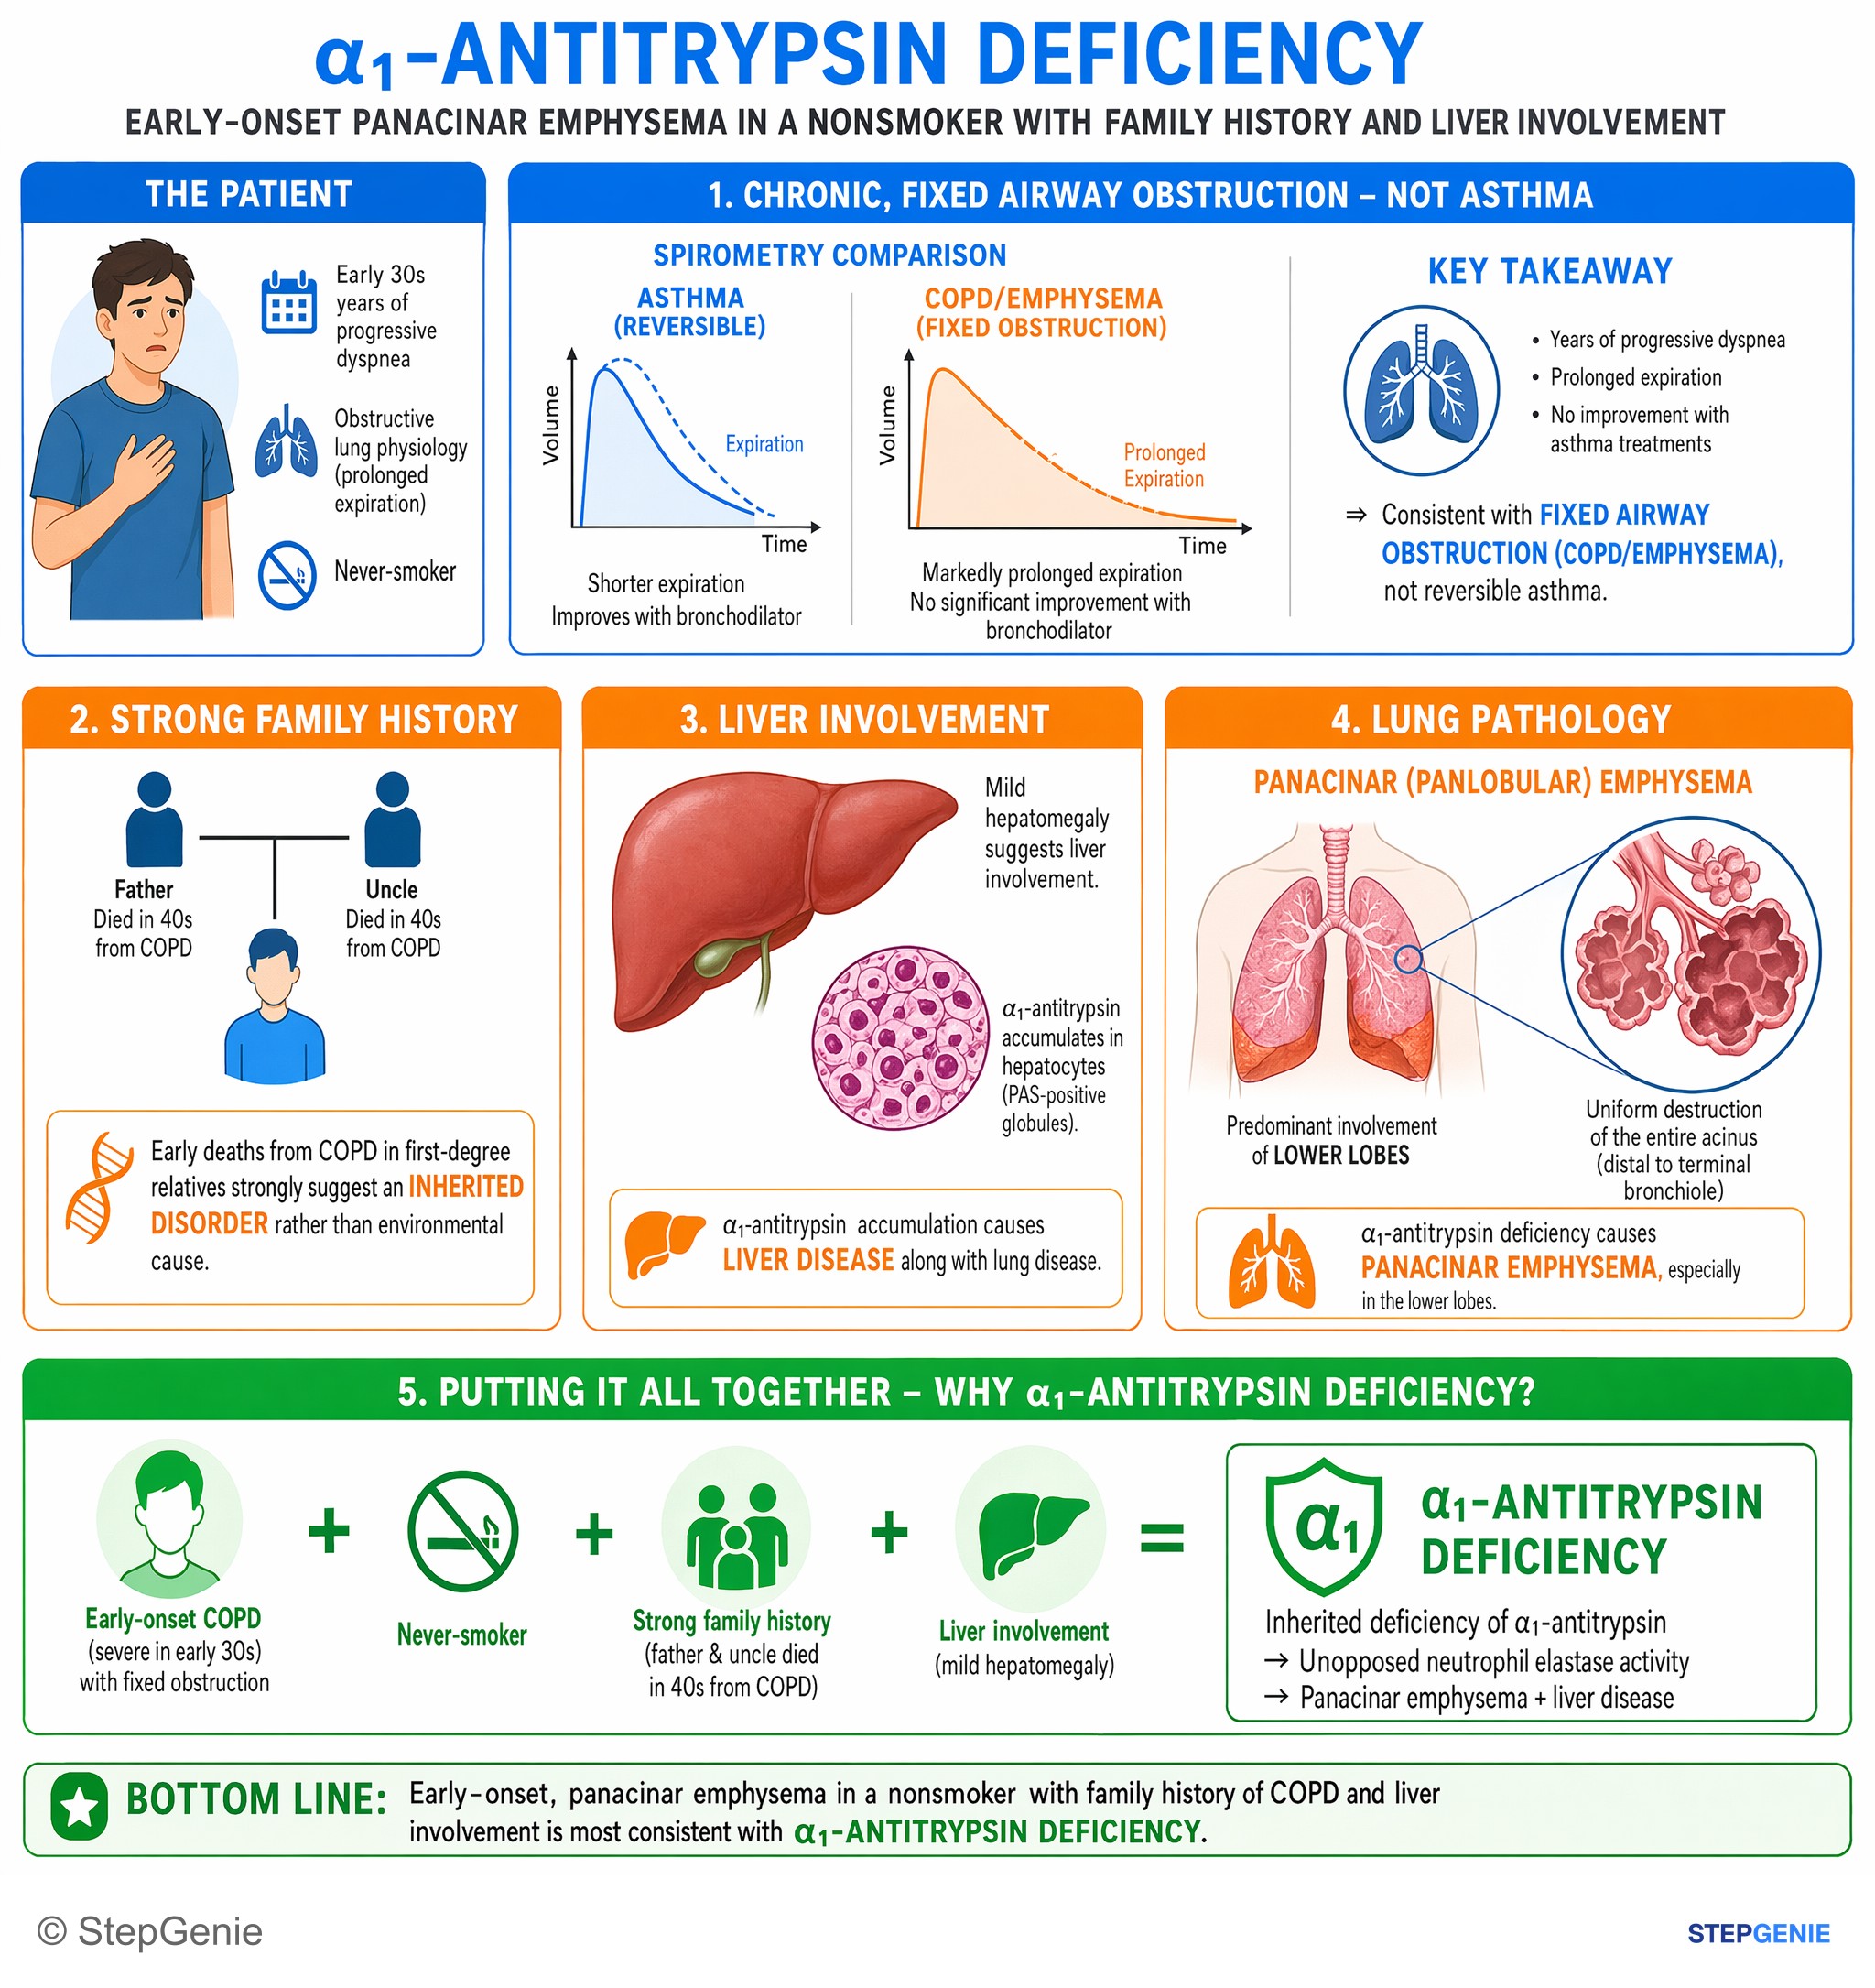
α1-antitrypsin deficiency → early-onset panacinar emphysema in a nonsmoker with family history of COPD and liver involvement.
USMLE Step 2Frequently Asked Questions
Why does alpha-1 antitrypsin deficiency cause liver disease instead of just lung disease?
Alpha-1 antitrypsin deficiency causes liver disease because the mutant protein misfolds, polymerizes, and gets retained in the rough ER of hepatocytes. That intracellular accumulation creates ER stress, hepatocyte injury, and inflammation, making the liver problem a toxic gain-of-function process. In contrast, the lung problem comes from low A1AT in the alveoli and unopposed elastase activity.
What biopsy finding points to alpha-1 antitrypsin deficiency in an infant with jaundice?
PAS-positive, diastase-resistant cytoplasmic globules in hepatocytes strongly point to alpha-1 antitrypsin deficiency. These globules represent retained A1AT, which is a glycoprotein highlighted by PAS staining. The fact that they are diastase-resistant helps distinguish them from glycogen, since diastase digests glycogen. In the right clinical setting, this is a classic clue for A1AT-related liver disease.
How do you tell alpha-1 antitrypsin liver disease from physiologic jaundice or Gilbert syndrome?
Alpha-1 antitrypsin liver disease presents with conjugated hyperbilirubinemia and hepatocellular injury, not an isolated bilirubin conjugation defect. A typical clue is elevated direct bilirubin with increased AST and ALT, often with hepatomegaly or cholestasis. By contrast, physiologic jaundice, Gilbert syndrome, and Crigler-Najjar involve impaired bilirubin conjugation and are categorized as unconjugated bilirubin problems.
How do you distinguish A1AT liver disease from PBC or PSC?
Alpha-1 antitrypsin liver disease is distinguished by infant presentation and PAS-positive, diastase-resistant globules in hepatocytes, which indicate abnormal protein accumulation. Primary biliary cholangitis instead classically affects middle-aged women with pruritus, fatigue, elevated ALP, anti-mitochondrial antibodies, and bile duct destruction. Primary sclerosing cholangitis is associated with ulcerative colitis, biliary duct beading, onion-skin fibrosis, and cholangiocarcinoma risk.
What are the high-yield liver and lung mechanisms of alpha-1 antitrypsin deficiency for Step 1?
The key distinction is liver equals toxic protein retention, while lung equals loss of antiprotease activity. In the liver, misfolded A1AT is trapped in the ER of hepatocytes, causing cholestasis, hepatitis, cirrhosis, and increased hepatocellular carcinoma risk. In the lung, low A1AT leaves neutrophil elastase uninhibited, leading to panacinar emphysema, typically in the lower lobes and worse with smoking.