The cholelithiasis mnemonic is the 5 F's: fat, female, fertile, forty and fair, the textbook profile of a patient with cholesterol gallstones. Female sex, obesity and pregnancy are solid risk factors, "forty" holds only as "older", and "fair" is the shakiest, a crude stand-in for ancestry; the mnemonic also misses family history, fast weight loss and the pigment-stone causes (hemolysis, cirrhosis, ileal disease). Up to 80% of people with gallstones have no symptoms; the classic symptom is biliary colic, steady right upper quadrant pain usually lasting under 6 hours, and the first test is ultrasound. Symptomatic stones → laparoscopic cholecystectomy; silent stones → usually observe.
Cholelithiasis at a glance
| Feature | High-yield fact |
|---|---|
| Who has stones | About 14% of US adults over 20; up to 80% have no symptoms |
| Stone types | Cholesterol (more than 85% in Western countries), black pigment, brown pigment |
| Classic symptom | Biliary colic: steady (not colicky) pain, intense within 15–60 minutes, usually lasting under 6 hours, without fever |
| First test | Right upper quadrant ultrasound, about 95% sensitive and specific for gallbladder stones |
| Duct stones | Ultrasound misses most: the ASGE 2019 criteria decide between ERCP, EUS or MRCP, and surgery |
| Complications | Acute cholecystitis, choledocholithiasis, cholangitis, gallstone pancreatitis, gallstone ileus, Mirizzi syndrome |
| Treatment | Symptomatic stones: laparoscopic cholecystectomy; asymptomatic stones: observe, with a few exceptions |
The 5 F's: what the evidence supports
A 2013 study tested the mnemonic directly: it compared 198 patients admitted with upper abdominal pain (March 2009 to April 2010) who had gallstones on ultrasound with 200 admitted with the same complaint but no stones.
| F | Stands for | Verdict | Evidence |
|---|---|---|---|
| Female | Female sex, estrogen | Real | Estrogen from pregnancy, hormone therapy or birth control pills raises risk; 75.8% of patients with stones were women vs 55.5% of controls |
| Fat | Obesity, metabolic syndrome | Real | Excess cholesterol secreted into bile is the usual cause of supersaturation; BMI over 30 in 28.3% vs 9.5% |
| Fertile | Pregnancy, several pregnancies | Real | Progesterone reduces gallbladder contraction and pregnancy breeds sludge; 68.2% vs 25% |
| Forty | Older age | Real as "older", not as a cut-off | Prevalence rises with age (more than 25% of women over 60 have stones), but age over 40 did not separate the groups (41.4% vs 39.5%) |
| Fair | Fair skin, European ancestry | Shakiest: a crude proxy for ancestry | More common in patients with stones in the 2013 study, but the risk follows ancestry: high in northern Europeans, yet American Indians have the highest US rates; lower in Asian and African American populations |
What the 2013 study found: fat, female, fertile and fair were all more common in patients with stones, forty was not, and 39.4% of patients with stones had a first-degree relative with gallstones vs 13.5% of controls, so the authors proposed "familial" in place of "forty". About a quarter of the predisposition to cholesterol stones appears to be inherited.
Why "fair" is the weakest F: the risk tracks ancestry, not skin tone. Native American and Hispanic populations are at least as affected as northern Europeans, and American Indians carry genes that raise the cholesterol in their bile, so a darker-skinned patient is not protected. Use the F's to recognize the typical patient, never to rule gallstones out.
Upgrade the mnemonic: keep all five, add familial and fast weight loss (the 7 F's), and learn pigment-stone causes separately: hemolysis, cirrhosis, ileal disease.
Risk factors the 5 F's miss
| Risk factor | Why it matters |
|---|---|
| Family history | The strongest addition: 39.4% vs 13.5% in the study above |
| Native American ancestry | Highest US prevalence; Mexican Americans are also at higher risk |
| Fast weight loss | Severe calorie restriction and gastric bypass cause gallbladder stasis; semaglutide, a GLP-1 receptor agonist, carries a gallbladder warning (adult trials of the injection: gallstones in 1.6% vs 0.7% on placebo, an excess that persisted after accounting for weight loss) |
| Estrogen therapy | Oral contraceptives and hormone therapy; estrogen for prostate cancer raises risk in men too |
| Parenteral nutrition, prolonged fasting | Gallbladder stasis produces sludge, often the forerunner of stones |
| Ileal Crohn disease or ileal resection | Bile salts are not reabsorbed; also a black-stone risk |
| Chronic hemolysis, cirrhosis, cystic fibrosis | Black pigment stones (hemolysis: sickle cell disease, hereditary spherocytosis, β-thalassemia) |
| High spinal cord injury | Gallbladder stasis |
| Drugs | Octreotide and other somatostatin analogs (slow gallbladder emptying), fibrates such as fenofibrate (more cholesterol excreted into bile), ceftriaxone (calcium–ceftriaxone precipitate) |
| Metabolic, lifestyle | Insulin resistance, lipid abnormalities, physical inactivity |
- Octreotide: in clinical trials (mostly in acromegaly or psoriasis), 27% of patients developed gallstones and 24% sludge without stones; see the octreotide mnemonic.
- Fibrates: stop fenofibrate if gallstones are found; clofibrate, named in older texts, is no longer sold in the US.
- Ceftriaxone: precipitates are most likely in children, can mimic sludge or stones on ultrasound, and usually resolve once the drug is stopped ("pseudolithiasis").
How gallstones form and the three stone types
Cholesterol stones form in three steps: bile supersaturated with cholesterol (too much cholesterol, or too few bile salts and lecithin to keep it in solution), precipitation of microcrystals, sped up by gallbladder mucin, and growth on a mucin scaffold in a gallbladder that empties poorly. Biliary sludge (calcium bilirubinate, cholesterol microcrystals and mucin) often comes first, especially in pregnancy and parenteral nutrition. Stones grow about 1–2 mm a year and take 5–20 years to cause symptoms.
| Cholesterol | Black pigment | Brown pigment | |
|---|---|---|---|
| How common | More than 85% in Western countries | 10–20% of US gallstones | Unusual in the US; fairly common in parts of Southeast Asia |
| Made of | Cholesterol microcrystals on mucin | Calcium bilirubinate with inorganic calcium salts; small and hard | Calcium bilirubinate with calcium salts of fatty acids; soft and greasy |
| Where they form | Gallbladder | Gallbladder, almost always | Bile ducts (primary duct stones) |
| Mechanism | Supersaturation, crystal precipitation, stasis | Excess bilirubin crystallizing as calcium bilirubinate | Bile stasis plus chronic bacterial colonization |
| Classic setting | The F's, rapid weight loss, estrogen, fibrates, octreotide | Chronic hemolysis (hereditary spherocytosis, sickle cell disease), cirrhosis, ileal disease, older age | Infection, liver flukes such as Clonorchis, strictures; the share of duct stones that are pigment stones rises with time after cholecystectomy |
| Plain radiograph | Usually radiolucent | May contain enough calcium to be radiopaque | Lie in the ducts: look with MRCP, EUS or ERCP |
On ultrasound, gallbladder stones are echogenic foci that move with position and cast an acoustic shadow; sludge does not shadow. Only 10–15% of gallstones are calcified enough to show on a plain radiograph, so an X-ray never rules them out.
Biliary colic vs the complications
| Condition | Key clue | Labs | Imaging | Management |
|---|---|---|---|---|
| Biliary colic | Steady RUQ pain, often after a heavy meal; intense within 15–60 min, usually lasting <6 h; no fever | Normal | Stones, no inflammation | Elective laparoscopic cholecystectomy |
| Acute cholecystitis | Pain >6 h, Murphy sign, low-grade fever; at least 90% have stones | Leukocytosis; bilirubin up to about 4 mg/dL even without a duct stone | Wall thickening, pericholecystic fluid, sonographic Murphy sign; on HIDA the gallbladder does not fill | Fluids, usually antibiotics, cholecystectomy within 7 days of admission; cholecystostomy if surgical risk is very high |
| Choledocholithiasis | Biliary pain plus jaundice; up to 10% of patients with symptomatic stones | High bilirubin, alkaline phosphatase, GGT and ALT | Duct >6 mm (>10 mm after cholecystectomy); ultrasound often misses the stone | ASGE pathway; ERCP with sphincterotomy, then cholecystectomy |
| Acute cholangitis | Charcot triad: fever or chills, jaundice, RUQ pain; Reynolds pentad adds confusion and hypotension | Leukocytosis, cholestatic liver tests; take blood cultures | Dilated duct, stone or other cause | Antibiotics plus biliary drainage: ERCP within 48 h (consider within 24 h in septic shock that does not respond to fluids) |
| Gallstone pancreatitis | Steady epigastric pain that can radiate to the back | Lipase or amylase >3 × upper limit of normal; rising bilirubin suggests a retained stone | Gallstones on ultrasound | Supportive care; ERCP only for cholangitis or ongoing obstruction; cholecystectomy before discharge if mild |
| Gallstone ileus | Older woman with small bowel obstruction | Nonspecific | Rigler triad: bowel obstruction, air in the biliary tree, ectopic gallstone (usually distal ileum) | Enterolithotomy; fistula repair and cholecystectomy may be added |
| Mirizzi syndrome | Jaundice or cholangitis from a stone impacted in the cystic duct or gallbladder neck that compresses the common duct | Cholestatic | MRCP: stone in the gallbladder neck, dilated ducts tapering to a normal common bile duct | Surgery; often recognized only at operation; subtotal cholecystectomy when anatomy is unclear |
Gallstones are the most common cause of acute pancreatitis (40–70% of cases), and most patients pass the stone without ERCP. Mirizzi syndrome affects under 1% of patients with gallstones. Practice with the gallstone ileus breakdown and these tips on acute vs chronic cholecystitis.
Workup: which test, and when
- Right upper quadrant ultrasound first: about 95% sensitive and specific for gallbladder stones; it also shows sludge and signs of cholecystitis and measures the common bile duct. In uncomplicated colic, liver tests and lipase are usually normal.
- HIDA scan (cholescintigraphy) when cholecystitis is suspected but ultrasound is equivocal: if the tracer never fills the gallbladder, the cystic duct is blocked. Parenteral nutrition, critical illness, severe liver disease and a previous sphincterotomy cause false positives; morphine helps the gallbladder fill. It is also the most reliable test for acalculous cholecystitis.
- MRCP or endoscopic ultrasound (EUS) for an intermediate probability of duct stones. On MRCP, stones are dark filling defects; EUS also finds gallbladder stones under 3 mm when other tests are equivocal.
- ERCP when a duct stone is likely or proven, or for cholangitis: it treats as well as diagnoses.
- CT is less sensitive than ultrasound for gallbladder stones but shows complications such as perforation and pancreatitis.
Duct stones: ASGE 2019 risk stratification
The 2019 ASGE guideline rates the probability of a common bile duct stone in a patient with symptomatic gallstones:
| Probability | Any one of | Next step |
|---|---|---|
| High | Duct stone on ultrasound or cross-sectional imaging; ascending cholangitis; total bilirubin >4 mg/dL plus a dilated duct (>6 mm with the gallbladder in place) | ERCP (before or after cholecystectomy), or laparoscopic duct clearance, depending on local expertise |
| Intermediate (10–50%) | Abnormal liver tests; age >55; dilated duct on imaging | EUS or MRCP, or laparoscopic intraoperative cholangiography or ultrasound |
| Low | None of these | Cholecystectomy, without preoperative duct imaging |
What changed from 2010: the old scheme called a stone on ultrasound, cholangitis or a bilirubin >4 mg/dL alone "very strong" predictors, bilirubin 1.8–4 mg/dL and a dilated duct "strong", and abnormal liver tests other than bilirubin, age >55 and gallstone pancreatitis "moderate"; any very strong predictor, or both strong ones, meant high risk, so a dilated duct alone was already intermediate. The 2019 version dropped bilirubin 1.8–4 mg/dL and gallstone pancreatitis as predictors, downgraded a dilated duct from "strong" to an intermediate predictor, and counts a high bilirubin as high risk only with a dilated duct, so fewer ERCPs find no stone. ASGE also recommends against urgent ERCP (within 48 hours) in gallstone pancreatitis without cholangitis or biliary obstruction.
Tokyo Guidelines 2018 (TG18) in one table
TG18 adopted the 2013 (TG13) criteria for acute cholangitis.
| Acute cholangitis | Acute cholecystitis | |
|---|---|---|
| A | Systemic inflammation: fever >38 °C or shaking chills; WBC <4,000 or >10,000/mm³, or CRP ≥1 mg/dL | Local signs: Murphy sign; RUQ mass, pain or tenderness |
| B | Cholestasis: total bilirubin ≥2 mg/dL; ALP, GGT, AST or ALT >1.5 × upper limit of normal | Systemic signs: fever, raised CRP, raised WBC |
| C | Imaging: biliary dilatation, or the cause (stricture, stone, stent) | Imaging findings typical of acute cholecystitis |
| Suspected | One A plus one B or C | One A plus one B |
| Definite | One each of A, B and C | One A, one B, plus C |
| Grade II (moderate) | Any two: WBC >12,000 or <4,000/mm³; fever ≥39 °C; age ≥75; total bilirubin ≥5 mg/dL; albumin <0.7 × lower limit of normal | Any one: WBC >18,000/mm³; palpable tender RUQ mass; symptoms >72 h; marked local inflammation (gangrenous or emphysematous cholecystitis, pericholecystic or hepatic abscess, biliary peritonitis) |
| Grade III (severe) | Organ dysfunction | Organ dysfunction |
Organ dysfunction (grade III) means any of: hypotension needing dopamine ≥5 µg/kg/min or any norepinephrine; reduced consciousness; PaO₂/FiO₂ <300; oliguria or creatinine >2.0 mg/dL; PT-INR >1.5; platelets <100,000/mm³. Grade I is anything milder.
- Cholangitis: antibiotics and fluids for all; drainage is urgent in grade III as soon as organ support has stabilized the patient, early in grade II, and considered in grade I only if there is no response to initial treatment within 24 hours. ASGE (2021) prefers ERCP to percutaneous drainage, within 48 hours, with sphincterotomy and stone extraction rather than a stent alone in stable patients. Practice with this cholangitis question on the Tokyo criteria.
- Cholecystitis: TG18 limits early surgery in grades II and III to advanced centers; percutaneous cholecystostomy is the fallback for patients too sick for surgery.
Management (Step 2 CK depth)
- Asymptomatic stones: observe. About 2% a year become symptomatic (10% at 5 years). Prophylactic cholecystectomy may be considered for stones >3 cm or a porcelain (calcified) gallbladder, which raise the risk of gallbladder carcinoma (the porcelain indication is debated), and for patients with stones who are having bariatric surgery.
- Symptomatic stones: laparoscopic cholecystectomy. Once colic starts it recurs in 20–40% of patients a year, and 1–2% a year develop complications.
- Acute cholecystitis: cholecystectomy within 7 days of admission and 10 days of onset (benefit shown in the first 24–48 hours); antibiotics such as ampicillin–sulbactam or piperacillin–tazobactam are usual, though unproven in mild cases.
- Duct stones: ERCP with sphincterotomy and stone removal, then cholecystectomy; sphincterotomy alone is an alternative for patients at high surgical risk.
- Mild gallstone pancreatitis: cholecystectomy in the same admission (PONCHO trial: biliary events in 17% when surgery was delayed vs 5%).
- Ursodeoxycholic acid (ursodiol): works best on tiny (<0.5 cm) radiolucent stones in a functioning gallbladder, takes months, and suits patients who refuse or cannot have surgery; stones recur in up to 50% within 5 years, and it does not dissolve calcified or pigment stones. It can also prevent stones during rapid weight loss after bariatric surgery.
How USMLE tests it: traps
- Biliary colic is not colicky: the pain is steady, fatty food is not a specific trigger, gas and bloating are not specific gallstone symptoms, and gallstones do not cause dyspepsia.
- A normal ultrasound does not exclude a duct stone: transabdominal ultrasound detects only 15–40% of them.
- A mildly raised bilirubin in cholecystitis (up to about 4 mg/dL) does not prove a duct stone; a lipase above 3 times normal suggests duct obstruction.
- Acalculous cholecystitis: critically ill patient (burns, sepsis, trauma, parenteral nutrition), no stones, and a distended, thick-walled gallbladder with sludge.
- Brown stones form in the ducts; black stones form in the gallbladder. Ileal disease turns up as a gallstone risk in Crohn disease questions.
Worked vignettes
Vignette 1 (Step 1). A 15-year-old boy with hereditary spherocytosis has had two episodes of right upper quadrant pain after meals. Ultrasound shows several small gallbladder stones, faintly visible on a plain radiograph. What are they made of?
Answer: black pigment stones (calcium bilirubinate). Chronic hemolysis floods bile with bilirubin, which crystallizes as calcium bilirubinate in the gallbladder; the calcium salts they contain can make black stones visible on X-ray. Not cholesterol: he has no metabolic risk factors, and cholesterol stones are usually radiolucent. Not brown: brown stones form in infected bile ducts.
Vignette 2 (Step 2 CK). A 60-year-old man has had three attacks of right upper quadrant pain; the last settled yesterday, and he is now afebrile and pain-free. Total bilirubin is 2.4 mg/dL, alkaline phosphatase 260 U/L and ALT 180 U/L; lipase is normal. Ultrasound shows gallbladder stones, a normal wall, a 7-mm common bile duct and no visible duct stone. Best next step?
Answer: MRCP or EUS (intraoperative cholangiography or ultrasound at cholecystectomy is the guideline's surgical alternative). He is intermediate risk under ASGE 2019 (abnormal liver tests, age over 55, dilated duct) with no high-risk feature: no stone seen, no cholangitis, bilirubin under 4 mg/dL. Under the 2010 criteria (bilirubin 1.8–4 mg/dL plus a dilated duct) he would have gone straight to ERCP. A stone means ERCP, then cholecystectomy; no stone means cholecystectomy. HIDA answers a different question (cholecystitis).
Vignette 3 (Step 2 CK). A 79-year-old woman has 2 days of right upper quadrant pain, rigors and jaundice. Temperature is 39.4 °C and blood pressure 118/70 mm Hg; she is alert and comfortable on room air. WBC is 16,800/mm³, total bilirubin 4.6 mg/dL and alkaline phosphatase 3 times normal; creatinine, platelets and INR are normal. Ultrasound shows an 11-mm common bile duct containing a stone. Diagnosis, grade and next step?
Answer: definite acute cholangitis, TG18 grade II → blood cultures, IV antibiotics (such as piperacillin–tazobactam) and early ERCP (within 48 hours) with sphincterotomy and stone extraction, then cholecystectomy if she is fit for surgery. She has A (fever, high WBC), B (bilirubin ≥2 mg/dL) and C (dilated duct with a stone). Grade II needs two of five predictors; she has three: WBC >12,000/mm³, fever ≥39 °C and age ≥75 (bilirubin is under 5 mg/dL). With no organ dysfunction she is not grade III. Emergency cholecystectomy would not drain the duct.
Key takeaways
- 5 F's: female, fat and fertile hold up, forty means "older", and fair is the shakiest; add family history and fast weight loss.
- Cholesterol stones dominate; black stones form in the gallbladder (hemolysis, cirrhosis, ileal disease); brown stones form in infected ducts.
- Colic is steady pain under 6 hours with normal labs; fever, longer pain, jaundice or a high lipase signals a complication.
- Ultrasound first, HIDA for equivocal cholecystitis, ASGE 2019 for duct stones, TG18 to grade cholangitis and cholecystitis.
- Treat symptoms, not stones: cholecystectomy for symptomatic gallstones, observation for most silent ones.
Sources
- Cholelithiasis — Merck Manual Professional Edition (2026)
- Acute Cholecystitis — Merck Manual Professional Edition (2025)
- Choledocholithiasis and Cholangitis — Merck Manual Professional Edition (2025)
- Acute Pancreatitis — Merck Manual Professional Edition (2026)
- Definition & Facts for Gallstones — NIDDK (2017)
- Gallstones (Cholelithiasis) — Medscape (2019)
- Gallstones (Cholelithiasis) Workup — Medscape (2016)
- Bass G, et al. Validating the 5Fs mnemonic for cholelithiasis: time to include family history — Postgraduate Medical Journal (2013)
- ASGE guideline on the role of endoscopy in the evaluation and management of choledocholithiasis, Spanish edition — ASGE (2019)
- Wang L, et al. Systematic review and meta-analysis of the 2010 ASGE non-invasive predictors of choledocholithiasis and comparison to the 2019 ASGE predictors — Clinical Journal of Gastroenterology (2022)
- ASGE guideline on the management of cholangitis, Spanish edition — ASGE (2021)
- Kiriyama S, et al. TG13 guidelines for diagnosis and severity grading of acute cholangitis — Journal of Hepato-Biliary-Pancreatic Sciences (2013)
- Acute Cholecystitis, Tips & Tricks — European Society for Trauma and Emergency Surgery (ESTES) (2025)
- Ceftriaxone for injection, prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
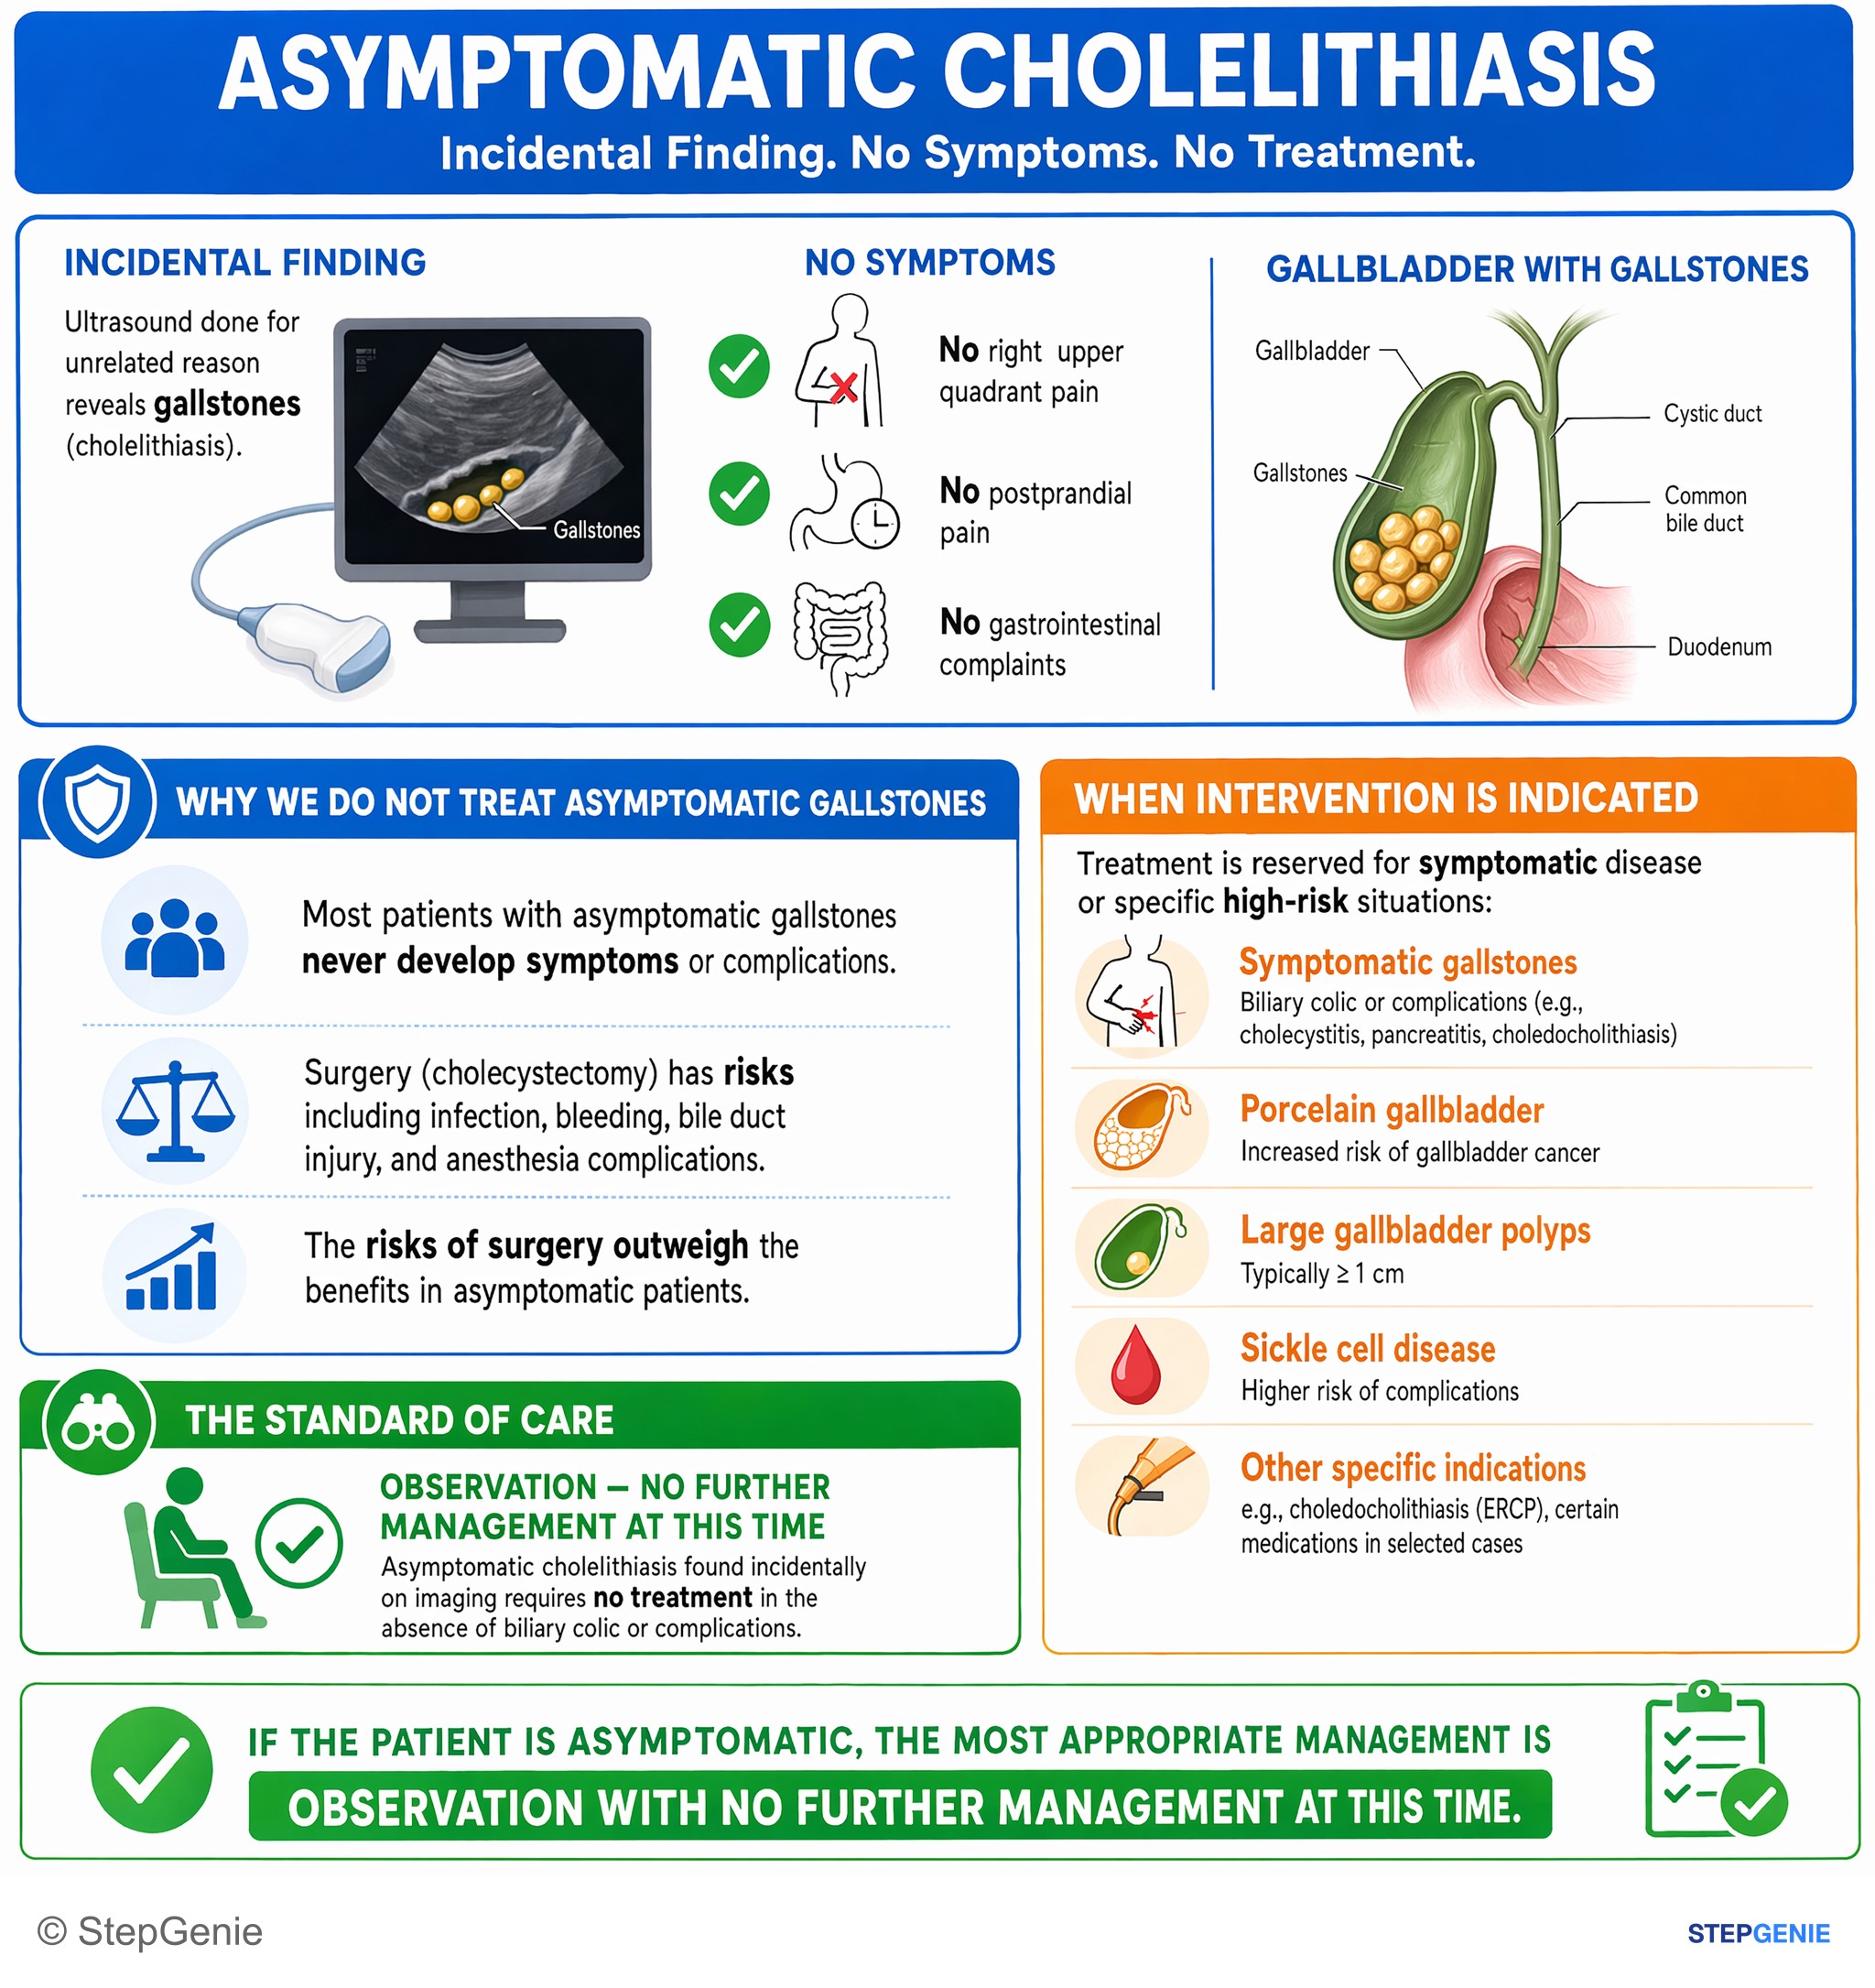
Asymptomatic cholelithiasis found incidentally on imaging requires no treatment in the absence of biliary colic or complications.
USMLE Step 2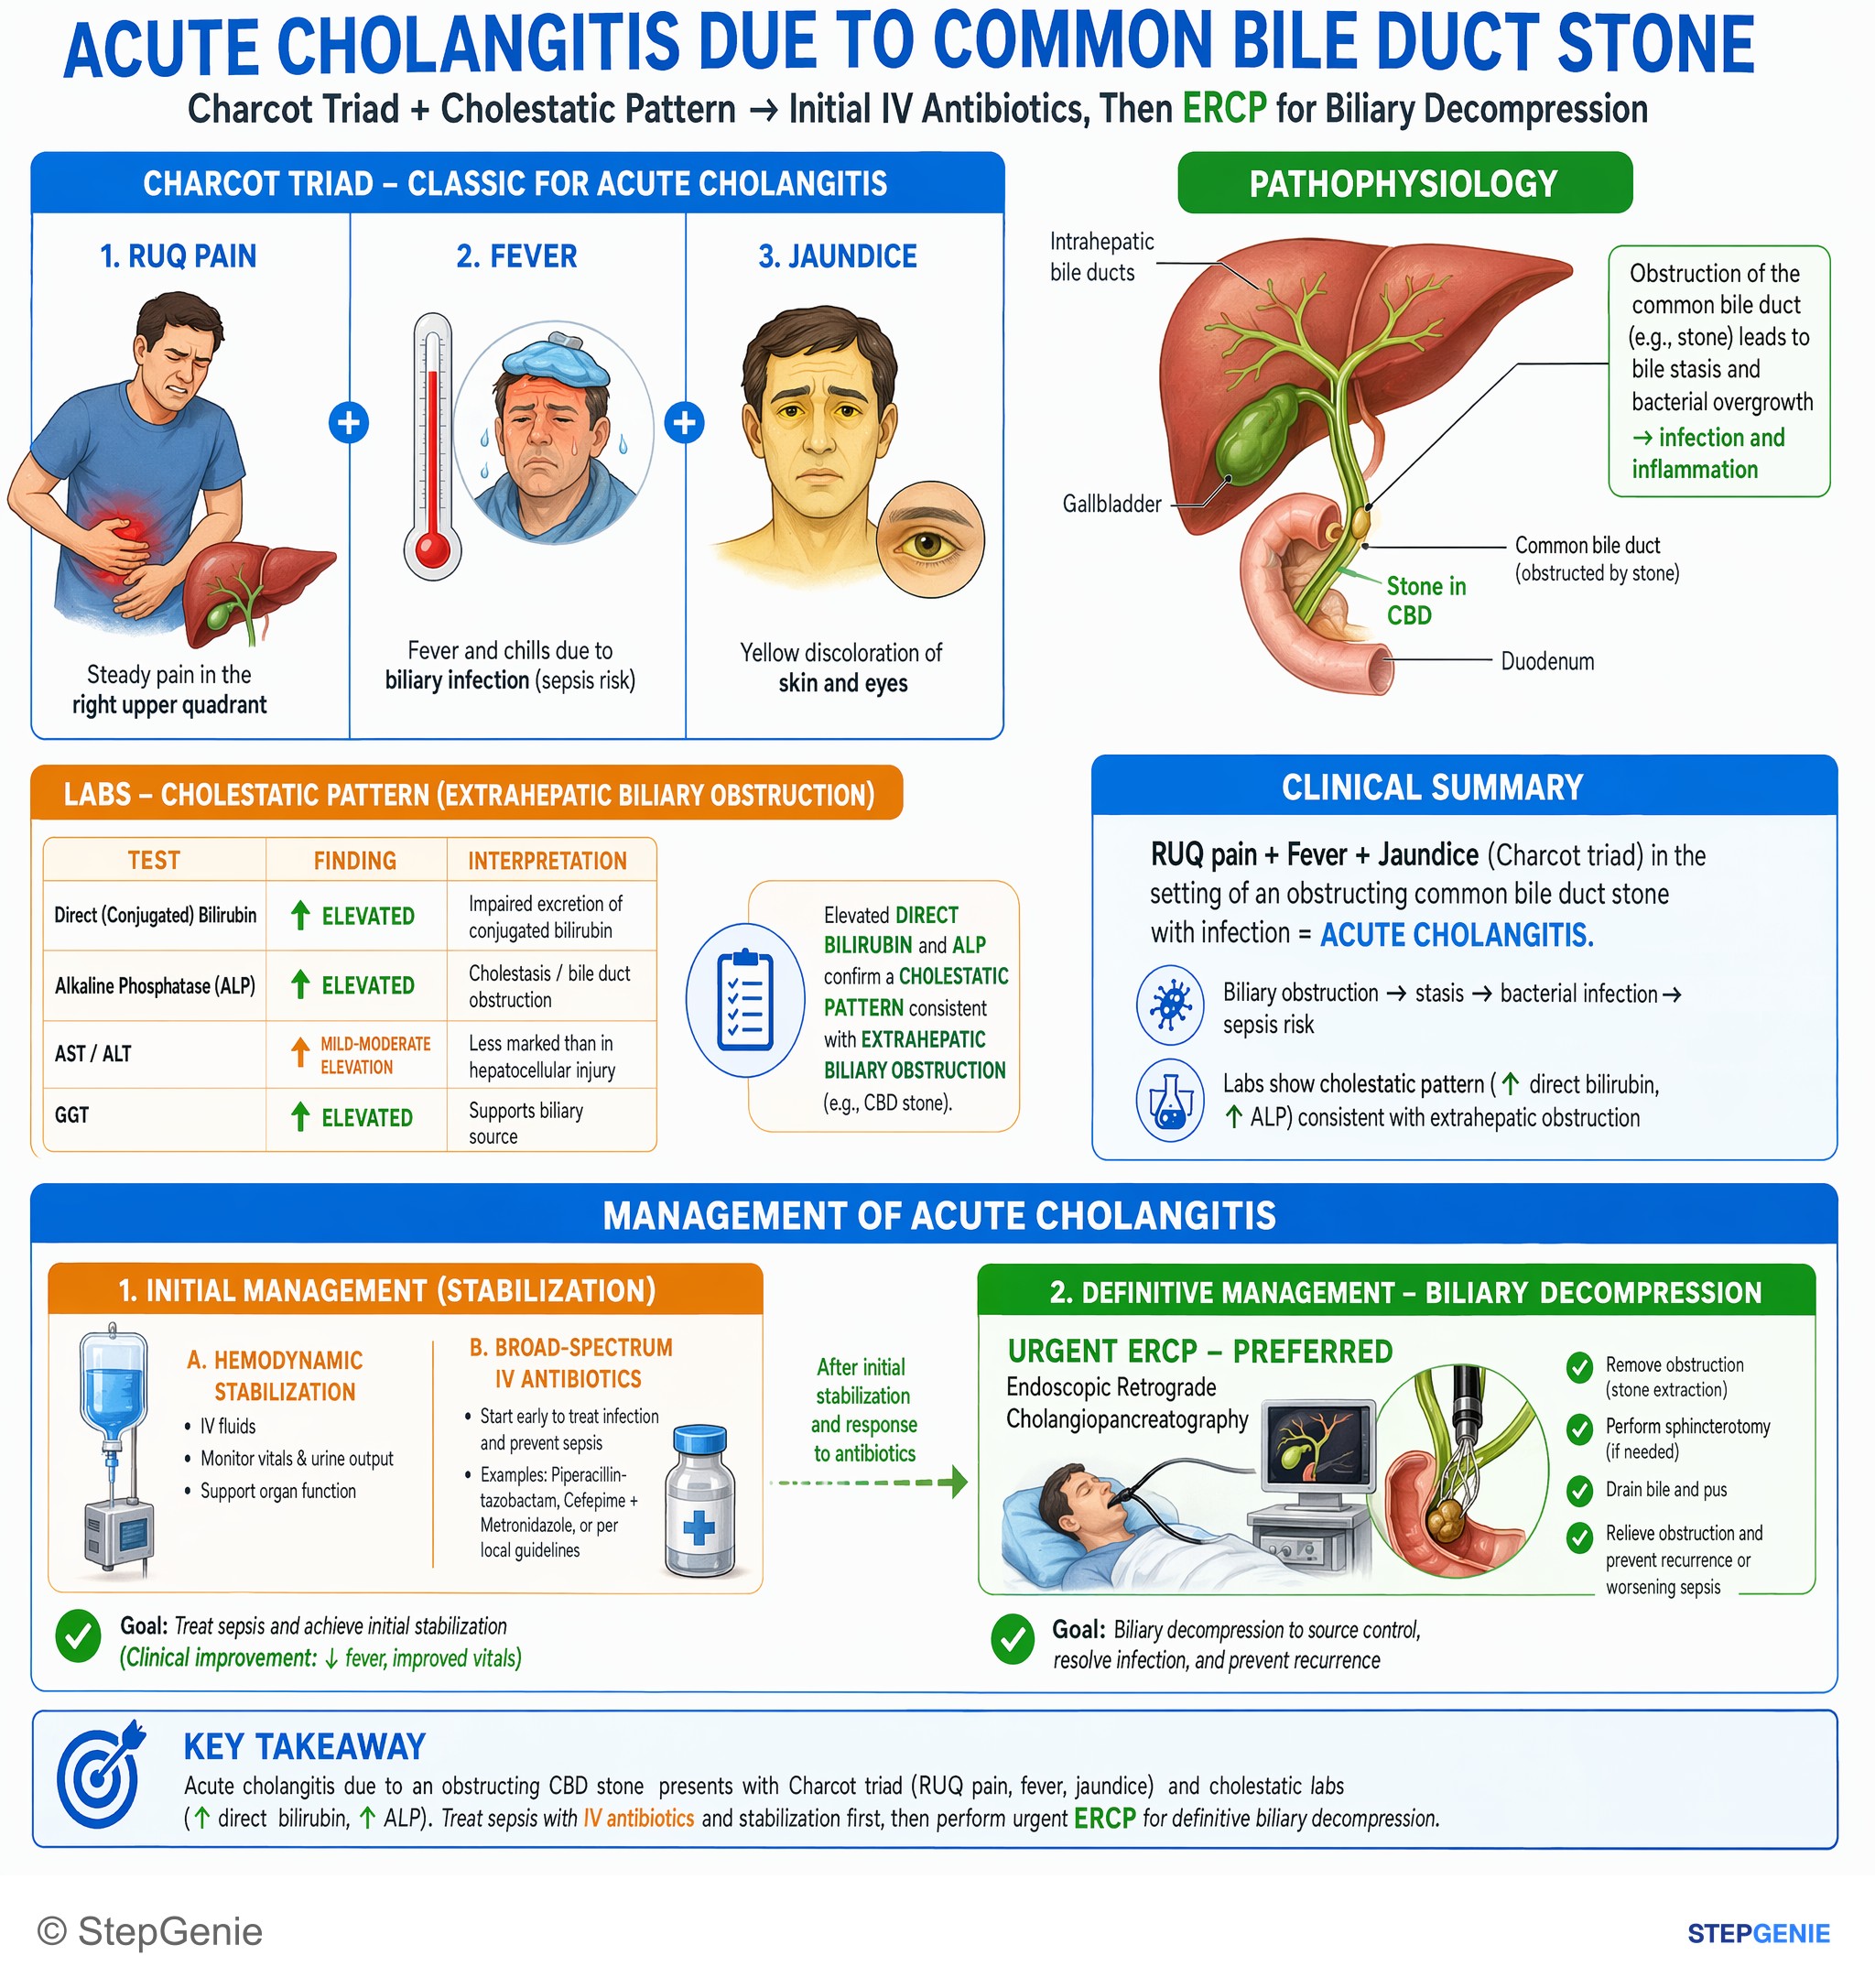
Acute cholangitis from obstructing common bile duct stone: RUQ pain, fever, jaundice. Initial IV antibiotics, then urgent ERCP for biliary…
USMLE Step 2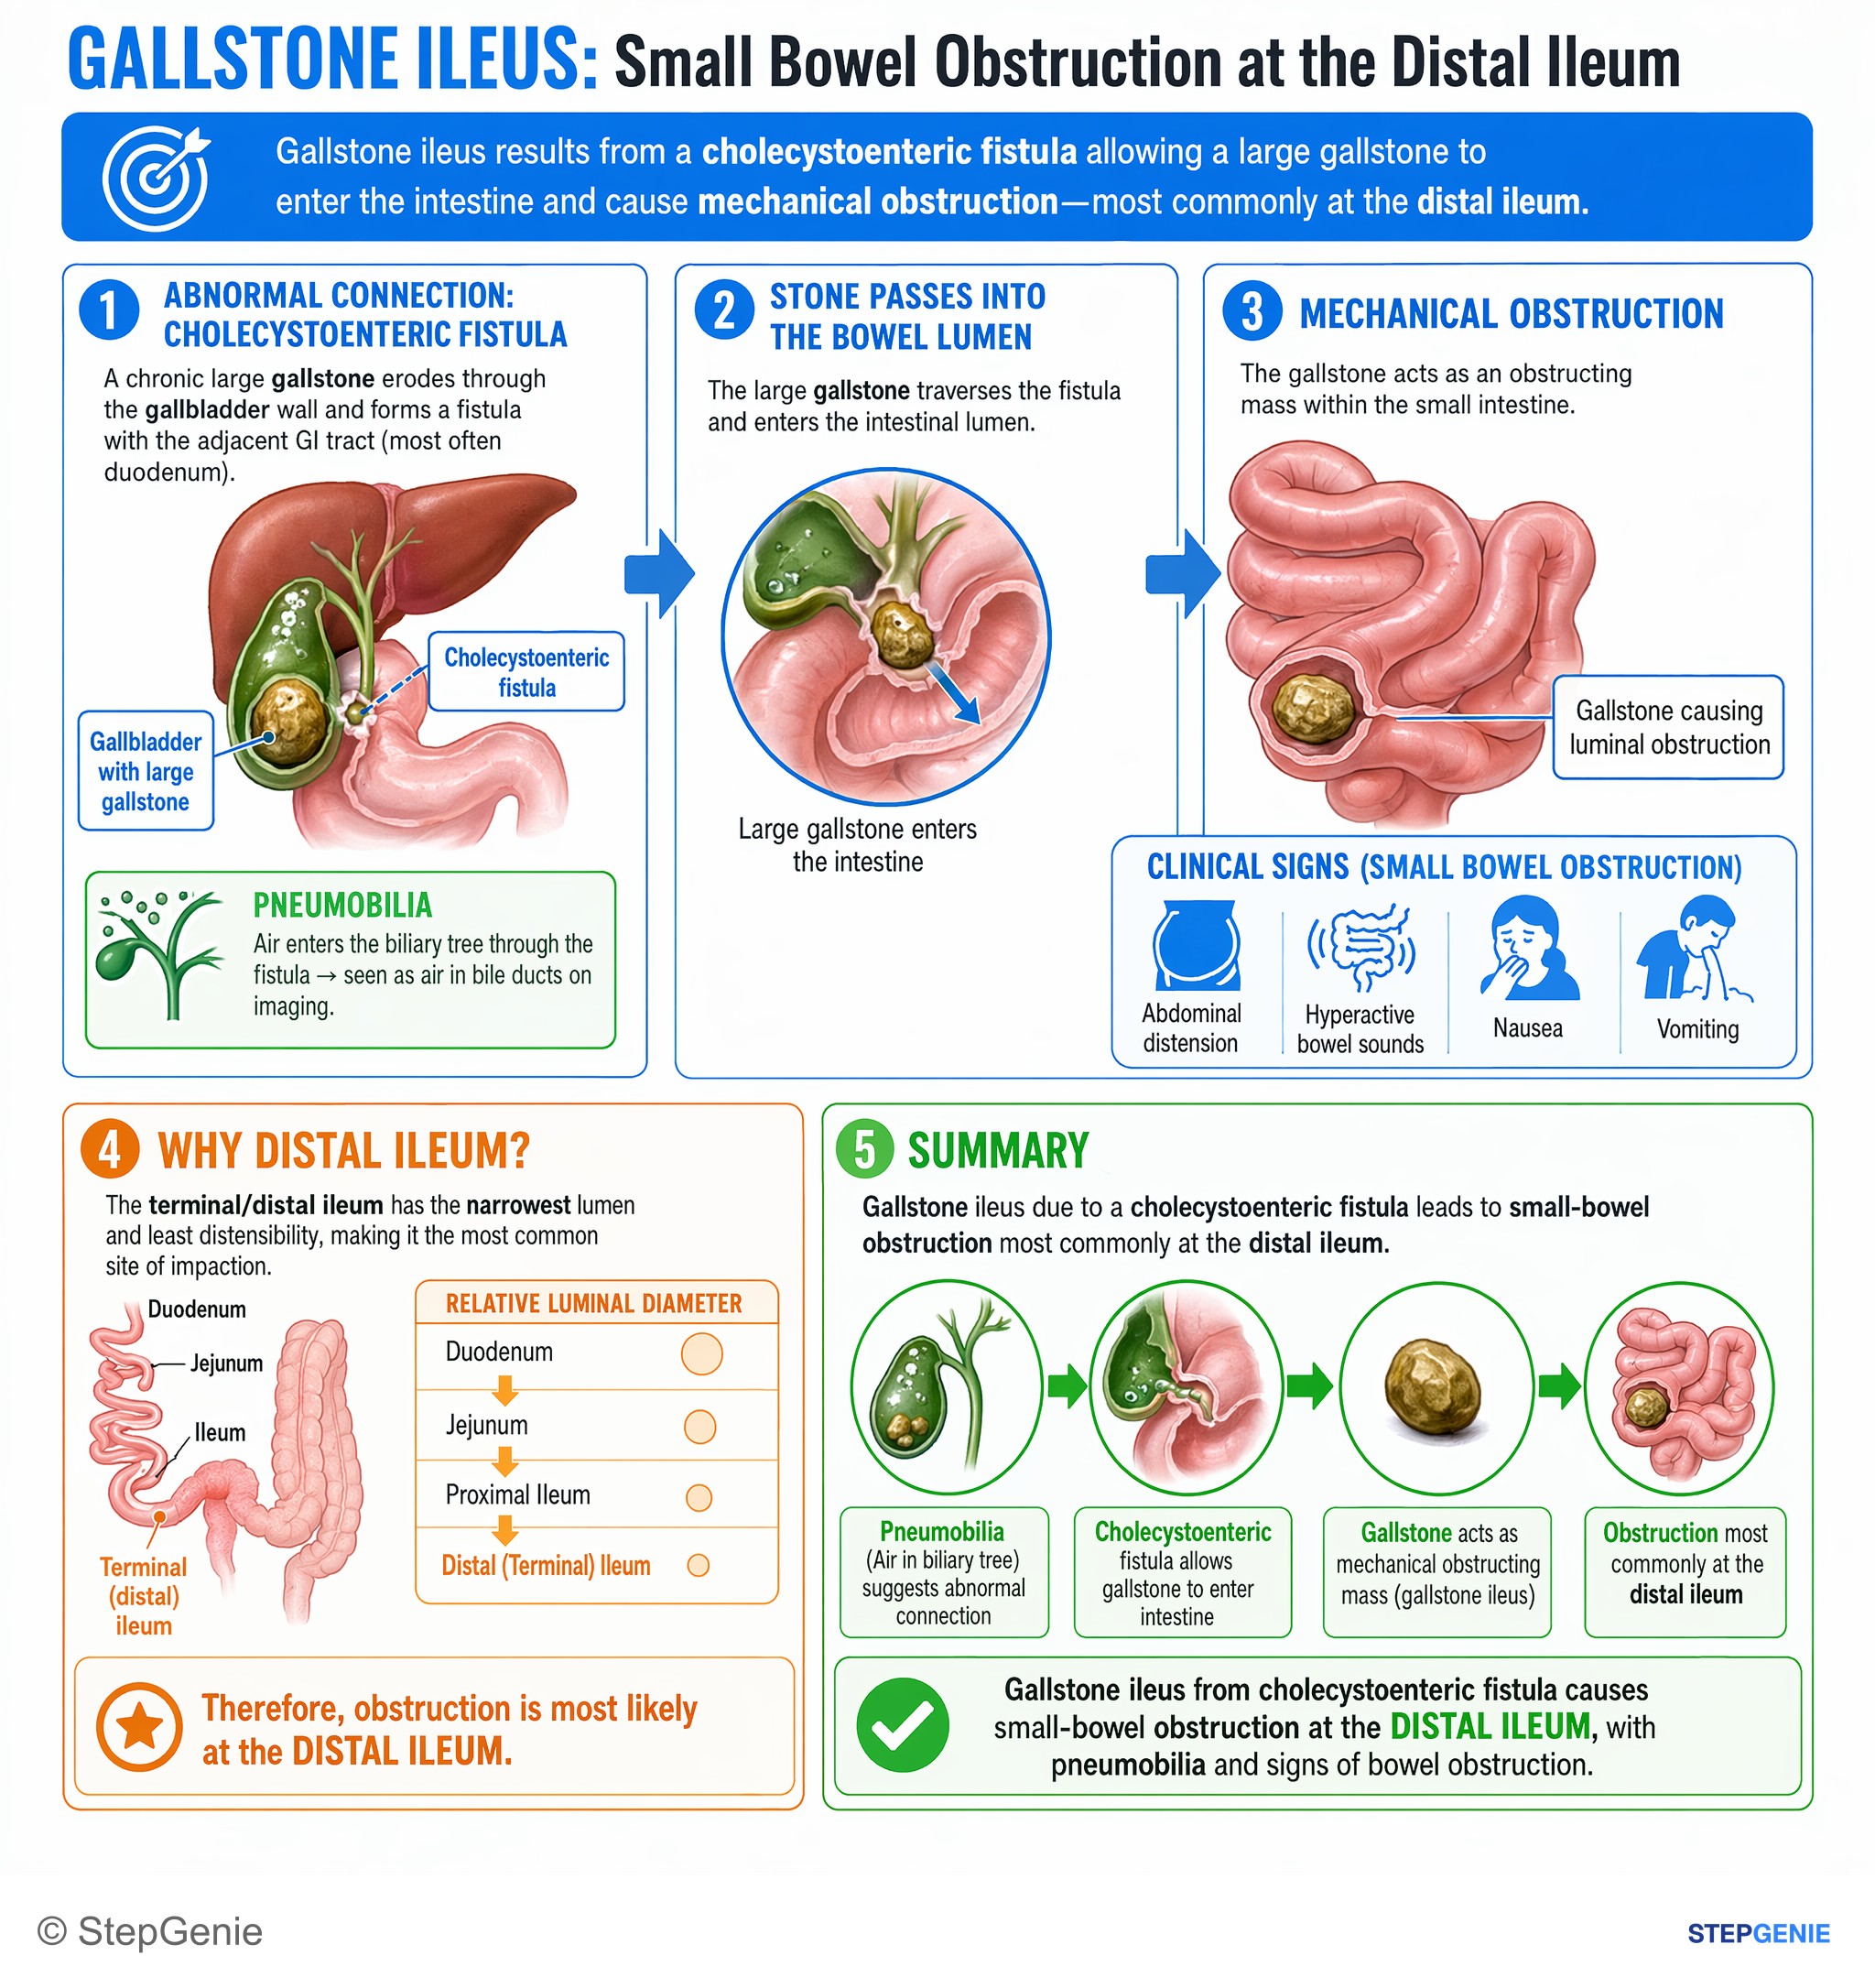
Gallstone ileus from cholecystoenteric fistula causes small-bowel obstruction at the distal ileum, with pneumobilia and signs of bowel…
USMLE Step 1Frequently Asked Questions
What are the 5 F's of gallstones?
The 5 F's are fat, female, fertile, forty and fair: the classic profile of a patient with cholesterol gallstones (cholelithiasis). Obesity, female sex and pregnancy are well-supported risk factors, and age counts as "older" rather than as a cut-off at 40. "Fair" is the shakiest F, a crude stand-in for ancestry. In a 2013 test of the mnemonic, 39.4% of patients with stones had a first-degree relative with gallstones vs 13.5% of controls, so add family history, plus fast weight loss.
Are the 5 F's for cholecystitis or cholelithiasis?
The 5 F's describe who gets gallstones (cholelithiasis), specifically cholesterol stones. They turn up in cholecystitis teaching because at least 90% of acute cholecystitis is caused by a gallstone blocking the cystic duct, so the same patients are at risk. The F's do not diagnose cholecystitis: that needs local signs such as a Murphy sign, systemic inflammation such as fever or leukocytosis, and typical imaging findings, as set out in the Tokyo Guidelines 2018.
How long does biliary colic last, and how is it different from cholecystitis?
Biliary colic starts suddenly, becomes intense within 15 to 60 minutes, stays steady (it is not truly colicky) for usually less than 6 hours and then fades over 30 to 90 minutes. Nausea is common, but fever is not, and labs are normal. Pain lasting more than 6 hours, especially with fever, a Murphy sign or leukocytosis, suggests acute cholecystitis; jaundice suggests a duct stone, and a lipase above 3 times normal suggests gallstone pancreatitis.
What are the three types of gallstones?
Cholesterol stones, more than 85% of gallstones in Western countries, form in the gallbladder from cholesterol-supersaturated bile and are usually radiolucent. Black pigment stones are small, hard calcium bilirubinate stones that form in the gallbladder with chronic hemolysis (sickle cell disease, hereditary spherocytosis), cirrhosis or ileal disease, and they may contain enough calcium to show on X-ray. Brown pigment stones are soft stones of calcium bilirubinate and fatty acid salts that form in the bile ducts with stasis and infection, including liver flukes.
What is the first test for gallstones, and when is MRCP, EUS or ERCP needed?
Right upper quadrant ultrasound comes first: it is about 95% sensitive and specific for gallbladder stones. A HIDA scan helps when cholecystitis is suspected but ultrasound is equivocal. For duct stones, the 2019 ASGE guideline sends high-risk patients (a duct stone on imaging, cholangitis, or bilirubin above 4 mg/dL with a dilated duct) to ERCP, intermediate-risk patients (abnormal liver tests, age over 55, or a dilated duct) to MRCP, EUS or intraoperative cholangiography, and low-risk patients straight to cholecystectomy.
When should asymptomatic gallstones be removed?
Usually they are left alone: up to 80% of people with gallstones have no symptoms, and only about 2% a year become symptomatic. Prophylactic cholecystectomy may be considered for stones larger than 3 cm or a calcified (porcelain) gallbladder, both linked to gallbladder carcinoma (the porcelain indication is debated), and for patients with stones who are having bariatric surgery. Once biliary colic starts, laparoscopic cholecystectomy is the treatment of choice, because pain recurs in 20 to 40% of patients a year.