Cirrhosis is diffuse hepatic fibrosis with regenerative nodules. The scarred liver resists portal blood flow while nitric oxide-driven splanchnic vasodilation pushes more blood in, so portal pressure climbs: a hepatic venous pressure gradient (HVPG) above 5 mm Hg is portal hypertension, 10 mm Hg or more is clinically significant portal hypertension (CSPH), and varices rarely bleed below 12 mm Hg. Decompensation means overt ascites, variceal bleeding or overt hepatic encephalopathy. Current guidance (AASLD 2024, Baveno VIII 2026) gives carvedilol to prevent decompensation once CSPH is present, and treats an acute variceal bleed with a vasoactive drug, IV ceftriaxone, banding within 12 hours and pre-emptive TIPS for high-risk patients.
The 5-10-12 rule: HVPG thresholds
HVPG is the wedged minus the free hepatic vein pressure, a stand-in for the portal-to-caval gradient.
| HVPG | Meaning | Clinical consequence |
|---|---|---|
| 1-5 mm Hg | Normal | None |
| 6-9 mm Hg | Mild (subclinical) portal hypertension | Decompensation uncommon below 10 |
| ≥10 mm Hg | CSPH | Varices and decompensation can develop; NSBB indicated in compensated cirrhosis |
| >12 mm Hg | Bleeding range | Variceal bleeding almost never occurs below this |
HVPG needs a catheter, so practice uses surrogates. CSPH is already proven by any decompensation, varices on endoscopy or collaterals on imaging (AASLD 2024). On elastography (Baveno VIII 2026), liver stiffness ≤15 kPa with platelets ≥150 × 10⁹/L rules out CSPH, and ≥25 kPa rules it in in viral or alcohol-related disease and nonobese (BMI <30) MASLD.
Why the pressure rises
- Fixed resistance: injury activates hepatic stellate (Ito) cells, vitamin A-storing cells in the sinusoid wall, which become myofibroblasts and lay down collagen. Fibrous septa and regenerating nodules distort and compress the sinusoids and hepatic venules.
- Dynamic resistance: less intrahepatic nitric oxide and more endothelin raise vascular tone, about 30% of the rise in intrahepatic resistance (AASLD).
- More inflow: splanchnic vasodilation (nitric oxide) creates a hyperdynamic circulation that increases portal flow ("tight liver, wide pipes"). The resulting arterial underfilling switches on RAAS, sympathetic tone and ADH: the root of ascites and hepatorenal syndrome.
| Level | Classic causes |
|---|---|
| Prehepatic | Portal or splenic vein thrombosis |
| Intrahepatic, presinusoidal | Schistosomiasis, congenital hepatic fibrosis |
| Intrahepatic, sinusoidal | Cirrhosis (most common cause in Western countries) |
| Intrahepatic, postsinusoidal | Sinusoidal obstruction syndrome (veno-occlusive disease) |
| Posthepatic | Budd-Chiari syndrome, IVC obstruction, right heart failure |
The leading US causes of cirrhosis are alcohol, chronic hepatitis C and MASH (metabolic dysfunction-associated steatohepatitis). Budd-Chiari has its own pattern; see the Budd-Chiari question breakdown.
Stigmata and labs: what each one means
| Finding | Mechanism |
|---|---|
| Spider angiomas, palmar erythema | Raised estrogen-to-free-testosterone ratio |
| Gynecomastia, testicular atrophy, axillary hair loss | Less testosterone made, more converted to estrogen |
| Splenomegaly, thrombocytopenia | Sequestration in an enlarged spleen plus altered thrombopoietin |
| ↑ PT/INR, ↓ albumin | Synthetic failure (in cirrhosis the INR does not predict bleeding risk) |
| AST:ALT > 2 with ↑ GGT | Suggests alcohol as the cause |
| Asterixis, fetor hepaticus | Hepatic encephalopathy |
| Caput medusae | Recanalized paraumbilical veins (much rarer than other abdominal wall collaterals) |
Portosystemic collaterals: the anatomy Step 1 tests
| Site | Portal side | Systemic side | Result |
|---|---|---|---|
| Distal esophagus, gastric fundus | Left gastric vein | Esophageal veins → azygos | Esophageal and gastric varices: painless, massive hematemesis |
| Umbilicus | Paraumbilical veins | Superficial and inferior epigastric tributaries | Caput medusae |
| Rectum | Superior rectal vein → inferior mesenteric vein | Middle and inferior rectal veins → internal iliac | Rectal varices |
Varices: prevent first, then stop the bleed
Prevention (AASLD 2024, Baveno VIII):
- Compensated cirrhosis with CSPH → nonselective beta-blocker, preferably carvedilol (6.25 mg, then 12.5 mg/day), to prevent decompensation, not just bleeding. Without CSPH, NSBBs are not recommended.
- Patients already on an NSBB do not need screening endoscopy.
- High-risk varices and NSBB intolerance → endoscopic band ligation (EVL) every 2-4 weeks until the varices are obliterated.
- TIPS is not used for primary prophylaxis or to prevent decompensation.
- Mechanism (classic pharm question): β1 blockade lowers cardiac output; β2 blockade leaves splanchnic α-adrenergic tone unopposed, constricting splanchnic arterioles and cutting portal inflow. Carvedilol adds α1 blockade and nitric oxide release (intrahepatic vasodilation), so it lowers HVPG more than propranolol or nadolol. A β1-selective drug such as metoprolol lacks the β2 effect; AASLD notes such patients can be switched to an NSBB.
Acute variceal hemorrhage (AASLD 2024 bundle):
- Vasoactive drug at presentation (octreotide, or somatostatin or terlipressin where available), continued 2-5 days once portal hypertensive bleeding is confirmed.
- IV antibiotic prophylaxis, usually ceftriaxone 1 g/24 h, up to 5 days; it also prevents SBP.
- Restrictive transfusion to hemoglobin ~7 g/dL unless comorbidities demand more. Liberal blood products worsen portal pressure and survival; don't give plasma or platelets to "correct" the INR or platelet count.
- Upper endoscopy within 12 hours → band ligation.
- Pre-emptive TIPS within 72 hours (ideally 24) for Child-Pugh C 10-13, or Child-Pugh B >7 with active bleeding at endoscopy.
- Uncontrolled bleeding: balloon tamponade or an esophageal stent as a bridge to salvage TIPS.
- Afterwards: NSBB + EVL as secondary prophylaxis.
TIPS connects a portal vein branch to a hepatic vein, so it decompresses the portal system but lets more gut-derived toxins bypass the liver: new or worse hepatic encephalopathy is the classic complication. More drill: the esophageal varices review.
Ascites and spontaneous bacterial peritonitis
Diagnostic paracentesis for new ascites, ascites of unknown cause, or suspected SBP.
| SAAG (serum minus ascites albumin) | Meaning | Causes |
|---|---|---|
| ≥1.1 g/dL | Portal hypertension | Cirrhosis, alcoholic hepatitis, Budd-Chiari, portal vein thrombosis, heart failure |
| <1.1 g/dL | Not portal hypertension | Peritoneal carcinomatosis, peritoneal TB, pancreatitis, nephrotic syndrome |
Ascites treatment: sodium 2,000 mg/day; spironolactone (it targets the secondary hyperaldosteronism), usually with furosemide; restrict fluid only if sodium is <125 mEq/L. Large-volume paracentesis of >5 L needs IV albumin, 6-8 g per liter removed. Ascites refractory to spironolactone 400 mg + furosemide 160 mg → serial paracentesis, TIPS or transplant evaluation.
SBP is infection of ascitic fluid without an apparent source. It can present with fever and abdominal pain, or only with new encephalopathy or worsening liver function.
- Diagnosis: ascitic neutrophil (PMN) count >250 cells/µL; inoculating blood culture bottles raises the culture yield.
- Bugs: usually a single organism: gram-negative rods (E. coli, Klebsiella) or gram-positive cocci (S. pneumoniae, enterococci, S. aureus). Mixed flora suggests a perforated viscus (secondary peritonitis) or contamination.
- Treatment: IV ceftriaxone or cefotaxime for at least 5 days, plus albumin 1.5 g/kg on day 1 and 1 g/kg on day 3 to prevent hepatorenal syndrome.
- Prophylaxis: long-term after a first episode (SBP recurs within a year in up to 70% of patients), typically an oral quinolone; short-term IV antibiotics during any GI bleed in cirrhosis.
Hepatic encephalopathy
Gut bacteria make ammonia; a failing liver and portosystemic shunts let it reach the brain, where astrocytes convert it to glutamine, which swells them. Look for asterixis, sleep disturbance and confusion (West Haven grade 2 = lethargy, mild disorientation).
- Precipitants: GI bleeding, infection (including SBP), constipation, hypokalemia, metabolic alkalosis, dehydration or over-diuresis, benzodiazepines and opioids, TIPS, kidney injury.
- Ammonia level: a normal level argues against HE, but a high level alone neither diagnoses nor guides therapy.
- Treatment: fix the trigger; lactulose titrated to 2-3 soft stools/day (colonic bacteria turn it into acids that trap NH₃ as NH₄⁺); add rifaximin 550 mg twice daily to prevent recurrence. Do not restrict protein (target 1.2-1.5 g/kg/day).
See the hepatic encephalopathy question breakdown for trigger-based stems.
Hepatorenal syndrome (HRS-AKI)
A functional kidney failure: extreme splanchnic vasodilation → low effective arterial volume → intense renal vasoconstriction, with structurally normal kidneys. The urine looks prerenal: very low urine sodium (FENa often <0.2%) and bland sediment.
HRS-AKI criteria (International Club of Ascites): cirrhosis with ascites; an AKI-range creatinine rise (0.3 mg/dL within 48 hours or 50% within 7 days); no response after 2 days of stopping diuretics and giving albumin 1 g/kg/day (max 100 g); no shock; no current or recent nephrotoxins; no signs of structural kidney disease (proteinuria >500 mg/day, hematuria, abnormal ultrasound). Common triggers: SBP and other infections, GI bleeding, over-diuresis, and large-volume paracentesis without albumin.
Treatment: terlipressin (a V1-selective vasopressin analog) plus albumin. Terlipressin (Terlivaz, FDA-approved 2022 for HRS with rapidly falling kidney function) has a boxed warning for serious or fatal respiratory failure: don't start it while SpO₂ is below 90%; the risk is higher with volume overload, and the label says to avoid it in ACLF grade 3. Alternatives: norepinephrine + albumin, or midodrine + octreotide + albumin. Liver transplant is definitive. Unlike ordinary prerenal AKI (AKI breakdown), HRS does not improve with volume.
Staging, prognosis and HCC
- Child-Pugh (5 items; mnemonic ABCDE: Albumin, Bilirubin, Coagulation [INR], Distension [ascites], Encephalopathy): A 5-6, B 7-9, C 10-15 points.
- MELD 3.0 (bilirubin, INR, creatinine, sodium, albumin and, in adults, sex) ranks US transplant candidates aged 12 or older; refer for transplant evaluation at MELD ≥15.
- Median survival is more than 12 years while compensated, but under 1.5 years after decompensation (AASLD 2024).
- Cirrhosis calls for HCC surveillance: ultrasound with or without AFP every 6 months (HCC recognition rule).
- Recompensation (Baveno VIII): the cause is removed, controlled or suppressed; ascites has resolved off diuretics; there is no overt HE off lactulose or rifaximin; there is no recurrent variceal bleeding; all of this has lasted more than 6 consecutive months; and liver tests are back in the Child-Pugh A range.
How USMLE tests it
- NSBB question: the answer is propranolol, nadolol or carvedilol, never metoprolol or atenolol.
- Confused cirrhotic: find the precipitant (bleed, infection, hypokalemia, sedative), then lactulose.
- Fever, abdominal pain or new confusion with ascites: tap it; PMN >250 = SBP.
- TIPS fixes bleeding and ascites but worsens encephalopathy.
Practice question
A 58-year-old man with alcohol-associated cirrhosis has been abstinent for a year. He has never had ascites, bleeding or confusion. Platelets are 92,000/mm³. Upper endoscopy shows small esophageal varices without red wale signs. Blood pressure is 126/78 mm Hg and pulse 76/min; he has no asthma. Which is the most appropriate next step to lower his risk of decompensation?
A. Carvedilol B. Metoprolol C. Octreotide infusion D. TIPS placement E. Spironolactone
Answer: A. Varices on endoscopy prove CSPH, and he is compensated, so AASLD 2024 and Baveno VIII recommend a nonselective beta-blocker, preferably carvedilol, to prevent decompensation (ascites, bleeding, encephalopathy).
- B: metoprolol is β1-selective. Without β2 blockade there is no unopposed α-mediated splanchnic vasoconstriction, so portal inflow barely falls.
- C: octreotide is for the acute bleed (2-5 days), not long-term prevention.
- D: TIPS is not used to prevent decompensation or a first bleed, and it raises the risk of encephalopathy.
- E: spironolactone treats ascites, which he doesn't have.
Key takeaways
- HVPG 5-10-12: >5 = portal hypertension, ≥10 = CSPH, >12 = bleeding range.
- Classic anastomoses: left gastric ↔ esophageal (varices), paraumbilical ↔ epigastric (caput medusae), superior ↔ middle/inferior rectal (rectal varices).
- Compensated + CSPH → carvedilol; no screening endoscopy needed once on an NSBB.
- Acute variceal bleed: octreotide + ceftriaxone + Hb target ~7 + EGD with banding in 12 h; pre-emptive TIPS for Child C 10-13 or B >7 with active bleeding.
- SAAG ≥1.1 = portal hypertension; PMN >250 = SBP (ceftriaxone + albumin).
- HE: find the trigger, lactulose, add rifaximin; don't restrict protein.
- HRS: functional, low urine Na, no response to albumin; terlipressin + albumin, transplant.
Sources
- Baveno VIII – Advancing consensus in portal hypertension — Journal of Hepatology (2026)
- AASLD Practice Guidance on Risk Stratification and Management of Portal Hypertension and Varices in Cirrhosis — AASLD (2024)
- Portal Hypertension — Merck Manual Professional Edition (2026)
- Cirrhosis — Merck Manual Professional Edition (2026)
- Ascites — Merck Manual Professional Edition (2025)
- Spontaneous Bacterial Peritonitis (SBP) — Merck Manual Professional Edition (2025)
- Portosystemic Encephalopathy — Merck Manual Professional Edition (2025)
- Hepatic Encephalopathy — StatPearls, NCBI Bookshelf (2025)
- Ascites — StatPearls, NCBI Bookshelf (2025)
- Hepatorenal Syndrome — StatPearls, NCBI Bookshelf (2026)
- TERLIVAZ (terlipressin) prescribing information — DailyMed (2026)
- MELD Calculator — Organ Procurement and Transplantation Network, HRSA
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
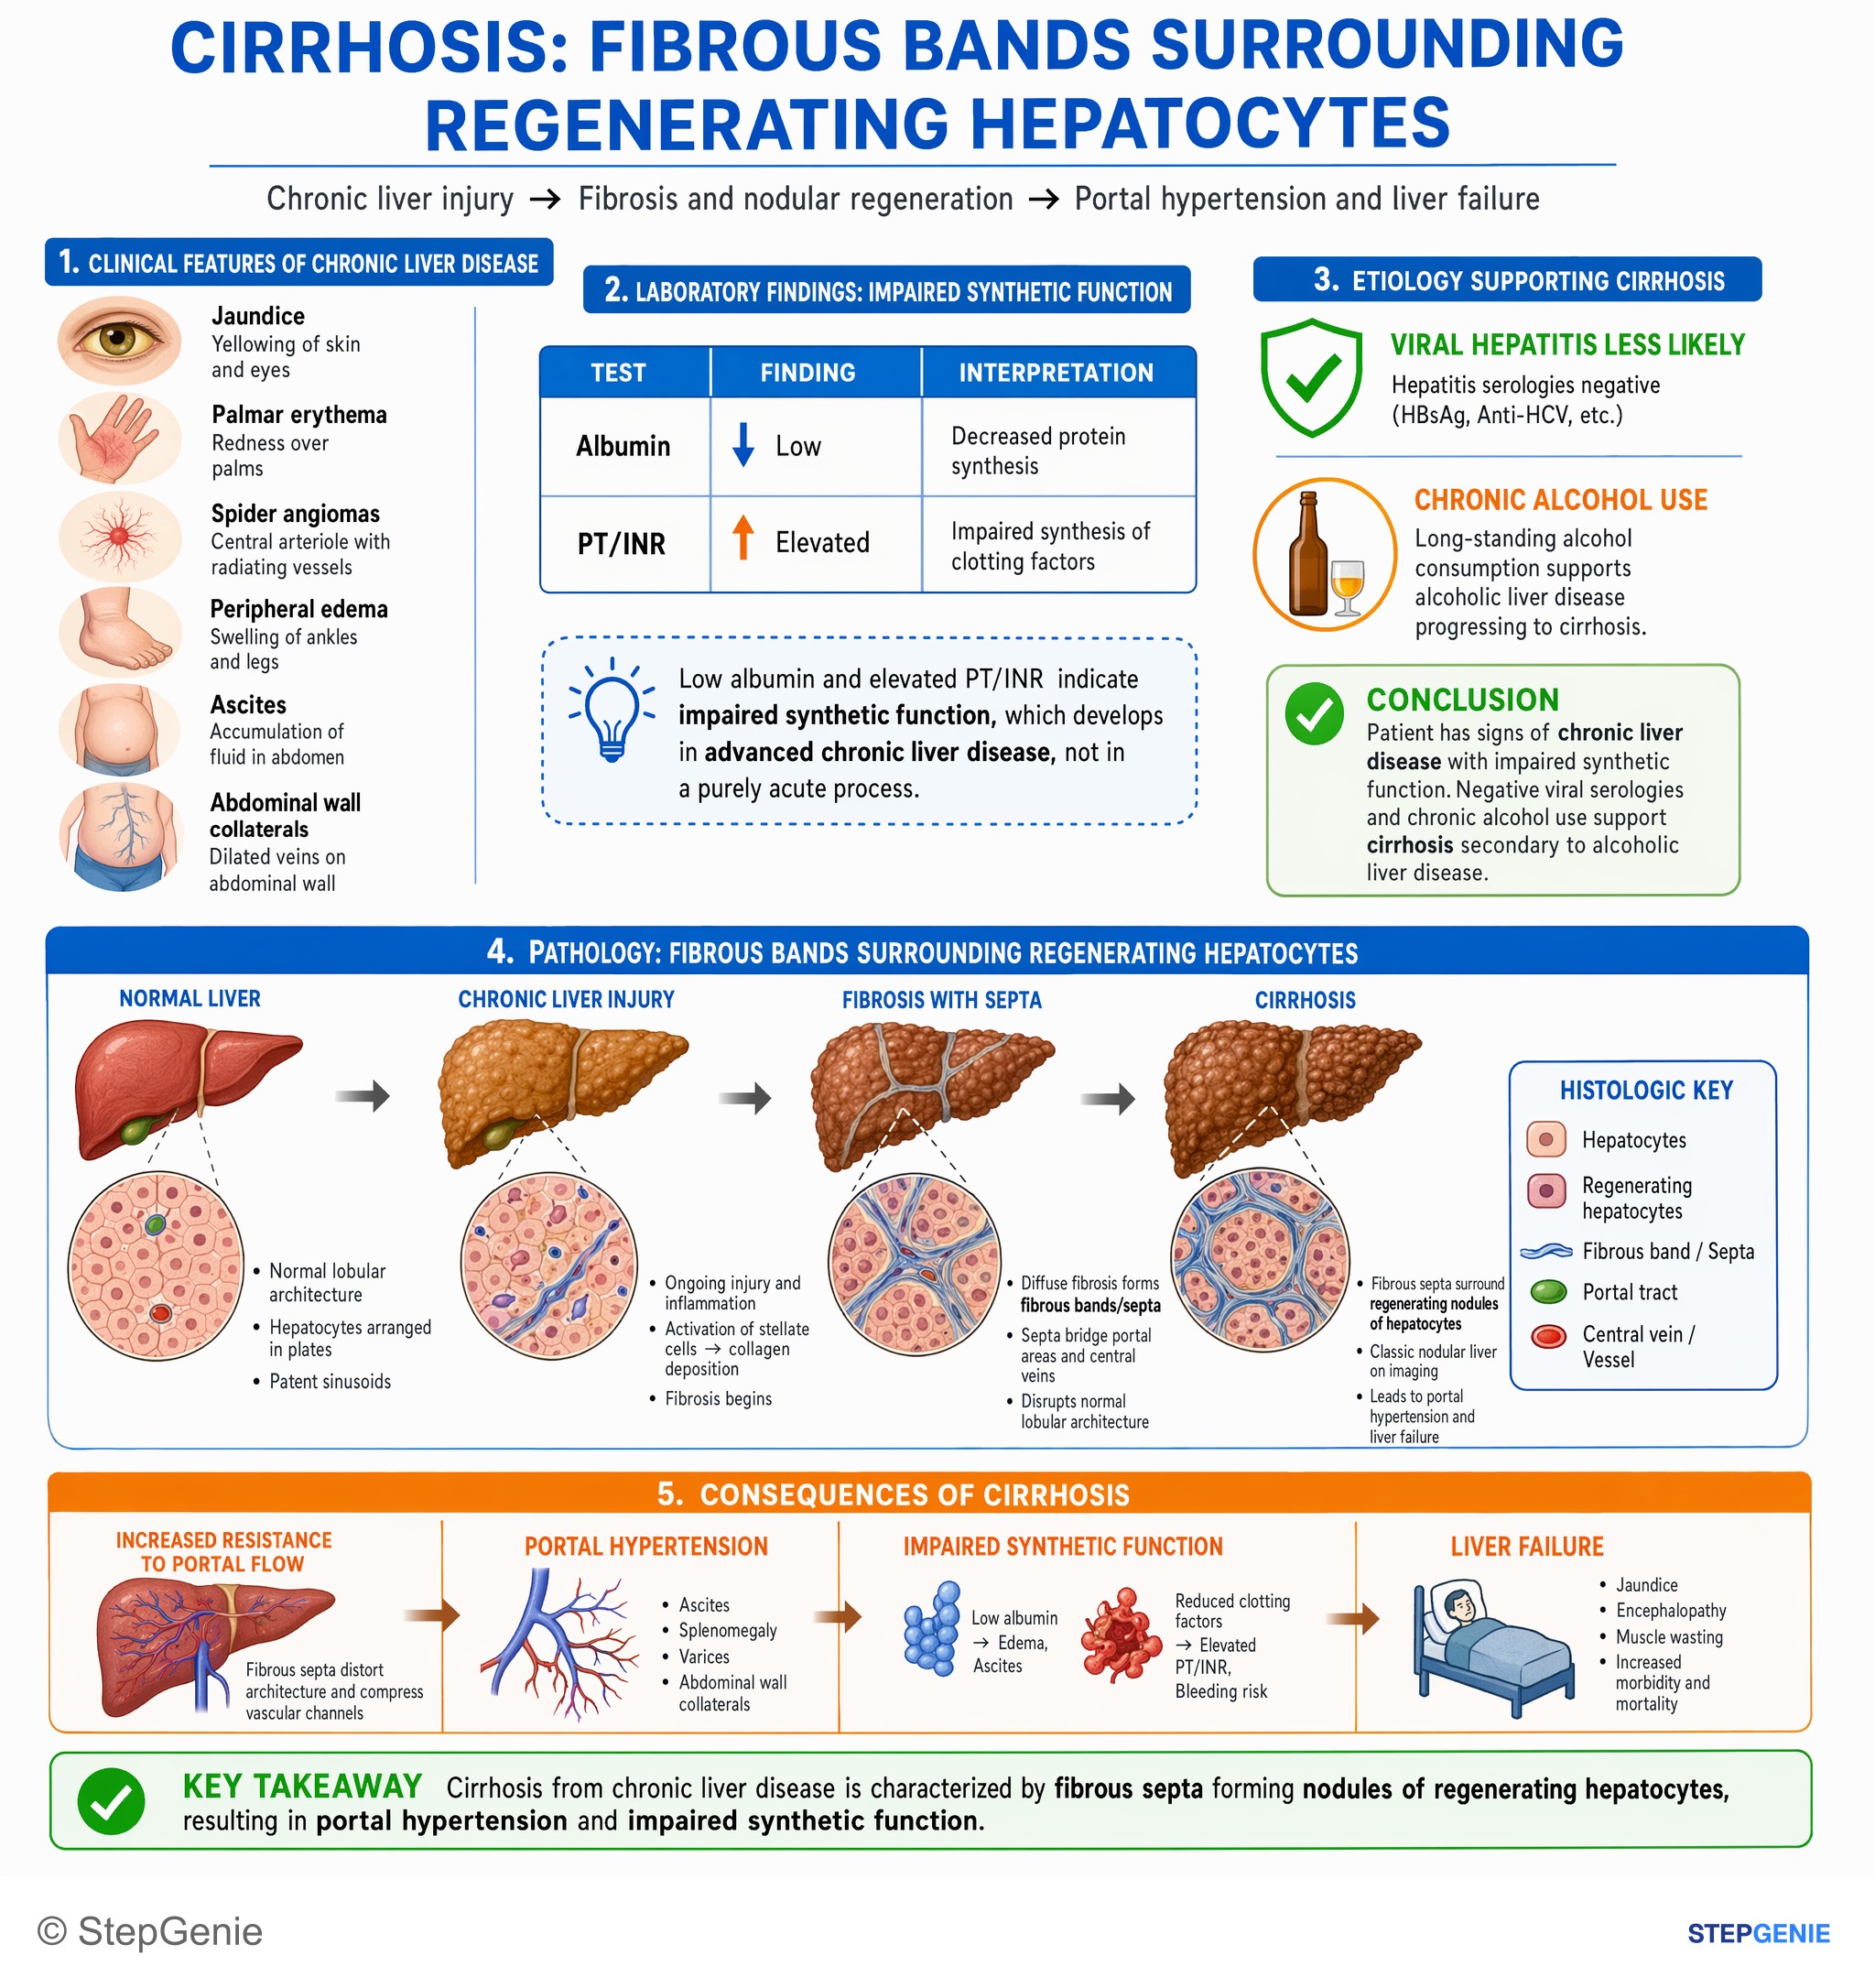
Cirrhosis from chronic liver disease shows fibrous septa forming nodules of regenerating hepatocytes, causing portal hypertension and…
USMLE Step 1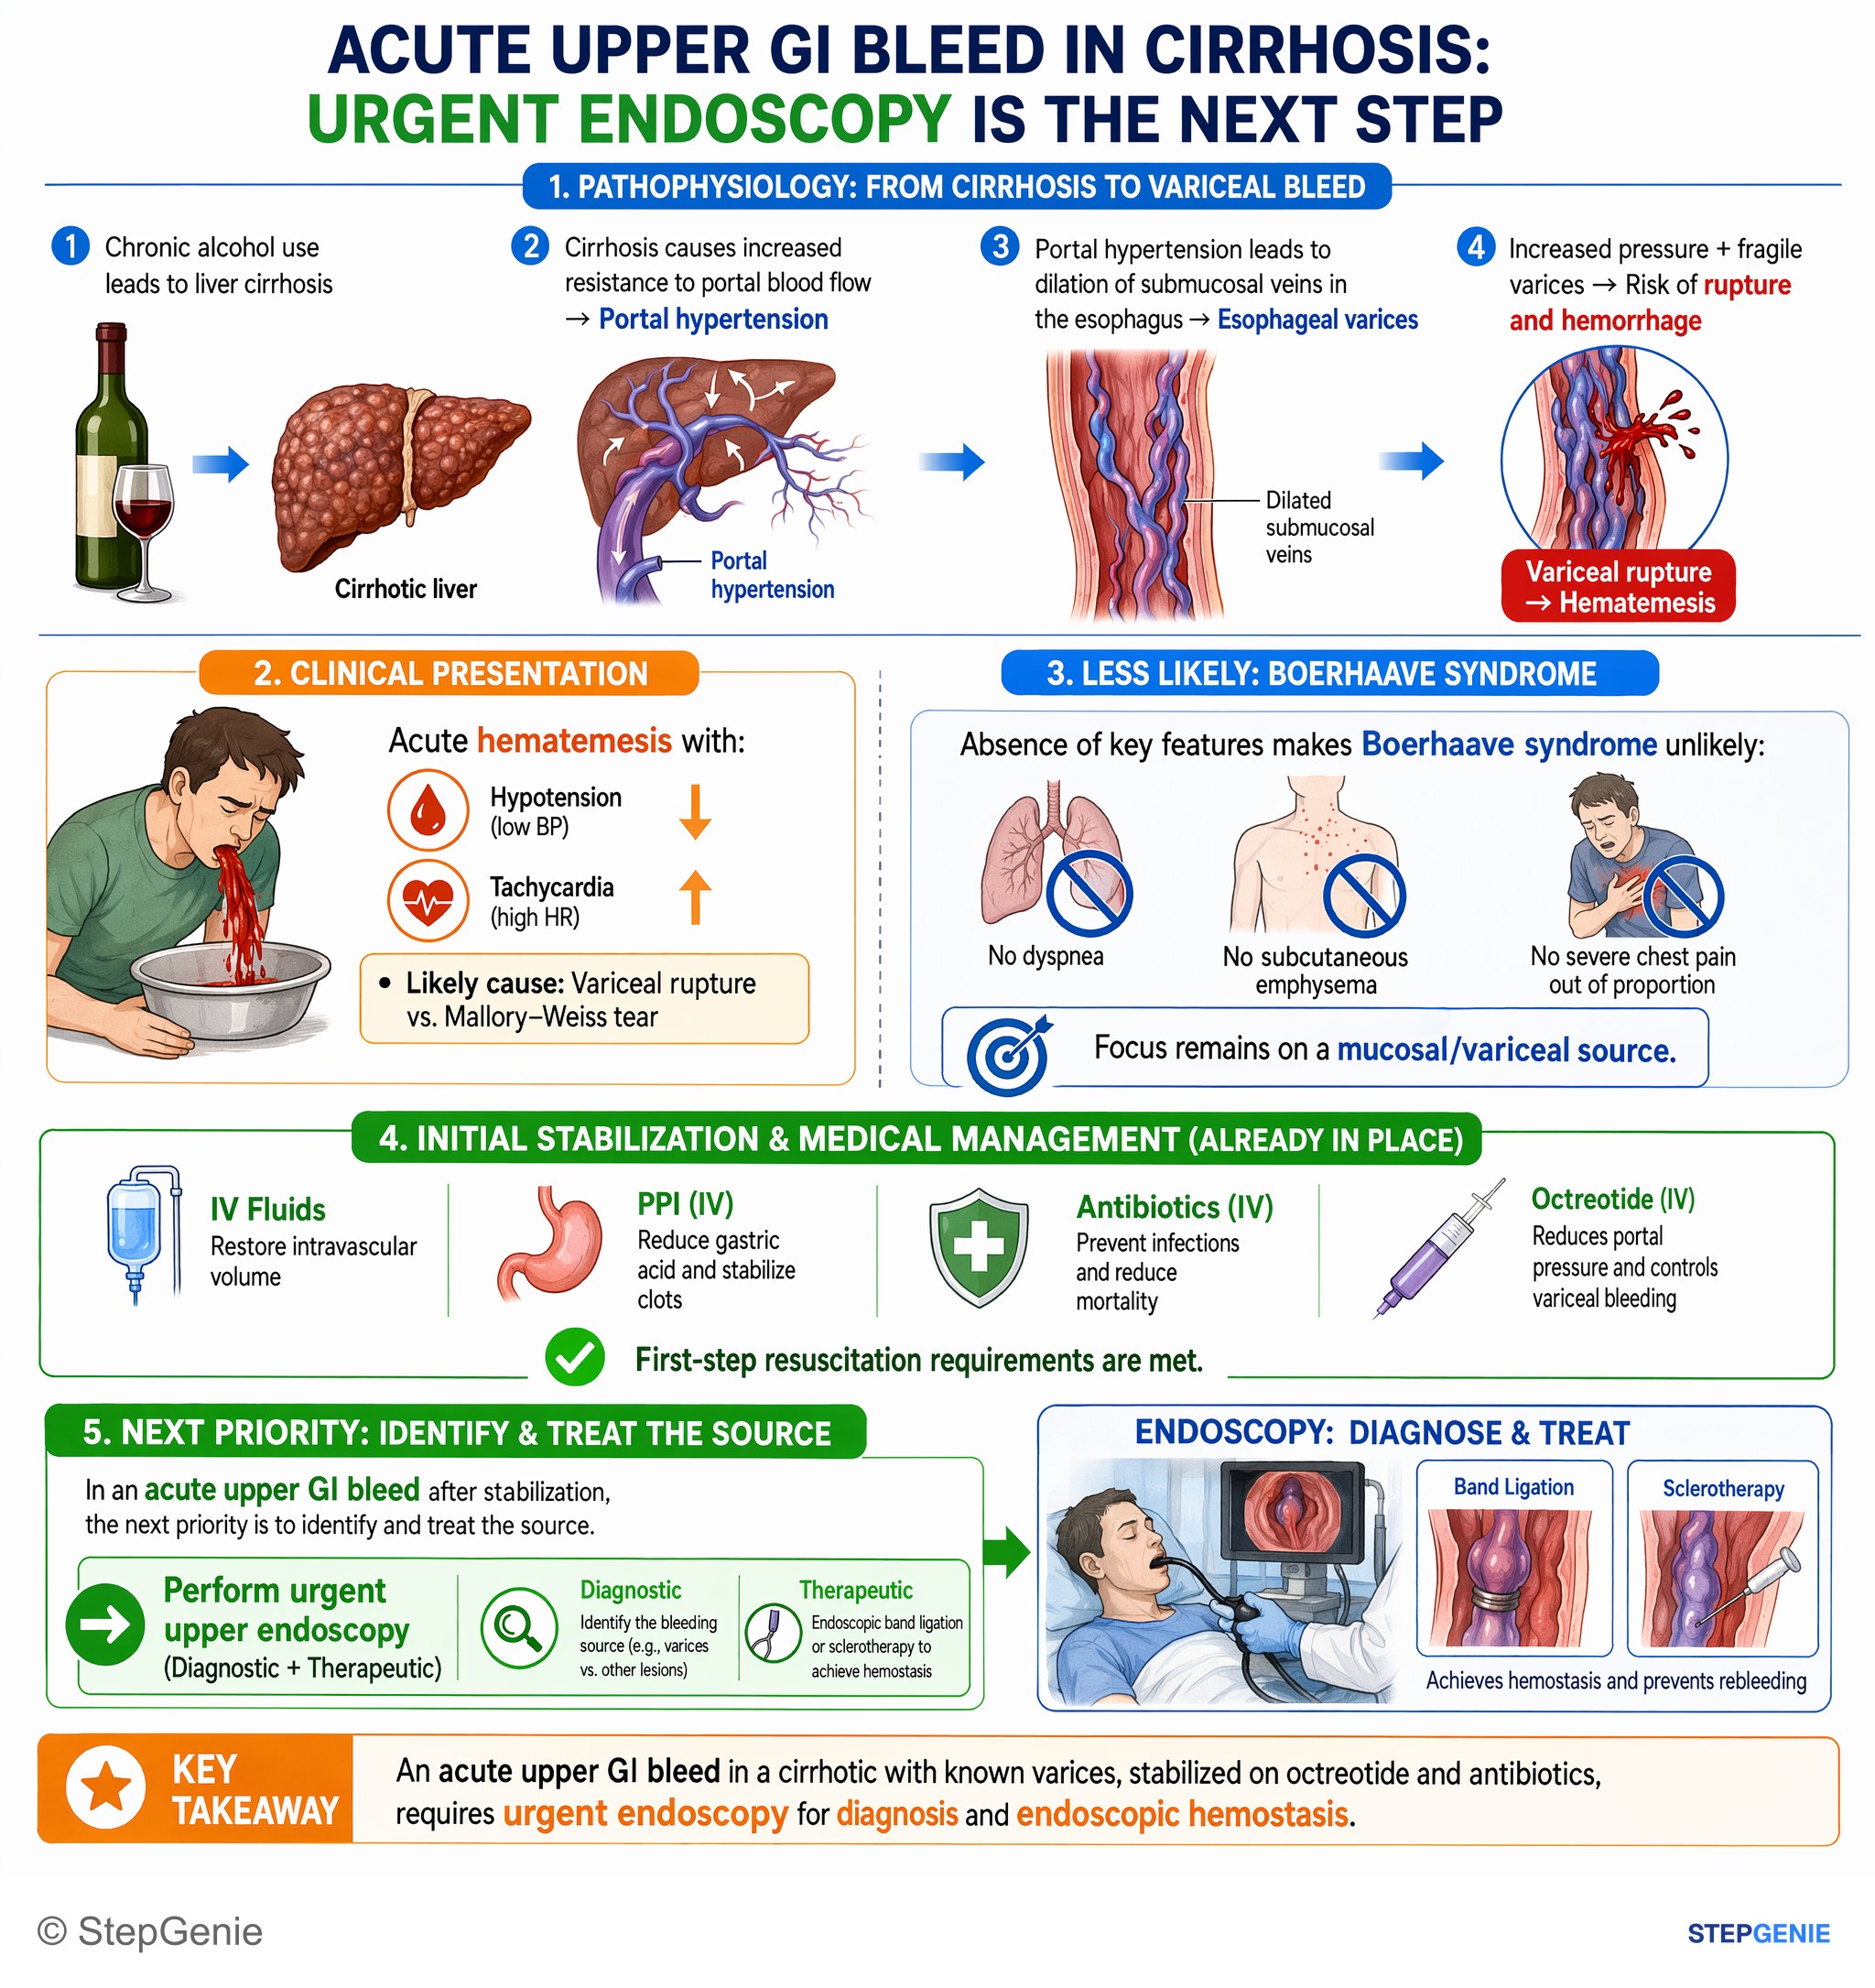
Acute upper GI bleed in a cirrhotic with varices stabilized on octreotide/ABX requires urgent endoscopy for diagnosis and endoscopic…
USMLE Step 2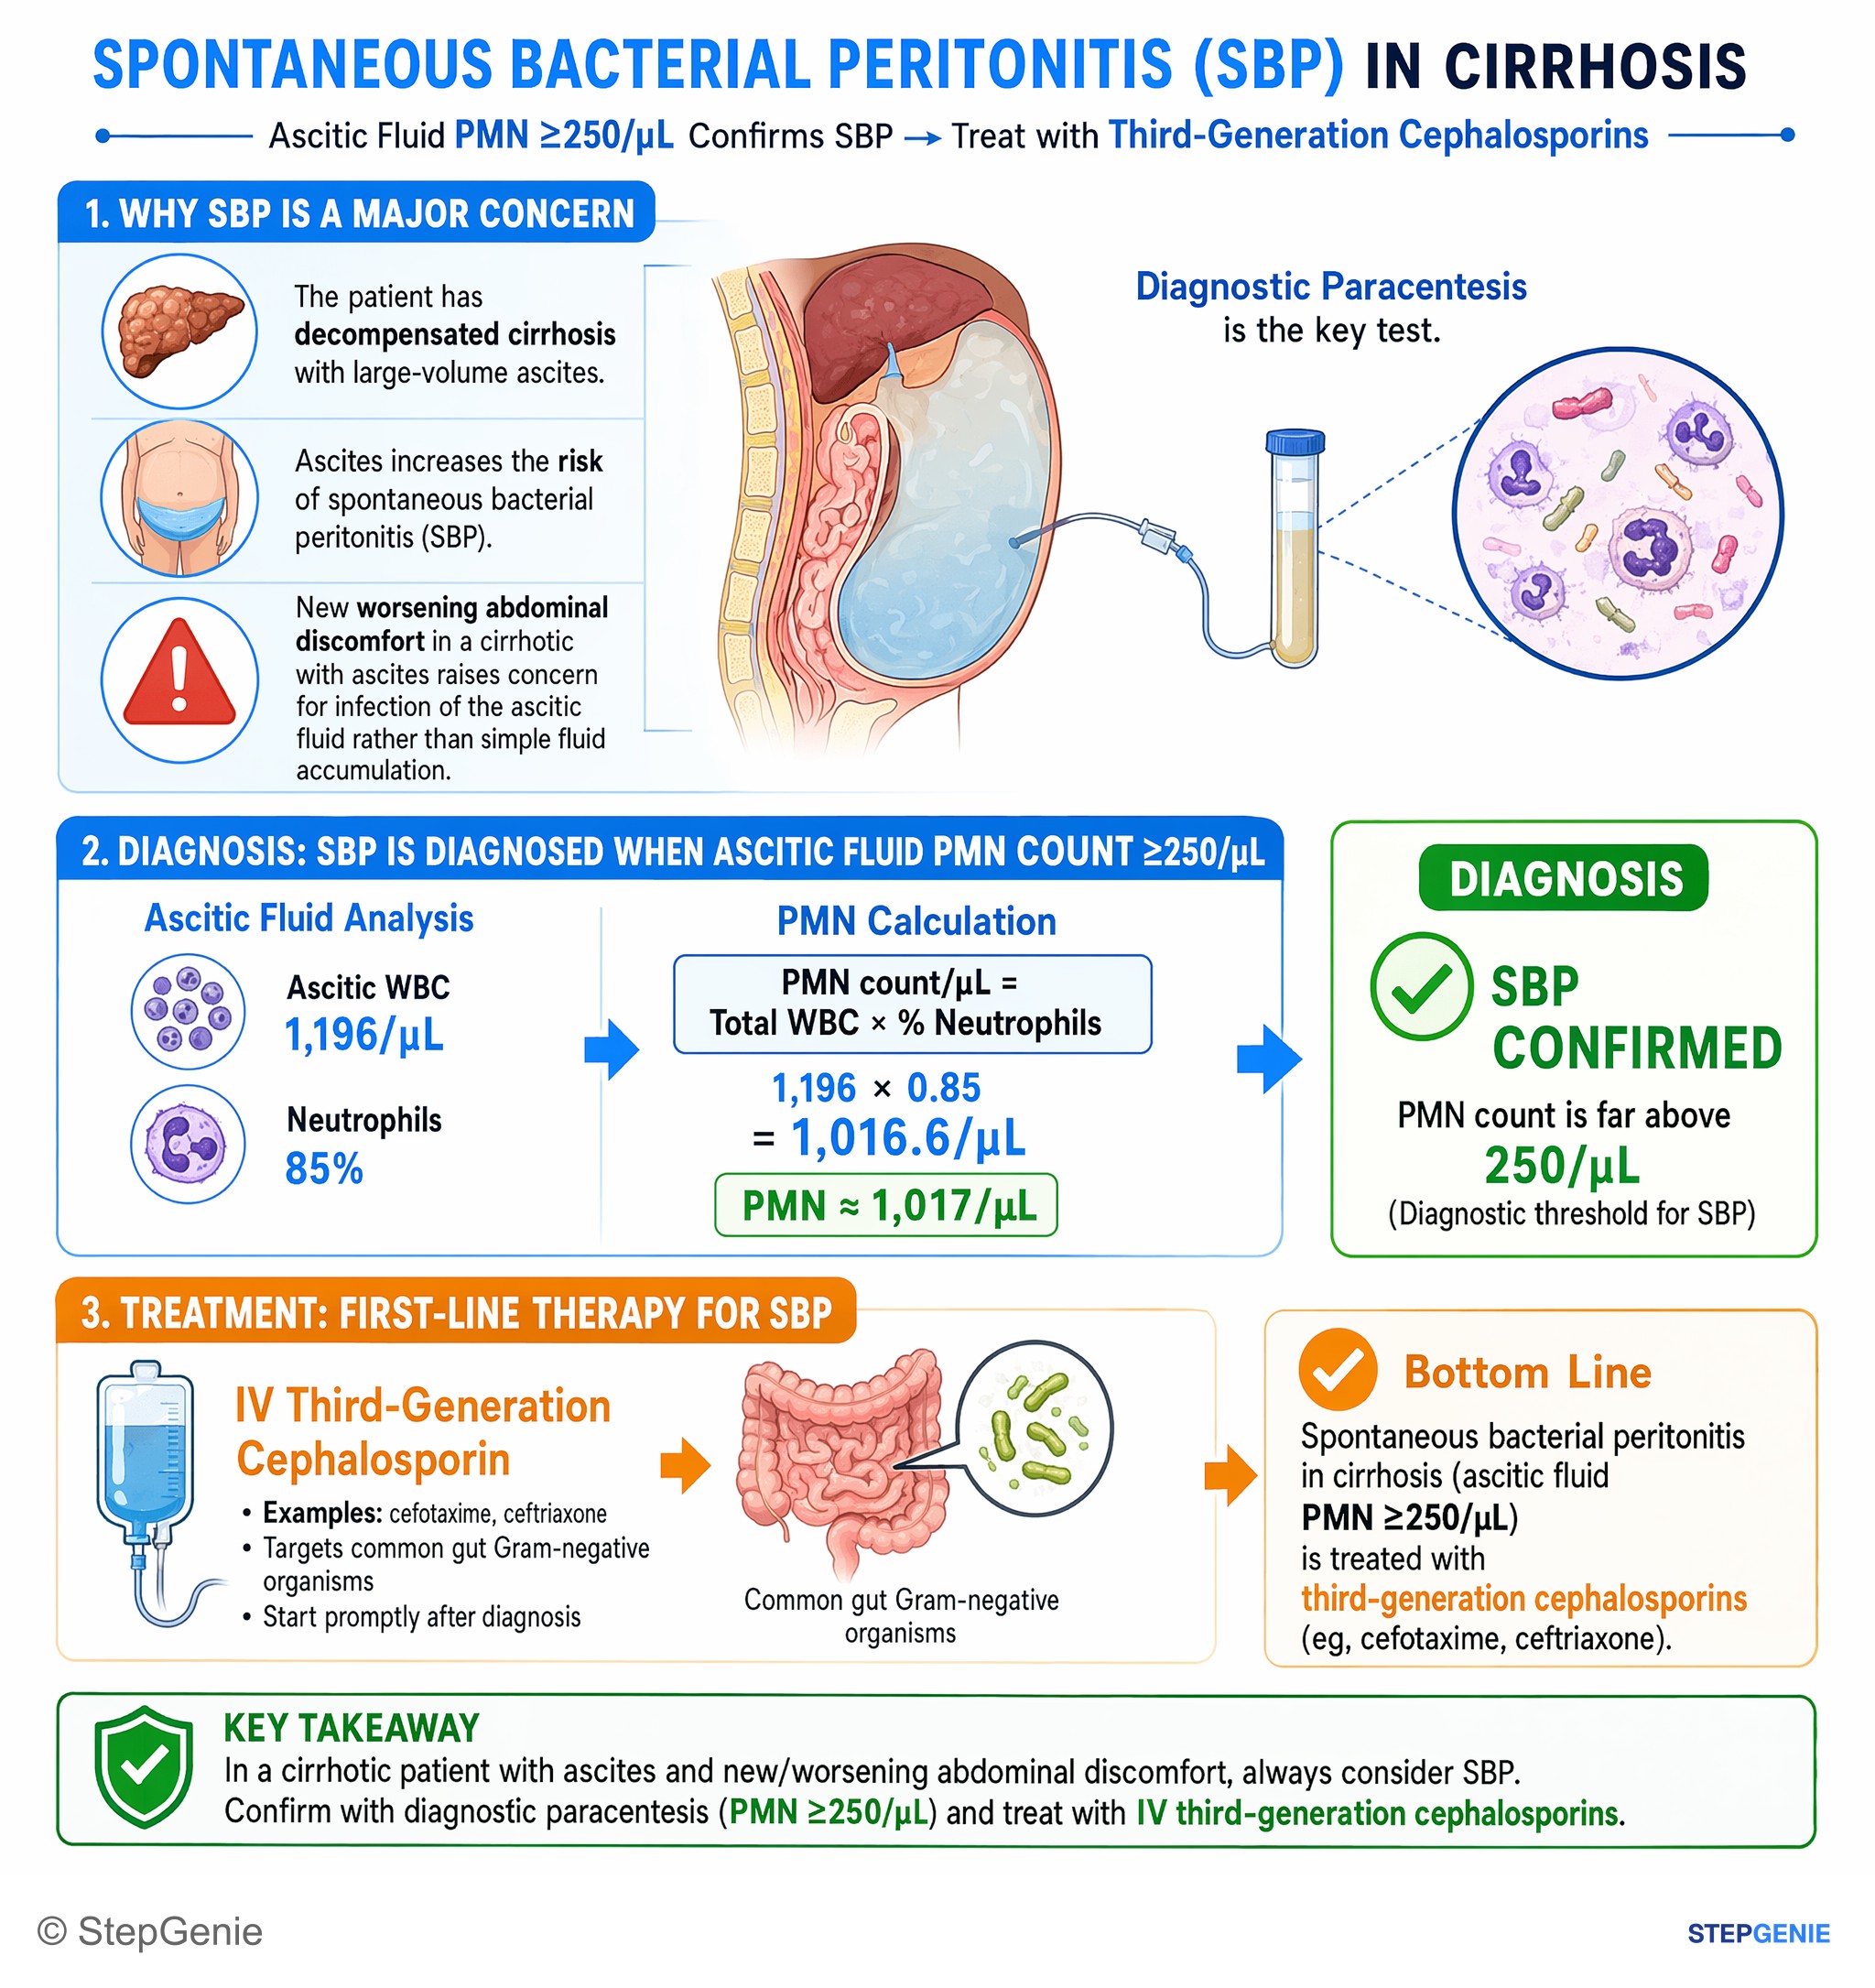
Spontaneous bacterial peritonitis in cirrhosis (ascitic fluid PMN ≥250/µL) is treated with third-generation cephalosporins (eg…
USMLE Step 2Frequently Asked Questions
How does cirrhosis cause portal hypertension?
Activated hepatic stellate cells lay down collagen, and fibrous septa plus regenerating nodules compress the sinusoids and hepatic venules, raising fixed resistance to portal flow. Less nitric oxide and more endothelin inside the liver add a dynamic component, about 30% of the rise in resistance. At the same time, nitric oxide-driven splanchnic vasodilation increases portal inflow, so pressure climbs further. The result is collaterals such as varices, ascites, splenomegaly and encephalopathy.
What HVPG defines clinically significant portal hypertension?
The hepatic venous pressure gradient (wedged minus free hepatic vein pressure) is normally 1 to 5 mm Hg. Above 5 mm Hg is portal hypertension, and 10 mm Hg or more is clinically significant portal hypertension (CSPH), the point at which varices and decompensation can develop. Variceal bleeding almost never occurs below 12 mm Hg. In practice, CSPH is usually shown noninvasively: varices on endoscopy, collaterals on imaging, or high liver stiffness on elastography (25 kPa or more on its own, or lower readings combined with a low platelet count).
Why is carvedilol preferred for portal hypertension?
Nonselective beta-blockers lower portal pressure because beta-1 blockade reduces cardiac output and beta-2 blockade leaves splanchnic alpha tone unopposed, constricting splanchnic arterioles. Carvedilol also blocks alpha-1 receptors and releases nitric oxide, dilating the liver's own vessels, so it lowers HVPG more than propranolol or nadolol. AASLD 2024 and Baveno VIII recommend it for compensated cirrhosis with CSPH to prevent decompensation. Beta-1 selective drugs like metoprolol do not work this way.
What is the treatment of an acute variceal bleed in cirrhosis?
Start a vasoactive drug such as octreotide and IV antibiotics, usually ceftriaxone, at presentation. Transfuse to a hemoglobin of about 7 g/dL, because liberal transfusion raises portal pressure, and do not give plasma just to correct the INR. Perform endoscopy with band ligation within 12 hours. High-risk patients (Child-Pugh C 10 to 13, or Child-Pugh B above 7 with active bleeding) should get a pre-emptive TIPS within 72 hours, ideally 24. Afterwards, combine a beta-blocker with banding.
How is spontaneous bacterial peritonitis diagnosed and treated?
Spontaneous bacterial peritonitis is infection of ascitic fluid without an apparent source. Diagnose it with paracentesis: an ascitic neutrophil count above 250 cells per microliter. Typical organisms are E. coli and Klebsiella, and less often gram-positive cocci. Treat with IV ceftriaxone or cefotaxime for at least 5 days, plus IV albumin 1.5 g/kg on day 1 and 1 g/kg on day 3 to prevent hepatorenal syndrome. After a first episode, long-term prophylaxis with an oral quinolone is usual.
What is hepatorenal syndrome and how is it treated?
Hepatorenal syndrome is functional kidney failure in advanced cirrhosis with ascites: splanchnic vasodilation lowers effective arterial volume and the kidneys clamp down, so urine sodium is very low and the sediment is bland. It is diagnosed when creatinine rises and fails to improve after 2 days of stopping diuretics and giving albumin, with no shock, nephrotoxins or structural kidney disease. Treatment is terlipressin plus albumin, or norepinephrine plus albumin; liver transplant is definitive.