Cholecystitis questions love to bait you with “RUQ pain after a fatty meal” and then make you decide: is this acute inflammation (a “sick gallbladder”) or chronic scarring (a “worn-out gallbladder”)? Here are 3 quick, test-ready tips to separate acute vs chronic cholecystitis—plus a simple visual mnemonic you can recall under pressure.
Tip #1: Think Inflamed vs Fibrosed
Acute cholecystitis = obstructed + inflamed
One-liner: Gallstone blocks the cystic duct → gallbladder distention + inflammation (often bacterial superinfection).
High-yield clues:
- Constant RUQ pain (not just colicky)
- Fever, leukocytosis
- Murphy sign: inspiratory arrest with RUQ palpation
- Most common cause: gallstone in cystic duct
Chronic cholecystitis = repeated injury + scarring
One-liner: Repeated bouts of inflammation → thick, fibrotic gallbladder with impaired contraction.
High-yield clues:
- Recurrent postprandial RUQ discomfort, food intolerance, bloating
- Usually no fever, no marked leukocytosis
- Due to long-standing gallstones causing recurrent irritation
Tip #2: Know the Imaging “Go-To” (and what it means)
Best initial test when you suspect cholecystitis: RUQ ultrasound
Look for:
- Gallstones (echogenic with shadowing)
- Gallbladder wall thickening
- Pericholecystic fluid
- Sonographic Murphy sign
If ultrasound is equivocal but suspicion stays high: HIDA scan
- Acute cholecystitis: nonvisualization of gallbladder (cystic duct obstruction → tracer can’t enter)
- Chronic cholecystitis: gallbladder may fill but can show low ejection fraction (poor contraction), depending on protocol
USMLE pearl:
- Obstruction of the common bile duct → think choledocholithiasis (and potentially ascending cholangitis), not isolated cholecystitis.
Tip #3: Treat Acute Early—Chronic Electively
Acute cholecystitis management (board-style)
Core steps:
- NPO + IV fluids
- Pain control
- Antibiotics (cover gut flora; especially if moderate/severe or systemic signs)
- Early laparoscopic cholecystectomy (often within 72 hours if stable)
When surgery isn’t possible (critically ill):
- Percutaneous cholecystostomy as a temporizing measure
Chronic cholecystitis management
- Elective laparoscopic cholecystectomy for symptomatic disease
- No emergent antibiotics unless there’s acute infection
Quick Visual/Mnemonic Device: “A.C.U.T.E. vs C.H.R.O.N.I.C.”
Use this as a rapid mental split-screen.
| Feature | A.C.U.T.E. (Acute) | C.H.R.O.N.I.C. (Chronic) |
|---|---|---|
| Meaning | A = Abrupt obstruction + inflammation | C = Constant wear-and-tear |
| Pain | C = Constant RUQ pain | H = Habitual postprandial discomfort |
| Vitals/Labs | U = Up temp, WBC up | R = Regular vitals, labs often normal |
| Exam | T = Tender + Murphy | O = Often no Murphy |
| Imaging | E = Empty gallbladder on HIDA (nonvisualized) | N = Narrowed/fibrotic, poor contraction |
| Path | — | I = Injury repeated → fibrosis + thick wall |
| C = Cholelithiasis usually present |
(Don’t memorize every letter—use it to trigger the big idea: acute = inflamed/infected; chronic = scarred/dysfunctional.)
High-Yield Differentials (Common USMLE Traps)
Biliary colic (NOT cholecystitis)
- Intermittent RUQ pain after fatty meals
- No fever, no leukocytosis
- Pain resolves as stone dislodges (transient cystic duct obstruction)
Ascending cholangitis (Charcot triad)
- Fever + jaundice + RUQ pain
- Think CBD obstruction + infection
- Can progress to Reynolds pentad (add hypotension + altered mental status) → emergent drainage
Gallstone pancreatitis
- Epigastric pain radiating to back, elevated lipase
- Due to transient obstruction near the ampulla of Vater
Rapid-Fire USMLE Facts to Lock In
- Murphy sign points to acute cholecystitis (irritated gallbladder).
- HIDA nonvisualization = cystic duct obstruction → acute cholecystitis.
- Chronic cholecystitis is a fibrosis/atrophy story: repeated inflammation → thick, shrunken gallbladder.
- Complication buzzwords:
- Empyema, gangrenous cholecystitis, perforation (acute complications)
- Porcelain gallbladder (calcified wall; associated with chronic inflammation; classic boards association with gallbladder carcinoma risk—management often cholecystectomy)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
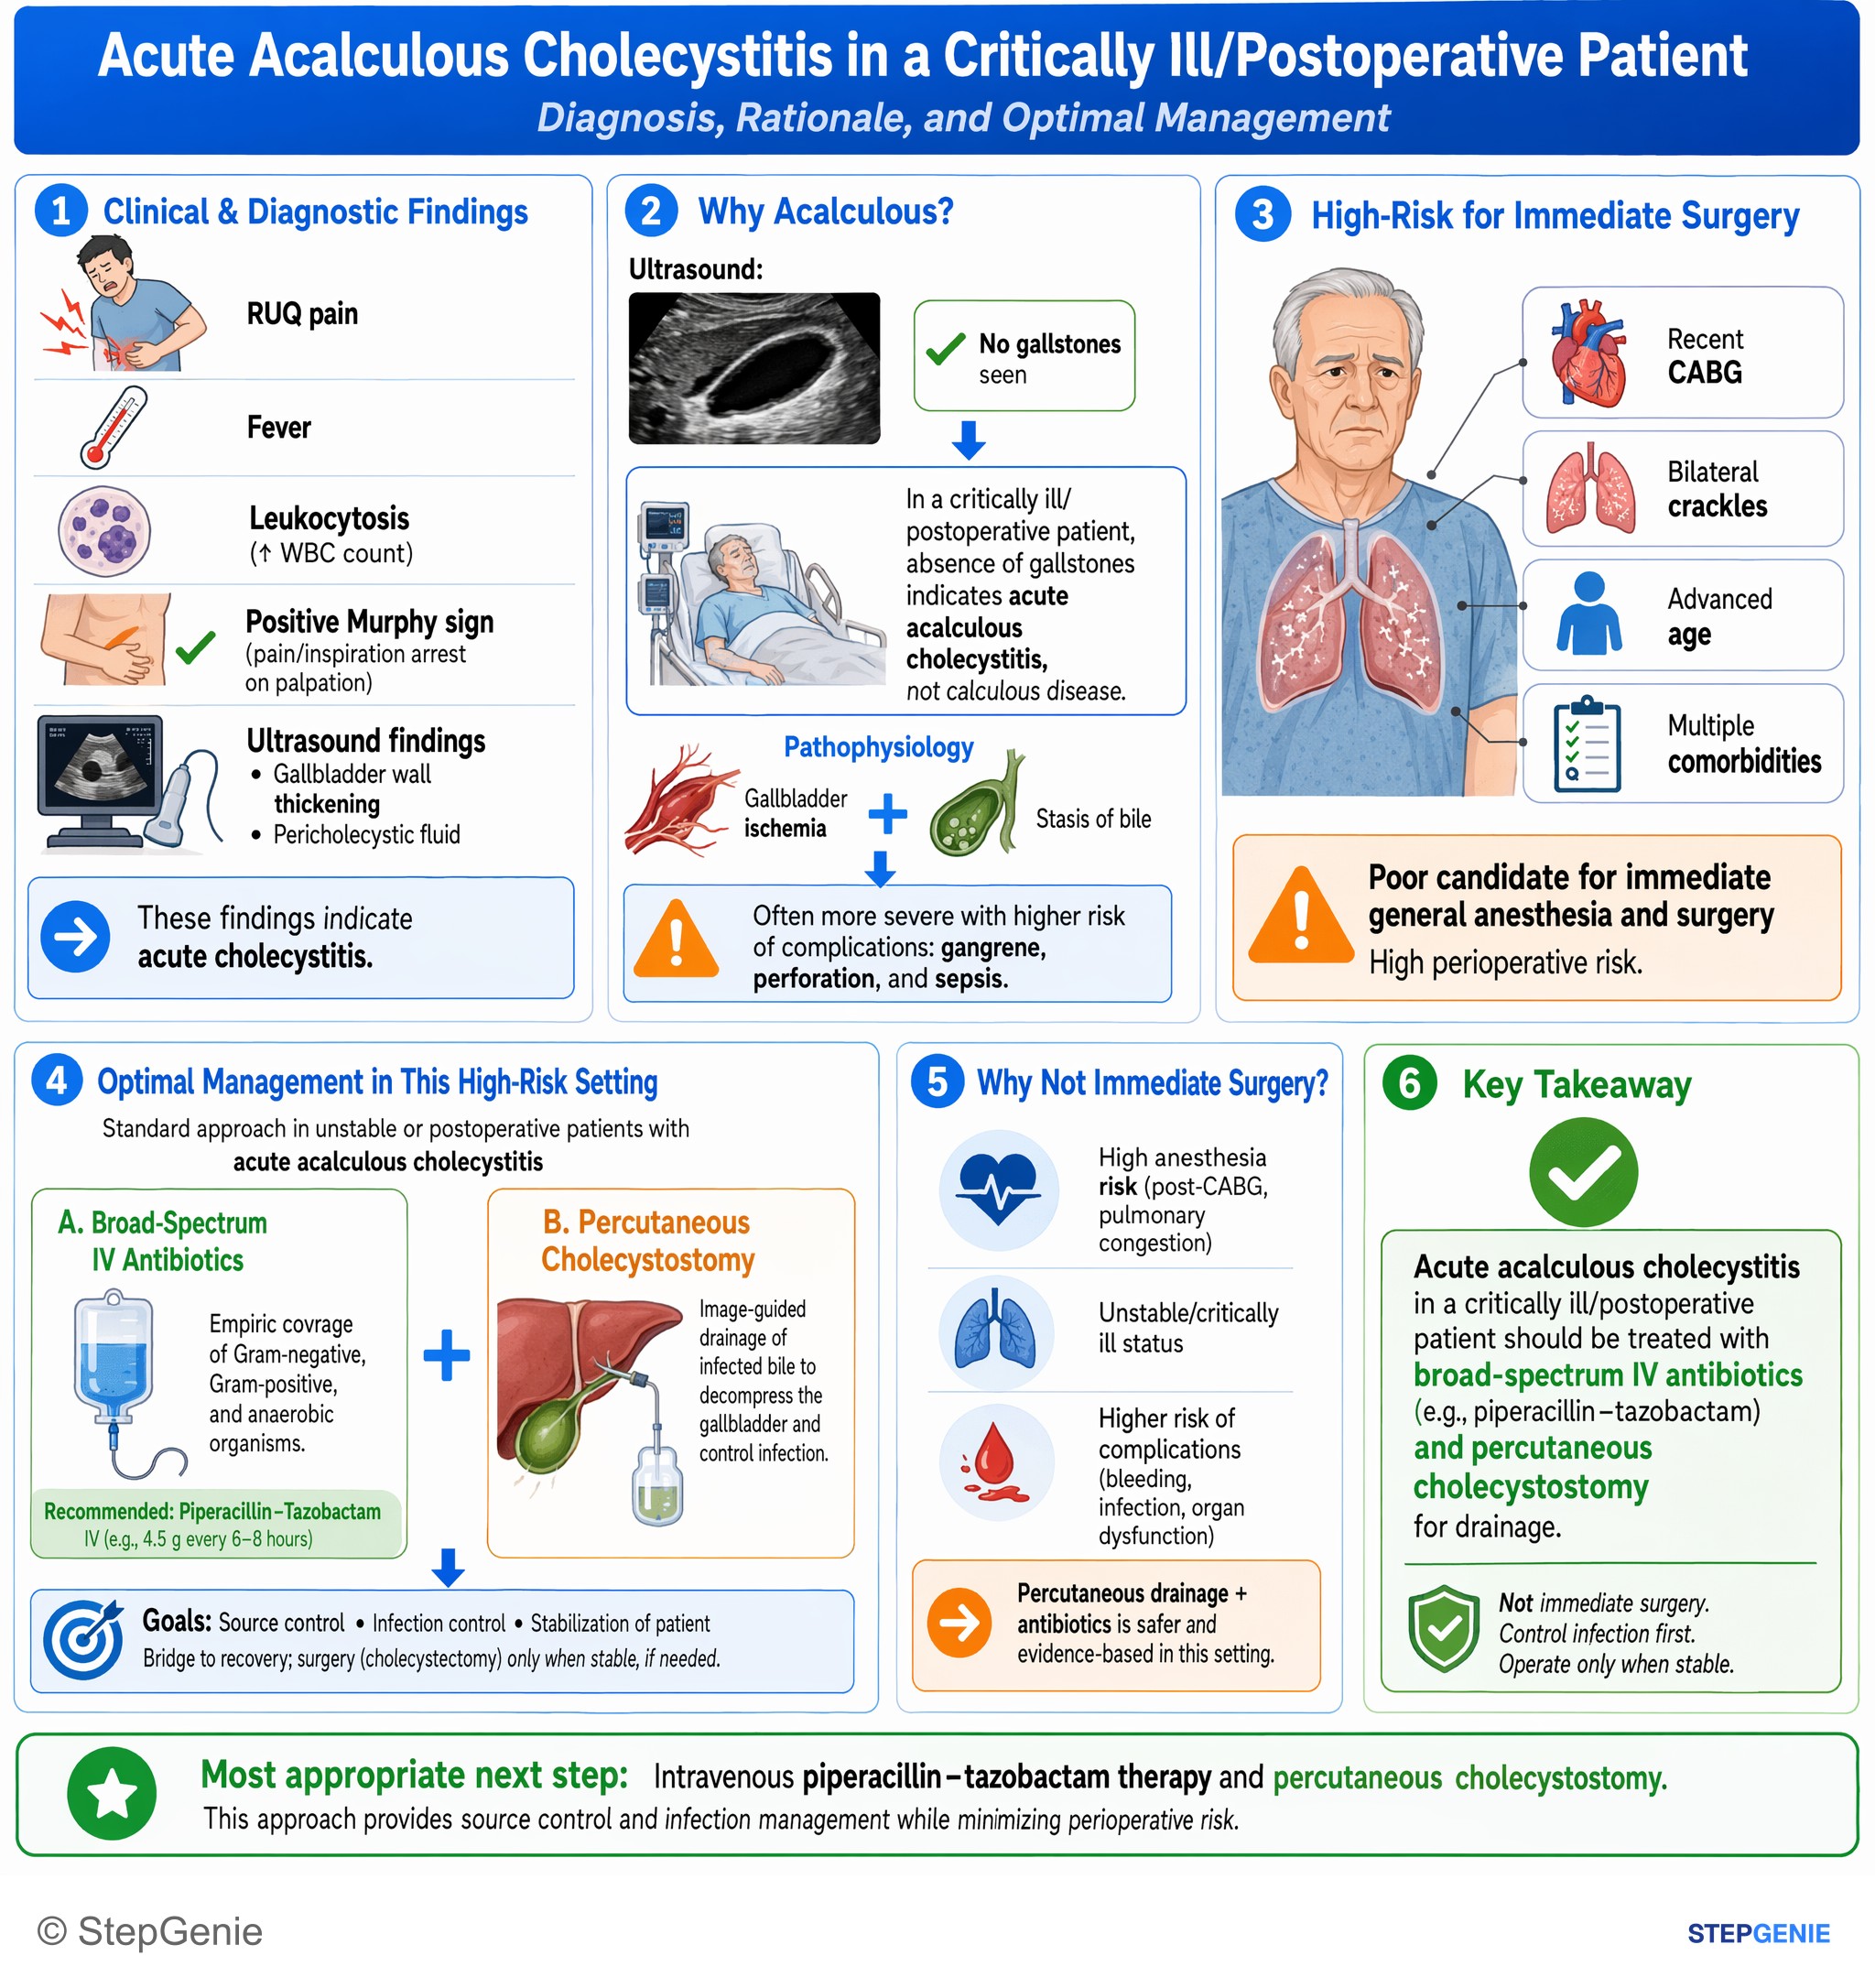
Acute acalculous cholecystitis in a critically ill/postoperative patient → treat with broad-spectrum IV antibiotics and percutaneous…
USMLE Step 2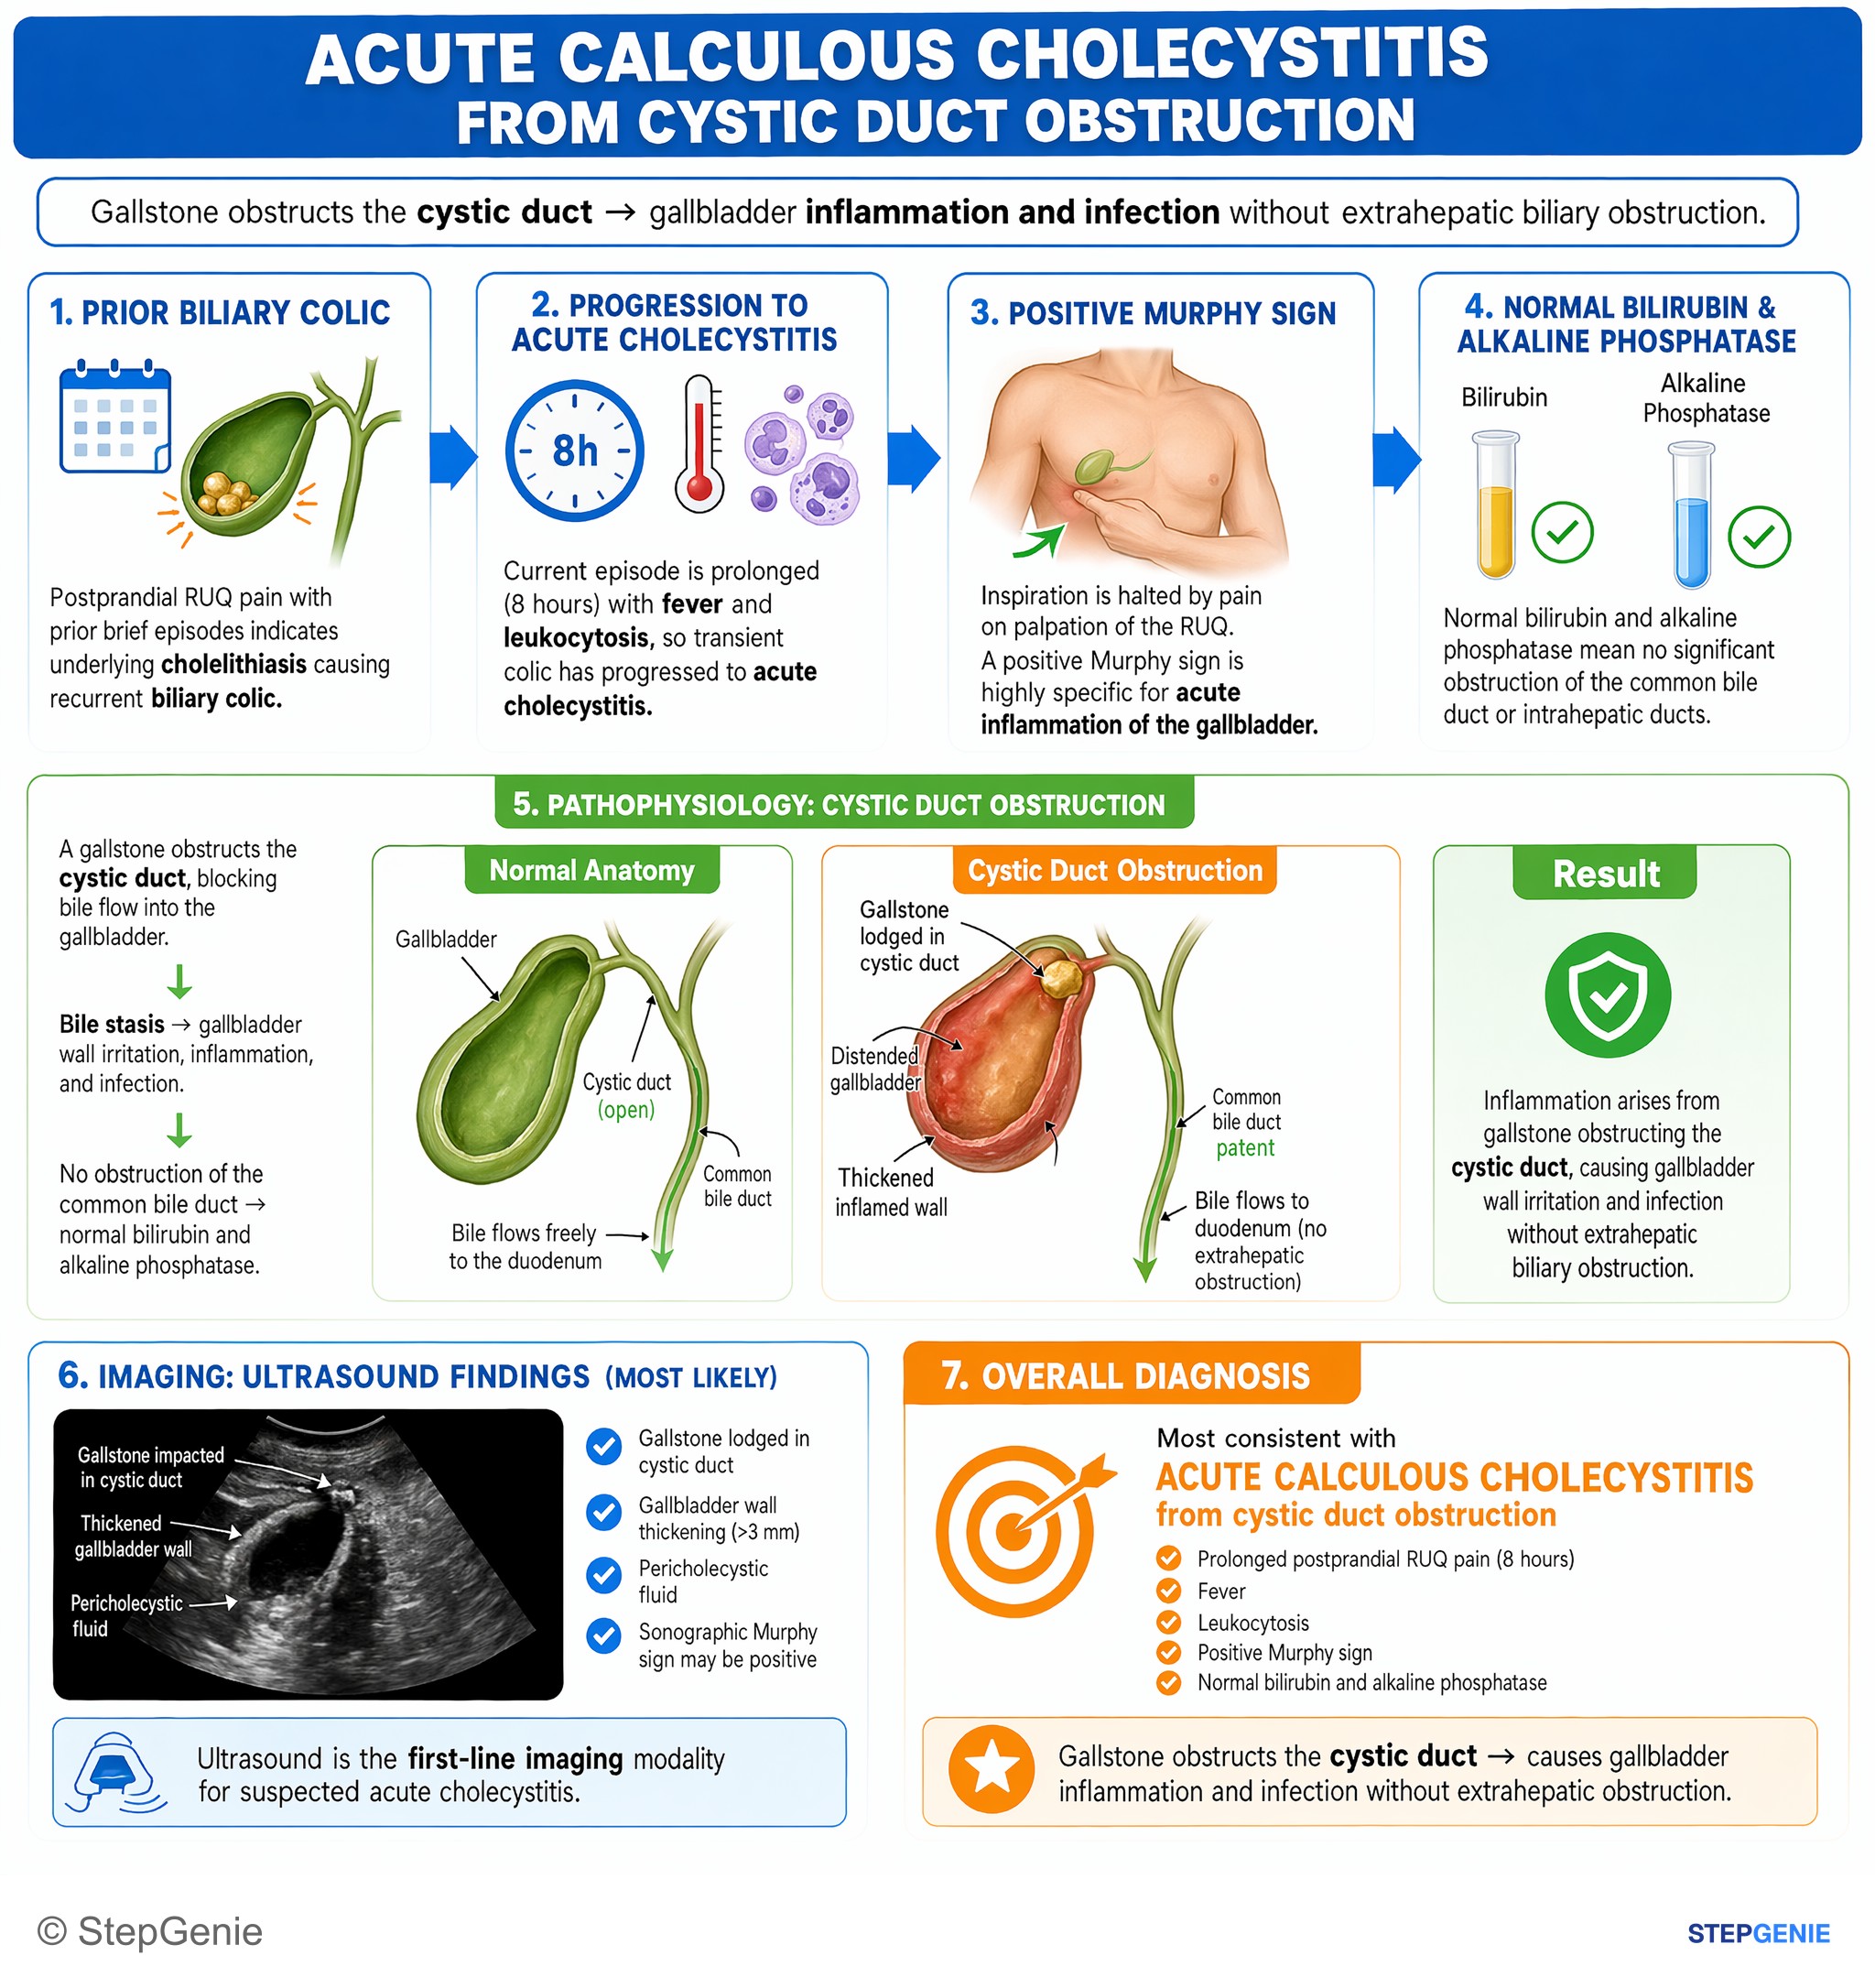
Acute calculous cholecystitis from cystic duct obstruction: prolonged postprandial RUQ pain, fever, leukocytosis, positive Murphy sign…
USMLE Step 2
Acute cholecystitis from cholesterol gallstones due to female sex, obesity, multiparity, and RUQ pain with positive Murphy sign and mild…
USMLE Step 2Frequently Asked Questions
How do you tell acute cholecystitis from chronic cholecystitis on a question stem?
Acute cholecystitis usually presents with constant RUQ pain plus inflammatory signs, while chronic cholecystitis causes recurrent postprandial RUQ discomfort without systemic illness. Acute disease is tied to cystic duct obstruction with gallbladder inflammation, so fever, leukocytosis, and a positive Murphy sign are high-yield clues. Chronic disease reflects repeated injury and fibrosis, so patients often have food intolerance and bloating but usually no fever or marked leukocytosis.
What is the best initial imaging test for suspected cholecystitis?
The best initial imaging test for suspected cholecystitis is a RUQ ultrasound. It can show gallstones, gallbladder wall thickening, pericholecystic fluid, and a sonographic Murphy sign. If the ultrasound is equivocal but clinical suspicion remains high, the next study is a HIDA scan to assess whether the gallbladder fills normally or whether cystic duct obstruction is preventing tracer entry.
What does nonvisualization of the gallbladder on HIDA scan mean?
Nonvisualization of the gallbladder on HIDA scan points to acute cholecystitis caused by cystic duct obstruction. The tracer cannot enter the gallbladder when the cystic duct is blocked, so the gallbladder does not appear on the study. In chronic cholecystitis, the gallbladder may still fill, but it can show poor contraction and a low ejection fraction depending on the protocol used.
What is the first-line treatment for acute cholecystitis?
Initial treatment for acute cholecystitis includes NPO status, IV fluids, pain control, antibiotics when indicated, and early laparoscopic cholecystectomy if the patient is stable. This approach addresses both the inflammation and the underlying gallbladder problem. If a patient is too ill for surgery, percutaneous cholecystostomy can be used as a temporizing measure until more definitive management is possible.
How do you distinguish biliary colic from acute cholecystitis?
Biliary colic causes intermittent RUQ pain after fatty meals without fever or leukocytosis, whereas acute cholecystitis causes constant RUQ pain with inflammatory findings. In biliary colic, the pain resolves when the stone dislodges after transient cystic duct obstruction. Acute cholecystitis reflects ongoing obstruction and inflammation, so patients are more likely to have fever, elevated white blood cells, and a positive Murphy sign.