You’re in the middle of a GI block, you see “hematemesis,” and your brain immediately starts sprinting through varices, ulcers, and tears. Mallory–Weiss tears are classic Step material because the diagnosis is pattern recognition—but the points come from ruling out the tempting distractors. Let’s break down a typical Q-bank vignette and make every answer choice teach you something.
The Vignette (Classic Q-bank Style)
A 28-year-old man comes to the ED after several episodes of vomiting following heavy alcohol intake. He now has one episode of bright red hematemesis. He is hemodynamically stable. Physical exam shows mild epigastric tenderness. No stigmata of chronic liver disease. Labs are unremarkable.
Most likely diagnosis?
A. Boerhaave syndrome
B. Esophageal varices
C. Mallory–Weiss tear
D. Peptic ulcer disease
E. Acute erosive (hemorrhagic) gastritis
Correct Answer: Mallory–Weiss Tear
Why it fits
Mallory–Weiss tear = mucosal laceration at the gastroesophageal junction caused by a sudden rise in intra-abdominal pressure (most commonly repeated retching/vomiting).
High-yield clues:
- Forceful vomiting/retching → then hematemesis
- Often associated with alcohol use disorder, bulimia, hyperemesis gravidarum
- Bleeding is usually self-limited
- Patients are often hemodynamically stable (though brisk bleeding can happen)
Pathophysiology snapshot
- Longitudinal mucosal tears at the GE junction
- Not transmural (that’s the key distinction vs Boerhaave)
Best next steps (what Step wants)
- Initial management: stabilize (ABCs, IV access, fluids if needed)
- Diagnosis: upper endoscopy (EGD) if ongoing bleeding or diagnostic uncertainty
- Treatment:
- Often supportive
- If active bleeding on EGD: endoscopic hemostasis (e.g., clipping, cautery, epinephrine injection)
Why the Other Answer Choices Are Wrong (and What They Would Look Like)
A. Boerhaave Syndrome (Esophageal Rupture) — the dangerous cousin
Core idea: transmural tear of the esophagus after severe vomiting → mediastinitis.
How it would present:
- Severe vomiting followed by sudden, severe chest pain
- Subcutaneous emphysema (crepitus), dyspnea
- Fever, tachycardia, toxic appearance
- Possible left pleural effusion
- Mackler triad (vomiting + chest pain + subcutaneous emphysema) is classic but not always complete
Diagnostic test:
- CT chest or contrast esophagram with water-soluble contrast (Gastrografin first)
Why it’s not this case:
- The vignette screams hematemesis after retching with stability—not chest pain, crepitus, or systemic toxicity.
Step trap to remember:
- Mallory–Weiss = mucosa only
- Boerhaave = full-thickness rupture → mediastinitis → high mortality
B. Esophageal Varices — portal HTN until proven otherwise
Core idea: dilated submucosal veins due to portal hypertension, classically from cirrhosis.
How it would present:
- Massive, painless hematemesis
- Signs of chronic liver disease: jaundice, ascites, spider angiomas, caput medusae
- Often hemodynamically unstable if brisk bleed
Initial management (very testable):
- Resuscitate
- Octreotide (reduces portal pressures)
- Endoscopic band ligation
- Prophylactic antibiotics (e.g., ceftriaxone) in cirrhotics with GI bleed
- Consider TIPS if refractory
Why it’s not this case:
- No cirrhosis clues, not described as massive/painless, and the trigger is classic retching.
D. Peptic Ulcer Disease (PUD) — ulcer bleeding is real, but the setup differs
Core idea: gastric/duodenal mucosal injury, commonly due to H. pylori or NSAIDs.
How it would present:
- Epigastric pain +/- melena or hematemesis
- Risk factors: NSAIDs, H. pylori, smoking
- Bleeding can be significant, but doesn’t require retching as a precipitant
Quick differentiators (Step 1/2):
- Duodenal ulcer: pain improves with meals, nocturnal pain, increased acid
- Gastric ulcer: pain worsens with meals
Why it’s not this case:
- The hallmark here is vomiting → tear → hematemesis, not chronic dyspepsia or NSAID/H. pylori story.
E. Acute Erosive (Hemorrhagic) Gastritis — stress/NSAIDs/EtOH can do it, but the pattern shifts
Core idea: acute inflammation/erosion of gastric mucosa leading to bleeding.
Common triggers:
- NSAIDs
- Alcohol
- Severe physiologic stress (ICU patients: burns = Curling ulcers; CNS injury = Cushing ulcers—often taught alongside “stress-related mucosal disease”)
How it would present:
- Epigastric discomfort, nausea/vomiting
- Hematemesis or coffee-ground emesis possible
- Often in hospitalized/critically ill patients or heavy NSAID users
Why it’s not this case:
- Alcohol is a shared risk factor, but the stem’s signature move is retching preceding hematemesis, pointing more strongly to a mechanical tear than diffuse mucosal oozing.
Mallory–Weiss vs Boerhaave vs Varices (High-Yield Table)
| Feature | Mallory–Weiss tear | Boerhaave syndrome | Esophageal varices |
|---|---|---|---|
| Depth of injury | Mucosal laceration | Transmural rupture | Dilated veins (submucosal) |
| Trigger | Retching/vomiting | Forceful vomiting | Portal HTN/cirrhosis |
| Key symptom | Hematemsis after vomiting | Severe chest pain, toxicity | Massive painless hematemesis |
| Key findings | Usually stable | Crepitus, mediastinitis | Cirrhosis stigmata |
| Diagnosis | EGD (if needed) | CT/contrast esophagram | EGD |
| Treatment | Supportive ± endoscopic hemostasis | Surgical/emergent management + antibiotics | Octreotide + banding + antibiotics |
“Buzzwords” That Should Trigger Mallory–Weiss on Test Day
- “After a night of heavy drinking”
- “Repeated retching”
- “Bright red hematemesis”
- “Stable vitals” (often, not always)
- “Mucosal tear at GE junction”
Rapid-Fire USMLE Pearls
- Upper GI bleed stabilization is always first: 2 large-bore IVs, type & screen/cross, transfuse as needed.
- Mallory–Weiss usually stops bleeding spontaneously, but persistent bleeding → EGD with therapy.
- Boerhaave is a surgical emergency—think mediastinitis and subcutaneous emphysema.
- Variceal bleed management is a common Step 2 algorithm: octreotide + endoscopic banding + prophylactic antibiotics.
Takeaway
Mallory–Weiss isn’t just “vomiting + blood.” It’s a pattern where the sequence matters: retch first, tear second, hematemesis third—and the distractors are all about what else you’d expect (chest pain/toxicity for Boerhaave, cirrhosis clues for varices, chronic dyspepsia/NSAIDs for ulcers, ICU-level stress for erosive gastritis). Train yourself to read answer choices as mini-lessons, and your GI questions start feeling way more predictable.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
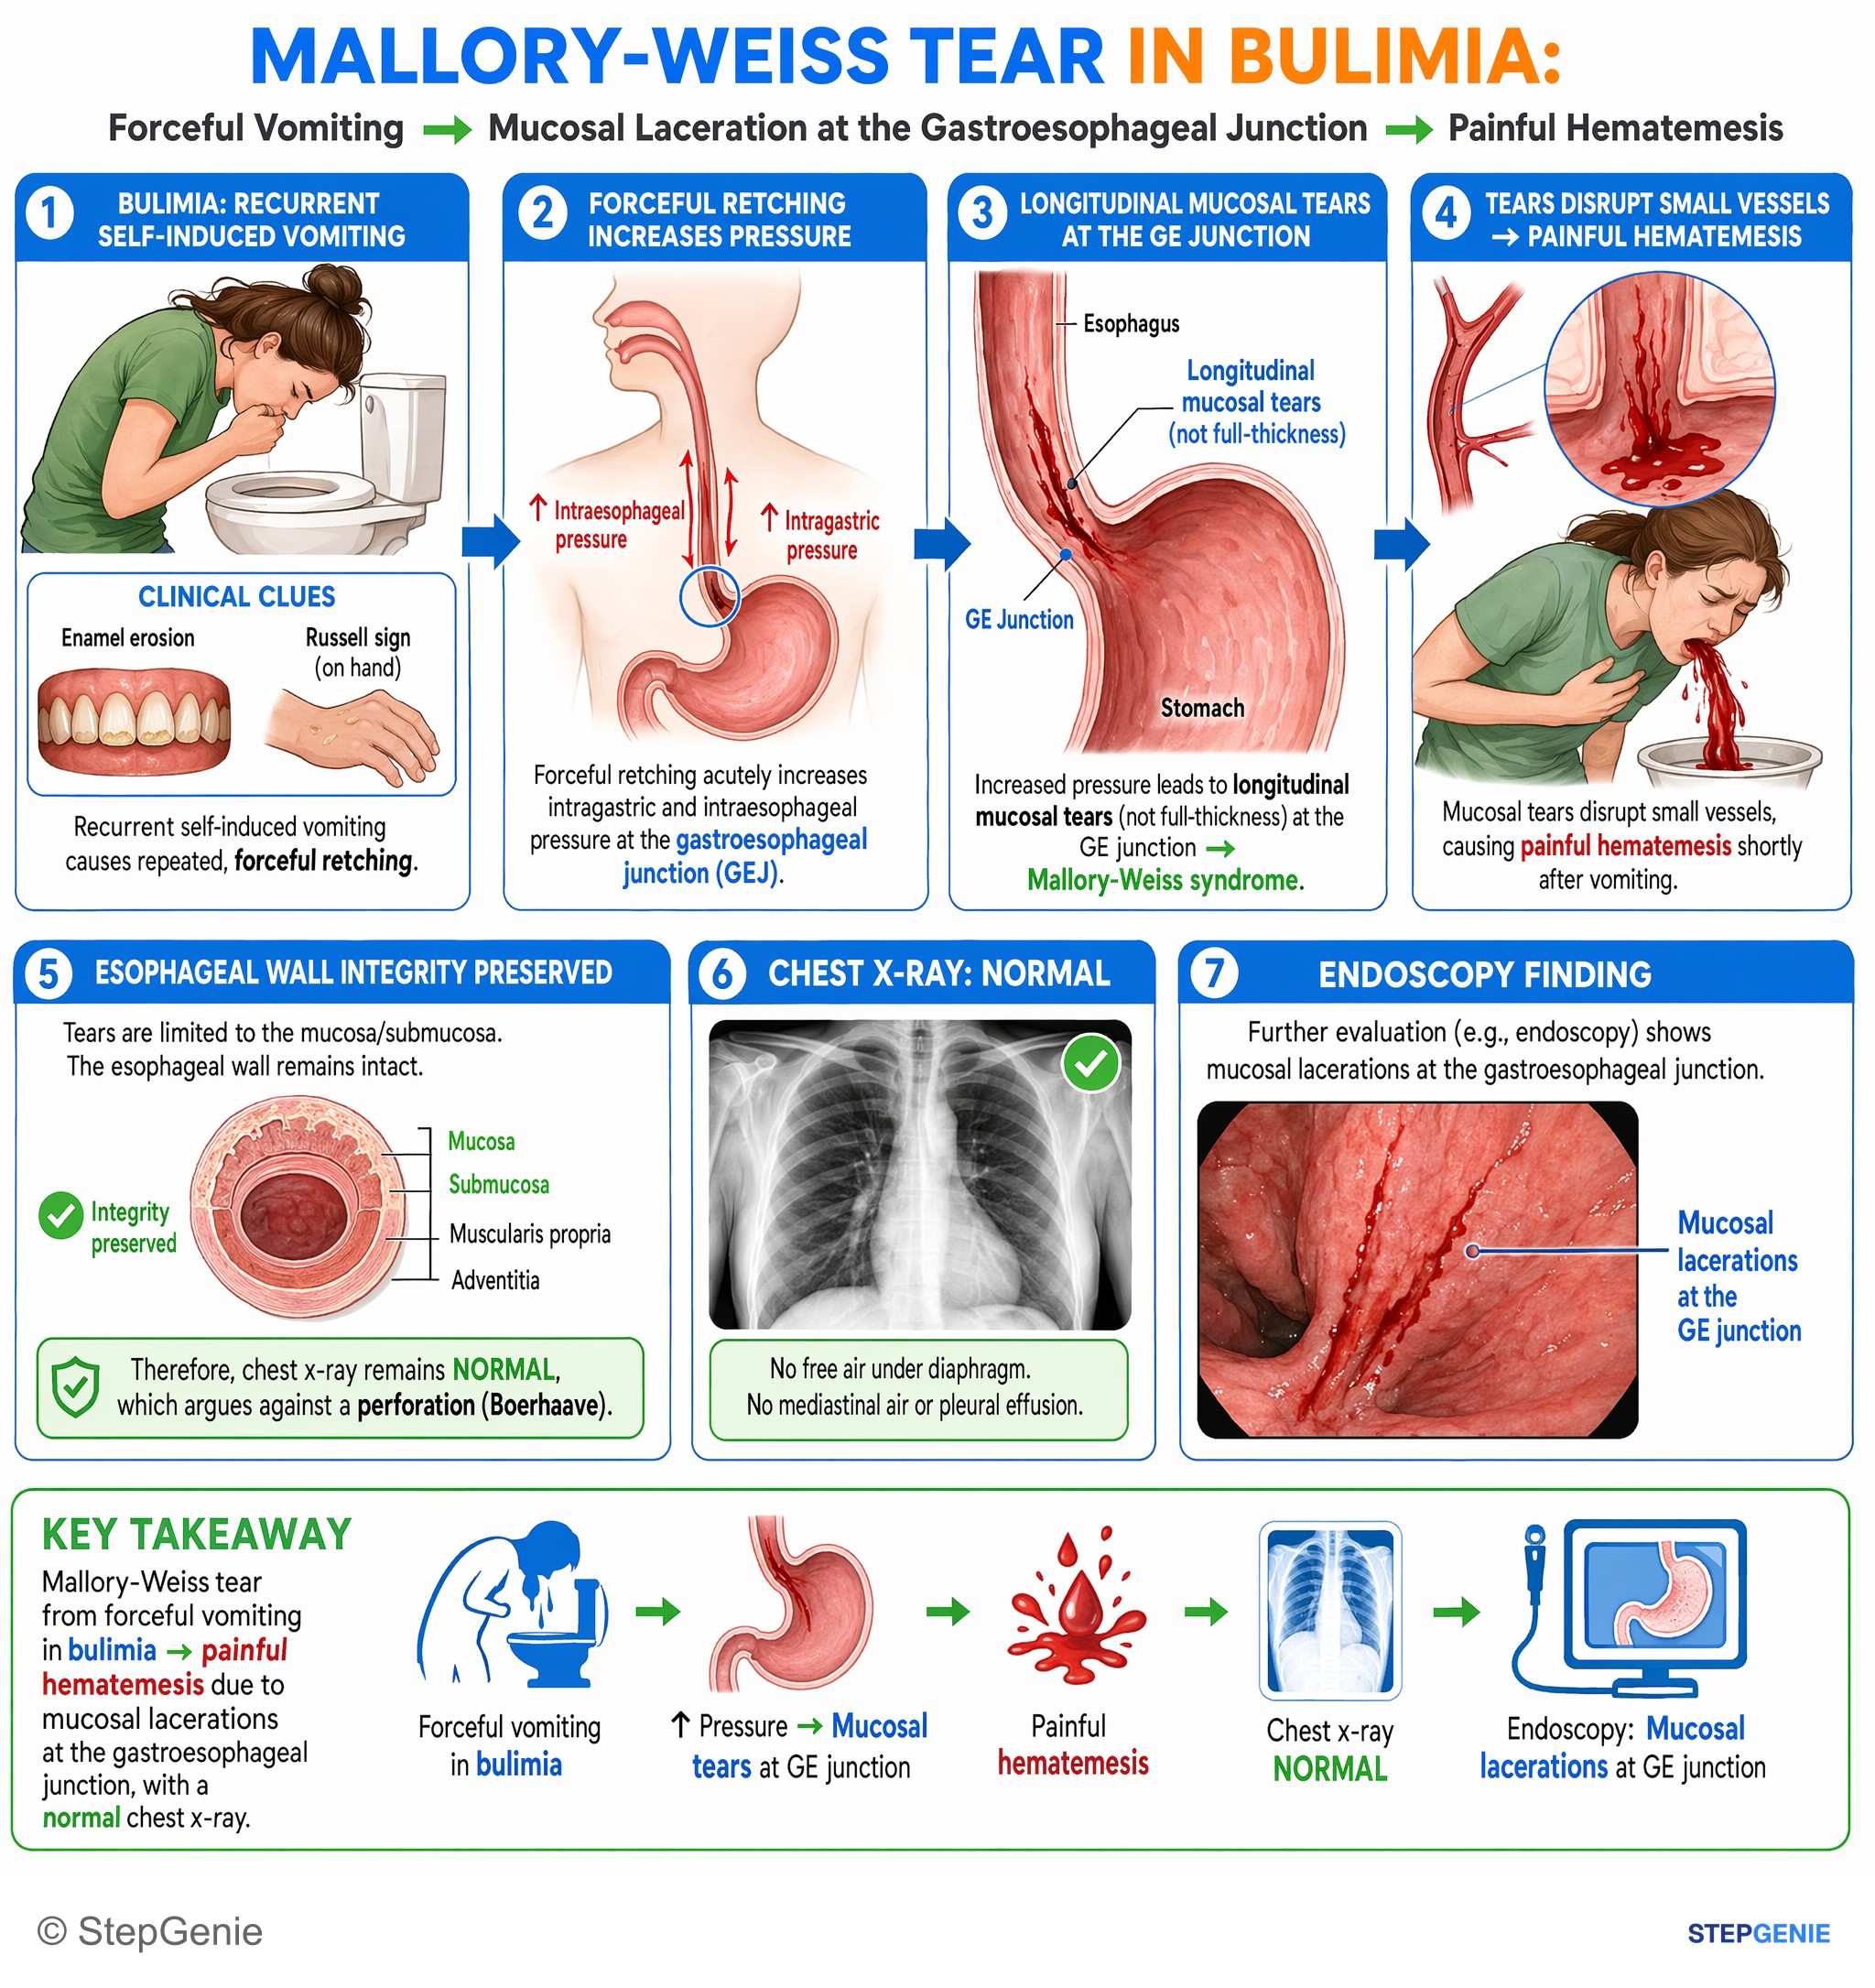
Mallory-Weiss tear from forceful vomiting in bulimia → painful hematemesis due to mucosal lacerations at gastroesophageal junction, normal…
USMLE Step 1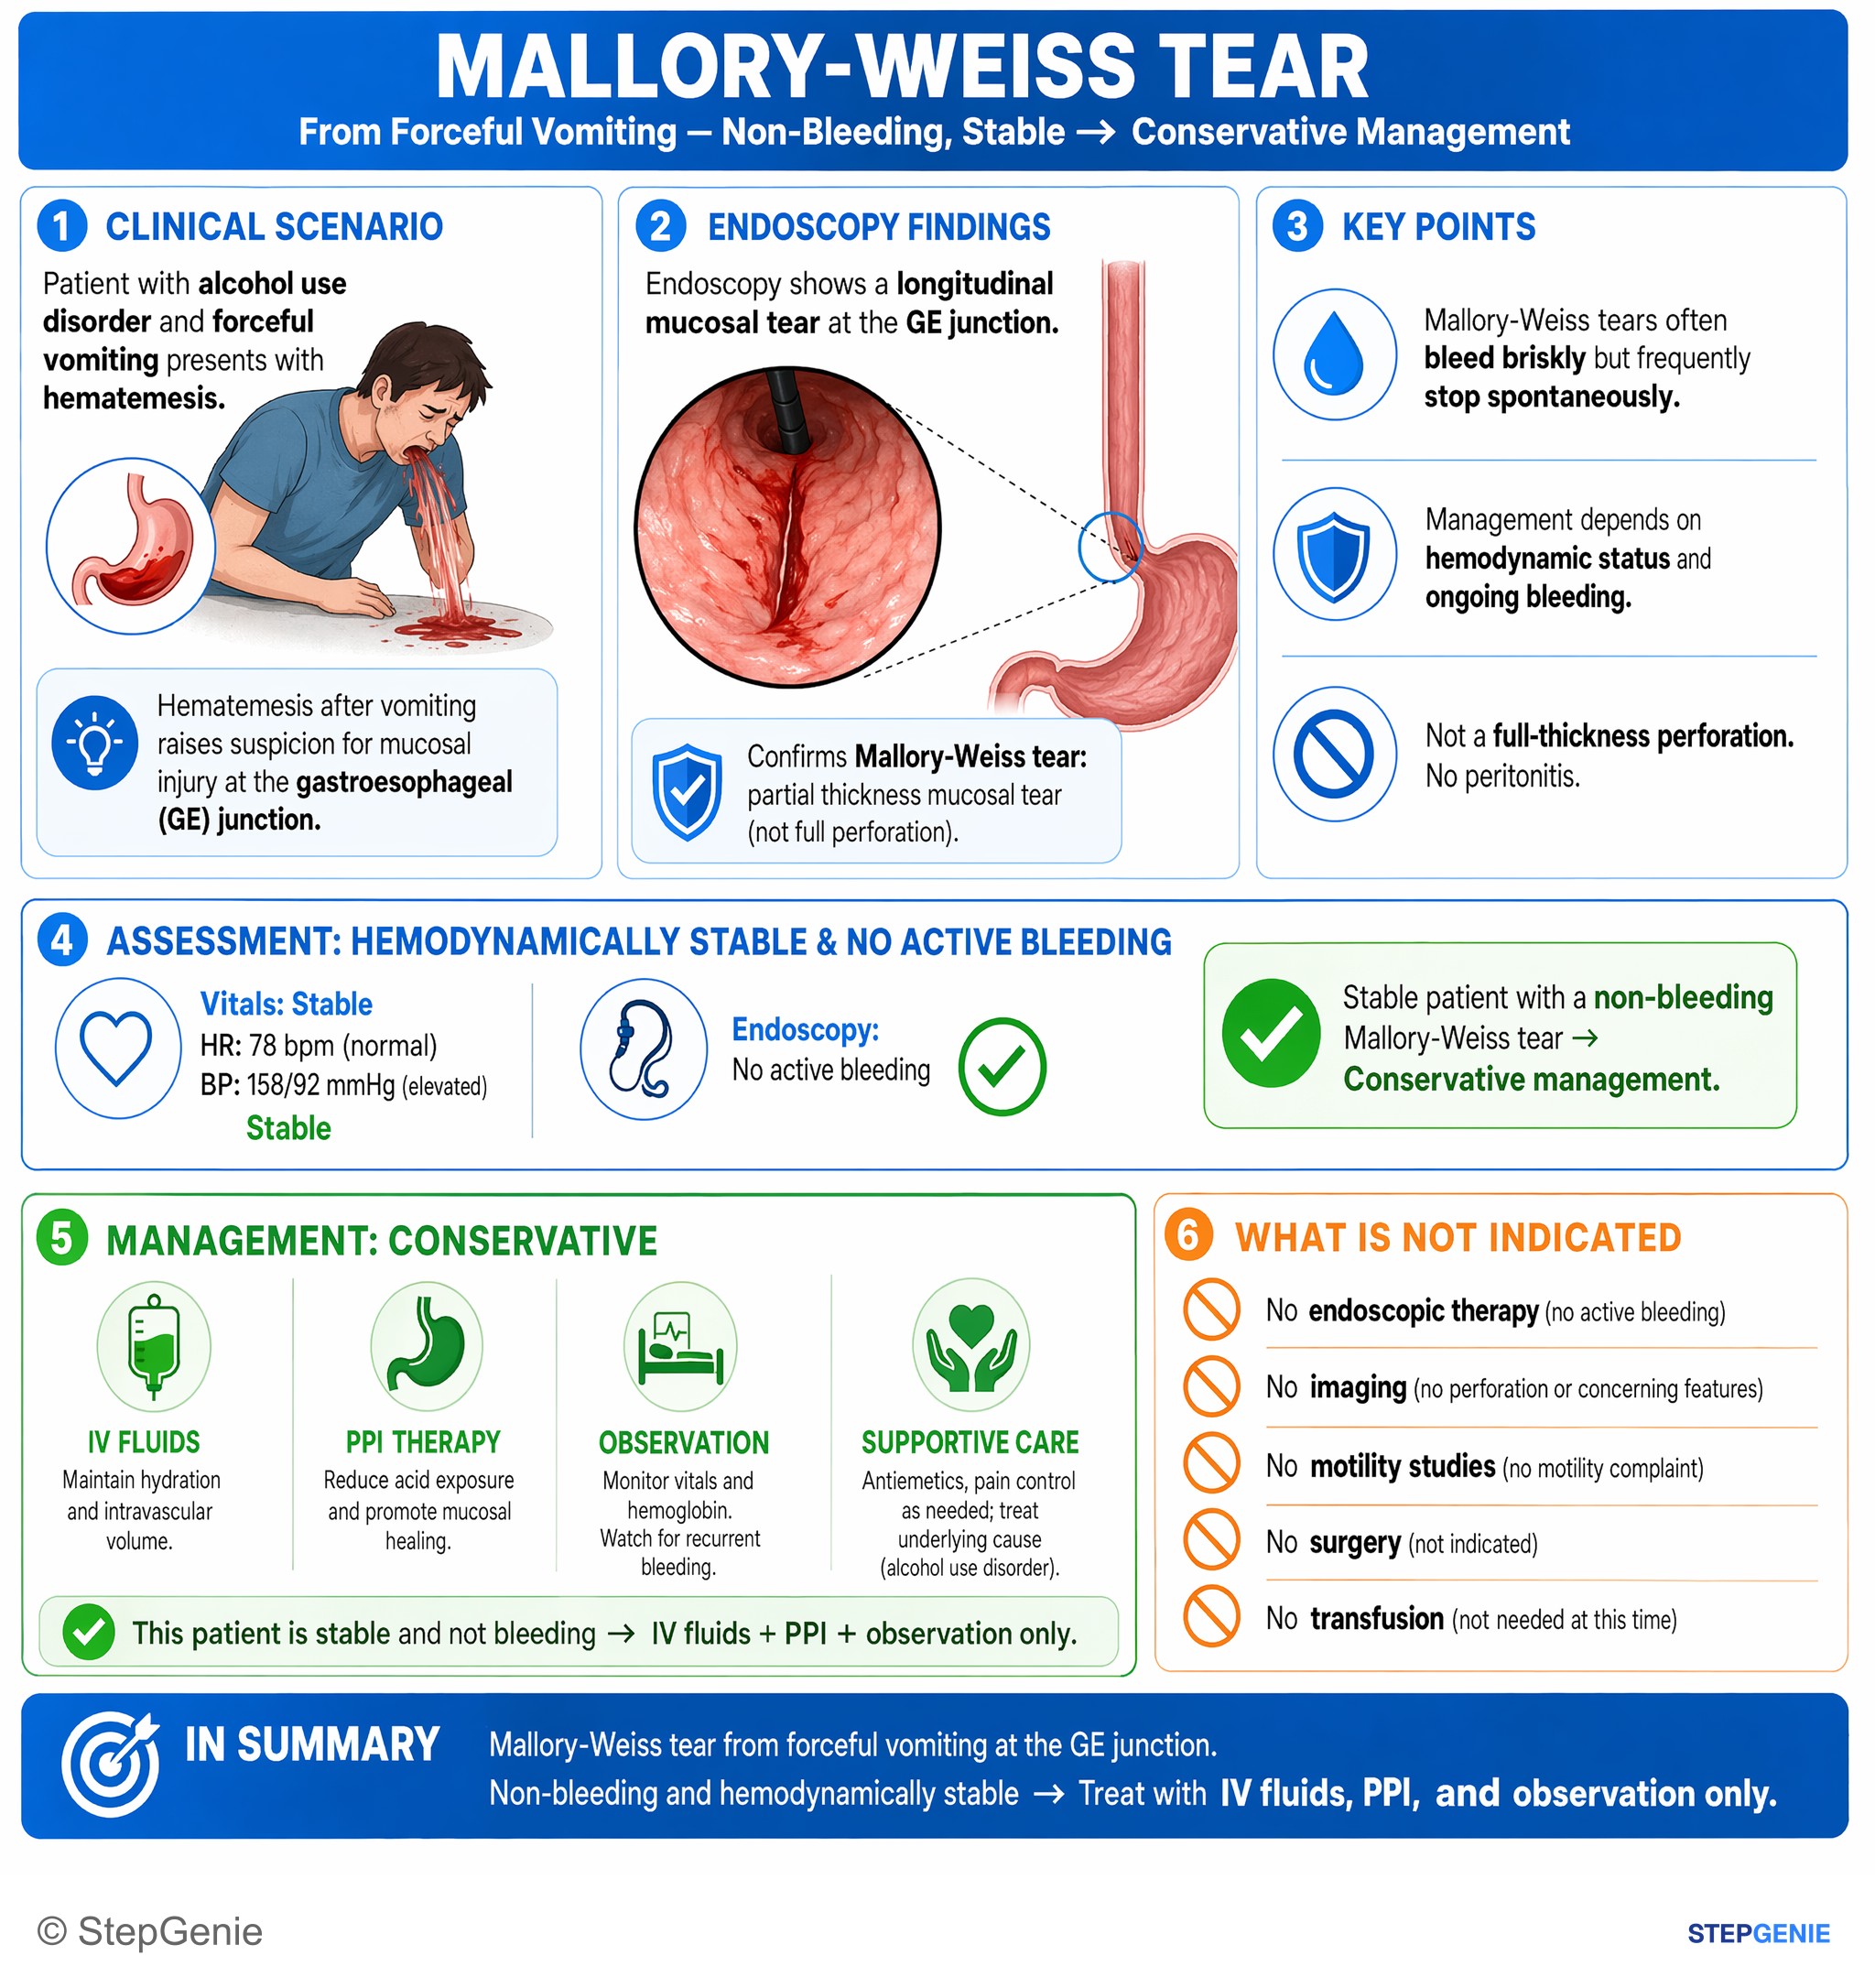
Mallory-Weiss tear from forceful vomiting; non-bleeding, hemodynamically stable → treat with IV fluids, PPI, and observation only.
USMLE Step 2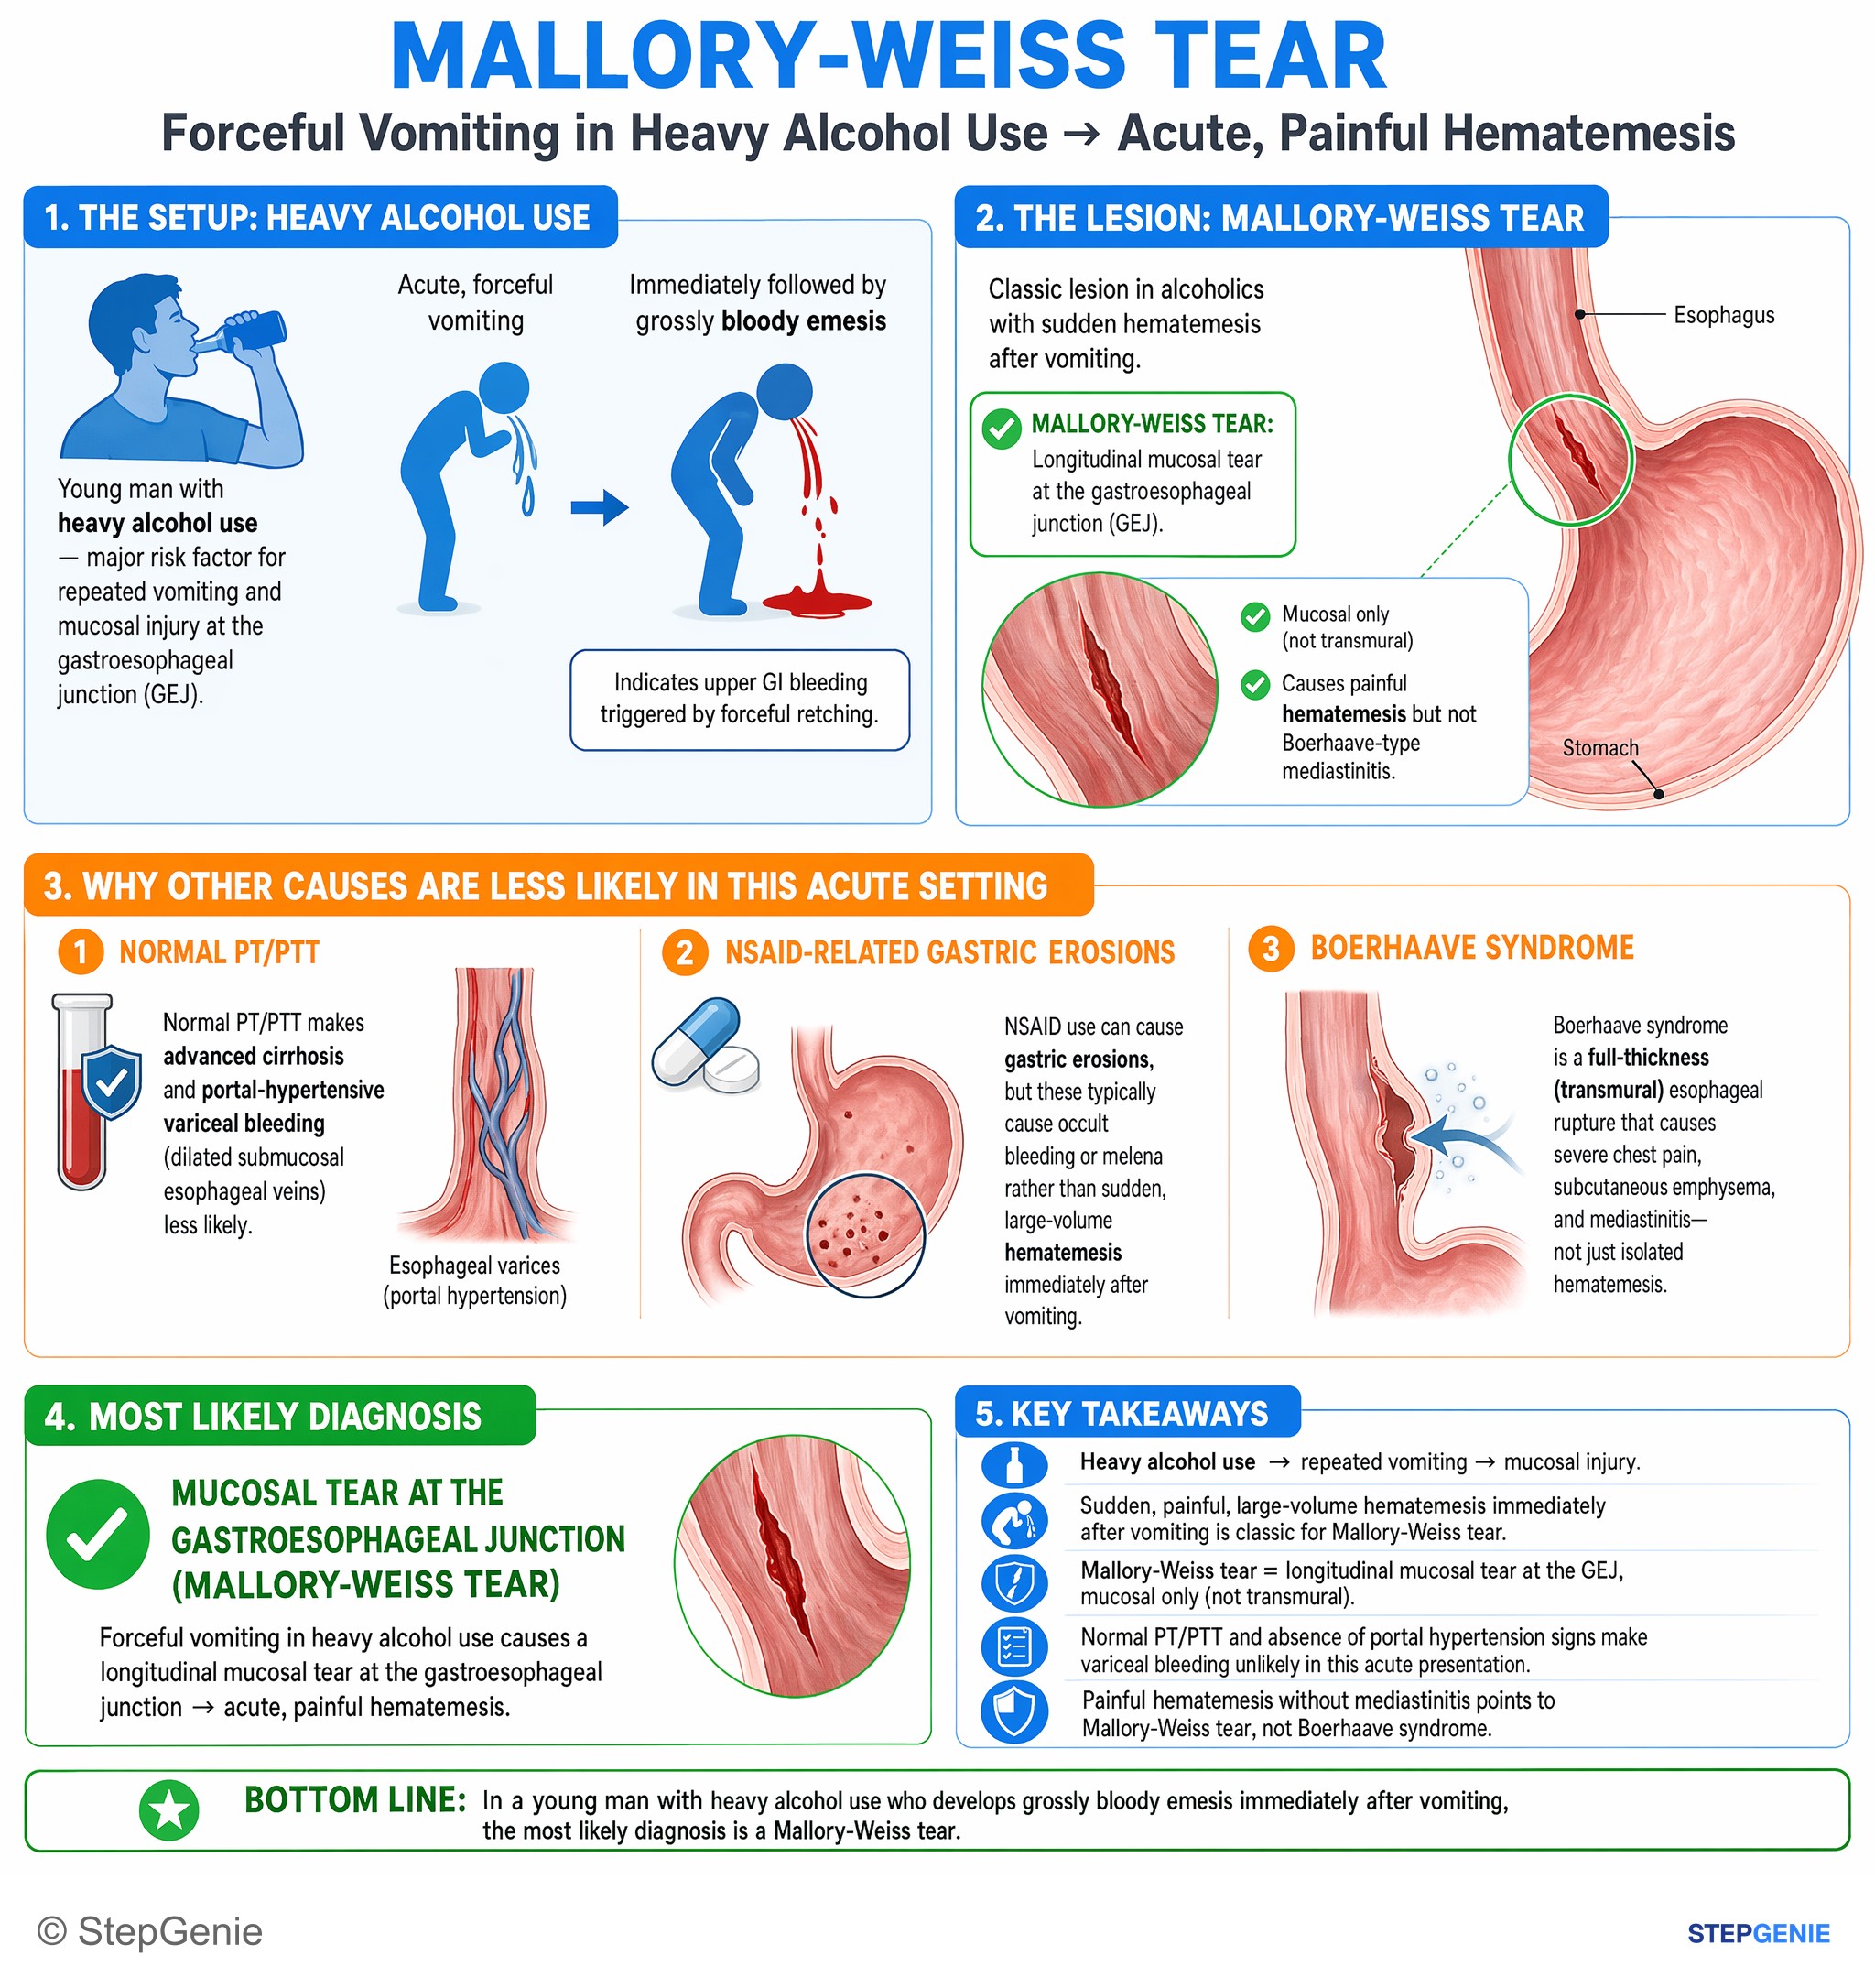
Mallory-Weiss tear: forceful vomiting in heavy alcohol use causes longitudinal mucosal tear at gastroesophageal junction → acute, painful…
USMLE Step 2Frequently Asked Questions
How do you recognize a Mallory-Weiss tear on a GI vignette?
A Mallory-Weiss tear is suggested by forceful vomiting or retching followed by bright red hematemesis in a usually hemodynamically stable patient. The classic setup often includes heavy alcohol intake and mild epigastric tenderness without signs of chronic liver disease. The key pattern is vomiting first, then bleeding, which points to a mucosal laceration at the gastroesophageal junction.
Why does vomiting cause a Mallory-Weiss tear?
Vomiting causes a Mallory-Weiss tear because repeated retching creates a sudden rise in intra-abdominal pressure that produces longitudinal mucosal tears at the gastroesophageal junction. The injury is limited to the mucosa rather than the full thickness of the esophagus. That distinction explains why patients are often stable and why this differs from Boerhaave syndrome.
How do you tell Mallory-Weiss tear from Boerhaave syndrome?
Mallory-Weiss tear causes hematemesis after retching, while Boerhaave syndrome causes a transmural esophageal rupture with severe chest pain and systemic toxicity after vomiting. Boerhaave is associated with findings like subcutaneous emphysema, dyspnea, fever, tachycardia, possible left pleural effusion, and mediastinitis. Mallory-Weiss is a mucosal tear, whereas Boerhaave is full-thickness and much more dangerous.
How do you tell Mallory-Weiss tear from esophageal varices or peptic ulcer disease?
Mallory-Weiss tear is favored when hematemesis follows repeated retching, especially after heavy alcohol intake, and the patient is relatively stable. Esophageal varices more often cause massive, painless hematemesis with signs of portal hypertension or cirrhosis. Peptic ulcer disease is more associated with epigastric pain, NSAID use, H. pylori, smoking, and bleeding that does not require vomiting as the trigger.
What is the diagnosis and treatment approach for Mallory-Weiss tear?
The diagnosis is evaluated with upper endoscopy if bleeding is ongoing or the diagnosis is uncertain, and treatment is often supportive. Initial management focuses on stabilization with ABCs, IV access, and fluids if needed. Because bleeding is usually self-limited, many patients do not need intervention, but active bleeding seen on endoscopy can be treated with endoscopic hemostasis such as clipping, cautery, or epinephrine injection.