GERD questions are deceptively simple: you see “heartburn,” you pick a PPI, and you move on. But on Step exams, the answer choices are where the test writers hide the real learning—alarm features, complications, mimics, and what to do next. Let’s break down a classic GERD vignette the way you should review your Q-bank: why the correct answer is correct, and why every distractor is wrong.
Tag: GI > Esophageal & Gastric Disorders
The Clinical Vignette (GERD Core Presentation)
A 46-year-old man reports burning substernal pain after meals and when lying down. He has sour taste/regurgitation at night. Symptoms occur 4–5 days/week for 3 months. He denies dysphagia, weight loss, GI bleeding, or anemia. Exam is normal.
Question: What is the best next step in management?
✅ Correct Answer: Start empiric PPI therapy + lifestyle modifications
Why this is correct (Step logic):
- This is classic, uncomplicated GERD (heartburn + regurgitation, worse after meals/recumbency).
- No alarm features → no immediate endoscopy needed.
- For frequent symptoms (≥2 days/week), PPIs are first-line and superior to H2 blockers for healing erosive esophagitis and symptom control.
High-yield management pearls
- Empiric PPI trial: typically once daily before breakfast (optimize timing).
- If partial response: ensure adherence/timing → then consider BID dosing.
- Add lifestyle:
- Weight loss (best evidence)
- Elevate head of bed
- Avoid late meals (stop eating 2–3 hours before bed)
- Trigger foods/alcohol: individualized (not universal)
The Distractors: Why Each Wrong Choice Matters
Below are common answer choices that appear in GERD stems—and what clues should push you toward or away from them.
1) ❌ Upper endoscopy (EGD) now
Why it’s tempting: You’re thinking about Barrett esophagus, ulcers, or cancer.
Why it’s wrong here: In uncomplicated GERD, initial step is empiric PPI, not EGD.
When EGD is indicated (memorize this list):
- Alarm features:
- Dysphagia/odynophagia
- Weight loss
- GI bleeding, anemia
- Persistent vomiting
- Refractory symptoms despite optimized PPI therapy
- Screening for Barrett in patients with chronic GERD plus risk factors (commonly tested):
- Male, age >50, White, obesity/central adiposity, smoking, family history
(Exact screening criteria can vary by guideline, but Step-style questions reward recognizing the risk profile.)
- Male, age >50, White, obesity/central adiposity, smoking, family history
2) ❌ Barium swallow
Why it’s tempting: It “evaluates the esophagus,” right?
Why it’s wrong here: Barium swallow is not a first-line test for routine GERD.
When barium swallow is useful:
- Suspected structural abnormality (e.g., rings/webs, strictures) contributing to dysphagia
- Achalasia evaluation (classically “bird-beak”)
- Sometimes pre-endoscopy mapping in complex anatomy
But for GERD symptoms without dysphagia, it’s not the move.
3) ❌ Ambulatory pH monitoring now
Why it’s tempting: GERD = acid, so measure acid.
Why it’s wrong here: If symptoms are classic and uncomplicated, you treat empirically.
When pH monitoring is indicated:
- Persistent symptoms with normal EGD
- Symptoms refractory to PPI when diagnosis is uncertain
- Pre-op evaluation before antireflux surgery in select cases
High-yield nuance:
- pH impedance monitoring can detect non-acid reflux (important in refractory cases).
4) ❌ H2-receptor blocker instead of PPI
Why it’s tempting: Mild GERD can respond to H2 blockers.
Why it’s wrong here: This patient has frequent symptoms (4–5 days/week) → PPI is preferred.
Where H2 blockers shine:
- Mild/intermittent symptoms
- Nocturnal breakthrough symptoms (sometimes added at night)
- Cost/short-term symptom relief
Board-style pearl: H2 blockers can develop tachyphylaxis (reduced efficacy over time).
5) ❌ Treat for H. pylori (or order H. pylori testing)
Why it’s tempting: Epigastric issues = H. pylori?
Why it’s wrong here: This stem is classic reflux, not dyspepsia or ulcer disease. GERD and H. pylori aren’t synonymous.
When to test for H. pylori:
- Peptic ulcer disease
- Gastric MALT lymphoma
- After endoscopic resection of early gastric cancer
- Uninvestigated dyspepsia in appropriate patients (age/risk dependent)
Clue difference:
- GERD: heartburn, regurgitation, worse recumbent
- Ulcer/dyspepsia: epigastric pain, meal relationship varies; not usually “sour taste in mouth”
6) ❌ Immediate antireflux surgery (e.g., Nissen fundoplication)
Why it’s tempting: “Definitive” solution.
Why it’s wrong here: Surgery is not first-line in uncomplicated cases.
When surgery becomes the right answer:
- Persistent symptoms despite optimized medical therapy and objective evidence of reflux
- Complications or patient preference to avoid long-term meds (after evaluation)
- Large hiatal hernia with significant reflux (case-dependent)
High-yield complication: Fundoplication can cause gas-bloat syndrome, dysphagia if too tight.
7) ❌ Reassure only / no meds
Why it’s tempting: Normal exam, common complaint.
Why it’s wrong here: Symptoms are frequent and impacting quality of life; untreated reflux can lead to complications.
High-Yield GERD: What Step Wants You to Recognize
Classic symptoms
- Heartburn (burning substernal discomfort)
- Regurgitation (sour/bitter taste)
- Worse after meals, worse when lying down, improved with antacids
Pathophysiology (common testable core)
- Transient relaxation or incompetence of the lower esophageal sphincter (LES)
- Risk factors: obesity, pregnancy, hiatal hernia, smoking, certain foods/meds
Complications you must know
| Complication | What happens | Buzzwords / What Step tests |
|---|---|---|
| Erosive esophagitis | Mucosal injury from acid | Odynophagia, EGD findings |
| Peptic stricture | Chronic inflammation → fibrosis | Progressive solid-food dysphagia |
| Barrett esophagus | Intestinal metaplasia of distal esophagus | Goblet cells, risk of adenocarcinoma |
| Esophageal adenocarcinoma | Malignancy linked to Barrett | Dysphagia, weight loss, chronic GERD history |
Barrett pathology pearl: Squamous epithelium → intestinal-type columnar epithelium with goblet cells (metaplasia).
Rapid-Fire “Next Best Step” Triggers (Exam Pattern Recognition)
Uncomplicated typical GERD
- Empiric PPI + lifestyle
GERD + alarm symptoms
- EGD
Persistent symptoms despite optimized PPI
- Confirm correct dosing/timing → consider EGD
- If EGD normal and symptoms persist → pH monitoring (± impedance)
Progressive dysphagia (especially solids → then liquids)
- Think stricture/cancer → EGD (not barium first on Step unless specifically asking for suspected achalasia/structural mapping)
How to Review Your Q-Bank Like a Pro
When you miss (or even when you get it right), ask:
- What is the diagnosis being tested? (GERD vs dyspepsia vs achalasia vs ACS mimic)
- Are there alarm features? If yes → EGD.
- Is the question asking for initial therapy or confirmation testing?
- Which answer choices are “tests,” which are “treatments,” and which are “definitive” options?
Test writers love mixing levels of escalation.
Takeaway
For classic, uncomplicated GERD: empiric PPI therapy is the best next step, and the wrong answers become right only when the stem adds alarm symptoms, refractory symptoms, or an alternative diagnosis. Train yourself to read the answer choices as a checklist of “What would have to be true for this to be correct?”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
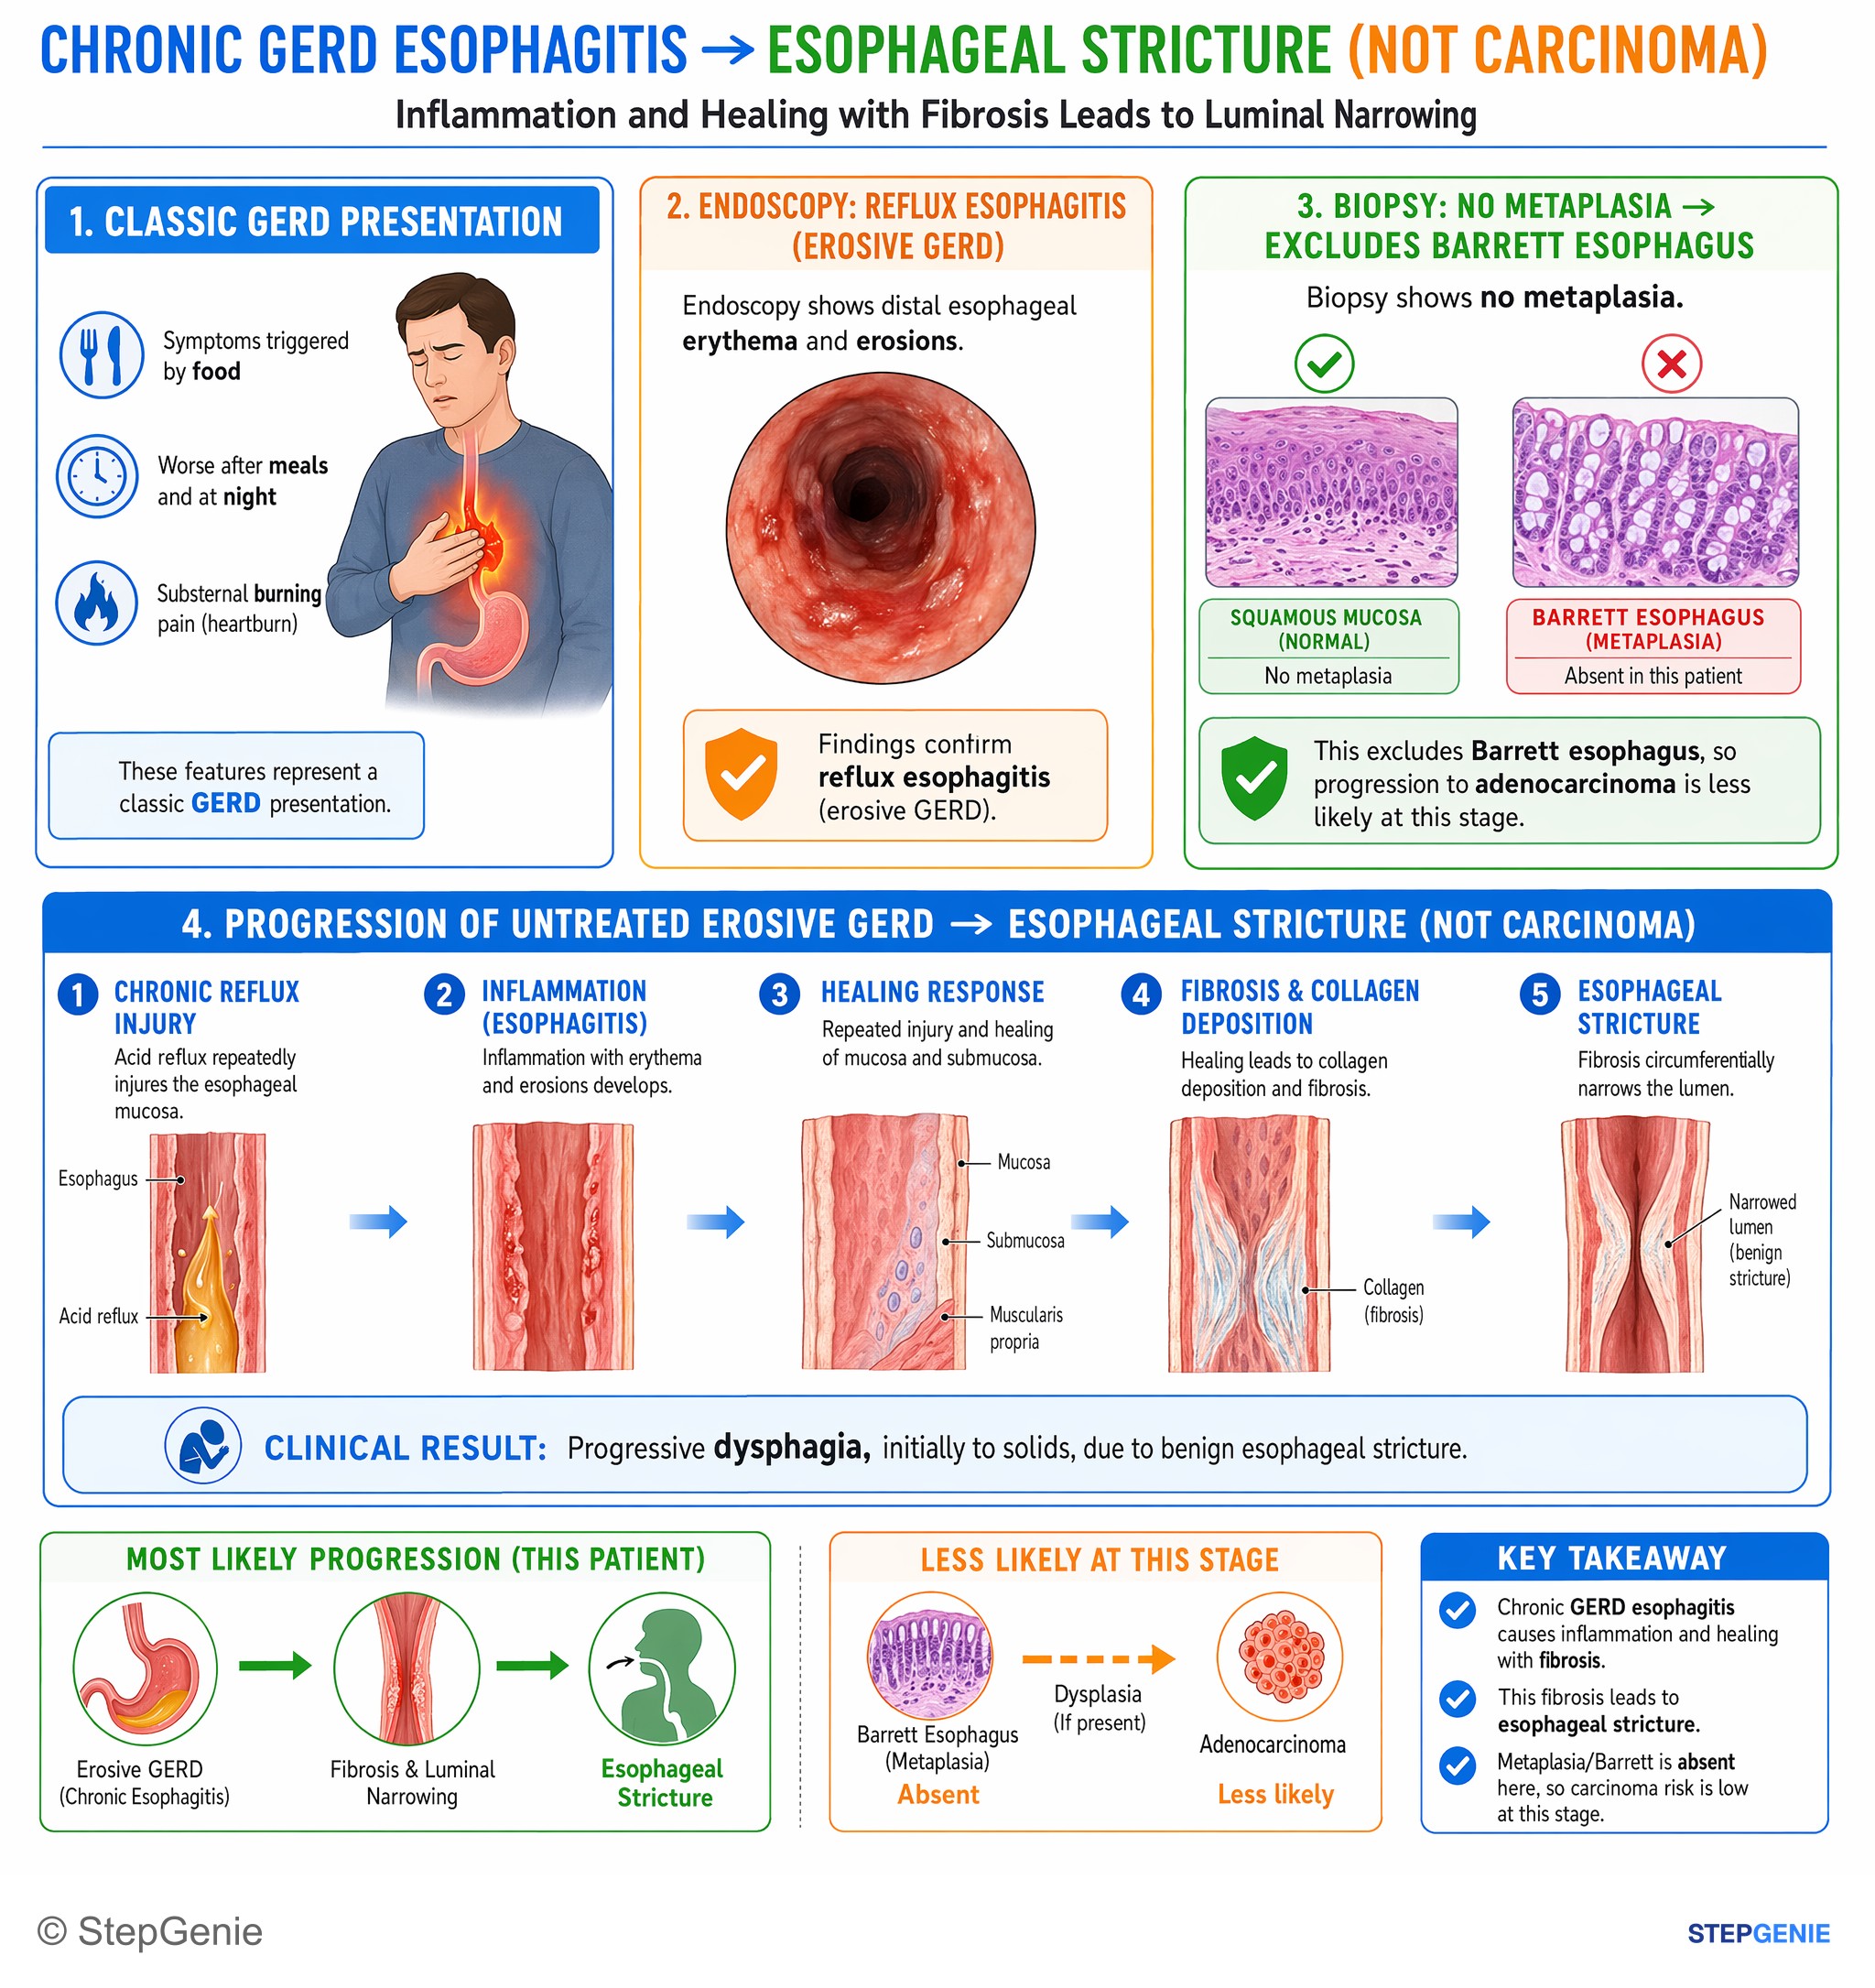
Chronic GERD esophagitis causes inflammation and healing with fibrosis, leading to esophageal stricture; metaplasia/Barrett is absent here.
USMLE Step 1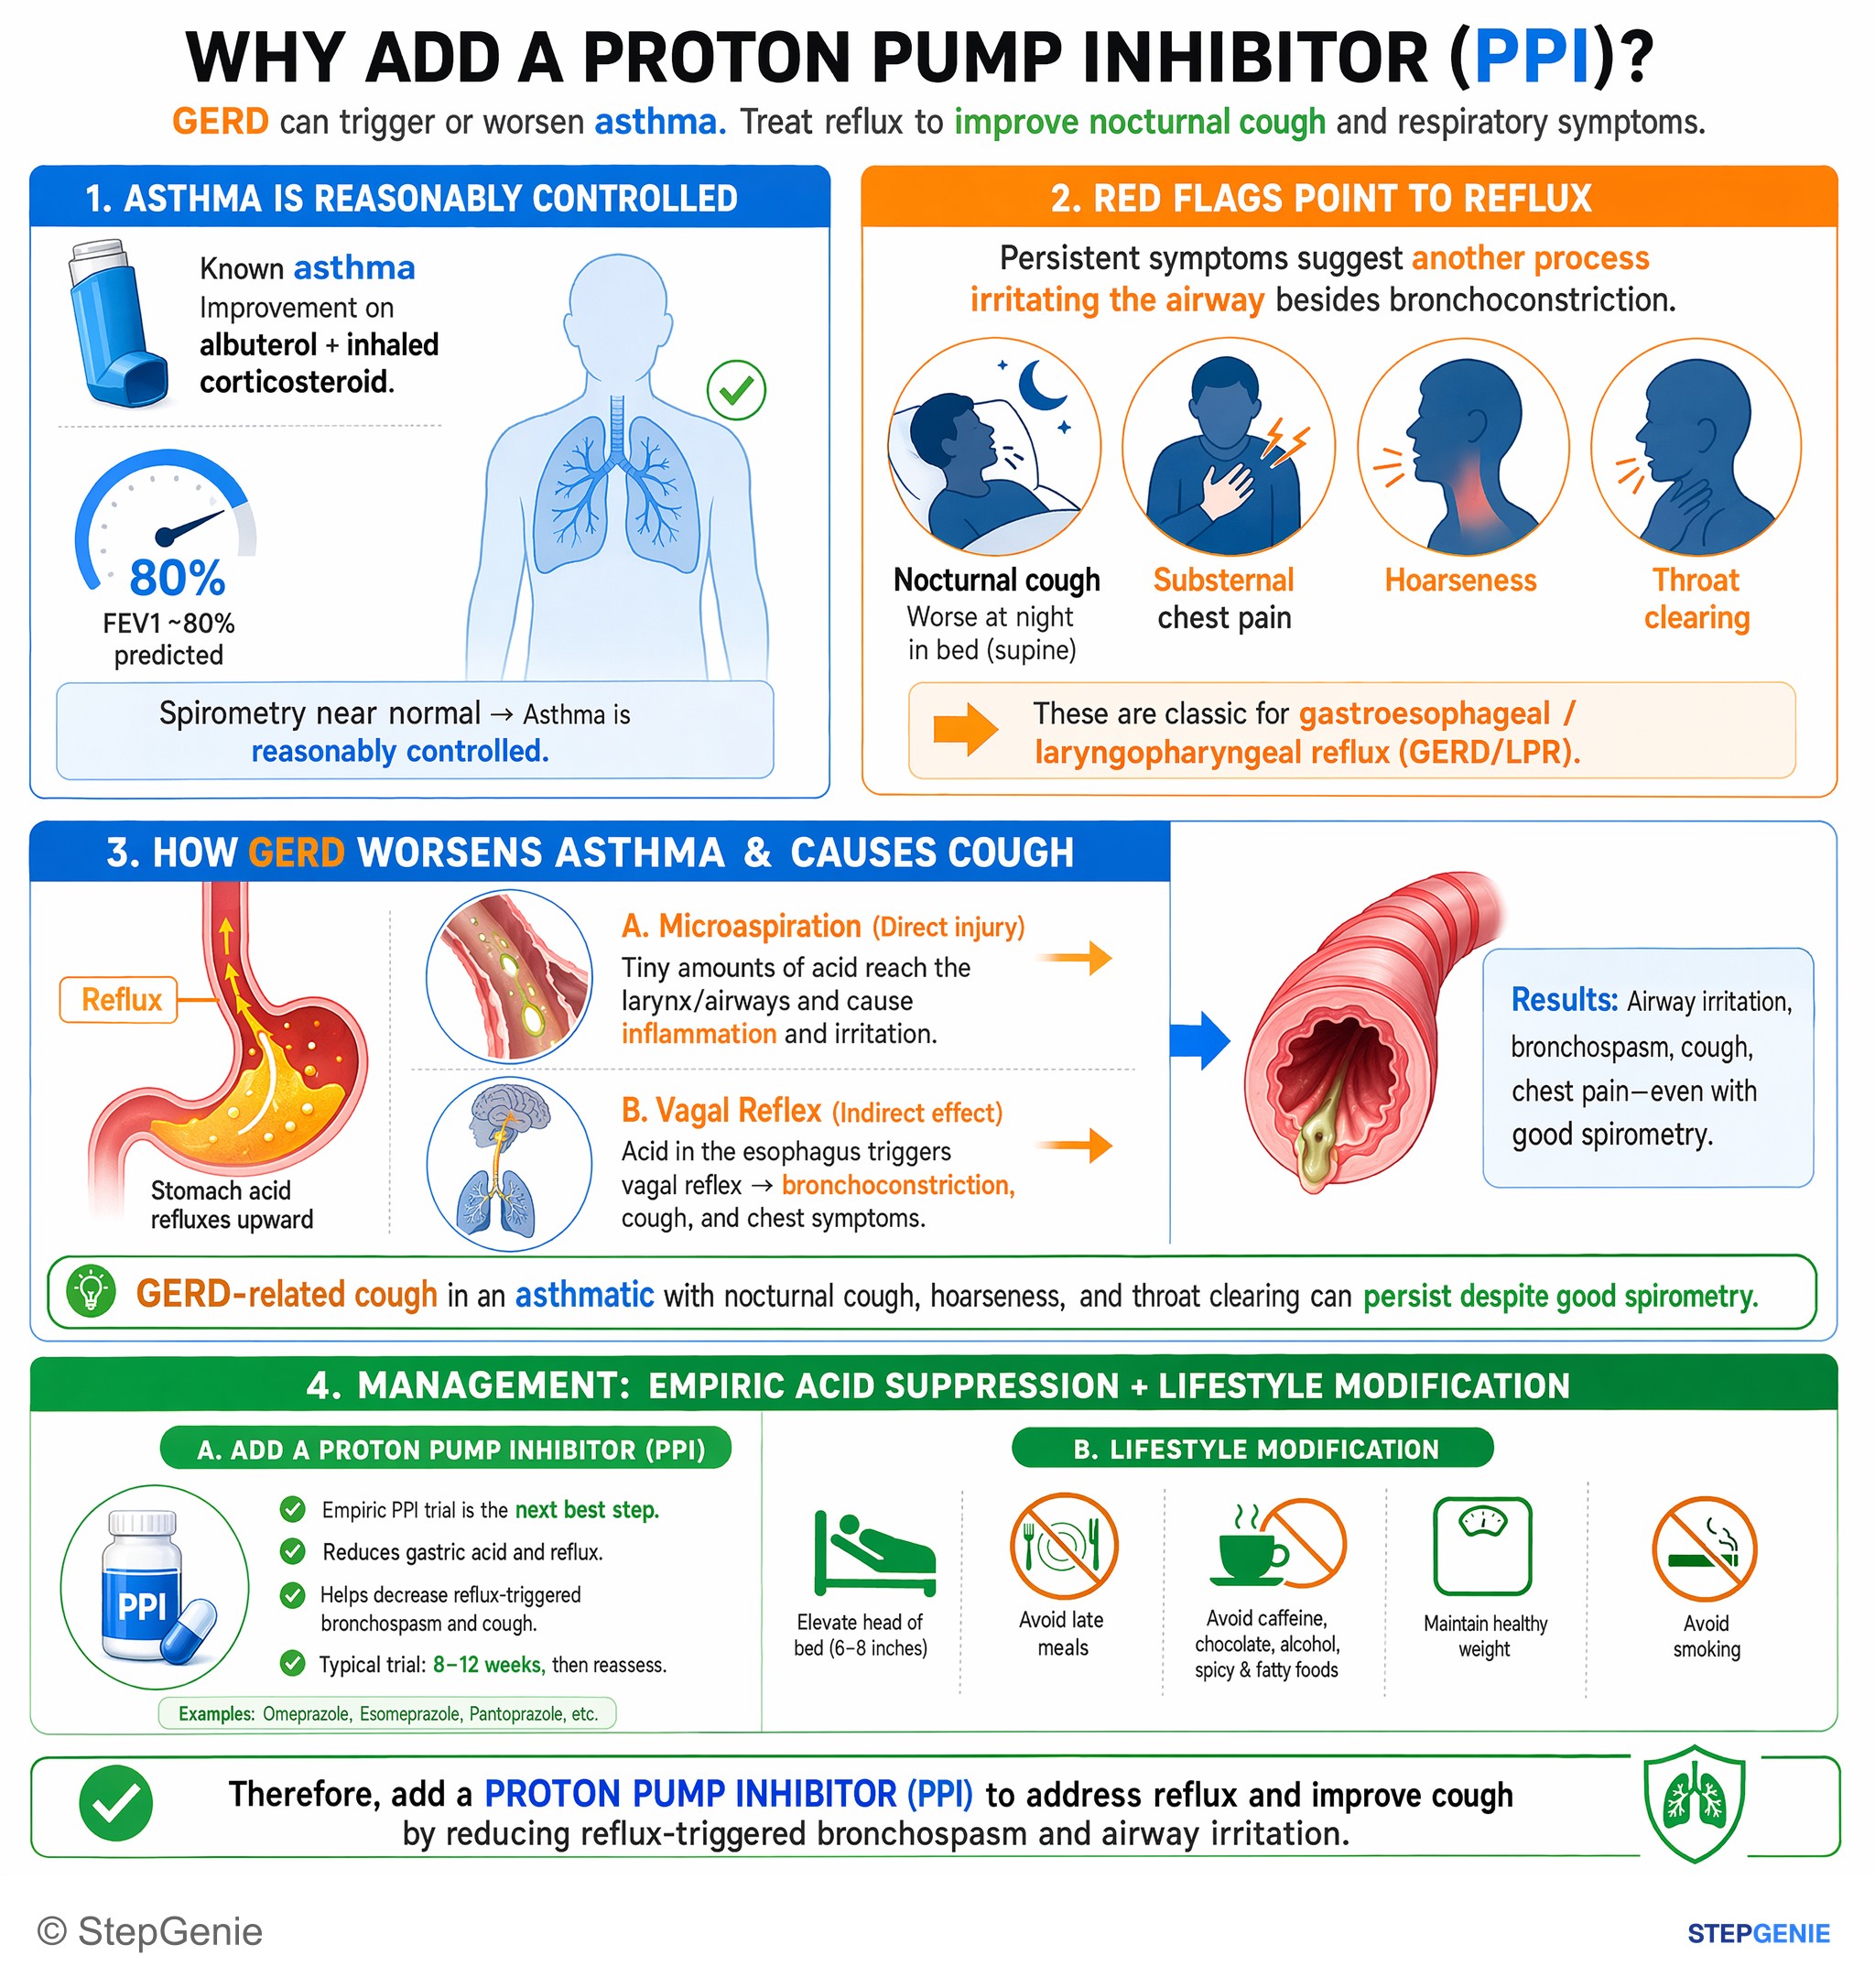
GERD-related cough in an asthmatic with nocturnal cough, hoarseness, and throat clearing; treat with PPI to reduce reflux-triggered…
USMLE Step 2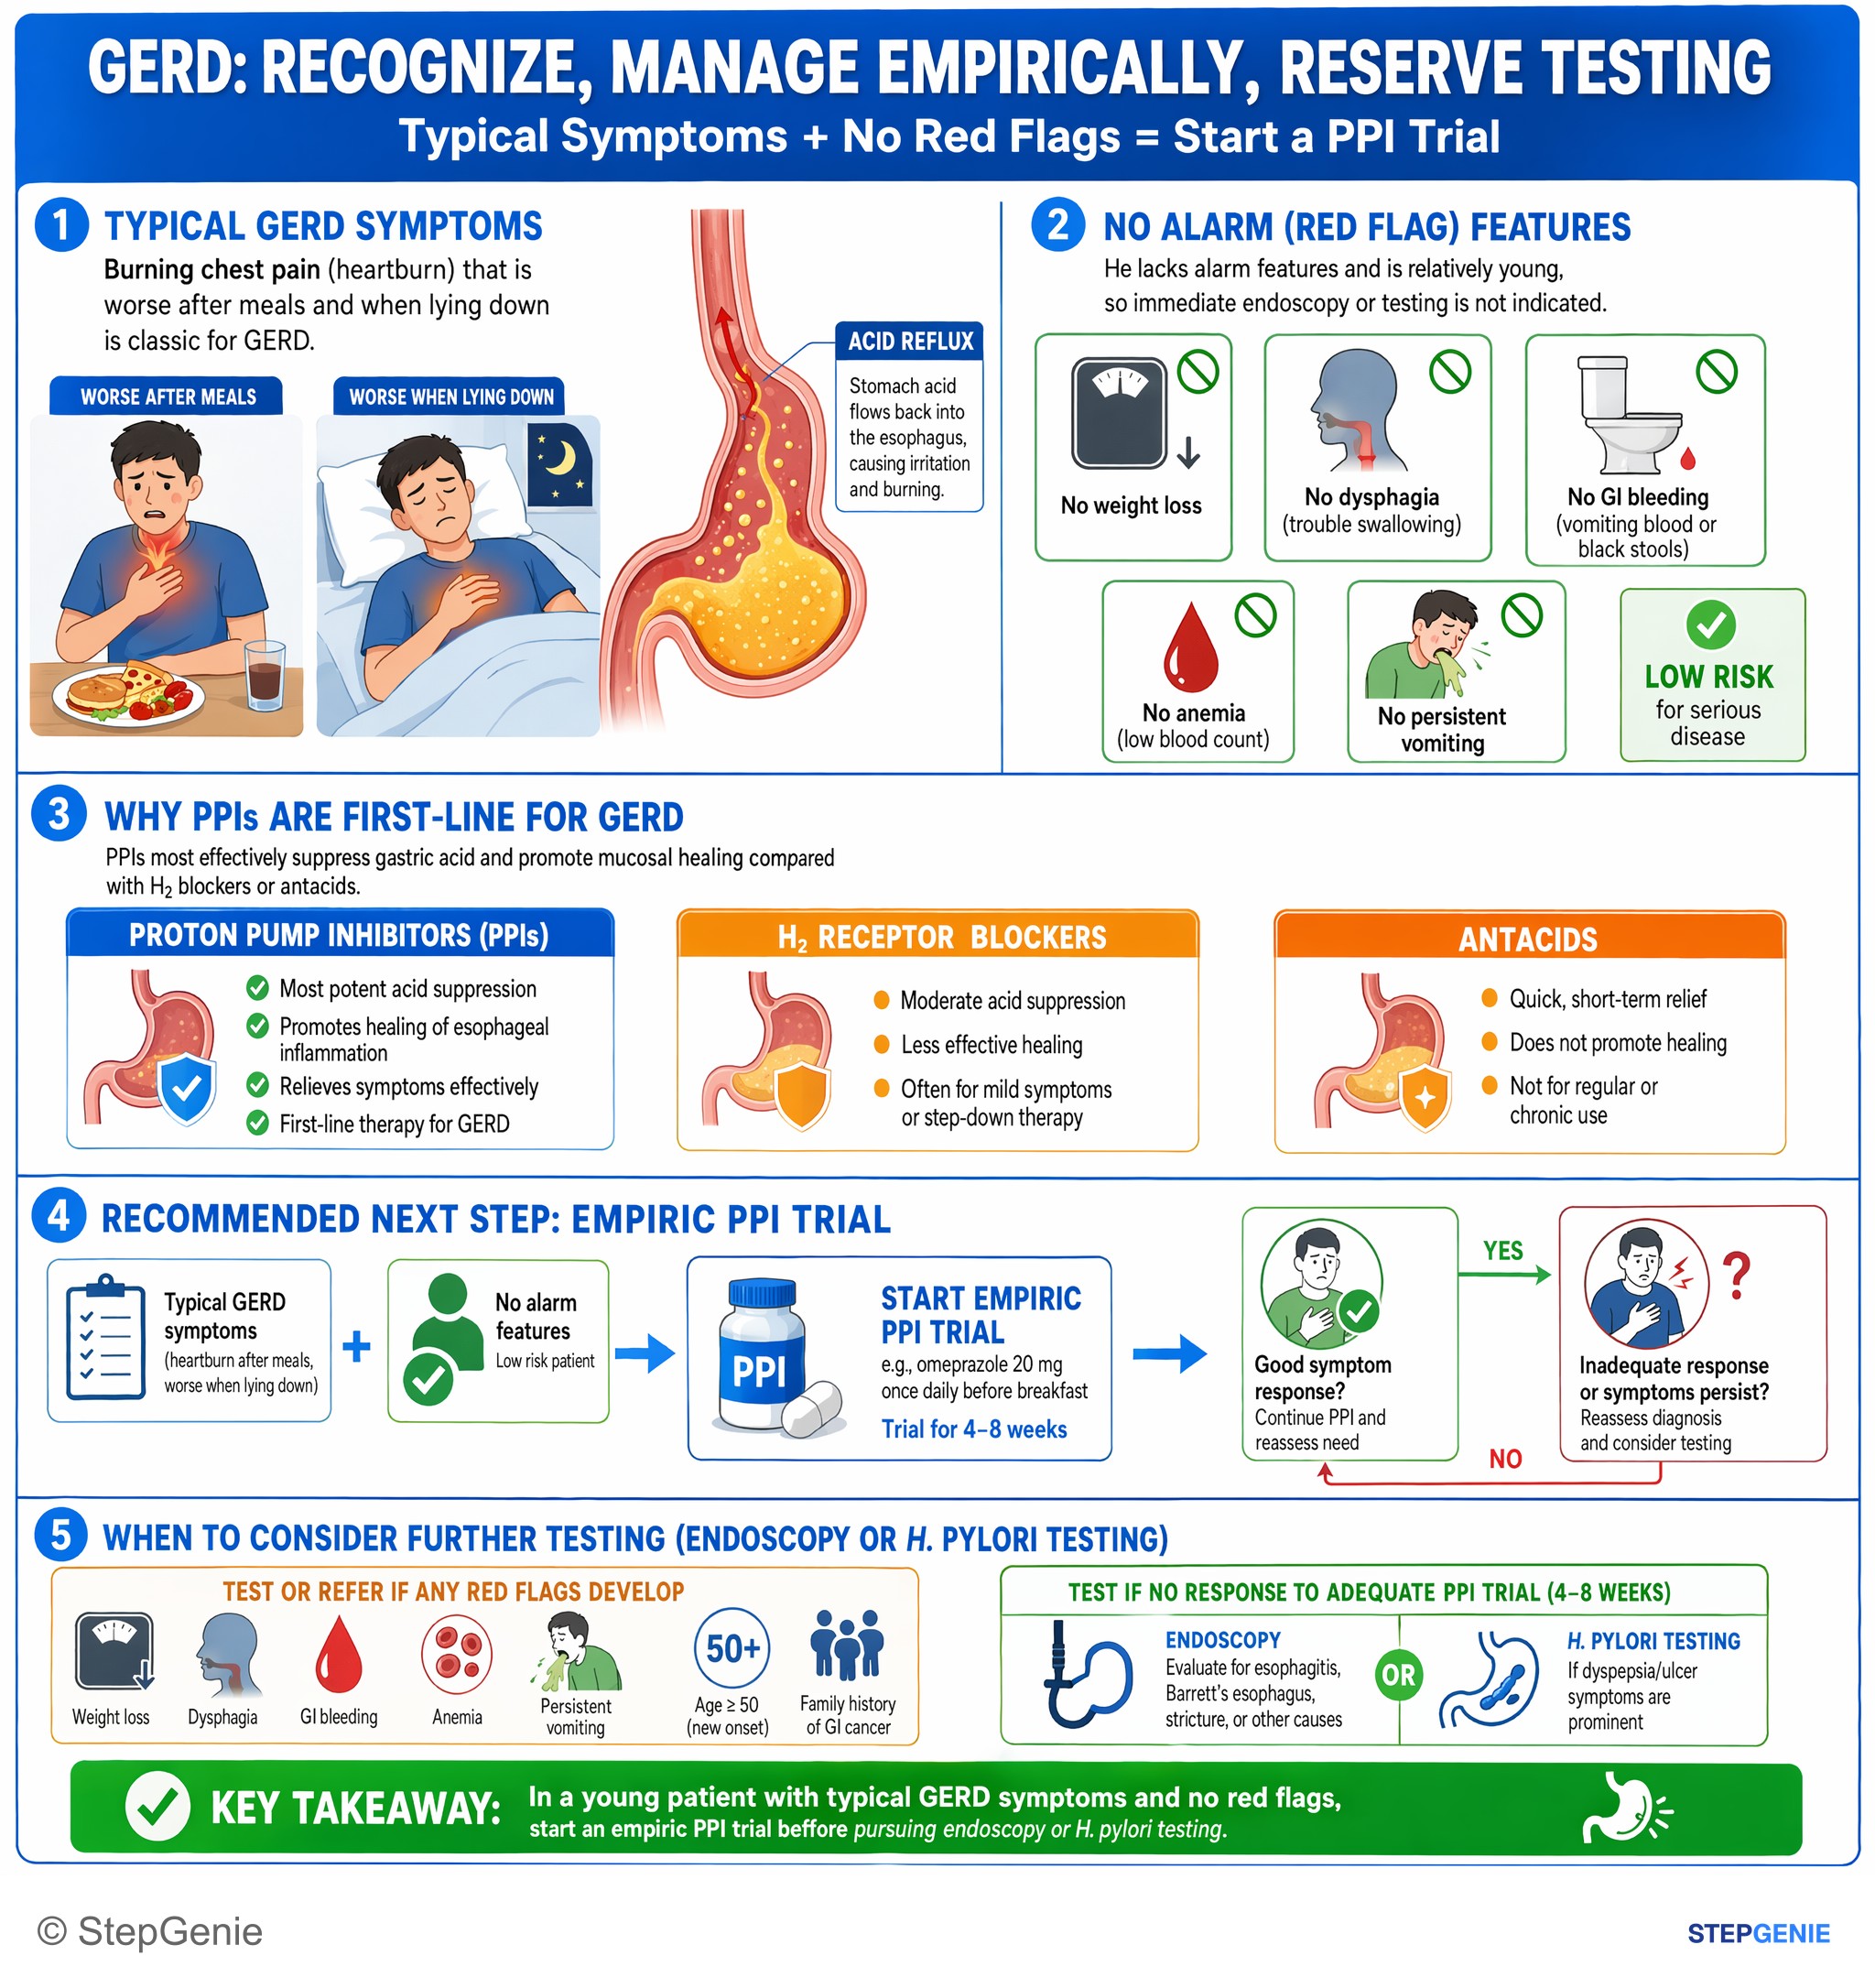
GERD with typical symptoms, no red flags: manage empirically with a proton-pump inhibitor trial before pursuing endoscopy or H. pylori…
USMLE Step 2Frequently Asked Questions
What is the best next step for classic GERD without alarm features?
The best next step is to start empiric PPI therapy plus lifestyle modifications. A patient with burning substernal pain, nighttime regurgitation, and symptoms worse after meals or lying down has classic uncomplicated GERD. When there are no alarm features such as dysphagia, weight loss, GI bleeding, or anemia, immediate endoscopy is not needed, and PPIs are first-line for frequent symptoms.
When do you need an upper endoscopy for GERD instead of just giving a PPI?
Upper endoscopy is indicated when GERD has alarm features, refractory symptoms, or concern for Barrett esophagus risk. Alarm features include dysphagia, odynophagia, weight loss, GI bleeding, anemia, and persistent vomiting. Endoscopy is also used when symptoms persist despite optimized PPI therapy and for Barrett screening in patients with chronic GERD plus a typical risk profile such as male sex, older age, White race, obesity, smoking, or family history.
Why is a PPI preferred over an H2 blocker in frequent GERD symptoms?
A PPI is preferred because frequent GERD symptoms are treated most effectively with acid suppression that is stronger than an H2 blocker. In patients with symptoms occurring at least 2 days per week, PPIs are first-line and are superior to H2 blockers for symptom control and healing erosive esophagitis. H2 blockers are more useful for mild or intermittent symptoms, nocturnal breakthrough symptoms, or short-term relief.
When is ambulatory pH monitoring actually used in GERD?
Ambulatory pH monitoring is used when the diagnosis is uncertain rather than for classic uncomplicated GERD. If symptoms are typical, empiric treatment comes first. pH monitoring becomes useful when symptoms persist despite therapy and the EGD is normal, when refractory symptoms make the diagnosis unclear, or before antireflux surgery in select patients. pH impedance monitoring can also identify non-acid reflux in refractory cases.
How do you tell GERD from dyspepsia or peptic ulcer disease on a question stem?
GERD is suggested by heartburn and regurgitation, especially when symptoms worsen after meals or when lying down and include a sour or bitter taste. Dyspepsia or peptic ulcer disease is more associated with epigastric pain and a meal-related pattern that varies, without classic sour regurgitation. That distinction matters because classic reflux does not automatically call for H. pylori testing or ulcer treatment.