You just opened a q-bank question that looks like “classic BPH,” but the answer choices are a minefield of renal pharm, autonomic physiology, and urinary stone buzzwords. The trick isn’t recognizing benign prostatic hyperplasia (you can do that in your sleep)—it’s knowing why every other option is wrong for this specific presentation. That’s how you turn one vignette into 5–7 board-relevant facts.
The Clinical Vignette (What You’re Given)
A 68-year-old man presents with:
- Progressive hesitancy, weak stream, intermittency
- Nocturia
- Sensation of incomplete emptying
- Now acutely can’t urinate: painful suprapubic fullness (acute urinary retention)
- Exam: enlarged, smooth, “rubbery” prostate
- Bladder ultrasound/post-void residual: markedly elevated
The Question Stem Twist
You’re asked which medication will provide the most rapid symptomatic relief (or which is best for immediate decompression/relief of retention).
Step 1: Diagnosis + Pathophysiology in One Breath
BPH basics
- Hyperplasia of periurethral/transitional zone prostate tissue → compresses urethra
- Driven by dihydrotestosterone (DHT) made from testosterone via 5-α-reductase
- Two components of obstruction:
- Static: increased prostate bulk (size)
- Dynamic: increased smooth muscle tone in prostate and bladder neck via receptors
Acute urinary retention = emergency
- Immediate management: bladder decompression (urethral or suprapubic catheter)
- Medication to prevent recurrence / relieve obstruction depends on timeframe:
- Fast relief (days): blockers
- Slow shrinkage (months): 5-α-reductase inhibitors
The Correct Answer (Most Likely): -Blocker (e.g., tamsulosin)
Why this is correct
Tamsulosin (also alfuzosin, silodosin; older: terazosin, doxazosin) blocks receptors in the:
- Prostate
- Bladder neck
- Prostatic urethra
➡️ Relaxation of smooth muscle improves urinary flow quickly (often within days).
High-yield details
- Tamsulosin = more uroselective ()
→ fewer systemic BP effects than nonselective blockers - Side effects to know:
- Orthostatic hypotension (less with tamsulosin than terazosin/doxazosin)
- Dizziness
- Ejaculatory dysfunction
- Intraoperative floppy iris syndrome (boards love this)
USMLE-style phrasing: “Provides rapid symptomatic relief” = blocker.
Why the Other Answers Matter (Systematic Distractor Breakdown)
Below are common distractors that show up in BPH/retention questions—plus how to eliminate them fast.
1) Finasteride / Dutasteride (5-α-reductase inhibitors)
Why it’s tempting: BPH is driven by DHT, so blocking DHT makes sense.
Why it’s wrong for immediate relief/retention:
- These drugs reduce prostate size over months, not days.
- They treat the static component (bulk), not the dynamic component (tone).
Key facts
- Mechanism: block conversion
- Effects: ↓ prostate volume, ↓ PSA (roughly 50% after ~6 months)
- Adverse effects:
- ↓ libido, erectile dysfunction
- Gynecomastia
Exam pearl:
If the vignette says very enlarged prostate or needs long-term reduction, finasteride/dutasteride becomes attractive—but not for acute relief.
2) Antimuscarinics (e.g., oxybutynin, tolterodine)
Why it’s tempting: urinary symptoms = “overactive bladder,” urgency/frequency.
Why it’s dangerous/wrong here:
- Antimuscarinics decrease detrusor contraction → can worsen urinary retention
- In obstructive symptoms with high post-void residual, they can precipitate retention.
Key facts
- Used for urge incontinence/overactive bladder
- Side effects: classic anticholinergic tox
- Dry mouth, constipation, blurry vision, confusion (esp older adults)
Board move:
If you see weak stream + hesitancy + high PVR, don’t pick antimuscarinics.
3) Bethanechol
Why it’s tempting: “Urinary retention” = stimulate bladder contraction.
When it’s correct (different vignette):
- Atonic bladder (detrusor underactivity), often:
- Postoperative urinary retention
- Diabetic autonomic neuropathy
- Spinal cord injury (context dependent)
Why it’s wrong in BPH obstruction:
- The problem isn’t weak detrusor; it’s outflow obstruction
- Pushing the detrusor against an obstruction = pain + minimal benefit, may worsen hydronephrosis over time.
Key facts
- Muscarinic agonist → ↑ detrusor contraction
- Side effects: DUMBBELSS/SLUDGE-type cholinergic effects (bradycardia, diarrhea, sweating, etc.)
4) Loop or thiazide diuretics
Why they show up: renal pharmacology crossovers; urinary symptoms involve “urine volume.”
Why they’re wrong:
- Diuretics increase urine output, which can worsen frequency/nocturia
- They do nothing to relieve obstruction and can exacerbate discomfort in retention.
Thiazide stone tie-in (high yield)
- Thiazides ↓ urinary calcium → used to prevent calcium oxalate/phosphate stones
- But that has nothing to do with BPH obstruction in the acute setting.
5) Allopurinol or potassium citrate (stone prophylaxis distractors)
These appear because the question is housed under “renal pharm & stones,” and test writers love mixing categories.
Allopurinol
- Used for uric acid stones (and gout): inhibits xanthine oxidase → ↓ uric acid
- Not a urinary retention treatment
Potassium citrate / urine alkalinization
- Alkalinizes urine → helps prevent/treat:
- Uric acid stones (increase solubility)
- Cystine stones (increase solubility)
- Again: not an obstruction fix
Board pearl:
If the stem doesn’t mention colicky flank pain, hematuria, crystals, pH, or stone history—stone prophylaxis is probably bait.
6) Opioids (or other drugs causing retention)
Sometimes the “distractor” is actually etiologic.
High-yield: drugs that can precipitate urinary retention:
- Anticholinergics (TCAs, antihistamines, antipsychotics)
- Sympathomimetics (increase sphincter tone)
- Opioids (reduce detrusor contractility)
- -agonists (increase outlet resistance)
If the vignette highlights a new medication and a distended bladder without classic BPH symptoms, think medication-induced retention rather than BPH progression.
Quick Table: Match the Drug to the Clinical Scenario
| Scenario clue | Best pharmacologic move | Why |
|---|---|---|
| Rapid improvement needed in LUTS/BPH | blocker (tamsulosin) | Relaxes prostate/bladder neck smooth muscle quickly |
| Markedly enlarged prostate, long-term shrinkage | Finasteride/dutasteride | ↓ DHT → ↓ prostate volume over months |
| Urge incontinence, normal PVR, no obstruction | Oxybutynin/tolterodine | Relaxes detrusor via antimuscarinic effect |
| Post-op urinary retention / atonic bladder | Bethanechol | Stimulates detrusor contraction |
| Recurrent calcium stones, hypercalciuria | Thiazide | ↓ urinary calcium |
| Uric acid stones or low urine pH | Allopurinol ± alkalinization | ↓ uric acid production; raise pH for solubility |
USMLE High-Yield “If They Ask This, Say That”
If they ask: “Most rapid symptomatic relief in BPH?”
- Tamsulosin (or another blocker)
If they ask: “Reduces risk of BPH progression/need for surgery?”
- Finasteride/dutasteride (especially with large prostate)
If they ask: “Major side effect that can show up intraoperatively?”
- Floppy iris syndrome → tamsulosin
If they ask: “BPH zone?”
- Transitional (periurethral) zone
(vs prostate cancer: peripheral zone)
If they ask: “Next step in acute urinary retention?”
- Catheterize first (treat emergently), then address BPH medically
Takeaway: How to Beat the Question, Not Just Answer It
In BPH with acute urinary retention, the stem is screaming outflow obstruction. The correct drug is the one that drops urethral resistance fast: an blocker. Every distractor is either:
- too slow (5-α-reductase inhibitors),
- actively harmful (antimuscarinics),
- meant for a different type of retention (bethanechol),
- or a renal pharm/stone fact-check trap.
If you can explain why each answer choice is wrong, you’re no longer “recognizing patterns”—you’re thinking like the test writer.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
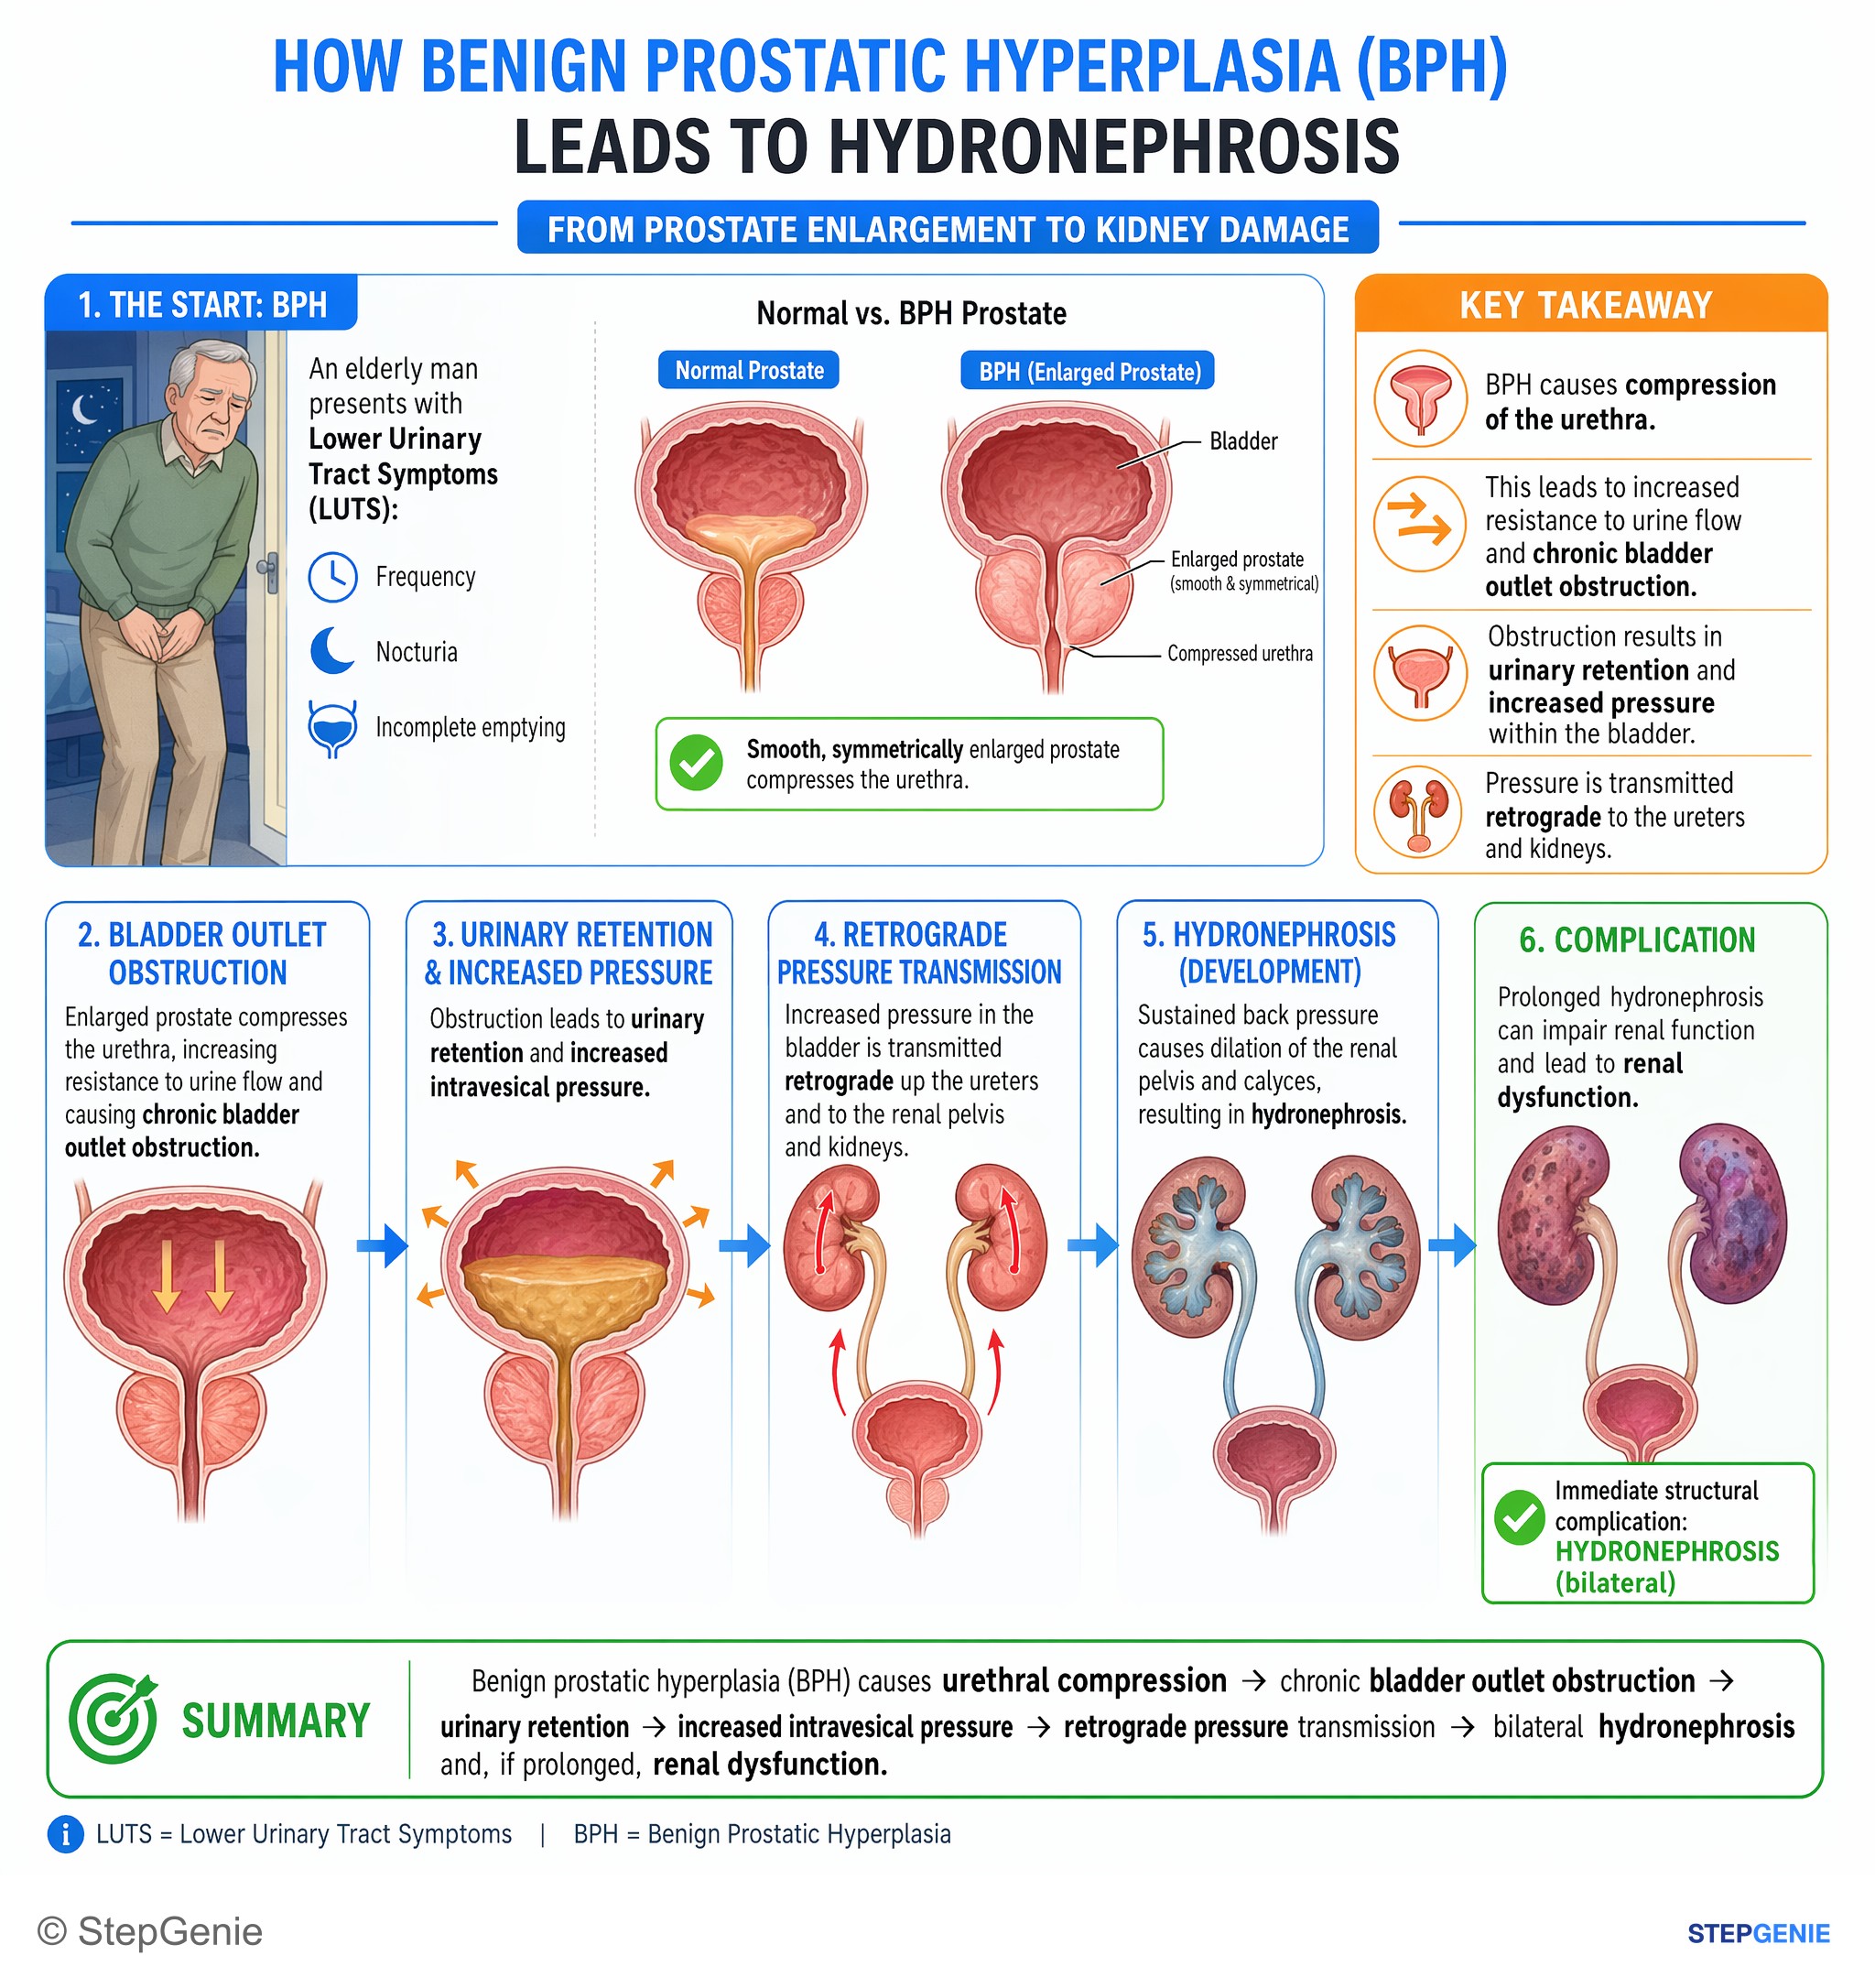
Benign prostatic hyperplasia (BPH) causes chronic bladder outlet obstruction, leading to urinary retention, increased back pressure, and…
USMLE Step 1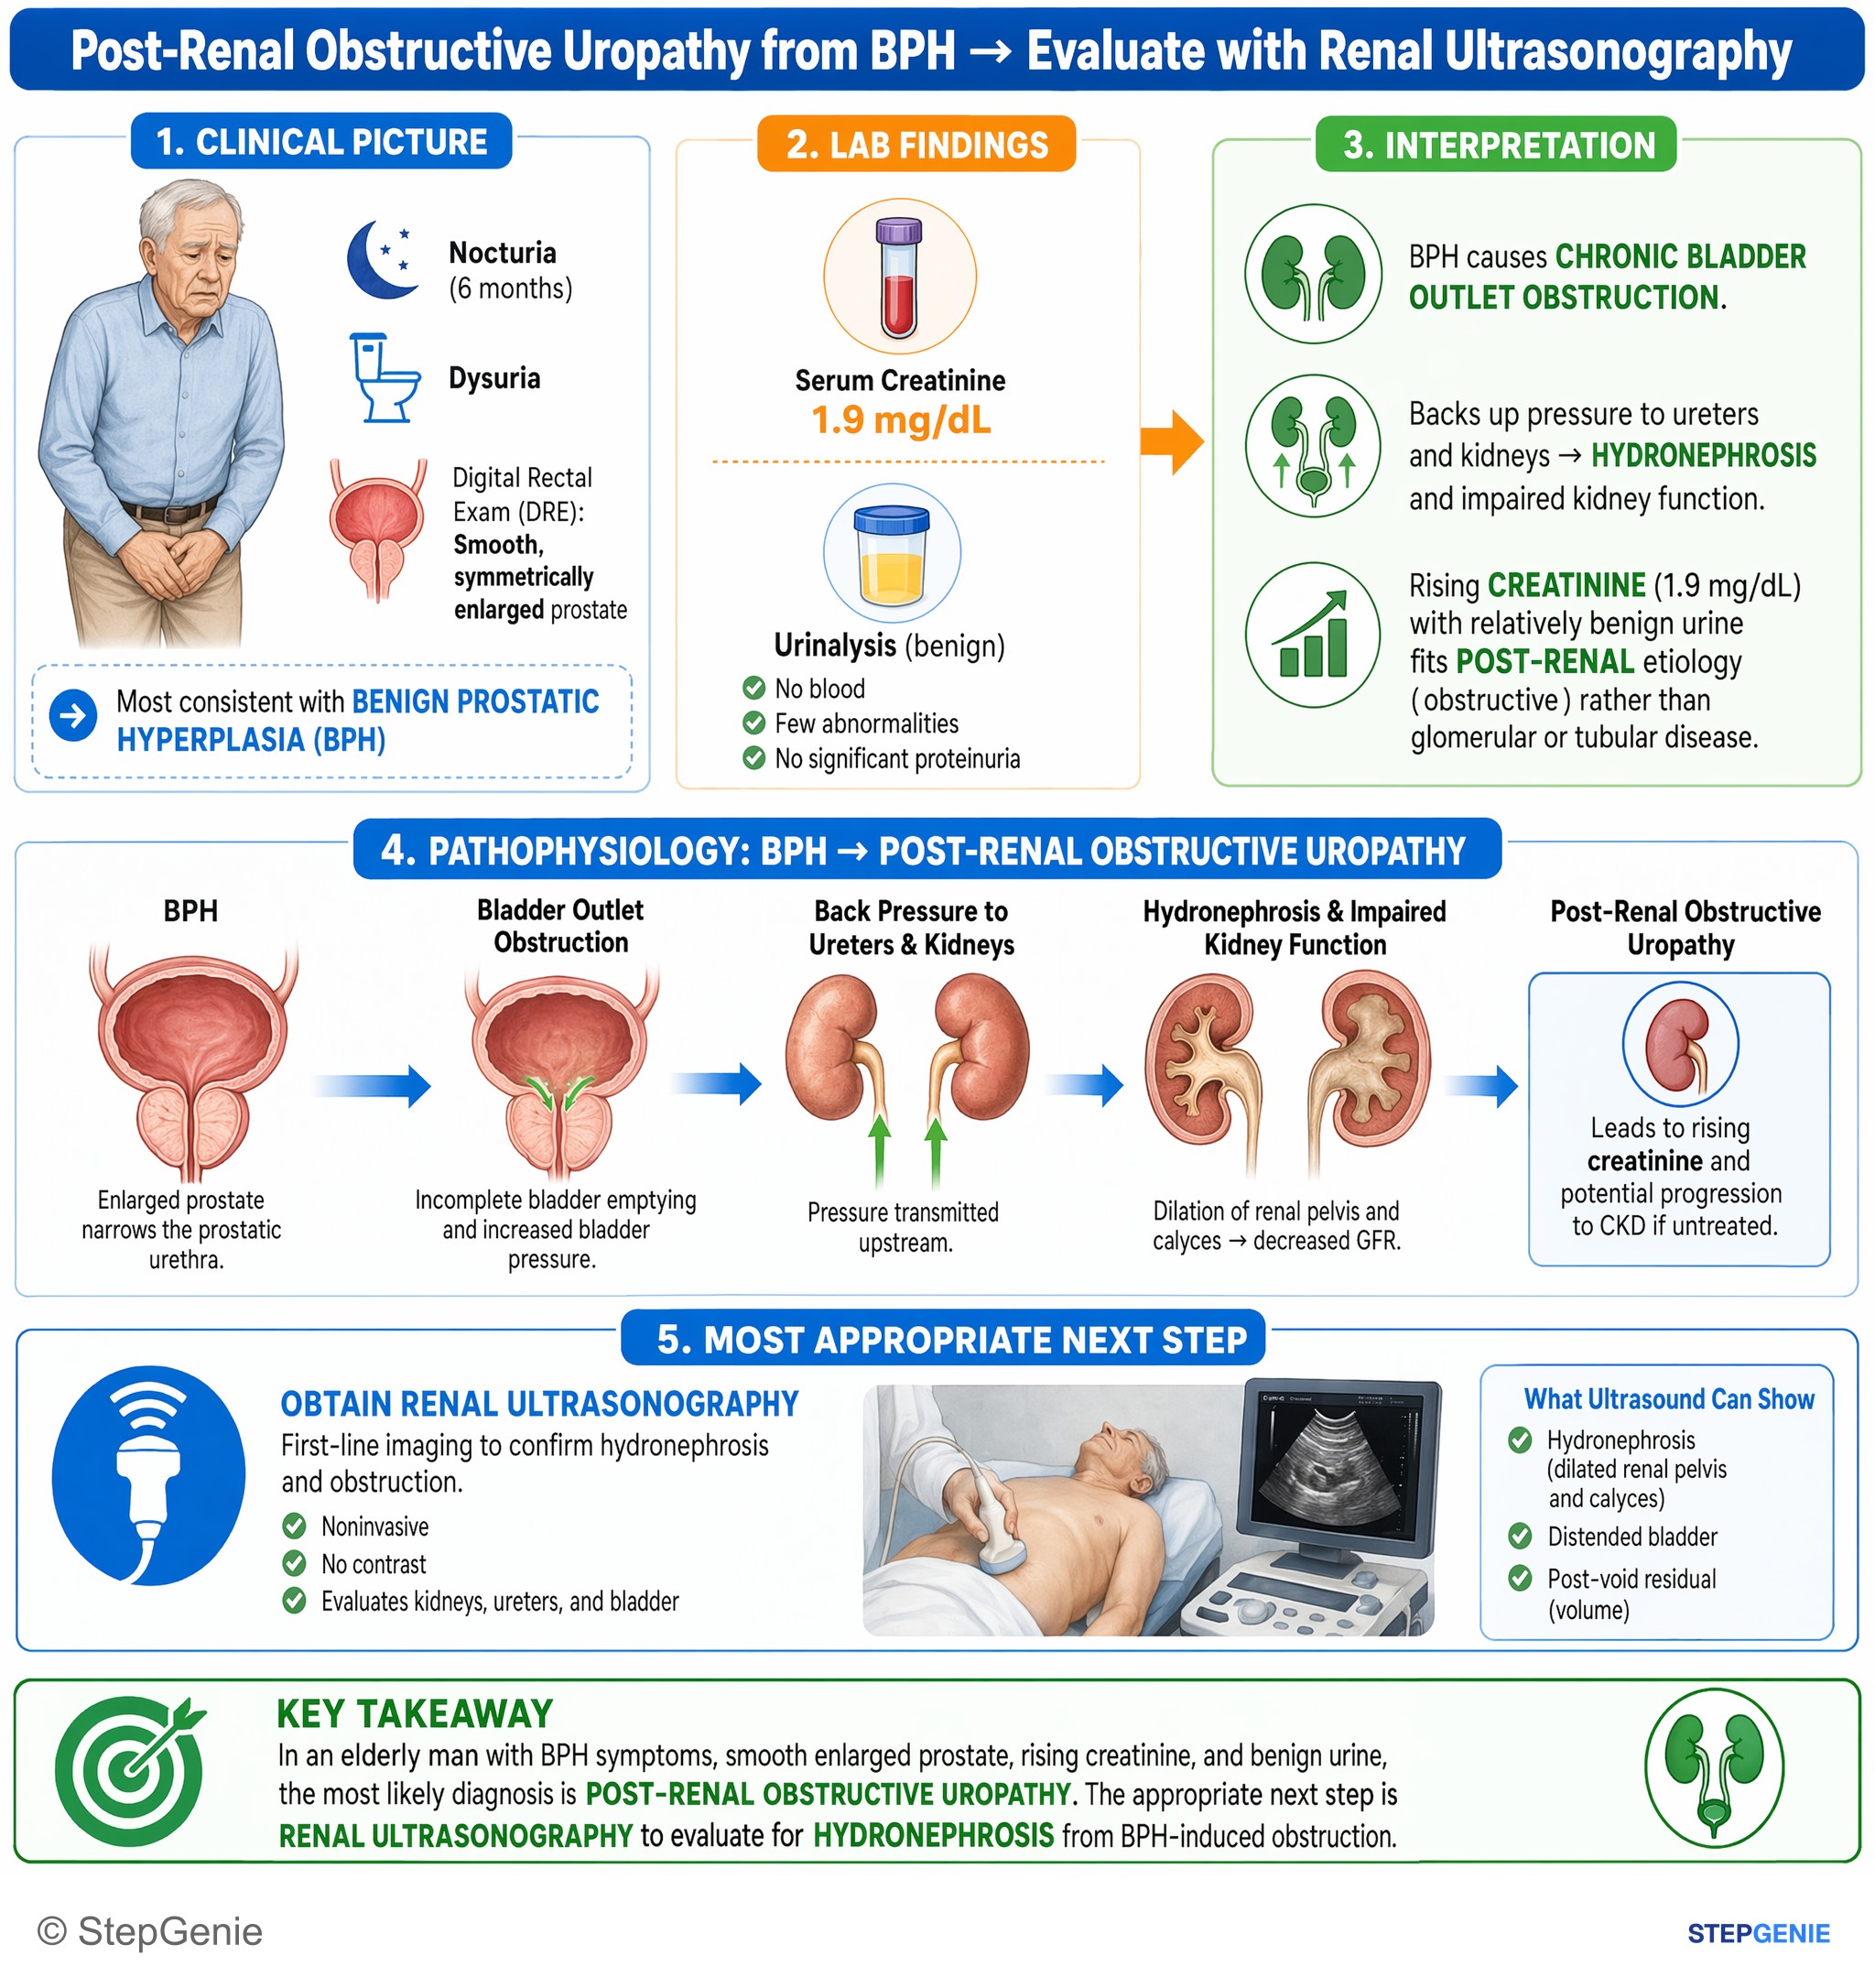
Post‑renal obstructive uropathy from BPH causing rising creatinine → evaluate for hydronephrosis with renal ultrasound.
USMLE Step 2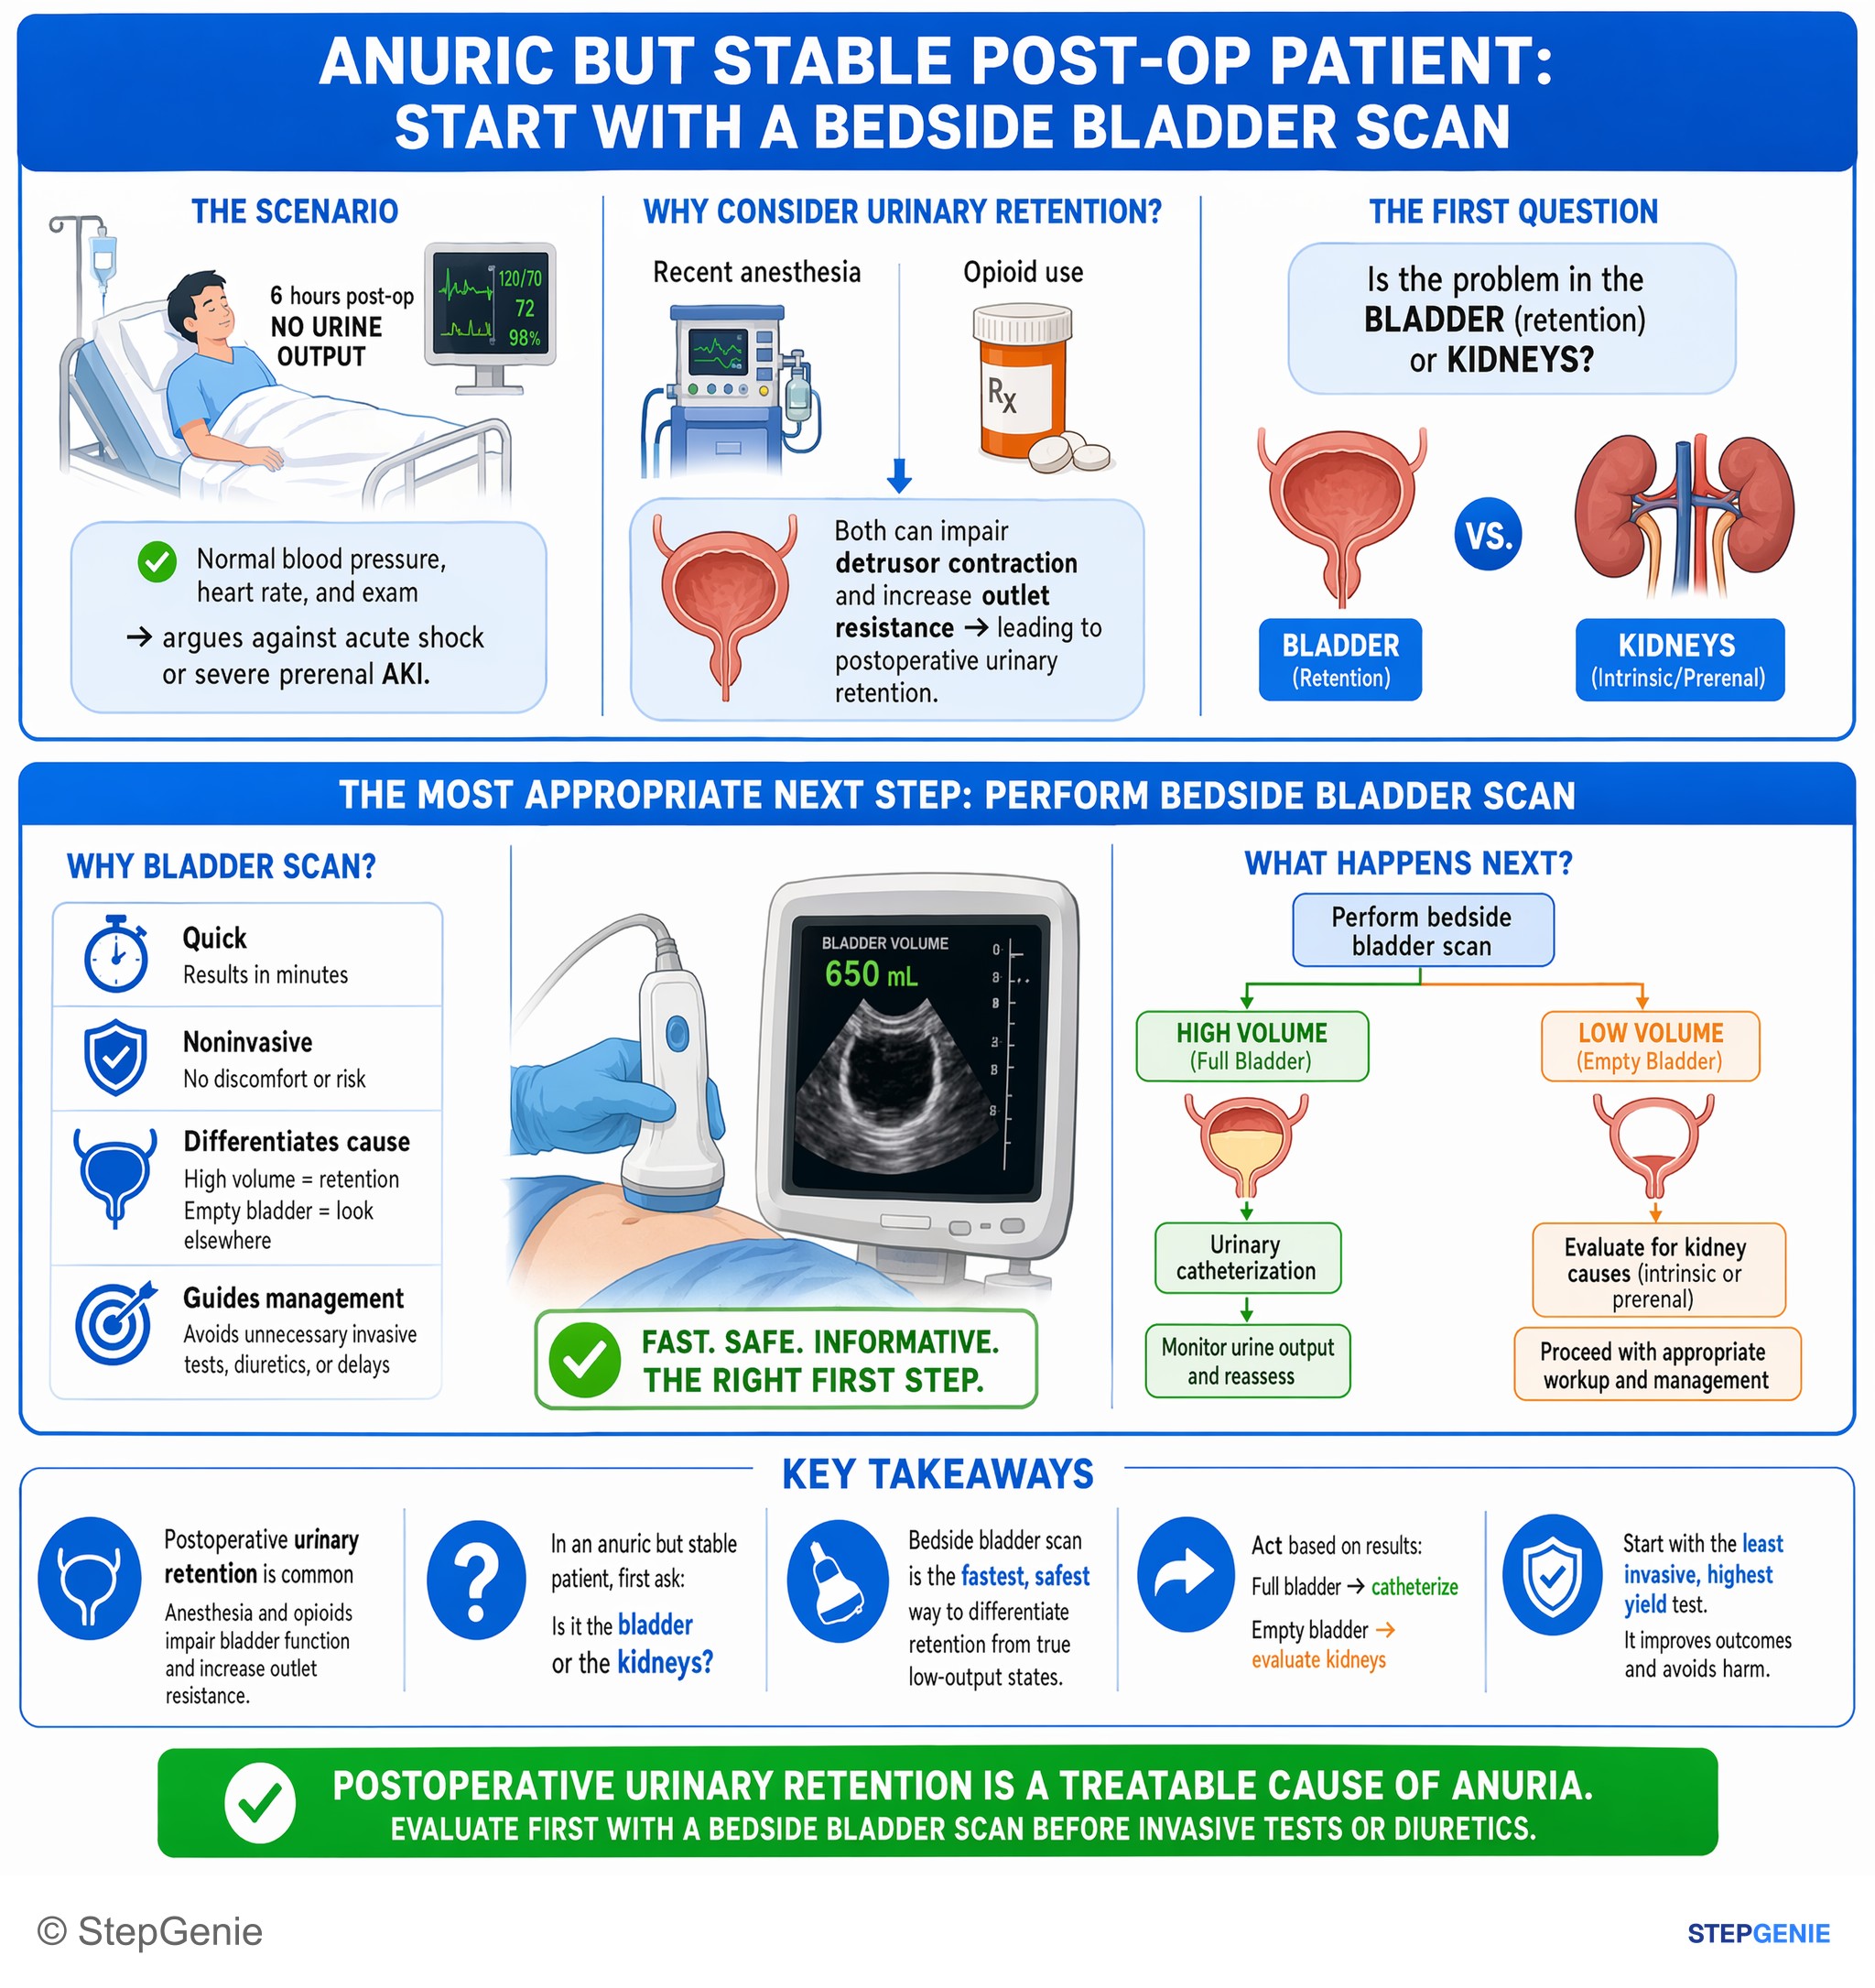
Postoperative urinary retention due to bladder outlet/functional obstruction → evaluate anuric but stable patient first with bedside…
USMLE Step 2Frequently Asked Questions
What gives the most rapid symptomatic relief for BPH causing acute urinary retention?
An α1-blocker such as tamsulosin provides the most rapid symptomatic relief. These drugs relax smooth muscle in the prostate, bladder neck, and prostatic urethra, improving urinary flow within days. In true acute urinary retention, immediate management is bladder decompression with a urethral or suprapubic catheter, while α1-blockers help relieve the obstructive dynamic component and reduce recurrence.
Why isn’t finasteride the right choice for immediate relief of urinary retention in BPH?
Finasteride is not the right drug for immediate relief because it works over months, not days. It blocks 5-α-reductase and reduces conversion of testosterone to dihydrotestosterone, which gradually shrinks prostate size. That treats the static component of BPH obstruction, but acute symptoms and retention are driven by the need for rapid relief of smooth muscle tone and immediate decompression.
Why can antimuscarinic drugs worsen urinary retention in a patient with BPH?
Antimuscarinic drugs can worsen urinary retention because they decrease detrusor contraction. In a patient with obstructive symptoms such as weak stream, hesitancy, and a high post-void residual, the problem is already impaired bladder emptying from outlet obstruction. Reducing bladder contraction further can precipitate or worsen retention, even though these drugs are used for urge incontinence and overactive bladder in other settings.
When would bethanechol be appropriate for urinary retention, and why is it wrong in BPH obstruction?
Bethanechol is appropriate when urinary retention is due to an atonic bladder, such as detrusor underactivity after surgery, diabetic autonomic neuropathy, or sometimes spinal cord injury. It is wrong in BPH because the main issue is outflow obstruction from the prostate, not weak bladder contraction. Stimulating the detrusor against an obstruction may cause pain, give minimal benefit, and can worsen hydronephrosis over time.
How do you quickly tell a BPH retention question from a kidney stone prophylaxis distractor?
A BPH retention question is signaled by hesitancy, weak stream, nocturia, incomplete emptying, a smooth enlarged prostate, and a high post-void residual. Stone prophylaxis answers like allopurinol or potassium citrate are bait unless the vignette mentions flank pain, hematuria, crystals, urine pH, or stone history. Those therapies are for uric acid or cystine stone prevention, not relief of bladder outlet obstruction.