Boerhaave syndrome is one of those “don’t-miss” GI emergencies that Q-banks love because it punishes vague thinking. The vignette can look like pancreatitis, MI, pneumonia, or even a simple Mallory-Weiss tear—until you notice the key clue: sudden severe chest pain after forceful vomiting with signs of systemic toxicity. Let’s break it down like a real question stem, then make every distractor earn its keep.
Tag: GI > Esophageal & Gastric Disorders
The Clinical Vignette (Classic Q-bank Style)
A 52-year-old man presents with sudden, severe retrosternal chest pain after several episodes of forceful vomiting following heavy alcohol intake. He is diaphoretic and ill-appearing. Vitals: T 38.6°C, HR 118, BP 92/58, RR 26, O₂ sat 92% on room air. Exam shows subcutaneous emphysema over the neck and upper chest. Lungs: decreased breath sounds on the left. Labs show leukocytosis. Chest X-ray shows a left pleural effusion and mediastinal air.
Most likely diagnosis?
➡️ Boerhaave syndrome (transmural esophageal rupture)
Why the Correct Answer Is Boerhaave Syndrome
The “can’t-ignore” triad (and how it shows up on exams)
Boerhaave is a full-thickness perforation of the esophagus due to a sudden rise in intraesophageal pressure (classically after forceful emesis).
High-yield clues:
- Severe chest pain after vomiting (often abrupt, “tearing,” radiating to back)
- Subcutaneous emphysema (crepitus in neck/chest)
- Systemic toxicity: fever, leukocytosis, tachycardia, hypotension → mediastinitis/sepsis
- Imaging hints:
- Pneumomediastinum
- Left-sided pleural effusion (classically)
- Possible hydropneumothorax
- “Mackler triad” (vomiting + chest pain + subQ emphysema) is classic but not always complete
Pathophysiology you should actually remember
- Forceful vomiting causes a pressure spike → rupture typically in the distal esophagus, often left posterolateral.
- Leakage of gastric contents → chemical + bacterial mediastinitis → rapid decompensation.
Best diagnostic test (Step-friendly nuance)
- If stable: CT chest with water-soluble oral contrast or water-soluble contrast esophagram (e.g., Gastrografin).
- Avoid barium initially (can inflame mediastinum if it leaks), though barium may be used if water-soluble study is negative but suspicion remains high.
Immediate management (what to do “right now”)
Boerhaave is a surgical emergency.
Initial steps:
- NPO
- IV fluids, analgesia
- Broad-spectrum IV antibiotics covering oral/GI flora (including anaerobes)
- Surgical consultation urgently
Depending on timing/extent: operative repair vs endoscopic stenting + drainage.
USMLE pearl: mortality rises sharply with delay; “toxic after vomiting” should trigger the diagnosis fast.
The Answer Choices: Why Every Distractor Is Wrong (and What It Really Describes)
Below is a high-yield “distractor map” that Q-banks repeatedly reuse.
Distractor 1: Mallory–Weiss Tear
What it is: Mucosal tear at the gastroesophageal junction due to retching.
| Feature | Mallory–Weiss | Boerhaave |
|---|---|---|
| Depth | Mucosal | Transmural |
| Key symptom | Hematemesis after retching | Chest pain after vomiting |
| Toxic? | Usually no | Yes—mediastinitis/sepsis |
| Imaging | No free air | Pneumomediastinum, effusions |
Why it’s tempting: Both follow vomiting and alcohol binge.
How to rule it out fast: Mallory-Weiss = bleeding; Boerhaave = air leak + toxic.
Distractor 2: Spontaneous Pneumothorax
What it is: Air in pleural space, often in tall thin young men (primary) or COPD (secondary).
Why it’s tempting: Sudden chest pain + dyspnea, decreased breath sounds.
Why it’s wrong here:
- The stem gives vomiting trigger, subcutaneous emphysema, and mediastinal air with systemic illness.
- Boerhaave can cause pleural findings (effusion/hydropneumothorax), especially on the left.
Board move: If the vignette screams “GI leak,” don’t anchor on a pure lung diagnosis.
Distractor 3: Acute Pancreatitis
What it is: Inflammation of the pancreas, commonly from gallstones or alcohol.
Why it’s tempting: Alcohol history + vomiting + epigastric pain that can radiate to the back.
Why it’s wrong here:
- Pancreatitis pain is typically epigastric, not abrupt retrosternal tearing chest pain.
- Pancreatitis doesn’t classically cause pneumomediastinum or crepitus in the neck.
- You’d expect elevated lipase/amylase (often included in Q-stems).
USMLE tip: Vomiting is common in many conditions—what’s unique is air escaping from the esophagus.
Distractor 4: Myocardial Infarction (ACS)
What it is: Ischemic myocardial injury causing chest pain, diaphoresis, nausea.
Why it’s tempting: Older patient, diaphoresis, chest pain, hypotension.
Why it’s wrong here:
- The chest pain is immediately after forceful emesis (mechanical trigger).
- You’re given subcutaneous emphysema and mediastinal/pleural findings—these are not ACS features.
- ACS doesn’t cause pneumomediastinum.
Exam strategy: ACS is common—Q-banks make it a distractor to test whether you can recognize extra-cardiac red flags.
Distractor 5: Aortic Dissection
What it is: Intimal tear → false lumen; classically “tearing” chest pain radiating to back.
Why it’s tempting: “Tearing pain” + radiation to back + shock.
Why it’s wrong here:
- Dissection classically has pulse deficits, blood pressure differential, or widened mediastinum (not subQ emphysema).
- The trigger in this vignette is vomiting, and the findings include air leak signs (crepitus, pneumomediastinum).
Memory hook: Dissection = “blood tracking”; Boerhaave = “air + gastric contents tracking.”
Distractor 6: Esophageal Variceal Bleeding
What it is: Portal HTN → dilated submucosal veins → massive hematemesis.
Why it’s tempting: Alcohol use can imply cirrhosis.
Why it’s wrong here:
- Varices present with painless hematemesis and hemodynamic instability.
- The stem emphasizes severe chest pain, fever, subQ emphysema—points you away from a pure bleeding diagnosis.
Distractor 7: GERD / Esophagitis
What it is: Reflux causing burning chest pain, worse after meals/lying down.
Why it’s tempting: Chest discomfort can mimic cardiac pain.
Why it’s wrong here:
- GERD doesn’t cause acute toxicity, fever, hypotension, or mediastinal air.
- Boerhaave is sudden and catastrophic, not chronic and positional.
Rapid-Fire USMLE High-Yield Takeaways
Boerhaave in one line
Forceful vomiting → transmural esophageal rupture → pneumomediastinum + sepsis/mediastinitis.
Must-know associations
- Alcohol binge / overeating → vomiting → rupture
- Left pleural effusion and mediastinal air are classic imaging clues
- Crepitus on exam is a huge hint
Tests and “don’t do this”
- Prefer water-soluble contrast imaging first
- Avoid blind endoscopy if perforation suspected (can worsen tear)
Management priorities
- NPO + IV fluids + broad-spectrum antibiotics
- Urgent surgical consult (time-sensitive)
Quick Comparison Table: Esophageal “Vomiting-Related” Lesions
| Condition | Trigger | Depth | Key presentation | Big clue |
|---|---|---|---|---|
| Mallory–Weiss | Retching/vomiting | Mucosal | Hematemesis | Bleeding without toxicity |
| Boerhaave | Forceful vomiting | Transmural | Chest pain + toxicity | SubQ emphysema, pneumomediastinum |
| Varices | Portal HTN | Vascular rupture | Massive hematemesis | Cirrhosis signs |
| GERD | Meals/lying down | Mucosal irritation | Burning pain | Chronic, non-toxic |
Bottom Line (What Q-banks Want)
When vomiting is followed by sudden severe chest pain plus subcutaneous emphysema or pneumomediastinum, the test is asking for Boerhaave syndrome—and the next step mindset is life-threatening perforation until proven otherwise.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
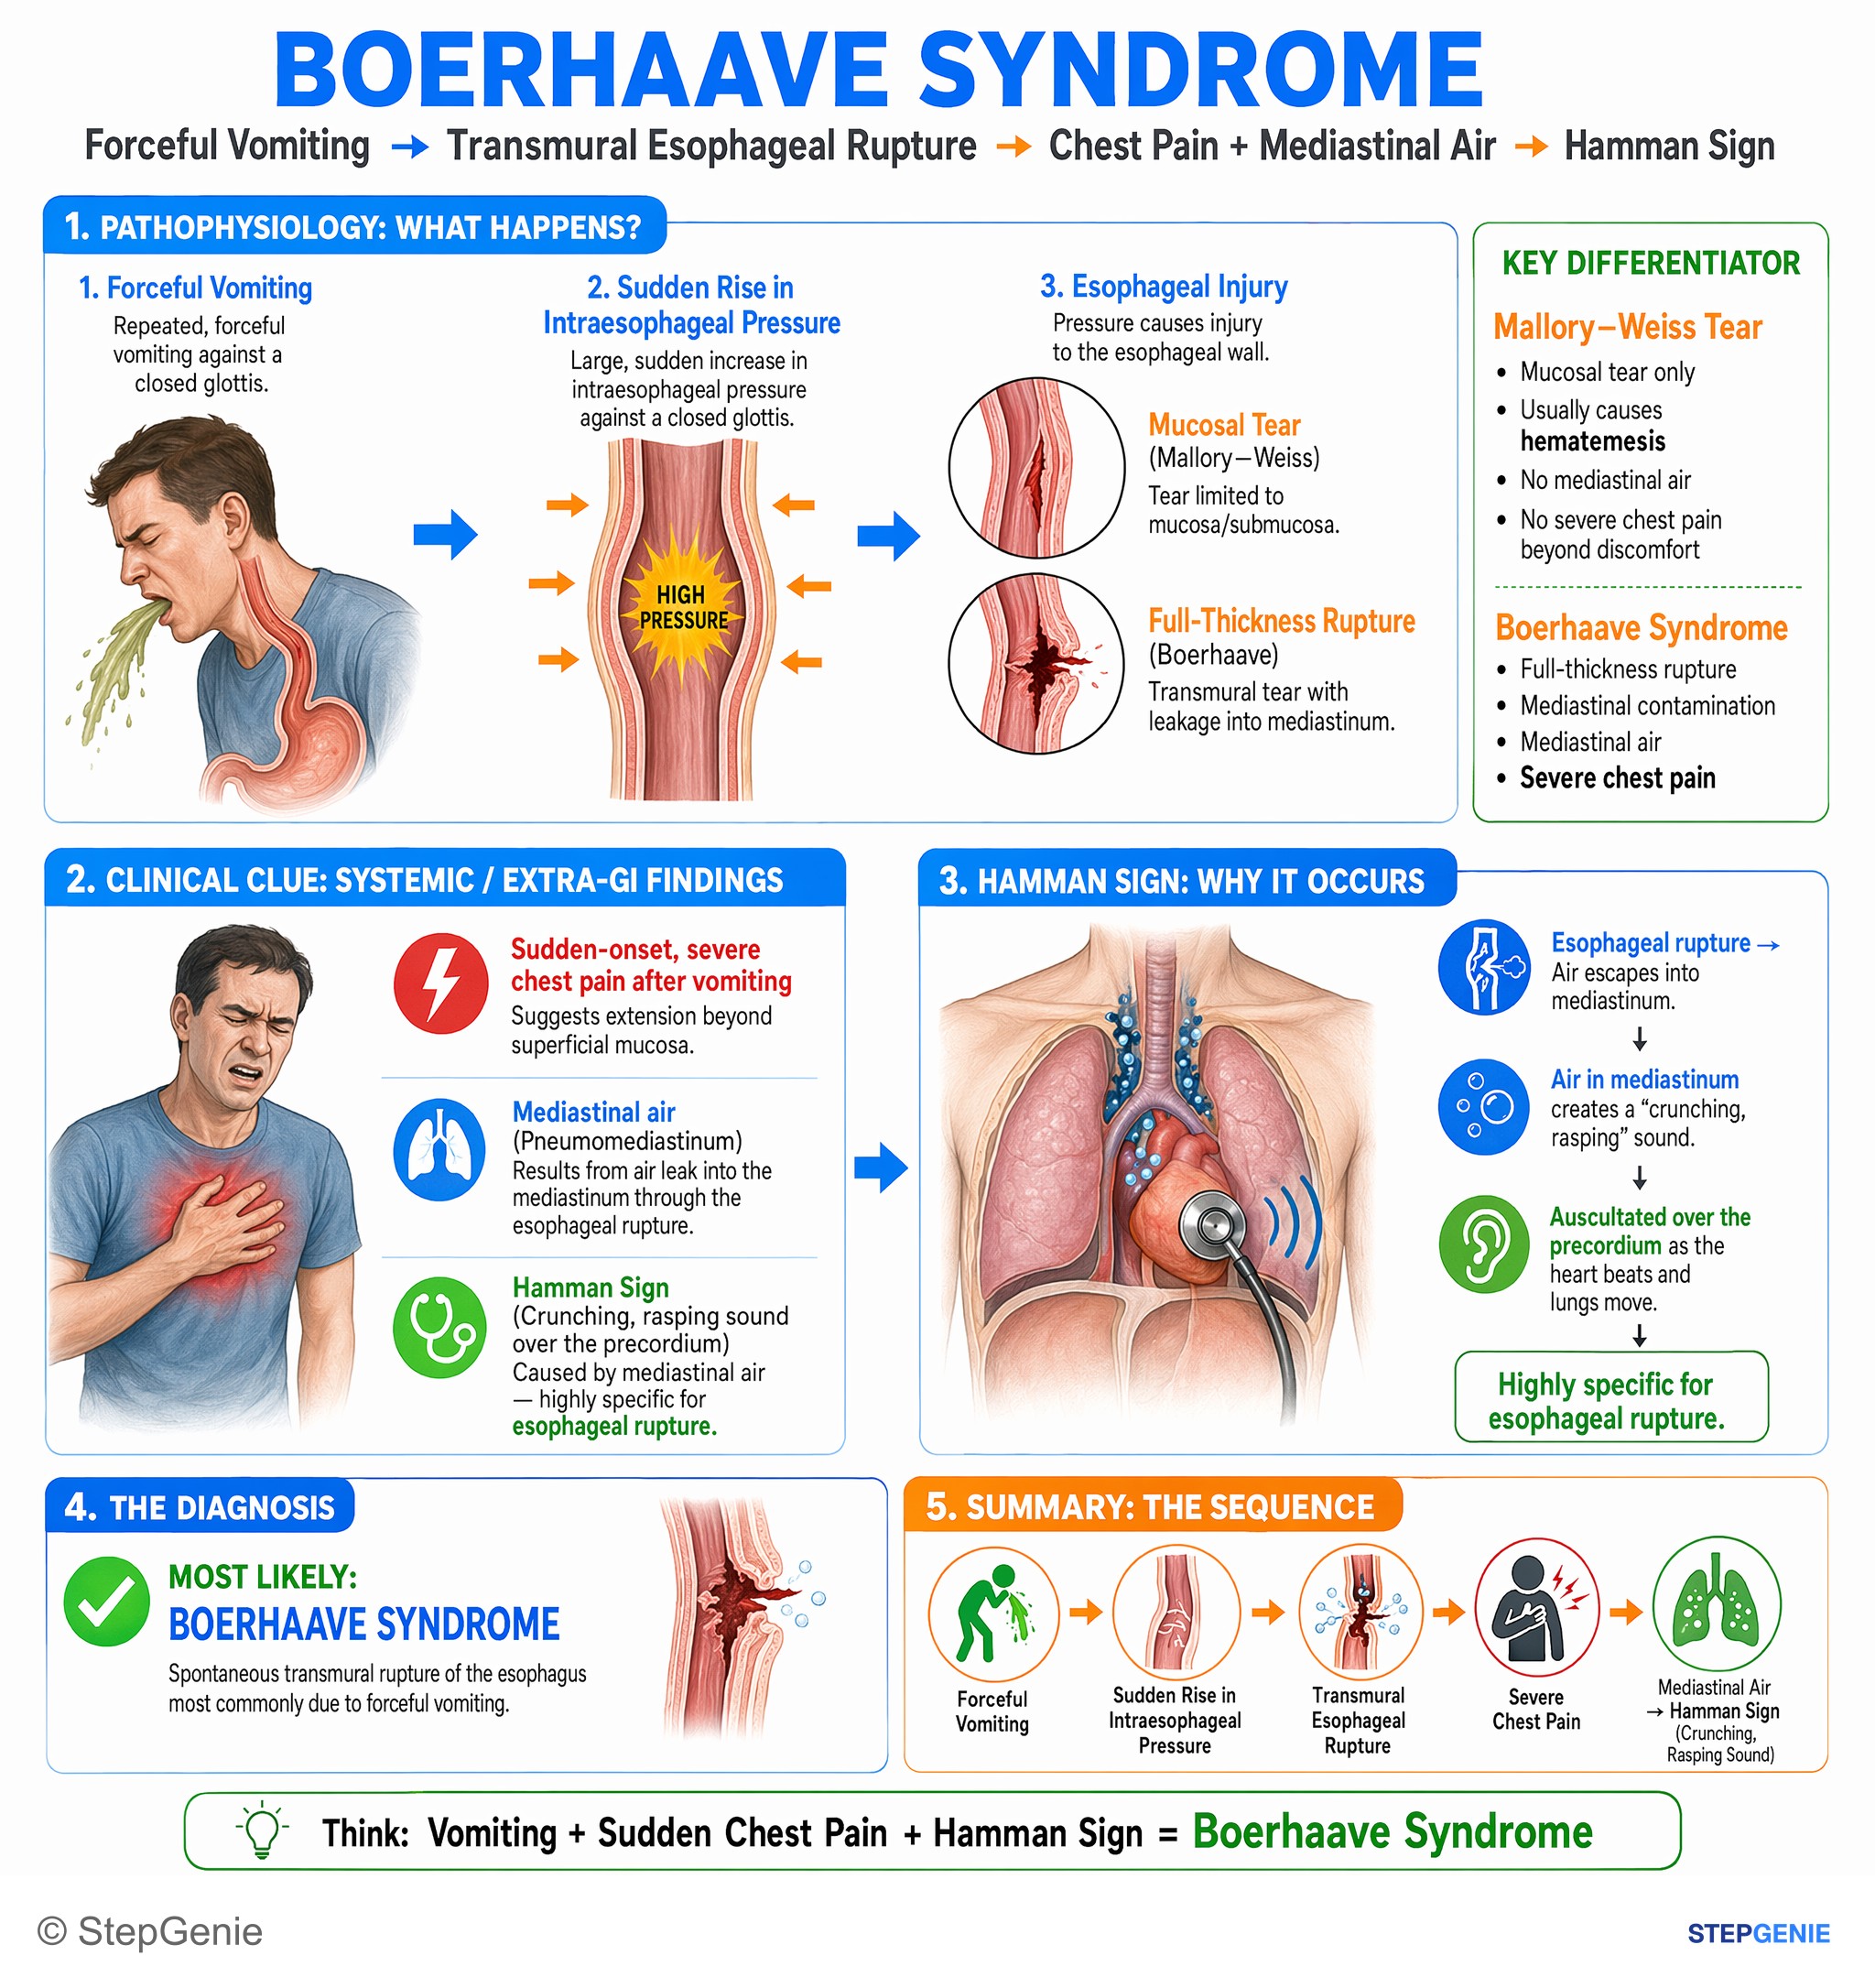
Boerhaave syndrome: forceful vomiting → spontaneous transmural esophageal rupture → chest pain + mediastinal air causing Hamman sign…
USMLE Step 1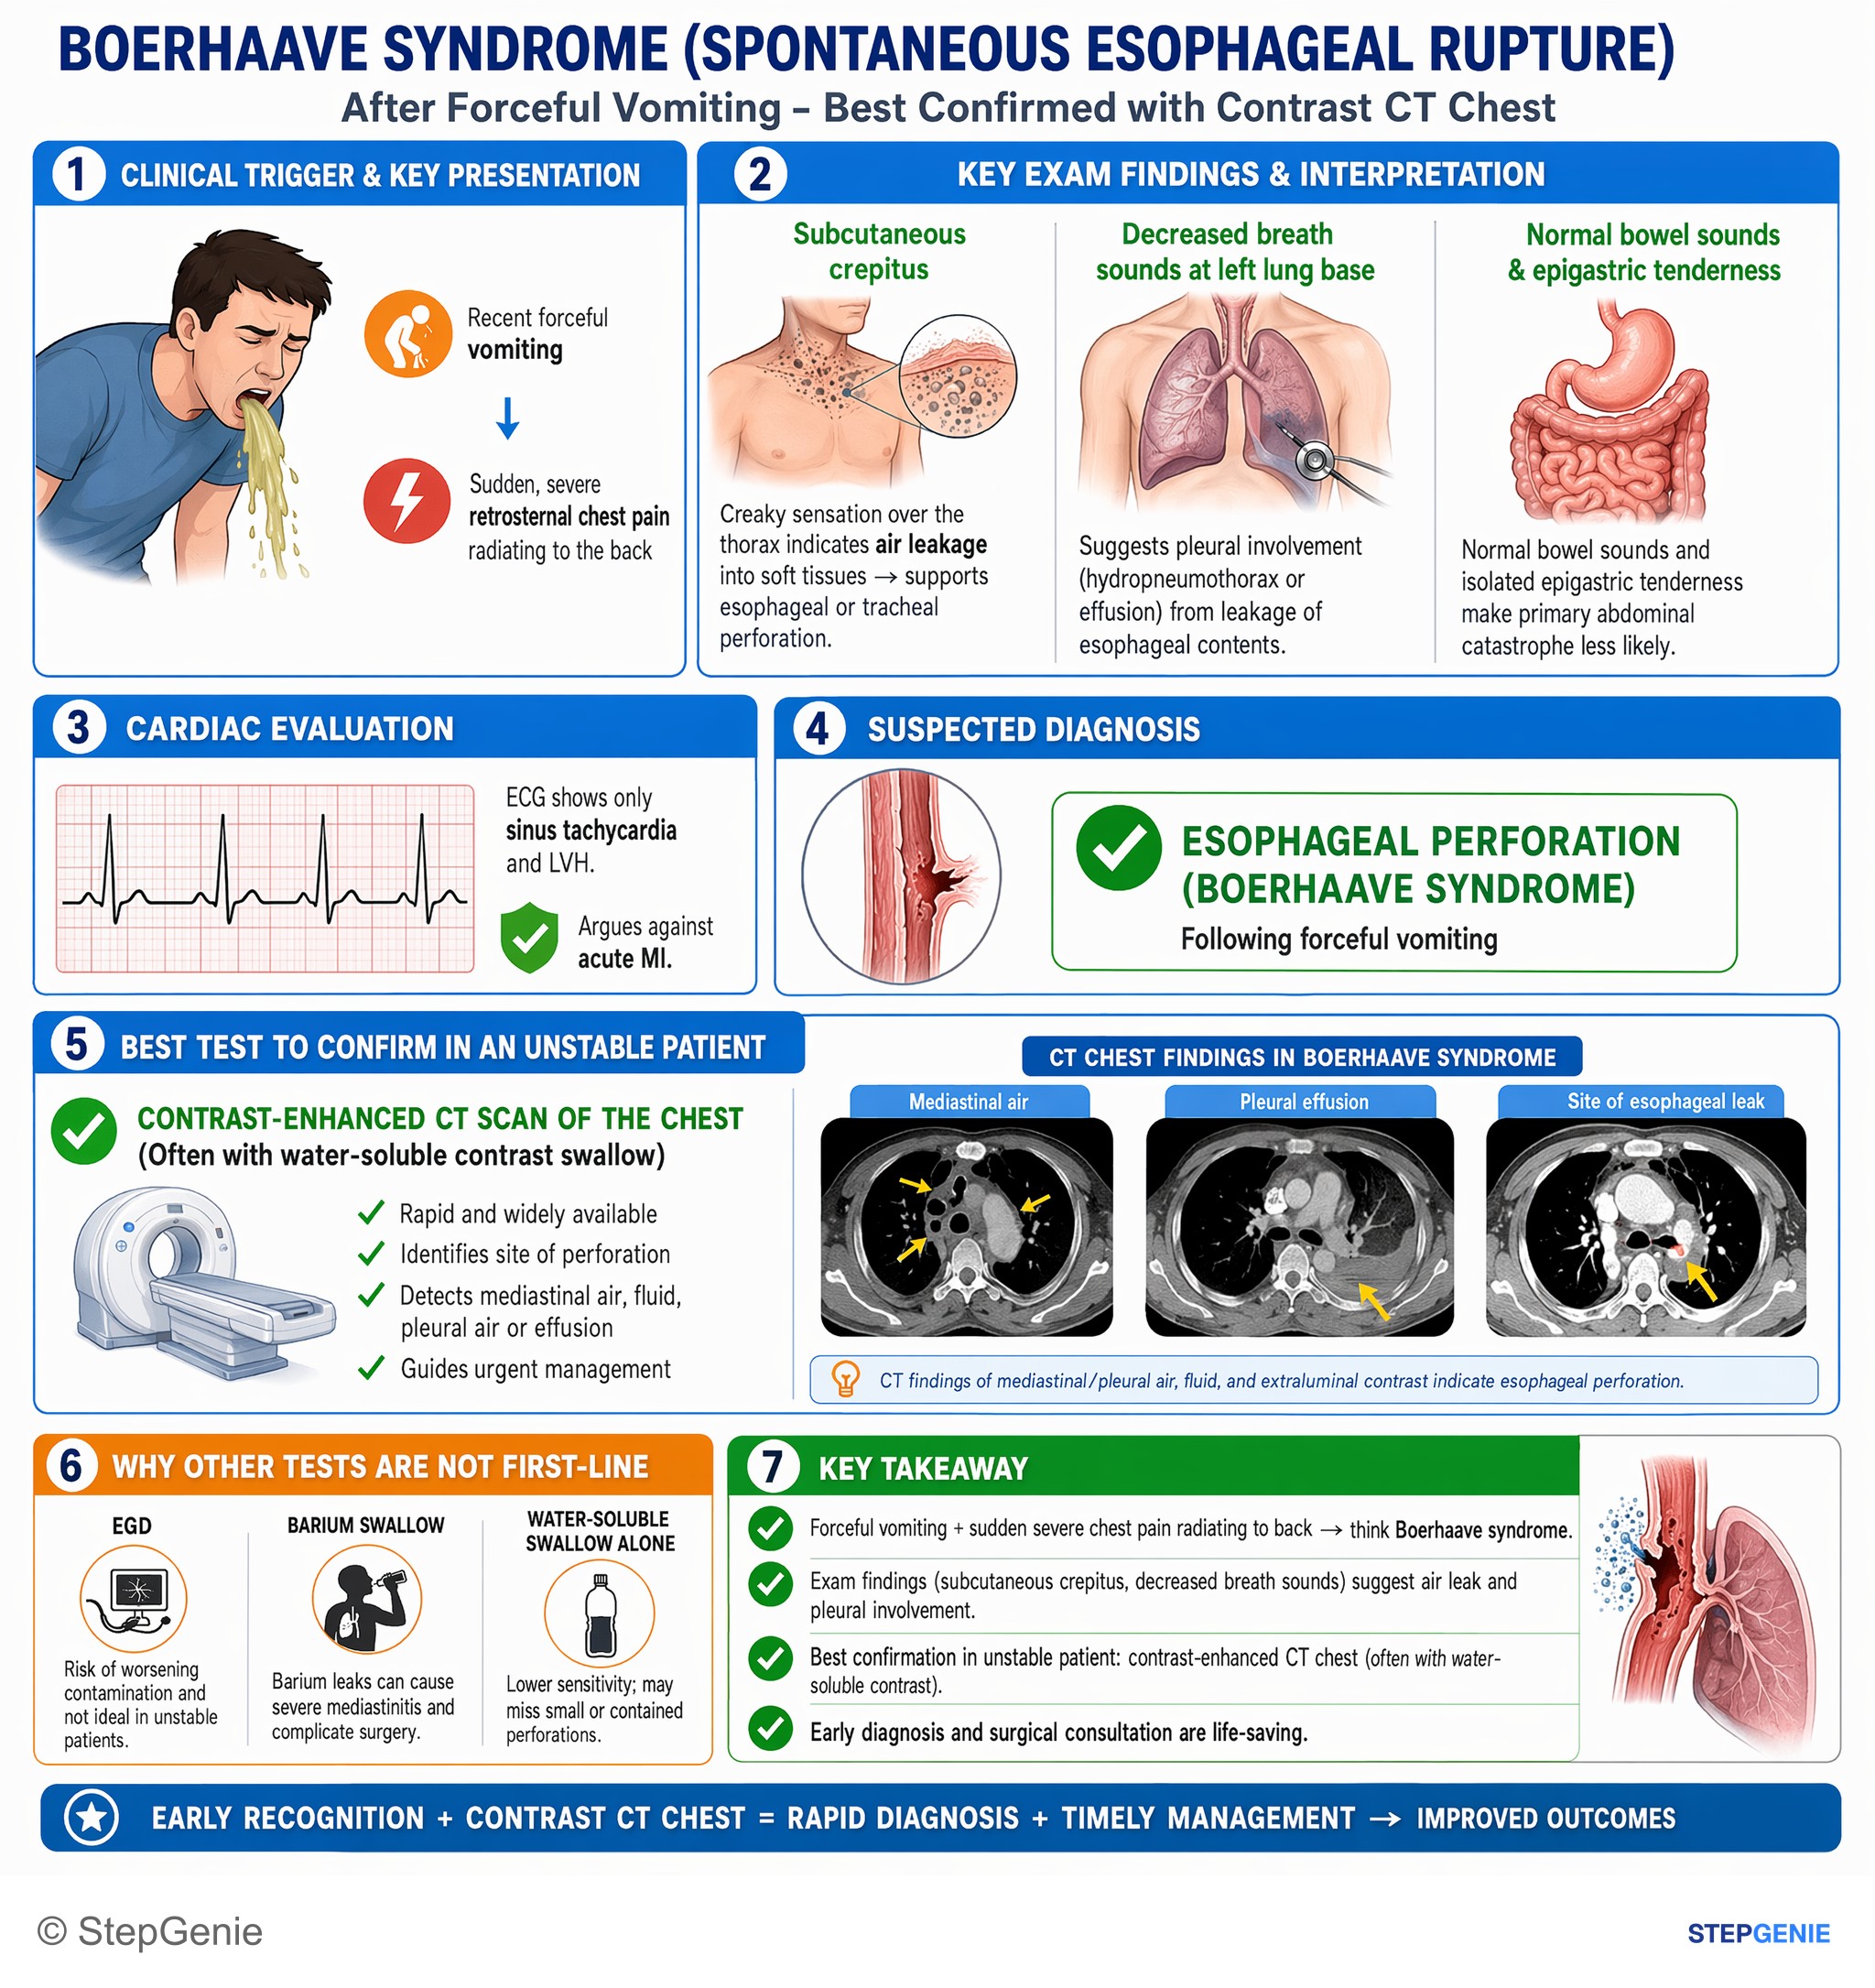
Esophageal perforation (Boerhaave syndrome) after forceful vomiting; best confirmed with contrast CT chest showing mediastinal/pleural air…
USMLE Step 2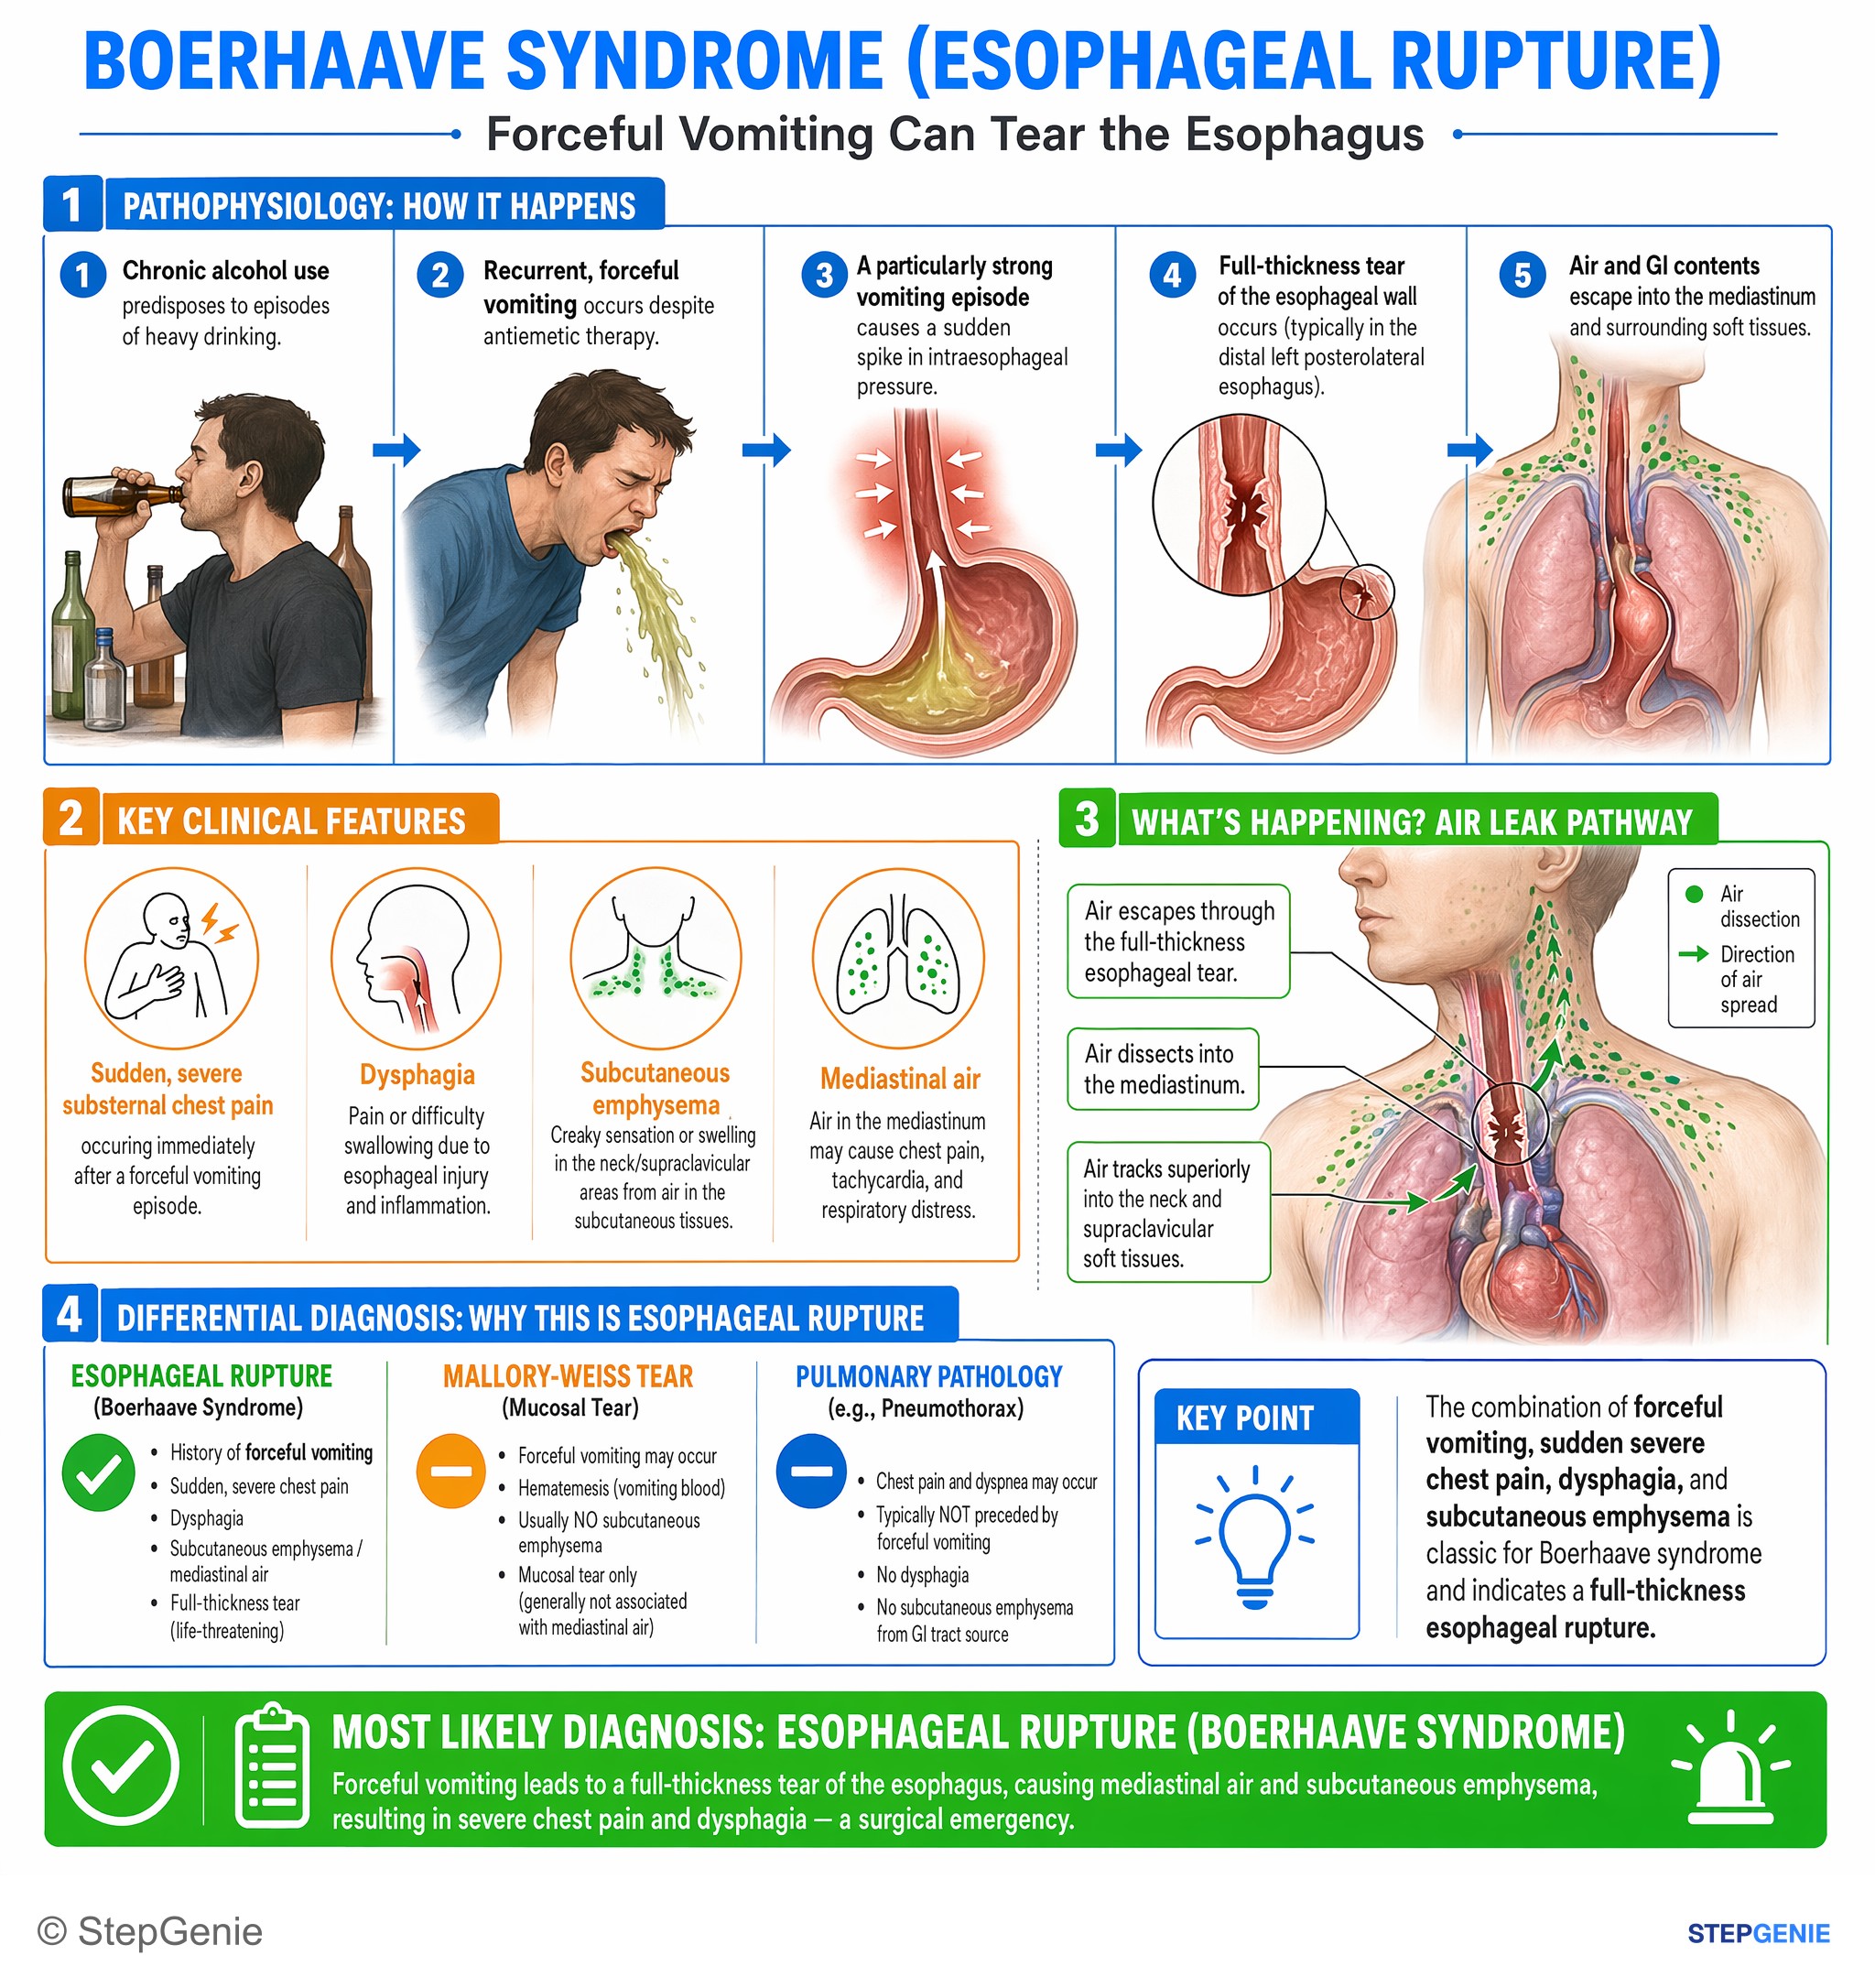
Boerhaave syndrome (esophageal rupture) from forceful vomiting → severe chest pain + dysphagia + subcutaneous emphysema/mediastinal air.
USMLE Step 2Frequently Asked Questions
What is the classic presentation of Boerhaave syndrome on a question stem?
The classic presentation is sudden severe retrosternal chest pain after forceful vomiting, often with subcutaneous emphysema and systemic toxicity. Typical clues include fever, leukocytosis, tachycardia, hypotension, mediastinal air, and a left-sided pleural effusion. Vomiting plus chest pain plus crepitus is the classic Mackler triad, although all three findings are not always present.
Why does forceful vomiting cause Boerhaave syndrome?
Forceful vomiting causes Boerhaave syndrome by creating a sudden rise in intraesophageal pressure that leads to a full-thickness esophageal rupture. The tear usually occurs in the distal esophagus, often on the left posterolateral side. Once the esophagus ruptures, gastric contents leak into the mediastinum, causing chemical and bacterial mediastinitis with rapid clinical decompensation and possible sepsis.
How do you tell Boerhaave syndrome from a Mallory-Weiss tear?
Boerhaave syndrome is a transmural esophageal rupture that causes chest pain, air leak findings, and toxicity, whereas a Mallory-Weiss tear is a mucosal tear that usually causes hematemesis after retching. Mallory-Weiss is mainly a bleeding problem without free air, while Boerhaave produces pneumomediastinum, pleural effusions, subcutaneous emphysema, and signs of mediastinitis or sepsis.
What is the best diagnostic test for suspected Boerhaave syndrome?
If the patient is stable, the best diagnostic test is CT chest with water-soluble oral contrast or a water-soluble contrast esophagram. Barium should be avoided initially because leakage can inflame the mediastinum. However, barium may be used later if the water-soluble study is negative but clinical suspicion for Boerhaave syndrome remains high.
What should you do right away when Boerhaave syndrome is suspected?
Treat Boerhaave syndrome as a surgical emergency and start immediate supportive and definitive management. Initial steps are NPO, IV fluids, analgesia, broad-spectrum IV antibiotics covering oral and gastrointestinal flora including anaerobes, and urgent surgical consultation. Mortality rises sharply with delay, so a toxic patient after vomiting should trigger rapid recognition and action.