Barrett esophagus is one of those “Step classics” that shows up in a deceptively simple way: a reflux story, a biopsy buzzword, and then a question that tests whether you can separate risk factors, histology, and management from a pile of tempting distractors. Let’s walk through a Q-bank-style vignette and then dismantle every answer choice like you’re reviewing with a friend after a long block.
The Vignette (GI > Esophageal & Gastric Disorders)
A 52-year-old man presents with years of heartburn and regurgitation, worse after meals and when lying down. He has central obesity and uses OTC antacids most days. He denies weight loss but notes intermittent dysphagia to solids over the past few months. Upper endoscopy shows salmon-colored mucosa extending proximally from the gastroesophageal junction. Biopsies reveal intestinal-type columnar epithelium with goblet cells.
Question: Which of the following is the most important long-term complication of this condition?
Answer choices
A. Squamous cell carcinoma of the esophagus
B. Esophageal adenocarcinoma
C. Esophageal varices
D. Mallory-Weiss tear
E. Achalasia due to loss of myenteric plexus neurons
The Correct Answer: B. Esophageal adenocarcinoma
Barrett esophagus is metaplasia of the distal esophagus: nonciliated, mucin-secreting columnar epithelium with goblet cells replaces normal stratified squamous epithelium in response to chronic acid exposure.
Why this is the key complication
- Barrett esophagus is a premalignant condition that increases risk of esophageal adenocarcinoma.
- The classic progression you should have in your head:
- GERD → Barrett (intestinal metaplasia) → dysplasia → adenocarcinoma
- Most adenocarcinomas arise in the distal esophagus (near the GE junction), matching the typical Barrett location.
High-yield associations (USMLE-style)
- Risk factors for Barrett/adenocarcinoma:
- Chronic GERD
- Obesity
- Male sex
- White race
- Smoking
- Endoscopic clue: “Salmon-colored” tongues of mucosa extending upward from GE junction
- Histology clue: goblet cells = intestinal metaplasia (the money phrase)
Why Every Other Answer Choice Is Wrong (and what it’s trying to test)
A. Squamous cell carcinoma of the esophagus
Why it’s tempting: “Cancer of the esophagus” is true, but wrong type.
High-yield distinction:
- Squamous cell carcinoma is linked to:
- Alcohol
- Tobacco
- Very hot beverages
- Achalasia
- Plummer-Vinson syndrome
- More common in the mid-esophagus (classically), and worldwide is historically the most common type.
Barrett specifically increases risk of: adenocarcinoma, not squamous cell carcinoma.
C. Esophageal varices
Why it’s tempting: Students see “esophagus” + serious bleeding and jump to varices.
Reality check:
- Varices result from portal hypertension, usually due to cirrhosis.
- They occur at the lower esophagus due to porto-systemic anastomoses (left gastric vein ↔ azygos system).
This vignette has no portal HTN clues:
- No cirrhosis stigmata (jaundice, ascites, spider angiomas)
- No hematemesis/melena
- Endoscopy description is classic for Barrett, not varices (varices look like dilated submucosal veins)
D. Mallory-Weiss tear
Why it’s tempting: Another common esophageal bleeding entity.
What it actually is:
- A mucosal laceration at the gastroesophageal junction from forceful vomiting/retching
- Presents with hematemesis after repeated vomiting
- Common associations: alcohol binge, bulimia, gastroenteritis
Why it doesn’t fit:
- Barrett is about chronic reflux and metaplasia, not acute vomiting-induced mucosal tears.
E. Achalasia due to loss of myenteric plexus neurons
Why it’s tempting: Dysphagia is in the stem.
But the mechanism and symptoms differ:
- Achalasia = failure of LES relaxation + loss of peristalsis due to degeneration of Auerbach (myenteric) plexus
- Dysphagia to solids and liquids from the start (not just solids)
- Barium swallow: bird-beak appearance
- Complication: increased risk of squamous cell carcinoma, not Barrett-type adenocarcinoma
In this stem:
- Chronic heartburn + regurgitation + endoscopic Barrett findings → this is GERD → Barrett, not achalasia.
“Dysphagia” in Barrett/GERD: A subtle board-style point
The stem includes intermittent dysphagia to solids, which can signal:
- Peptic stricture from chronic GERD (benign narrowing)
- Or a red flag for malignancy if progressive + weight loss
Boards like to see whether you:
- Recognize GERD/Barrett as the primary diagnosis, and
- Don’t prematurely switch diagnoses just because “dysphagia” appears
Mini-Table: Quick Differentiation (High Yield)
| Condition | Key risk factors | Hallmark clue | Main complication tested |
|---|---|---|---|
| Barrett esophagus | Chronic GERD, obesity, male, smoking | Salmon mucosa + goblet cells | Adenocarcinoma |
| Esophageal adenocarcinoma | Barrett, GERD | Distal esophagus mass | Progressive dysphagia, weight loss |
| Esophageal SCC | Alcohol, smoking, hot beverages, achalasia | Classically mid-esophagus | Local invasion, metastasis |
| Varices | Cirrhosis/portal HTN | Massive painless hematemesis | Exsanguination risk |
| Mallory-Weiss | Retching/vomiting | Hematemesis after vomiting | Usually self-limited bleeding |
| Achalasia | Idiopathic, Chagas | Bird-beak, dysphagia solids + liquids | Aspiration, SCC risk |
USMLE Management Pearls You’re Expected to Know
Even when the question is about complications, Step writers love management-adjacent details.
For GERD symptoms
- Lifestyle: weight loss, elevate head of bed, avoid late meals, trigger foods
- Medications: PPIs are first-line for frequent symptoms
For Barrett esophagus
- Confirm with endoscopy + biopsy (must show intestinal metaplasia with goblet cells)
- Surveillance endoscopy depending on dysplasia status (broad concept > exact intervals for Step)
- If high-grade dysplasia: endoscopic eradication therapy (e.g., radiofrequency ablation, endoscopic mucosal resection)
- PPI therapy is commonly used to reduce acid exposure
Test-taking anchor: Barrett = metaplasia due to reflux; the big fear is adenocarcinoma.
Rapid-Fire Takeaways (What to remember on exam day)
- Barrett = intestinal metaplasia (goblet cells) in distal esophagus due to GERD.
- The major long-term risk is esophageal adenocarcinoma.
- SCC is linked to alcohol/tobacco/hot liquids/achalasia, not Barrett.
- Varices = portal HTN; Mallory-Weiss = retching; Achalasia = dysphagia to solids + liquids and bird-beak.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
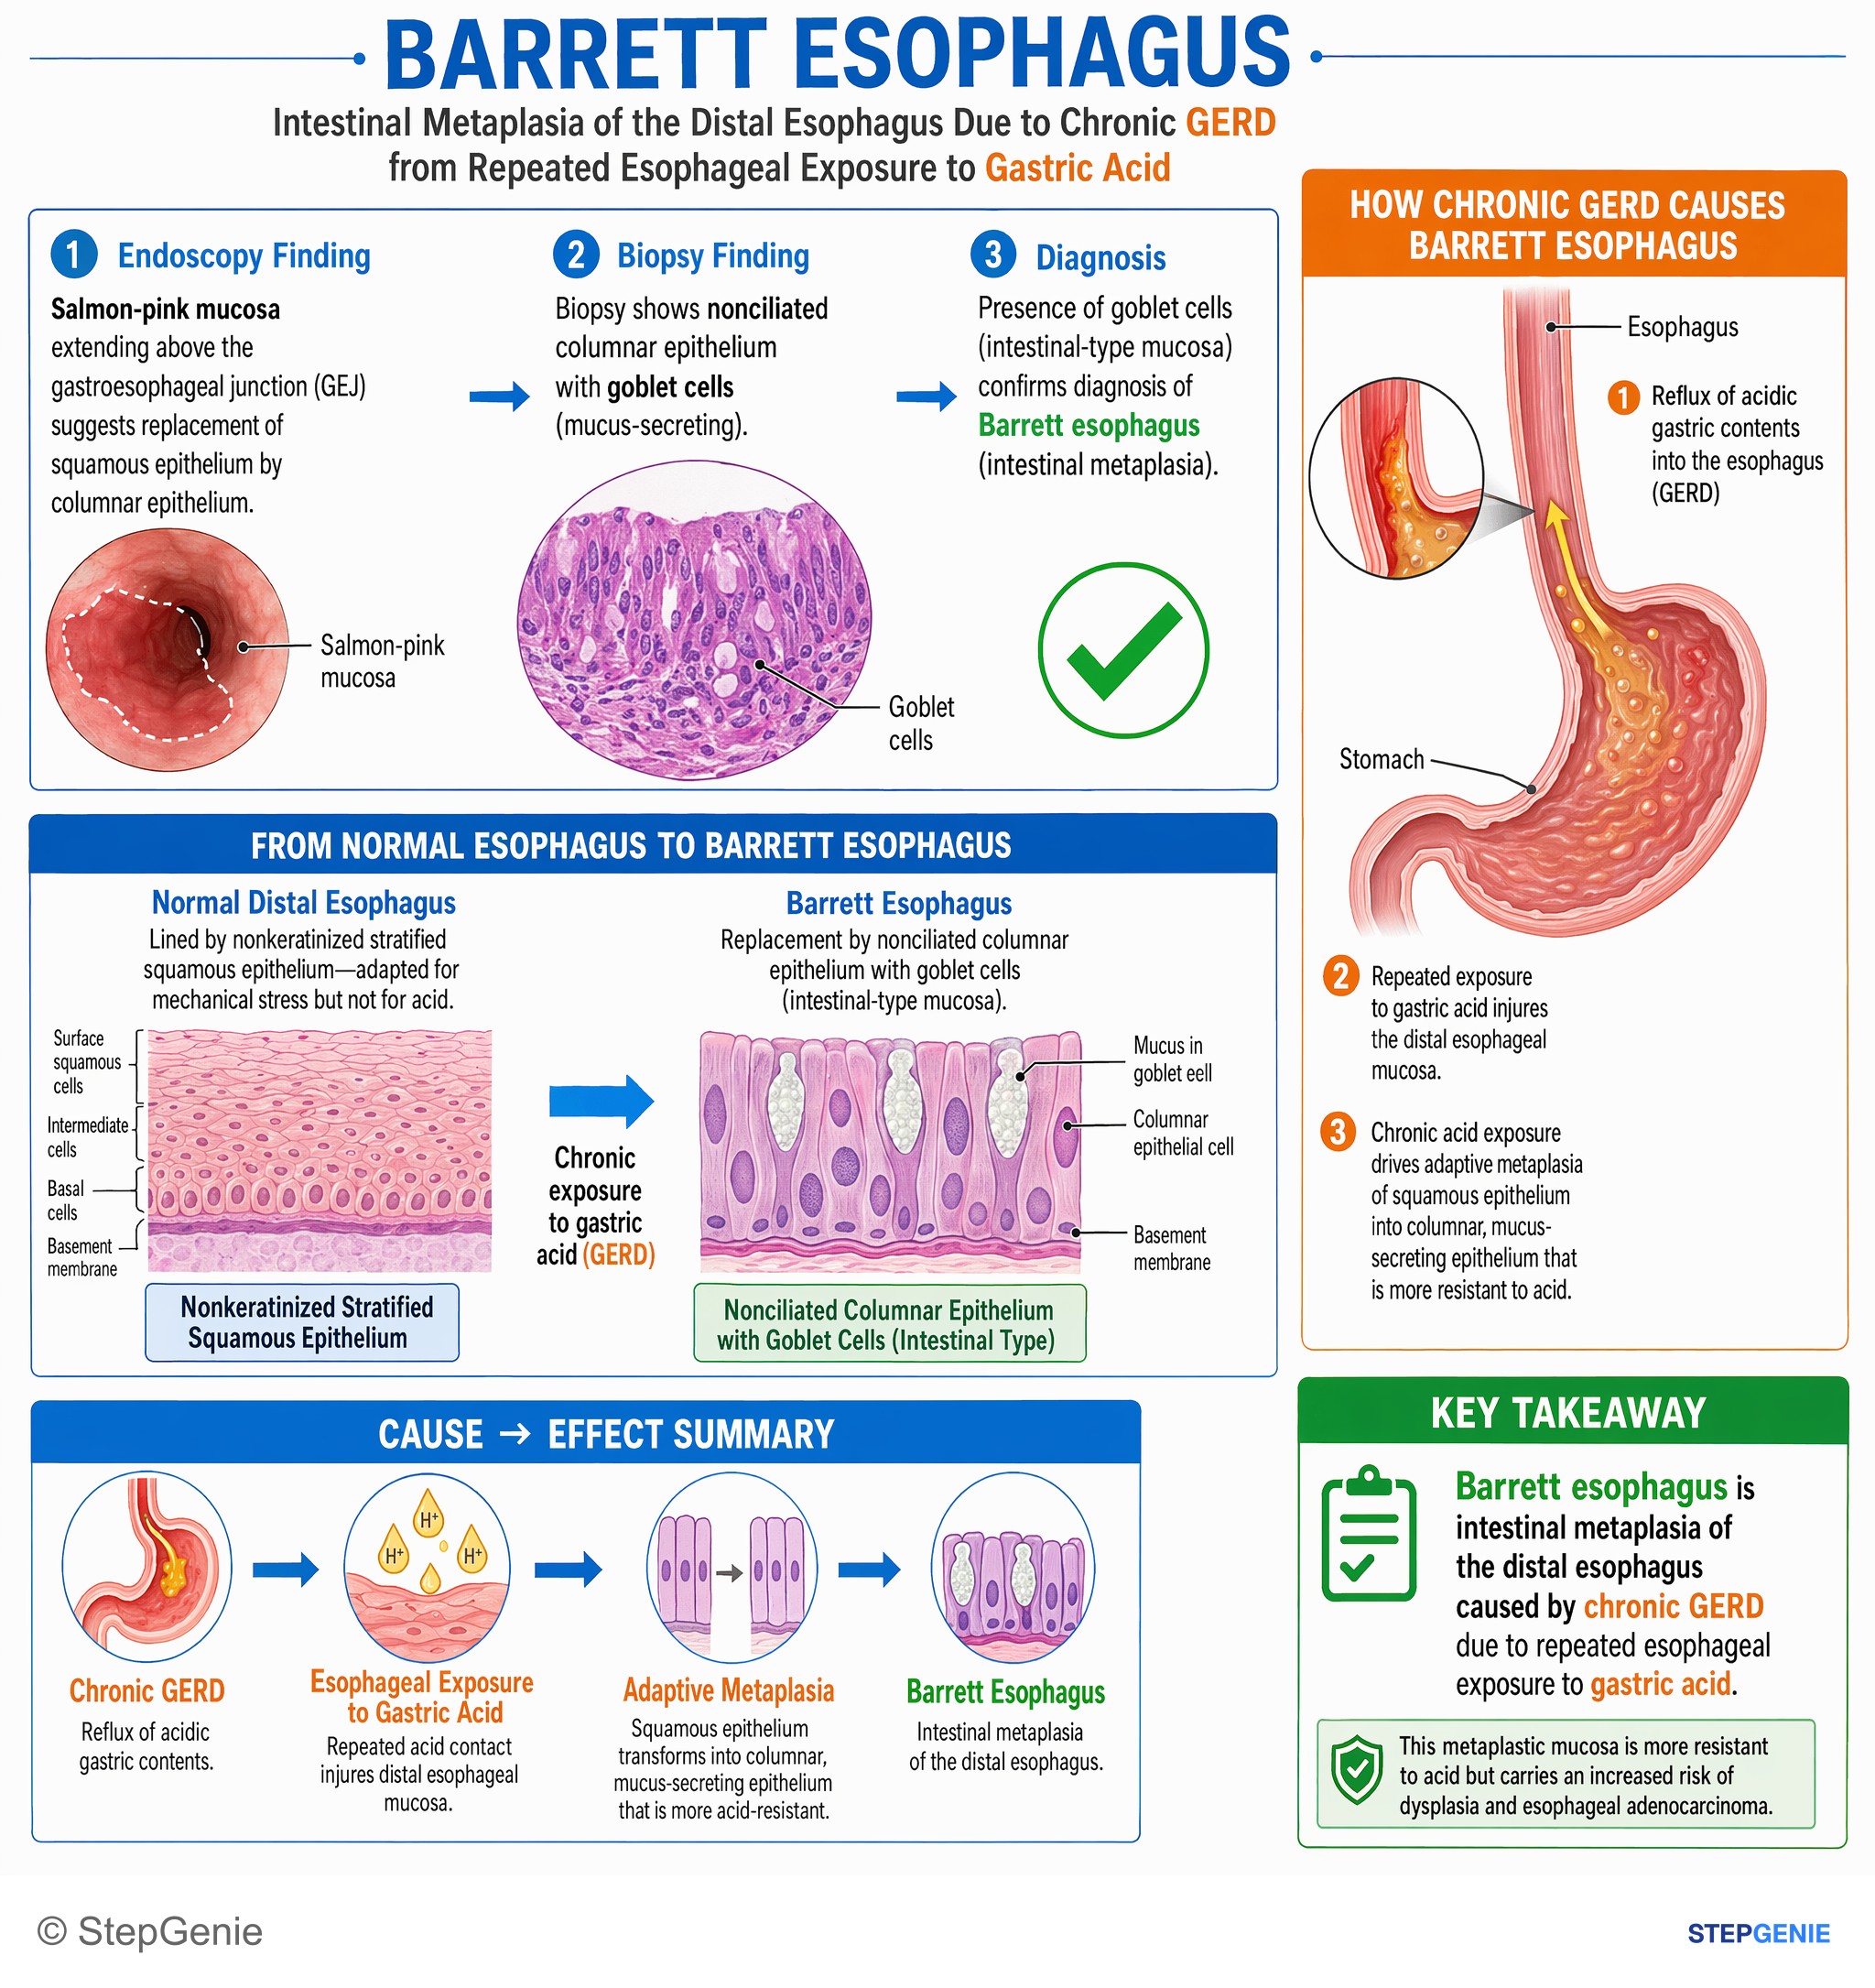
Barrett esophagus: intestinal metaplasia of distal esophagus due to chronic GERD from repeated esophageal exposure to gastric acid.
USMLE Step 1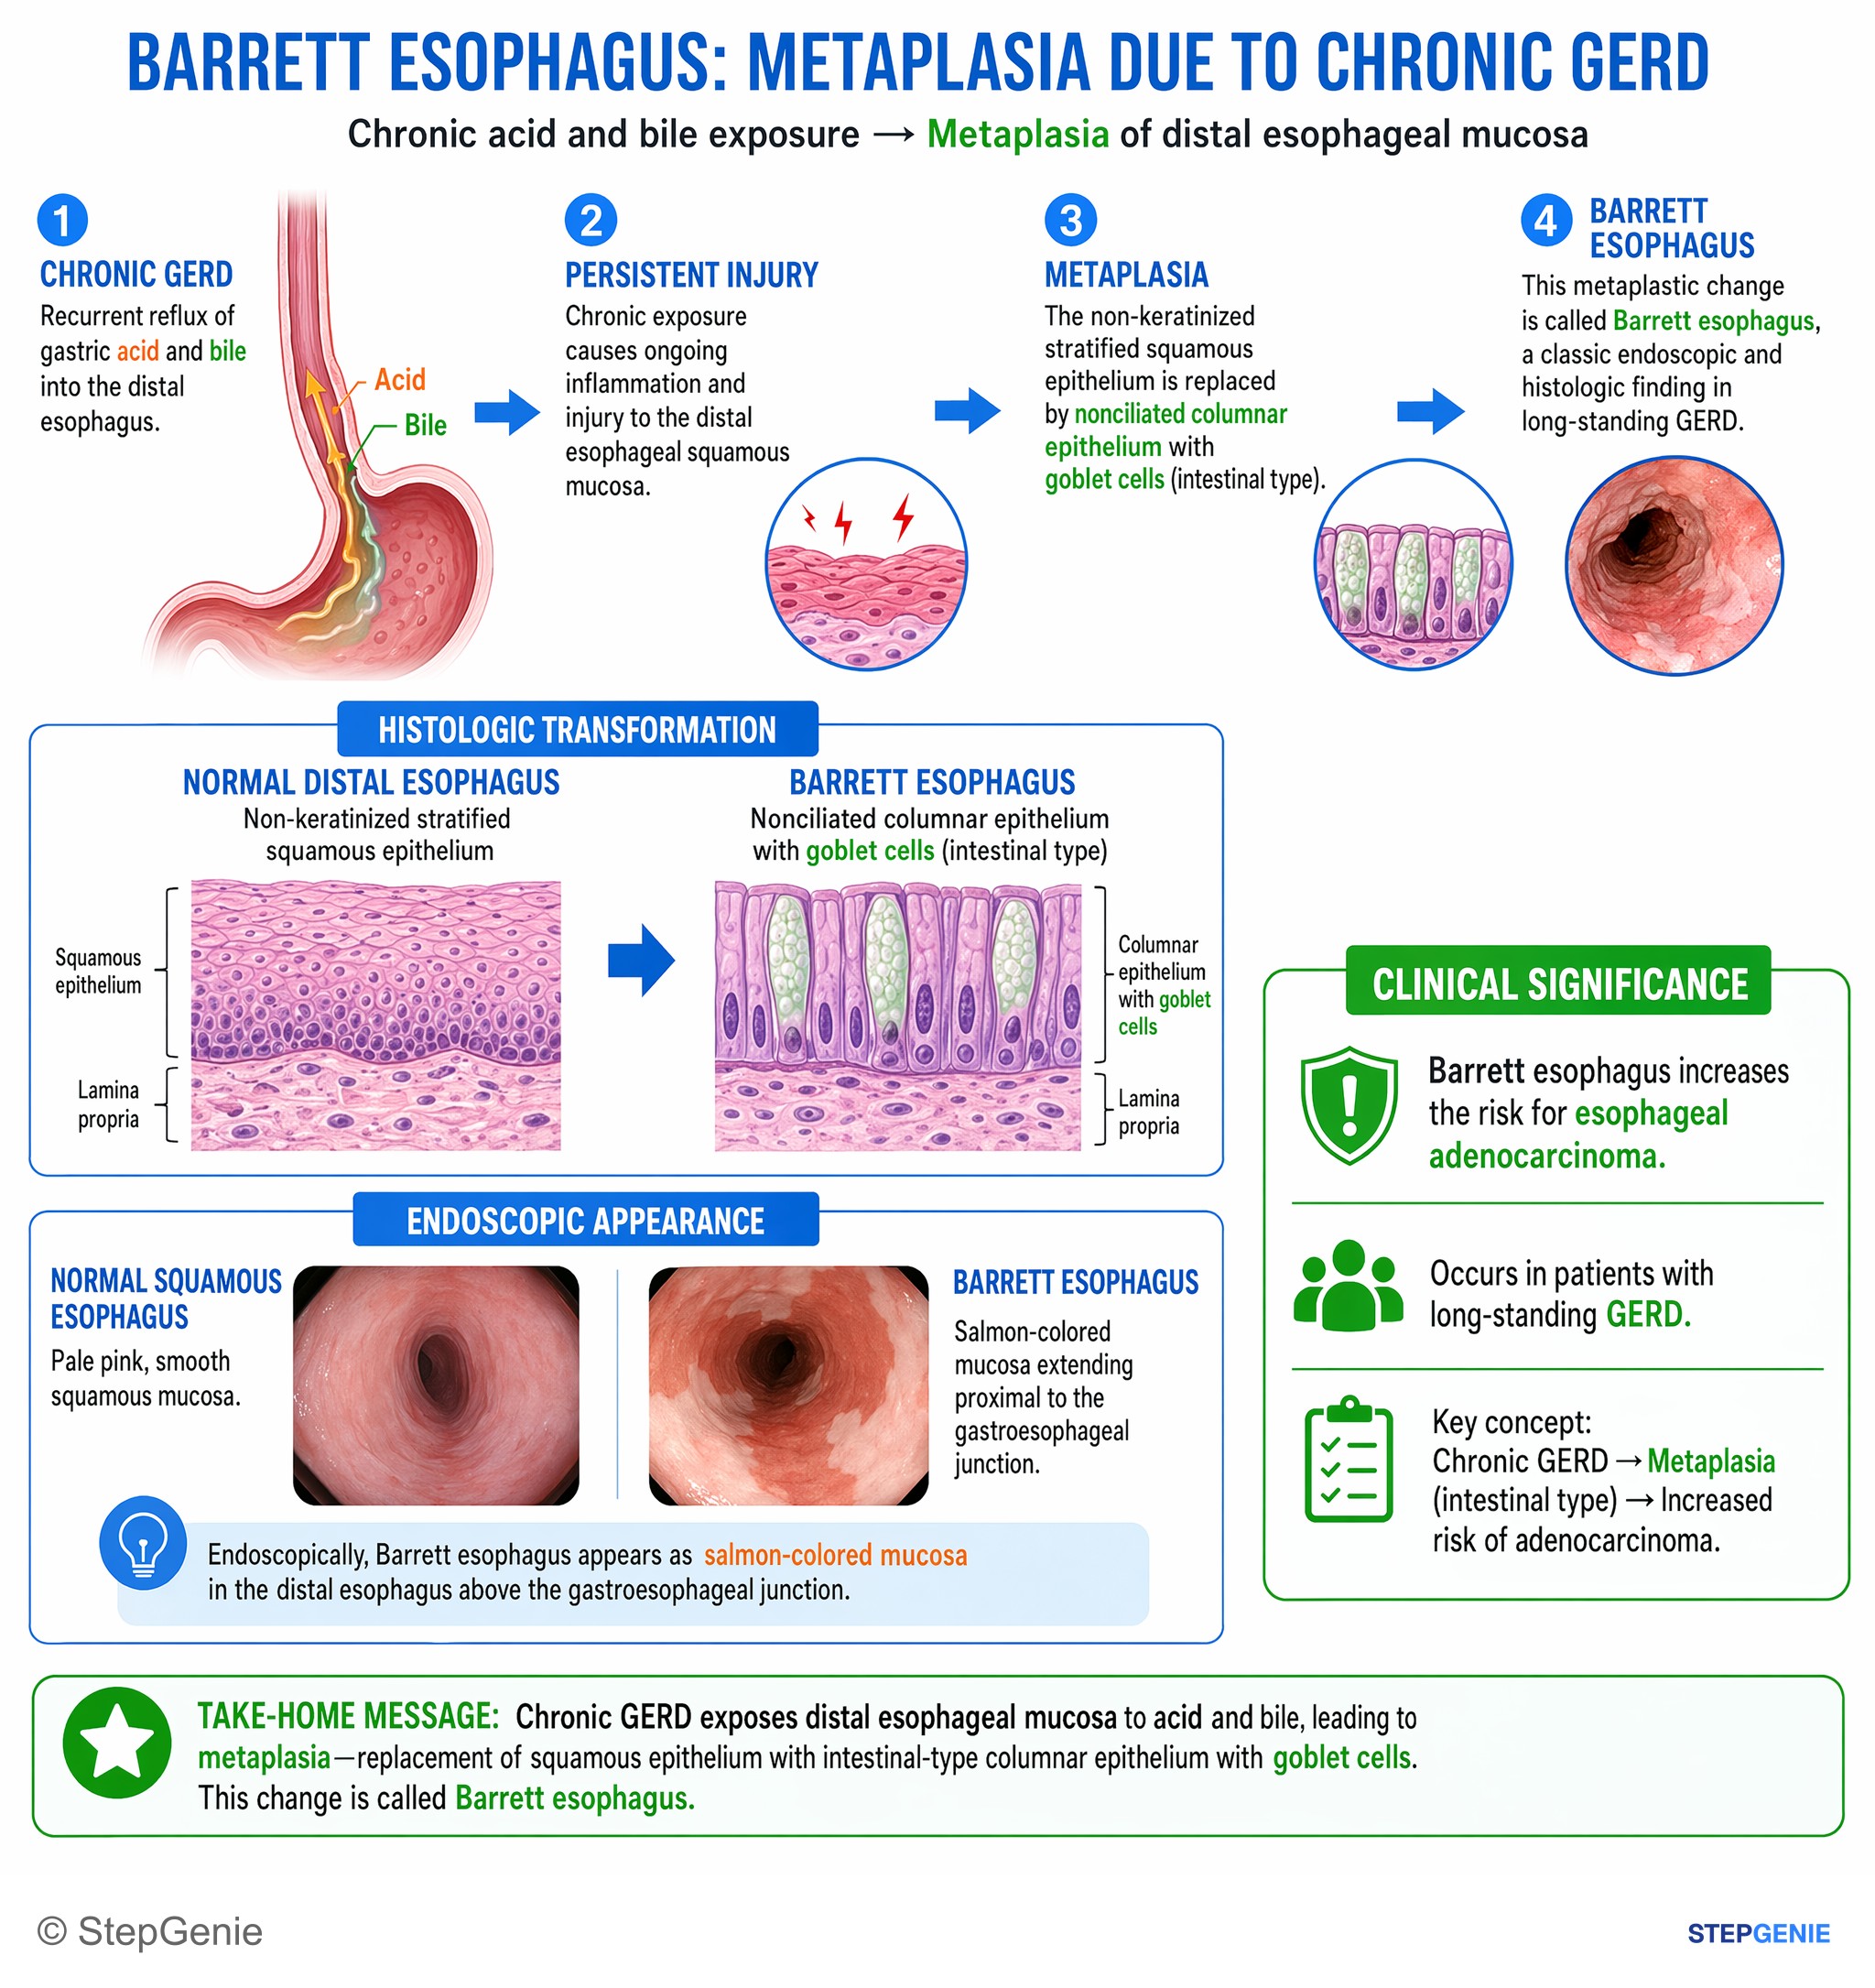
Barrett esophagus: chronic GERD → intestinal-type columnar metaplasia in distal esophagus; risk for adenocarcinoma.
USMLE Step 1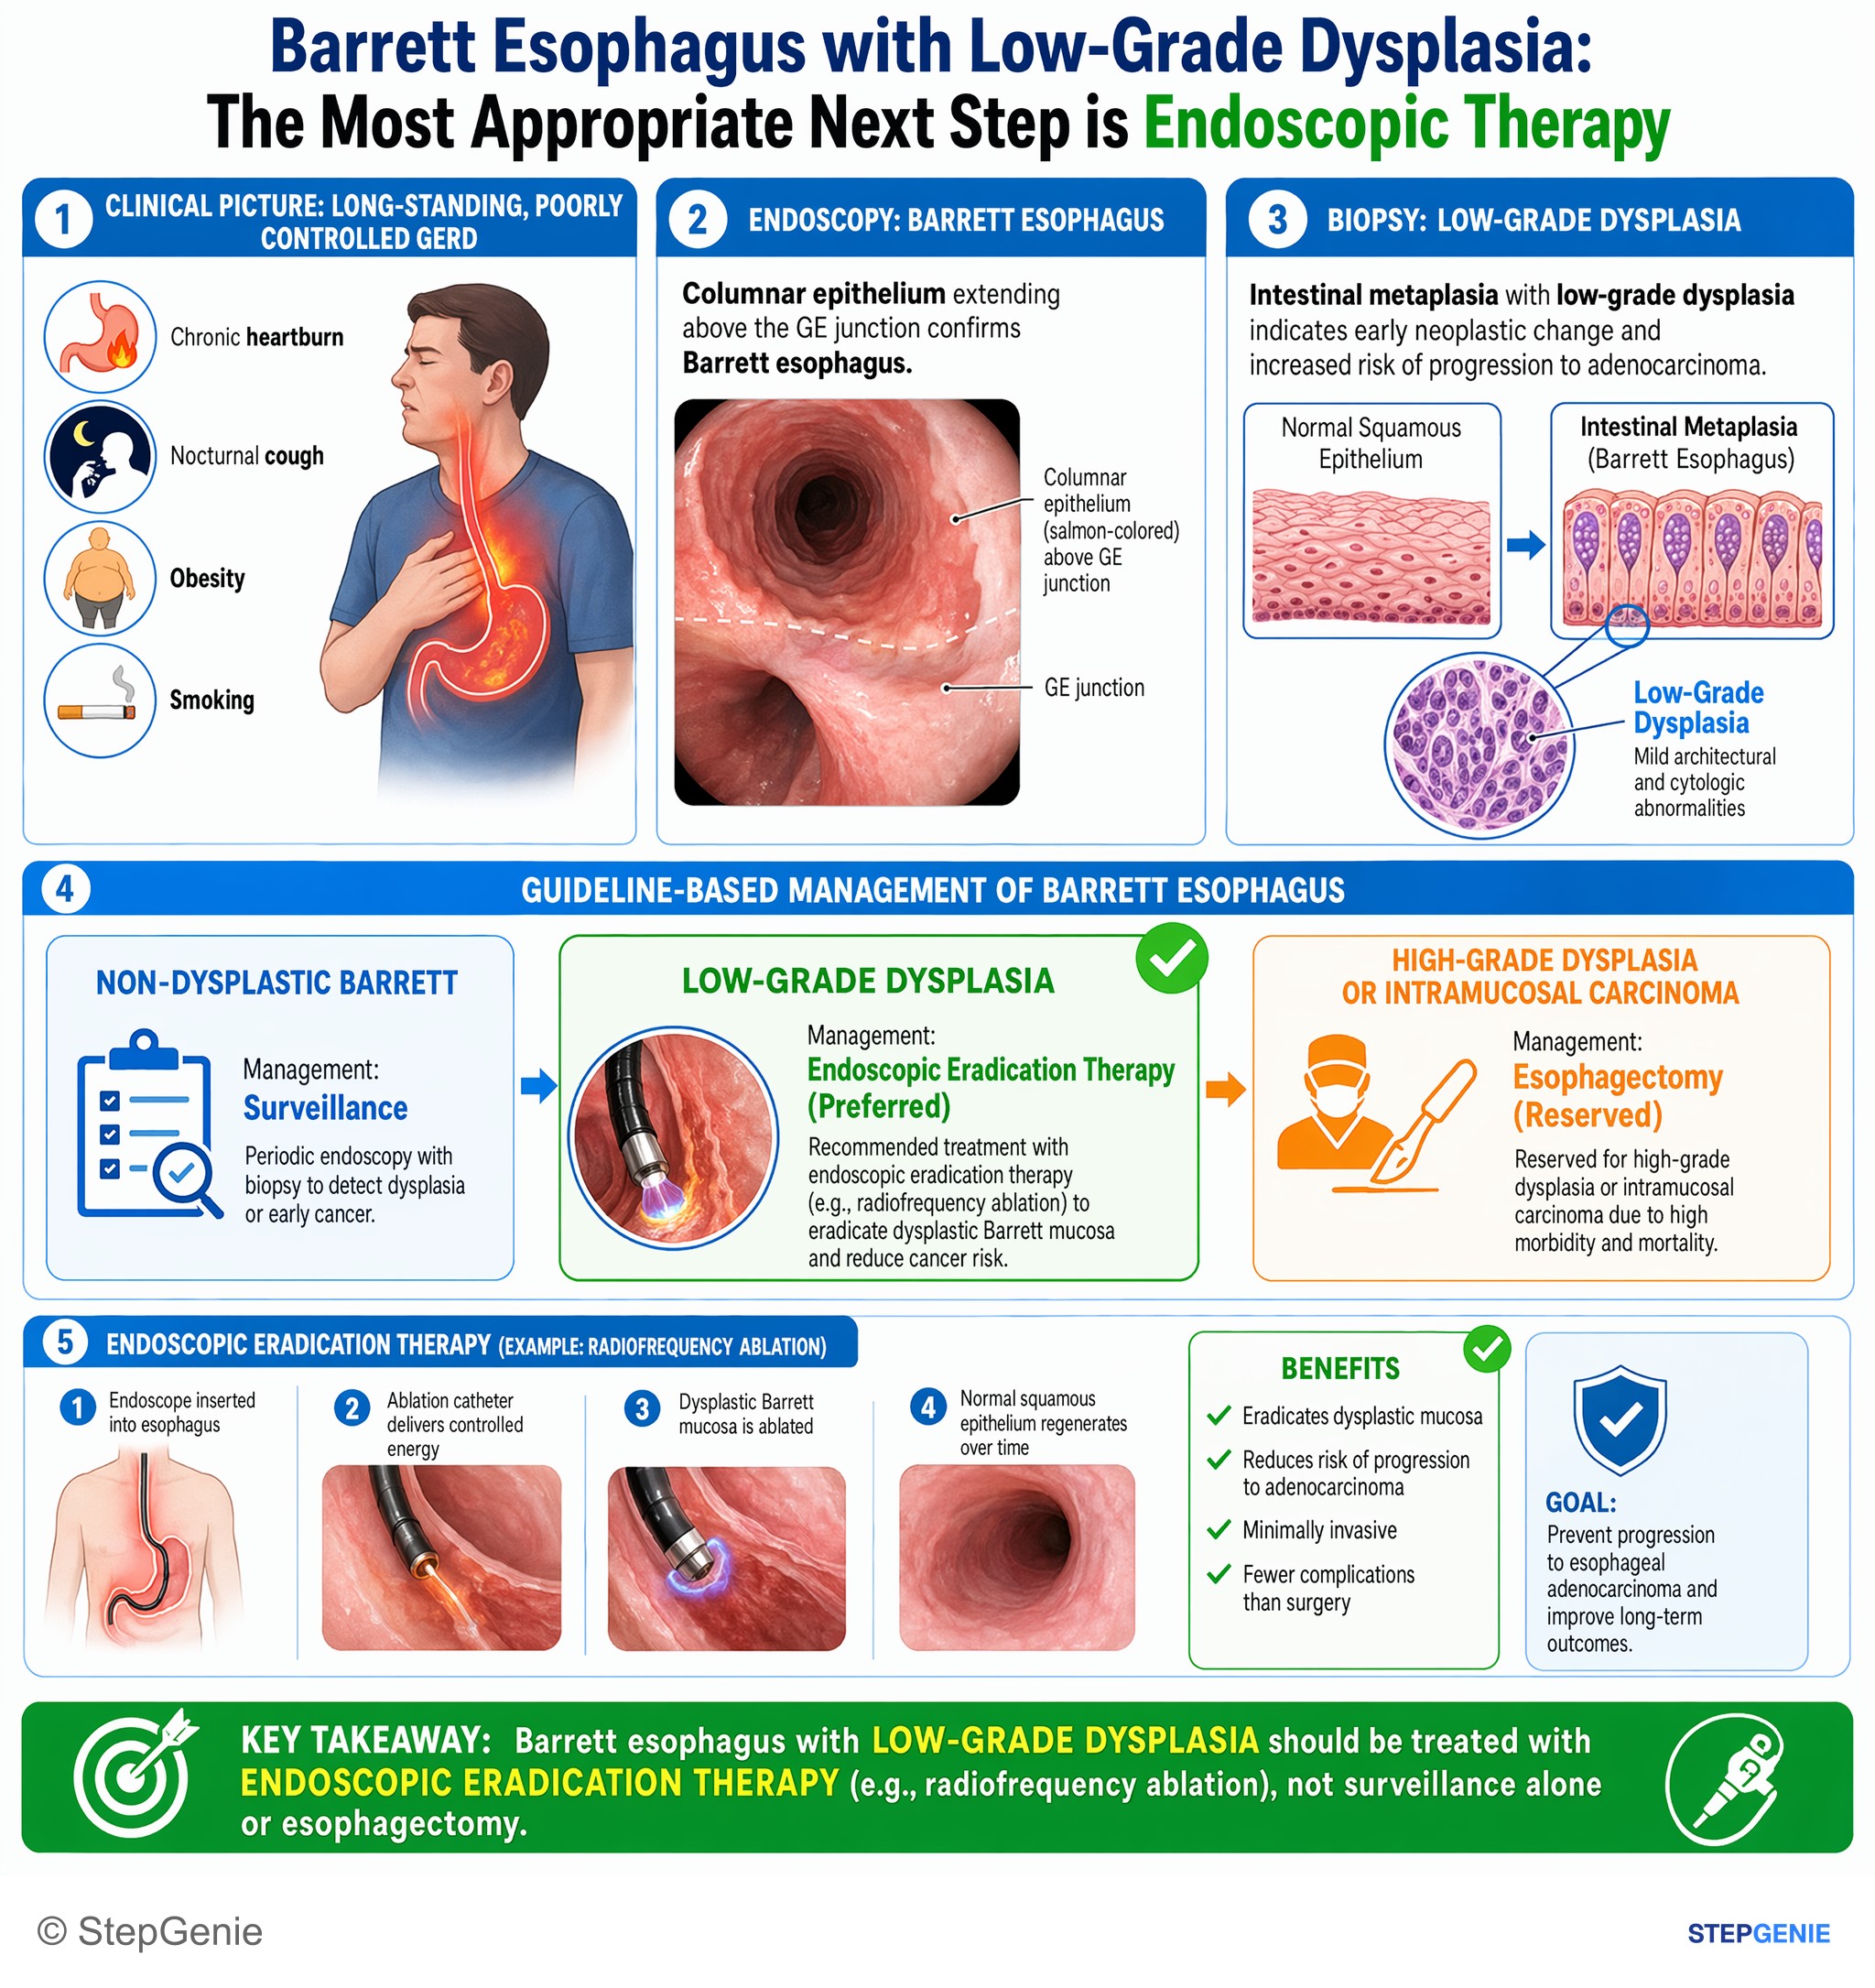
Barrett esophagus with low-grade dysplasia requires endoscopic eradication therapy, not surveillance alone or esophagectomy.
USMLE Step 2Frequently Asked Questions
What is the most important long-term complication of Barrett esophagus?
The most important long-term complication of Barrett esophagus is esophageal adenocarcinoma. Barrett esophagus is a premalignant condition in which chronic acid exposure leads to intestinal metaplasia of the distal esophagus. The classic progression is GERD to Barrett esophagus to dysplasia to adenocarcinoma, and these cancers typically arise in the distal esophagus near the gastroesophageal junction.
How do you recognize Barrett esophagus on endoscopy and biopsy?
Barrett esophagus is recognized by salmon-colored mucosa extending upward from the gastroesophageal junction on endoscopy and intestinal-type columnar epithelium with goblet cells on biopsy. This reflects metaplasia of the distal esophagus, where normal stratified squamous epithelium is replaced by nonciliated, mucin-secreting columnar epithelium in response to chronic acid exposure.
How do you tell Barrett-related adenocarcinoma risk from esophageal squamous cell carcinoma risk?
Barrett esophagus specifically increases the risk of esophageal adenocarcinoma, not squamous cell carcinoma. Adenocarcinoma is linked to chronic GERD and Barrett changes in the distal esophagus near the gastroesophageal junction. In contrast, squamous cell carcinoma is associated with alcohol, tobacco, very hot beverages, achalasia, and Plummer-Vinson syndrome, and it is classically more common in the mid-esophagus.
Why doesn’t dysphagia in a reflux vignette automatically mean achalasia?
Dysphagia in a reflux vignette does not automatically mean achalasia because Barrett esophagus and chronic GERD can also cause dysphagia, such as from a peptic stricture. Achalasia has a different pattern: dysphagia to both solids and liquids from the start, due to failure of LES relaxation and loss of peristalsis from degeneration of the Auerbach myenteric plexus, often with a bird-beak appearance on barium swallow.
What are the key risk factors and first-line treatment clues for Barrett esophagus and GERD?
Key risk factors for Barrett esophagus and esophageal adenocarcinoma include chronic GERD, obesity, male sex, White race, and smoking. For GERD symptoms, first-line treatment for frequent symptoms is a proton pump inhibitor. Lifestyle measures are also important, including weight loss, elevating the head of the bed, avoiding late meals, and avoiding trigger foods.