Achalasia is one of those GI topics that seems straightforward—until a question stem sneaks in one extra symptom (like heartburn) and suddenly every answer choice sounds “kind of right.” The key to crushing achalasia vignettes on Step is knowing the mechanism, the signature tests, and exactly how to rule out the classic distractors.
Tag: GI > Esophageal & Gastric Disorders
The Clinical Vignette (Q-bank style)
A 45-year-old man presents with 6 months of progressive dysphagia to both solids and liquids. He reports regurgitation of undigested food, especially at night, and has lost 10 lb unintentionally. He occasionally has substernal chest discomfort after eating. Physical exam is unremarkable.
A barium swallow shows smooth tapering at the distal esophagus. High-resolution manometry demonstrates incomplete relaxation of the lower esophageal sphincter (LES) and absence of normal peristalsis.
What is the most likely underlying pathophysiology?
The Correct Answer: Achalasia
What’s happening pathophysiologically?
Achalasia is due to degeneration of inhibitory neurons (NO, VIP) in the myenteric (Auerbach) plexus, leading to:
- Increased LES tone
- Failure of LES relaxation
- Aperistalsis in the esophageal body
High-yield clinical features
- Dysphagia to solids and liquids (often progressive)
- Regurgitation of undigested food
- Nocturnal cough/aspiration risk
- Chest pain can occur (spasm/stretching)
- Weight loss (mild–moderate; pronounced weight loss raises concern for malignancy/pseudoachalasia)
High-yield diagnostics (know the hierarchy)
| Test | What it shows | Why it matters |
|---|---|---|
| Esophageal manometry | Aperistalsis + incomplete LES relaxation | Gold standard |
| Barium swallow | “Bird beak” tapering + dilated esophagus | Classic imaging clue |
| Upper endoscopy (EGD) | Rules out mass/stricture | Important to exclude pseudoachalasia |
High-yield associations
- Primary (idiopathic) achalasia is most common.
- Secondary achalasia (pseudoachalasia): malignancy at GE junction can mimic it.
- Trypanosoma cruzi (Chagas disease): destruction of myenteric plexus → achalasia + megacolon.
Treatment (Step-friendly)
- Pneumatic dilation or Heller myotomy (often with partial fundoplication)
- POEM (peroral endoscopic myotomy) is increasingly common
- Botulinum toxin into LES (older/high-risk surgical patients)
- Nitrates/CCBs: less effective, temporary symptom relief
Why Every Distractor Matters (and how to eliminate them)
Below are the answer choices Step loves to place next to achalasia—and the one detail that should make you say “nope.”
Distractor 1: GERD (decreased LES tone)
Why it sounds tempting
Patients with achalasia can report heartburn-like discomfort, and regurgitated food can be mistaken for reflux.
Why it’s wrong
GERD is about low LES tone and acid reflux, not a tight LES.
GERD hallmark clues:
- Heartburn worse after meals/lying down
- Sour taste/acid regurgitation
- Dysphagia usually suggests complications (stricture, cancer) rather than primary GERD
- Manometry would not show classic aperistalsis + failed LES relaxation
Testable difference:
- Achalasia: bird beak, aperistalsis
- GERD: erosive esophagitis, possible Barrett, normal peristalsis early on
Distractor 2: Esophageal adenocarcinoma causing obstruction (pseudoachalasia)
Why it sounds tempting
Cancer near the GE junction can mimic achalasia symptoms (dysphagia + weight loss).
When to suspect it
- Older age (often >60)
- Rapid symptom progression
- Marked weight loss
- History of Barrett esophagus/chronic GERD
How to distinguish from true achalasia
- EGD is key: malignancy may show an obstructing lesion.
- Manometry in pseudoachalasia can resemble achalasia, so endoscopy is essential when red flags exist.
USMLE pearl:
If the vignette emphasizes rapid onset + big weight loss, think malignancy until proven otherwise.
Distractor 3: Diffuse esophageal spasm (DES)
Why it sounds tempting
Chest pain + dysphagia makes DES an easy trap.
How DES differs
- Dysphagia can involve solids and liquids, like achalasia
- But peristalsis isn’t absent; it’s uncoordinated
Key diagnostic clue:
- Barium swallow: “corkscrew” esophagus
- Manometry: premature, simultaneous contractions, not classic aperistalsis with failed LES relaxation
Memory anchor:
- Achalasia = can’t relax
- DES = relaxes, but contracts chaotically
Distractor 4: Scleroderma esophagus
Why it sounds tempting
It’s also a motility disorder and shows up in the same question neighborhoods.
The opposite LES problem
Scleroderma causes:
- atrophy/fibrosis of smooth muscle
- decreased LES tone
- severe GERD and reflux complications
Clues that scream scleroderma instead of achalasia:
- Longstanding GERD symptoms
- Systemic features: Raynaud, skin thickening, telangiectasias
- Manometry: low LES pressure + hypoperistalsis
High-yield contrast:
| Disorder | LES tone | Peristalsis | Typical symptom emphasis |
|---|---|---|---|
| Achalasia | High | Absent | Dysphagia + regurgitation |
| Scleroderma | Low | Weak/absent distally | Severe reflux/heartburn |
Distractor 5: Zenker diverticulum (pharyngoesophageal diverticulum)
Why it sounds tempting
Regurgitation + aspiration risk can look similar.
How to spot Zenker quickly
- Older patient
- Halitosis (food trapped in pouch)
- Regurgitation of undigested food is common—but dysphagia is often oropharyngeal (initiating swallow issues)
- Gurgling in the neck, cough, aspiration
Anatomy high-yield:
- Herniation through Killian triangle (between thyropharyngeus and cricopharyngeus)
Best diagnostic test: barium swallow (avoid endoscopy initially due to perforation risk).
Distractor 6: Peptic stricture (from chronic GERD)
Why it sounds tempting
Stricture causes dysphagia and can be distal.
The giveaway
- Dysphagia is typically to solids first, then progresses to liquids later (mechanical obstruction pattern).
- History of longstanding GERD
Achalasia vs stricture pattern
- Achalasia: solids and liquids from early on (motility)
- Stricture: solids first (mechanical), liquids later
Achalasia: The “Step 1 & Step 2” High-Yield Snapshot
Core triad to memorize
- Dysphagia to solids + liquids
- Aperistalsis
- Incomplete LES relaxation (high LES tone)
Classic imaging phrase
- Barium swallow: “bird beak”
Gold standard
- Esophageal manometry
Biggest “don’t miss”
- Rule out malignancy (pseudoachalasia) with EGD, especially with older age, rapid course, significant weight loss.
Complications worth mentioning in answers
- Aspiration pneumonia
- Esophagitis
- Increased risk of esophageal squamous cell carcinoma (classically associated)
Rapid-Fire Practice: One-line Differentiators
- Achalasia: bird beak + manometry shows failed LES relaxation
- GERD: low LES tone → heartburn, Barrett risk
- DES: corkscrew esophagus + intermittent chest pain
- Scleroderma: low LES tone + severe reflux + systemic signs
- Zenker: halitosis + regurgitation + older patient + barium swallow
- Stricture: solids first + chronic GERD history
Takeaway
Achalasia questions are rarely testing whether you’ve heard of achalasia—they’re testing whether you can defend it against the distractors. If you anchor on the mechanism (loss of NO/VIP inhibitory neurons) and confirm with the signature tests (manometry gold standard; bird beak on barium), you’ll not only pick the right answer—you’ll know why everything else is wrong.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
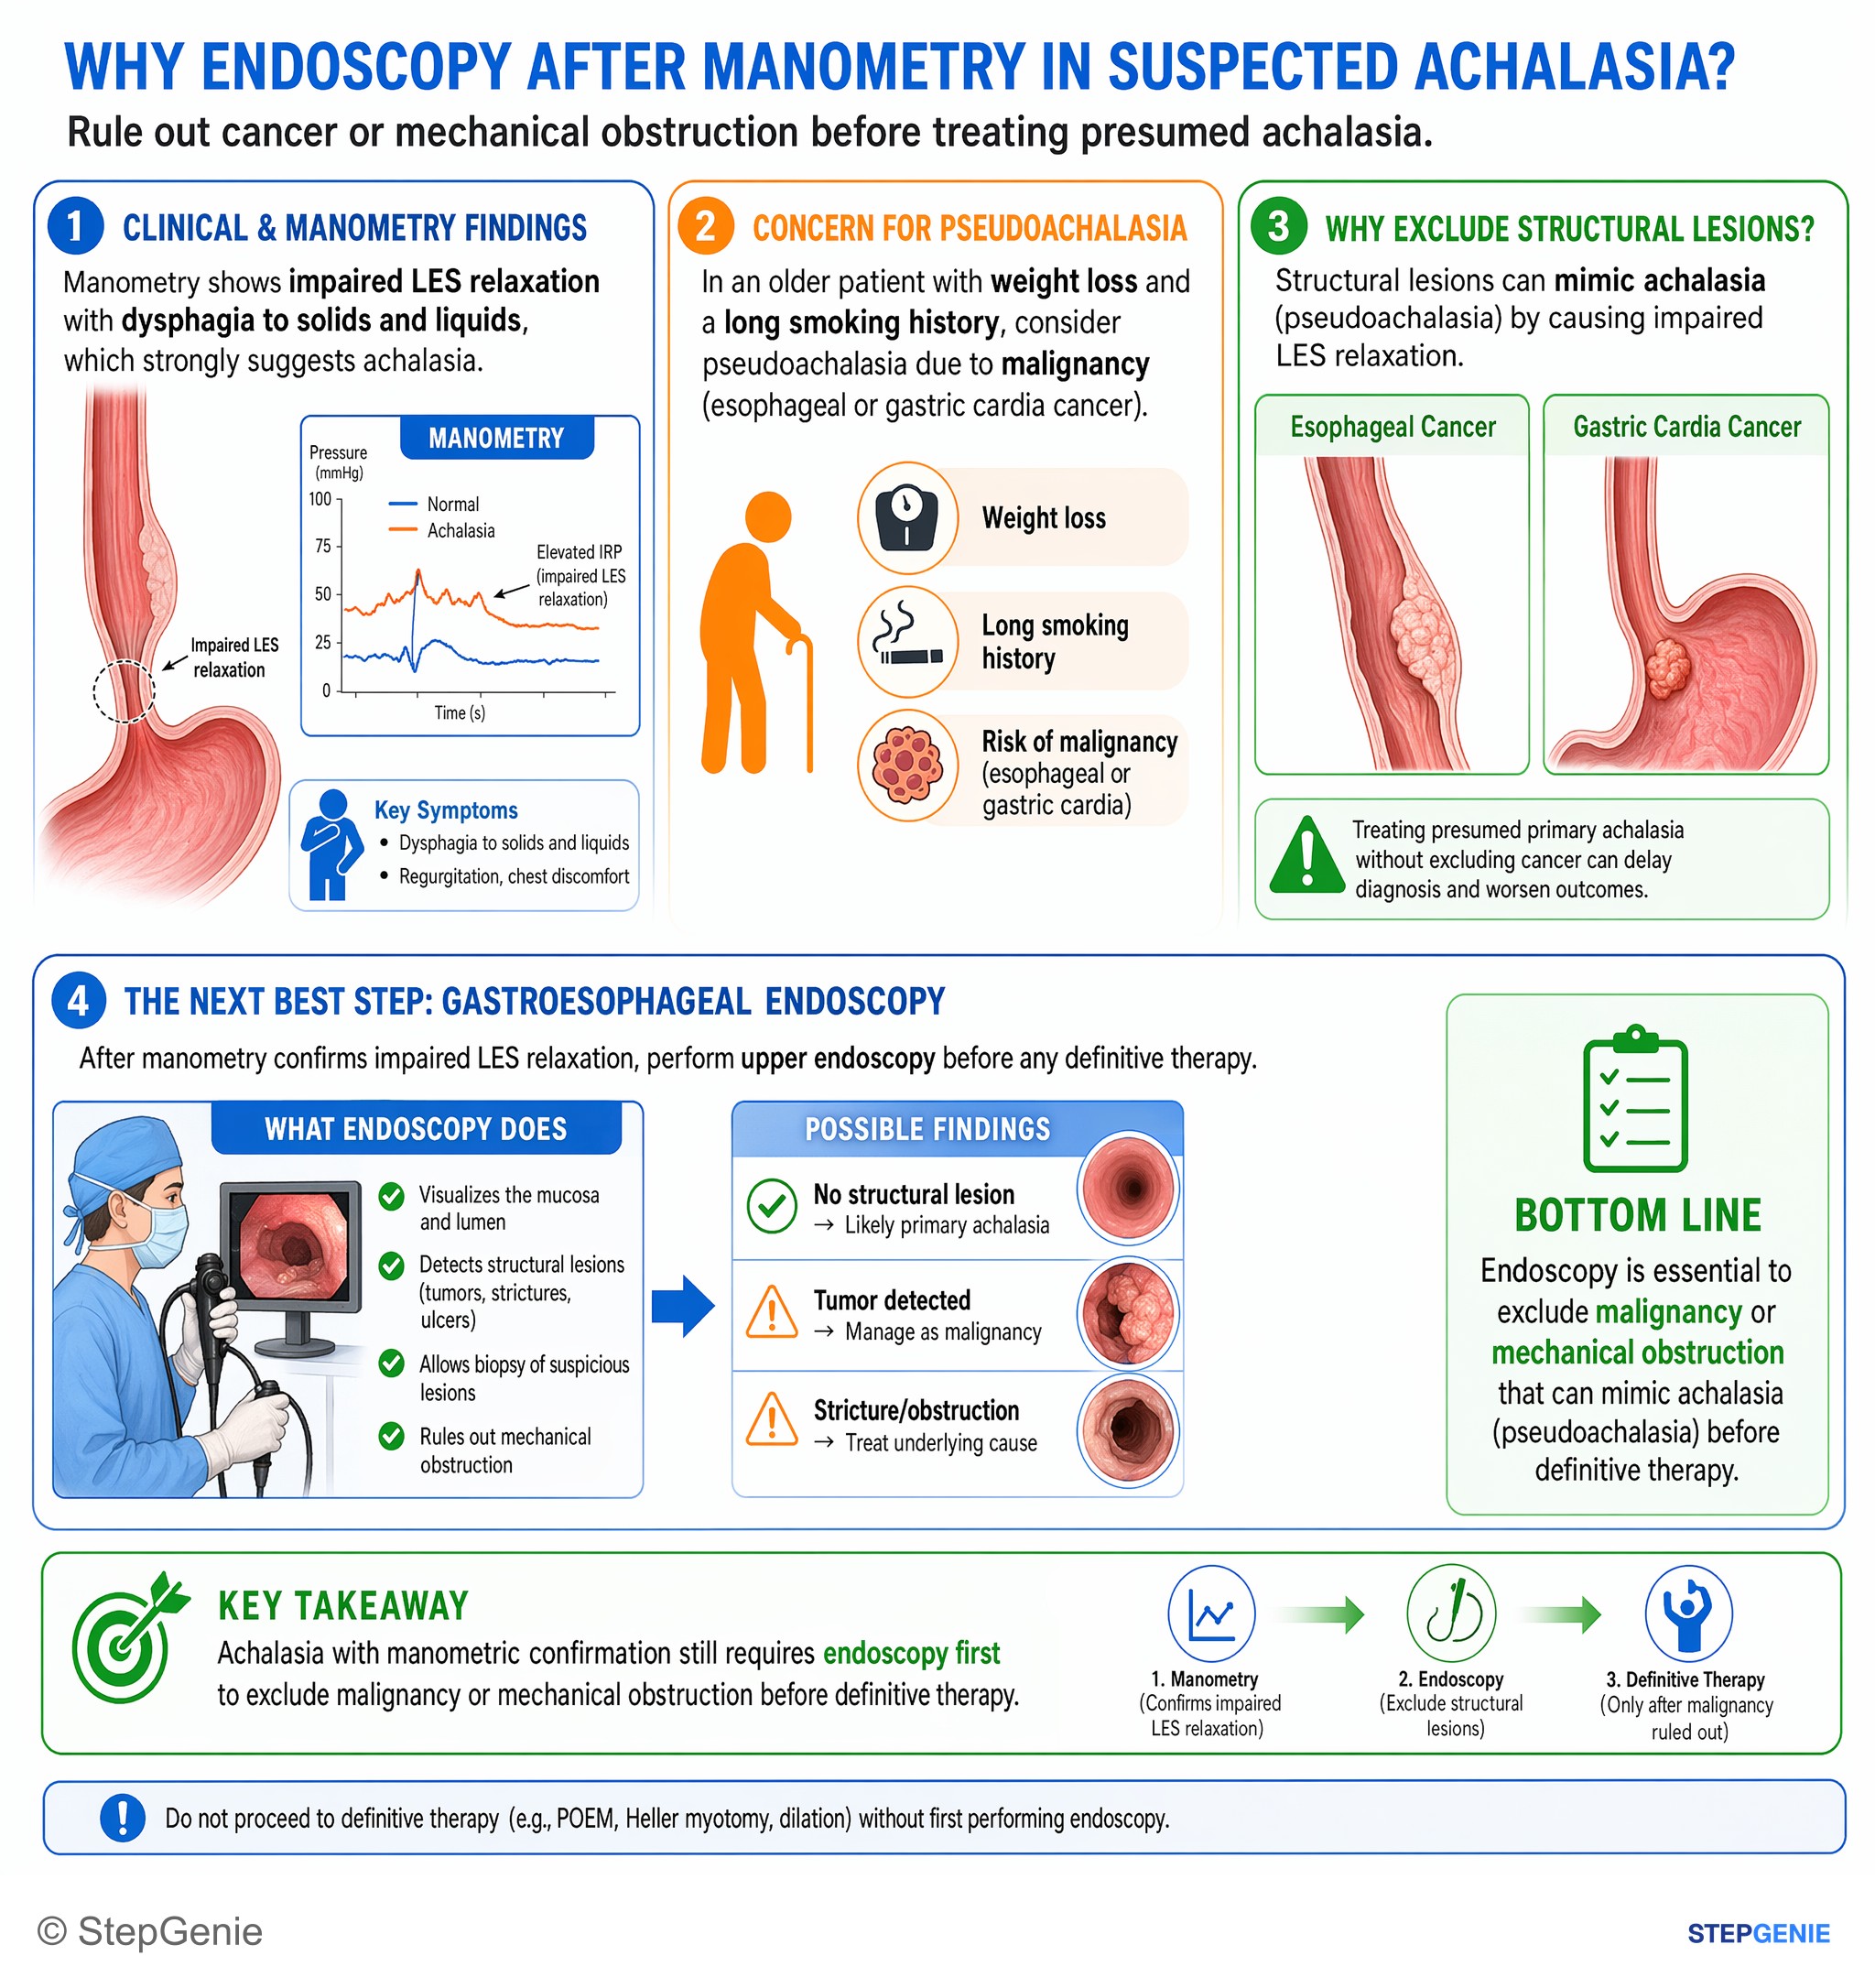
Achalasia with manometric confirmation still requires endoscopy first to exclude malignancy or mechanical obstruction before definitive…
USMLE Step 2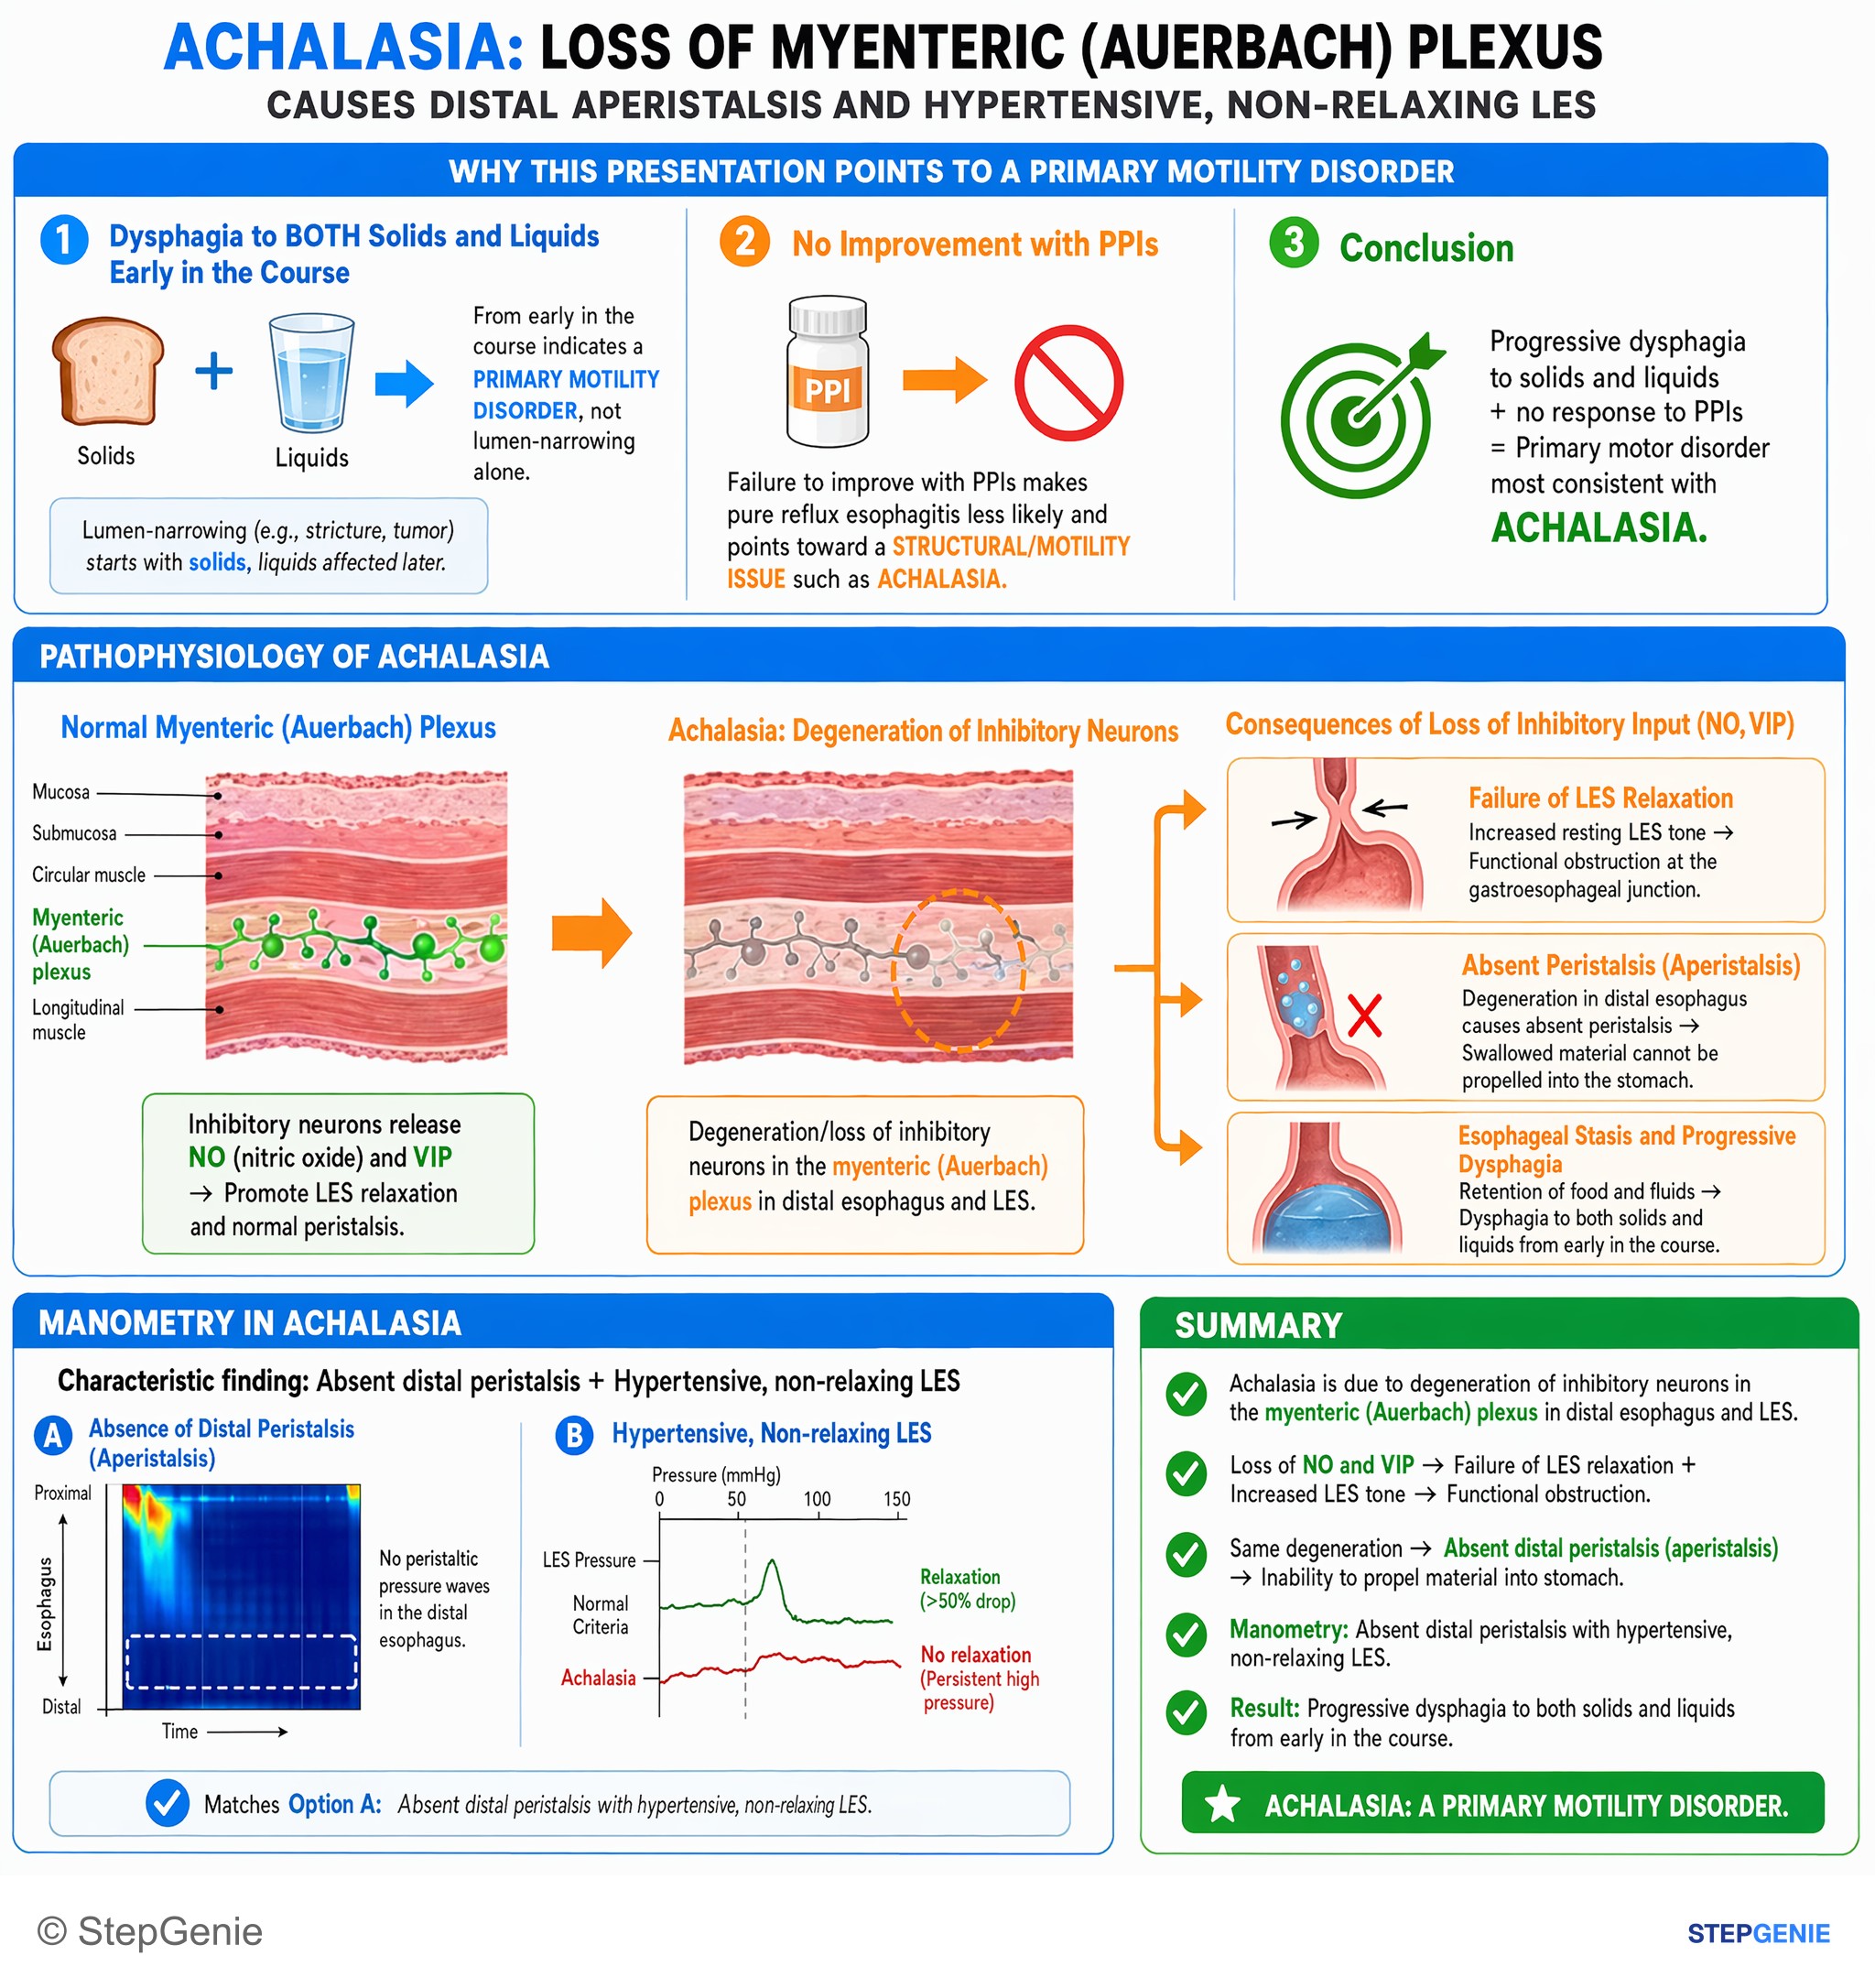
Achalasia from loss of myenteric (Auerbach) plexus causes distal aperistalsis and hypertensive, non-relaxing LES, producing progressive…
USMLE Step 2Frequently Asked Questions
Why does achalasia cause dysphagia to both solids and liquids?
Achalasia causes dysphagia to both solids and liquids because the lower esophageal sphincter fails to relax and the esophageal body loses normal peristalsis. The underlying problem is degeneration of inhibitory neurons that use nitric oxide and VIP in the myenteric plexus. That leads to increased LES tone, incomplete LES relaxation, and aperistalsis, so both solid food and liquids have trouble passing normally.
What is the gold-standard test for achalasia?
Esophageal manometry is the gold-standard test for achalasia. It shows the two key findings that define the disorder: absence of normal peristalsis and incomplete relaxation of the lower esophageal sphincter. A barium swallow can give the classic bird-beak tapering clue, but manometry is the study that confirms the motility pattern most directly.
How do you tell achalasia from diffuse esophageal spasm on tests?
Achalasia is distinguished from diffuse esophageal spasm by its pattern of failed relaxation and absent peristalsis. In achalasia, manometry shows aperistalsis with incomplete LES relaxation, and barium swallow shows smooth distal tapering or a bird-beak appearance. In diffuse esophageal spasm, peristalsis is not absent but uncoordinated, manometry shows premature simultaneous contractions, and barium swallow shows a corkscrew esophagus.
When should you worry that achalasia symptoms are actually pseudoachalasia from cancer?
You should worry about pseudoachalasia when the vignette emphasizes older age, rapid symptom progression, or marked weight loss. Malignancy at the gastroesophageal junction can mimic achalasia symptoms and even resemble it on manometry. Upper endoscopy is important in that setting because it can identify an obstructing lesion or rule out a mass or stricture that would explain the symptoms.
What are the first-line treatments for achalasia?
The main treatments for achalasia are pneumatic dilation and Heller myotomy, often paired with partial fundoplication. POEM, or peroral endoscopic myotomy, is also increasingly common. Botulinum toxin injection into the LES is used more for older or high-risk surgical patients, while nitrates and calcium channel blockers provide only temporary symptom relief and are less effective overall.