Peptic ulcer disease (PUD) is one of those USMLE staples that shows up as “epigastric pain + anemia” one day and as a sudden rigid abdomen the next. The good news: most questions boil down to (1) cause (H. pylori vs NSAIDs), (2) location (gastric vs duodenal), (3) complication (bleed vs perforation vs obstruction), and (4) what to do next. Here’s the shareable, one-page version.
PUD in one line (the Step-ready definition)
Peptic ulcer disease = mucosal ulceration in the stomach or proximal duodenum due to acid-pepsin injury, most commonly from H. pylori or NSAIDs.
Visual mnemonic (quick and sticky): “D is for Dinner, G is for Grim”
- Duodenal ulcer (D): pain gets better with Dinner (food)
- Gastric ulcer (G): pain gets Grim with Grub (food)
One-liner explanation:
Food temporarily buffers acid → helps duodenal ulcer pain; gastric ulcers often worsen with eating because acid secretion and gastric mucosal injury are provoked during meals.
Test-day caveat: symptoms overlap; use patterns + risk factors + complications to lock it in.
High-yield compare table: Duodenal vs Gastric ulcers
| Feature | Duodenal ulcer | Gastric ulcer |
|---|---|---|
| Classic pain timing | Improves with meals, returns 2–3 hours later; may wake patient at night | Worsens with meals |
| Weight change | Weight gain (eating relieves pain) | Weight loss (eating hurts) |
| Acid level | Often increased (esp. with H. pylori–associated increased gastrin) | Often normal/decreased (mucosal defense problem) |
| Most common cause | H. pylori | NSAIDs (also H. pylori) |
| Typical location | 1st part of duodenum | Lesser curvature (antrum/body) |
| Malignancy concern | Generally benign | Can be malignant → evaluate if concerning features/persistent |
Etiology: the two big hitters
1) H. pylori
Buzzwords: chronic gastritis, ulcer, MALT lymphoma risk, adenocarcinoma risk.
Mechanisms (Step 1 friendly):
- Urease+ → converts urea to ammonia → locally buffers acid, damages mucosa
- Inflammation and impaired mucosal defenses
- In antral-predominant gastritis, reduced somatostatin → ↑ gastrin → ↑ acid → more duodenal ulcers
Where it lives: gastric mucous layer (not truly “in” the lumen)
2) NSAIDs
Key mechanism: COX inhibition → ↓ prostaglandins → ↓ mucus + ↓ bicarbonate + ↓ mucosal blood flow
Net effect: mucosa becomes defenseless against acid → ulcers (often gastric).
Clinical presentation (what USMLE loves to ask)
Core symptoms
- Epigastric burning/gnawing pain
- Nausea, bloating, early satiety (sometimes)
- GI bleeding symptoms:
- Melena (black, tarry stool)
- Hematemesis (coffee-ground or frank blood)
- Iron deficiency anemia (fatigue, pallor)
Alarm features (think urgent evaluation / malignancy / complication)
- Unintentional weight loss
- Progressive dysphagia or persistent vomiting
- GI bleeding/anemia
- Family history of upper GI malignancy
- Palpable mass, early satiety, age “older” (threshold varies—watch your question stem)
Complications: memorize by anatomy
1) Bleeding (most common complication)
- Posterior duodenal ulcer → gastroduodenal artery → massive bleed
- Clue: brisk hematemesis/melena, hypotension, shock
- Gastric ulcer on lesser curvature → left gastric artery (bleeding)
USMLE tip: If they say “posterior duodenal ulcer + hemorrhage,” your reflex should be gastroduodenal artery.
2) Perforation (surgical abdomen)
- Sudden severe pain + rigid abdomen + rebound
- Free air under diaphragm on upright CXR
Classics:
- Anterior duodenal ulcer → perforation → free air
3) Gastric outlet obstruction
- Classically from chronic duodenal/pyloric channel ulcer scarring/edema
- Nonbilious vomiting, early satiety, succussion splash
- Metabolic derangements: hypochloremic, hypokalemic metabolic alkalosis
- Loss of gastric HCl (H+) → alkalosis
- Volume depletion → RAAS → worsens hypokalemia
Diagnosis: what test, when?
Noninvasive H. pylori tests (preferred in many stable patients)
- Urea breath test (high sensitivity/specificity)
- Stool antigen test
Important test-taking pearl:
PPIs, bismuth, and antibiotics can cause false negatives. Many question stems imply “stop PPI before testing” (often ~2 weeks) and “stop antibiotics/bismuth longer.”
When to scope (EGD)
- Alarm features
- Complications/active bleeding
- Failure of empiric therapy
- Concern for malignancy (especially gastric ulcer patterns)
Upper GI bleed algorithm (high yield):
Unstable bleed → resuscitate first (IV fluids/blood), then urgent endoscopy for diagnosis + therapy.
Treatment: the cheat-sheet version
PUD basics
- Stop the injury: discontinue NSAIDs if possible
- Suppress acid: PPI is first-line for ulcer healing
If H. pylori positive: eradicate (and confirm cure)
Common US regimens (practice often depends on local resistance patterns):
- Bismuth quadruple therapy (very commonly favored):
- PPI + bismuth + tetracycline + metronidazole
- Concomitant therapy (another common option):
- PPI + clarithromycin + amoxicillin + metronidazole
Confirm eradication with urea breath or stool antigen (not serology), typically after completing therapy and being off PPIs long enough to avoid false negatives.
If NSAID-related but NSAID must continue
- PPI maintenance is typical; consider protective strategies
- (Step concept) Misoprostol can prevent NSAID ulcers but is limited by side effects; avoid in pregnancy due to uterotonic effects.
Rapid-fire pharmacology (Step 1 & 2 hits)
PPIs (omeprazole, pantoprazole, etc.)
- Mechanism: irreversible inhibition of H+/K+ ATPase in parietal cells
- High-yield adverse effects associations:
- C. difficile risk
- Pneumonia (esp. early use)
- Hypomagnesemia
- ↓ B12 absorption (long-term)
- Possible fracture risk (long-term)
H2 blockers (famotidine, cimetidine)
- Mechanism: block H2 receptors on parietal cells → ↓ acid
- Cimetidine classic associations:
- CYP450 inhibition
- Antiandrogen effects (gynecomastia, impotence)
- Confusion in elderly
Sucralfate
- Coats ulcers; requires acidic environment
- Can bind meds; constipation
Bismuth
- Dark stools/tongue; part of H. pylori regimens
Classic USMLE vignettes (pattern recognition)
- Pain relieved by food + wakes at night + smoker → think duodenal ulcer, often H. pylori
- Epigastric pain worse with meals + weight loss + NSAID use → think gastric ulcer
- Sudden severe abdominal pain + rigid abdomen + free air → perforated ulcer (often anterior duodenal)
- Massive GI bleed + posterior duodenal ulcer → gastroduodenal artery
- Chronic vomiting + metabolic alkalosis + hypochloremia/hypokalemia → gastric outlet obstruction
The “one-page” mini checklist (what to answer in your head)
- G or D? (meal association + location clues)
- Cause? H. pylori vs NSAIDs
- Complication? bleed (which artery?), perforation (free air), obstruction (alkalosis)
- Next step? stabilize if bleeding/peritonitis; test/treat H. pylori; PPI; stop NSAIDs; confirm eradication
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
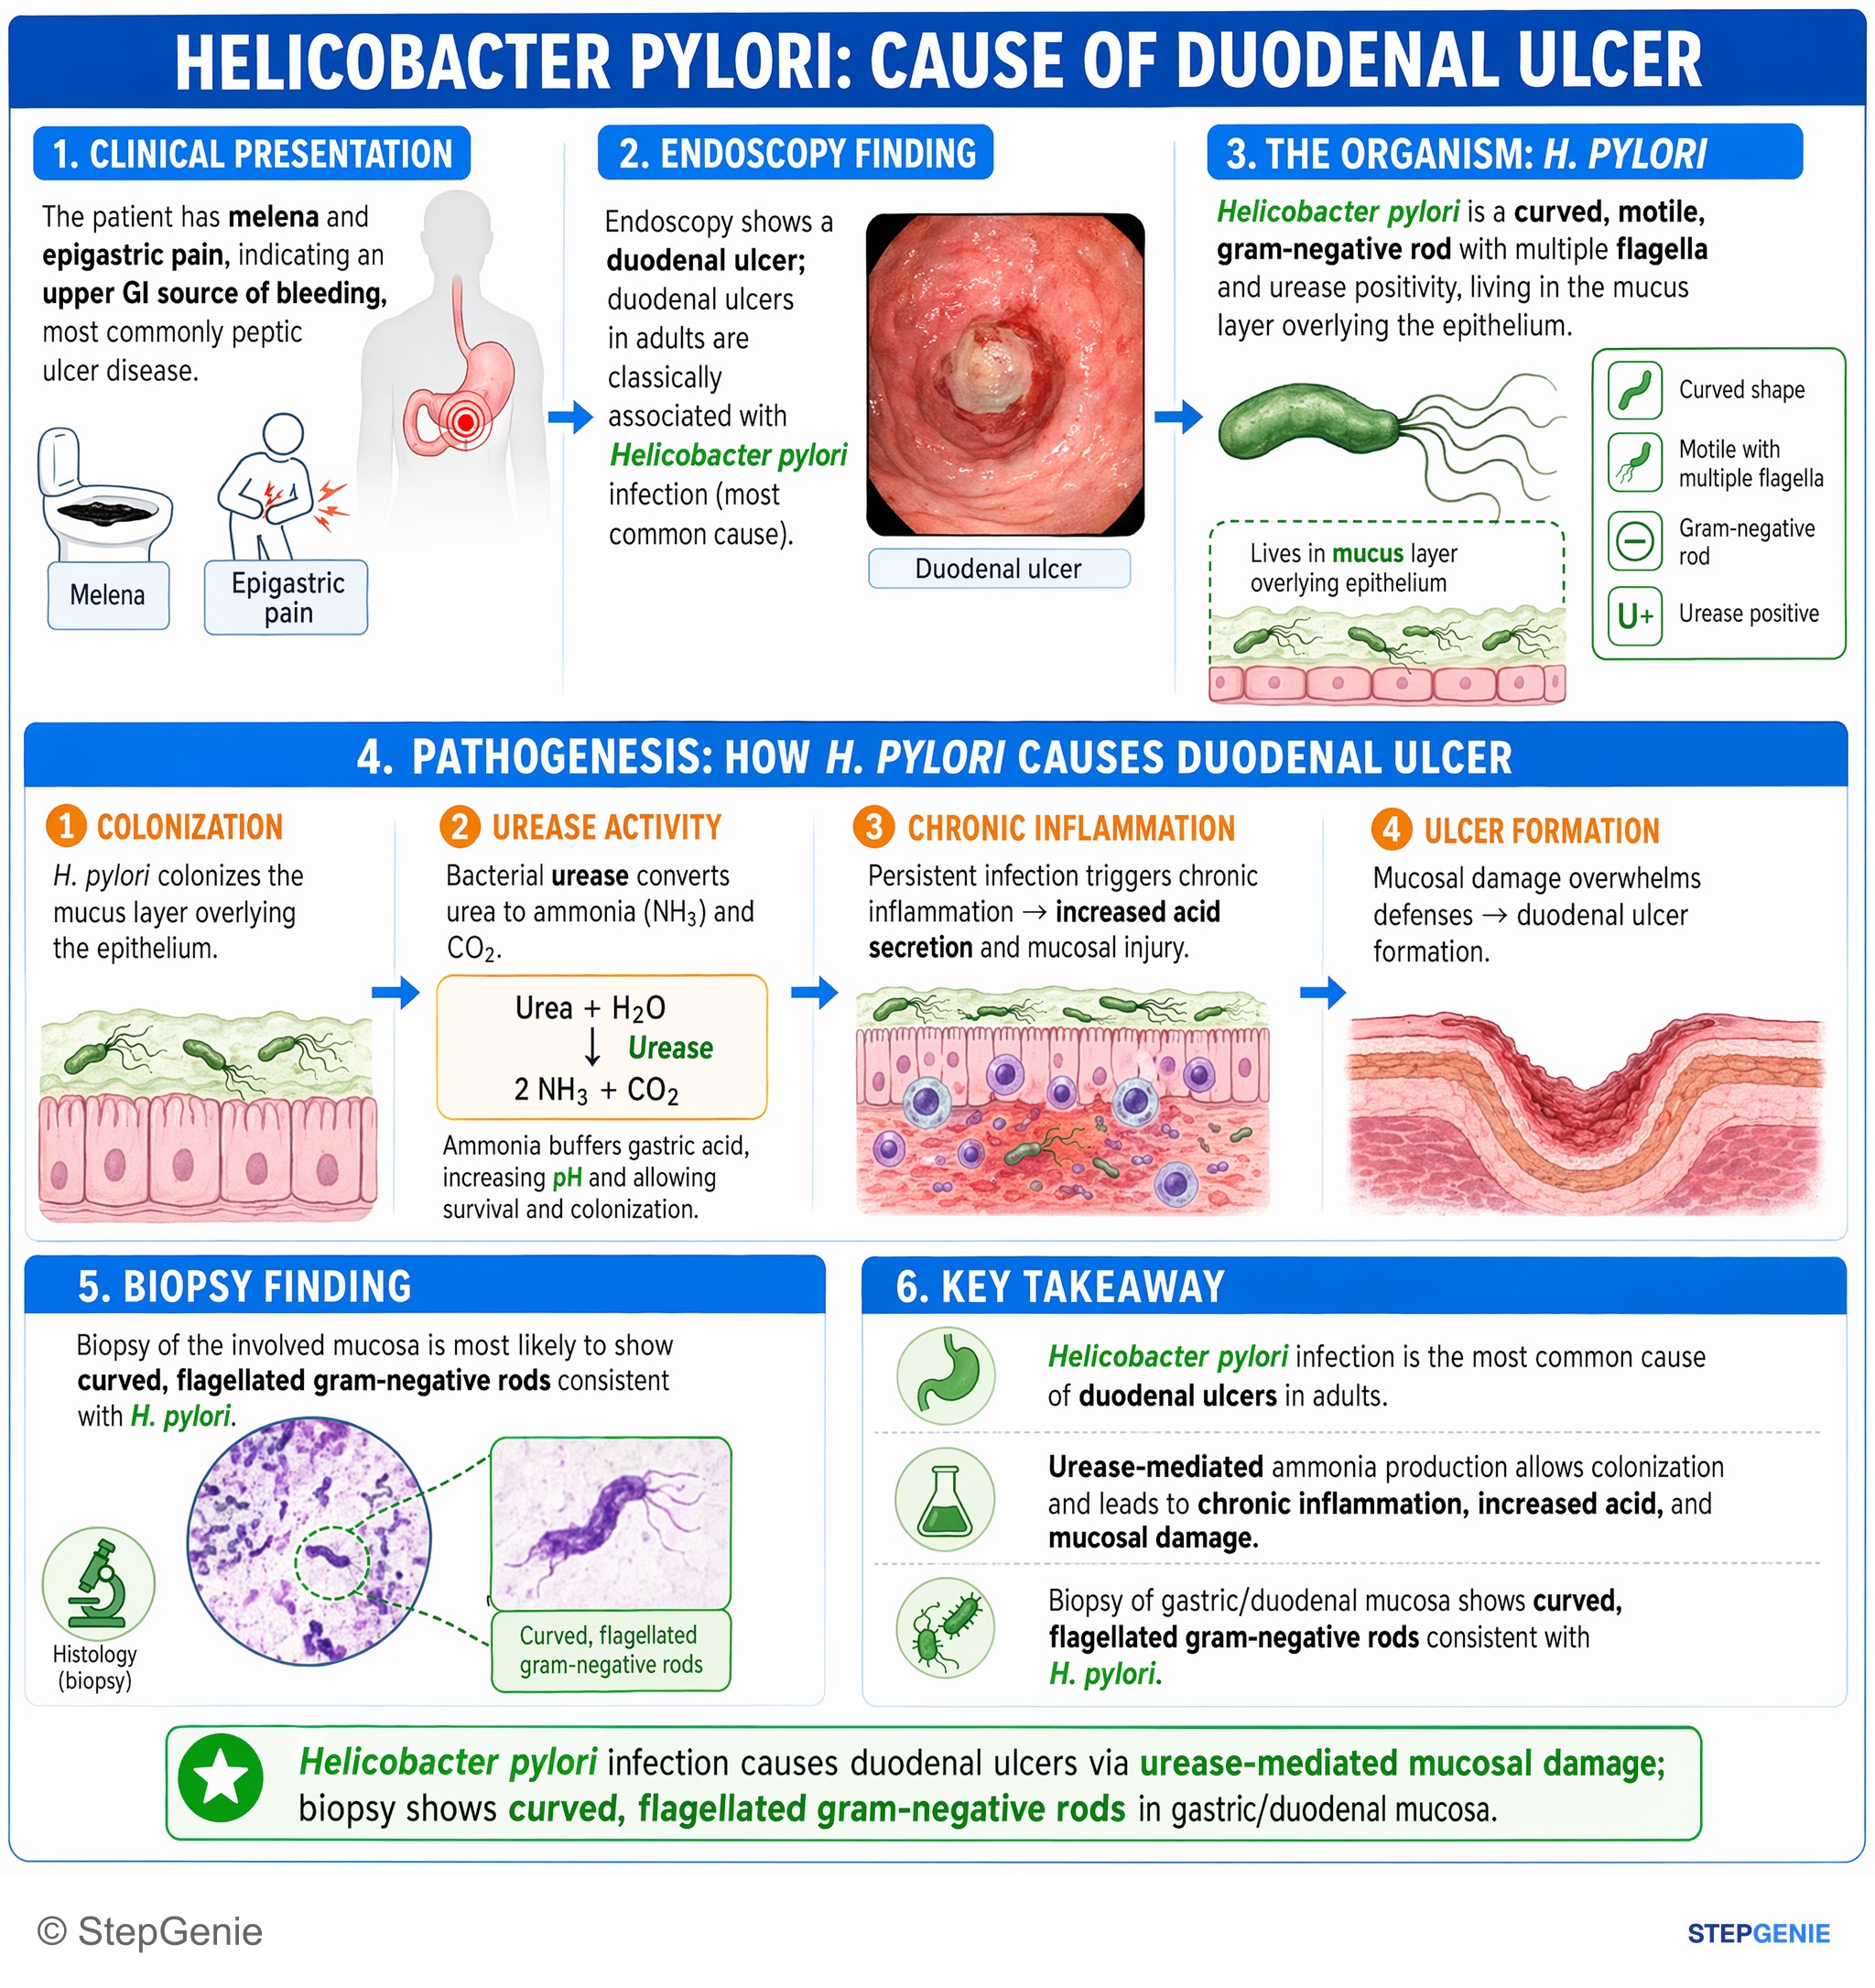
Helicobacter pylori infection causes duodenal ulcers via urease-mediated mucosal damage; biopsy shows curved, flagellated gram-negative…
USMLE Step 1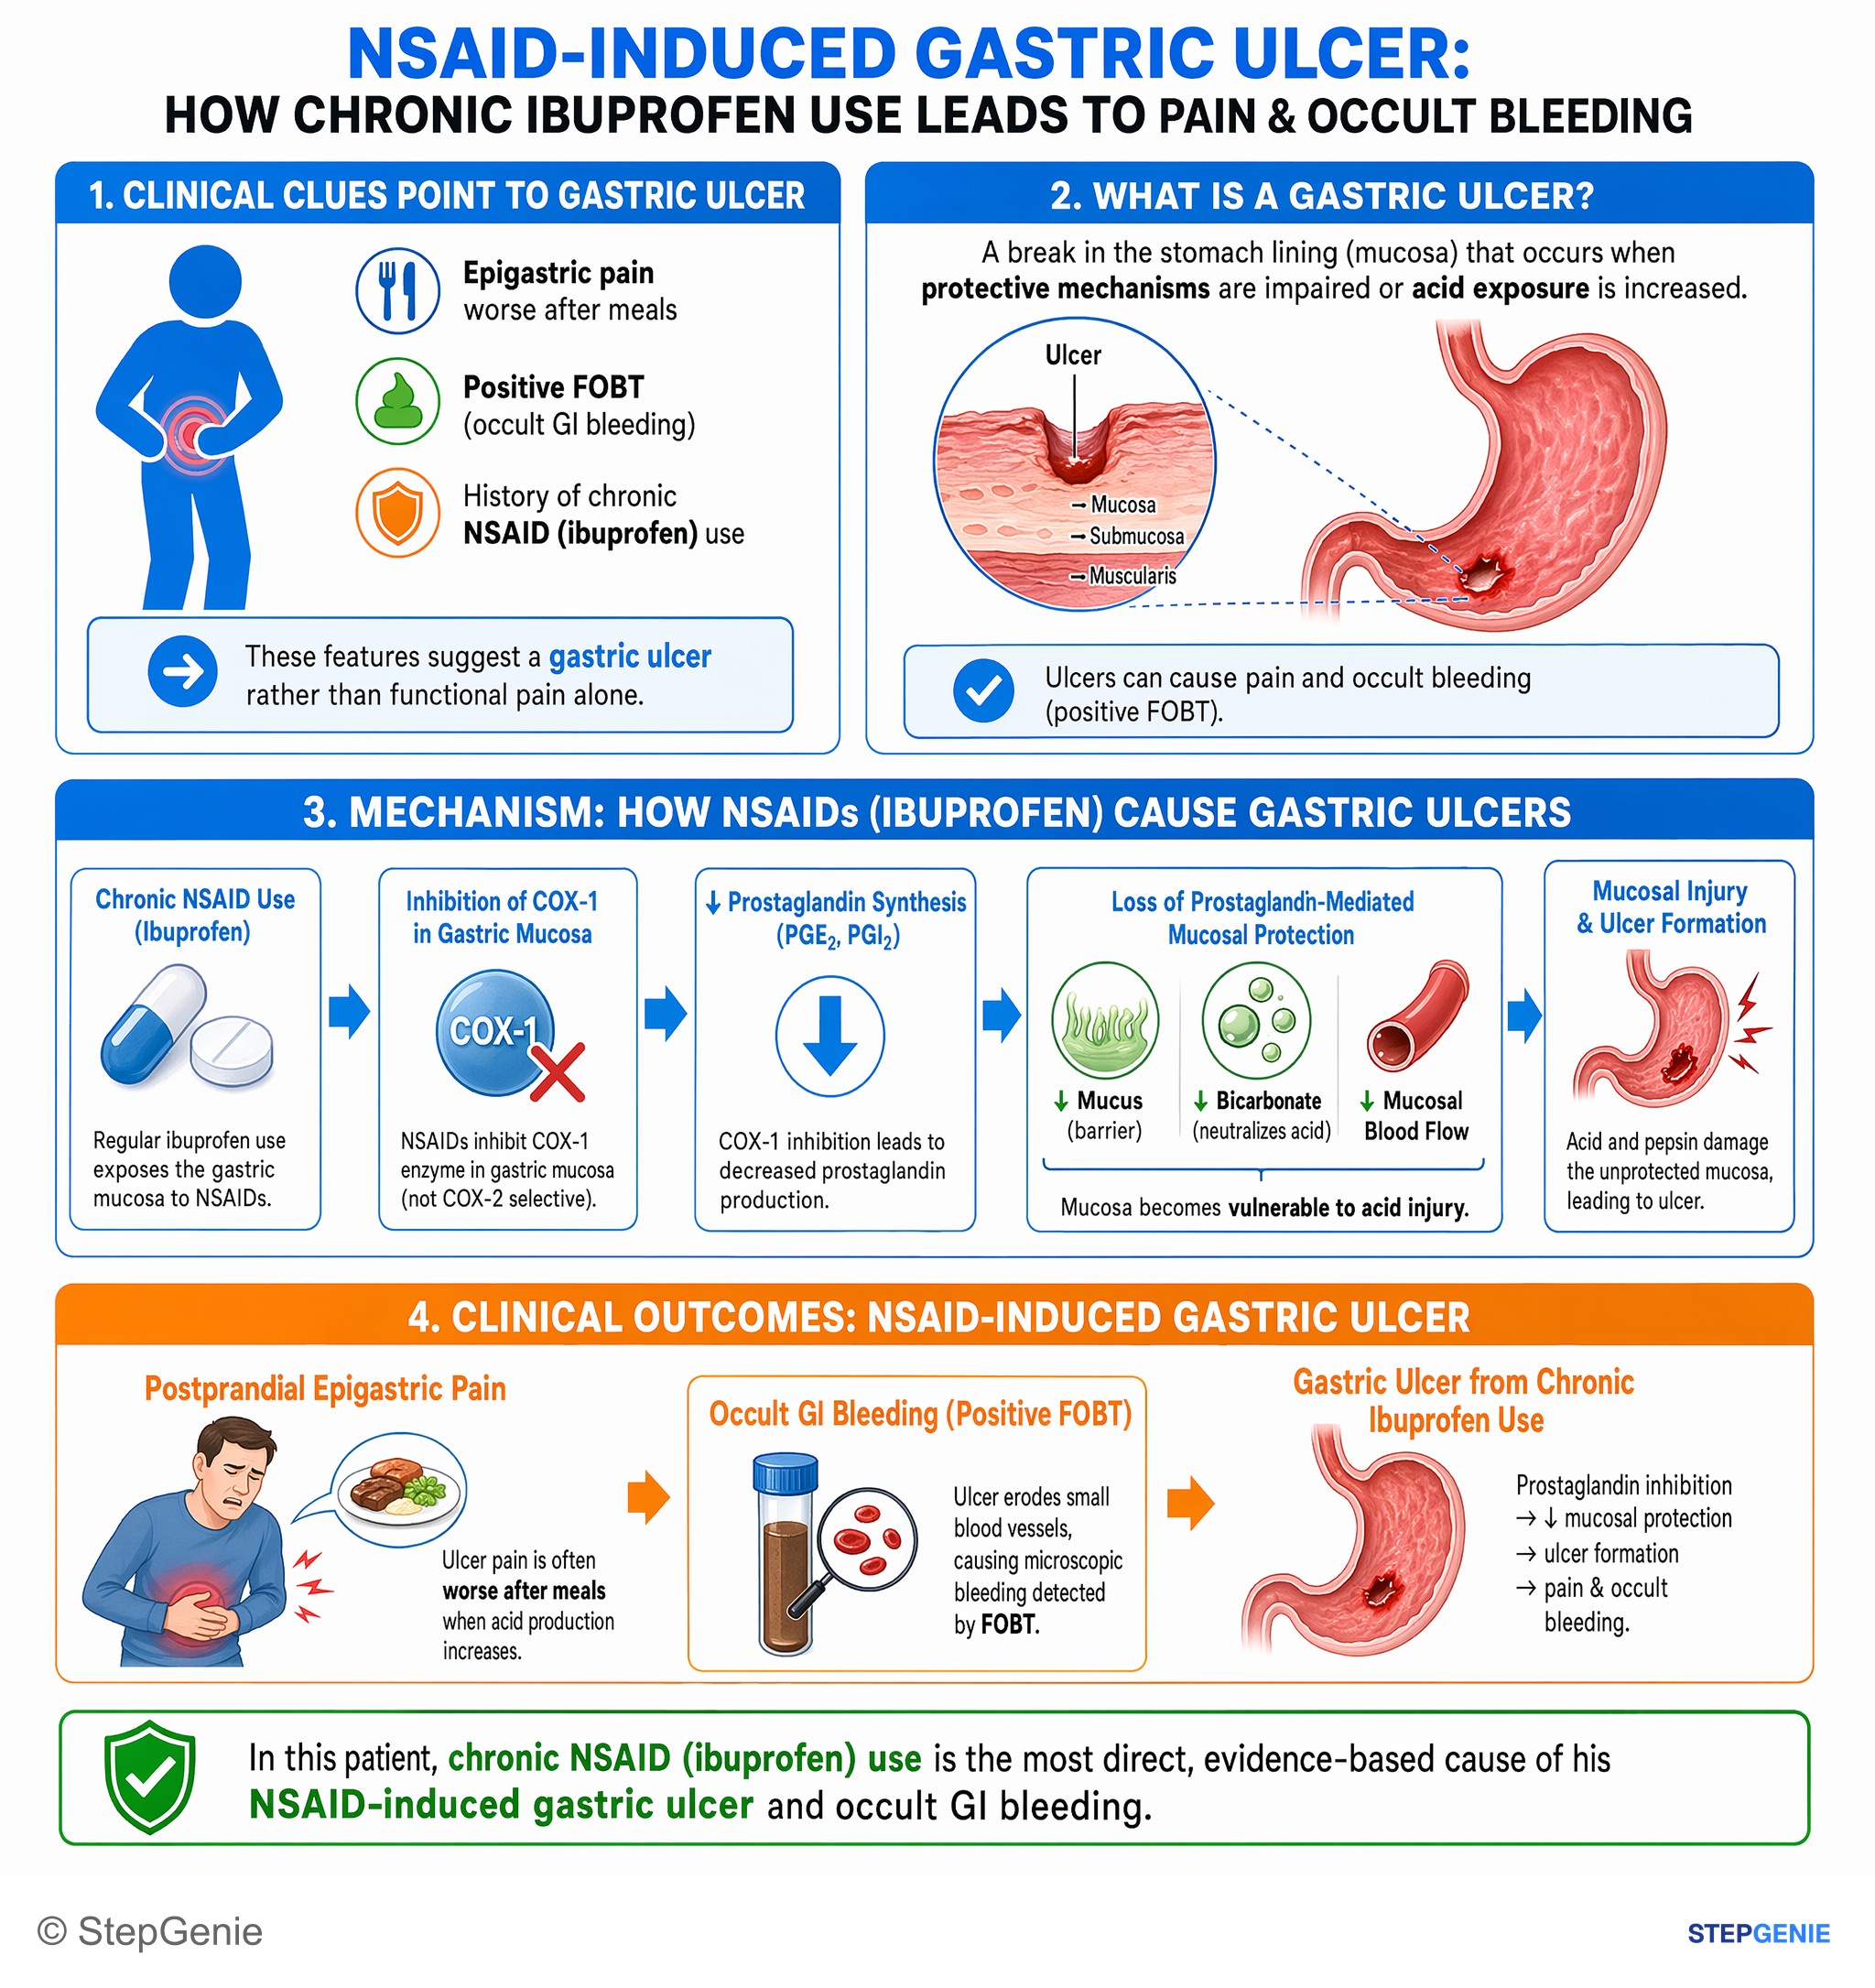
NSAID-induced gastric ulcer from chronic ibuprofen use: prostaglandin inhibition → ↓mucosal protection → postprandial epigastric pain…
USMLE Step 1Frequently Asked Questions
How do you tell a duodenal ulcer from a gastric ulcer on a question stem?
A duodenal ulcer classically improves with meals and returns 2–3 hours later, while a gastric ulcer usually worsens with meals. Duodenal ulcer patients may gain weight because eating relieves pain, whereas gastric ulcer patients may lose weight because eating hurts. Duodenal ulcers are commonly linked to H. pylori and occur in the first part of the duodenum, while gastric ulcers are often related to NSAIDs and classically occur along the lesser curvature.
Why does H. pylori cause duodenal ulcers?
H. pylori promotes duodenal ulcers by damaging mucosal defenses and, in antral-predominant gastritis, increasing acid production. It is urease positive, converting urea to ammonia, which locally buffers acid and contributes to mucosal injury. The infection also causes inflammation, and reduced somatostatin in the antrum leads to increased gastrin and increased acid, a pattern especially associated with duodenal ulcers.
Why do NSAIDs cause peptic ulcers?
NSAIDs cause peptic ulcers by blocking COX, which lowers prostaglandin production and weakens mucosal protection. With fewer prostaglandins, the stomach has less mucus, less bicarbonate, and less mucosal blood flow. That leaves the lining more vulnerable to acid-pepsin injury, so ulcers can form, often in the stomach. This is why NSAID use is a major cause of gastric ulcer disease.
What artery is involved in a bleeding posterior duodenal ulcer?
A bleeding posterior duodenal ulcer classically erodes into the gastroduodenal artery. This is a high-yield anatomic association because posterior duodenal ulcers can cause massive hemorrhage. On exam-style presentations, clues include brisk hematemesis or melena with hypotension or shock. If the stem says posterior duodenal ulcer plus severe bleeding, gastroduodenal artery should be the reflex answer.
What is the first-line treatment for peptic ulcer disease, and what do you do if H. pylori is positive?
First-line treatment for ulcer healing is a proton pump inhibitor and removal of the offending injury, such as stopping NSAIDs if possible. If H. pylori is present, the infection should be eradicated with a regimen such as bismuth quadruple therapy or concomitant therapy. Cure is then confirmed with a urea breath test or stool antigen test, not serology, after avoiding PPIs long enough to reduce false negatives.