Osmotic diuretics are solutes the kidney filters but cannot reclaim. The prototype, mannitol, is freely filtered, less than 10% is reabsorbed and none is secreted, so it holds water in the tubule, mainly in the proximal tubule and the water-permeable descending limb of the loop of Henle. Given IV, it first raises plasma osmolality and pulls water out of cells, which is why it lowers intracranial pressure and intraocular pressure, and why that early volume surge can cause pulmonary edema or worsen heart failure. The FDA label contraindicates it in anuria, severe hypovolemia, pre-existing severe pulmonary congestion or edema, and active intracranial bleeding (except during craniotomy); the main hazards are volume shifts, sodium and potassium swings, and acute kidney injury.
How mannitol works: one molecule, two compartments
Picture mannitol as a sponge that nothing can wring out. It is a six-carbon sugar alcohol that is poorly absorbed from the gut, so it is given IV, and it stays mostly in the extracellular fluid.
- In the blood: extra plasma osmoles pull water out of cells. Mannitol does not cross an intact blood–brain barrier, so water leaves the brain; in the eye it draws water out of the vitreous. The same shift expands plasma volume, which matters most before the extra water is excreted.
- In the tubule: filtered mannitol stays in the lumen. Wherever water normally follows solute passively, the trapped osmoles hold it back, so urine volume rises. Sodium and chloride excretion rise too, but water loss outpaces sodium loss (Merck), which is why prolonged use tends toward hypernatremia.
With normal kidneys its half-life is 0.5–2.5 hours and about 80% of a dose is in the urine within 3 hours; in kidney failure the half-life stretches to about 36 hours (label).
Because mannitol is an osmole the lab formula does not count, it widens the osmolal gap:
\text{Osmolal gap} = \text{measured osm} - \left(2\text{Na}^+ + \frac{\text{glucose}}{18} + \frac{\text{BUN}}{2.8}\right)
The label asks for serum osmolality and osmolal gap monitoring during treatment.
Where it acts in the nephron
| Segment | Normal water handling | Effect of luminal mannitol |
|---|---|---|
| Proximal tubule | About two-thirds of filtered water (and sodium) is reabsorbed here | Trapped osmoles keep water in the lumen |
| Thin descending limb | Aquaporin-rich, freely permeable to water | Less water is drawn into the hypertonic medulla |
| Thick ascending limb | Impermeable to water; NaCl is pumped out | No transporter is blocked; this is where loop diuretics act |
| Collecting duct | Water reabsorbed through ADH-regulated aquaporins | Solute left in the distal lumen limits urine concentration |
The board answer for the site of action is the proximal tubule and the (descending) loop of Henle, the segments where water moves passively.
Clinical uses
| Use | Why it works | Label and exam details |
|---|---|---|
| Raised intracranial pressure, cerebral edema | Draws water out of brain tissue across an intact blood–brain barrier | Osmitrol label: 0.25 g/kg IV over 30 minutes, repeatable every 6–8 hours. An older generic label notes a fall in CSF pressure within 15 minutes, and Merck says the effect lasts a few hours. Merck (brain injury) reserves it for deteriorating patients or before surgery for a hematoma and calls hypertonic saline the more effective osmotic agent |
| Acutely raised intraocular pressure (for example, acute angle-closure glaucoma, before eye surgery) | Draws water out of the vitreous | Osmitrol label: 1.5–2 g/kg IV over at least 30 minutes, given 60–90 minutes before surgery; the older label puts the maximal fall 30–60 minutes after injection. Oral glycerol or isosorbide are other osmotic options (Merck) |
| Oliguric acute kidney injury, toxin excretion | Promotes urine flow | Still on some older-format generic labels; updated labels such as Osmitrol's list only intracranial and intraocular pressure |
Hypertonic saline vs mannitol: both are osmotherapy. OpenStax notes similar clinical outcomes, but hypertonic saline does not cause hypovolemia, which matters in patients who are hypotensive or bleeding, and it can run through a peripheral vein until central access is ready.
Adverse effects, in the order they happen
- Minutes to hours: volume expansion. Water shifted from cells expands plasma volume and can precipitate pulmonary edema (raised capillary hydrostatic pressure, one of the Starling mechanisms of edema) and heart failure exacerbation. The same shift dilutes sodium: translocational hyponatremia with a normal or high serum osmolality, not hypotonic hyponatremia. Compare the true hypotonic patterns in the SIADH vs psychogenic polydipsia guide.
- Hours to days: water loss. Diuresis causes dehydration, hemoconcentration and hypernatremia; the label also lists hypokalemia or hyperkalemia and metabolic acidosis or alkalosis.
- Kidney: acute kidney injury (osmotic nephrosis), especially with large doses, pre-existing kidney disease, nephrotoxins such as aminoglycosides or cyclosporine, or other diuretics. If the patient becomes anuric, mannitol accumulates and the volume load can bring on heart failure and pulmonary edema.
- Brain: confusion, lethargy or coma, and a rebound rise in intracranial pressure hours later, especially when a damaged blood–brain barrier lets mannitol leak into brain tissue.
- Other: hypersensitivity including anaphylaxis; phlebitis, and compartment syndrome after extravasation (hence a large central vein); crystals in cold solutions (warm them and use an in-line filter); falsely low phosphate and false-positive ethylene glycol results; with lithium, excretion rises at first, but toxicity can follow if hypovolemia or kidney injury develops (the label suggests holding lithium).
Contraindications and monitoring
- Current FDA label: known hypersensitivity, anuria, severe hypovolemia, pre-existing severe pulmonary vascular congestion or pulmonary edema, and active intracranial bleeding except during craniotomy.
- Heart failure: the current label lists it as a warning (hypervolemia may exacerbate it); the older-format label contraindicates continuing mannitol if heart failure progresses after it is started, and review texts (OpenStax, StatPearls) list heart failure among contraindications. On an exam, anuria and heart failure are the classic "do not give mannitol" answers.
- Why anuria: mannitol works only if it is filtered. With no filtration it stays in the blood, pulling in water with nowhere to go (it can be removed by dialysis).
- Monitor: serum osmolality and osmolal gap, sodium and potassium, urine output, and kidney, heart and lung status. StatPearls advises stopping if serum osmolality reaches 320 mOsm or more.
Mannitol vs the other diuretic classes
| Class (prototype) | Site | Mechanism | Classic uses | Signature adverse effects |
|---|---|---|---|---|
| Carbonic anhydrase inhibitor (acetazolamide) | Proximal tubule | Blocks bicarbonate reclamation | Acute glaucoma | Normal anion gap metabolic acidosis |
| Osmotic (mannitol) | Proximal tubule, loop of Henle | Nonreabsorbed solute holds water | Raised ICP, raised IOP | Pulmonary edema, sodium swings, AKI |
| Loop (furosemide) | Thick ascending limb | Inhibits NKCC2 | Edema in heart failure, cirrhosis or kidney disease; hypercalcemia | Hypokalemia, metabolic alkalosis, ototoxicity, hyperuricemia |
| Thiazide (hydrochlorothiazide) | Distal convoluted tubule | Inhibits the Na-Cl cotransporter | Hypertension, edema | Hyponatremia, hypokalemia, hypercalcemia, hyperglycemia, hyperuricemia |
| Potassium-sparing (spironolactone, amiloride) | Collecting duct | Blocks aldosterone receptors or ENaC | Hyperaldosteronism, heart failure, preventing hypokalemia | Hyperkalemia, metabolic acidosis; gynecomastia with spironolactone |
Mannitol is the only class with no protein target (no transporter, enzyme, channel or receptor); it works purely by osmosis. The loop class is drilled in the furosemide memory palace.
Other osmotic agents you may meet
- Glucose: in uncontrolled diabetes, filtered glucose exceeds the tubule's transport capacity and drags water into the urine, the classic natural osmotic diuresis (polyuria, thirst, volume depletion).
- Oral urea: a treatment for SIADH. It is filtered and stays in the nephron, forcing out free water despite high vasopressin (Merck).
- Oral glycerol and isosorbide: osmotic options for acute angle-closure glaucoma (Merck). Isosorbide here is not isosorbide dinitrate.
- Hypertonic saline: osmotherapy for intracranial pressure, but not a diuretic.
Exam traps
- "Lower ICP or IOP fast" → mannitol, not a loop diuretic.
- Heart failure patient + mannitol + new crackles → pulmonary edema from volume expansion.
- Low sodium right after mannitol with a high measured osmolality is translocational, not SIADH.
- Polyuria with urine osmolality above 300 mOsm/kg usually means a solute (osmotic) diuresis (mannitol, glucose, urea); below 300 points to a water diuresis such as diabetes insipidus (Merck). The water-diuresis side is in the central vs nephrogenic diabetes insipidus guide.
- Repeated doses can backfire through rebound intracranial hypertension.
Practice question
Vignette. A 72-year-old woman with heart failure with reduced ejection fraction (ejection fraction 25%) has a large middle cerebral artery infarct with cerebral edema and early midline shift. She receives IV mannitol. Two hours later she is short of breath, with bibasilar crackles and an oxygen saturation of 86%. Serum sodium has fallen from 139 to 131 mEq/L, while measured serum osmolality has risen to 312 mOsm/kg. Which mechanism best explains her respiratory decline?
Answer: Expansion of intravascular volume by water drawn out of cells. Mannitol raises plasma osmolality before it is excreted, pulling intracellular water into the circulation; a failing ventricle cannot handle the extra volume, so pulmonary edema follows. The falling sodium with rising osmolality is part of the same water shift (translocational hyponatremia).
Why not the others?
- Inappropriate ADH secretion with hypotonic hyponatremia: her serum osmolality is high, not low.
- Inhibition of NKCC2 in the thick ascending limb: that is how loop diuretics work, and they relieve pulmonary edema rather than cause it.
- Anaphylaxis to mannitol: possible, but expect hypotension, wheeze or urticaria, and it would not explain the osmolality change.
- Hypovolemia from brisk osmotic diuresis: a later effect that lowers filling pressures; it does not cause crackles.
Key takeaways
- Mannitol is filtered, not reabsorbed (under 10%) and not secreted; it holds water in the proximal tubule and loop of Henle.
- IV mannitol first expands plasma volume, then causes a water-predominant diuresis.
- Uses: raised intracranial pressure and raised intraocular pressure; updated labels such as Osmitrol's dropped the old oliguric kidney failure indication.
- Contraindications: anuria, severe hypovolemia, pulmonary edema or severe congestion, active intracranial bleeding; use great caution, or avoid, in heart failure.
- Watch osmolality and osmolal gap, sodium (low early, high later), potassium, kidney function and rebound ICP.
Sources
- OSMITROL (mannitol injection) prescribing information — DailyMed (2025)
- Mannitol Injection, USP 25% (older-format label) — DailyMed (2022)
- Mannitol — StatPearls, NCBI Bookshelf (2024)
- Osmotic Diuretics — OpenStax Pharmacology for Nurses
- Tubular Reabsorption — OpenStax Anatomy and Physiology 2e
- Traumatic Brain Injury (TBI) — Merck Manual Professional Edition (2025)
- Hyponatremia — Merck Manual Professional Edition (2025)
- Polyuria — Merck Manual Professional Edition (2026)
- Loop Diuretics — OpenStax Pharmacology for Nurses
- Thiazide and Thiazide-Like Diuretics — OpenStax Pharmacology for Nurses
- Angle-Closure Glaucoma — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
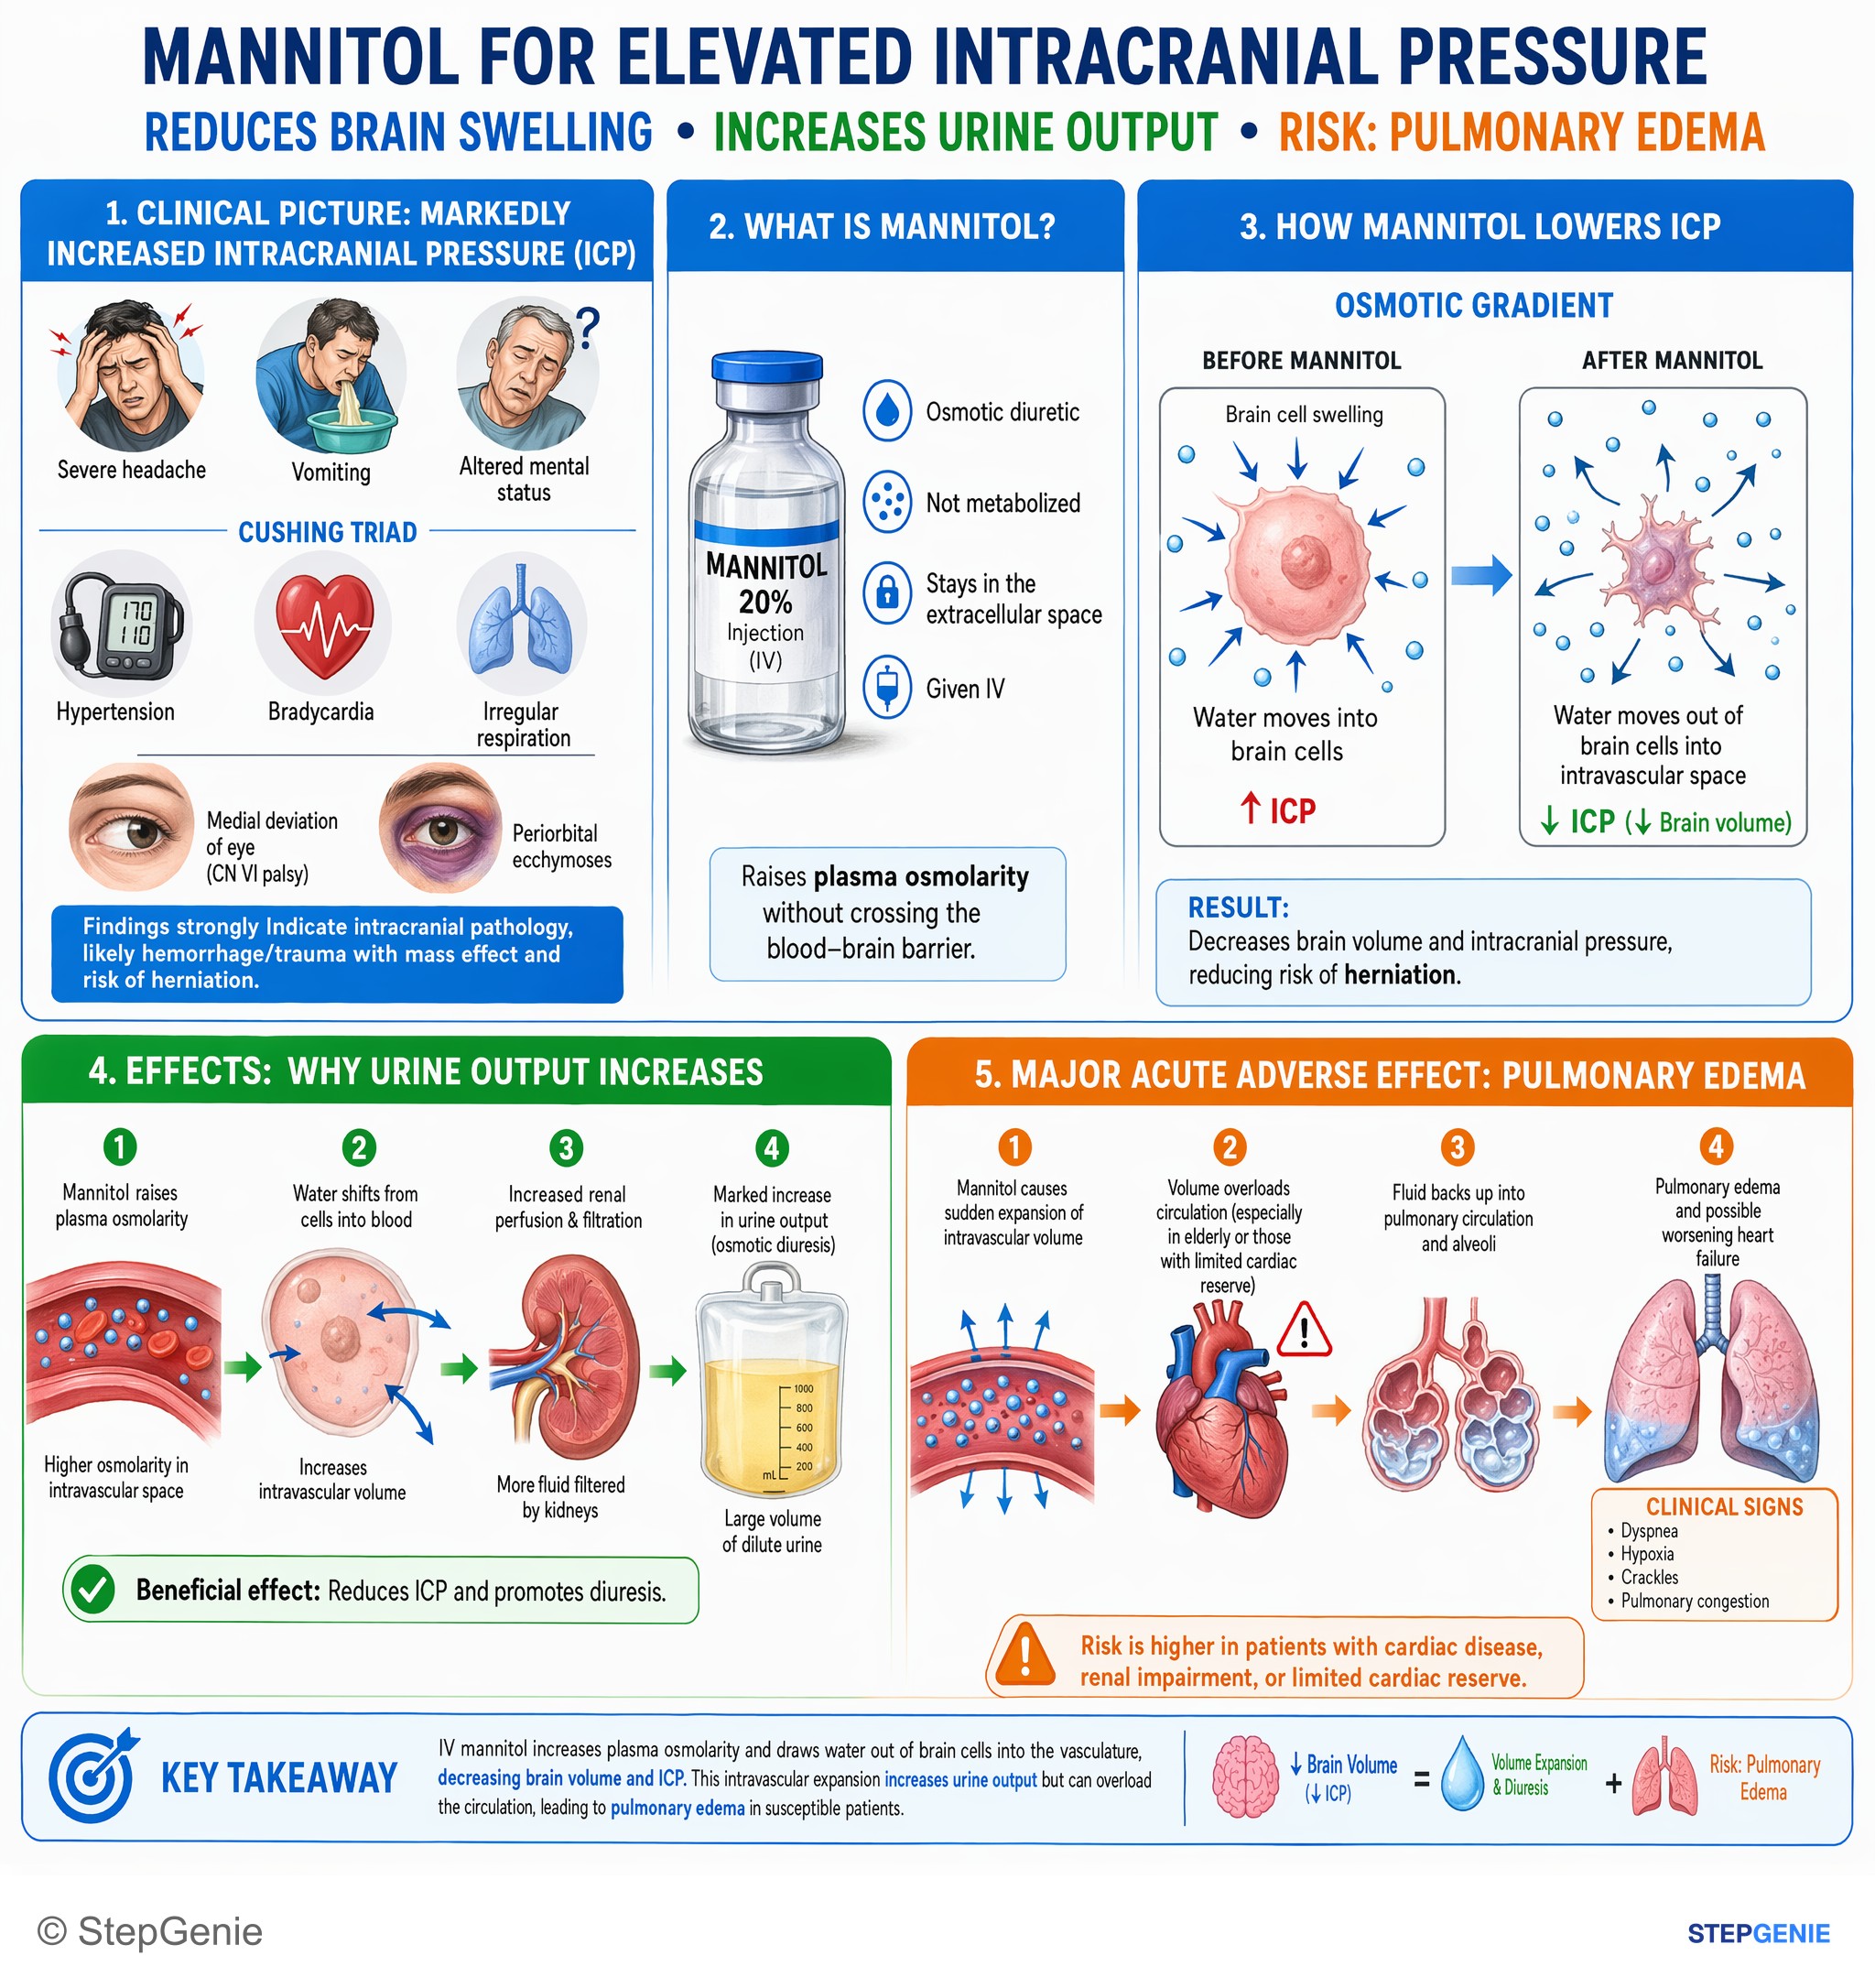
Mannitol for elevated intracranial pressure draws fluid from cells into vasculature, risking pulmonary edema in volume-overloaded or…
USMLE Step 1Frequently Asked Questions
How do osmotic diuretics like mannitol work?
Mannitol is freely filtered at the glomerulus, less than 10% is reabsorbed and none is secreted, so it stays in the tubule and holds water there by osmosis, raising urine volume. Given intravenously, it also raises plasma osmolality before it is excreted, pulling water out of cells into the circulation. That second effect is what lowers intracranial and intraocular pressure.
Where in the nephron does mannitol act?
Mannitol acts mainly where water is normally reabsorbed passively, the proximal tubule and the loop of Henle, especially the water-permeable thin descending limb. It does not block any transporter, unlike loop diuretics, which inhibit NKCC2 in the thick ascending limb, or thiazides, which inhibit the Na-Cl cotransporter in the distal convoluted tubule. Solute left in the lumen also limits how concentrated the final urine can become.
Why is mannitol used for increased intracranial pressure?
Mannitol raises plasma osmolality and cannot cross an intact blood-brain barrier, so water moves out of brain tissue into the blood and intracranial pressure falls, often within about 15 minutes and for a few hours. Repeated doses can backfire, because mannitol leaking through a damaged barrier can cause a rebound rise in pressure. Hypertonic saline is the main alternative osmotic agent and does not cause the hypovolemia that mannitol's diuresis can.
Why is mannitol contraindicated in anuria and heart failure?
Mannitol first expands plasma volume by drawing water out of cells, which can push a failing heart into pulmonary edema; the FDA label lists pre-existing severe pulmonary congestion or edema as a contraindication and warns that it can worsen heart failure. In anuria the drug cannot be filtered, so it accumulates, with a half-life of about 36 hours in kidney failure, and keeps pulling water into the circulation. Severe hypovolemia and active intracranial bleeding, except during craniotomy, are also contraindications.
What electrolyte changes does mannitol cause?
Early on, water drawn out of cells dilutes the serum sodium, a translocational hyponatremia with a normal or high serum osmolality. Later, the diuresis removes more water than sodium, causing dehydration and hypernatremia, and potassium can go either low or high. Mannitol also widens the osmolal gap, so serum osmolality, the osmolal gap, electrolytes and kidney function are monitored during treatment.
What is the difference between mannitol and hypertonic saline for raised intracranial pressure?
Both are osmotic therapies that pull water out of the brain by raising plasma osmolality. Mannitol also causes an osmotic diuresis, which can lead to hypovolemia and kidney injury, whereas hypertonic saline does not cause hypovolemia and can be started through a peripheral vein. The Merck Manual calls hypertonic saline the more effective osmotic agent for lowering intracranial pressure after brain injury, while other sources report similar clinical outcomes.