Nephrolithiasis is stone formation in the urinary tract when urine becomes supersaturated with stone-forming salts. Calcium stones (mostly calcium oxalate) make up about 75-85% of stones, uric acid 8-10%, struvite 7-8% and cystine 1-2% (StatPearls). Each type has a signature: calcium oxalate forms envelope or dumbbell crystals; uric acid forms rhomboid crystals in acidic urine (usually pH below 5.5) and is radiolucent on x-ray but visible on CT; struvite forms coffin-lid crystals in alkaline urine infected by urease-producing bacteria such as Proteus; cystine forms hexagonal crystals in autosomal recessive cystinuria. Non-contrast CT is the preferred first imaging test, and making at least 2.5 L of urine a day is the backbone of prevention.
The four stone types at a glance
| Calcium oxalate | Uric acid | Struvite | Cystine | |
|---|---|---|---|---|
| Share of stones | Calcium stones: 75-85% (most common) | 8-10% | 7-8% | 1-2% |
| Crystal shape | Envelope (dihydrate) or dumbbell (monohydrate) | Rhomboid, rosettes or plates | Coffin-lid | Hexagonal |
| Urine pH | Tends to form below pH 7.2 | Acidic, usually below 5.5 | Alkaline, above 7.2 | Acidic urine lowers solubility; treat to pH 7.5 |
| Plain x-ray | Radiopaque | Radiolucent (CT shows it) | Radiopaque, often staghorn | Faintly radiopaque, ground-glass |
| Typical patient | Hypercalciuria, hyperoxaluria, low urine citrate or volume | Gout, diabetes, obesity, metabolic syndrome | Women with recurrent UTIs (3:1) | Child or young adult with recurrent stones |
| Mechanism | Too much calcium or oxalate, too little citrate or water | Persistently acidic urine ± high urine uric acid | Urease splits urea into ammonia, raising pH | Cystinuria: poor reabsorption of cystine, ornithine, lysine, arginine (COLA) |
| Prevention | Fluids, normal calcium, less sodium and animal protein, thiazide, potassium citrate | Potassium citrate to pH 6-6.5; allopurinol if uric acid stays high | Remove every fragment, culture-directed antibiotics, acetohydroxamic acid | 3 L or more of urine a day, alkalinize to pH 7.5, tiopronin |
Calcium stones: oxalate and phosphate
- Hypercalciuria (Merck: over 250 mg/day in men, over 200 mg/day in women) is a major risk factor. Primary hyperparathyroidism is found in up to 5% of patients with calcium stones (Merck), so check serum calcium in recurrent formers, and PTH when needed (see primary hyperparathyroidism).
- Hyperoxaluria comes from oxalate-rich foods (rhubarb, spinach, cocoa, nuts, tea), from increased oxalate absorption in gut disease (Crohn disease, ulcerative colitis, bacterial overgrowth, chronic pancreatic or biliary disease) or bariatric surgery, from high-dose vitamin C, and rarely from primary hyperoxaluria (Merck, StatPearls).
- Ethylene glycol is metabolized to oxalate: calcium oxalate crystals in the urine plus a high anion gap metabolic acidosis and a raised osmolar gap suggest the ingestion (Merck; see anion gap vs non-anion gap acidosis).
- Hypocitraturia (urine citrate below 320 mg/day) affects about 30% of stone formers. Citrate binds urinary calcium and blocks crystal growth. Causes: distal RTA, chronic diarrhea, hypokalemia, metabolic acidosis, a high animal-protein diet, thiazides, acetazolamide and topiramate (StatPearls).
- Calcium phosphate stones form in alkaline urine. The classic cause is distal (type 1) RTA: urine pH stays above 5.5, with hypercalciuria and low citrate, leading to nephrocalcinosis and stones (Merck; see RTA types 1, 2 and 4).
- Do not restrict calcium. Dietary calcium binds oxalate in the gut; cutting it raises oxalate absorption. Merck advises a normal intake of about 1,000 mg/day (2-3 dairy servings).
- Prevention: fluids for at least 2.5 L of urine a day, less sodium and animal protein, a long-acting thiazide (chlorthalidone, indapamide) to lower urine calcium (see the thiazide mnemonic), potassium citrate for low citrate (aim for urine pH 6-6.5; above about 7.2 favors calcium phosphate stones, StatPearls), and allopurinol for calcium stone formers with high urine uric acid when diet fails.
Uric acid stones
- Uric acid stones form only in acidic urine, usually pH below 5.5. Very rarely, severe hyperuricosuria alone causes them (Merck).
- Associations: gout, diabetes, obesity and metabolic syndrome, older age and a purine-rich diet (StatPearls; see gout vs pseudogout).
- Imaging: radiolucent on plain x-ray, but visible on non-contrast CT.
- Treatment: prolonged alkalinization can sometimes dissolve them. Merck targets urine pH 6-6.5 with potassium citrate, plus more fluid; allopurinol is added when urine uric acid stays high.
Struvite (infection) stones
- Composition: magnesium ammonium phosphate mixed with calcium phosphate ("triple phosphate").
- Mechanism: bacterial urease splits urea into ammonia and CO₂; struvite precipitates only when urine pH exceeds about 7.2 (StatPearls).
- Organisms: Proteus, Klebsiella, Staphylococcus, Pseudomonas, Providencia, Serratia and Morganella; E. coli is the least likely cause (StatPearls).
- Staghorn calculi: branched, usually radiopaque stones filling the renal pelvis and calyces. First-time struvite formers are three times more often women.
- Treatment: complete stone removal (percutaneous nephrolithotomy is the standard for large staghorn stones), because the infection can't be cleared while stone material remains, plus culture-specific antibiotics. Acetohydroxamic acid, a urease inhibitor, slows regrowth, but about 20% of patients have significant side effects, including deep vein thrombosis and hemolytic anemia; its FDA label contraindicates it in pregnancy and when serum creatinine is above 2.5 mg/dL.
Cystine stones (cystinuria)
- Genetics: autosomal recessive, from SLC3A1 (chromosome 2) or SLC7A9 (chromosome 19) variants; about 1 in 10,000 people.
- Defect: the kidney tubules fail to reabsorb cystine, ornithine, lysine and arginine (COLA), but only cystine is insoluble enough to form stones.
- Clues: 80% have their first stone in the first two decades. Hexagonal crystals are diagnostic but appear in only about 25% of cases; the cyanide-nitroprusside screen has a sensitivity of 72% and a specificity of 95%. Stones are faintly radiopaque with a ground-glass look and resist shock wave lithotripsy.
- Treatment (StatPearls): cystine solubility rises from about 250 mg/L at pH 7 to 750 mg/L at pH 8, so the targets are 3 L or more of urine a day and urine pH 7.5; add tiopronin if needed (preferred over penicillamine, which has more side effects).
Renal colic: presentation, imaging and acute care
- Pain: severe colicky flank pain as the stone enters the ureter, often with nausea and vomiting; patients can't lie still. Lower ureteral stones radiate to the groin or genitals, and stones near the bladder cause urgency and frequency. Hematuria is common but not always present (Merck).
- Imaging: non-contrast CT is the preferred initial study in most patients, and low-dose protocols cut radiation (Merck). Ultrasound avoids radiation and is used in pregnancy.
- Analgesia: NSAIDs such as IV ketorolac work well and avoid opioid side effects; opioids are added if needed.
- Medical expulsive therapy: α-blockers such as tamsulosin. Stones of 5 mm or less are more likely to pass on their own (StatPearls: about 90% of stones under 5 mm pass with medical expulsive therapy); extra IV fluid does not speed passage (Merck).
- Home management fits stones under 1 cm without infection or obstruction, when pain is controlled and the patient can drink.
- Emergency: obstruction plus infection. Decompress with a ureteral stent or percutaneous nephrostomy and give antibiotics; remove the stone later (Merck). Obstruction of a solitary kidney, bilateral obstruction and a rising creatinine also need urgent drainage (postrenal AKI).
- Procedures (Merck): shock wave lithotripsy is a reasonable first option for symptomatic stones under 1 cm in the kidney or proximal ureter, ureteroscopy is usually preferred for mid and distal ureteral stones, and percutaneous nephrolithotomy is the treatment of choice for kidney stones over 2 cm.
Workup after the stone
- Stone analysis of a strained stone guides prevention.
- Recurrent stone formers (Merck): serum electrolytes, calcium and uric acid (PTH when needed), plus two 24-hour urine collections on the usual diet measuring volume, pH, calcium, oxalate, uric acid, citrate, sodium and creatinine.
How USMLE tests kidney stones
| Clue in the stem | Answer |
|---|---|
| Stone invisible on x-ray, seen on CT, urine pH 5 | Uric acid |
| Teenager with recurrent stones, hexagonal crystals, positive nitroprusside test | Cystine (cystinuria) |
| Staghorn calculus, urine pH 8, Proteus | Struvite |
| Envelope crystals + anion gap acidosis + osmolar gap | Ethylene glycol (calcium oxalate) |
| Calcium phosphate stones + non-anion gap acidosis + urine pH above 5.5 | Distal (type 1) RTA |
| Crohn disease or bariatric surgery + calcium oxalate stones | Enteric hyperoxaluria |
| "Cut dietary calcium" as prevention | Wrong: it increases oxalate absorption |
Practice question
A 56-year-old man with gout and type 2 diabetes has sudden right flank pain radiating to the groin. Urinalysis shows blood, a pH of 5.0 and rhomboid crystals. A plain abdominal x-ray shows no stone, but non-contrast CT shows a 4-mm stone in the distal right ureter. The stone passes with analgesia and tamsulosin. Which is the most appropriate long-term measure to prevent recurrence?
A. Acetohydroxamic acid B. Hydrochlorothiazide C. Low-calcium diet D. Potassium citrate E. Tiopronin
Answer: D. Acidic urine, rhomboid crystals and a stone missed on x-ray but seen on CT make this a uric acid stone, typical with gout and diabetes. Potassium citrate alkalinizes the urine to pH 6-6.5, where uric acid dissolves, alongside high fluid intake; allopurinol is added if urine uric acid stays high.
- A: acetohydroxamic acid inhibits bacterial urease; it is for struvite stones, which form in alkaline, infected urine.
- B: thiazides lower urine calcium and prevent recurrent calcium stones with hypercalciuria; they do not fix acidic urine.
- C: restricting calcium is the classic wrong answer: less calcium in the gut means more oxalate absorbed, and it does nothing for uric acid.
- E: tiopronin is for cystine stones (cystinuria, hexagonal crystals) when fluids and alkalinization are not enough.
Key takeaways
- Calcium oxalate (envelope or dumbbell crystals) is the most common stone; uric acid is radiolucent and forms in urine with pH below 5.5; struvite (coffin-lid) needs urease and urine pH above 7.2; cystine crystals are hexagonal.
- Non-contrast CT is the first-line imaging test; use ultrasound in pregnancy.
- Obstructing stone + fever = drain now (stent or nephrostomy) plus antibiotics.
- Prevention for everyone: at least 2.5 L of urine a day, normal calcium intake, less sodium and animal protein.
- Targeted prevention: thiazide for hypercalciuria; potassium citrate for low citrate and uric acid stones; complete removal for struvite; alkalinization to pH 7.5 plus tiopronin for cystine.
- Distal RTA → calcium phosphate stones; ethylene glycol → calcium oxalate crystals; gut malabsorption → enteric hyperoxaluria.
Sources
- Urinary Calculi — Merck Manual Professional Edition (2025)
- Renal Calculi, Nephrolithiasis — StatPearls, NCBI Bookshelf (2024)
- Struvite and Triple Phosphate Renal Calculi — StatPearls, NCBI Bookshelf (2023)
- Cystinuria — StatPearls, NCBI Bookshelf (2023)
- Hypocitraturia and Renal Calculi — StatPearls, NCBI Bookshelf (2024)
- Cystinuria — MedlinePlus Genetics
- Renal Tubular Acidosis — Merck Manual Professional Edition (2026)
- Metabolic Acidosis — Merck Manual Professional Edition (2025)
- LITHOSTAT (acetohydroxamic acid) tablet label — DailyMed, US National Library of Medicine (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
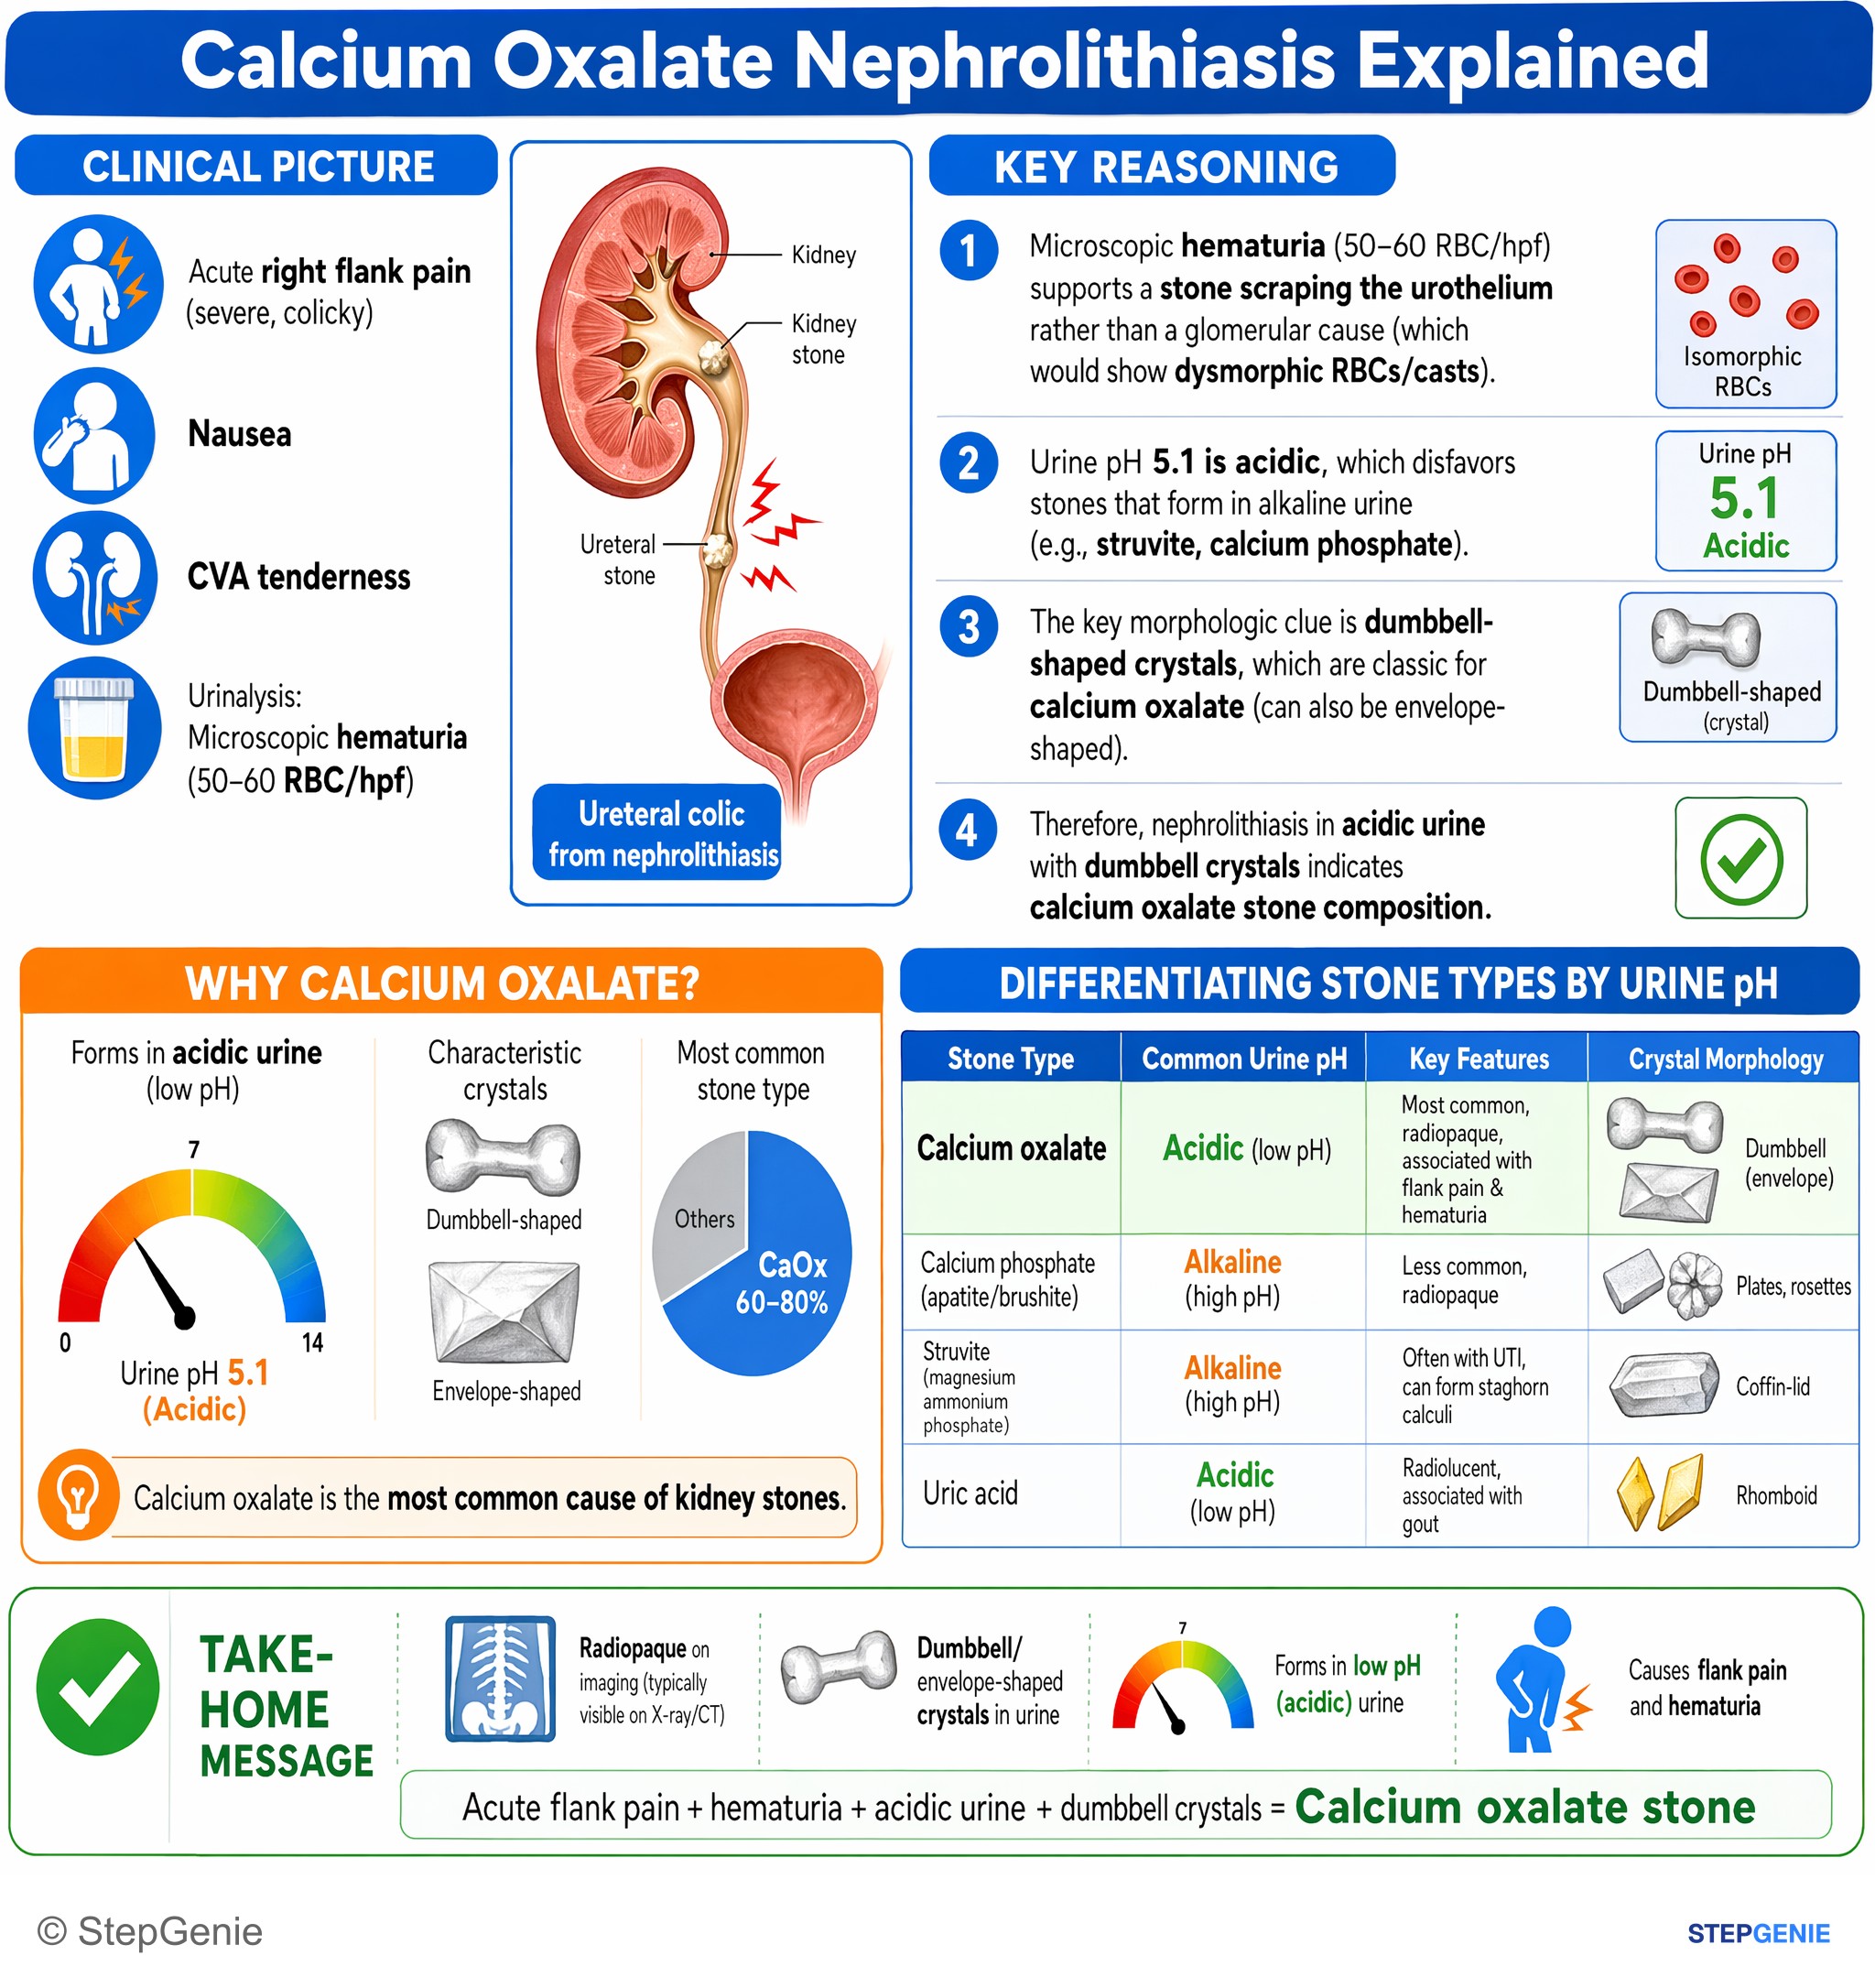
Calcium oxalate stones: most common nephrolithiasis; radiopaque, dumbbell/envelope-shaped crystals, form in low pH acidic urine, cause…
USMLE Step 1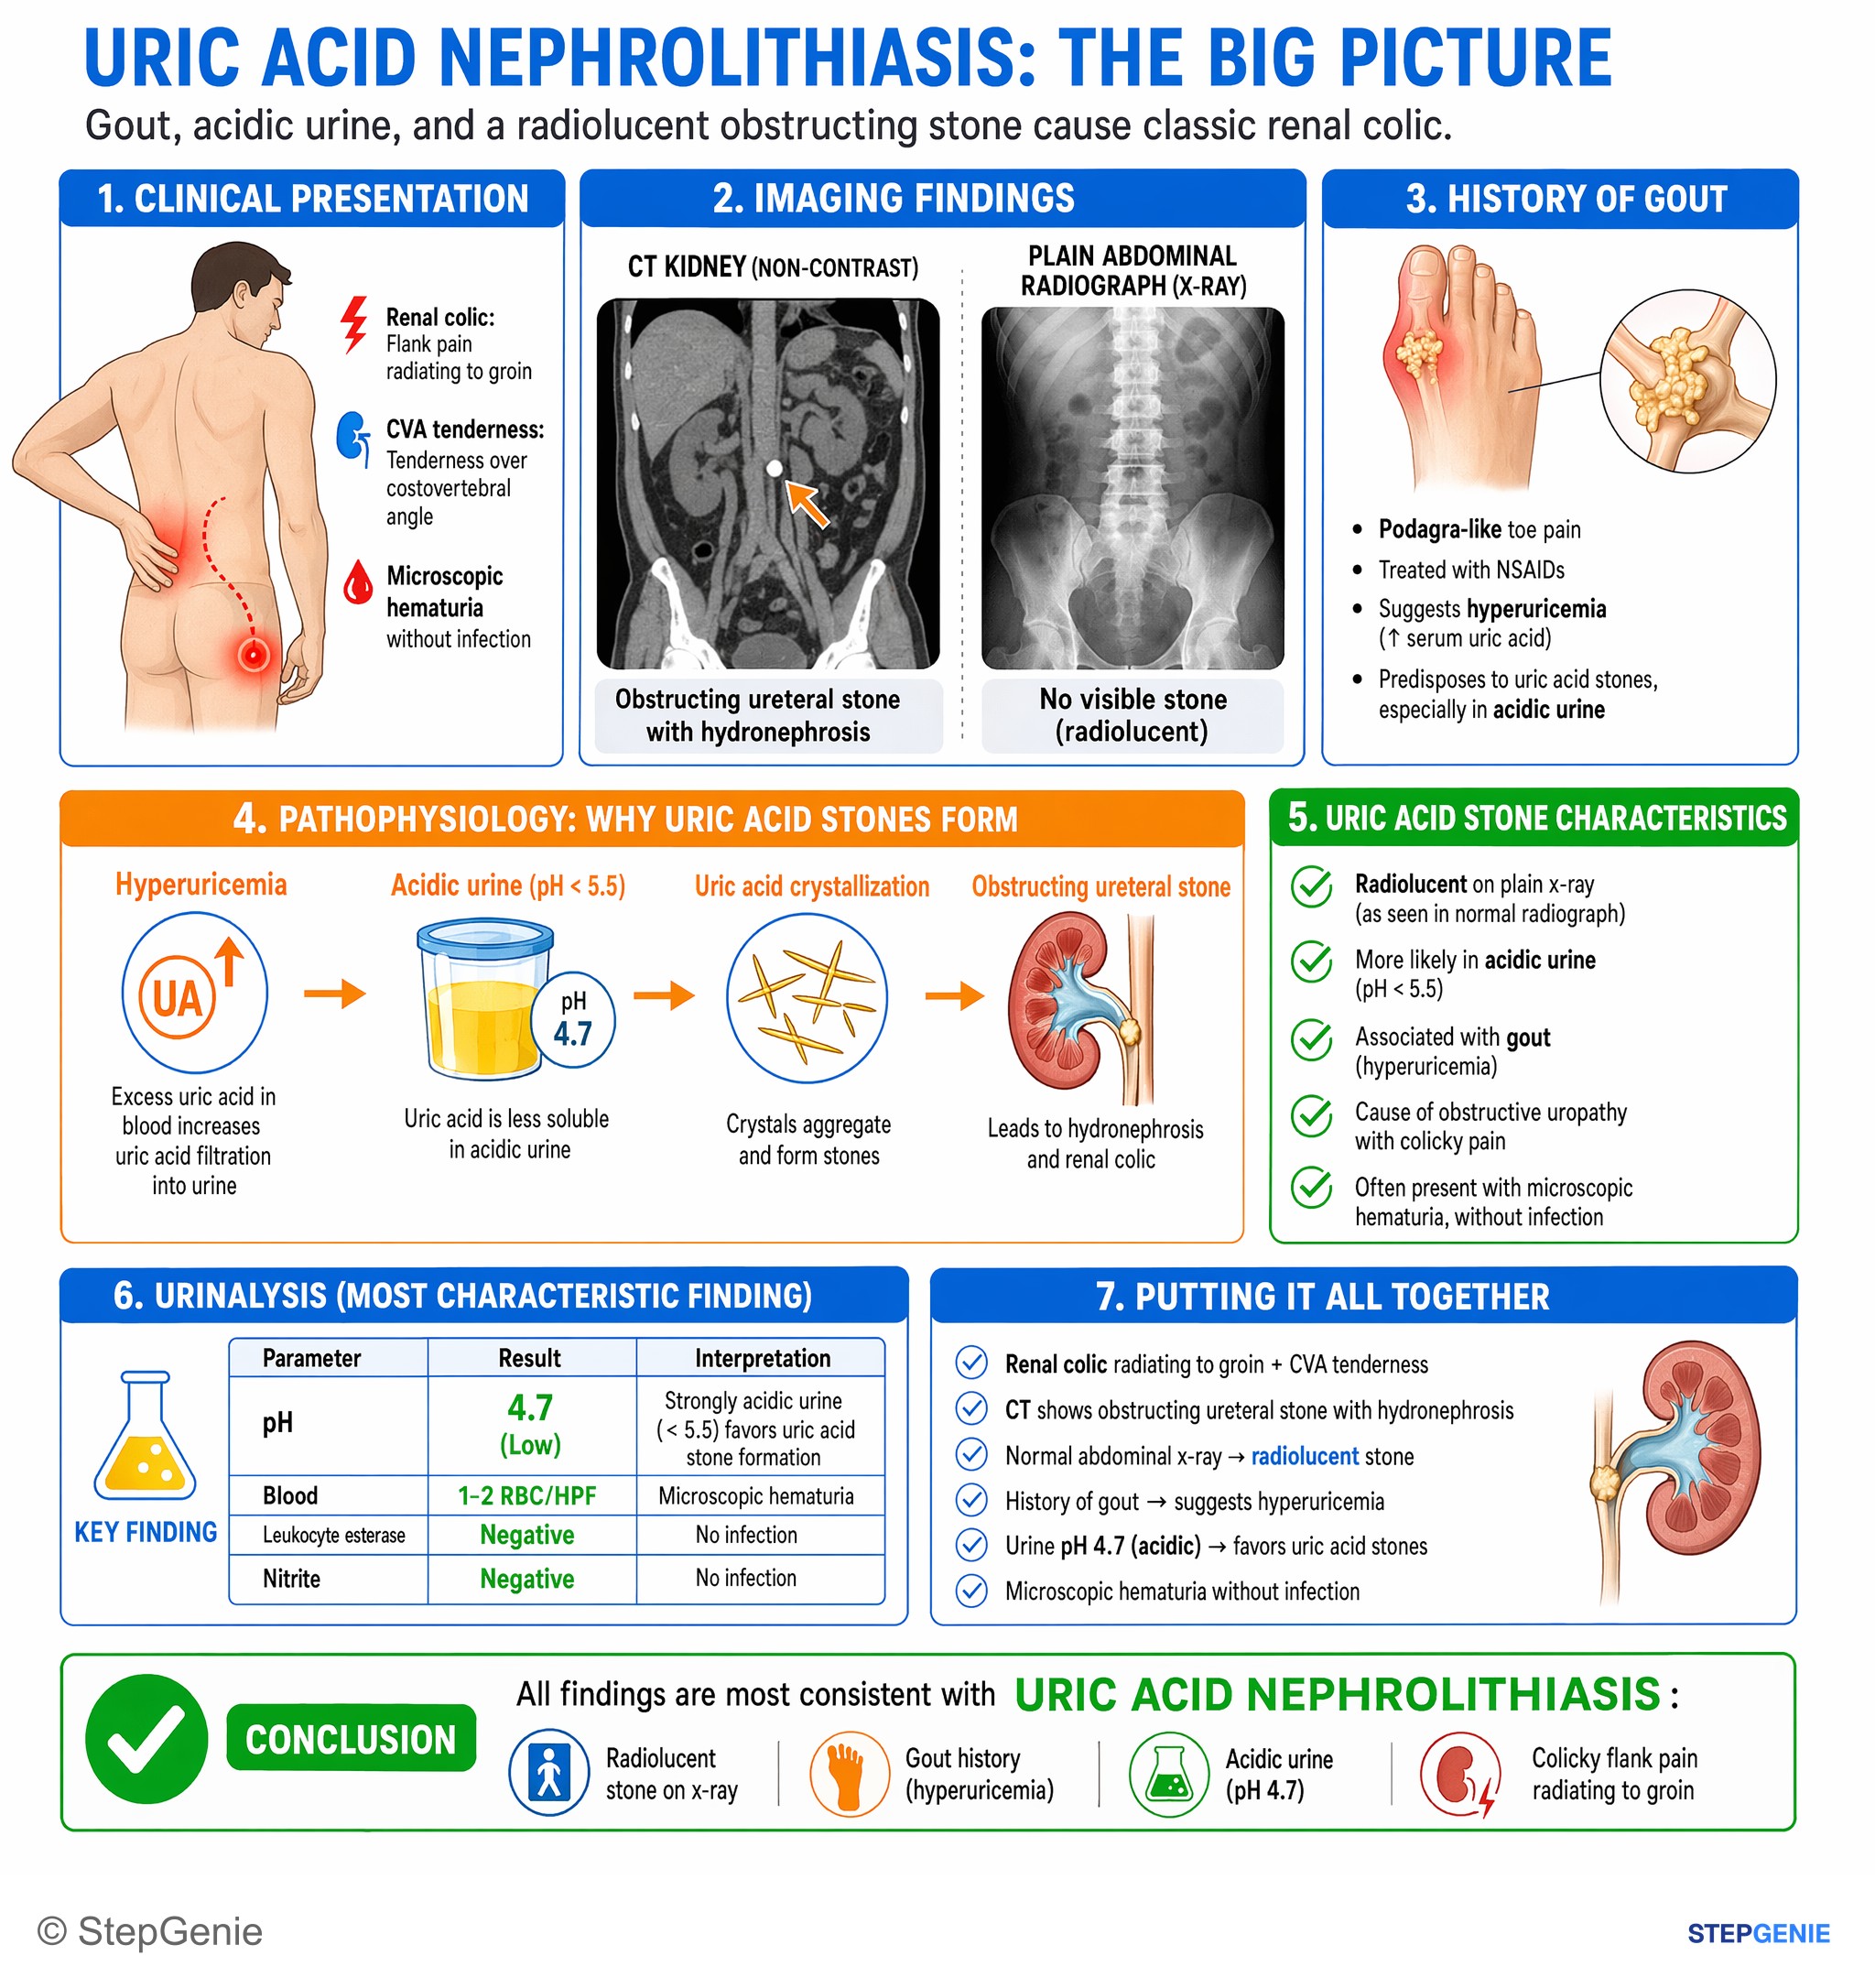
Uric acid nephrolithiasis: radiolucent stone, gout history, acidic urine, colicky flank pain radiating to groin, microscopic hematuria…
USMLE Step 1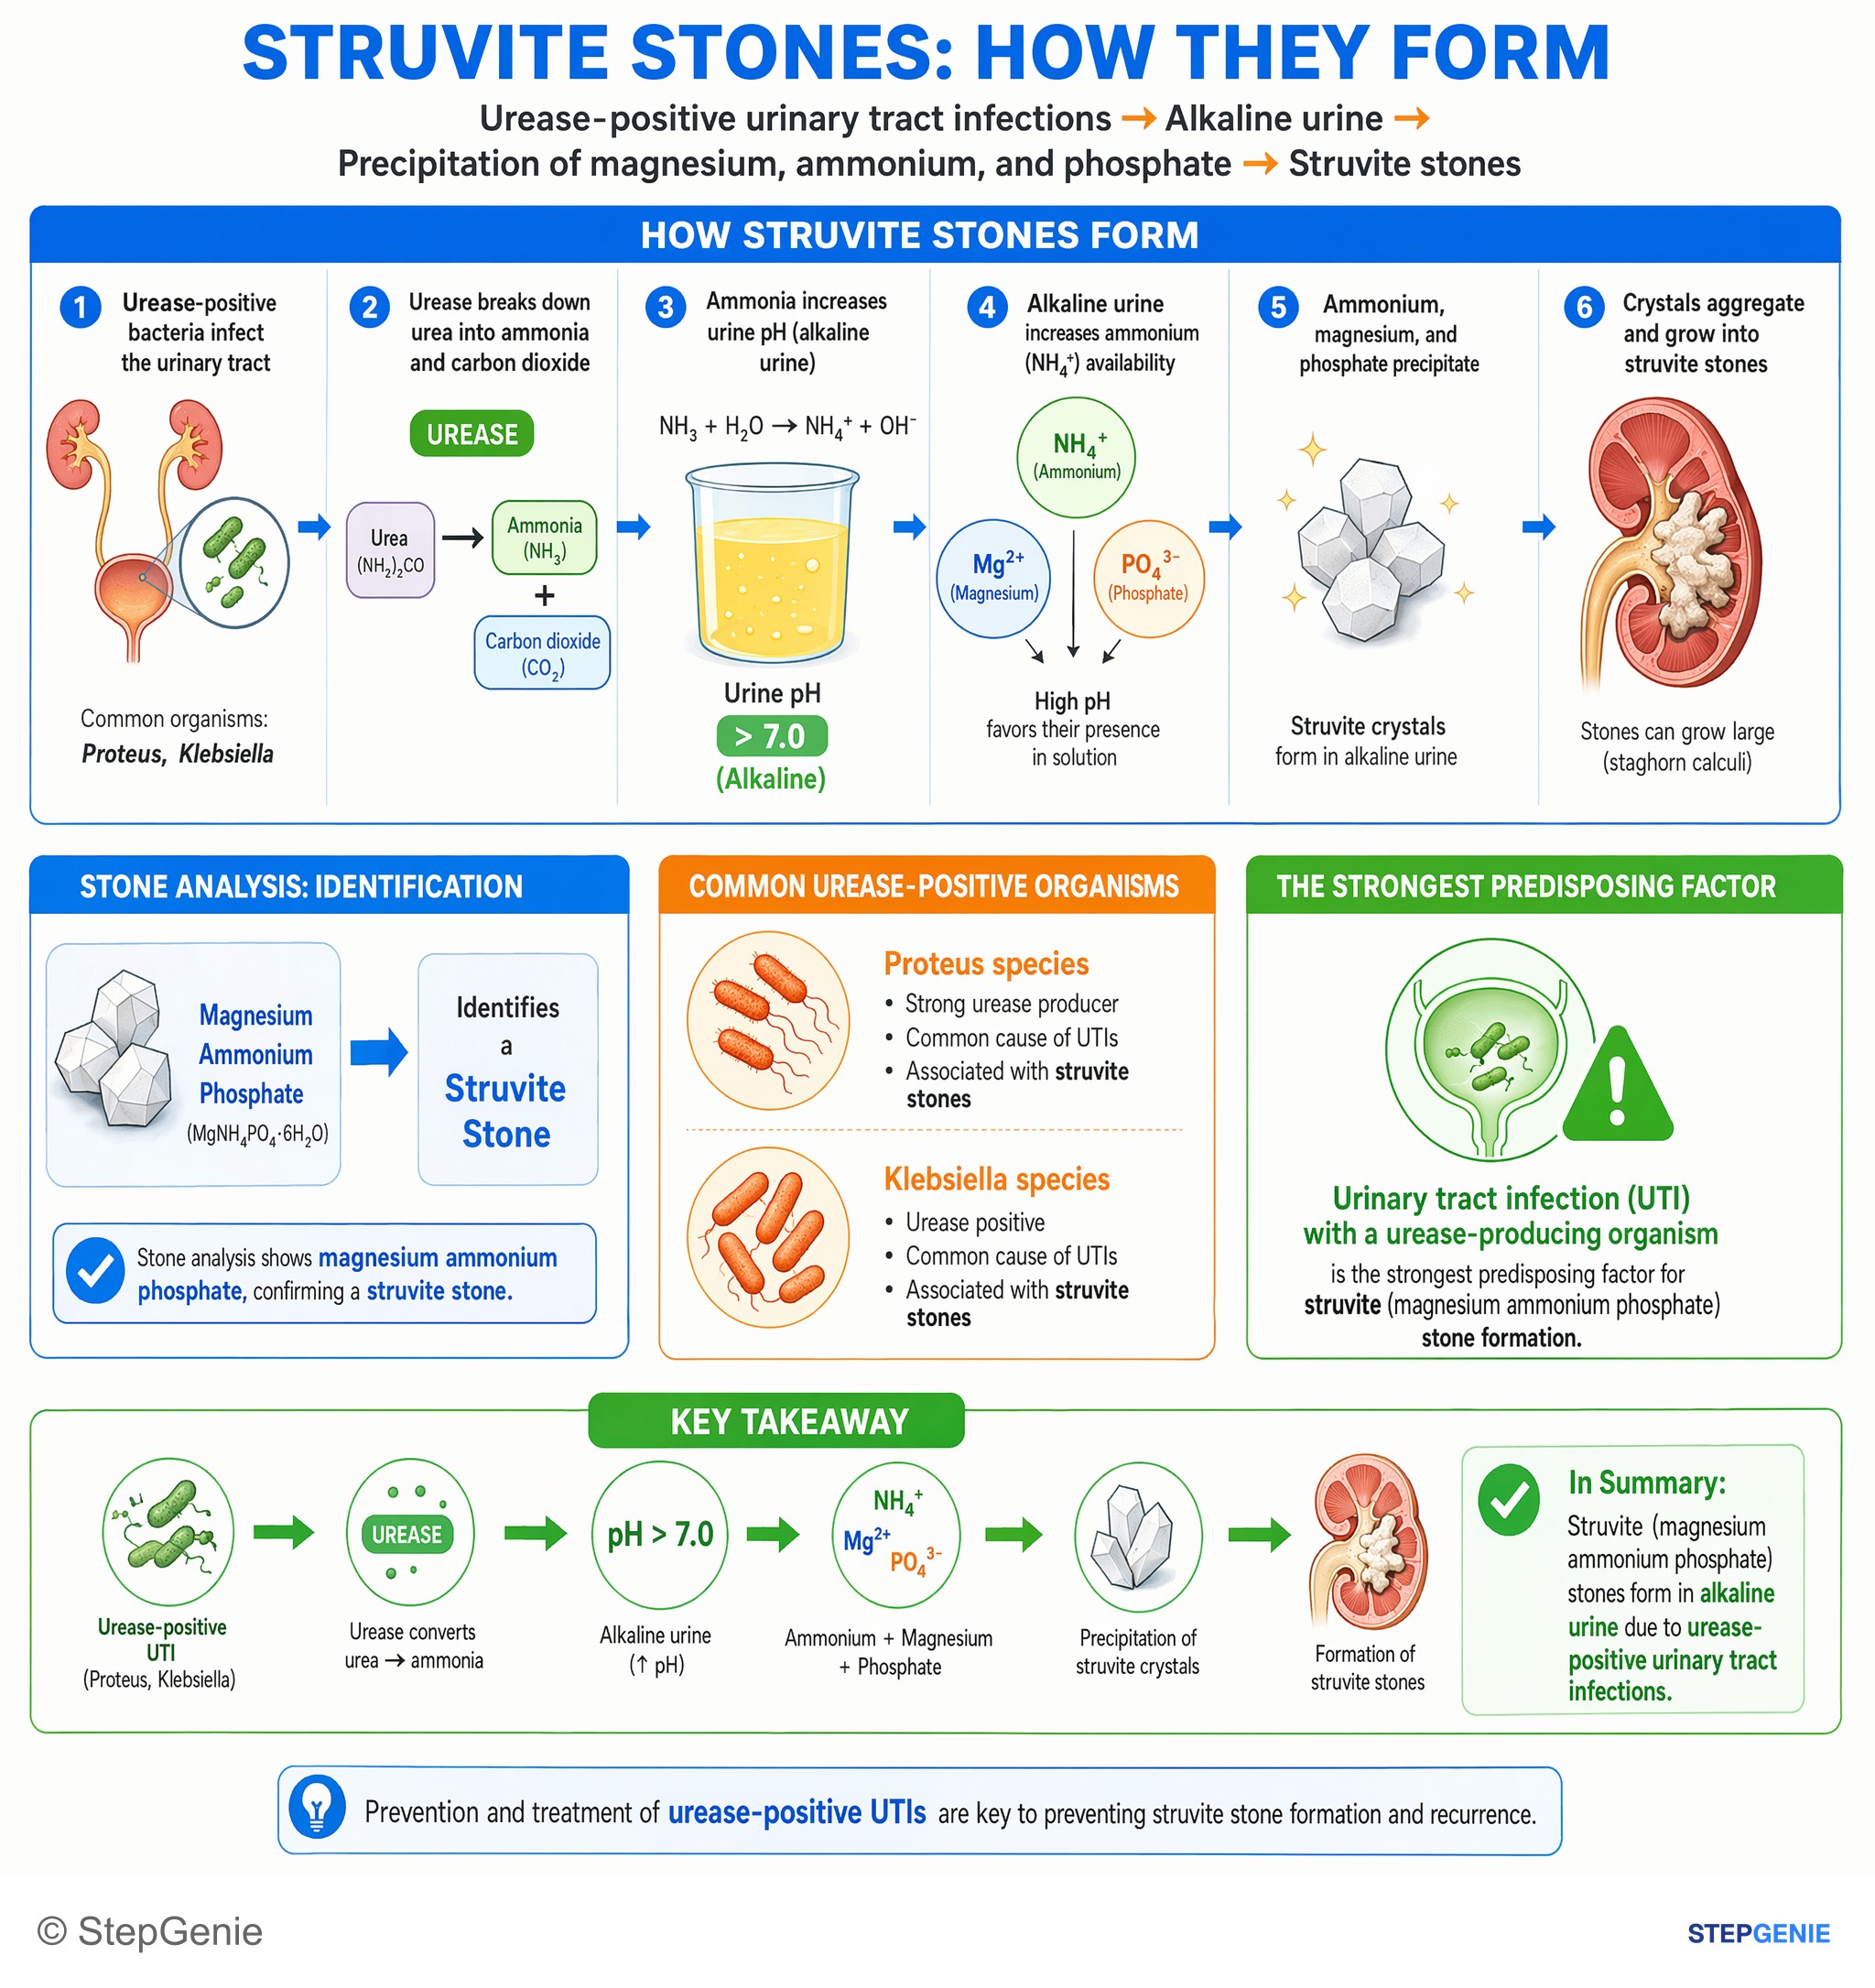
Struvite (magnesium ammonium phosphate) stones form in alkaline urine due to urease-positive urinary tract infections (e.g., Proteus…
USMLE Step 1Frequently Asked Questions
What are the four main types of kidney stones?
Calcium stones, mostly calcium oxalate, are the most common (about 75-85% of stones in StatPearls); uric acid stones make up about 8-10%, struvite (infection) stones 7-8% and cystine stones 1-2%. Calcium oxalate forms envelope or dumbbell crystals, uric acid forms rhomboid crystals in acidic urine, struvite forms coffin-lid crystals in alkaline urine infected by urease-producing bacteria, and cystine forms hexagonal crystals in people with inherited cystinuria.
Which kidney stones are radiolucent on x-ray?
Uric acid stones are the classic radiolucent stones: they do not show on a plain abdominal x-ray but are visible on non-contrast CT. Calcium oxalate and calcium phosphate stones are radiopaque, and struvite stones are usually radiopaque because they contain calcium phosphate. Cystine stones are only faintly radiopaque, with a ground-glass look. This is one reason non-contrast CT, not a plain film, is the preferred first test for a suspected stone.
What urine pH causes each type of kidney stone?
Uric acid stones form in acidic urine, usually below pH 5.5, and cystine is also less soluble in acidic urine. Calcium oxalate stones tend to form below about pH 7.2. Calcium phosphate stones form in alkaline urine, as in distal renal tubular acidosis, and struvite stones need urine above about pH 7.2, created when bacterial urease splits urea into ammonia. Treatment uses this: alkalinize the urine to pH 6-6.5 for uric acid stones and to pH 7.5 for cystine stones.
What bacteria cause struvite stones?
Struvite stones need bacteria that make urease, which splits urea into ammonia and raises urine pH above about 7.2. Proteus is the classic cause; Klebsiella, Staphylococcus, Pseudomonas, Providencia, Serratia and Morganella can also make urease, while E. coli is the least likely cause. Struvite stones can grow into staghorn calculi that fill the renal pelvis and calyces, so treatment requires complete stone removal plus culture-directed antibiotics.
How do you prevent calcium oxalate kidney stones?
Drink enough fluid to make at least 2.5 liters of urine a day, keep a normal calcium intake of about 1,000 mg a day, and cut back on sodium and animal protein. Restricting calcium backfires, because dietary calcium binds oxalate in the gut. For recurrent stones, 24-hour urine testing guides drug therapy: a thiazide for high urine calcium, potassium citrate for low urine citrate, and allopurinol for high urine uric acid when diet changes are not enough.
What is the best imaging test for a kidney stone?
Non-contrast CT of the abdomen and pelvis is the preferred initial test for most patients. It shows the stone's size and location, including radiolucent uric acid stones, the degree of obstruction and other possible causes of the pain, and low-dose protocols reduce the radiation. Ultrasound avoids radiation, can show obstruction and is used in pregnancy. A plain x-ray misses uric acid stones.