Gastric cancer is one of those Step topics that feels “vague” until you can see the pattern: where it occurs, who it hits, how it spreads, and which histology matches the story. Here’s a quick, draw-it-out way to lock it in—perfect for rapid review and shareable notes.
The Draw-it-out Method (30 seconds)
Grab a scrap paper and draw a stomach shaped like a “J”. Then add these 4 features:
- A target/bullseye in the antrum → intestinal-type adenocarcinoma (classically distal)
- A “leather jacket” outline around the whole stomach → diffuse-type adenocarcinoma (linitis plastica)
- A left supraclavicular node labeled “V” → Virchow node metastasis
- A belly button dot → Sister Mary Joseph nodule (periumbilical metastasis)
One-liner mnemonic
“Bullseye distal = intestinal; leather jacket = diffuse; V-node + belly button = metastasis.”
What You Just Drew (and why it matters)
1) Intestinal-type gastric adenocarcinoma (the “bullseye”)
High-yield vibe: environment-driven, gland-forming, older patient, distal stomach.
Associations to remember (USMLE favorites):
- Chronic H. pylori gastritis → intestinal metaplasia → dysplasia → carcinoma
- Nitrosamines (smoked/salted foods), low fruits/vegetables
- Chronic atrophic gastritis (including autoimmune gastritis via metaplasia pathway)
- More common in older patients, historically more distal (antrum/lesser curvature)
Histology buzzwords:
- Gland formation
- “Intestinal metaplasia” with goblet cells is often in the stem
2) Diffuse-type gastric adenocarcinoma (the “leather jacket”)
High-yield vibe: infiltrative, signet rings, younger, worse prognosis, genetic.
Key mechanism:
- Loss of E-cadherin (CDH1) → decreased cell adhesion → infiltrative growth
Pathology clue:
- Signet ring cells (mucin pushes nucleus to the periphery)
Classic gross description:
- Linitis plastica = rigid, thickened stomach with loss of rugal folds (“leather bottle/jacket stomach”)
Step-relevant association:
- Hereditary diffuse gastric cancer (CDH1 mutations)
- Often co-associated with lobular breast carcinoma risk
Spread Patterns You Must Know (aka why we drew the “V” and the belly button)
Lymphatic spread
- Virchow node: left supraclavicular lymph node enlargement
- Think: abdominal malignancy draining via thoracic duct
Hematogenous spread
- Liver metastases are common (portal circulation logic)
Transcoelomic/peritoneal spread
- Sister Mary Joseph nodule: periumbilical metastatic implant
- Can also seed ovaries → Krukenberg tumor
- Bilateral ovarian metastases with signet ring cells (often from diffuse gastric cancer)
Symptoms & Clinical Clues (what shows up in stems)
Alarm symptoms (don’t ignore):
- Unintentional weight loss
- Early satiety (especially with linitis plastica)
- Anemia (often iron deficiency from occult bleeding)
- Persistent vomiting, dysphagia (more proximal involvement)
Common presentations:
- Vague epigastric pain, anorexia, nausea
- Occult GI bleeding → fatigue, pallor
H. pylori: the nuance Step questions love
H. pylori is most strongly linked to:
- Intestinal-type gastric adenocarcinoma
- MALT lymphoma (can regress with eradication therapy)
Board-style linkage:
- Chronic inflammation → intestinal metaplasia → dysplasia → carcinoma
- Distal stomach involvement is classic, but modern epidemiology varies—Step stems still often test the traditional patterns.
Rapid Compare Table (copy/paste-friendly)
| Feature | Intestinal-type | Diffuse-type |
|---|---|---|
| Core idea | Environmental/inflammatory pathway | Cell-adhesion defect |
| Key association | H. pylori, nitrosamines, chronic gastritis | CDH1 (E-cadherin) loss |
| Histology | Gland-forming | Signet ring cells |
| Gross | Often ulcerating mass | Linitis plastica, thick rigid wall |
| Typical patient | Older | Younger (can be) |
| Spread clue | Virchow, SMJ nodule possible in both | Krukenberg classically tied to signet rings |
Micro–Pearls (1–2 liners you can recall under pressure)
- Virchow node (left supraclavicular) = “abdominal cancer reached the thoracic duct.”
- Sister Mary Joseph nodule = periumbilical metastasis via peritoneal spread.
- Krukenberg tumor = bilateral ovarian metastases with signet ring cells, often gastric.
- Diffuse gastric cancer = E-cadherin loss → infiltrative growth → early satiety.
Mini Self-Check (3 quick prompts)
- A rigid stomach with loss of rugae and early satiety → Diffuse adenocarcinoma (linitis plastica)
- Left supraclavicular node enlargement in GI malignancy → Virchow node
- Bilateral ovarian masses with signet ring cells → Krukenberg tumor (gastric source)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
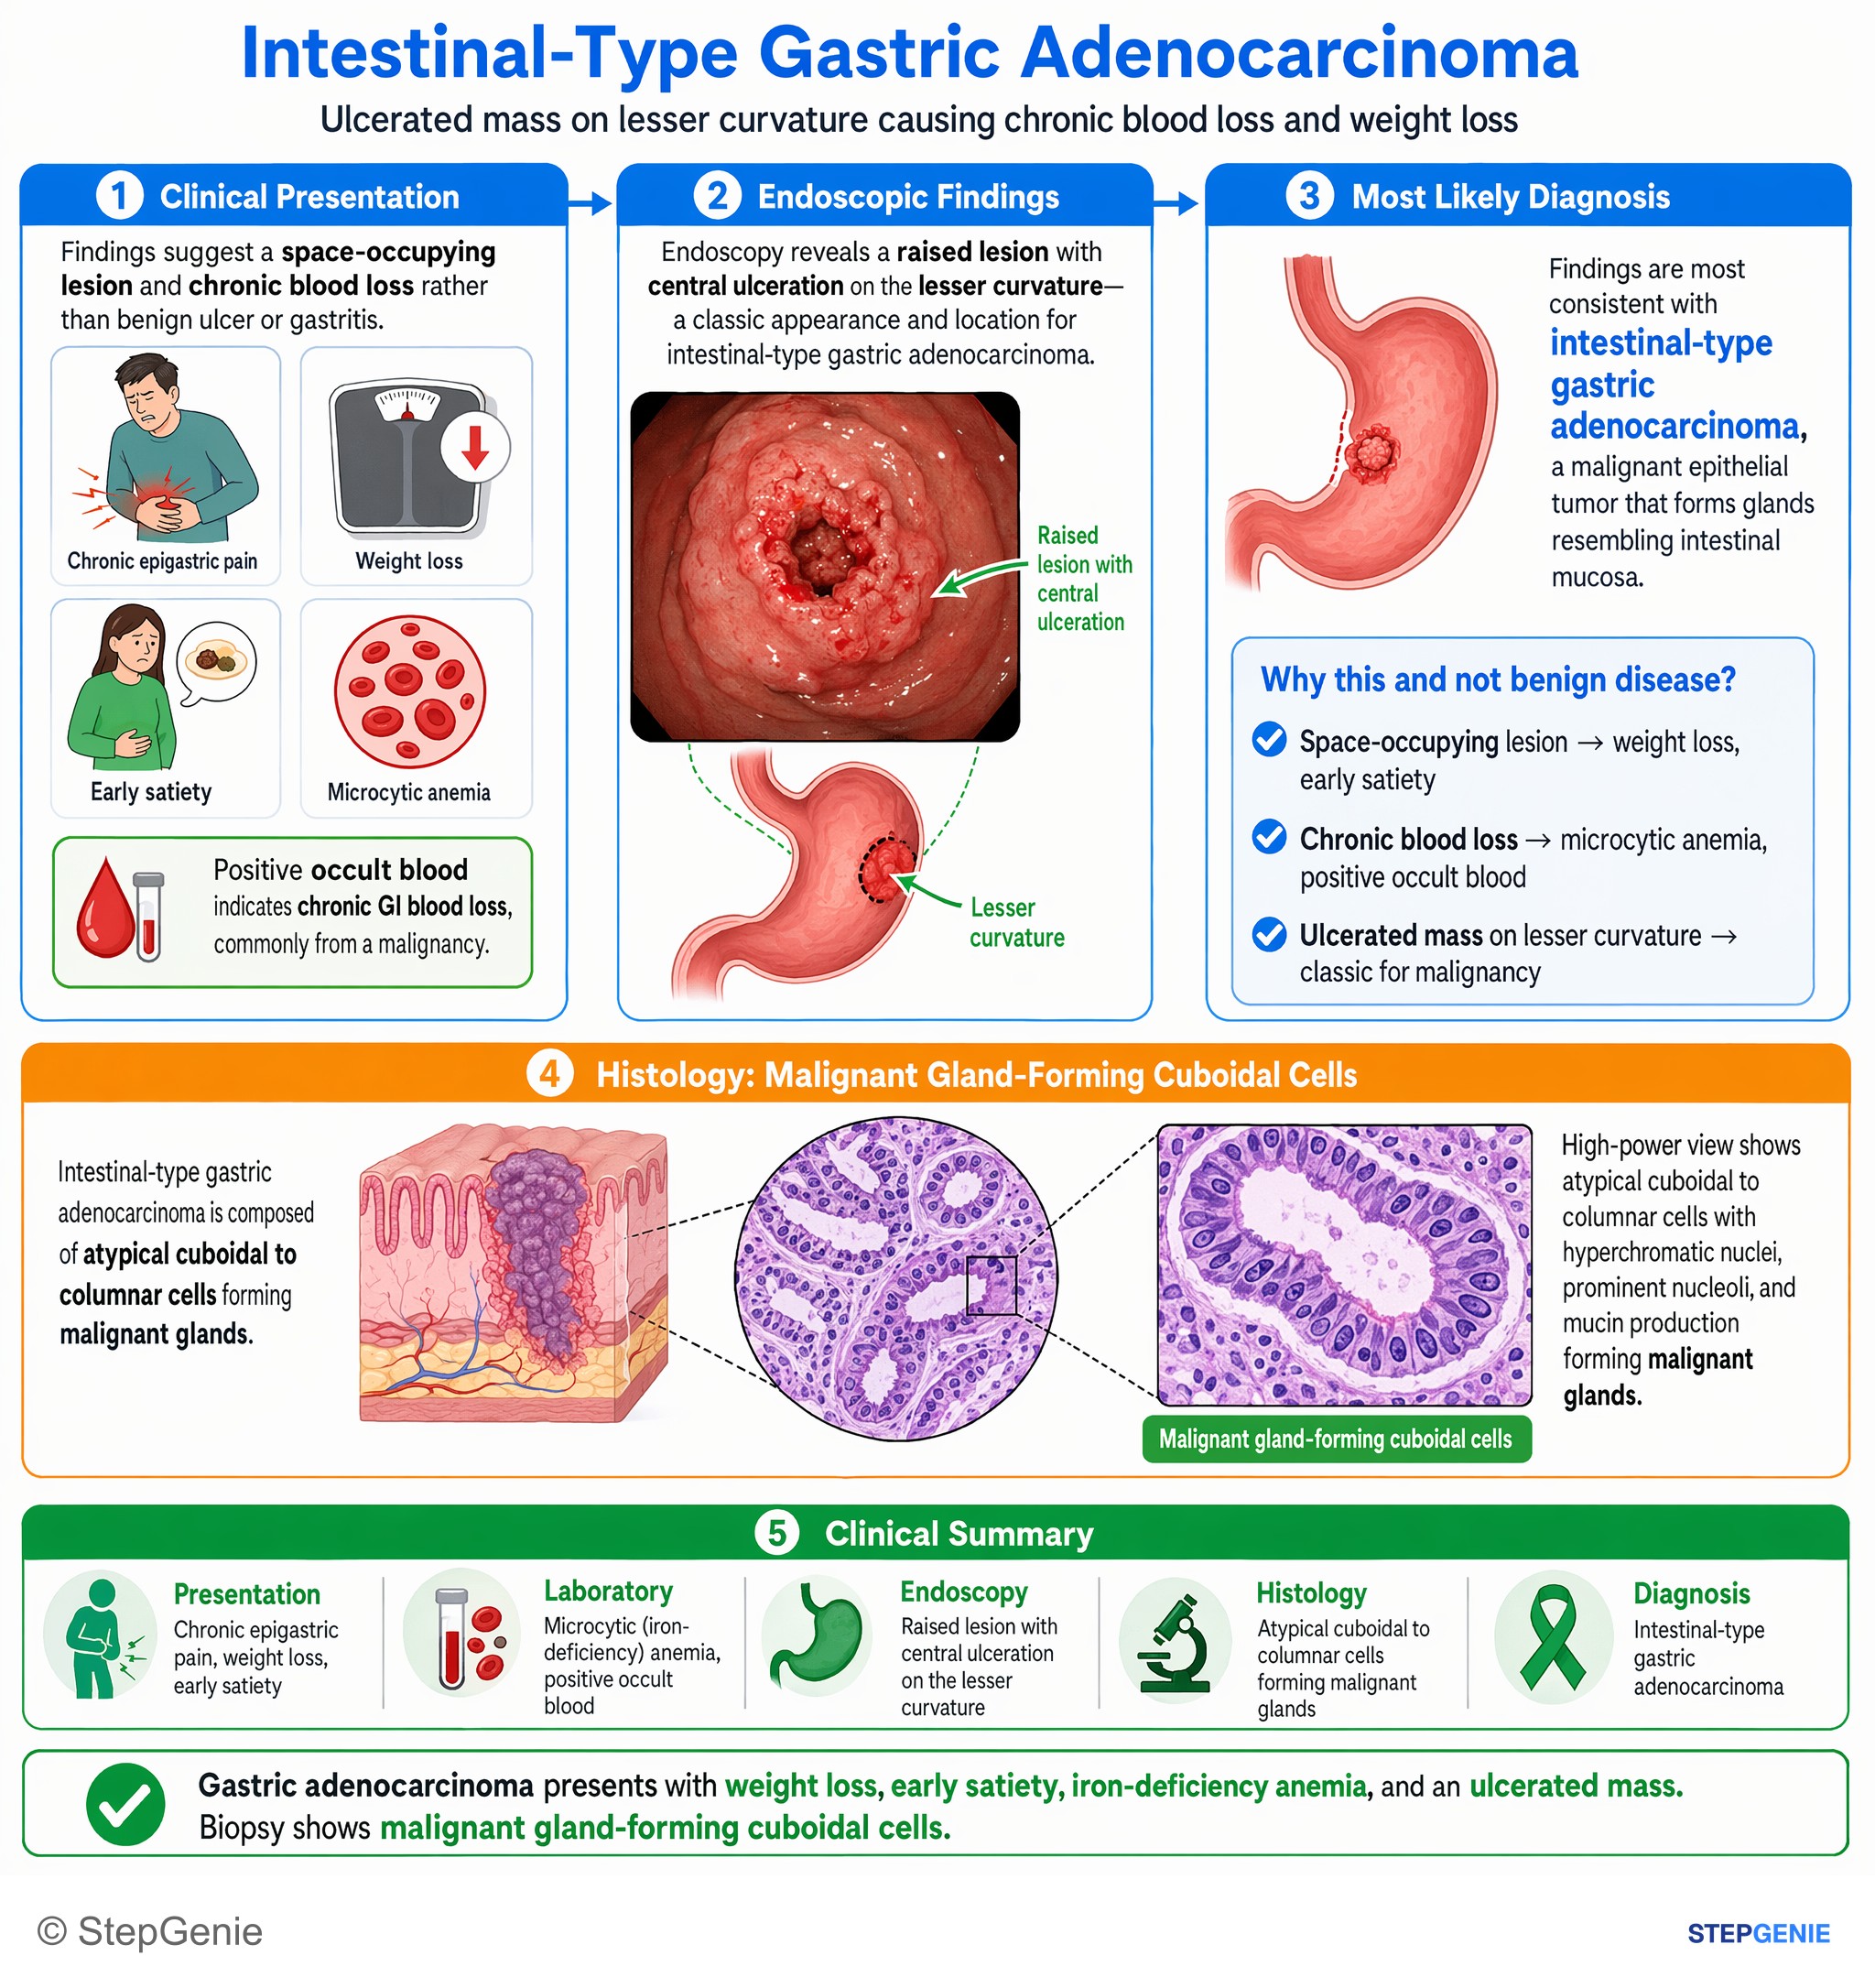
Gastric adenocarcinoma presents with weight loss, early satiety, iron-deficiency anemia, and an ulcerated mass; biopsy shows malignant…
USMLE Step 1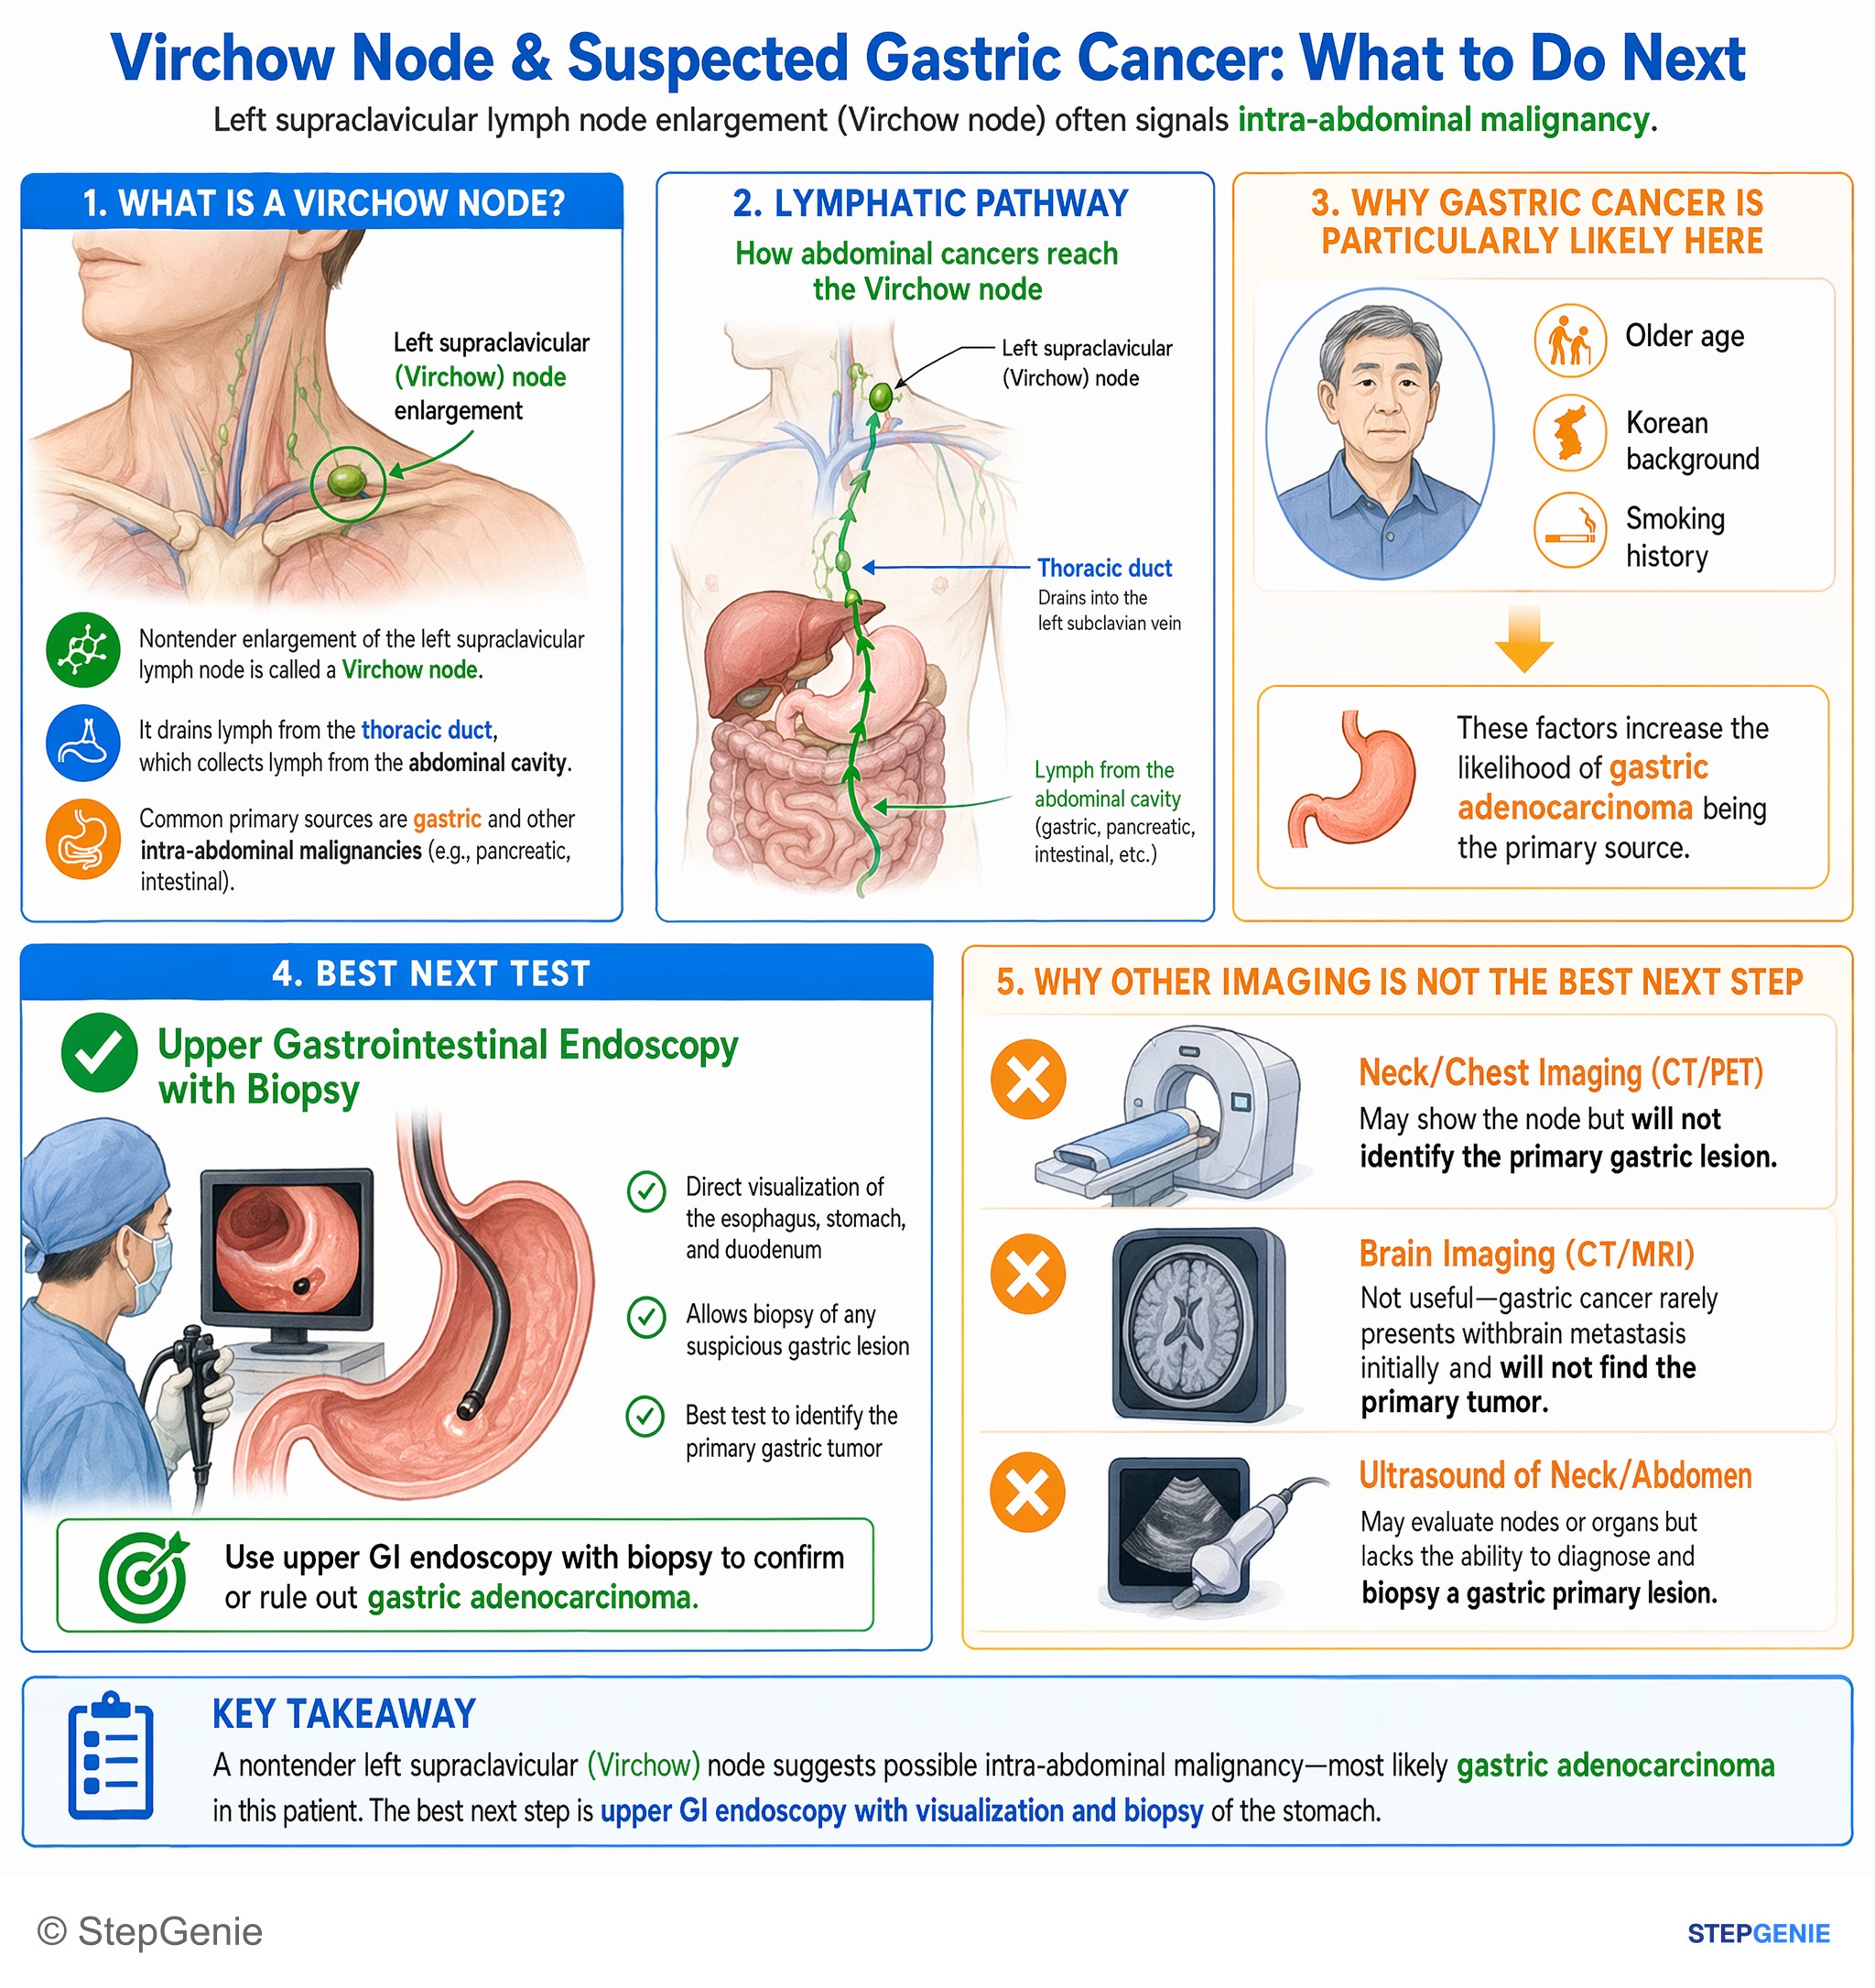
Gastric adenocarcinoma often metastasizes to a left supraclavicular (Virchow) node; evaluate primary lesion with upper GI endoscopy and…
USMLE Step 2Frequently Asked Questions
How do you tell intestinal-type gastric adenocarcinoma from diffuse-type gastric adenocarcinoma?
Intestinal-type gastric adenocarcinoma is usually gland-forming and linked to an environmental or inflammatory pathway, while diffuse-type is infiltrative with signet ring cells and is driven by loss of E-cadherin. Intestinal-type classically occurs in older patients in the distal stomach and is associated with H. pylori, nitrosamines, and chronic gastritis. Diffuse-type is associated with linitis plastica, younger patients, and a worse prognosis.
Why does E-cadherin loss cause diffuse gastric cancer to spread through the stomach wall?
E-cadherin loss causes diffuse gastric cancer to become infiltrative because decreased cell adhesion allows malignant cells to spread through the stomach wall rather than forming glands. This produces the classic diffuse growth pattern with signet ring cells and can lead to linitis plastica, a rigid thickened stomach with loss of rugal folds. That infiltrative process also helps explain symptoms like early satiety.
What is the classic link between H. pylori and gastric cancer?
H. pylori is most strongly linked to intestinal-type gastric adenocarcinoma through a chronic inflammation sequence that progresses to intestinal metaplasia, then dysplasia, then carcinoma. The cancer is classically distal and often gland-forming. H. pylori is also linked to MALT lymphoma, which is a separate but commonly tested association.
What does a left supraclavicular node mean in gastric cancer?
A left supraclavicular node in gastric cancer suggests Virchow node metastasis from an abdominal malignancy. The clue is that abdominal cancer can drain through the thoracic duct and present as enlargement of the left supraclavicular lymph node. This is one of the classic spread patterns students should recognize along with periumbilical metastasis to a Sister Mary Joseph nodule.
What are the classic metastatic clues for gastric cancer on exams?
The classic metastatic clues are Virchow node, Sister Mary Joseph nodule, liver spread, and Krukenberg tumor. Virchow node is left supraclavicular lymphadenopathy from lymphatic spread, and Sister Mary Joseph nodule is a periumbilical metastatic implant from peritoneal spread. Gastric cancer can also metastasize hematogenously to the liver, and signet ring cell tumors can seed both ovaries as a Krukenberg tumor.