Zollinger-Ellison syndrome (ZES) is gastric acid hypersecretion driven by a gastrin-secreting neuroendocrine tumor (gastrinoma), usually in the duodenum or pancreas; the acid causes severe, recurrent or oddly placed peptic ulcers, reflux and diarrhea. Diagnose it by reading a fasting serum gastrin together with the gastric pH: gastrin more than 10 times the upper limit of normal with a pH below 2 is diagnostic, and a smaller rise needs a secretin stimulation test, in which gastrin paradoxically climbs. About 20-25% of patients have MEN1. Management is high-dose PPI therapy, somatostatin receptor PET to find the tumor, and surgery for sporadic tumors that can be removed.
The 5-second rule
Ulcer + diarrhea, an ulcer in the wrong place, or an ulcer that won't heal → order a fasting gastrin AND a gastric pH.
Then read the pair in one glance:
- Gastrin high + pH low (below 2) = think gastrinoma.
- Gastrin high + pH high = the stomach is answering low acid (PPI use, atrophic gastritis, pernicious anemia). Not ZES.
| Trigger in the stem | Why it points to ZES |
|---|---|
| Ulcer plus chronic diarrhea | Acid floods the small bowel; diarrhea occurs in about 73% and is the first symptom in 25-40% |
| Ulcer beyond the duodenal bulb (postbulbar duodenum, jejunum) or multiple ulcers | Up to 25% of ZES ulcers lie distal to the bulb |
| Recurrent or refractory ulcer without H. pylori or NSAIDs | The common causes are missing: why is acid so high? |
| Thick gastric folds on endoscopy | Gastrin makes the acid-secreting mucosa grow; enlarged folds in more than 90% |
| Ulcer plus hypercalcemia, kidney stones or a pituitary tumor | MEN1 (parathyroid, pituitary, pancreas) |
Why it happens: one tumor, too much acid
- Normal loop: antral and duodenal G cells release gastrin, which drives parietal cells to secrete HCl; acid in the antrum then turns gastrin down.
- Gastrinoma: autonomous gastrin ignores that brake, so acid output stays high, and chronic hypergastrinemia thickens the gastric mucosa (prominent folds).
- Ulcers. Most still sit in the duodenal bulb, so a bulb ulcer does not exclude ZES; the clues are severity, multiplicity, recurrence and the up-to-25% distal to the bulb. As many as 25% of patients have no ulcer at diagnosis (Merck).
- Diarrhea and steatorrhea. Low duodenal pH inhibits pancreatic lipase and fat digestion, and the acid load plus hypergastrinemia cause sodium and water malabsorption. Diarrhea can be the only symptom.
- Other features: abdominal pain (about 75%), heartburn (about 44%), weight loss (about 17%). Complications: bleeding, penetration, perforation and strictures, including esophageal strictures from acid reflux.
- Routine ulcer causes are in the peptic ulcer disease cheat sheet.
Where gastrinomas are and how often they spread
- Duodenum about 70%, pancreas about 25%, other sites about 5%. Most are small (often under 1 cm) and slow-growing, so they are hard to find.
- Gastrinoma (Passaro) triangle: at operation, about 85% of gastrinomas lie in this region around the head of the pancreas and the adjoining duodenum (NCI PDQ).
- Malignant behavior: up to 50% are malignant; nodal metastases occur in almost half and liver metastases in about one third. Merck quotes 5- and 10-year survival above 90% after complete removal of an isolated tumor, versus 43% at 5 years with incomplete removal.
- MEN1: about 20-25% of ZES occurs in MEN1 (NIDDK; NCI gives 15-35%). MEN1 is autosomal dominant loss of the menin tumor suppressor (chromosome 11): hyperparathyroidism in at least 95%, pancreatic or duodenal NETs in 30-90%, pituitary tumors (most often prolactinomas) in 15-42%. Gastrinoma is its most common functioning enteropancreatic tumor, usually multicentric. Compare the syndromes in MEN1 vs MEN2A vs MEN2B.
- Calcium matters: calcium stimulates gastrin release, and in MEN1 parathyroidectomy usually lowers gastrin and acid output, so check calcium and PTH for primary hyperparathyroidism.
Diagnosis: gastrin, pH, then secretin
| Step | What you do | How to read it |
|---|---|---|
| 1. Fasting serum gastrin | Ideally off PPIs (see below); reference about < 100 pg/mL | Raised in essentially every patient (Merck: all above 150 pg/mL), but raised gastrin alone is not specific |
| 2. Gastric pH | Measured on gastric aspirate at the same time | pH below 2 = acid hypersecretion; a high pH points to a low-acid cause |
| 3a. Gastrin > 10 times normal (> 1,000 pg/mL) + pH < 2 | No further proof needed | Diagnostic of ZES |
| 3b. Gastrin raised but < 10 times normal + pH < 2 | Secretin stimulation test: secretin 0.4 mcg/kg IV, gastrin drawn at baseline and at 1, 2, 5, 10 and 30 minutes | Rise of more than 110 pg/mL over baseline (FDA label cut-off; reviews often quote ≥ 120 pg/mL) strongly suggests gastrinoma |
| 4. Look for MEN1 | Calcium, PTH, prolactin, family history | Changes surgery and family screening |
| 5. Localize | Somatostatin receptor PET/CT, CT/MRI, EUS | Only after a biochemical diagnosis |
The secretin paradox
In healthy people and in ordinary duodenal ulcer disease, IV secretin causes no or only a small change in serum gastrin. Gastrinoma cells express secretin receptors, so secretin makes them release more gastrin. Reported sensitivity is about 94%, but false negatives (6-20%) and false positives (with PPIs or H2 blockers, and in achlorhydric states such as pernicious anemia) occur, so read the result with the gastrin, pH and clinical picture.
The PPI problem
PPIs raise gastrin on their own (less acid, more gastrin) and can make the secretin test falsely positive. FDA labels say to stop omeprazole at least 14 days and esomeprazole 4 weeks before secretin testing, and H2 blockers at least 2 days before. But stopping acid suppression in true ZES can cause severe ulcer complications, so withdrawal is decided case by case and done cautiously, usually with an H2 blocker such as famotidine started as the PPI stops (and itself stopped at least 2 days before a secretin test). On a stem, high gastrin with a high pH in a patient on a PPI is drug effect until proven otherwise. More: PPIs for Step 1.
High gastrin: is the acid high or low?
| Cause | Gastrin | Gastric acid and pH | Tell-tale clue |
|---|---|---|---|
| ZES (gastrinoma) | ↑, sometimes > 10 times normal | Acid ↑, pH < 2 | Ulcers, diarrhea, thick folds, positive secretin test |
| PPI therapy | ↑ | Acid ↓, pH high | Falls back after the drug is stopped |
| Atrophic gastritis, pernicious anemia | ↑ | Achlorhydria, pH high | B12 deficiency, anti-intrinsic factor and anti-parietal cell antibodies |
| H. pylori infection | ↑ | Variable | Common ulcers that heal after eradication (H. pylori review) |
| Chronic kidney disease, massive small-bowel resection | ↑ | Variable | Raised creatinine or surgical history |
Localization: finding a sub-centimeter tumor
- Somatostatin receptor PET/CT (gallium-68 or copper-64 dotatate), FDA-approved for localizing somatostatin receptor-positive NETs: sensitivity 72-100%, better than older Octreoscan scintigraphy.
- CT misses many tumors under 1 cm and extrapancreatic tumors; MRI is better for liver metastases.
- Endoscopic ultrasound: sensitive for pancreatic tumors (75-100%), less so for duodenal ones (38-63%); allows biopsy.
- At surgery, duodenotomy with intraoperative transillumination or ultrasound finds small duodenal tumors.
Treatment
- Acid first: high-dose PPI. The omeprazole label starts at 60 mg once daily for hypersecretory states, adjusted to the patient. Ulcers heal within 4 weeks in 90-100%; acid suppression is often lifelong.
- Sporadic, non-metastatic gastrinoma: attempt resection, because complete removal is the only route to cure.
- MEN1: tumors are multiple, and these patients are less likely to be cured by surgery. Parathyroidectomy for hyperparathyroidism usually lowers gastrin and acid output, and pancreatic NETs are generally resected when larger than about 2 cm.
- Metastatic or unresectable disease: somatostatin analogs (octreotide, lanreotide), everolimus, sunitinib, cabozantinib, lutetium-177 dotatate (peptide receptor radionuclide therapy), chemotherapy, and liver-directed therapy. PPIs continue throughout.
How USMLE tests ZES: traps and look-alikes
- VIPoma: watery diarrhea, hypokalemia and achlorhydria (WDHA): no ulcers, low acid, the opposite of ZES.
- Atrophic gastritis or pernicious anemia: high gastrin with high pH. Its tumor risks are gastric carcinoid and adenocarcinoma, not aggressive ulcers.
- Carcinoid syndrome: diarrhea with flushing, wheezing and right-sided valve disease. Somatostatinoma: steatorrhea, diabetes, gallstones.
- Ordinary PUD: H. pylori and NSAIDs explain most ulcers; pick ZES when ulcers are multiple, distal or refractory without either, or come with diarrhea or MEN1 features.
- MEN1 add-on: a ZES stem with hypercalcemia or a prolactinoma is asking about the 3 Ps (see pituitary adenomas).
Practice question
A 38-year-old woman has had 8 months of burning epigastric pain and watery diarrhea despite twice-daily omeprazole. She takes no NSAIDs, and gastric biopsies are negative for H. pylori. Endoscopy shows thick gastric folds, an ulcer in the duodenal bulb and a second ulcer in the proximal jejunum. Serum calcium is 11.4 mg/dL, and she passed a kidney stone last year. After her PPI is carefully withheld, fasting serum gastrin is 420 pg/mL (reference < 100 pg/mL) and gastric pH is 1.4. Which is the most appropriate next step to confirm the diagnosis?
A. Secretin stimulation test B. Urea breath test C. Serum vasoactive intestinal peptide level D. Anti-intrinsic factor antibodies E. Double the PPI dose and repeat endoscopy in 8 weeks
Answer: A. Refractory ulcers, a jejunal ulcer, diarrhea and thick folds point to ZES; hypercalcemia with a kidney stone suggests MEN1. Gastrin is raised about 4-fold with a pH below 2, so the diagnosis needs a secretin stimulation test: a rise of more than 110 pg/mL over baseline strongly suggests a gastrinoma. Then check PTH and localize with somatostatin receptor PET.
- B: a urea breath test looks for H. pylori. Biopsies are already negative, and H. pylori does not explain jejunal ulcers, diarrhea or hypercalcemia.
- C: VIP is the test for VIPoma, which causes watery diarrhea with achlorhydria and hypokalemia; this patient has a gastric pH of 1.4 and ulcers.
- D: anti-intrinsic factor antibodies support pernicious anemia, where gastrin is high because acid is absent. A pH of 1.4 rules that out.
- E: more PPI treats symptoms but confirms nothing. Ulcers that fail PPI therapy, with high gastrin and low pH, need a diagnosis, MEN1 screening and tumor localization.
Key takeaways
- 5-second rule: ulcer + diarrhea, ulcer beyond the bulb, or an ulcer that won't heal → gastrin with gastric pH.
- High gastrin + pH < 2 = ZES; high gastrin + high pH = PPI or atrophic gastritis.
- Gastrin > 10 times normal with pH < 2 is diagnostic; otherwise a secretin test shows a paradoxical gastrin rise (> 110 pg/mL on the FDA label).
- PPIs raise gastrin and can cause a false-positive secretin test; withdraw them for testing only with care.
- Gastrinomas are mostly duodenal (about 70%), mostly in the gastrinoma triangle, and up to half are malignant.
- 20-25% have MEN1: check calcium and PTH; parathyroidectomy lowers gastrin.
- High-dose PPI, somatostatin receptor PET, and resection of sporadic disease.
Sources
- Gastrinoma — Merck Manual Professional Edition (2023)
- Overview of Malabsorption — Merck Manual Professional Edition (2025)
- Multiple Endocrine Neoplasia, Type 1 (MEN 1) — Merck Manual Professional Edition (2025)
- Pancreatic Neuroendocrine Tumors (Islet Cell Tumors) Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- Zollinger-Ellison Syndrome — NIDDK, National Institutes of Health (2021)
- MEN1 gene — MedlinePlus Genetics (2026)
- Gastrinoma and Zollinger Ellison syndrome: A roadmap for the management between new and old therapies — World Journal of Gastroenterology (2021)
- ChiRhoStim (human secretin) prescribing information — DailyMed (2025)
- Prilosec (omeprazole) prescribing information — DailyMed (2024)
- Nexium (esomeprazole) prescribing information — DailyMed (2025)
- NETSPOT (gallium Ga 68 dotatate) prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
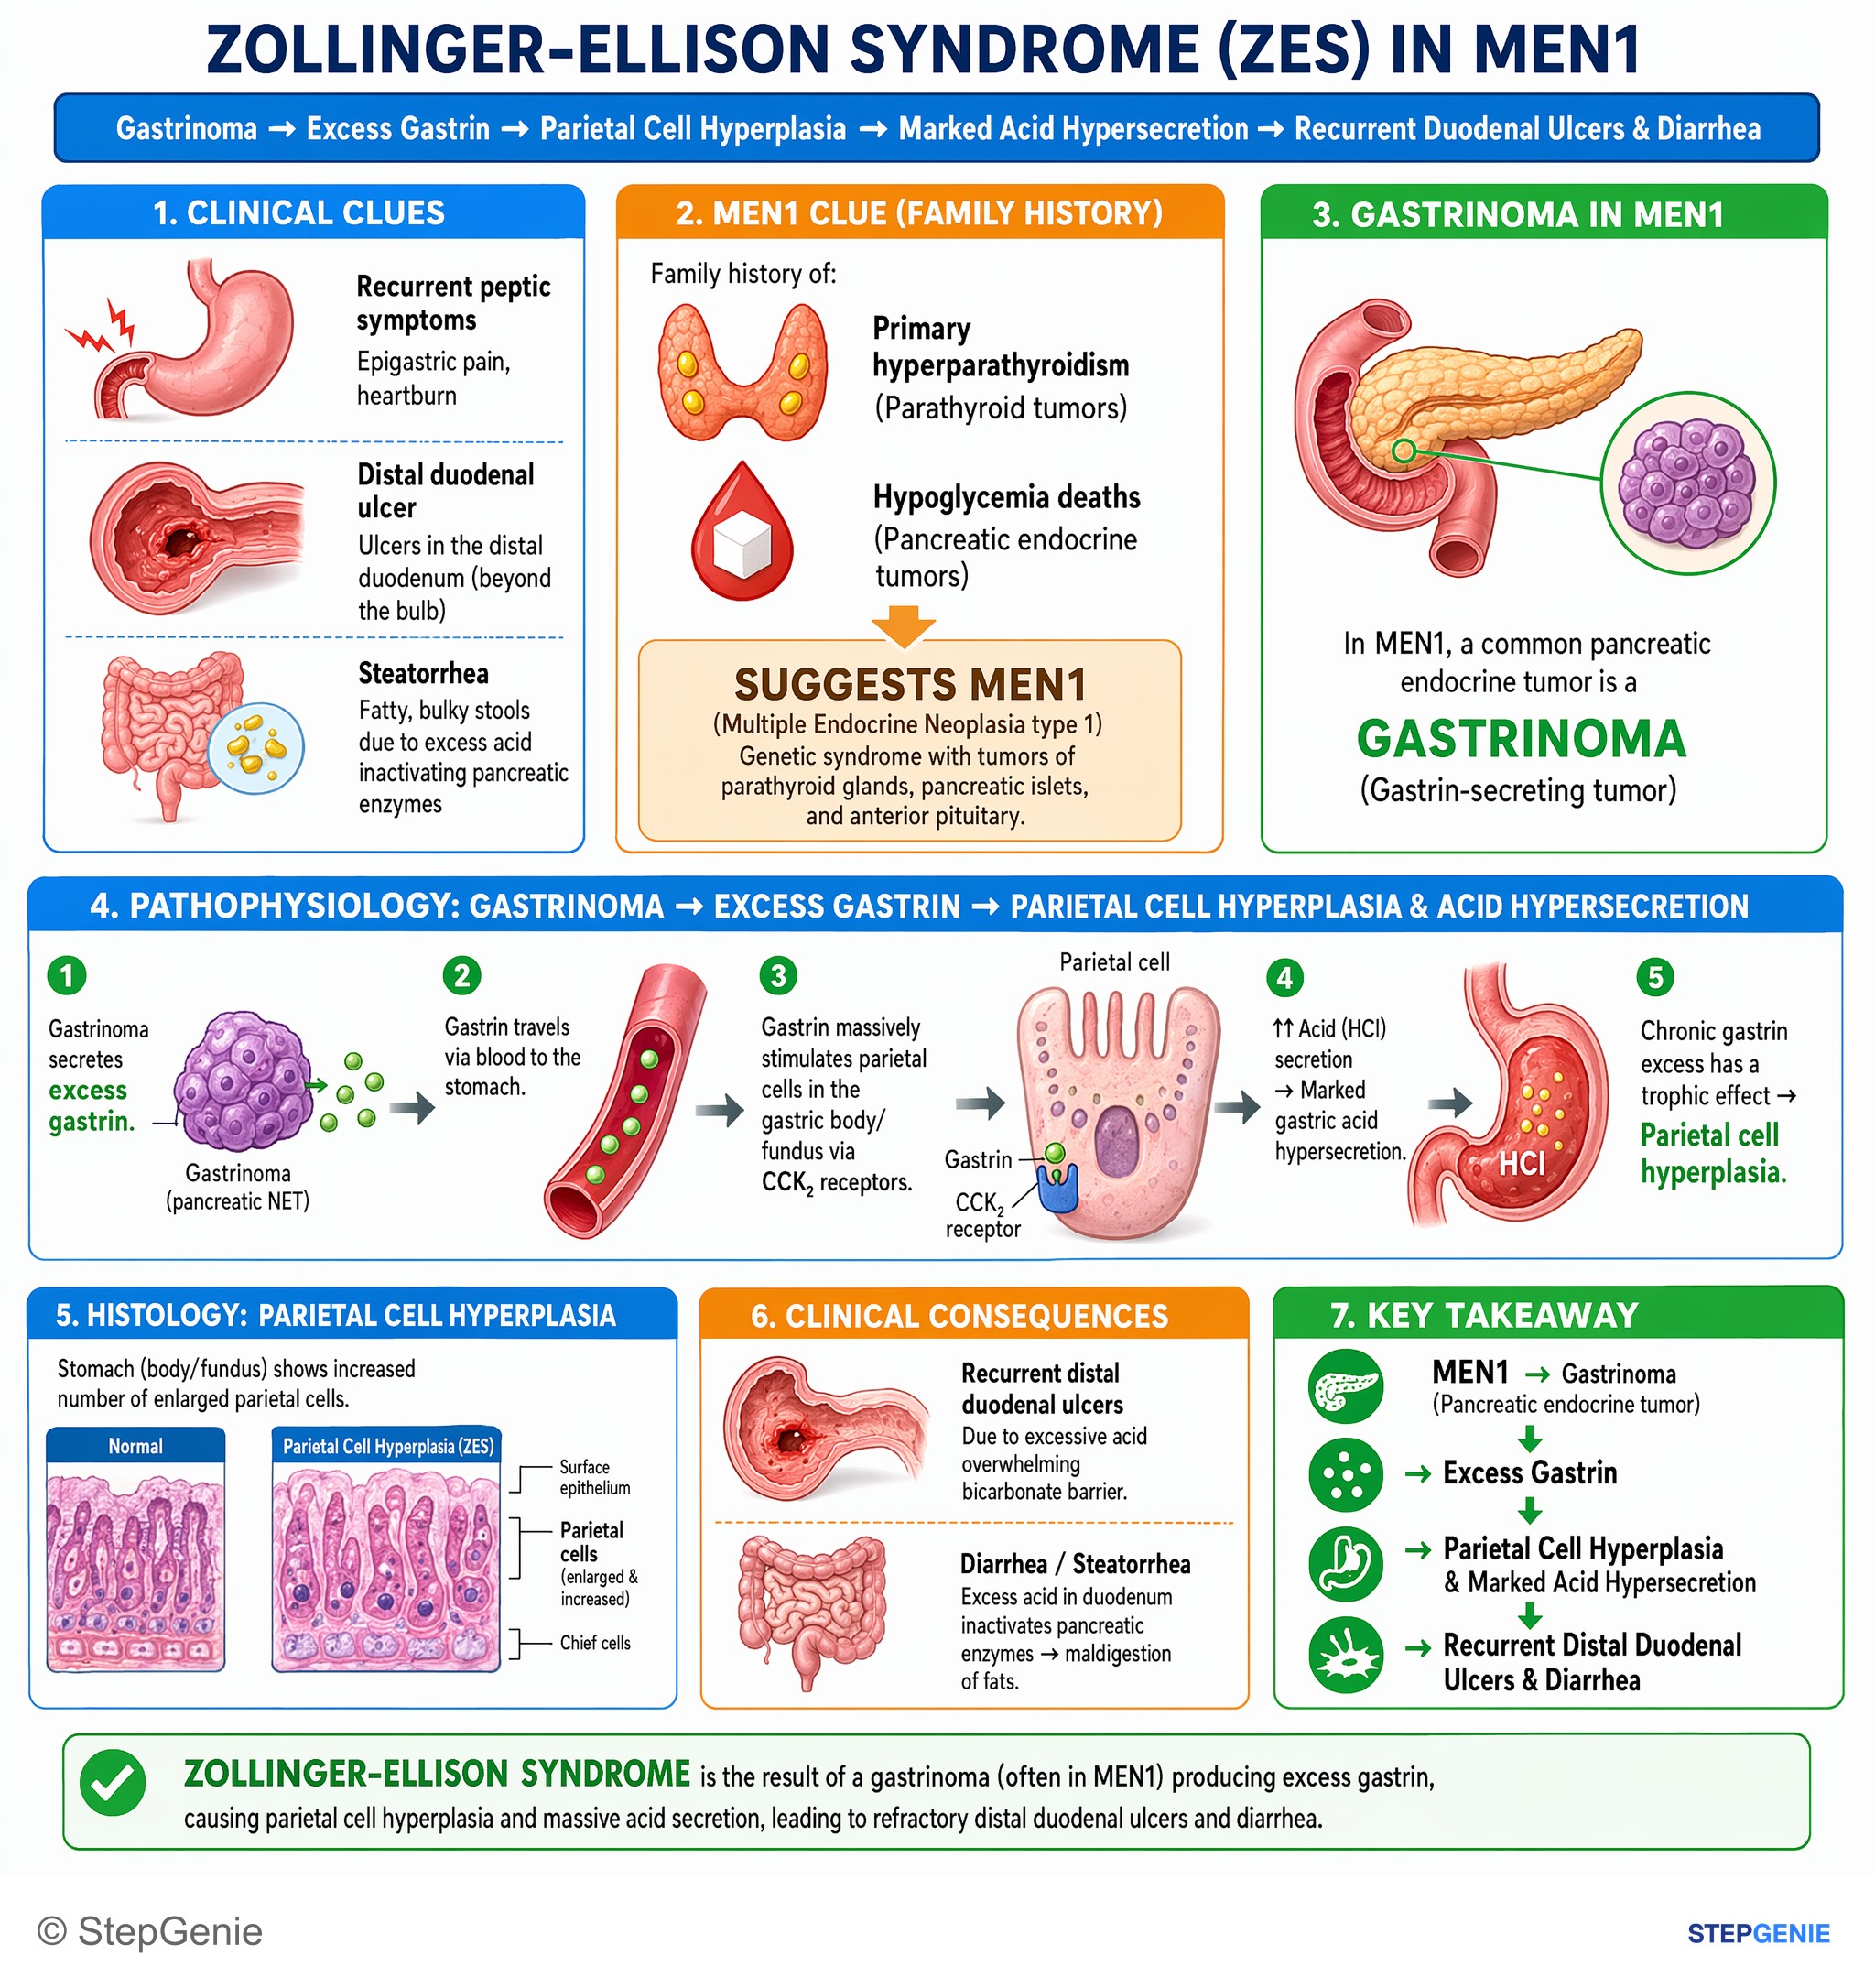
Zollinger–Ellison syndrome (often in MEN1) causes excess gastrin, leading to marked parietal cell hyperplasia and recurrent distal…
USMLE Step 1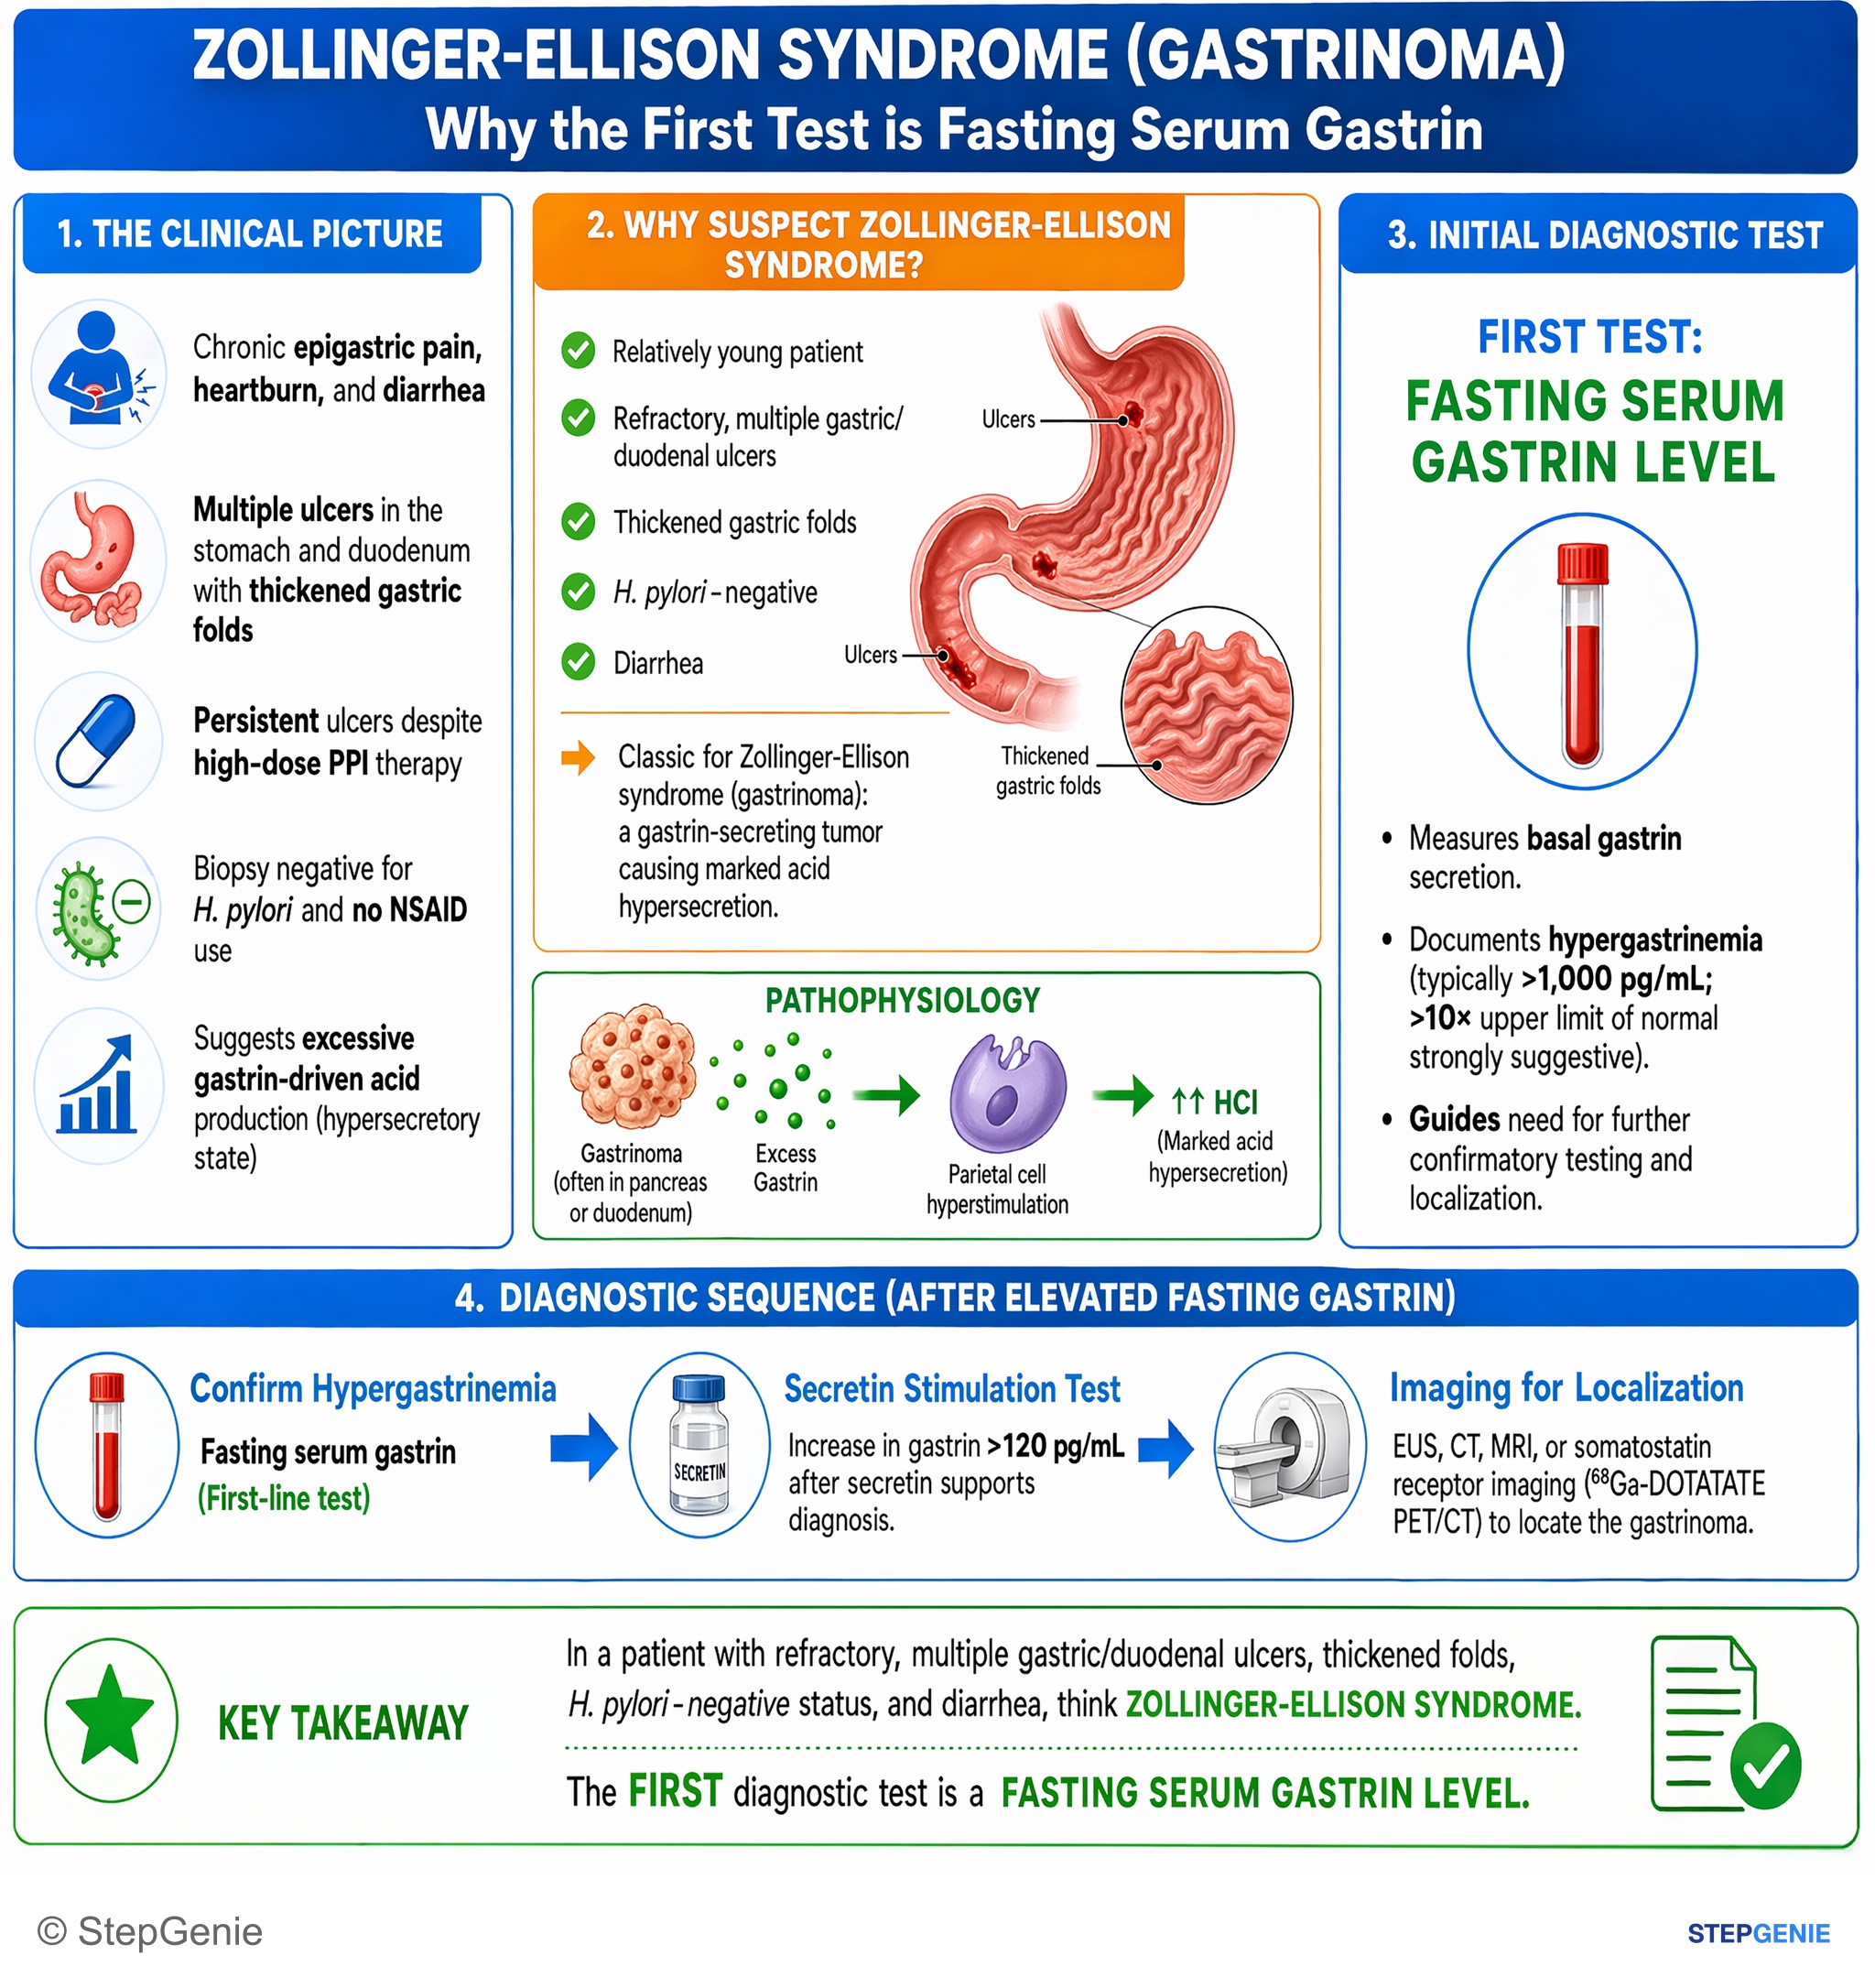
Zollinger-Ellison syndrome: refractory, multiple gastric/duodenal ulcers + thickened folds, H. pylori− → first test is fasting serum…
USMLE Step 2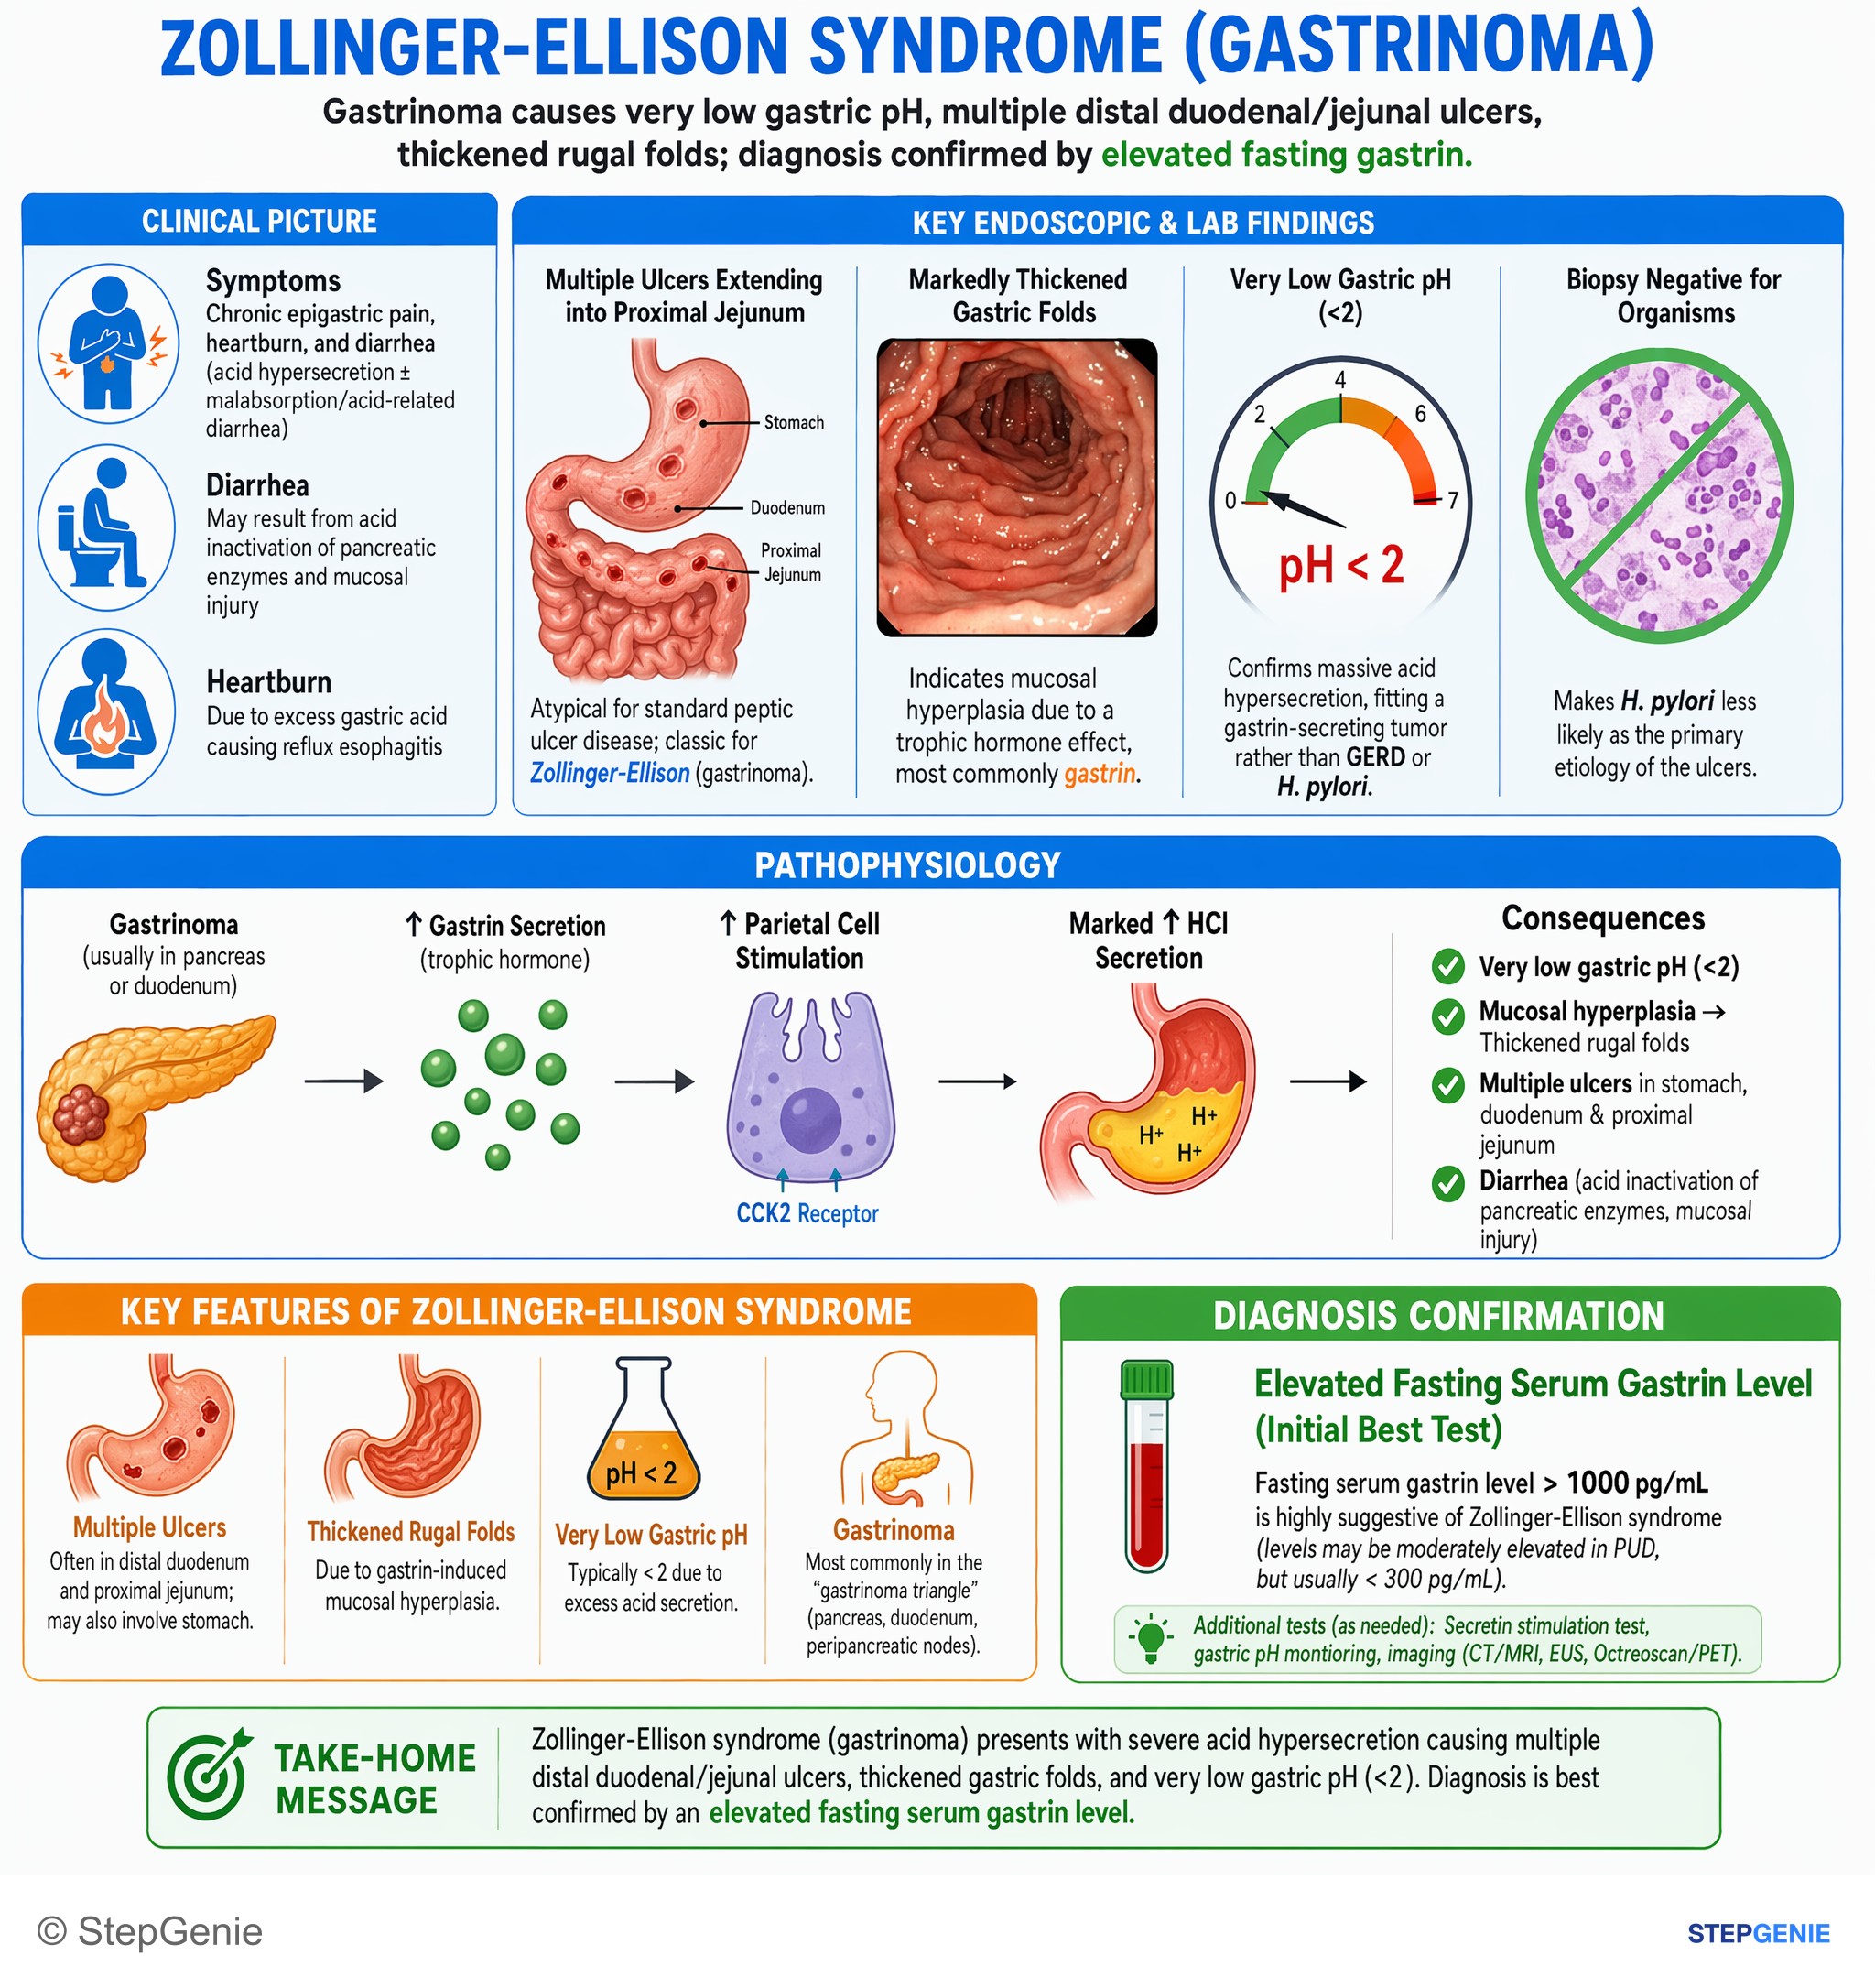
Zollinger-Ellison syndrome: gastrinoma causes very low gastric pH, multiple distal duodenal/jejunal ulcers, thickened rugal folds…
USMLE Step 2Frequently Asked Questions
What is the 5-second rule for Zollinger-Ellison syndrome?
If a peptic ulcer comes with diarrhea, sits beyond the duodenal bulb, or keeps coming back without H. pylori or NSAIDs, think of a gastrinoma and order a fasting serum gastrin together with a gastric pH. High gastrin with a pH below 2 means acid hypersecretion and points to Zollinger-Ellison syndrome. High gastrin with a high pH means the stomach is responding to low acid, as with PPI use or atrophic gastritis.
How is Zollinger-Ellison syndrome diagnosed?
Start with a fasting serum gastrin and a gastric pH, ideally after PPIs have been carefully withheld. Gastrin more than 10 times the upper limit of normal (above about 1,000 pg/mL) with a gastric pH below 2 establishes the diagnosis. If gastrin is raised less than that and the pH is below 2, a secretin stimulation test is done; a rise of more than 110 pg/mL over baseline (the FDA label cut-off) supports a gastrinoma. The tumor is then localized with somatostatin receptor PET/CT, CT or MRI, and endoscopic ultrasound.
Why does secretin raise gastrin in a gastrinoma?
In healthy people and in ordinary duodenal ulcer disease, intravenous secretin causes little or no change in serum gastrin. Gastrinoma cells carry secretin receptors, so secretin makes the tumor release more gastrin, which is why the response is called paradoxical. In the test, secretin 0.4 mcg/kg is given IV and gastrin is measured at baseline and at 1, 2, 5, 10 and 30 minutes. H2 blockers and PPIs can cause a false-positive rise, so they are stopped beforehand.
Do PPIs need to be stopped before gastrin testing?
Ideally yes, because PPIs raise gastrin by lowering acid and can make the secretin test falsely positive. FDA labels advise stopping omeprazole at least 14 days and esomeprazole 4 weeks before secretin testing, and H2 blockers at least 2 days before. Stopping acid suppression in a patient who truly has Zollinger-Ellison syndrome can lead to severe ulcer complications, so the decision is made case by case and withdrawal is done carefully, usually with an H2 blocker such as famotidine as a bridge, which is itself stopped at least 2 days before a secretin test.
How is Zollinger-Ellison syndrome linked to MEN1?
About 20 to 25 percent of patients with Zollinger-Ellison syndrome have multiple endocrine neoplasia type 1, an autosomal dominant syndrome caused by inactivating variants in the MEN1 tumor suppressor gene on chromosome 11, which encodes the protein menin. MEN1 causes parathyroid, pituitary and pancreatic or duodenal tumors, and gastrinoma is its most common functioning enteropancreatic tumor. Hypercalcemia from hyperparathyroidism worsens hypergastrinemia, and parathyroidectomy usually lowers gastrin and acid output, so calcium and PTH should be checked in patients with ZES.
Why does Zollinger-Ellison syndrome cause diarrhea?
The tumor-driven flood of acid reaches the small bowel. Low duodenal pH inhibits pancreatic lipase and fat digestion, causing steatorrhea, and the acid load together with high gastrin impairs sodium and water absorption. Diarrhea affects most patients, is the first symptom in 25 to 40 percent and can be the only symptom. Unlike VIPoma, which causes watery diarrhea with low acid and hypokalemia, Zollinger-Ellison syndrome pairs diarrhea with high acid and peptic ulcers.