Potassium-sparing diuretics act on the principal cells of the late distal tubule and collecting duct, and they come in two classes: mineralocorticoid (aldosterone) receptor antagonists, or MRAs (spironolactone, eplerenone, finerenone), and epithelial sodium channel (ENaC) blockers (amiloride, triamterene). Both cut sodium reabsorption and the lumen-negative voltage that drives potassium and hydrogen ion secretion, so the class effects are hyperkalemia and a normal anion gap metabolic acidosis. MRAs are the drugs of choice when aldosterone is the problem (HFrEF, primary aldosteronism, cirrhotic ascites, resistant hypertension); only ENaC blockers work in Liddle syndrome, and amiloride is the one used for lithium-induced nephrogenic diabetes insipidus. Finerenone, a nonsteroidal MRA, is labeled for CKD with type 2 diabetes, CKD with type 1 diabetes (added September 2026) and heart failure with an ejection fraction of 40% or more.
The step-by-step flowchart
Step 1: Find the site of action
- Where: late distal tubule and cortical collecting duct.
- Principal cells: reabsorb Na+ through apical ENaC and secrete K+ through apical potassium channels, powered by the basolateral Na+/K+-ATPase. Aldosterone increases expression of these channels.
- Type A (alpha) intercalated cells: secrete H+ through an apical H+-ATPase, which aldosterone also upregulates.
Step 2: Ask what is driving the problem
- Aldosterone is the driver (primary aldosteronism, HFrEF, ascites from cirrhosis, resistant hypertension) → go to the MRA branch.
- The channel itself, or something aldosterone-independent (Liddle syndrome, lithium entering principal cells, potassium loss from a thiazide or loop diuretic, where an MRA also works) → go to the ENaC-blocker branch.
Step 3: Pick the drug
- MRA branch: spironolactone is the default → switch to eplerenone if gynecomastia or sexual side effects appear. Finerenone is chosen for its own labeled indications: CKD with diabetes, or heart failure with an ejection fraction of 40% or more.
- ENaC branch: amiloride for Liddle syndrome, lithium-induced nephrogenic DI, or as an add-on to thiazide or loop diuretics; triamterene for edema (often combined with hydrochlorothiazide) or Liddle syndrome.
Step 4: Check potassium and kidney function first
- Spironolactone in heart failure: start 25 mg daily if potassium is 5.0 mEq/L or lower and eGFR is above 50 mL/min/1.73 m²; consider 25 mg every other day at an eGFR of 30-50.
- Eplerenone: contraindicated if potassium is above 5.5 mEq/L at the start or creatinine clearance is 30 mL/min or lower.
- Finerenone: do not start if potassium is above 5.0 mEq/L; initiation is not recommended if eGFR is below 25.
- Amiloride and triamterene: contraindicated with hyperkalemia, anuria or significant kidney impairment.
Step 5: Monitor
- Check potassium within 1 week of starting or raising spironolactone and regularly afterward (label). Merck advises potassium and creatinine every 1-2 weeks for the first 4-6 weeks of an MRA in heart failure, reducing the dose at a potassium of 5.0-5.5 mEq/L and stopping it above 5.5 mEq/L, if creatinine rises above 2.5 mg/dL, or with ECG changes of hyperkalemia.
Step 6: Screen for interactions
- Any other potassium-raising drug, a potassium supplement or salt substitute, another potassium-sparing diuretic, NSAIDs, lithium, and (for eplerenone and finerenone) strong CYP3A4 inhibitors. Details in the interactions table below.
Why they spare potassium and acid
Aldosterone binds the mineralocorticoid receptor inside principal cells and increases ENaC and Na+/K+-ATPase activity. More sodium entering the cell makes the tubular lumen more negative, which pulls K+ (and, via intercalated cells, H+) into the urine. MRAs block the receptor competitively; amiloride and triamterene plug ENaC directly, which works whether or not aldosterone is present (the triamterene label calls its effect a direct one on the tubule, not aldosterone antagonism). Either way, the lumen becomes less negative and less K+ and H+ is secreted: hyperkalemia plus a normal anion gap metabolic acidosis, the same pattern as type 4 RTA, whose causes Merck lists to include potassium-sparing diuretics (see RTA types 1, 2 and 4).
The natriuresis is weak. The amiloride label says it should rarely be used alone, and Merck notes potassium-sparing diuretics are not used for initial treatment of hypertension.
The five drugs compared
| Drug | Class | Key labeled uses | What makes it distinctive |
|---|---|---|---|
| Spironolactone | Steroidal MRA | NYHA class III-IV HFrEF (survival, edema, fewer admissions); add-on for hypertension; edema in cirrhosis or nephrotic syndrome; primary hyperaldosteronism | Antiandrogen: gynecomastia in about 9% of men in RALES (mean dose 26 mg/day), dose-dependent and usually reversible; low libido, erectile dysfunction, irregular menses. Contraindicated in Addison disease and with eplerenone |
| Eplerenone | Selective steroidal MRA | Symptomatic HFrEF after acute MI (survival); hypertension | Merck says it does not block the androgen receptor, so gynecomastia and sexual side effects are uncommon (the label still reports occasional gynecomastia); CYP3A4 substrate |
| Finerenone | Nonsteroidal selective MRA | CKD with type 2 diabetes (less eGFR decline, kidney failure, CV death, MI and HF admission); CKD with type 1 diabetes (lowers albuminuria, added 9/2026); HF with LVEF of 40% or more | No relevant affinity for androgen, progesterone, estrogen or glucocorticoid receptors. Hyperkalemia 14.0% vs 6.9% on placebo in the type 2 diabetes CKD trials. Contraindicated with strong CYP3A4 inhibitors and adrenal insufficiency |
| Amiloride | ENaC blocker | Add-on to thiazide or loop diuretics in heart failure or hypertension, to restore or protect potassium | Boxed hyperkalemia warning: about 10% when used alone, 1-2% with a thiazide. Off-label: Liddle syndrome, lithium-induced nephrogenic DI |
| Triamterene | ENaC blocker | Edema from heart failure, cirrhosis or nephrotic syndrome; steroid-induced, idiopathic and secondary-hyperaldosteronism edema | Kidney stones (found in calculi), weak folate antagonist (megaloblastosis), possible metabolic acidosis, acute kidney injury with indomethacin; boxed hyperkalemia warning |
Uses: match the stem to the drug
| Stem clue | Drug | Why |
|---|---|---|
| HFrEF with symptoms | Spironolactone or eplerenone | Merck: MRAs reduce mortality, including sudden death, and are part of guideline-directed therapy for NYHA class II-IV HFrEF |
| Heart failure with LVEF of 40% or more | Finerenone | Labeled to reduce CV death, HF hospitalization and urgent HF visits |
| CKD with type 2 diabetes | Finerenone | Labeled to slow eGFR decline and cut kidney failure and CV events |
| Primary aldosteronism from bilateral adrenal hyperplasia | Spironolactone (or eplerenone or amiloride) | An aldosterone-producing adenoma is removed laparoscopically instead (see Conn syndrome) |
| Ascites from cirrhosis | Spironolactone plus a loop diuretic | Counters secondary hyperaldosteronism; sodium restriction (2,000 mg/day) comes first |
| Resistant hypertension | Add an MRA | Merck: hyperaldosteronism or subclinical hypercortisolism is found in 15-20% of resistant hypertension |
| Liddle syndrome | Amiloride or triamterene | Gain-of-function ENaC; spironolactone is ineffective |
| Lithium-induced nephrogenic DI | Amiloride | Lithium enters principal cells through ENaC; amiloride blocks that entry |
| Hypokalemia on a thiazide or loop diuretic | Amiloride, triamterene or spironolactone | Not needed with an ACE inhibitor or ARB, which already raise potassium (see thiazides) |
| Hirsutism, often from PCOS | Spironolactone | Antiandrogen use; requires contraception because it may feminize a male fetus |
Liddle syndrome is a rare autosomal dominant disorder caused by gain-of-function mutations in ENaC subunit genes: hypertension before age 35, hypokalemic metabolic alkalosis, and low renin and low aldosterone (Merck). Spironolactone fails because there is no excess aldosterone to block; the channel is open on its own.
Lithium-induced nephrogenic DI (arginine vasopressin resistance in the newer naming Merck uses): lithium enters principal cells mainly through ENaC and downregulates aquaporin-2; in a 2009 Kidney International study, amiloride reduced lithium entry and attenuated the resulting polyuria in rats. See the lithium review and central vs nephrogenic DI.
Adverse effects you must know
- Hyperkalemia (all five drugs): risk rises with kidney impairment, diabetes, older age, potassium supplements or salt substitutes, and drugs that raise potassium. Expect weakness and ECG changes; review the hyperkalemia breakdown.
- Hyperkalemic normal anion gap metabolic acidosis: less H+ secretion, a type 4 RTA pattern. Merck lists amiloride, eplerenone, spironolactone and triamterene among its causes, and the triamterene label warns of possible metabolic acidosis.
- Spironolactone: gynecomastia, breast and nipple pain, decreased libido, erectile dysfunction, irregular menses or amenorrhea; also hyponatremia and hypomagnesemia. Switch to eplerenone if gynecomastia is the problem.
- Triamterene: nephrolithiasis, megaloblastosis when folate stores are low, and acute kidney injury when combined with indomethacin.
- Finerenone: hyperkalemia, hypotension and hyponatremia (CKD trials); kidney function declines more often than with placebo in heart failure.
Interactions
| Combine a K-sparing diuretic with | Result |
|---|---|
| ACE inhibitor or ARB | Additive hyperkalemia: the classic exam setup, especially in CKD or diabetes |
| Potassium supplements or potassium salt substitutes | Hyperkalemia; contraindicated with amiloride and triamterene, and with eplerenone for hypertension |
| Another potassium-sparing diuretic | Contraindicated (spironolactone plus eplerenone; triamterene or amiloride plus another) |
| NSAIDs | Higher potassium, blunted diuresis; acute kidney injury with triamterene plus indomethacin |
| Strong CYP3A4 inhibitors (such as ketoconazole) | Contraindicated with eplerenone and finerenone; grapefruit juice is avoided with finerenone |
| Lithium | Reduced lithium clearance and toxicity risk: monitor lithium levels |
| Cyclosporine or tacrolimus | Additive hyperkalemia (amiloride label) |
How USMLE tests it
- Liddle vs Conn: both give hypertension with hypokalemic alkalosis. High aldosterone, low renin = Conn (spironolactone works). Low aldosterone, low renin = Liddle (amiloride or triamterene; spironolactone fails).
- Gynecomastia on spironolactone: switch to eplerenone.
- New weakness or peaked T waves after spironolactone is added to an ACE inhibitor in CKD: hyperkalemia.
- Lithium patient with polyuria that does not respond to desmopressin: nephrogenic DI; amiloride.
- Triamterene: stones and folate antagonism.
- Hyperkalemic normal anion gap acidosis in a patient on a K-sparing diuretic: drug-induced, type 4 RTA pattern.
- Spironolactone in Addison disease: contraindicated.
Practice question
A 22-year-old man has a blood pressure of 168/104 mm Hg on repeated readings. His mother was diagnosed with hypertension at age 26. Serum potassium is 2.8 mEq/L and bicarbonate 32 mEq/L. Plasma renin activity and serum aldosterone are both low, and adrenal CT is normal. Which is the most appropriate treatment?
A. Amiloride
B. Spironolactone
C. Hydrochlorothiazide
D. Laparoscopic adrenalectomy
E. Lisinopril
Answer: A. Early, dominantly inherited hypertension with hypokalemic metabolic alkalosis and suppressed renin and aldosterone is Liddle syndrome: ENaC is constitutively active. Amiloride (or triamterene) closes the channel and corrects both the blood pressure and the potassium.
- B: spironolactone blocks the aldosterone receptor, but aldosterone is already low and the channel works without it; Merck calls it ineffective.
- C: a thiazide increases distal sodium delivery and potassium loss, worsening the hypokalemia and alkalosis.
- D: adrenalectomy treats an aldosterone-producing adenoma, which has high aldosterone and a visible adrenal lesion.
- E: an ACE inhibitor acts upstream on a renin-angiotensin system that is already suppressed and does not close ENaC.
Key takeaways
- Two classes, one site (principal cells): MRAs (spironolactone, eplerenone, finerenone) and ENaC blockers (amiloride, triamterene).
- Class effects: hyperkalemia and normal anion gap metabolic acidosis; avoid potassium supplements and other K-sparing drugs; watch ACE inhibitors, ARBs and NSAIDs.
- Spironolactone: HFrEF, primary aldosteronism, cirrhotic ascites, resistant hypertension; antiandrogen effects (gynecomastia), so switch to eplerenone if needed.
- Finerenone: nonsteroidal MRA for CKD with type 2 diabetes, CKD with type 1 diabetes and heart failure with LVEF of 40% or more.
- Amiloride: Liddle syndrome and lithium-induced nephrogenic DI. Triamterene: stones and folate antagonism.
Sources
- KERENDIA (finerenone) tablets: prescribing information — DailyMed, NLM (2026)
- ALDACTONE (spironolactone) tablets: prescribing information — DailyMed, NLM (2025)
- INSPRA (eplerenone) tablets: prescribing information — DailyMed, NLM (2025)
- Amiloride hydrochloride tablets: prescribing information — DailyMed, NLM (2026)
- DYRENIUM (triamterene) capsules: prescribing information — DailyMed, NLM (2024)
- Liddle Syndrome — Merck Manual Professional Edition (2026)
- Primary Aldosteronism — Merck Manual Professional Edition (2026)
- Medications for Heart Failure — Merck Manual Professional Edition (2026)
- Hypertension — Merck Manual Professional Edition (2026)
- Ascites — Merck Manual Professional Edition (2025)
- Renal Tubular Acidosis — Merck Manual Professional Edition (2026)
- Amiloride blocks lithium entry through the sodium channel thereby attenuating the resultant nephrogenic diabetes insipidus — Kidney International (2009)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
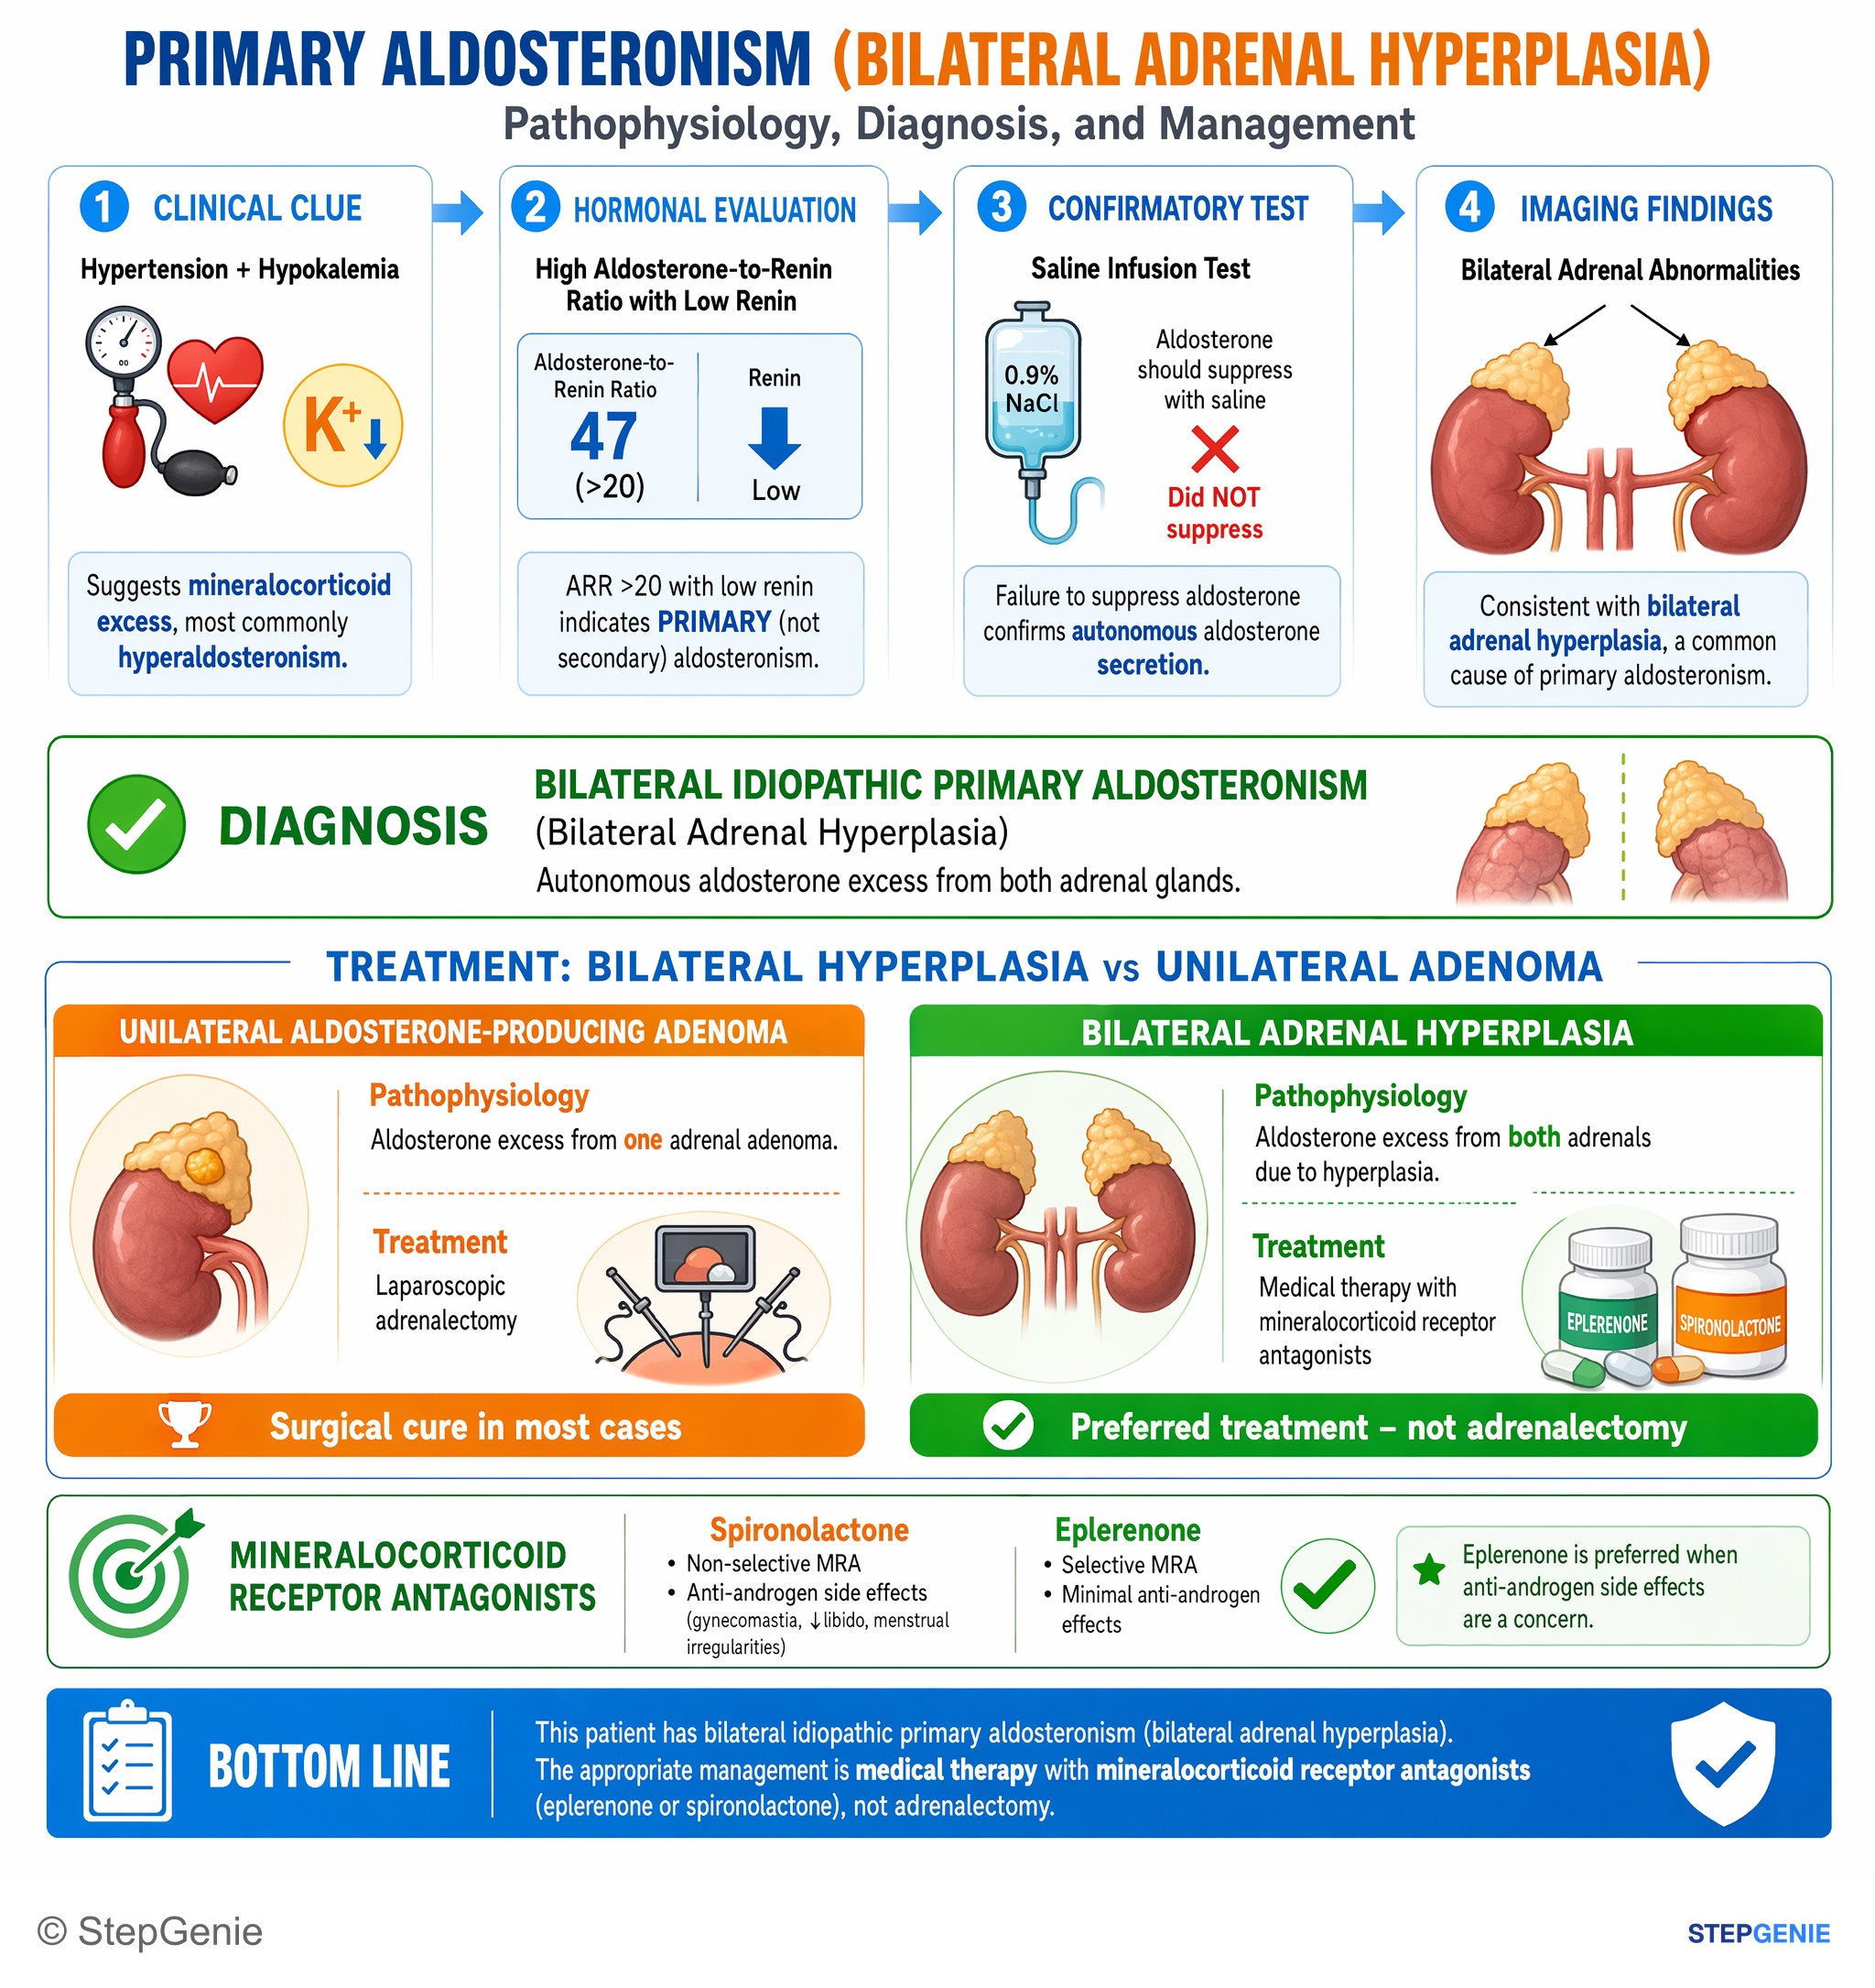
Bilateral idiopathic primary aldosteronism → treat with mineralocorticoid receptor antagonists (eplerenone/spironolactone), not…
USMLE Step 2Frequently Asked Questions
What are the potassium-sparing diuretics and where do they act?
There are two classes. Mineralocorticoid receptor antagonists (spironolactone, eplerenone and finerenone) block the aldosterone receptor, and ENaC blockers (amiloride and triamterene) block the epithelial sodium channel directly. Both act on principal cells of the late distal tubule and collecting duct, where they reduce sodium reabsorption and the lumen-negative voltage that drives potassium and hydrogen ion secretion. Their diuretic effect is weak, so they are used mainly for their potassium-sparing and anti-aldosterone effects.
Why do potassium-sparing diuretics cause hyperkalemia and metabolic acidosis?
Sodium entering principal cells through ENaC makes the tubular lumen negative, which drives potassium secretion and supports hydrogen ion secretion. Blocking aldosterone or ENaC reduces that voltage, so less potassium and acid reach the urine. The result is hyperkalemia and a normal anion gap metabolic acidosis, the same pattern as type 4 renal tubular acidosis. The risk is highest with kidney impairment, diabetes, older age, potassium supplements, and ACE inhibitors or ARBs.
What is the difference between spironolactone, eplerenone and finerenone?
All three block the mineralocorticoid receptor. Spironolactone is steroidal and also blocks androgen receptors, so it can cause gynecomastia, decreased libido and menstrual irregularities. Eplerenone is more selective, so gynecomastia is uncommon (Merck says it does not block androgen receptors, though its label reports occasional cases); it is labeled for HFrEF after myocardial infarction and for hypertension. Finerenone is nonsteroidal, with no relevant affinity for sex hormone receptors, and is labeled for CKD with diabetes and for heart failure with an ejection fraction of 40 percent or more.
Why is amiloride used in Liddle syndrome and lithium-induced diabetes insipidus?
Liddle syndrome is an autosomal dominant gain-of-function defect of the epithelial sodium channel, which then reabsorbs sodium without needing aldosterone, causing early hypertension, hypokalemic alkalosis and low renin and aldosterone. Amiloride or triamterene blocks the channel itself; spironolactone is ineffective because the defect does not depend on aldosterone. In lithium-induced nephrogenic diabetes insipidus, lithium enters principal cells mainly through the same channel, so amiloride limits its entry. Lithium levels still need monitoring.
Which potassium-sparing diuretic causes gynecomastia or kidney stones?
Spironolactone causes gynecomastia because it also blocks androgen receptors; in the RALES heart failure trial about 9 percent of men developed it at a mean dose of 26 mg a day, and it is dose-dependent and usually reversible. Eplerenone, which does not block androgen receptors, is the usual switch. Triamterene is the one linked to kidney stones, since the drug has been found in renal calculi, and it is also a weak folic acid antagonist.
What is finerenone approved for?
Under its current US label (updated September 2026), finerenone (Kerendia) is approved to reduce the risk of sustained eGFR decline, kidney failure, cardiovascular death, nonfatal myocardial infarction and heart failure hospitalization in adults with CKD and type 2 diabetes; to reduce albuminuria in adults with CKD and type 1 diabetes; and to reduce cardiovascular death, heart failure hospitalization and urgent heart failure visits in adults with heart failure and an ejection fraction of 40 percent or more.