Respiratory acid–base questions are deceptively simple: “CO₂ up = acidosis, CO₂ down = alkalosis.” But the reason people miss these on Q-banks (and on test day) is that every answer choice is usually a trap built around compensation rules, timing (acute vs chronic), and mixed disorders. Let’s do this the way the NBME does it: start with a vignette, lock in the diagnosis, and then interrogate every distractor until it can’t fool you again.
Clinical Vignette (Q-bank style)
A 68-year-old man with severe COPD is brought to the ED for worsening somnolence. He has been using home oxygen more frequently. Vitals: T 37.0°C (98.6°F), HR 92, RR 8/min, BP 138/84, SpO₂ 96% on 4 L nasal cannula. Exam shows diffuse wheezes and decreased air movement.
Arterial blood gas on oxygen shows:
| Value | Result |
|---|---|
| pH | 7.30 |
| PaCO₂ | 60 mm Hg |
| HCO₃⁻ | 29 mEq/L |
Question: Which of the following best describes this patient’s acid–base status?
A. Acute respiratory acidosis
B. Chronic respiratory acidosis with metabolic compensation
C. Metabolic acidosis with respiratory compensation
D. Respiratory alkalosis
E. Mixed metabolic acidosis and respiratory acidosis
Stepwise Approach (the one you should do every time)
1) Decide acidemia vs alkalemia
- pH 7.30 → acidemia
2) Identify the primary process (CO₂ vs HCO₃⁻)
- PaCO₂ 60 (high) pushes pH down → primary respiratory acidosis
- HCO₃⁻ 29 is elevated (alkalinizing) → suggests renal compensation, not the primary driver
3) Acute vs chronic? Use the compensation rule
For respiratory acidosis:
- Acute: HCO₃⁻ increases by ~1 mEq/L for every +10 mm Hg PaCO₂
- Chronic: HCO₃⁻ increases by ~3.5–4 mEq/L for every +10 mm Hg PaCO₂
Here, PaCO₂ went from ~40 → 60 (Δ = +20).
- Expected acute HCO₃⁻:
- Expected chronic HCO₃⁻:
Measured HCO₃⁻ is 29, which is in between—often seen when a chronic CO₂ retainer has an acute decompensation. But the best single answer among the choices is:
B. Chronic respiratory acidosis with metabolic compensation
Why B over A? Because HCO₃⁻ is elevated beyond acute expectations, implying the kidneys have had time to retain bicarbonate.
Correct answer: B
Why the Correct Answer Is Correct (High-yield pathophys)
Chronic respiratory acidosis = sustained hypoventilation → CO₂ retention
Common causes:
- COPD (classic)
- Obesity hypoventilation syndrome
- Neuromuscular weakness (ALS, myasthenia crisis)
- CNS respiratory depression (opioids, sedatives)
- Severe airway obstruction
Renal compensation (hours → days):
- ↑ H⁺ secretion (α-intercalated cells)
- ↑ HCO₃⁻ reabsorption and generation
- ↑ ammoniagenesis (NH₃ buffer → NH₄⁺ trapping)
So you expect:
- PaCO₂ high
- HCO₃⁻ high (if chronic)
- pH low but less low than it would be without compensation
Now, Destroy the Distractors (the part that raises your score)
A. Acute respiratory acidosis
Why it tempts you: pH low + CO₂ high.
Why it’s wrong here: compensation magnitude.
- Acute expected HCO₃⁻ with PaCO₂ 60: about 26
- Actual HCO₃⁻ = 29 → too high for pure acute
Exam tip: If HCO₃⁻ is meaningfully elevated, the kidneys have been involved → think chronic or acute-on-chronic.
C. Metabolic acidosis with respiratory compensation
Why it tempts you: low pH makes people reflexively pick “metabolic acidosis.”
Why it’s wrong: In metabolic acidosis, you expect:
- HCO₃⁻ low (primary)
- PaCO₂ low (compensation via hyperventilation)
This patient has:
- HCO₃⁻ high
- PaCO₂ high
That’s the opposite pattern.
High-yield: For metabolic acidosis, use Winter’s formula: If PaCO₂ isn’t appropriately low, you’re dealing with a mixed disorder.
D. Respiratory alkalosis
Why it tempts you: COPD patients can be tachypneic early, and some vignettes revolve around hyperventilation.
Why it’s wrong: Respiratory alkalosis requires:
- PaCO₂ low
- pH high (alkalemia) or near-normal if compensated
Here PaCO₂ is 60 and pH is 7.30 → not compatible.
High-yield causes of respiratory alkalosis:
- Anxiety/panic, pain
- Pregnancy (progesterone-driven hyperventilation)
- High altitude
- Early salicylate toxicity
- Sepsis, liver disease
- Pulmonary embolism (often with hypoxemia)
E. Mixed metabolic acidosis and respiratory acidosis
Why it tempts you: “He’s sick, so mixed disorder.” Also, acute-on-chronic COPD can coexist with lactic acidosis.
Why it’s wrong based on the ABG provided: A mixed metabolic acidosis + respiratory acidosis would show:
- PaCO₂ high (resp acidosis)
- HCO₃⁻ low (metabolic acidosis)
But HCO₃⁻ is 29 (elevated), which argues against a concurrent metabolic acidosis in this dataset.
How to catch a true mixed disorder:
- If pH is abnormal and compensation is too much or too little compared to expected, suspect a second primary process.
- Example clue: PaCO₂ is high, but HCO₃⁻ is lower than expected for chronic respiratory acidosis → add metabolic acidosis.
High-Yield Acid–Base Rules You Should Memorize
Primary respiratory disorders: expected bicarbonate change
| Disorder | Acute compensation | Chronic compensation |
|---|---|---|
| Respiratory acidosis (↑ PaCO₂) | ↑ HCO₃⁻ by ~1 per +10 | ↑ HCO₃⁻ by ~3.5–4 per +10 |
| Respiratory alkalosis (↓ PaCO₂) | ↓ HCO₃⁻ by ~2 per −10 | ↓ HCO₃⁻ by ~4–5 per −10 |
Memory hook: Chronic changes are bigger because kidneys need time.
USMLE-Style Clinical Tie-Ins (Renal > Fluid, Electrolytes & Acid-Base)
1) COPD + oxygen = CO₂ retention (but know the real mechanism)
On exams, oxygen can worsen hypercapnia in COPD due to:
- Worsened V/Q mismatch (reversal of hypoxic pulmonary vasoconstriction)
- Haldane effect (oxygenation of Hb reduces CO₂ carriage → more dissolved CO₂)
- Some decrease in hypoxic respiratory drive (less important but still testable)
Clinical clue in vignette: COPD patient on more O₂, RR 8, somnolent → hypoventilation with CO₂ narcosis.
2) pH can be “near-normal” in chronic respiratory disease
Chronic respiratory acidosis may have:
- Slightly low pH (or near normal)
- High PaCO₂
- High HCO₃⁻
If the pH is much lower than expected in a known CO₂ retainer, think acute decompensation (e.g., infection, sedatives, fatigue, pneumothorax).
3) The kidney is the long-game player
Renal compensation involves:
- α-intercalated cells: secrete H⁺ via H⁺-ATPase, generate new HCO₃⁻
- Ammonium trapping: NH₃ + H⁺ → NH₄⁺ excreted in urine
This is why compensation takes days, not minutes.
Rapid-Fire Practice: One-liners You Should Be Able to Answer
- Opioid overdose ABG: low pH, high PaCO₂ → acute respiratory acidosis
- Panic attack ABG: high pH, low PaCO₂; HCO₃⁻ slightly low → acute respiratory alkalosis
- Pregnancy ABG: mild respiratory alkalosis with decreased HCO₃⁻ chronically
- COPD baseline: high PaCO₂, high HCO₃⁻, pH near normal → chronic respiratory acidosis
- Salicylate toxicity early: respiratory alkalosis; late: mixed with anion gap metabolic acidosis
Takeaway: How to Win These Questions
- Start with pH (acidemia vs alkalemia).
- Pick the primary driver (PaCO₂ vs HCO₃⁻).
- Check compensation with numbers (acute vs chronic).
- If compensation is “wrong,” call a mixed disorder—but only if the values force you there.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
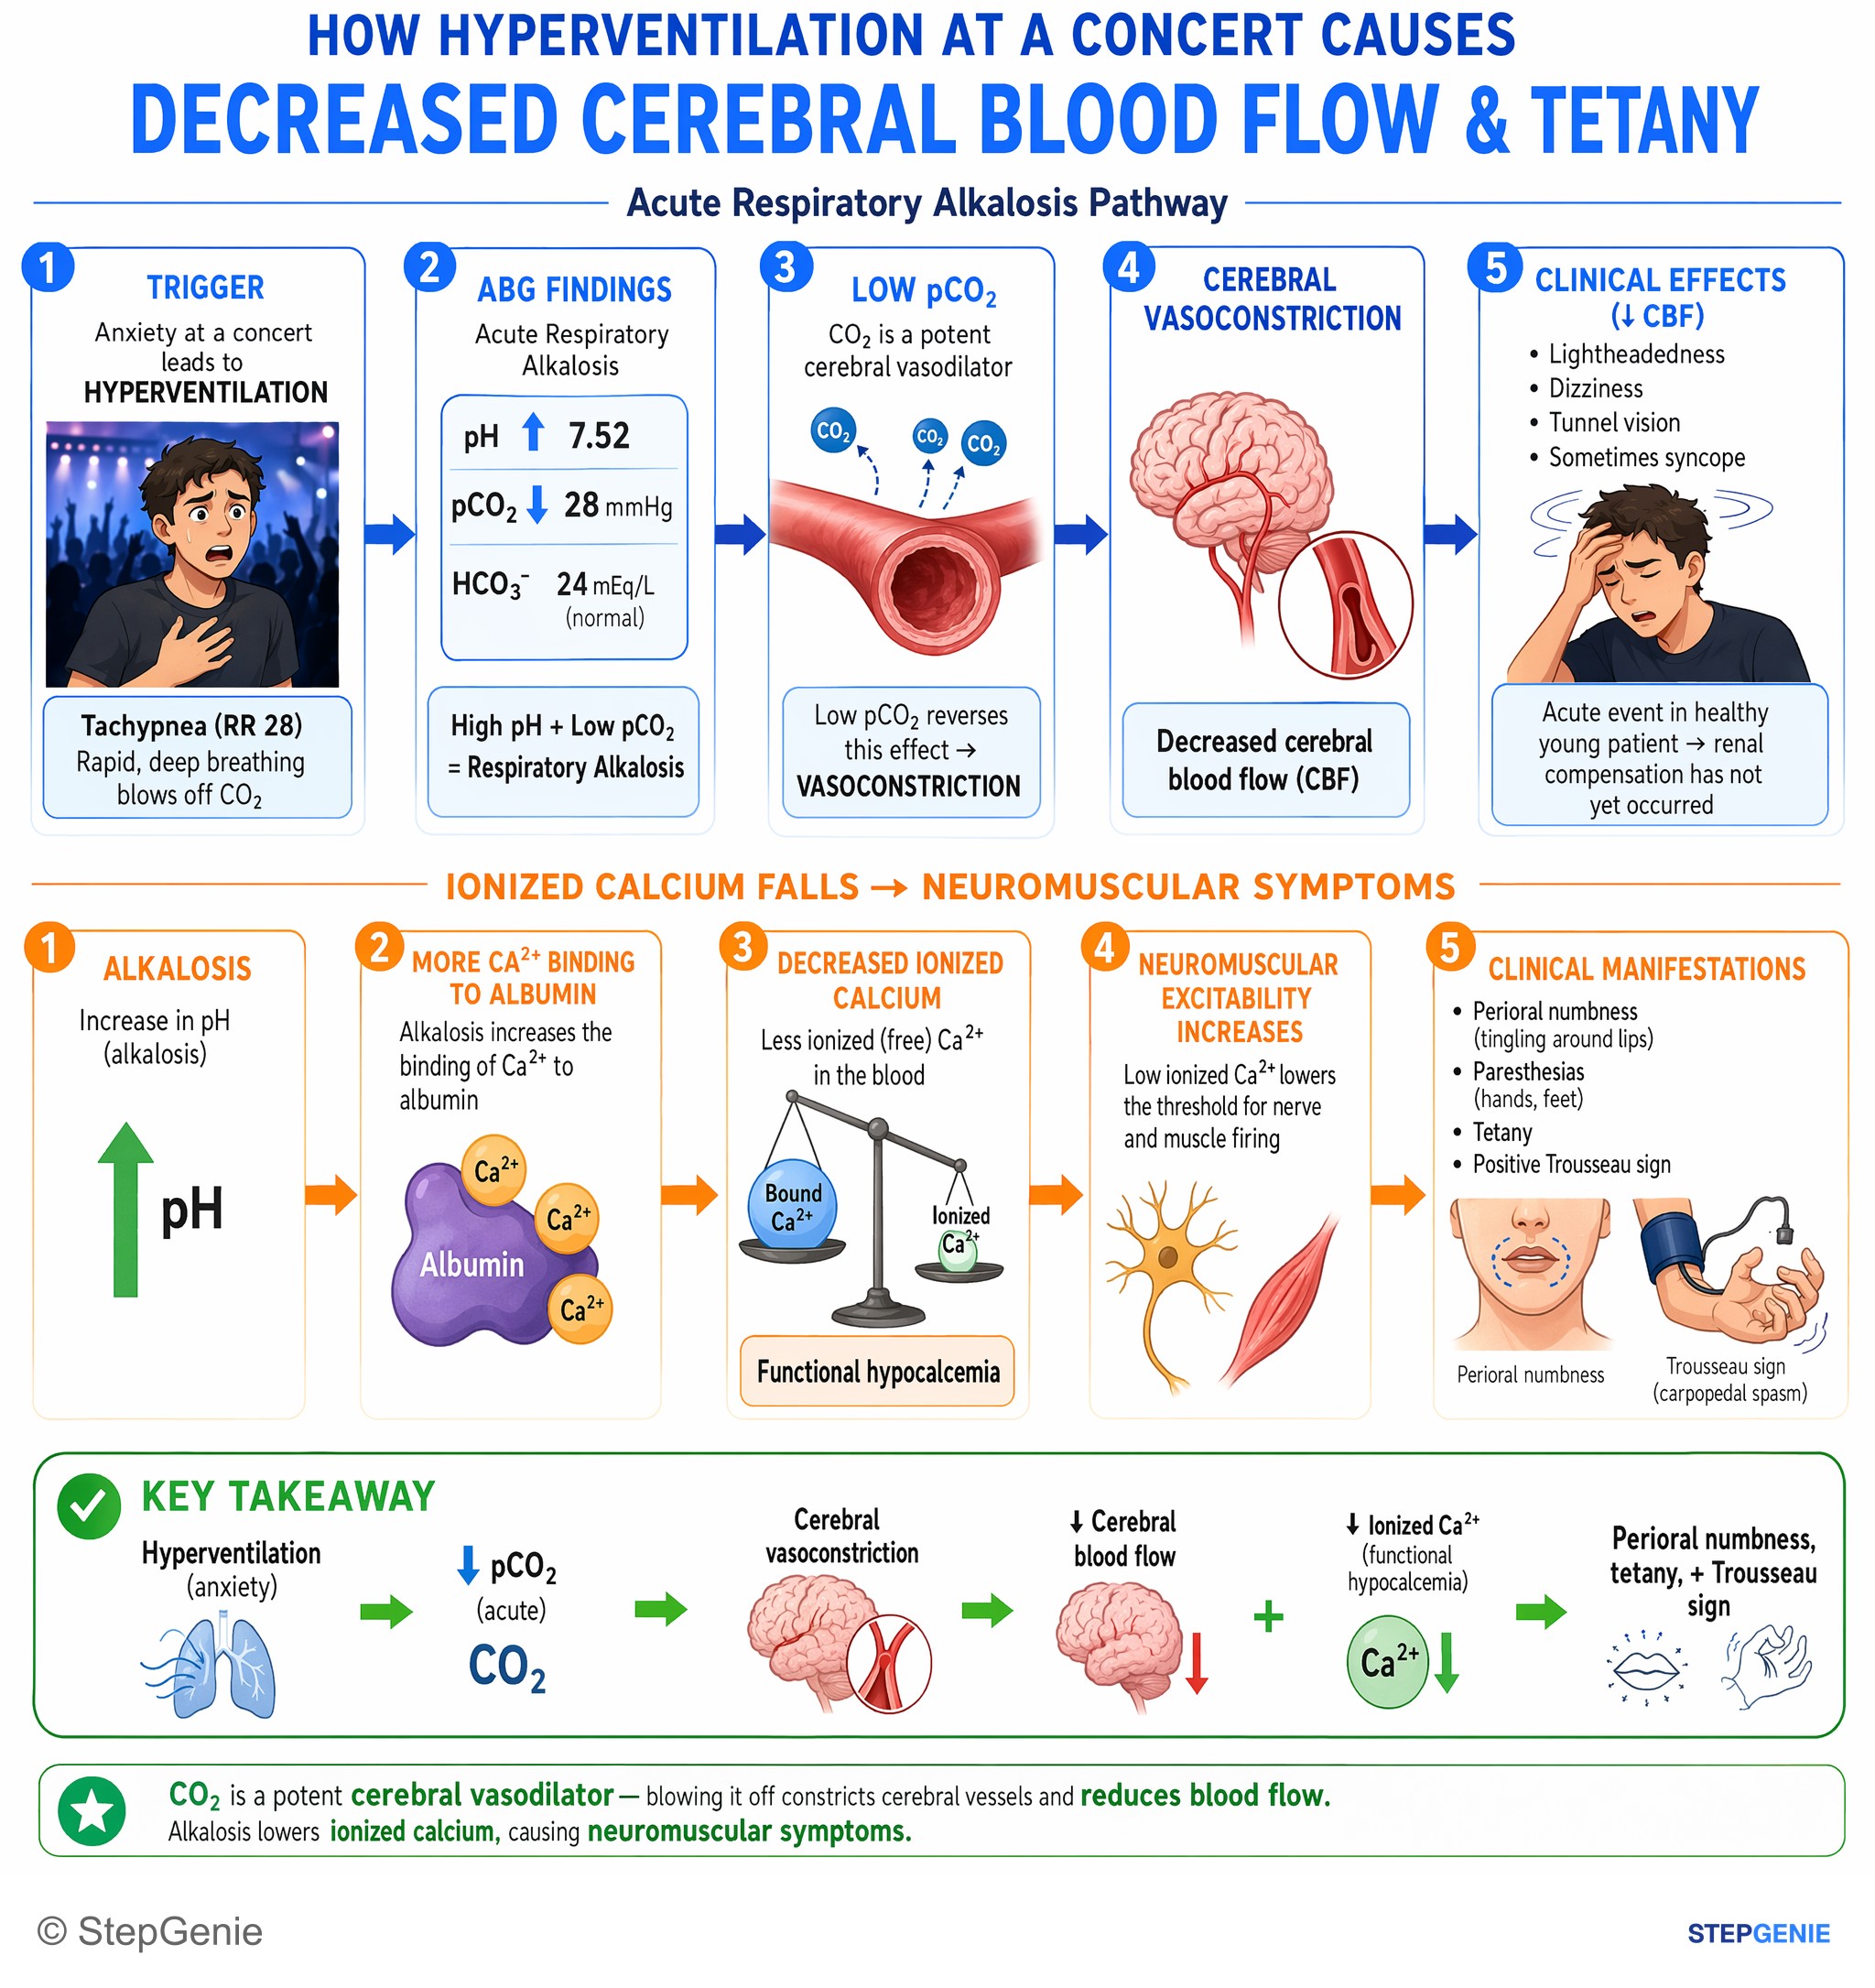
Acute respiratory alkalosis from hyperventilation → ↓pCO2 → cerebral vasoconstriction → decreased cerebral blood flow; ionized calcium…
USMLE Step 1Frequently Asked Questions
How do you tell acute respiratory acidosis from chronic respiratory acidosis on an ABG?
You distinguish them by how much the bicarbonate has risen for the increase in PaCO2. In acute respiratory acidosis, HCO3− increases by about 1 mEq/L for every 10 mm Hg rise in PaCO2, while in chronic respiratory acidosis it increases by about 3.5 to 4 mEq/L per 10. A meaningfully elevated bicarbonate suggests the kidneys have had time to compensate, pointing to chronic or acute-on-chronic disease.
Why is elevated bicarbonate a clue to chronic respiratory acidosis instead of pure acute respiratory acidosis?
Elevated bicarbonate suggests renal compensation, which takes hours to days to develop. In chronic respiratory acidosis, sustained hypoventilation causes CO2 retention, and the kidneys respond by increasing H+ secretion, increasing HCO3− reabsorption and generation, and increasing ammoniagenesis. Because pure acute respiratory acidosis has less time for this response, its bicarbonate rise is smaller than in chronic disease.
Why is this COPD vignette not metabolic acidosis with respiratory compensation?
It is not metabolic acidosis with respiratory compensation because the pattern is the opposite of what metabolic acidosis should show. Metabolic acidosis has a low HCO3− as the primary problem and a low PaCO2 from compensatory hyperventilation. In this vignette, PaCO2 is high and HCO3− is also high, which fits primary respiratory acidosis with renal compensation rather than metabolic acidosis.
When should you suspect a mixed acid-base disorder instead of simple compensation?
You should suspect a mixed disorder when the compensation is too much or too little compared with the expected response. The key is to compare the measured values with the usual compensation rules rather than guessing from the pH alone. For example, if PaCO2 is high but HCO3− is lower than expected for chronic respiratory acidosis, that suggests an added metabolic acidosis instead of simple compensation.
Why can oxygen worsen hypercapnia in COPD patients on exams?
Oxygen can worsen hypercapnia in COPD because it may increase CO2 retention through worsened ventilation-perfusion mismatch and the Haldane effect. A classic test setup is a COPD patient who becomes more somnolent after using more oxygen. The exam point is that the mechanism is not just a simplistic loss of respiratory drive, but these specific physiologic effects that promote CO2 retention.