Metabolic alkalosis is a primary rise in serum bicarbonate (HCO₃⁻) with a compensatory rise in PaCO₂. One process generates it (loss of gastric HCl, diuretics, alkali, mineralocorticoid excess), and the kidney maintains it, because volume, chloride or potassium depletion, or excess aldosterone, makes the nephron hold on to bicarbonate. The urine chloride sorts the causes: a low value (below 20 mEq/L in Merck; StatPearls uses below 10) means chloride- or saline-responsive alkalosis from vomiting, NG suction or past diuretic use, treated with 0.9% saline and potassium chloride. A high value (above 20 mEq/L) means a chloride-resistant cause, such as mineralocorticoid excess, Bartter or Gitelman syndrome, or a diuretic that is still acting.
The question
A 22-year-old woman comes to the clinic with 3 weeks of fatigue and muscle cramps. She says she eats normally and denies vomiting or taking laxatives, diuretics or any other medication. Her BMI is 21 kg/m². Blood pressure is 98/62 mm Hg and pulse is 104/min. She has dry mucous membranes, painless swelling of both parotid glands, erosion of the enamel of her front teeth and small scars on the back of her right hand.
| Test | Result |
|---|---|
| Serum Na⁺ | 137 mEq/L |
| Serum K⁺ | 2.9 mEq/L |
| Serum Cl⁻ | 89 mEq/L |
| Serum HCO₃⁻ | 36 mEq/L |
| Serum Mg²⁺ | 2.0 mg/dL (normal) |
| Creatinine | 0.9 mg/dL |
| Arterial pH / PaCO₂ | 7.50 / 48 mm Hg |
| Urine Na⁺ | 45 mEq/L |
| Urine Cl⁻ | 8 mEq/L |
| Urine diuretic screen | Negative |
Which of the following is the most likely cause of her acid-base disorder?
A. Bartter syndrome B. Gitelman syndrome C. Primary hyperaldosteronism D. Self-induced vomiting E. Surreptitious diuretic use
Answer: D. Self-induced vomiting.
Step 1: Read the blood gas
- pH 7.50 is alkalemia, and HCO₃⁻ of 36 mEq/L makes it a metabolic alkalosis.
- The lungs compensate by hypoventilating. PaCO₂ rises about 0.7 mm Hg for each 1 mEq/L rise in HCO₃⁻ (Merck gives 0.6-0.75), and Merck notes that compensation should not push PaCO₂ above 55 mm Hg. StatPearls writes it as expected PaCO₂ = 0.7 × HCO₃⁻ + 20 (± 5), which gives about 45 (40-50) here; the per-mEq rule gives 40 + 0.7 × 12, about 48.
- Measured PaCO₂ of 48 mm Hg fits, so there is no second respiratory disorder. A PaCO₂ clearly outside the expected range means a mixed disorder (the formulas are compared on the Winter's formula page).
- Anion gap = 137 − (89 + 36) = 12, so no anion gap acidosis is hiding underneath.
Step 2: Let the urine chloride sort the cause
| Urine Cl⁻ | Category | Typical causes | What fixes it |
|---|---|---|---|
| Low: below 20 mEq/L (Merck); below 10 (StatPearls) | Chloride- (saline-) responsive | Vomiting, NG suction, diuretics taken in the past, laxative abuse, posthypercapnia | IV 0.9% saline plus KCl |
| High: above 20 mEq/L | Chloride- (saline-) resistant | Primary or secondary hyperaldosteronism, licorice, Liddle syndrome, Bartter and Gitelman syndromes, K⁺ or Mg²⁺ depletion, a diuretic still acting | Treat the cause; replace K⁺ and Mg²⁺ |
- Why not urine sodium? When metabolic alkalosis and volume depletion coexist, bicarbonate spills into the urine and drags sodium with it, so urine Na⁺ can be high despite volume depletion. Merck: a urine chloride below 10 mEq/L more reliably indicates volume depletion. That explains this patient's urine Na⁺ of 45 mEq/L.
- Diuretics change the result with timing. Urine chloride is high while a diuretic is still acting and low once it wears off (CMAJ 2024). Repeated random urine samples help: chloride stays persistently high in Bartter and Gitelman syndromes but is only intermittently high with diuretic misuse, and a urine diuretic screen settles it.
- Next step when urine Cl⁻ is high (Merck): a urine K⁺ above 30 mEq/day without hypertension suggests diuretic abuse, Bartter or Gitelman syndrome; with hypertension, look for hyperaldosteronism, other mineralocorticoid excess or renovascular disease.
Every answer choice, explained
- D. Self-induced vomiting (correct). Hypokalemic metabolic alkalosis, low blood pressure and a urine chloride of 8 mEq/L make this chloride-responsive alkalosis, and the exam gives the source away: painless parotid enlargement, erosion of the front teeth and scars on the back of the hand from triggering the gag reflex are the purging signs Merck lists for bulimia nervosa. Patients with bulimia are typically of normal weight, so a normal BMI does not argue against it. With the diuretic screen negative, vomiting is the cause.
- A. Bartter syndrome. An autosomal recessive salt-wasting defect in the loop of Henle, so it behaves like a loop diuretic: the kidney keeps losing NaCl and urine chloride is high, not 8. Bartter syndrome begins before birth (polyhydramnios) or in early childhood, with hypercalciuria and nephrocalcinosis (loop diuretics cause the same pattern).
- B. Gitelman syndrome. An autosomal recessive defect in NaCl reabsorption in the distal convoluted tubule, usually from SLC12A3 variants, so it mimics a thiazide: hypomagnesemia, hypocalciuria and a persistently high urine chloride. It usually shows up in late childhood or adolescence, and some patients have low blood pressure. Her magnesium is normal and her urine chloride is low.
- C. Primary hyperaldosteronism. Mineralocorticoid excess expands volume, so it causes hypertension with suppressed renin and a high urine chloride (chloride-resistant). A blood pressure of 98/62 mm Hg with signs of volume depletion rules it out. Full workup: primary hyperaldosteronism (Conn syndrome).
- E. Surreptitious diuretic use. Diuretic misuse is itself a purging behavior and the classic look-alike of hidden vomiting: it also causes hypokalemic alkalosis with low blood pressure, and once the drug has worn off, urine chloride can be low, which is why this choice is tempting. But urine chloride is high while the drug acts, and here the urine diuretic screen is negative while the physical signs point to vomiting.
Saline-responsive vs saline-resistant: the full map
| Pattern | Blood pressure | Renin / aldosterone | Causes |
|---|---|---|---|
| Low urine Cl⁻ | Low or normal (volume depleted) | High / high (volume depletion stimulates aldosterone) | Vomiting, NG suction, past diuretics, laxative abuse |
| High urine Cl⁻ + hypertension | High | Low / high | Primary aldosteronism |
| High urine Cl⁻ + hypertension | High | Low / low | Licorice (glycyrrhizin), Cushing syndrome, Liddle syndrome |
| High urine Cl⁻ + hypertension | High | High / high | Renovascular disease (secondary aldosteronism) |
| High urine Cl⁻, no hypertension | Normal or low | High / high | Bartter, Gitelman, a diuretic still acting |
Liddle syndrome is an autosomal dominant gain of function of the epithelial sodium channel (ENaC): hypertension, hypokalemia and metabolic alkalosis with low renin and low aldosterone. Amiloride or triamterene works; spironolactone does not (Merck). Licorice (glycyrrhizin) blocks the enzyme that converts cortisol to less active metabolites, so cortisol behaves like a mineralocorticoid.
Why vomiting causes it: generation vs maintenance
- Generation. Vomiting or NG suction removes gastric HCl (stomach fluid has a pH of about 1.5-3.5), and plasma HCO₃⁻ rises.
- Maintenance. Bicarbonate is freely filtered, so a healthy kidney should excrete the excess. Merck: persistent alkalosis means the kidneys have increased HCO₃⁻ reabsorption. In vomiting, three problems lock it in:
- Chloride depletion. Pendrin, the Cl⁻/HCO₃⁻ exchanger of the distal tubule, reabsorbs chloride and secretes bicarbonate; with less chloride delivered, less bicarbonate is secreted (CMAJ).
- Volume depletion. A lower GFR filters less HCO₃⁻, and aldosterone drives distal Na⁺ reabsorption in exchange for H⁺ and K⁺ secretion.
- Hypokalemia. It shifts H⁺ into cells and acidifies proximal tubule cells, which stimulates ammonium production and adds new bicarbonate. Merck calls hypokalemia both a cause and a frequent consequence of metabolic alkalosis.
- Where the potassium goes. Mostly into the urine, not the vomitus: metabolic alkalosis and volume-driven aldosterone both make the kidneys excrete potassium (Merck). See hypokalemia vs hyperkalemia.
"Contraction alkalosis" is the exam term for losing NaCl-rich, bicarbonate-poor fluid (diuretics, cystic fibrosis sweat), which concentrates the HCO₃⁻ that remains. Chloride depletion is the shared problem, which is why chloride-containing fluid corrects it.
Treatment
- Saline-responsive: IV 0.9% saline plus KCl, and stop the losses. Merck suggests running saline 50-100 mL/hour above ongoing losses until urine Cl⁻ exceeds 25 mEq/L and urine pH normalizes.
- Saline-resistant: saline alone rarely helps; treat the cause. Potassium and magnesium supplements and/or potassium-sparing diuretics are usually needed: amiloride or triamterene for Liddle syndrome, adrenalectomy or a mineralocorticoid receptor antagonist for primary aldosteronism, and KCl plus magnesium for Gitelman syndrome, adding amiloride or eplerenone if needed (CMAJ).
- Severe alkalemia (pH above 7.6), per Merck: hemofiltration or hemodialysis, particularly with volume overload and kidney dysfunction; acetazolamide, which raises HCO₃⁻ excretion but can worsen K⁺ and phosphate losses (most helpful in volume-overloaded patients with diuretic-induced alkalosis and in posthypercapnic alkalosis); or dilute HCl through a central line for patients with kidney failure who cannot or should not undergo dialysis.
- Why it matters: severe alkalemia increases protein binding of ionized calcium, causing headache, lethargy, neuromuscular excitability, tetany and seizures, and lowers the threshold for angina and arrhythmias (Merck).
How USMLE tests metabolic alkalosis
- Infant of 3-6 weeks with projectile, nonbilious vomiting: hypertrophic pyloric stenosis, with hypochloremic, hypokalemic metabolic alkalosis. Ultrasound confirms it, and surgery follows once the infant is rehydrated (StatPearls).
- Normal-weight young woman with unexplained hypokalemic alkalosis who denies purging: check the urine chloride, then the teeth, parotids and hands.
- Hypertension + hypokalemic alkalosis: measure renin and aldosterone (Merck adds cortisol), then use the table above.
- Normal blood pressure + high urine chloride: Bartter (urine calcium high) vs Gitelman (magnesium low, urine calcium low) vs a hidden diuretic.
- Milk-alkali syndrome: calcium carbonate antacids cause hypercalcemia, which lowers PTH and increases bicarbonate reabsorption (Merck).
- Posthypercapnic alkalosis: the compensatory HCO₃⁻ of chronic respiratory acidosis persists after PaCO₂ falls, often with volume, K⁺ and Cl⁻ depletion (Merck).
For the full stepwise method, see how to approach acid-base questions.
Key takeaways
- Generation vs maintenance: losing acid or gaining alkali creates the alkalosis; chloride, volume and potassium depletion or mineralocorticoid excess keep the kidney from excreting it.
- Urine chloride is the branch point: low (below 20 mEq/L in Merck, below 10 in StatPearls) = saline-responsive; high (above 20) = saline-resistant or a diuretic still acting.
- Urine sodium misleads in vomiting, because bicarbonaturia drags sodium into the urine.
- High urine chloride: check blood pressure, then renin and aldosterone; Liddle syndrome and licorice have low renin and low aldosterone.
- Bartter is loop-like (hypercalciuria); Gitelman is thiazide-like (hypomagnesemia, hypocalciuria).
- Expected PaCO₂ ≈ 0.7 × HCO₃⁻ + 20 (± 5); compensation should not push PaCO₂ above 55 mm Hg.
- Treatment: 0.9% saline plus KCl for saline-responsive alkalosis; treat the cause for saline-resistant alkalosis.
Sources
- Metabolic Alkalosis — Merck Manual Professional Edition (2025)
- Acid-Base Disorders — Merck Manual Professional Edition (2025)
- Volume Depletion — Merck Manual Professional Edition (2026)
- Hypokalemia — Merck Manual Professional Edition (2025)
- Physiology, Metabolic Alkalosis — StatPearls, NCBI Bookshelf (2023)
- A 23-year-old woman with metabolic alkalosis and hypokalemia — CMAJ (2024)
- Liddle Syndrome — Merck Manual Professional Edition (2026)
- Gitelman syndrome — MedlinePlus Genetics
- Bartter syndrome — MedlinePlus Genetics
- Bulimia Nervosa — Merck Manual Professional Edition (2026)
- Primary Aldosteronism — Merck Manual Professional Edition (2026)
- Pyloric Stenosis — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
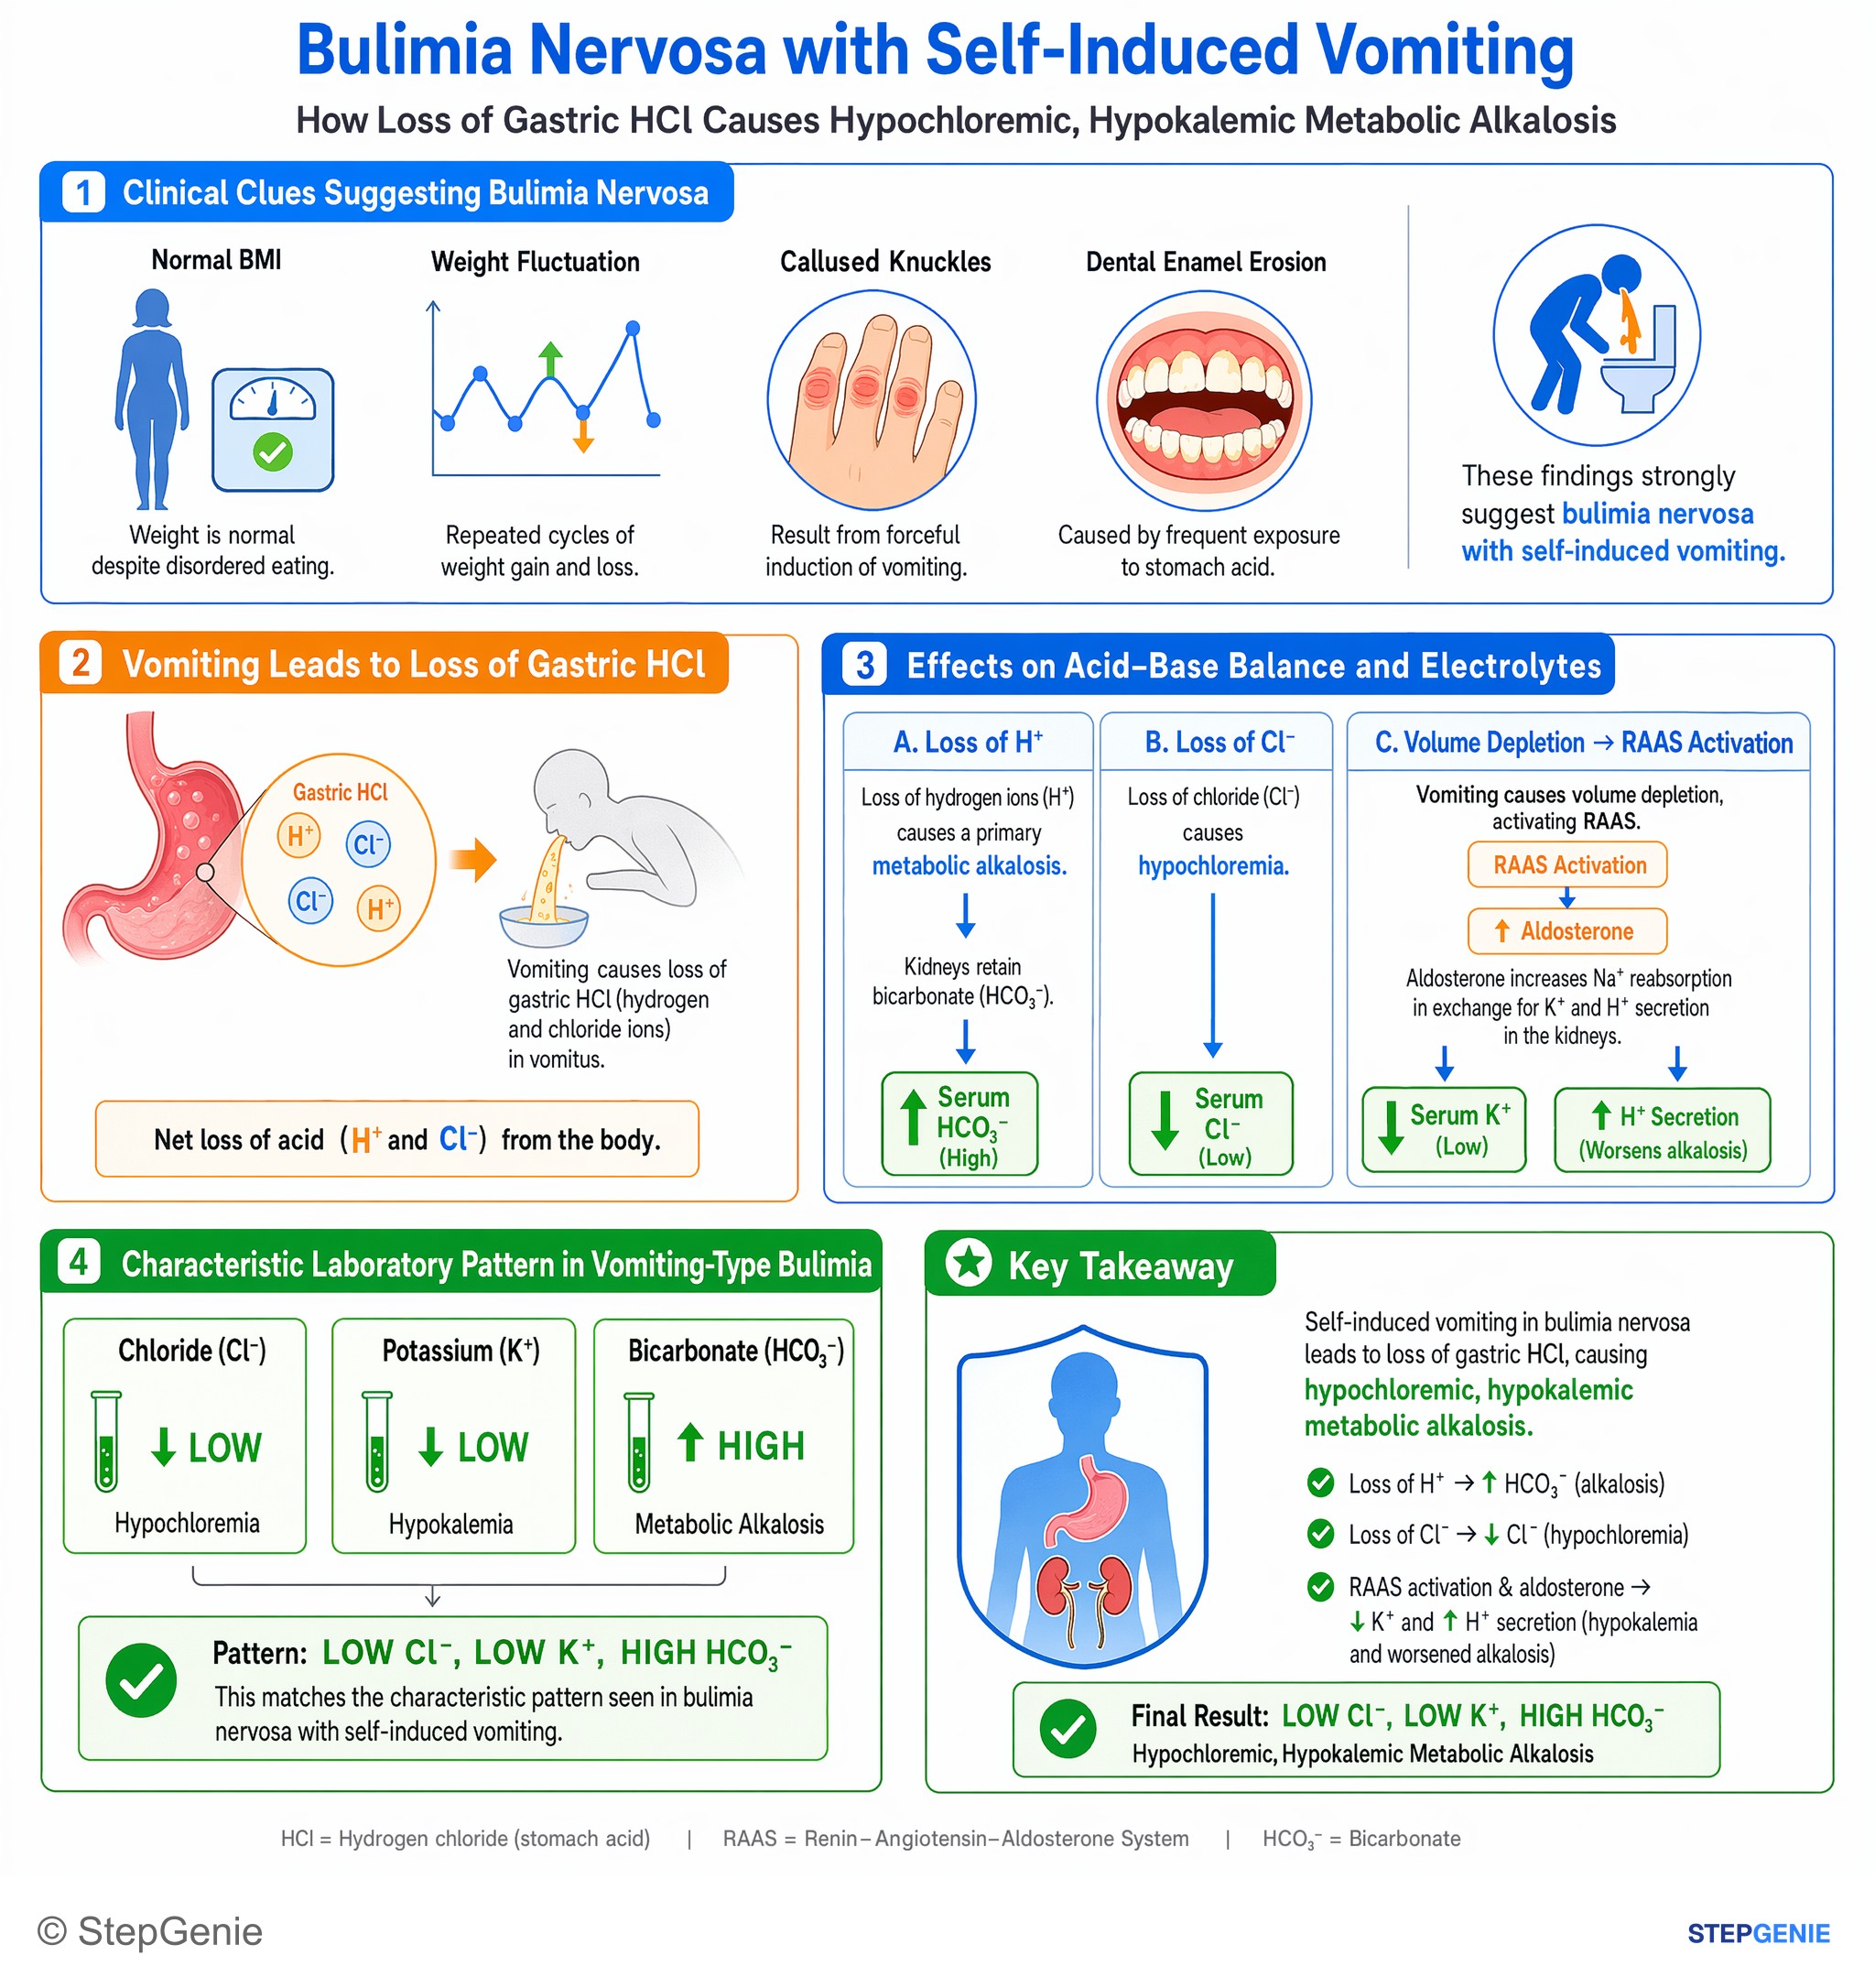
Bulimia nervosa with self-induced vomiting causes hypochloremic, hypokalemic metabolic alkalosis from loss of gastric HCl and secondary…
USMLE Step 1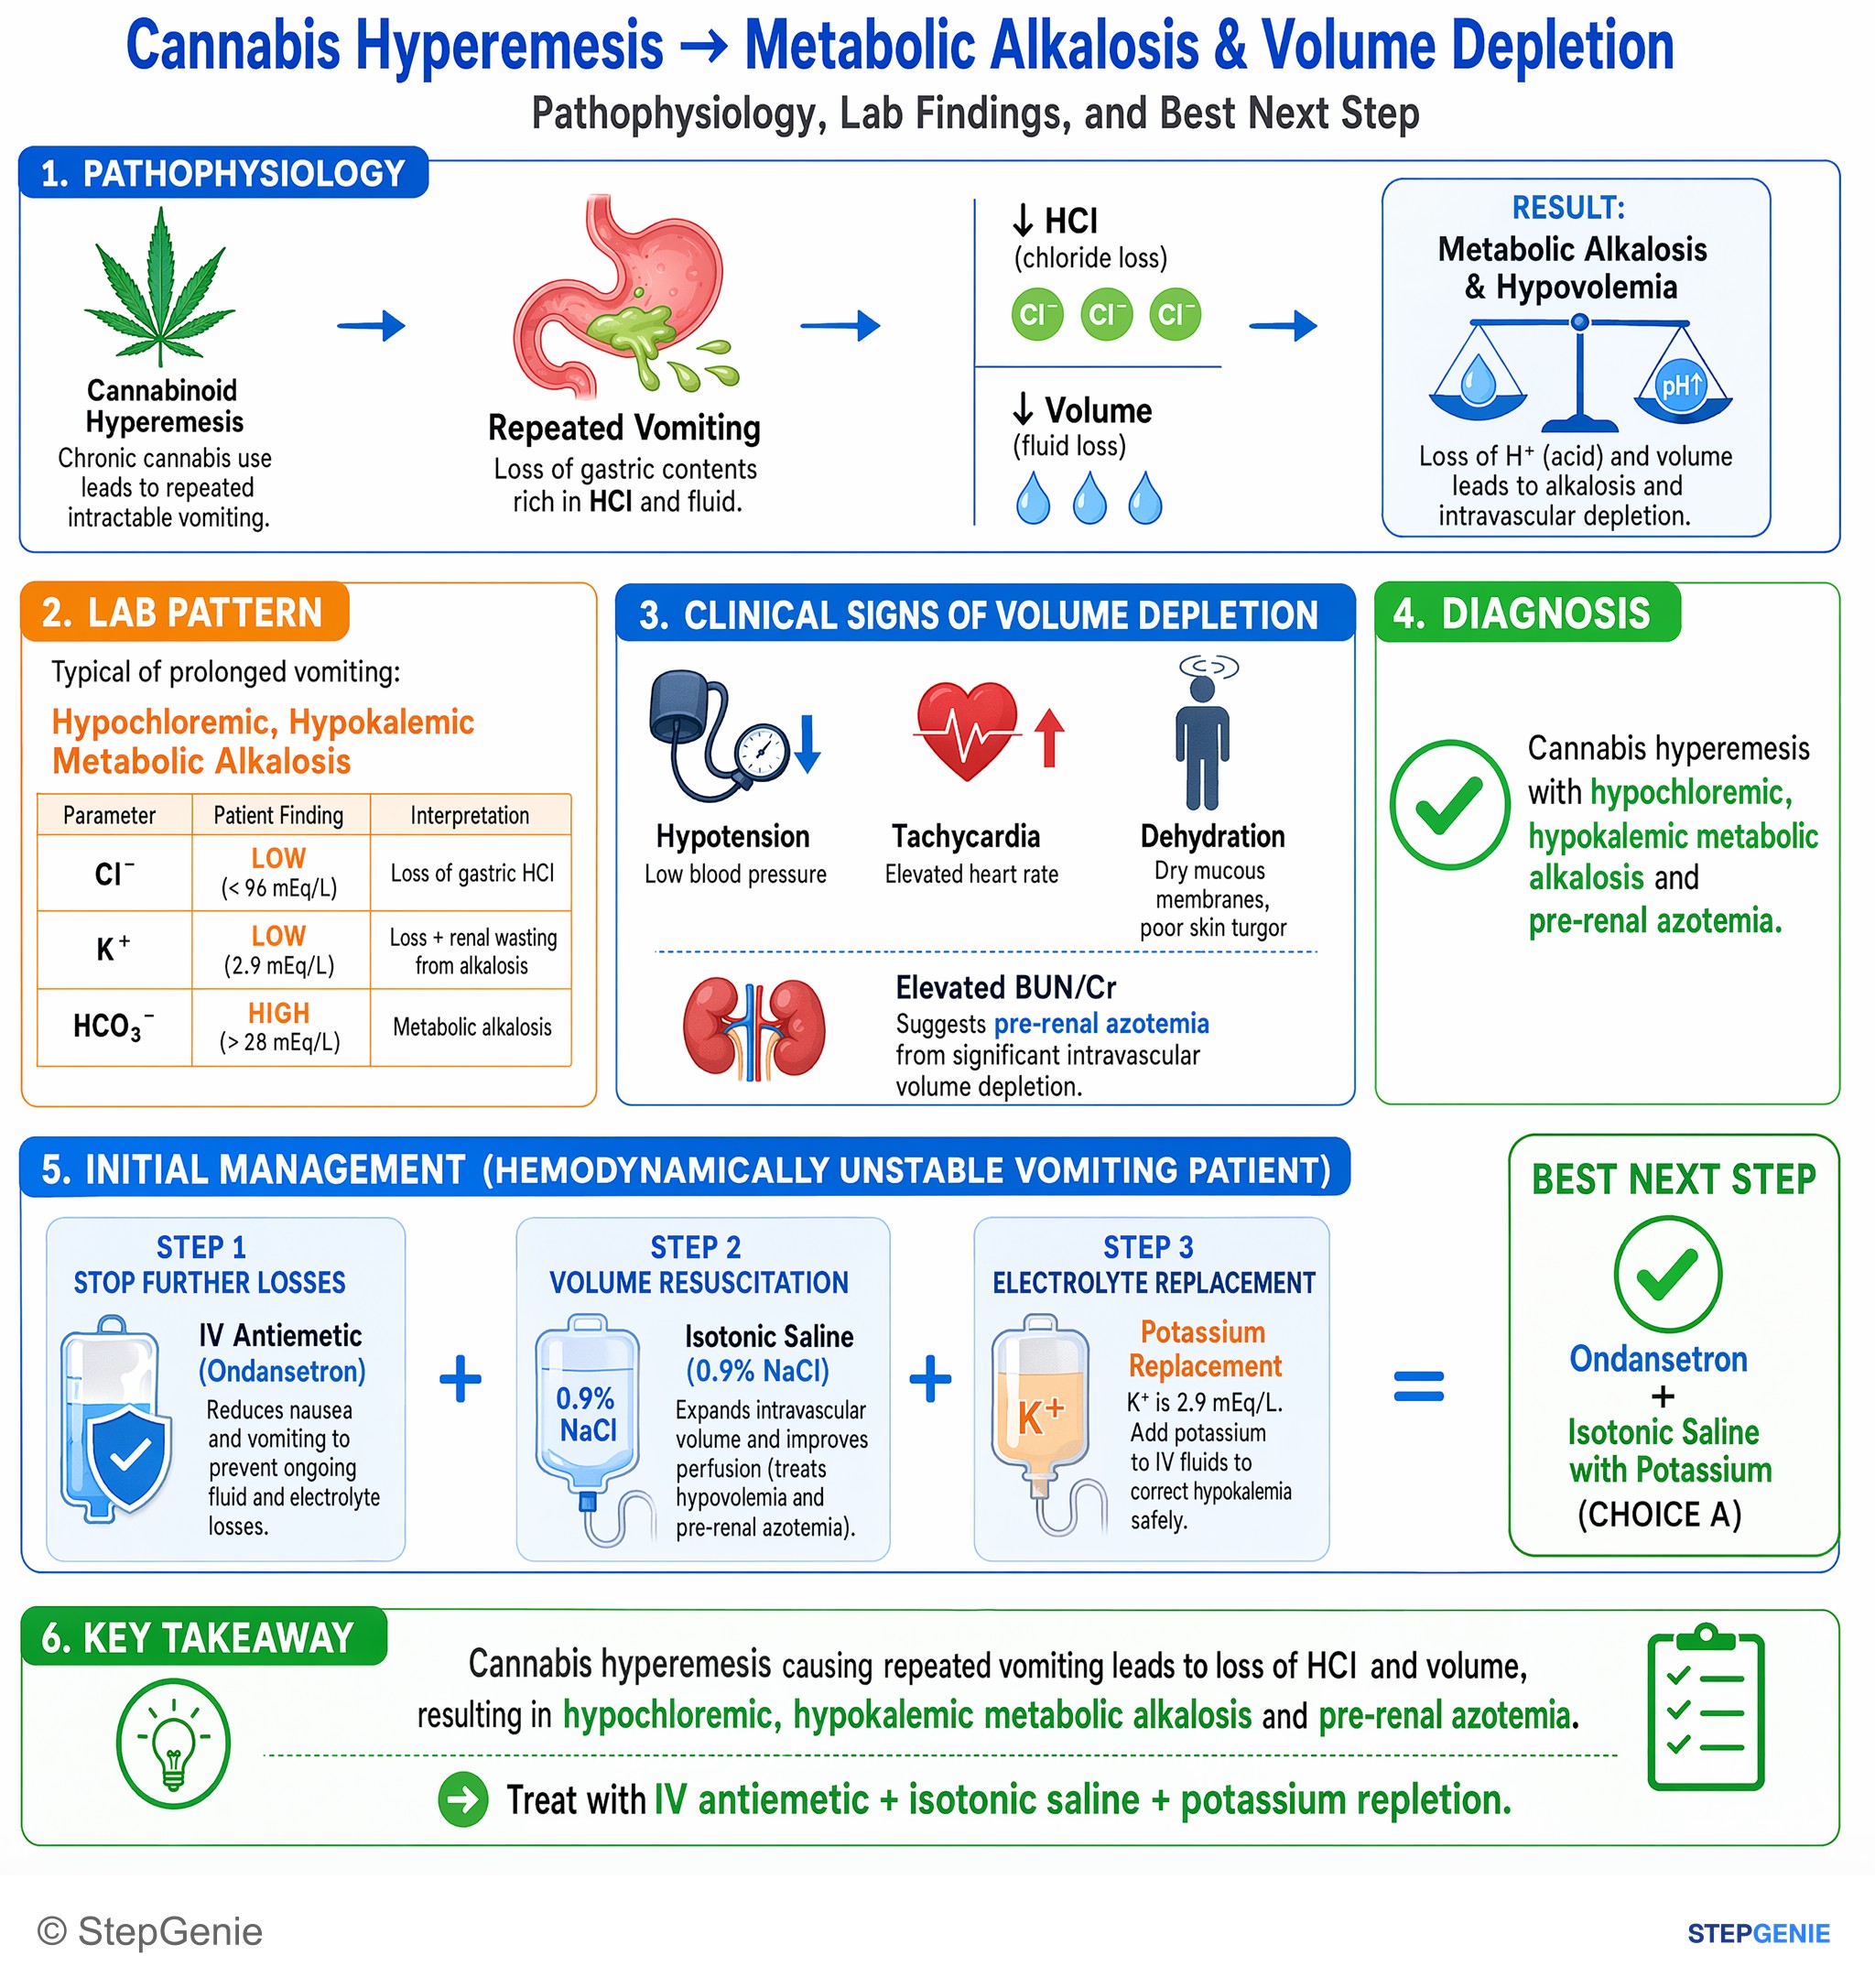
Cannabis hyperemesis with hypochloremic, hypokalemic metabolic alkalosis and volume depletion → treat with antiemetic + isotonic saline…
USMLE Step 2Frequently Asked Questions
What urine chloride level means saline-responsive metabolic alkalosis?
A low urine chloride means the kidney is conserving chloride, which marks chloride- (saline-) responsive metabolic alkalosis. Merck uses below 20 mEq/L for chloride-responsive and above 20 mEq/L for chloride-unresponsive causes; StatPearls uses below 10 and above 20. Typical low-chloride causes are vomiting, nasogastric suction and diuretics taken in the past. A high value points to mineralocorticoid excess, Bartter or Gitelman syndrome, or a diuretic that is still acting.
Why does vomiting cause hypokalemic metabolic alkalosis?
Vomiting removes gastric hydrochloric acid, which raises plasma bicarbonate. The loss of chloride and volume then stops the kidneys from excreting the extra bicarbonate: chloride depletion limits bicarbonate secretion by pendrin, and volume depletion stimulates aldosterone. Potassium falls mainly through the kidneys, not the vomitus, because both the alkalosis and aldosterone increase renal potassium excretion. The hypokalemia then helps keep the alkalosis going.
What is the difference between saline-responsive and saline-resistant metabolic alkalosis?
Saline-responsive (chloride-responsive) alkalosis comes from chloride and volume loss, as in vomiting, nasogastric suction or past diuretic use; urine chloride is low, and IV normal saline with potassium chloride corrects it. Saline-resistant (chloride-resistant) alkalosis comes from mineralocorticoid excess or a renal salt-wasting defect, such as primary aldosteronism, Liddle syndrome, licorice, Bartter or Gitelman syndrome; urine chloride is high and saline alone does not fix it, so the cause must be treated.
Why is urine chloride better than urine sodium in metabolic alkalosis?
When metabolic alkalosis and volume depletion occur together, the kidney can spill bicarbonate into the urine, and sodium has to be excreted with it to keep the urine electrically neutral. Urine sodium can therefore be high even though the patient is volume depleted. Chloride is not pulled out this way, so a low urine chloride (Merck: below 10 mEq/L) is the more reliable sign of volume depletion in this setting.
What is the expected PaCO2 in metabolic alkalosis?
The lungs compensate by hypoventilating, so PaCO2 rises roughly 0.7 mm Hg for every 1 mEq/L rise in bicarbonate (Merck gives 0.6 to 0.75). StatPearls writes this as expected PaCO2 = 0.7 x HCO3 + 20, plus or minus 5. Merck notes that compensation should not push PaCO2 above 55 mm Hg. A measured PaCO2 clearly outside the expected range means a second, respiratory disorder is also present.
How is metabolic alkalosis treated?
Treat the cause and replace what is missing. Saline-responsive alkalosis gets IV 0.9% saline plus potassium chloride; Merck suggests continuing saline until urine chloride exceeds 25 mEq/L and urine pH normalizes. Saline-resistant alkalosis needs cause-specific treatment, such as adrenalectomy or a mineralocorticoid receptor antagonist for primary aldosteronism, amiloride or triamterene for Liddle syndrome, and potassium and magnesium for Gitelman syndrome. Severe alkalemia (pH above 7.6) may need acetazolamide, dilute hydrochloric acid or dialysis.