Metabolic acidosis questions are “free points” on Step exams—if you have a repeatable framework. The trap is that most wrong answers are not random: each distractor usually corresponds to a specific acid–base pattern the test writers expect you to recognize. Let’s walk through a classic vignette, nail the correct diagnosis, and then dismantle every answer choice like you would in a real q-bank review.
Tag: Renal > Fluid, Electrolytes & Acid-Base
The Vignette (Q-bank style)
A 27-year-old woman comes to the ED for 2 days of profuse watery diarrhea. She feels weak and lightheaded. Vitals: T 37°C, HR 112, BP 92/58. Exam shows dry mucous membranes. Labs:
| Lab | Value |
|---|---|
| Na | 140 mEq/L |
| Cl | 112 mEq/L |
| HCO | 14 mEq/L |
| K | 3.0 mEq/L |
| BUN | 28 mg/dL |
| Cr | 1.2 mg/dL |
| Glucose | 90 mg/dL |
| ABG | pH 7.30, PaCO 28 mmHg |
Question: Which acid–base disturbance best explains these findings?
Answer choices (example set):
A. High anion gap metabolic acidosis due to ketoacidosis
B. Normal anion gap metabolic acidosis due to GI bicarbonate loss
C. Normal anion gap metabolic acidosis due to renal tubular acidosis type 1
D. High anion gap metabolic acidosis due to ethylene glycol ingestion
E. Respiratory alkalosis due to anxiety
Step 1: Identify the Primary Disorder
- pH 7.30 → acidemia
- HCO 14 (low) → metabolic process is driving acidemia
- PaCO 28 (low) → respiratory compensation (hyperventilation)
So this is metabolic acidosis with respiratory compensation.
Check compensation with Winter’s formula (high-yield)
For metabolic acidosis: \text{HCO}_3^-
Plug in:
- → expected PaCO 27–31
- Actual PaCO 28 → appropriate compensation
No mixed respiratory disorder.
Step 2: Calculate the Anion Gap
Many NBME-style questions use AG normal ~ 8–12 (some accept up to ~14 depending on lab). Here, the clue is the high chloride with low bicarbonate—classic for hyperchloremic metabolic acidosis, i.e., normal anion gap metabolic acidosis (NAGMA).
Correct Answer: B. Normal anion gap metabolic acidosis due to GI bicarbonate loss
Why diarrhea causes NAGMA (the mechanism you should say in your head)
- Diarrhea → loss of HCO-rich intestinal/pancreatic secretions
- To maintain electroneutrality, the kidney retains Cl → hyperchloremia
- Net effect: ↓ HCO, ↑ Cl, normal AG
Extra high-yield clinical associations
- Diarrhea commonly causes hypokalemia (seen here: K 3.0)
- Volume depletion → prerenal azotemia pattern (often ↑ BUN/Cr ratio), though this question doesn’t hinge on it
Now: Why Each Distractor Is Wrong (and what it would look like)
A. High anion gap metabolic acidosis due to ketoacidosis — Wrong
What ketoacidosis would show:
- High anion gap (unmeasured anions = ketones)
- Often hyperglycemia in DKA (though starvation ketoacidosis can have normal glucose)
- History: diabetes, missed insulin, infection; or prolonged fasting/alcohol use
- Often Kussmaul respirations (deep, labored breathing)
Why it doesn’t fit:
- This patient has hyperchloremia and a non-elevated AG
- Glucose is normal
- History screams GI loss (profuse watery diarrhea)
Exam tip: Ketoacidosis = AG goes up. Diarrhea = chloride goes up.
C. Normal anion gap metabolic acidosis due to RTA type 1 (distal) — Wrong
Distal (type 1) RTA is a favorite NAGMA distractor.
What distal RTA would show:
- NAGMA
- Inability to acidify urine → urine pH > 5.5
- Hypokalemia
- Increased risk of calcium phosphate stones (alkaline urine)
- Associations: amphotericin B toxicity, analgesic nephropathy, autoimmune disease (e.g., Sjögren)
Why it doesn’t fit best:
- The clinical trigger is diarrhea + dehydration; nothing points to chronic renal acidification defect
- In diarrhea, the kidney is usually trying to compensate; in distal RTA it cannot acidify urine despite systemic acidosis
How to separate diarrhea vs RTA quickly (high-yield): Urine anion gap (UAG)
- Diarrhea → kidneys excrete NH (as NHCl) → urine Cl rises → UAG negative
- RTA → impaired NH excretion → urine Cl not appropriately high → UAG positive
If the stem gives urine electrolytes, that’s your separator.
D. High anion gap metabolic acidosis due to ethylene glycol ingestion — Wrong
Ethylene glycol and methanol are classic HAGMA toxic alcohol causes.
What ethylene glycol would show:
- High anion gap metabolic acidosis
- Often osmolar gap early (before metabolites accumulate)
- Renal failure, flank pain
- Calcium oxalate crystals in urine (envelope/dumbbell)
- Possible hypocalcemia, tetany
Why it doesn’t fit:
- Again: no high AG pattern here; instead, we see hyperchloremic acidosis
- No ingestion history, no altered mental status, no urinary crystal clues
High-yield memory aid: HAGMA causes = “GOLD MARK” (Glycols, Oxoproline, L-lactate, D-lactate, Methanol, Aspirin, Renal failure, Ketoacidosis)
E. Respiratory alkalosis due to anxiety — Wrong
Anxiety-induced hyperventilation is a common distractor because PaCO is low.
What primary respiratory alkalosis would show:
- High pH (alkalemia)
- Low PaCO primary
- Compensatory ↓ HCO (renal) if chronic
Why it doesn’t fit:
- pH is low (acidemia), so PaCO decrease is compensatory—not primary
Test-taking pearl: Start with the pH to decide acidemia vs alkalemia. Then decide whether PaCO and HCO move in the direction that explains the pH.
Your Repeatable Approach (Use This Every Time)
1) Determine acidemia vs alkalemia
- pH < 7.35 → acidemia
- pH > 7.45 → alkalemia
2) Identify primary process
- Metabolic: HCO moves with pH
- Respiratory: PaCO moves opposite pH
3) Check compensation
- Metabolic acidosis → Winter’s formula
- Metabolic alkalosis → expected PaCO rises (~ HCO + 20 ± 5 is a commonly taught approximation)
- Respiratory disorders → use acute vs chronic compensation rules (often table-based)
4) If metabolic acidosis, calculate the anion gap
- High AG: add “GOLD MARK” differential
- Normal AG: think diarrhea vs RTA (then use UAG/urine pH if provided)
High-Yield Table: Anion Gap vs Non–Anion Gap Metabolic Acidosis
| Feature | High Anion Gap (HAGMA) | Normal Anion Gap (NAGMA) |
|---|---|---|
| Core problem | Added acids (unmeasured anions) | Loss of HCO or impaired H secretion with Cl retention |
| Anion gap | Increased | Normal |
| Chloride | Often normal | Increased (hyperchloremic) |
| Classic causes | Ketoacidosis, lactic acidosis, renal failure, toxins (methanol/ethylene glycol/salicylates) | Diarrhea, RTA (types 1, 2, 4), ureterosigmoidostomy |
| Key “separator” test | Osmolar gap (toxins), lactate/ketones | Urine anion gap (diarrhea negative, RTA positive) |
| Urine pH clue | Variable | Distal RTA: > 5.5 |
Board-Style Takeaways You Should Memorize
- Diarrhea → NAGMA + hypokalemia + hyperchloremia
- Winter’s formula confirms if compensation is appropriate:
- UAG negative points to extrarenal bicarbonate loss (e.g., diarrhea); UAG positive suggests RTA
- Don’t be tricked by a low PaCO: check the pH first to determine what’s primary
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
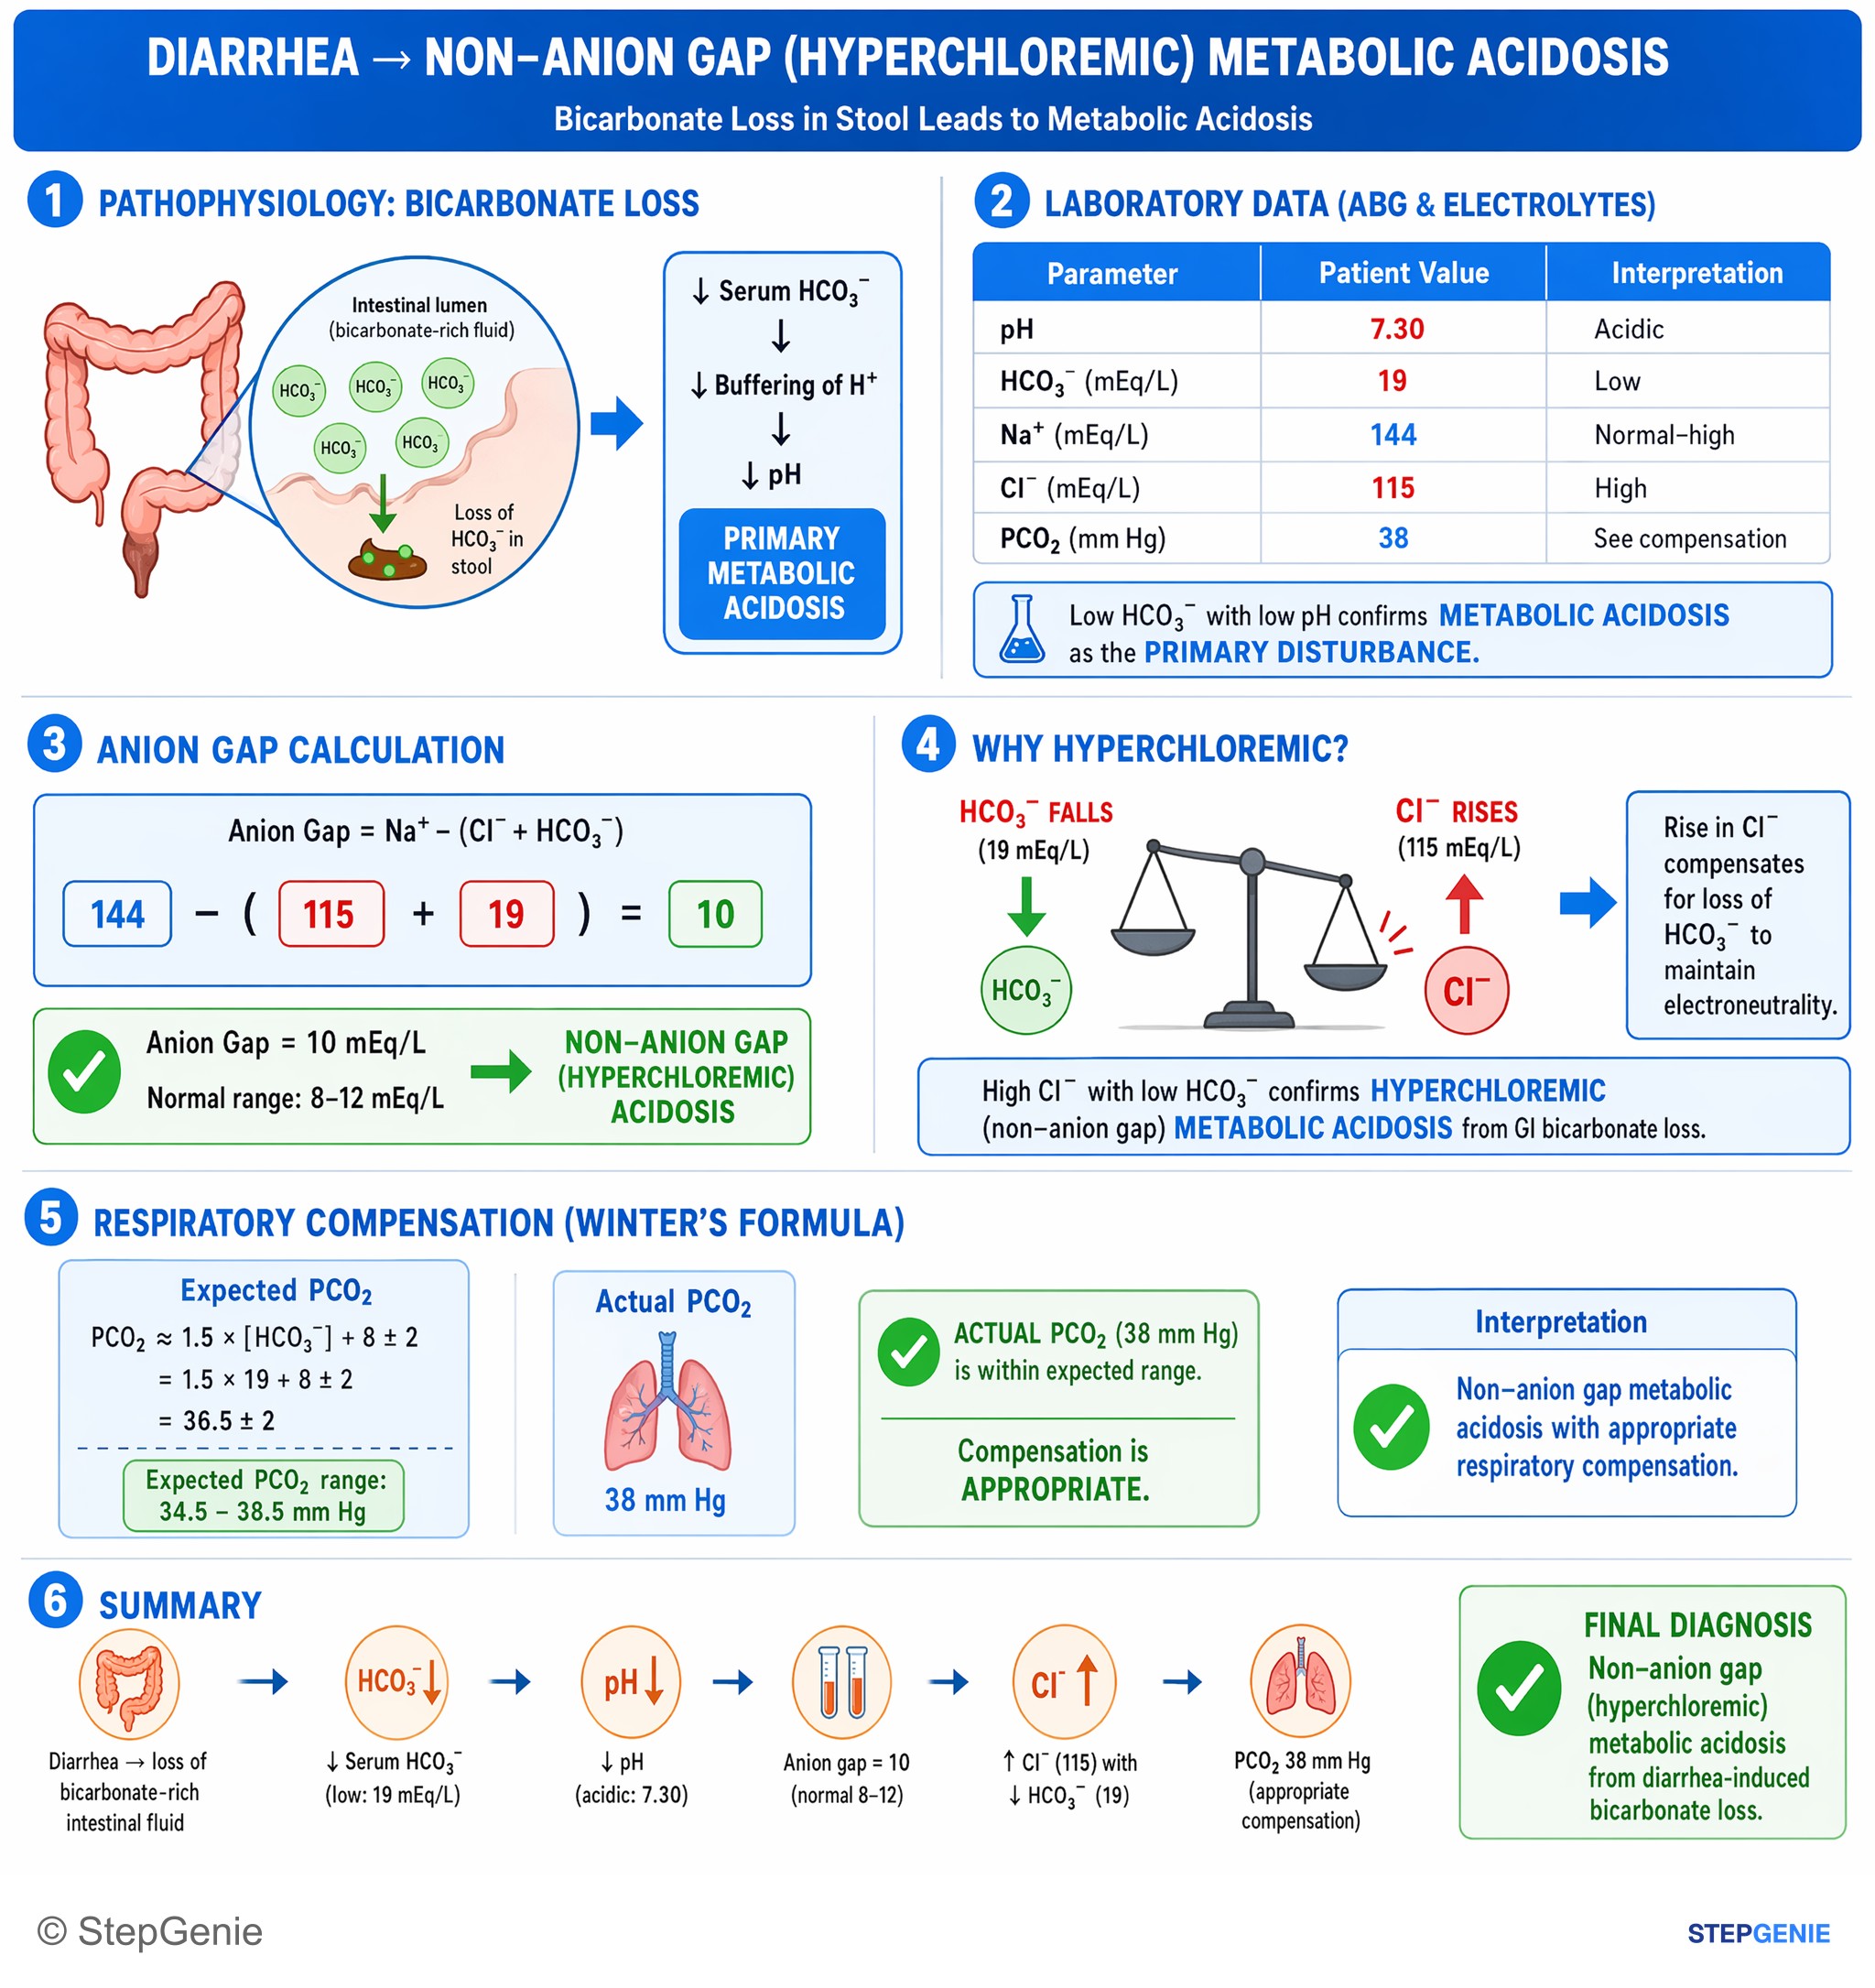
Non–anion gap metabolic acidosis from diarrhea-induced bicarbonate loss; mildly low HCO₃⁻, low pH, normal anion gap, slight respiratory…
USMLE Step 1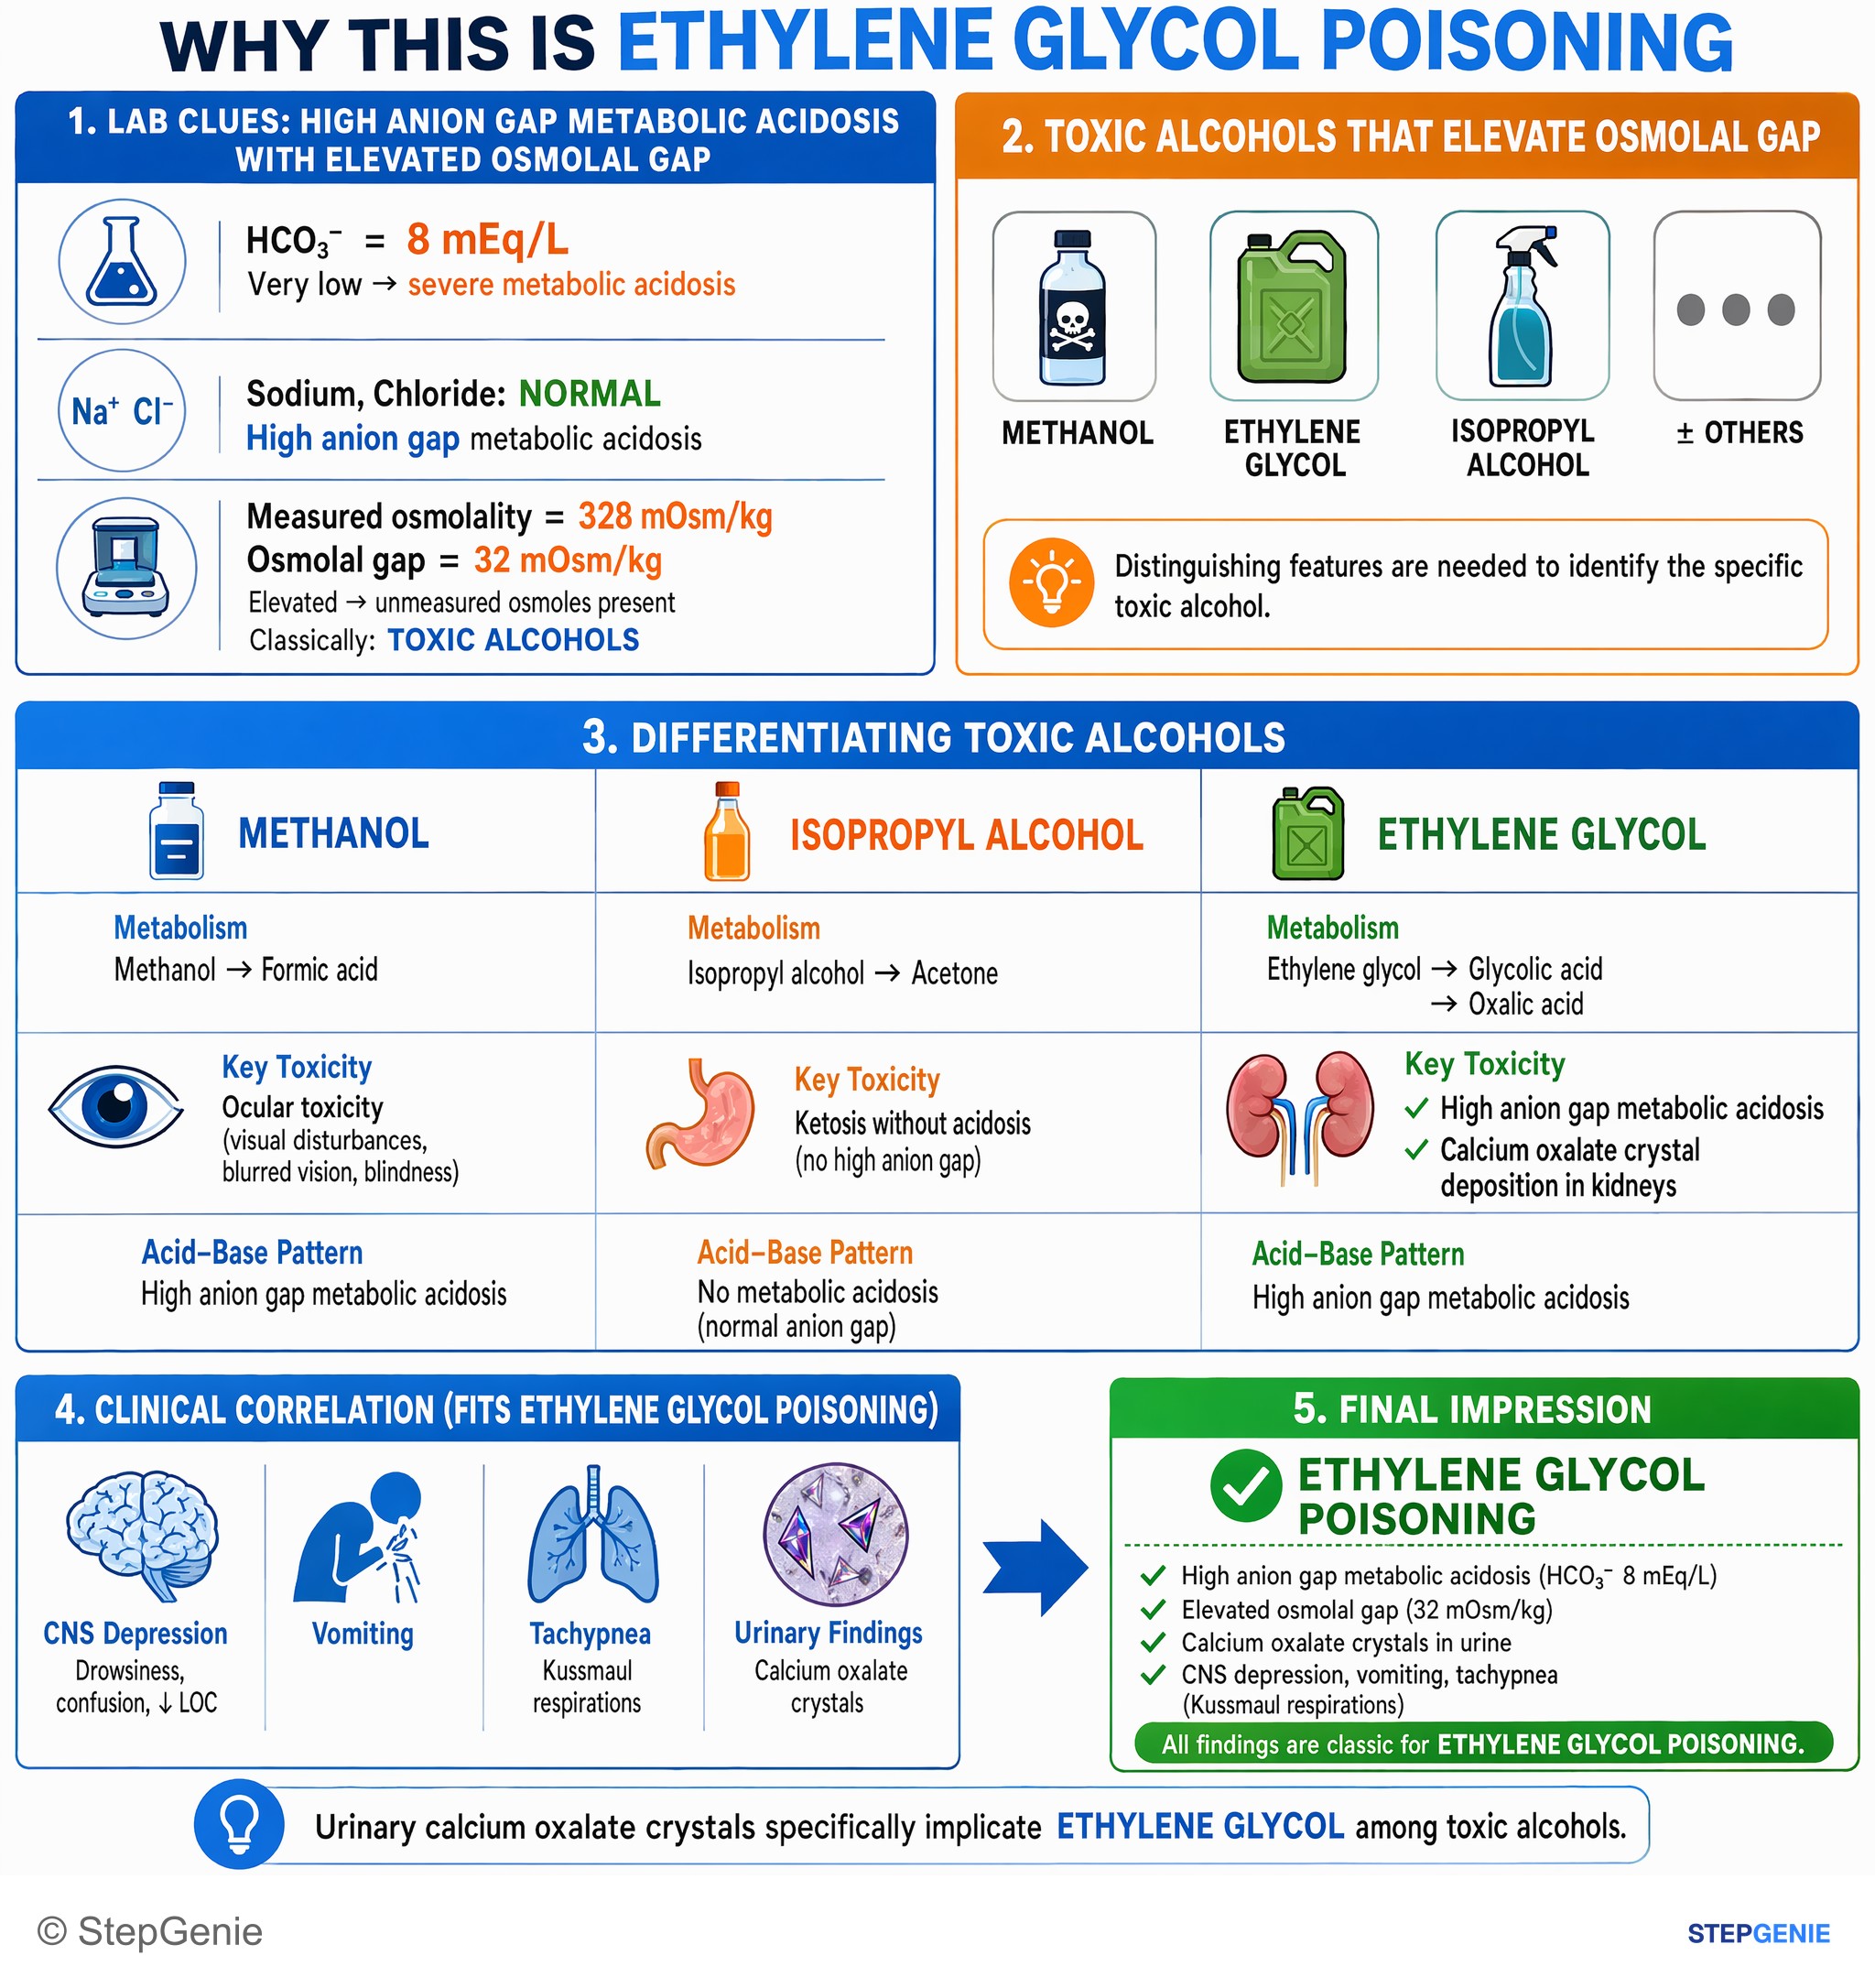
Ethylene glycol poisoning → high anion gap metabolic acidosis + elevated osmolal gap + calcium oxalate kidney crystals and neurologic…
USMLE Step 1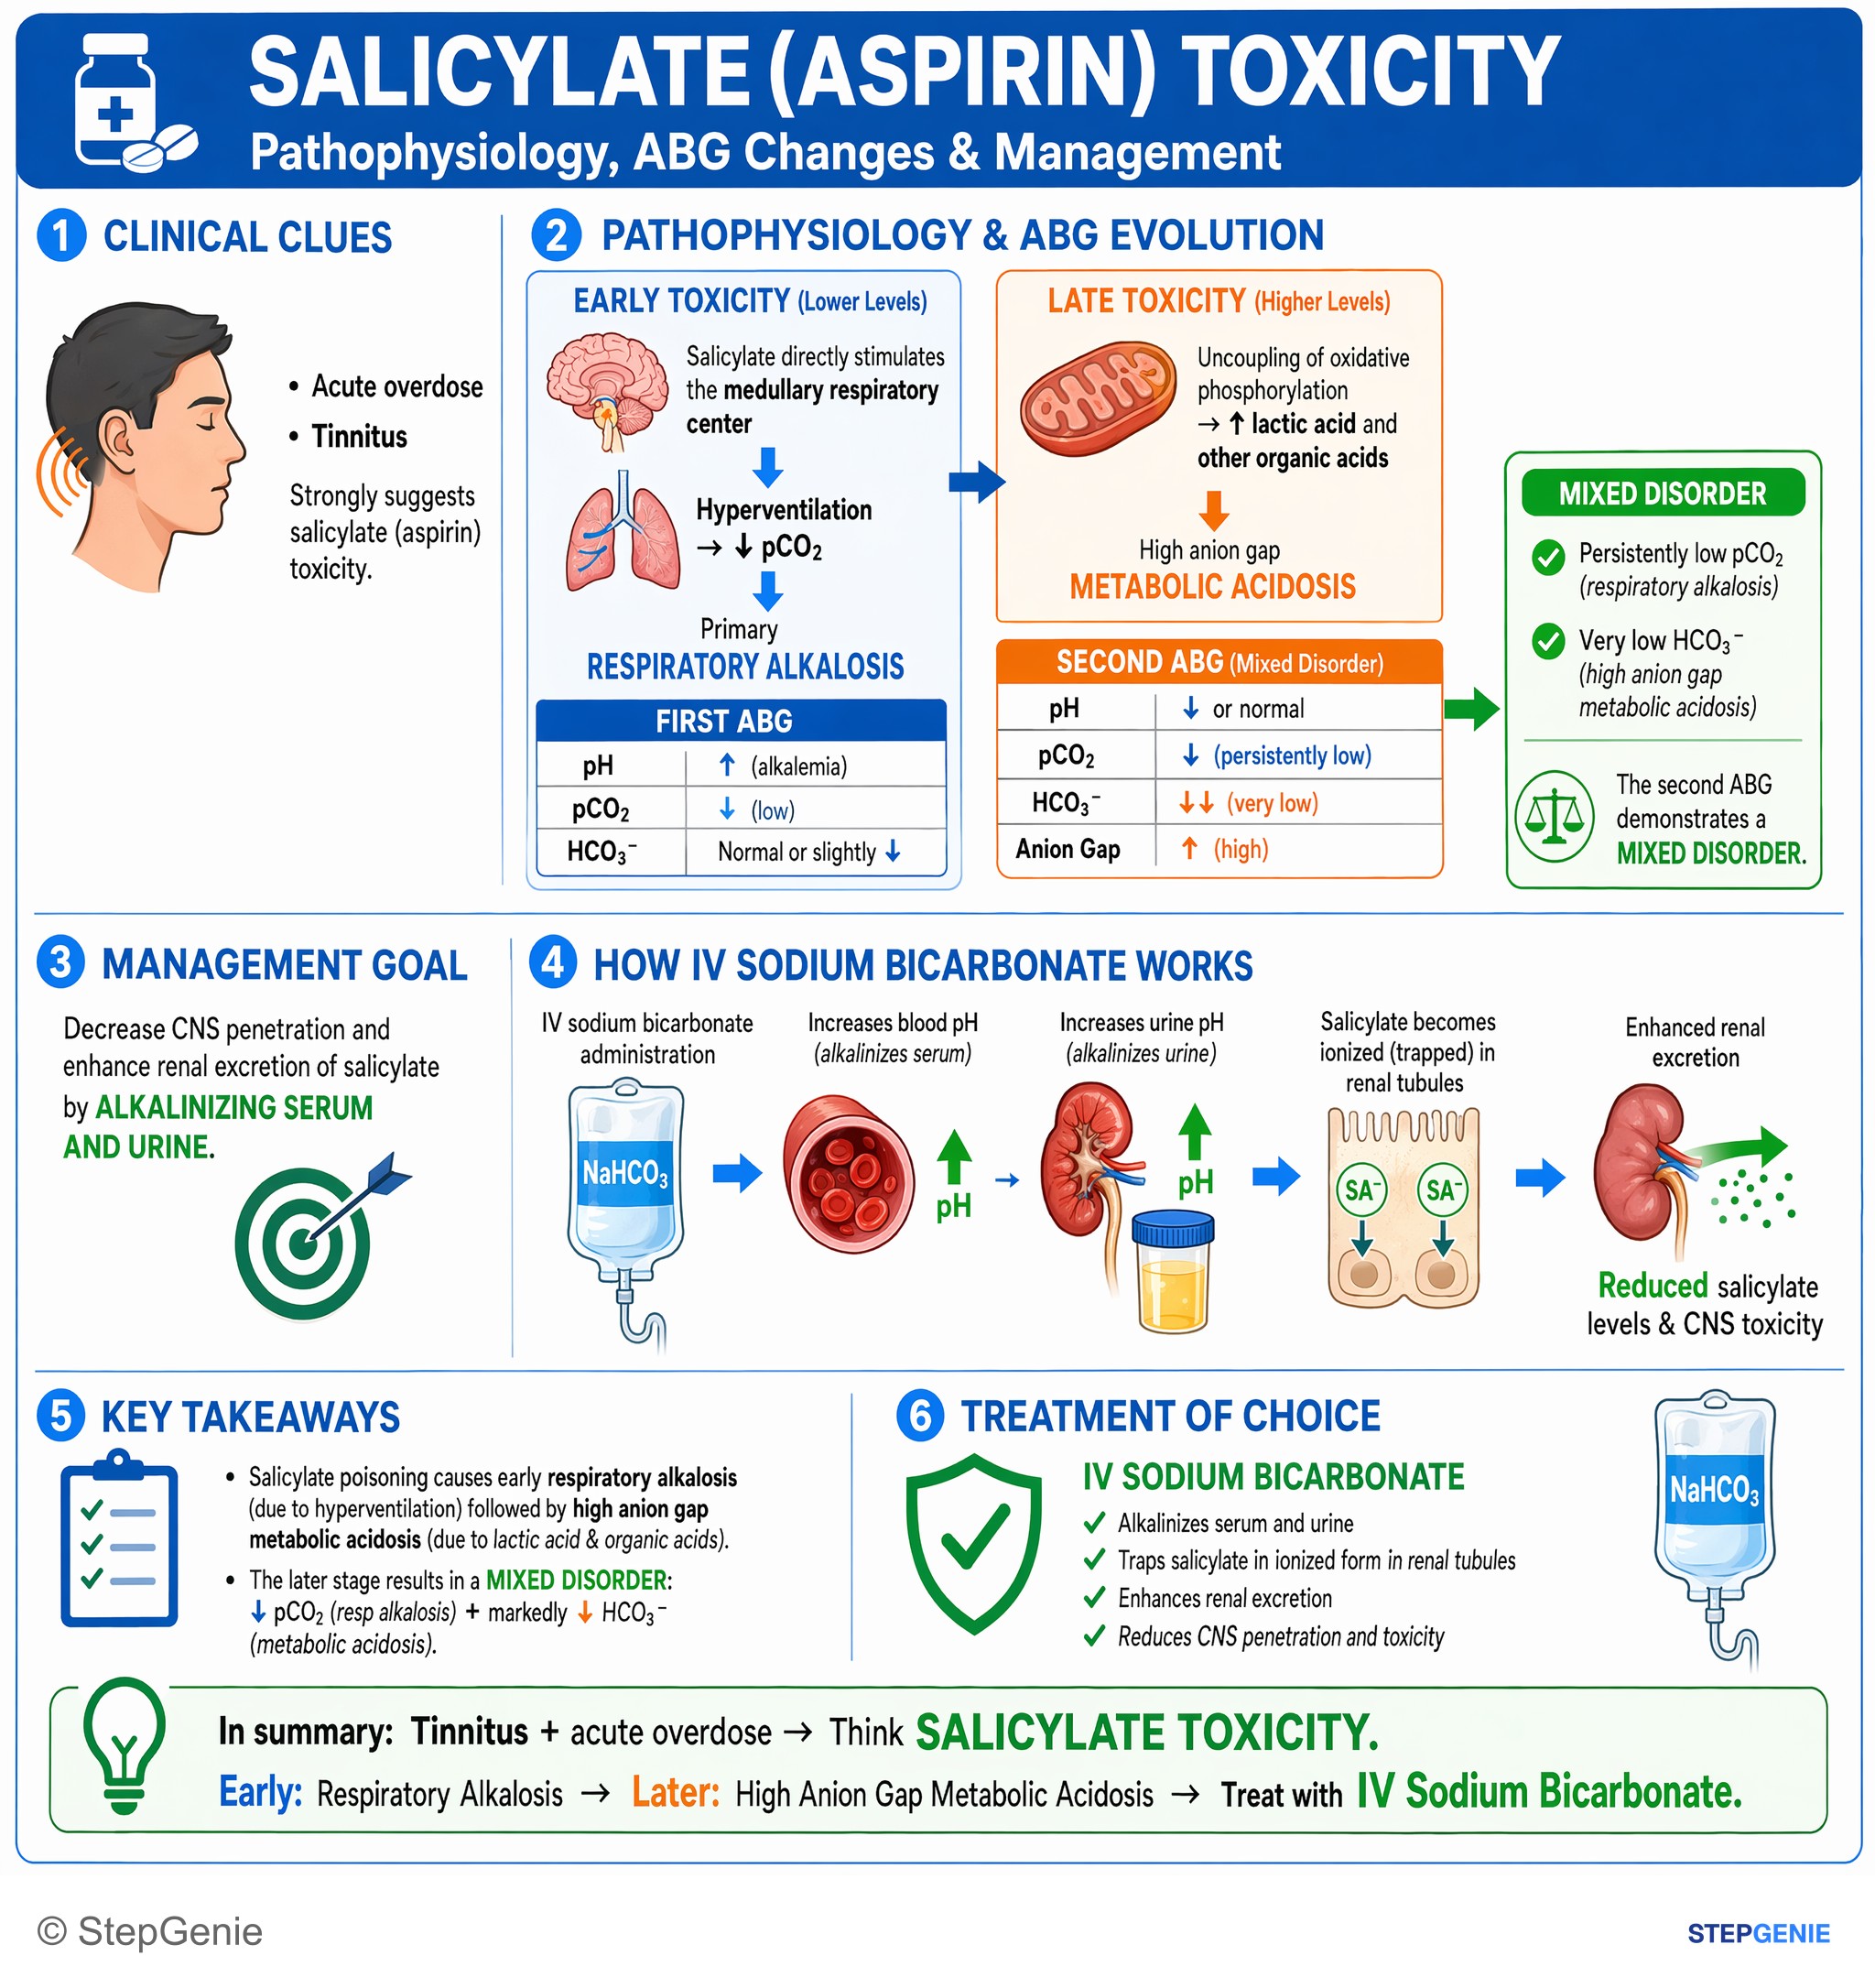
Salicylate poisoning causes early respiratory alkalosis followed by anion gap metabolic acidosis; treat with IV sodium bicarbonate to…
USMLE Step 2Frequently Asked Questions
How do you tell diarrhea from ketoacidosis or ethylene glycol in metabolic acidosis?
Diarrhea causes a normal anion gap, hyperchloremic metabolic acidosis, while ketoacidosis and ethylene glycol cause high anion gap metabolic acidosis. The diarrhea pattern is low bicarbonate with elevated chloride from GI bicarbonate loss and renal chloride retention. Ketoacidosis raises the gap through ketones, and ethylene glycol raises it through toxic metabolites, often with clues like urinary crystals or renal failure.
Why does diarrhea cause a normal anion gap metabolic acidosis?
Diarrhea causes normal anion gap metabolic acidosis because it leads to loss of bicarbonate-rich intestinal and pancreatic secretions. To preserve electroneutrality, the kidneys retain chloride, producing hyperchloremia. The result is decreased bicarbonate, increased chloride, and an anion gap that stays normal, which is the classic pattern of hyperchloremic metabolic acidosis seen with profuse watery diarrhea.
How do you know the low PaCO2 is compensation and not another disorder?
You use Winter’s formula to check whether respiratory compensation is appropriate. In metabolic acidosis, expected PaCO2 equals 1.5 times the bicarbonate plus 8, with a margin of 2. With a bicarbonate of 14, the expected PaCO2 is 27 to 31 mmHg, and the actual value is 28, which shows appropriate compensation rather than a mixed respiratory process.
How do you separate diarrhea from distal RTA in normal anion gap acidosis?
The quickest separator is the urine anion gap if urine electrolytes are provided. In diarrhea, the kidneys appropriately excrete ammonium as NH4Cl, which increases urine chloride and makes the urine anion gap negative. In distal type 1 renal tubular acidosis, ammonium excretion is impaired, urine chloride is not appropriately high, and the urine anion gap stays positive despite systemic acidosis.
Why isn’t anxiety-induced respiratory alkalosis the right answer?
It is not respiratory alkalosis because the patient is acidemic, not alkalemic. Anxiety-induced respiratory alkalosis would have a high pH with a low PaCO2 as the primary problem. Here, the pH is low and the bicarbonate is low, so the primary disorder is metabolic acidosis, and the decreased PaCO2 reflects compensatory hyperventilation rather than a primary respiratory disturbance.