You’re doing a calcium question, you recognize something about QT interval or stones, and then the answer choices all blur into “PTH stuff.” This is exactly where q-banks separate pattern recognition from real understanding: calcium disorders are systems physiology + lab interpretation + drug effects all bundled into one vignette. Let’s break down a classic pair—hypocalcemia vs hypercalcemia—and then do what top scorers actually do: interrogate every distractor until you could teach it.
Tag: Renal > Fluid, Electrolytes & Acid-Base
Calcium is a “renal” topic more than people realize: the kidney is where you activate vitamin D, handle phosphate, and decide how much calcium you lose or keep.
The Core Framework (High-Yield)
What calcium values actually mean
- Total calcium depends on albumin (binding).
- Ionized calcium is the biologically active fraction (what nerves and muscles care about).
Corrected calcium (for low albumin):
Acid–base pearl (testable)
- Alkalosis increases Ca binding to albumin → lowers ionized Ca → symptoms of hypocalcemia
- Classic: hyperventilation/panic → perioral numbness, tingling, tetany.
EKG association (fast points)
- Hypocalcemia → prolonged QT
- Hypercalcemia → shortened QT
PTH does three major things (memorize this as a unit)
PTH increases serum calcium and decreases serum phosphate by:
- Bone: ↑ osteoclast activity indirectly (via osteoblast RANKL) → ↑ Ca, ↑ PO₄ release
- Kidney:
- ↑ Ca reabsorption (distal tubule)
- ↓ PO₄ reabsorption (proximal tubule) → phosphaturia
- ↑ 1α-hydroxylase → ↑ calcitriol (1,25-(OH)₂ vitamin D) → ↑ gut Ca/PO₄ absorption
Clinical Vignette (Q-Bank Style)
A 42-year-old woman presents with perioral tingling and muscle cramps 2 days after a total thyroidectomy. Exam shows carpopedal spasm with BP cuff inflation. EKG shows QT prolongation. Labs:
- Ca: 6.9 mg/dL (low)
- Phosphate: 5.8 mg/dL (high)
- PTH: low
Question: What is the most likely cause of her symptoms?
✅ Correct Answer: Hypoparathyroidism due to surgical removal or devascularization of parathyroids
Why this fits perfectly
- Post-thyroidectomy timing + hypocalcemic symptoms (tetany, Chvostek/Trousseau) + prolonged QT
- Low PTH explains the lab pattern:
- ↓ Ca (less renal reabsorption + less bone resorption + less calcitriol activation)
- ↑ phosphate (because PTH normally wastes phosphate; without PTH, phosphate is retained)
Key USMLE takeaway:
Hypoparathyroidism = low Ca + high PO₄ + low PTH (often after thyroid/parathyroid surgery).
Now the Money: Why Every Distractor Is Wrong (and When It Would Be Right)
Below is a rapid “if-then” map. The goal isn’t just eliminating—it’s recognizing the alternate vignette each distractor belongs to.
Distractor 1: Vitamin D deficiency
Why it’s tempting: low Ca can happen.
Why it’s wrong here: phosphate is usually low/normal, and PTH would be high (secondary hyperparathyroidism).
Typical pattern
- ↓ vitamin D → ↓ GI Ca absorption → ↓ Ca → ↑ PTH
- PTH wastes phosphate → low phosphate
When you pick it
- Low Ca + low PO₄ + high PTH
- Risk factors: malnutrition, low sunlight, malabsorption, chronic liver disease
- Bone findings: osteomalacia/rickets (bone pain, fractures, widened growth plates in kids)
Distractor 2: Chronic kidney disease (secondary hyperparathyroidism)
Why it’s tempting: renal topic + calcium abnormality.
Why it’s wrong here: PTH is low in the vignette; CKD gives high PTH.
Typical CKD mineral bone disease
- ↓ GFR → phosphate retention → ↑ PO₄
- ↑ PO₄ binds Ca → ↓ Ca
- Diseased kidney → ↓ 1α-hydroxylase → ↓ calcitriol → ↓ Ca absorption
- Net: ↑ PTH (secondary hyperparathyroidism)
Classic pattern
- ↓ Ca, ↑ PO₄, ↑ PTH, ↓ calcitriol
When you pick it
- Longstanding CKD signs (anemia, uremic symptoms)
- Bone pain, pruritus, vascular calcifications
Distractor 3: Pseudohypoparathyroidism (end-organ resistance to PTH)
Why it’s tempting: low Ca + high PO₄ can match.
Why it’s wrong here: PTH should be high (the gland is working; tissues don’t respond).
Typical pattern
- ↓ Ca, ↑ PO₄, ↑ PTH
- Due to Gs protein signaling defect
Step-worthy associations
- Albright hereditary osteodystrophy: short 4th/5th metacarpals, short stature, round face
- Type 1a: GNAS mutation with hormone resistance (PTH, TSH, etc.)
When you pick it
- Hypocalcemic symptoms + physical phenotype + high PTH
Distractor 4: Loop diuretic use (e.g., furosemide)
Why it’s tempting: diuretics affect calcium handling.
Why it’s wrong here: there’s no loop exposure, and the phosphate/PTH story doesn’t line up with post-op low PTH.
Mechanism
- Loops block NKCC2 in thick ascending limb → abolish lumen-positive potential → ↓ paracellular Ca and Mg reabsorption → hypocalcemia/hypomagnesemia
When you pick it
- Patient on furosemide with low Ca and low Mg (or refractory hypocalcemia due to low Mg)
Contrast (very high-yield):
- Thiazides increase Ca reabsorption → hypercalcemia risk
- Loops increase Ca excretion → can treat hypercalcemia
Distractor 5: Acute hyperventilation (respiratory alkalosis)
Why it’s tempting: tingling/tetany can happen even with “normal” total calcium.
Why it’s wrong here: labs show true hypocalcemia with low total Ca and low PTH.
Mechanism
- Alkalosis → more Ca binds albumin → ↓ ionized Ca → neuromuscular excitability
When you pick it
- Panic attack/post-op pain → hyperventilation
- Ionized Ca low but total Ca may be normal
- Symptoms are often transient and improve with rebreathing/controlling ventilation
Quick Table: Lab Patterns You Need Cold
| Condition | Ca | PO₄ | PTH | Key clue |
|---|---|---|---|---|
| Hypoparathyroidism | ↓ | ↑ | ↓ | Post-thyroidectomy, autoimmune |
| Pseudohypoparathyroidism | ↓ | ↑ | ↑ | Albright hereditary osteodystrophy |
| Vitamin D deficiency | ↓ | ↓/N | ↑ | Malabsorption, low sunlight |
| CKD (secondary HPT) | ↓/N | ↑ | ↑ | Low calcitriol, high PO₄ |
| Primary hyperparathyroidism | ↑ | ↓ | ↑ | “Stones, bones…” |
| Humoral hypercalcemia (PTHrP) | ↑ | ↓ | ↓ | Squamous cell, renal cell; weight loss |
Hypercalcemia Mini-Vignette (So You Don’t Miss the “Other Side”)
A 63-year-old man has constipation, polyuria, and confusion. Calcium is 12.8 mg/dL. PTH is low. Phosphate is low. He has a lung mass.
Most likely cause: PTHrP-mediated hypercalcemia of malignancy
- PTHrP mimics PTH (↑ Ca, ↓ PO₄) but suppresses native PTH.
- Most commonly:
- Squamous cell carcinoma (lung, head/neck)
- Also renal cell carcinoma, bladder, ovarian, etc.
High-yield differentiator
- Granulomatous disease/lymphoma hypercalcemia: high calcitriol (1,25-(OH)₂ D), often high phosphate, low PTH
- Think sarcoidosis or TB (macrophage 1α-hydroxylase).
Treatment Pearls (Step-Relevant, Not Step-Overkill)
Symptomatic hypocalcemia (tetany, seizures, arrhythmia)
- IV calcium gluconate (acute)
- Fix contributing causes (especially hypomagnesemia, which can impair PTH secretion)
Severe hypercalcemia
- IV normal saline (volume expansion) + calcitonin (rapid, short-term)
- IV bisphosphonate (slower onset, durable)
- Consider loop diuretic after volume repletion (promotes calciuresis)
- Treat the cause (malignancy, hyperPTH, vitamin D excess)
Q-Bank Habit That Pays Off: “Anchor + Contrast”
When you see a calcium vignette, force yourself to answer these in order:
- Symptoms: neuromuscular irritability (hypo) vs stones/psych/GI slowing (hyper)
- EKG: QT long (hypo) vs QT short (hyper)
- PTH: high vs low (primary driver or suppressed)
- Phosphate: helps distinguish PTH-driven vs vitamin D/calcitriol-driven etiologies
- Context clue: surgery, CKD, malignancy, granulomas, diuretics
Do that, and distractors stop being noise—they become alternate diagnoses you can actively rule in/out.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
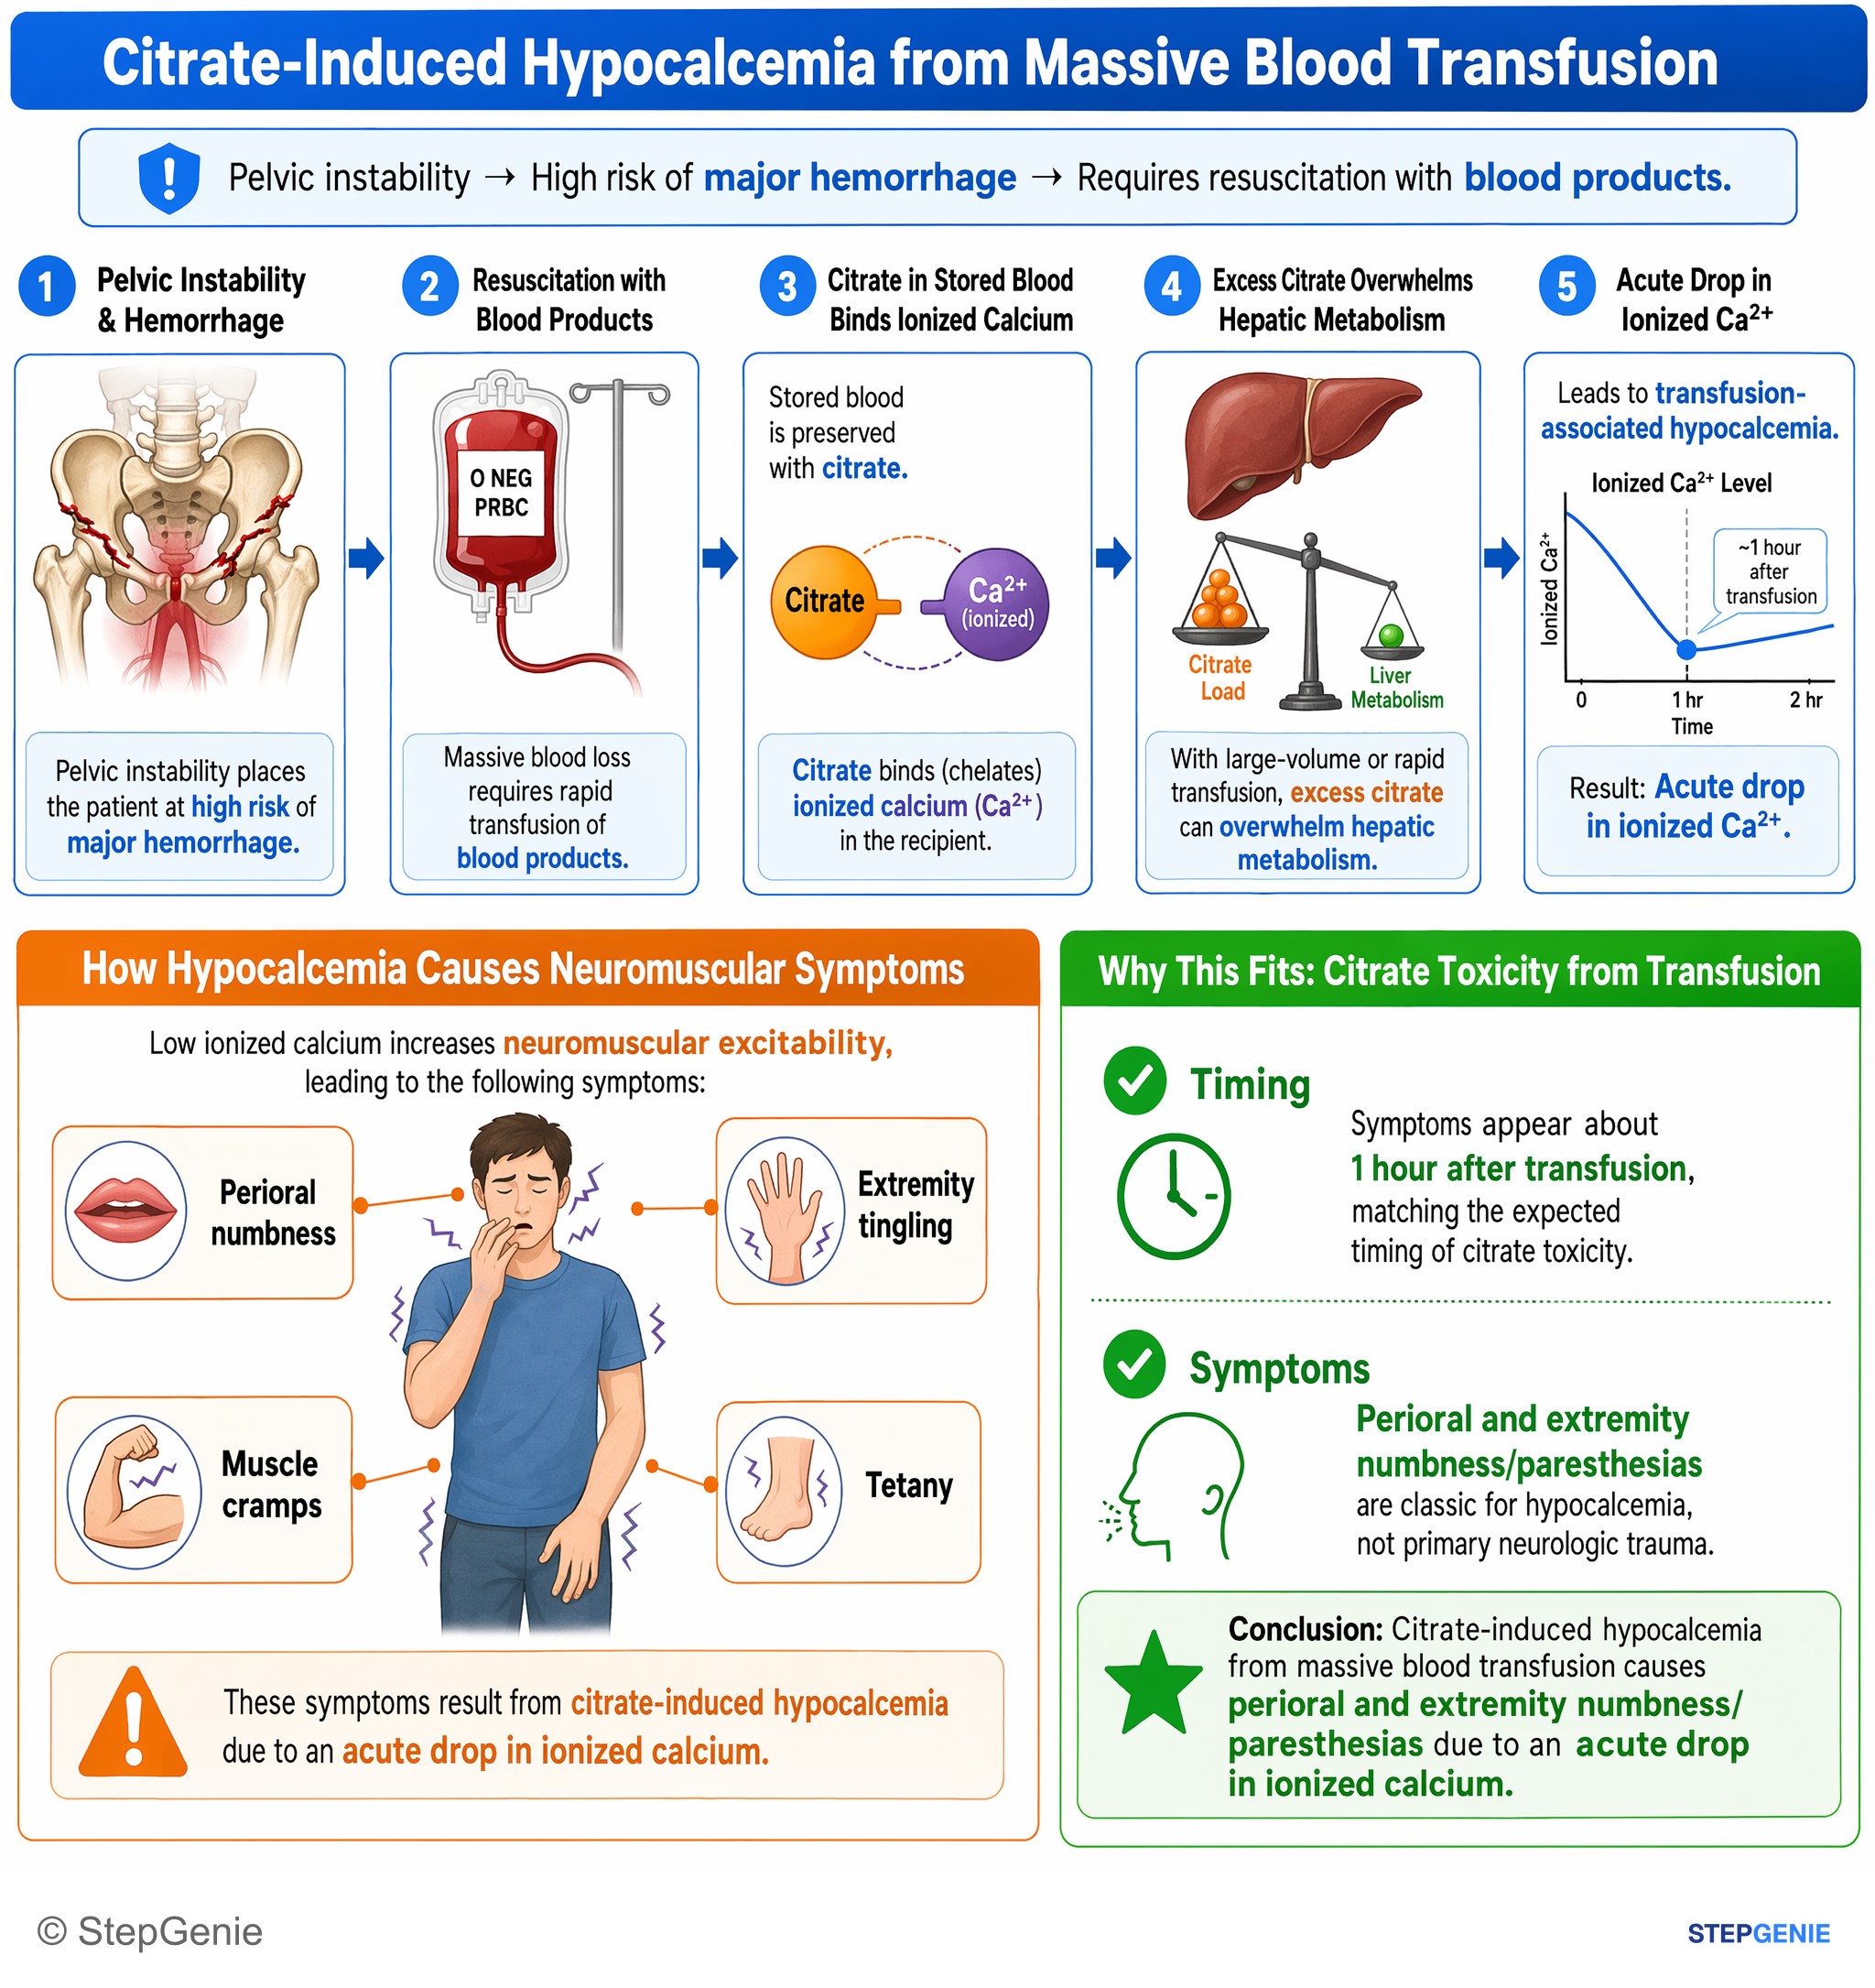
Citrate-induced hypocalcemia from massive blood transfusion causes perioral and extremity numbness/paresthesias due to acute drop in…
USMLE Step 2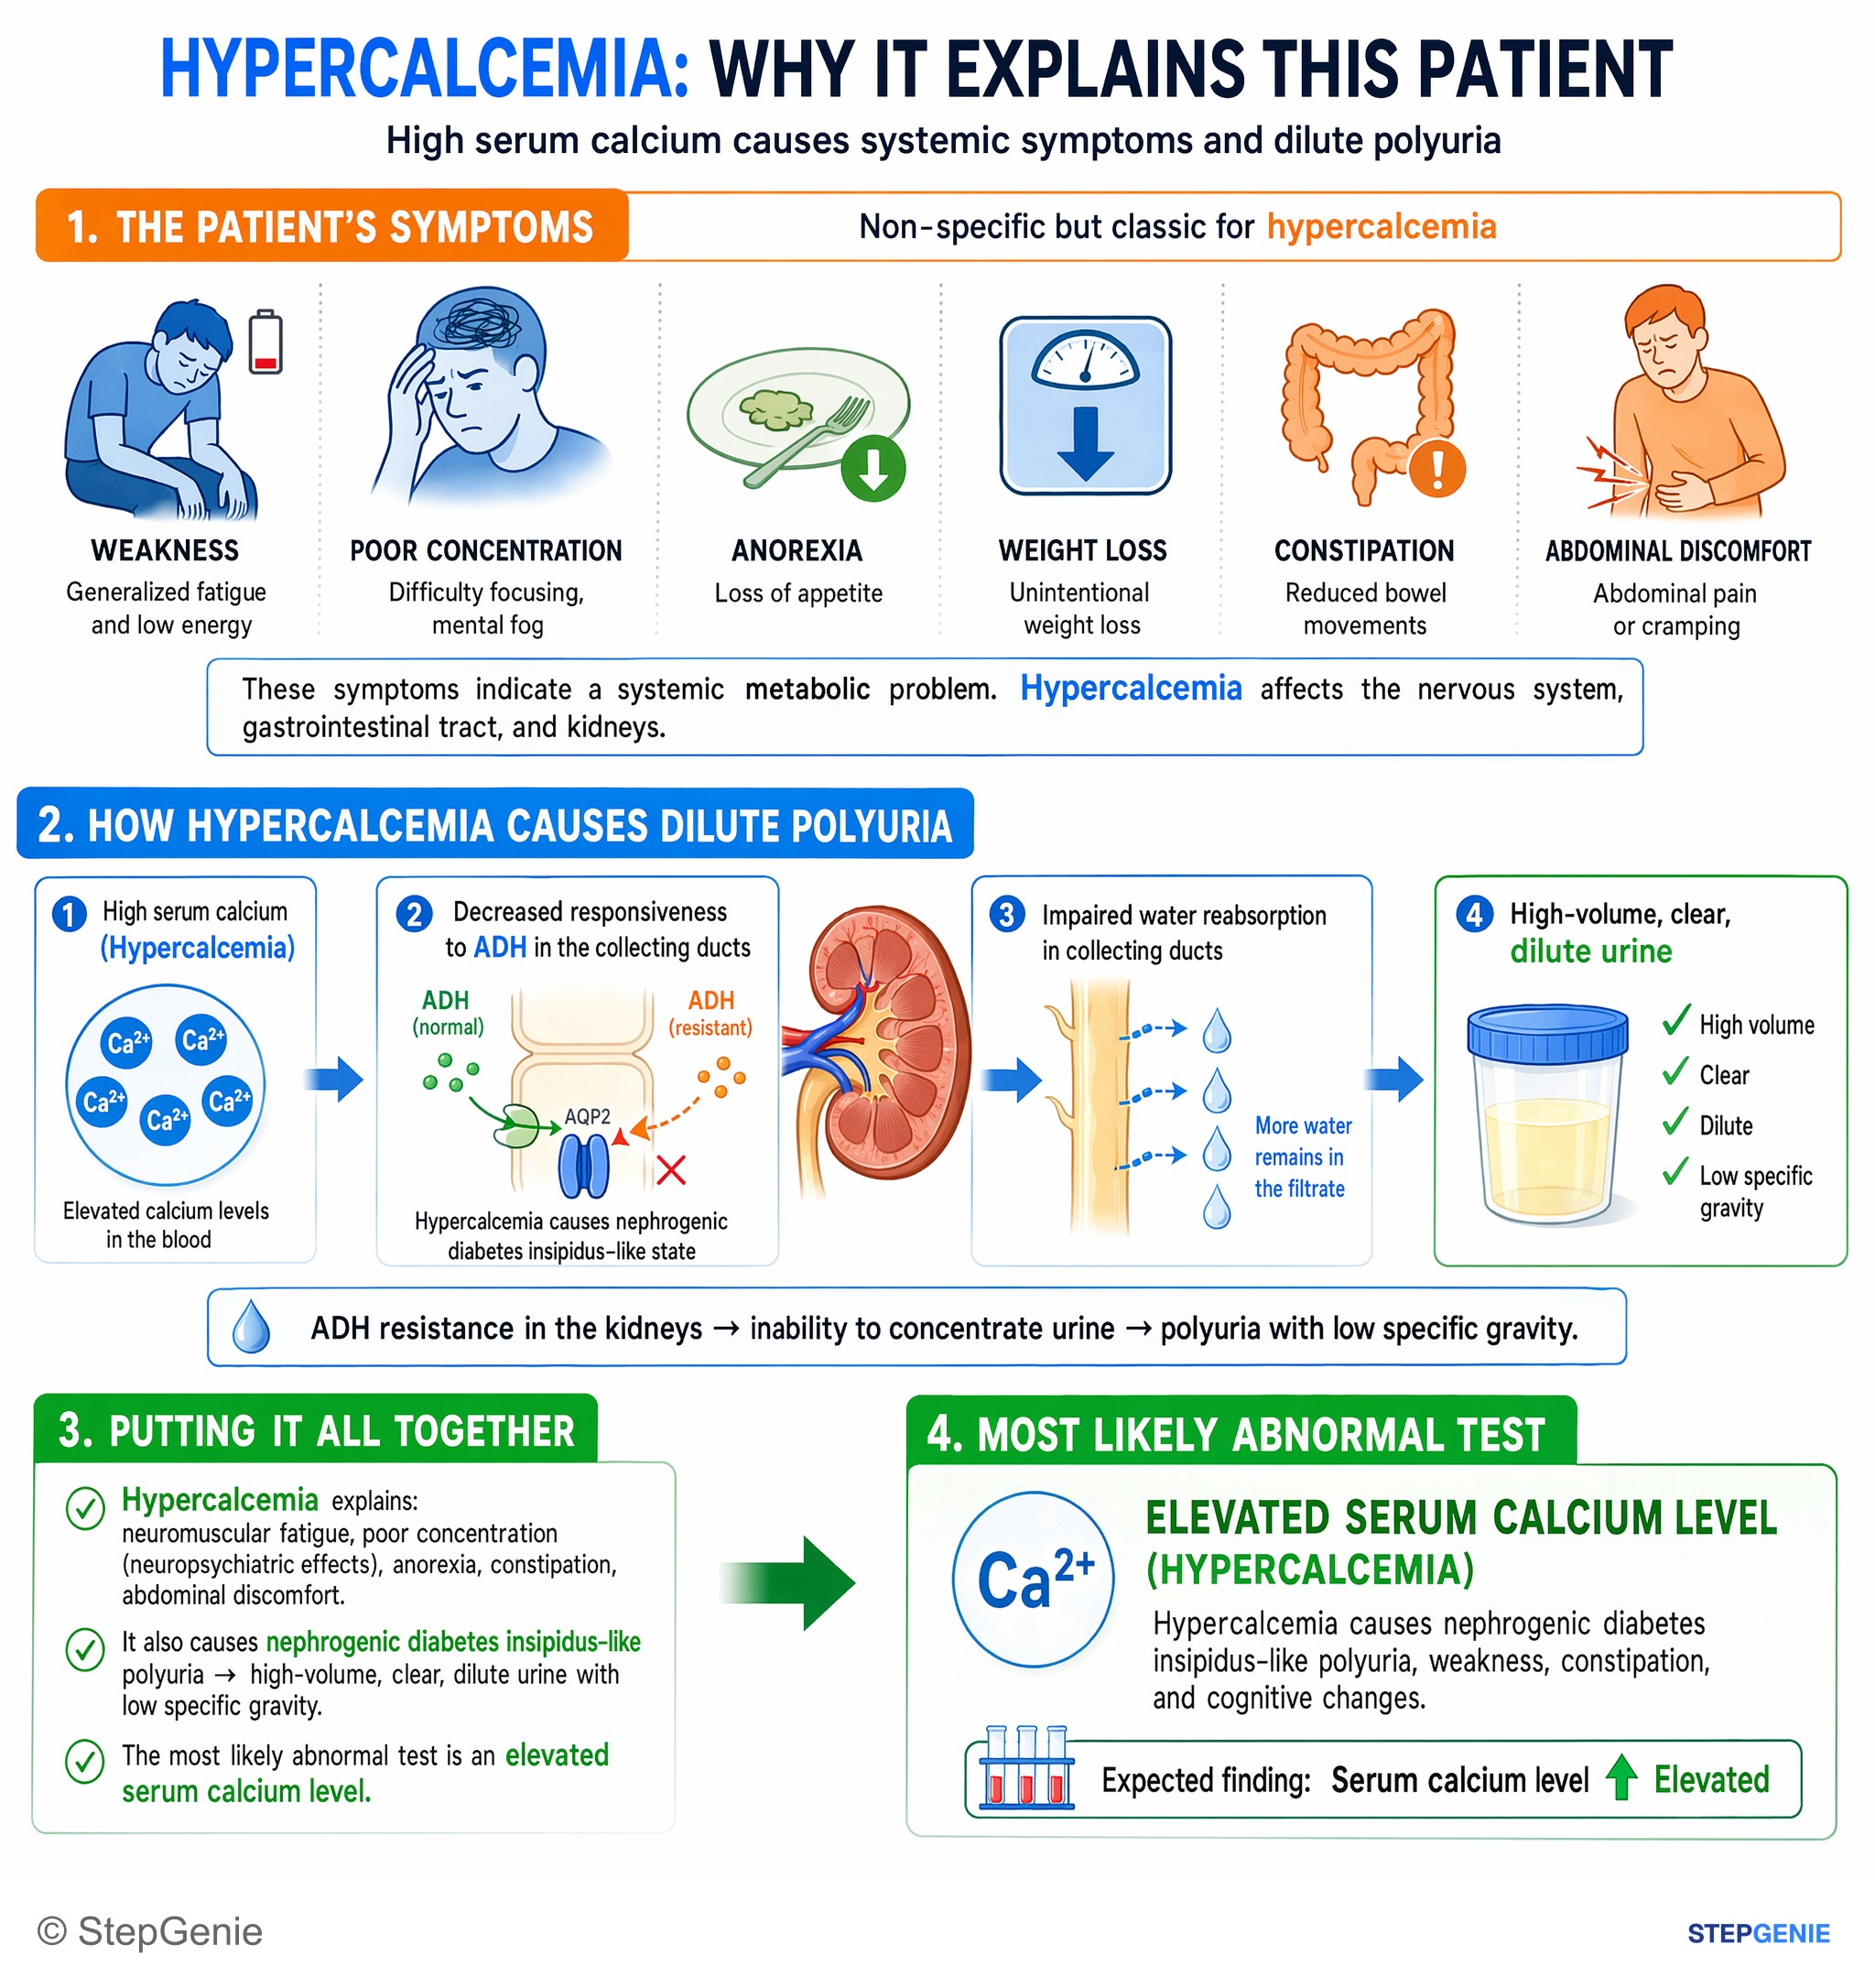
Hypercalcemia causes nephrogenic diabetes insipidus–like polyuria, weakness, constipation, and cognitive changes; serum calcium level will…
USMLE Step 1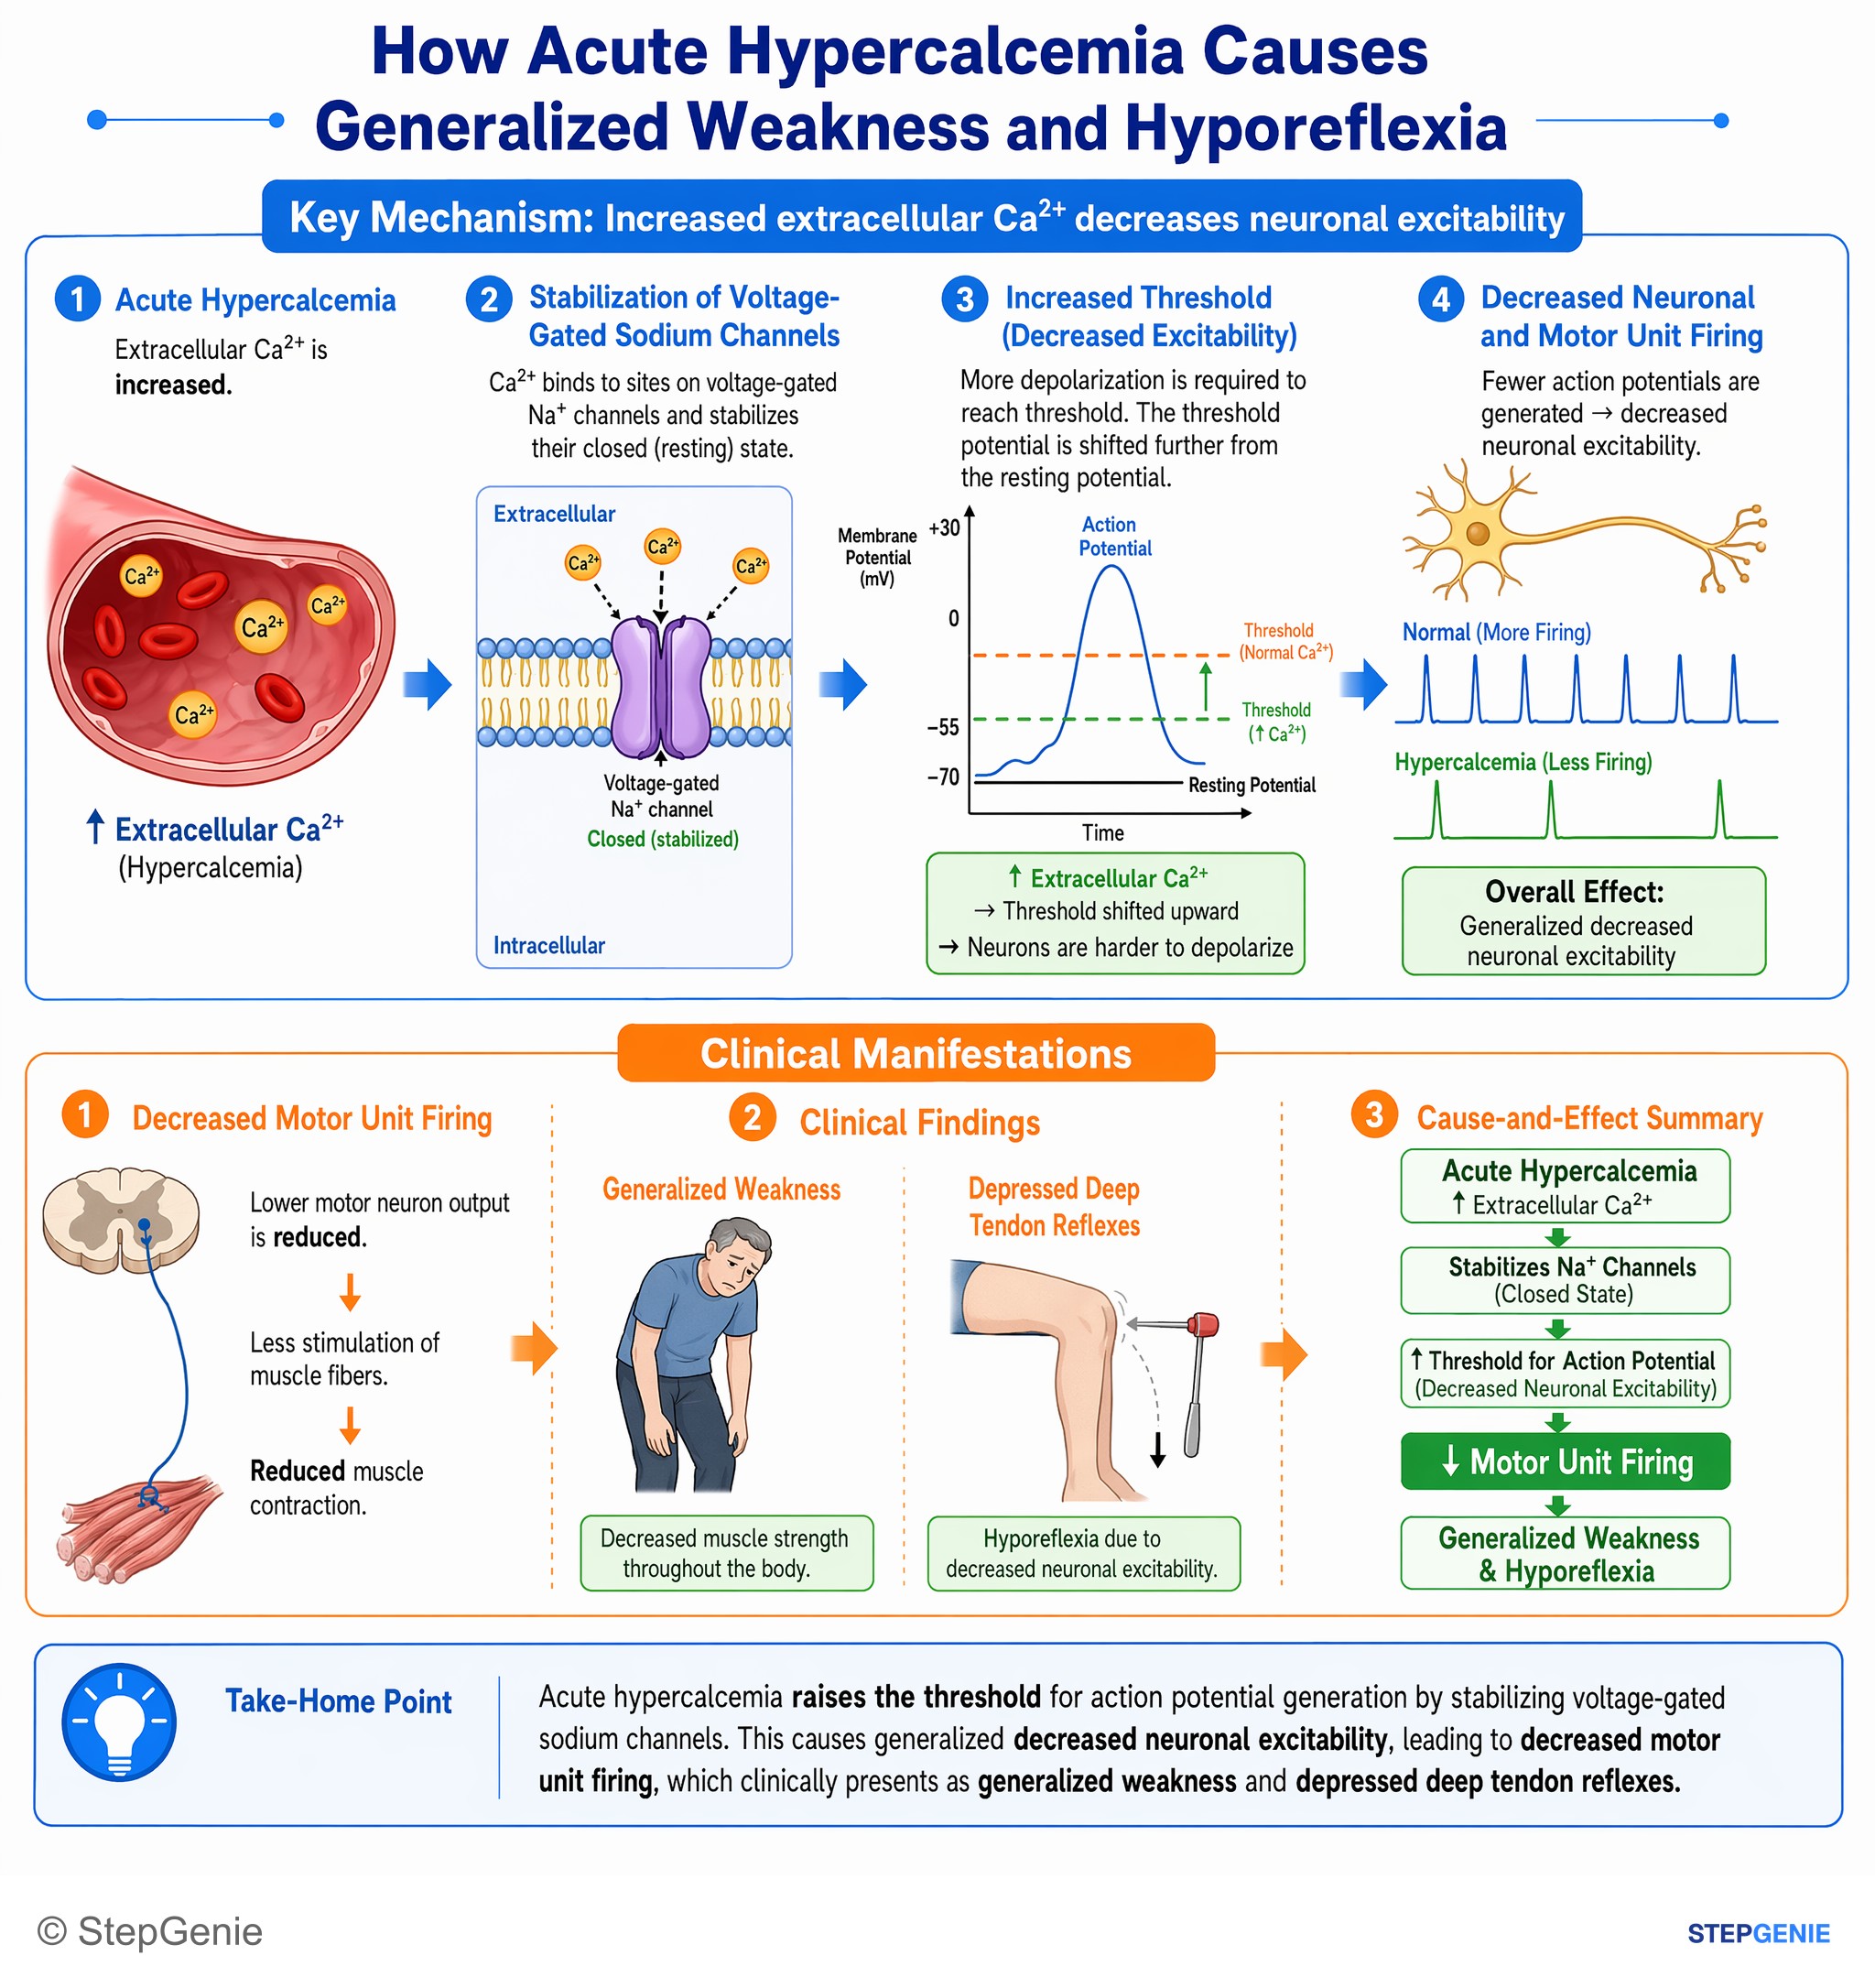
Acute hypercalcemia raises neuronal threshold, causing generalized weakness and hyporeflexia due to decreased neuronal excitability.
USMLE Step 1Frequently Asked Questions
Why does hypoparathyroidism after thyroidectomy cause low calcium and high phosphate?
It causes low calcium and high phosphate because loss of parathyroid function lowers PTH. Without PTH, the kidney reabsorbs less calcium, the kidney activates less vitamin D, and bone resorption decreases, all of which lower serum calcium. Phosphate rises because PTH normally promotes phosphate wasting in the proximal tubule, so absent PTH leads to phosphate retention.
How do you tell postoperative hypoparathyroidism from vitamin D deficiency in a hypocalcemia question?
The key distinction is the phosphate and PTH pattern. Postoperative hypoparathyroidism classically gives low calcium, high phosphate, and low PTH, especially after thyroid or parathyroid surgery. Vitamin D deficiency can also lower calcium, but it usually causes low or normal phosphate with high PTH from secondary hyperparathyroidism, because reduced gut calcium absorption stimulates PTH release.
Why can hyperventilation cause tingling and tetany even if total calcium is normal?
Hyperventilation can cause hypocalcemic symptoms because respiratory alkalosis increases calcium binding to albumin, which lowers ionized calcium. Ionized calcium is the biologically active form that nerves and muscles depend on, so patients can develop perioral numbness, tingling, and tetany even when total calcium is normal. This is a classic panic or acute hyperventilation presentation.
How do loop diuretics and thiazides affect calcium on exams?
Loop diuretics increase calcium excretion, while thiazides increase calcium reabsorption. Loops block NKCC2 in the thick ascending limb, abolishing the lumen-positive potential and decreasing paracellular calcium and magnesium reabsorption, so they can contribute to hypocalcemia and are used to treat hypercalcemia. Thiazides do the opposite for calcium and therefore increase hypercalcemia risk.
What EKG change helps distinguish hypocalcemia from hypercalcemia?
Hypocalcemia prolongs the QT interval, whereas hypercalcemia shortens it. This is a fast, testable clue that helps separate the two calcium disorders in a vignette. If a patient has tetany, perioral tingling, or carpopedal spasm with a prolonged QT, that supports hypocalcemia; a shortened QT points instead toward hypercalcemia.