Hypernatremia questions are rarely “just sodium.” On USMLE, they’re a stress test of whether you can connect water balance physiology to a vignette, interpret urine studies, and then defend your pick against very tempting distractors like osmotic diuresis, primary hyperaldosteronism, or cerebral salt wasting. Let’s walk through a classic diabetes insipidus (DI) Q-bank stem and—most importantly—why every answer choice matters.
The Vignette (Q-Bank Style)
A 27-year-old man is evaluated for intense thirst and polyuria for 2 weeks. He was recently started on lithium for bipolar disorder. He drinks water constantly but still wakes multiple times at night to urinate. Vitals are normal. Mucous membranes are dry.
Labs:
| Test | Value |
|---|---|
| Serum Na | 156 mEq/L |
| Serum osmolality | 310 mOsm/kg (high) |
| Urine specific gravity | 1.002 (very low) |
| Urine osmolality | 90 mOsm/kg (very low) |
| Glucose | Normal |
A desmopressin test is performed; urine osmolality rises to 110 mOsm/kg (minimal change).
Question: What is the most likely diagnosis / mechanism?
Stepwise Approach (How to Not Get Tricked)
Step 1: Recognize the core pattern
- Hypernatremia + high serum osmolality = not enough free water relative to sodium.
- Massively dilute urine (low urine osmolality, low specific gravity) = kidneys are dumping water when they shouldn’t.
- That combo screams: diabetes insipidus (central or nephrogenic) unless there’s an osmotic diuresis (which would have higher urine osmolality).
Step 2: Use desmopressin to classify DI
- Central DI = low ADH → desmopressin causes big rise in urine osmolality.
- Nephrogenic DI = kidney resistant to ADH → desmopressin causes little/no rise.
Here, urine osmolality barely changes (90 → 110), and the stem hands you lithium.
Correct Answer: Nephrogenic Diabetes Insipidus due to Lithium (ADH Resistance)
What’s happening physiologically?
ADH (vasopressin) normally binds V2 receptors on principal cells in the collecting duct → activates adenylate cyclase → increases cAMP → inserts aquaporin-2 channels into the apical membrane → water reabsorption.
Lithium enters principal cells via ENaC and disrupts signaling → decreased aquaporin-2 expression/insertion → impaired response to ADH → nephrogenic DI.
High-yield one-liners
- Central DI: “No ADH.” Fix with desmopressin.
- Nephrogenic DI: “No response to ADH.” Treat with thiazides, NSAIDs, and (if lithium-induced) amiloride.
- Desmopressin test is the classic differentiator:
- Central: urine osm ↑ >50%
- Nephrogenic: urine osm ↑ <10% (often minimal)
Management pearls you actually get asked
- Amiloride blocks ENaC, reducing lithium entry into principal cells → helps lithium-induced nephrogenic DI.
- Thiazides paradoxically reduce polyuria by causing mild volume depletion → ↑ proximal tubule Na/HO reabsorption → less water delivered distally.
- NSAIDs reduce prostaglandins that antagonize ADH action → improve concentrating ability.
Why the Distractors Are Wrong (and How They Trap You)
Below are common answer choices that show up in this exact vignette archetype.
Distractor 1: Central Diabetes Insipidus (Decreased ADH Secretion)
Why it’s tempting: You see hypernatremia + polyuria and think “DI → give desmopressin.”
Why it’s wrong here:
- Central DI should show a marked increase in urine osmolality after desmopressin.
- This patient has minimal response.
High-yield central DI associations
- Head trauma, neurosurgery
- Pituitary tumors
- Infiltrative disease (sarcoid, Langerhans cell histiocytosis)
Quick comparison
| Feature | Central DI | Nephrogenic DI |
|---|---|---|
| Problem | ↓ ADH | ADH resistance |
| Desmopressin response | Big rise in urine osm | Minimal/no rise |
| Common causes | Trauma, tumors, surgery | Lithium, demeclocycline, hyperCa, hypoK |
| Treatment | Desmopressin | Thiazides, NSAIDs, amiloride (lithium) |
Distractor 2: Primary Polydipsia (Psychogenic Polydipsia)
Why it’s tempting: Polyuria + psychiatric history.
Why it’s wrong here:
- Primary polydipsia typically leads to low or low-normal serum sodium (too much water intake).
- In primary polydipsia, serum osmolality is often low, not high.
- Urine may be dilute, but the serum profile doesn’t fit.
High-yield pearl:
If they give you hyponatremia + dilute urine + psychiatric disease → think primary polydipsia.
If they give you hypernatremia + dilute urine → think DI.
Distractor 3: Osmotic Diuresis from Hyperglycemia (e.g., Undiagnosed Diabetes Mellitus)
Why it’s tempting: Polyuria is a classic diabetes mellitus symptom.
Why it’s wrong here:
- Osmotic diuresis produces high urine osmolality (glucose drags water out).
- You’d expect glucosuria, elevated serum glucose, and often signs of volume depletion.
- This stem gives normal glucose and extremely low urine osmolality (90).
Test-taking shortcut:
Polyuria + high urine osmolality → osmotic diuresis (glucose, mannitol).
Polyuria + low urine osmolality → water diuresis (DI, polydipsia).
Distractor 4: Primary Hyperaldosteronism (Conn Syndrome)
Why it’s tempting: People associate aldosterone with sodium and think “hypernatremia = too much aldosterone.”
Why it’s wrong (important Step concept):
- Aldosterone increases Na reabsorption, but water follows → net effect is volume expansion, not dramatic hypernatremia.
- “Aldosterone causes hypernatremia” is usually not how the body presents because of thirst and ADH compensation.
- Instead, you see:
- Hypertension
- Hypokalemia
- Metabolic alkalosis
- Low renin (in primary)
If they wanted Conn: they’d give HTN + low K + alkalosis—not profoundly dilute urine.
Distractor 5: Cerebral Salt Wasting (CSW)
Why it’s tempting: Anything “brain-related” can make students think sodium problems.
Why it’s wrong here:
- CSW causes hyponatremia, not hypernatremia.
- It’s a renal loss of sodium + water (often after subarachnoid hemorrhage), leading to hypovolemia and high urine sodium.
Rule of thumb:
- SIADH: euvolemic/hypervolemic hyponatremia, concentrated urine
- CSW: hypovolemic hyponatremia, high urine sodium
- Neither causes hypernatremia with dilute urine.
Distractor 6: Syndrome of Inappropriate ADH (SIADH)
Why it’s tempting: Students know ADH and sodium are linked.
Why it’s wrong here:
- SIADH causes water retention → hyponatremia with inappropriately concentrated urine.
- Your patient has the opposite: hypernatremia with maximally dilute urine.
High-Yield Hypernatremia & DI Cheat Sheet
How hypernatremia happens (testable framework)
Hypernatremia is almost always free water loss or impaired water intake, not “too much sodium.”
Common buckets:
- Water loss via kidneys
- DI (central/nephrogenic)
- Osmotic diuresis (glucose, mannitol) → high urine osm
- Water loss outside kidneys
- Diarrhea, sweating, burns → urine becomes concentrated (ADH intact)
- Reduced intake
- Altered mental status, infants/elderly, lack of access to water
Key urine clues
| Condition | Serum Na | Urine Osm | Desmopressin response |
|---|---|---|---|
| Central DI | High | Low | Increases a lot |
| Nephrogenic DI | High | Low | Minimal change |
| Primary polydipsia | Low/normal | Low | Not the main test; water restriction increases urine osm |
| Osmotic diuresis | Normal/high | High | Not diagnostic |
Calculating free water deficit (Step 2-style)
Sometimes they ask how to correct it.
Free water deficit:
\text{Deficit} = \text{TBW} \times \left(\frac{$$\text{Na}^+$$_{\text{measured}}}{140} - 1\right)- TBW 0.6 × weight (kg) in men, 0.5 in women (varies with age/body fat)
Safety pearl: Correct chronic hypernatremia slowly to avoid cerebral edema (typical goal: 10–12 mEq/L per 24 hours).
Rapid-Fire Takeaways (What You Should Remember on Test Day)
- Hypernatremia + very dilute urine = DI until proven otherwise.
- Desmopressin response differentiates:
- big increase → central DI
- minimal increase → nephrogenic DI
- Lithium is a classic cause of nephrogenic DI; treat with amiloride (plus thiazides/NSAIDs).
- Osmotic diuresis has high urine osmolality (glucose, mannitol).
- Aldosterone problems cause HTN + hypokalemic metabolic alkalosis, not “pure hypernatremia with dilute urine.”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
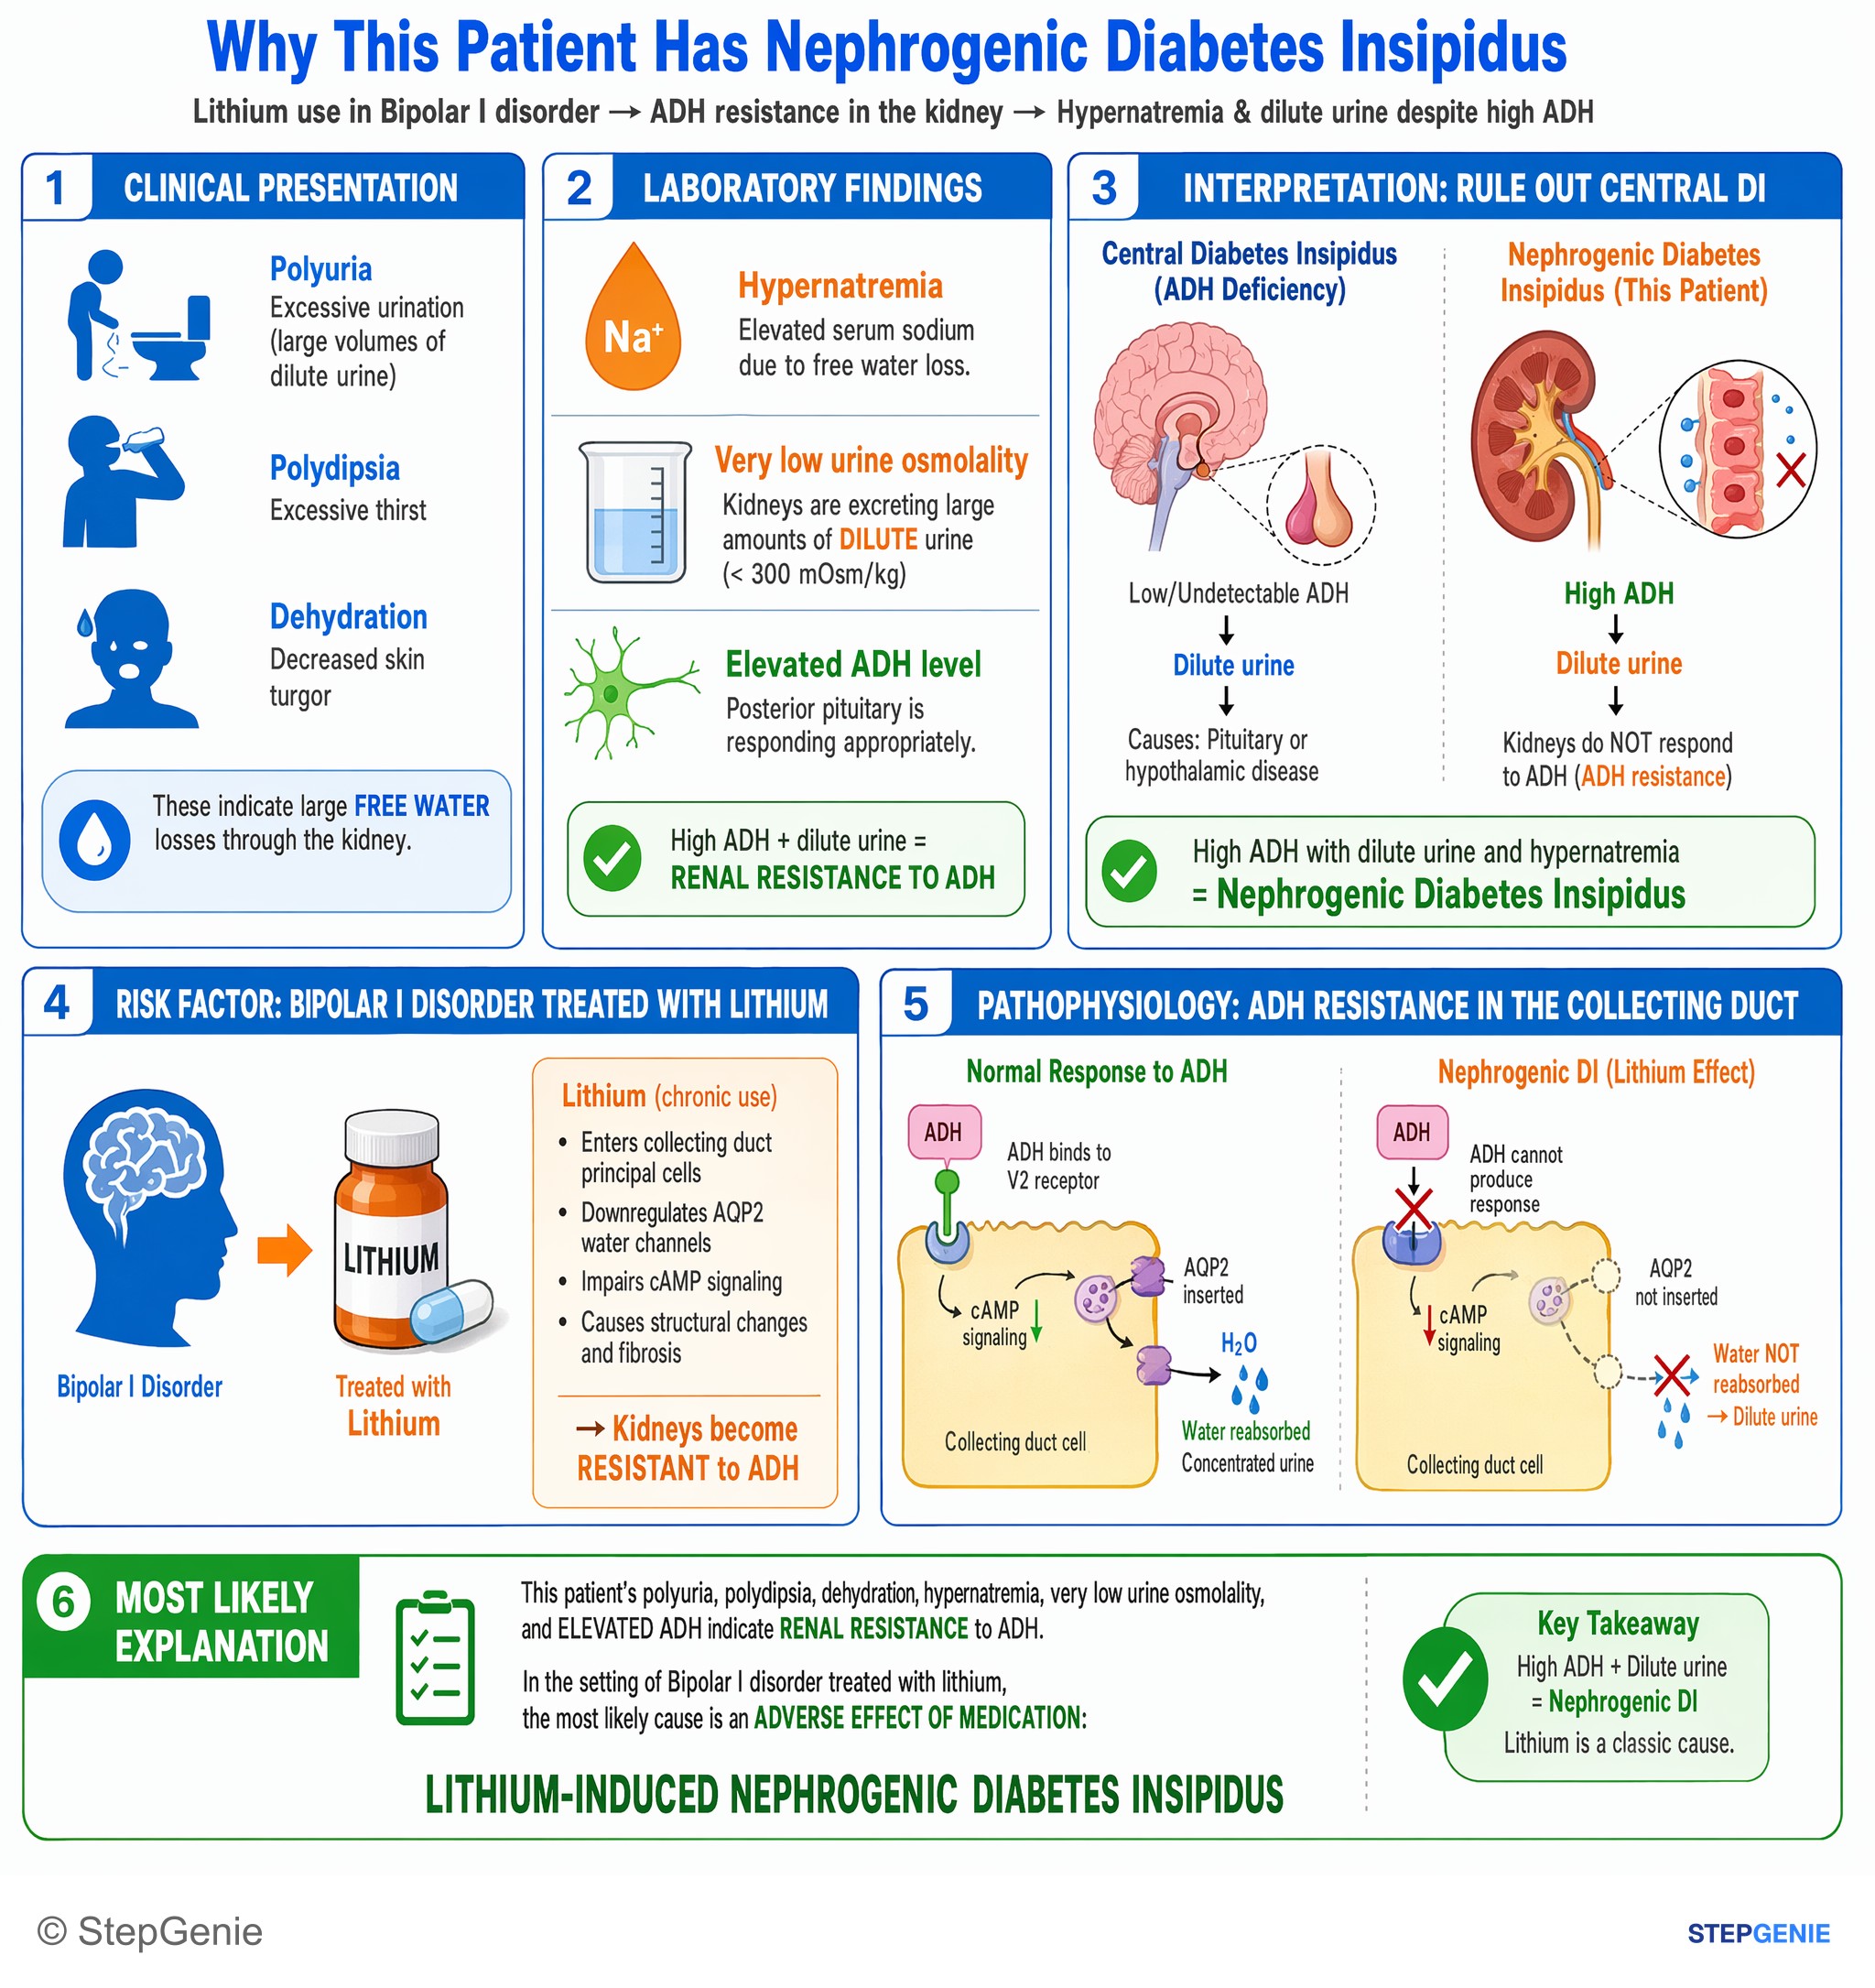
Nephrogenic diabetes insipidus from chronic lithium use in bipolar I: kidneys become ADH-resistant → hypernatremia + low urine osmolality…
USMLE Step 1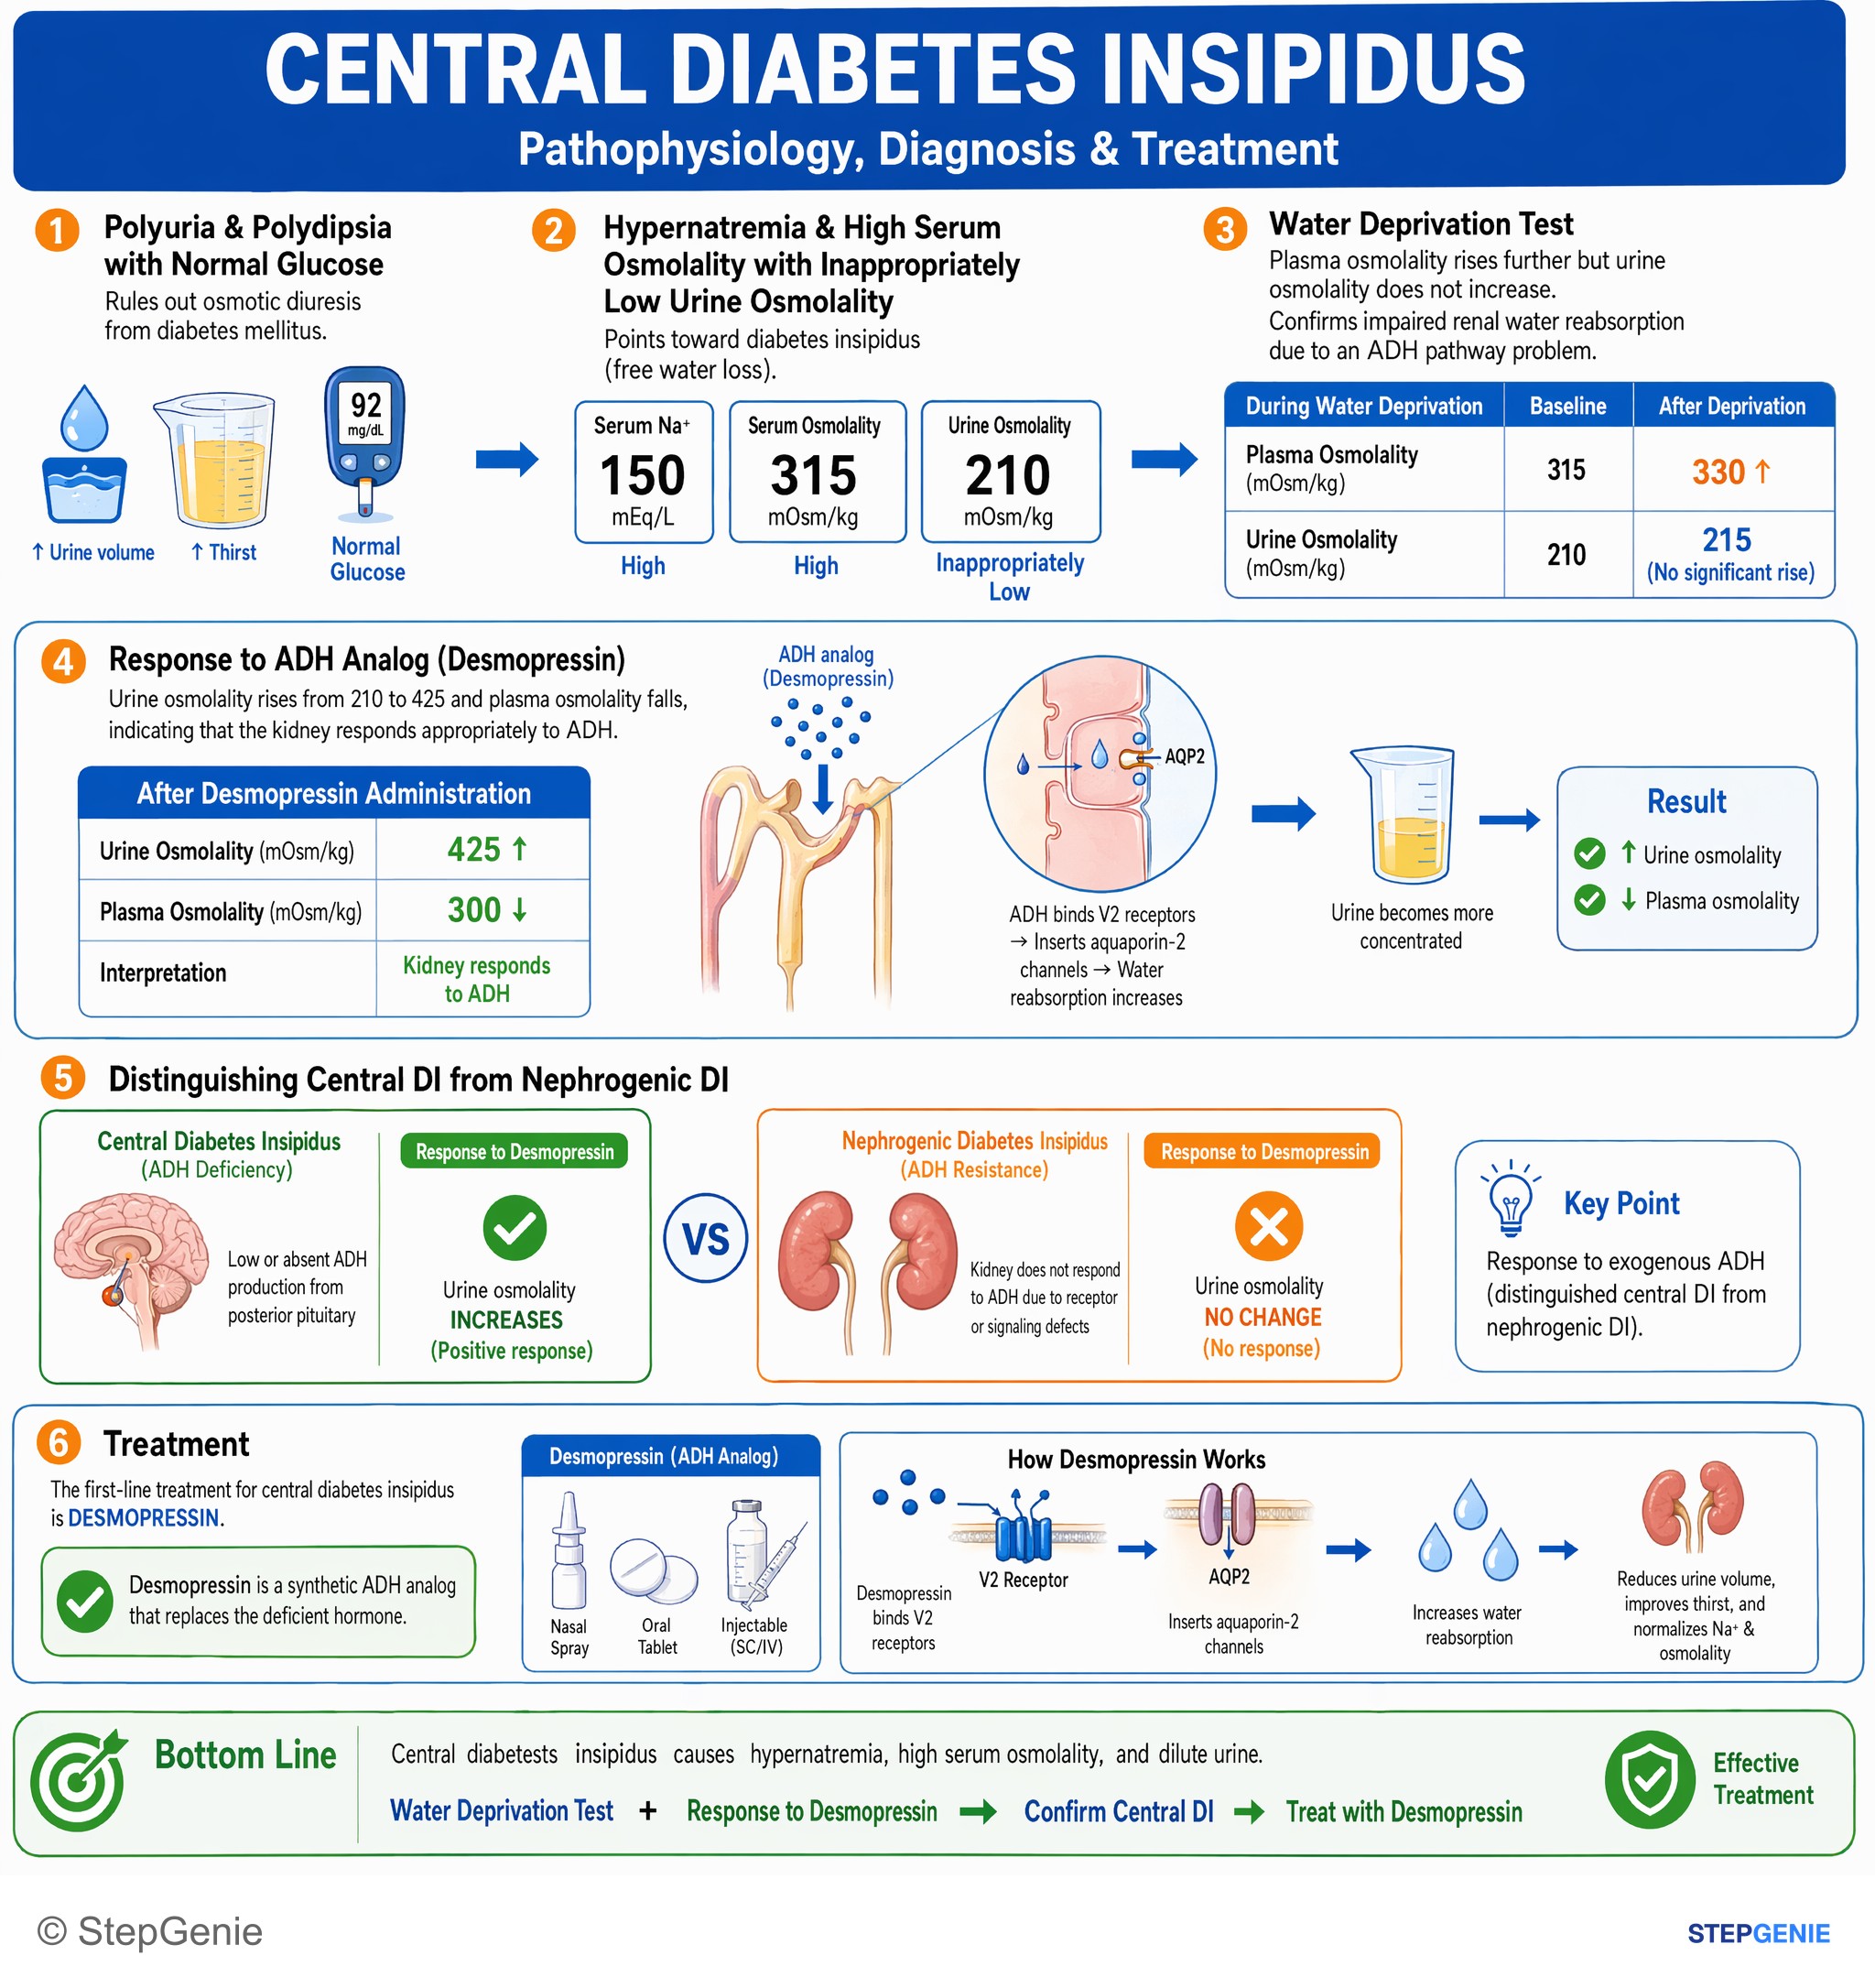
Central diabetes insipidus causes hypernatremia, high serum osmolality, dilute urine; water deprivation + response to ADH analog → treat…
USMLE Step 2Frequently Asked Questions
How do you tell nephrogenic diabetes insipidus from central diabetes insipidus on a desmopressin test?
You distinguish them by how much urine osmolality rises after desmopressin. Central diabetes insipidus is due to low ADH, so desmopressin causes a marked increase in urine osmolality, often more than 50%. Nephrogenic diabetes insipidus is due to renal resistance to ADH, so desmopressin causes little or no change, often less than 10%, as in the lithium case with only a minimal rise.
Why does lithium cause nephrogenic diabetes insipidus?
Lithium causes nephrogenic diabetes insipidus by making collecting duct principal cells resistant to ADH. Normally, ADH binds V2 receptors, activates adenylate cyclase, increases cAMP, and inserts aquaporin-2 channels so water can be reabsorbed. Lithium enters principal cells through ENaC and disrupts this signaling, decreasing aquaporin-2 expression and insertion, which prevents an appropriate water-reabsorbing response to ADH.
How do you tell diabetes insipidus from osmotic diuresis in a hypernatremia vignette?
The key distinction is urine osmolality. Diabetes insipidus causes a water diuresis, so the urine is very dilute with low urine osmolality and low specific gravity despite hypernatremia and high serum osmolality. Osmotic diuresis, such as from hyperglycemia, produces high urine osmolality because solutes like glucose pull water into the urine, and the vignette usually includes glucosuria or elevated serum glucose.
How do you tell primary polydipsia from diabetes insipidus on exams?
Primary polydipsia usually causes low or low-normal serum sodium and low serum osmolality because the patient is taking in too much water. Diabetes insipidus instead gives hypernatremia with high serum osmolality because the kidneys are losing free water inappropriately. Both can have dilute urine, so the serum profile is the important clue: hyponatremia suggests primary polydipsia, while hypernatremia suggests diabetes insipidus.
What is the treatment for lithium-induced nephrogenic diabetes insipidus?
Lithium-induced nephrogenic diabetes insipidus is treated with amiloride, thiazides, and NSAIDs. Amiloride is especially useful because it blocks ENaC, which reduces lithium entry into principal cells. Thiazides paradoxically reduce polyuria by causing mild volume depletion that increases proximal sodium and water reabsorption, so less water reaches the distal nephron. NSAIDs help by reducing prostaglandins that antagonize ADH action.