Loop diuretics are one of those Step essentials that show up everywhere—CHF, pulmonary edema, hypercalcemia, even nephrolithiasis vignettes. The trick is that furosemide is “simple” only until the exam starts asking mechanism + electrolytes + acid-base + toxicities all at once. Here’s a quick, shareable memory palace to lock it in.
The Memory Palace: “The Loop Water Park”
Picture a chaotic water park built around the Loop of Henle. You’re walking through it, and each attraction is a high-yield fact about furosemide.
1) The Gate: “NKCC2 Turnstile” (Site + MOA)
At the entrance to the park is a turnstile labeled:
Na⁺-K⁺-2Cl⁻ (NKCC2)
A lifeguard named Furo slaps a “CLOSED” sign on it.
- Site of action: Thick ascending limb (TAL) of Loop of Henle
- MOA: Inhibits NKCC2 → ↓ NaCl reabsorption
- Net effect: Big natriuresis/diuresis (“loops lose lots”)
One-liner: Furosemide blocks NKCC2 in the thick ascending limb, causing powerful salt and water loss.
2) The “Voltage VIP Lounge” (Why Ca²⁺ & Mg²⁺ get dumped)
Inside the park is a VIP lounge called “+ Lumen Voltage”. Normally, it’s powered by K⁺ recycling back into the lumen, making the lumen relatively positive—this pushes Ca²⁺ and Mg²⁺ paracellularly into blood.
But Furo cuts the power.
- Loop diuretics → ↓ NKCC2 activity → ↓ K⁺ recycling → ↓ lumen-positive potential
- Result: ↓ Ca²⁺ and ↓ Mg²⁺ reabsorption → increased urinary Ca²⁺ & Mg²⁺
High-yield hook for stones:
- Loops increase calciuria → can worsen calcium stones / contribute to stone risk in susceptible patients
- Thiazides decrease calciuria → used to prevent recurrent calcium stones
3) The “Osmotic Wave Pool” (Medullary gradient + concentrating ability)
Next you see a wave pool called “Medullary Gradient.” The TAL normally helps create the hypertonic medulla (countercurrent multiplier). Furo drains the pool.
- Loop diuretics blunt the medullary gradient → kidney becomes worse at concentrating urine
- Clinically: very effective diuresis, especially when you need to unload fluid fast
4) The “RAAS Roller Coaster” (Secondary electrolyte shifts)
You step onto a roller coaster named RAAS. It launches as soon as volume drops.
- ↓ Effective circulating volume → ↑ RAAS
- ↑ Aldosterone → ↑ ENaC activity in collecting duct → ↑ K⁺ and H⁺ secretion
Classic metabolic effect:
- Hypokalemic metabolic alkalosis
High-Yield Indications (What the lifeguard uses it for)
Think: “Fast fluid offload + calcium offload.”
- Acute pulmonary edema / CHF exacerbation
- Edema (HF, cirrhosis, nephrotic syndrome)
- Hypertension (less common long-term; useful with low GFR where thiazides underperform)
- Hypercalcemia (with IV fluids) → loop promotes calciuresis
Adverse Effects: “OHH DANG” in the Water Park
In the park gift shop there’s a souvenir shirt that says:
OHH DANG
- Ototoxicity
- Hypokalemia
- Hypomagnesemia
- Dehydration
- Allergy (sulfa; except ethacrynic acid)
- Nephritis (AIN)
- Gout (hyperuricemia)
Quick clinical connections
- Ototoxicity risk rises with:
- High doses, rapid IV infusion
- Aminoglycosides (synergy for ear toxicity)
- Hyperuricemia → gout:
- Volume depletion → ↑ urate reabsorption in proximal tubule
Exam-Grade Acid–Base + Electrolyte Summary
| Category | What furosemide does | Why |
|---|---|---|
| Na⁺ | ↓ reabsorption → ↑ urine Na⁺ | NKCC2 blocked |
| K⁺ | ↓ serum K⁺ | ↑ distal Na⁺ delivery + ↑ aldosterone → ↑ K⁺ secretion |
| H⁺ | Metabolic alkalosis | Aldosterone-driven H⁺ secretion + contraction alkalosis |
| Ca²⁺ | ↓ serum Ca²⁺ potential (↑ calciuria) | ↓ lumen-positive potential → ↓ paracellular Ca²⁺ reabsorption |
| Mg²⁺ | ↓ serum Mg²⁺ potential | Same mechanism as Ca²⁺ |
| Uric acid | ↑ (gout risk) | Volume depletion → ↑ proximal reabsorption |
Stones Tie-In (Renal Pharmacology & Stones)
On Step, stones love to hitchhike on pharm.
The key contrast
- Loop diuretics: ↑ urinary Ca²⁺ → may promote calcium stone formation
- Thiazides: ↓ urinary Ca²⁺ → used to prevent recurrent calcium oxalate stones (in hypercalciuria)
How it might be tested
- Patient with recurrent calcium stones is accidentally put on a loop → calciuria worsens
- Or: “Which diuretic is best for recurrent calcium stones?” → Thiazide, not loop
Quick “You’re in a hurry” Snapshot
- Where? Thick ascending limb
- What transporter? NKCC2
- What electrolytes drop? K⁺, Ca²⁺, Mg²⁺ (via urinary loss)
- Acid-base? Hypokalemic metabolic alkalosis
- Buzz toxicities? Ototoxicity + gout + sulfa allergy + AIN
Final One-Liner (Ultra-shareable)
Furosemide shuts down NKCC2 in the thick ascending limb → massive diuresis with hypokalemic metabolic alkalosis and increased urinary Ca²⁺/Mg²⁺ (ototoxic + gout risks).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
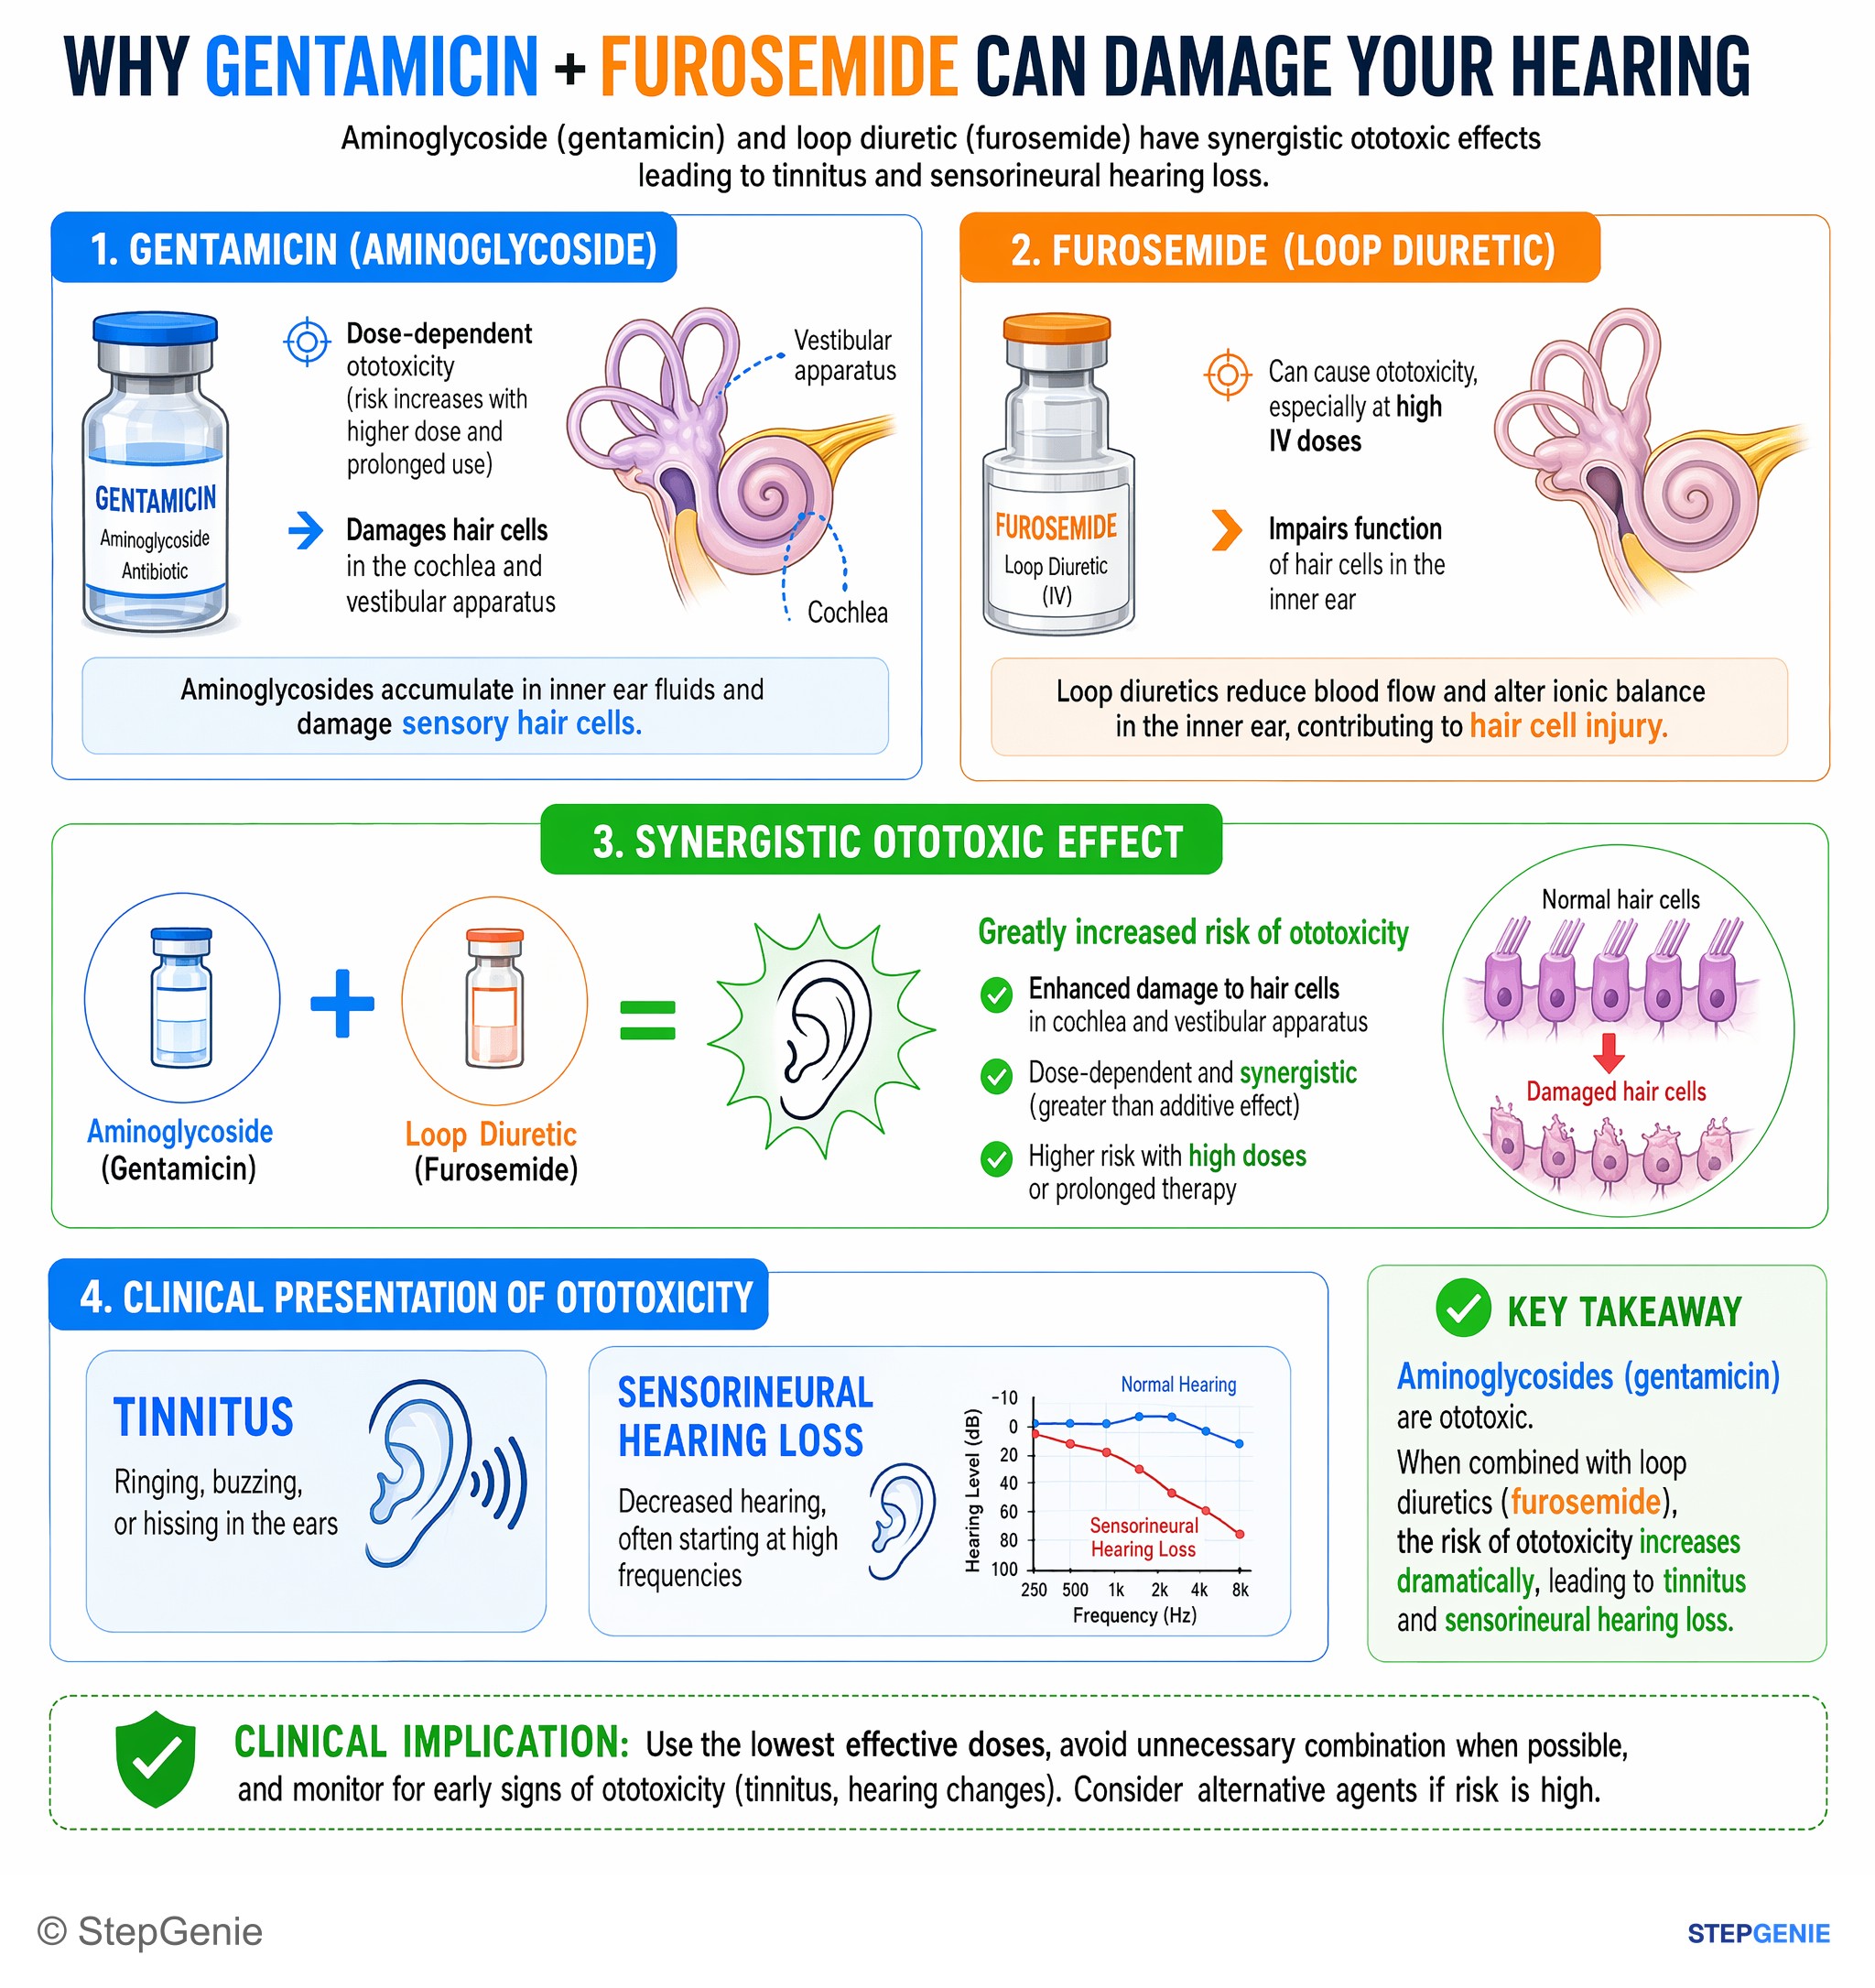
Aminoglycosides (gentamicin) are ototoxic, especially when combined with loop diuretics (furosemide), causing tinnitus and sensorineural…
USMLE Step 1Frequently Asked Questions
How does furosemide cause hypokalemic metabolic alkalosis?
Furosemide causes hypokalemic metabolic alkalosis by triggering volume loss that activates RAAS and aldosterone. Aldosterone increases ENaC activity in the collecting duct, which raises potassium and hydrogen ion secretion. The drug also increases distal sodium delivery, further promoting potassium loss. The result is the classic combination of low serum potassium and metabolic alkalosis.
Why do loop diuretics increase urinary calcium and magnesium?
Loop diuretics increase urinary calcium and magnesium because they reduce the lumen-positive potential in the thick ascending limb. By inhibiting NKCC2, furosemide decreases potassium recycling back into the tubular lumen. That weakens the positive voltage that normally drives paracellular calcium and magnesium reabsorption, so more of both ions are lost in the urine.
How do you tell loop diuretics from thiazides in calcium stone questions?
The key distinction is that loop diuretics increase calciuria, while thiazides decrease it. Furosemide can worsen calcium stone risk in susceptible patients because more calcium is excreted into the urine. Thiazides do the opposite and are used to prevent recurrent calcium stones, especially in patients with hypercalciuria. On exams, recurrent calcium stones point toward thiazides, not loops.
What are the classic high-yield adverse effects of furosemide?
The classic adverse effects of furosemide are ototoxicity, hypokalemia, hypomagnesemia, dehydration, sulfa allergy, acute interstitial nephritis, and gout. A useful memory aid is OHH DANG. Ototoxicity is more likely with high doses, rapid IV infusion, or concurrent aminoglycosides. Gout risk rises because volume depletion increases proximal urate reabsorption, leading to hyperuricemia.
Where does furosemide work, and what transporter does it block?
Furosemide works in the thick ascending limb of the loop of Henle and blocks the Na+-K+-2Cl- cotransporter, NKCC2. This reduces sodium chloride reabsorption and causes powerful natriuresis and diuresis. Because the thick ascending limb also helps build the medullary concentration gradient, blocking NKCC2 blunts urine-concentrating ability and makes the drug especially effective for rapid fluid removal.