Renal osteodystrophy is the bone disease of chronic kidney disease (CKD): failing kidneys retain phosphate and make too little calcitriol, calcium drifts down, and the parathyroid glands respond with secondary hyperparathyroidism. The classic labs are high phosphate, high PTH, low calcitriol and low or normal calcium, and FGF-23 typically rises first, before phosphate and PTH change. The bone lesion is osteitis fibrosa cystica when PTH is high (high turnover), adynamic bone disease when PTH is oversuppressed (low turnover), or osteomalacia when mineralization fails. The KDIGO 2017 CKD-MBD guideline treats it by lowering phosphate toward normal, avoiding hypercalcemia and keeping PTH at about 2 to 9 times the upper limit of normal on dialysis, with parathyroidectomy when drugs fail.
CKD-MBD vs renal osteodystrophy
KDIGO calls the whole syndrome CKD-mineral and bone disorder (CKD-MBD), a systemic disorder made of any combination of:
- Lab abnormalities of calcium, phosphate, PTH or vitamin D metabolism
- Bone abnormalities of turnover, mineralization, volume, linear growth or strength
- Vascular or other soft-tissue calcification
Renal osteodystrophy is strictly the bone piece: abnormal bone morphology in CKD, defined on bone biopsy by turnover, mineralization and volume. Vignettes use the two terms interchangeably. KDIGO recommends checking calcium, phosphate, PTH and alkaline phosphatase (ALP) from CKD G3a (eGFR 45–59) onward; the stage cutoffs are in the CKD stages by GFR mnemonic.
Pathophysiology: the chain to memorize
- FGF-23 rises first. Osteocytes secrete fibroblast growth factor 23 as nephrons are lost. Acting with its co-receptor Klotho, it makes the proximal tubule excrete phosphate and suppresses renal 1α-hydroxylase. It typically climbs before phosphate or PTH change, so phosphate stays normal early at the price of less calcitriol.
- Calcitriol falls. Less renal mass plus FGF-23 means less conversion of 25-hydroxyvitamin D to 1,25-dihydroxyvitamin D, so the gut absorbs less calcium.
- Phosphate rises late. Merck places overt hyperphosphatemia at a GFR below about 30 mL/min. Retained phosphate lowers ionized calcium and stimulates PTH directly.
- Secondary hyperparathyroidism. Low calcium, low calcitriol and high phosphate all push PTH up, and PTH can rise before calcium or phosphate is abnormal. Hyperplastic glands express fewer calcium-sensing receptors and respond poorly to vitamin D, so PTH keeps climbing.
- Tertiary hyperparathyroidism. After years of stimulation, nodular glands secrete PTH autonomously, regardless of serum calcium, and calcium rises. Classic stem: hypercalcemia with a very high PTH in long-standing dialysis, or persisting after a kidney transplant.
Step 1 link: PTH acts on osteoblasts through the PTH1 receptor (Gs, cAMP); they raise RANKL and lower osteoprotegerin, and RANKL activates osteoclasts. Persistently high PTH therefore means high bone turnover.
Lab patterns: renal osteodystrophy and its look-alikes
| Condition | Calcium | Phosphate | PTH | Tell |
|---|---|---|---|---|
| CKD with secondary HPT | Low or normal | High (late) | High | Low calcitriol; ALP high when turnover is high |
| Tertiary HPT | High | Variable | Very high, autonomous | Long-standing CKD or after transplant |
| Adynamic bone disease | Normal or high | Variable | Low for CKD | Low ALP; hypercalcemia with calcium loads |
| Primary HPT | High | Low | High | Normal kidneys; usually an adenoma |
| Vitamin D deficiency | Low or normal | Low | High | Low 25-hydroxyvitamin D; normal kidneys |
| Hypoparathyroidism | Low | High | Low | Neck surgery, autoimmune |
| Pseudohypoparathyroidism | Low | High | High | Normal GFR; PTH resistance (GNAS) |
How to read it: high phosphate with high PTH means CKD unless the GFR is normal, in which case think of pseudohypoparathyroidism. When calcium turns high in a dialysis patient, ask whether PTH is very high (tertiary) or low (adynamic bone plus a calcium load). In nutritional vitamin D deficiency the test is 25-hydroxyvitamin D, and phosphate is low, not high.
The three bone lesions
| Feature | Osteitis fibrosa cystica | Adynamic bone disease | Osteomalacia |
|---|---|---|---|
| Turnover | High | Low | Low |
| PTH | High to very high | Low for CKD | Variable |
| Cause | Uncontrolled secondary or tertiary HPT | Oversuppressed PTH: calcium loads, high-dose active vitamin D, calcimimetics, parathyroidectomy; also diabetes, peritoneal dialysis, older age | Failed mineralization: aluminum (historically), calcitriol deficiency |
| Histology | Active osteoclasts, marrow fibrosis, cysts, brown tumors | Few bone cells, no osteoid buildup | Excess unmineralized osteoid |
| Clues | Bone pain, high ALP, subperiosteal resorption | Hypercalcemia, fractures, vascular calcification | Bone pain, fractures; aluminum adds microcytic anemia and encephalopathy |
- Osteitis fibrosa cystica is the classic board answer, the lesion of secondary hyperparathyroidism. Mixed uremic osteodystrophy combines high turnover with a mineralization defect.
- Adynamic bone cannot take calcium into the skeleton, so calcium loads raise serum calcium and feed vascular calcification. The cinacalcet label warns it may develop if intact PTH is pushed below 100 pg/mL, and Merck notes that PTH is deliberately not corrected to normal in CKD for this reason. Management: stop calcium-based binders, lower dialysate calcium, and reduce or stop active vitamin D.
- Aluminum from old binders and contaminated dialysate caused osteomalacia (and adynamic bone), dementia and microcytic anemia; KDIGO recommends avoiding it.
- Bone biopsy is the definitive test for the lesion type, used only when the result would change treatment; markedly high or low PTH or bone-specific ALP already predicts turnover. Adult osteomalacia and rickets outside CKD are compared in osteoporosis vs osteomalacia vs rickets.
Clinical and imaging clues
- Symptoms: often silent for years, then bone and joint pain and fractures; children with CKD show slowed growth, short stature and leg deformities.
- Hands: subperiosteal resorption on the radial side of the middle phalanges of the index and middle fingers; the distal clavicles erode too.
- Skull and spine: a mottled "salt-and-pepper" skull, and rugger-jersey spine, with sclerotic bands along the vertebral endplates.
- Brown tumors: lytic, reparative (not neoplastic) lesions of osteoclast-like giant cells, fibrous tissue and hemorrhage; hemosiderin makes them brown.
- Vascular calcification: Merck links it to a calcium-phosphate product that stays above about 55 mg²/dL², and it drives stroke, MI and claudication; KDIGO now suggests judging calcium and phosphate individually rather than by their product.
- Calciphylaxis (calcific uremic arteriolopathy): calcified, thrombosed small vessels cause exquisitely painful purple mottling that ulcerates and turns black, usually on the legs. Risk factors include dialysis, female sex, obesity, diabetes, warfarin, high PTH and high phosphate. Mortality is high, mostly from infection and sepsis.
Treatment: KDIGO 2017 step by step
- Lower phosphate toward normal (2C): dietary phosphate restriction (Merck: 0.8–1 g a day), binders taken with meals, and more dialytic removal if it persists. Treat progressive or persistent hyperphosphatemia rather than giving binders to prevent it, and base decisions on trends in calcium, phosphate and PTH together, not on one value.
- Avoid hypercalcemia (2C) and restrict calcium-based binders (2B). Mild, asymptomatic hypocalcemia, for example on a calcimimetic, can be tolerated to avoid calcium loading.
- Correct 25-hydroxyvitamin D deficiency with cholecalciferol or ergocalciferol.
- Not on dialysis: don't use calcitriol or vitamin D analogs routinely (2C); reserve them for CKD G4–G5 with severe, progressive hyperparathyroidism. In the PRIMO and OPERA trials, paricalcitol raised the risk of hypercalcemia without improving surrogate cardiac end points.
- On dialysis: keep intact PTH at about 2–9 times the upper limit of normal (2C). If it needs lowering, use a calcimimetic, calcitriol or a vitamin D analog, or a calcimimetic plus one of them (2B).
- Parathyroidectomy for severe hyperparathyroidism that fails medical therapy (2B), and for tertiary disease: subtotal, or total with a fragment reimplanted, often in the forearm.
- Avoid aluminum binders long term and aluminum-contaminated dialysate (1C).
| Drug | How it works | Exam point |
|---|---|---|
| Calcium acetate, calcium carbonate | Calcium-based phosphate binders | Calcium loading: hypercalcemia and vascular calcification, so KDIGO limits the dose |
| Sevelamer, lanthanum carbonate | Calcium-free binders | Preferred with hypercalcemia, suspected adynamic bone or vascular calcification |
| Ferric citrate, sucroferric oxyhydroxide | Iron-based binders | Also supply iron, which many dialysis patients need |
| Aluminum hydroxide | Binder | Avoid long term: osteomalacia, dementia, microcytic anemia |
| Tenapanor | Gut NHE3 inhibitor; cuts paracellular phosphate absorption | Add-on on dialysis when binders fail or are not tolerated; diarrhea |
| Calcitriol, paricalcitol | Active vitamin D, vitamin D receptor activators | Suppress PTH but raise calcium and phosphate absorption |
| Cinacalcet (oral), etelcalcetide (IV after hemodialysis) | Calcimimetics: sensitize the parathyroid calcium-sensing receptor | Lower PTH and calcium; in CKD, labeled only for dialysis patients; hypocalcemia, QT prolongation |
Dialysis itself removes phosphate but rarely enough on its own; when to start it is covered in dialysis indications.
Practice question
Vignette. A 58-year-old man with diabetic kidney disease has been on hemodialysis for 7 years and has aching pain in his hips and lower back. He takes calcium acetate with meals and follows a low-phosphate diet. Calcium is 10.4 mg/dL (reference 8.5–10.2), phosphate 6.8 mg/dL, intact PTH 1,050 pg/mL (upper limit 65), ALP is high and 25-hydroxyvitamin D is 36 ng/mL. Hand radiographs show subperiosteal resorption along the radial margins of the middle phalanges. Calcium acetate is switched to sevelamer. Which is the most appropriate additional treatment?
- A. Aluminum hydroxide
- B. Calcitriol
- C. Cinacalcet
- D. Denosumab
- E. Ergocalciferol
- F. Parathyroidectomy
Answer: C, cinacalcet. PTH is about 16 times the upper limit, far above the KDIGO dialysis range of about 2 to 9 times, and the films show high-turnover osteitis fibrosa. A calcimimetic lowers PTH while lowering, not raising, calcium, which suits a patient whose calcium and phosphate are already high. Monitor for hypocalcemia and QT prolongation.
Why not the others?
- Aluminum hydroxide: binds phosphate well, but long-term aluminum causes osteomalacia, dementia and microcytic anemia; KDIGO recommends avoiding it.
- Calcitriol: suppresses PTH directly but increases gut absorption of calcium and phosphate, worsening both. It is a better fit when calcium and phosphate are not high.
- Denosumab: blocks RANKL but does not lower PTH, and its label carries a boxed warning for severe, sometimes fatal hypocalcemia in advanced CKD, especially with CKD-MBD.
- Ergocalciferol: corrects 25-hydroxyvitamin D deficiency, which he does not have.
- Parathyroidectomy: KDIGO suggests it for severe hyperparathyroidism that fails medical therapy, and Merck considers dialysis patients with refractory hyperparathyroidism and an intact PTH above 800 pg/mL candidates for subtotal parathyroidectomy. He has not yet had a calcimimetic or vitamin D analog, and his mild hypercalcemia developed on a calcium-based binder, so this is not yet refractory or proven autonomous (tertiary) disease. Surgery becomes the answer for refractory or tertiary disease, such as hypercalcemia with a high PTH that persists after a transplant.
Variant to know: a dialysis patient on calcium acetate and high-dose calcitriol develops hypercalcemia and a hip fracture, with an intact PTH of 80 pg/mL and a low ALP. That is adynamic bone disease: stop the calcium binder, lower dialysate calcium and cut back the vitamin D.
Key takeaways
- Renal osteodystrophy is the bone part of CKD-MBD; CKD-MBD adds the lab abnormalities and vascular calcification.
- Sequence: FGF-23 up first → calcitriol down → PTH up → phosphate up once GFR is below about 30 → calcium low or normal.
- Three lesions: osteitis fibrosa cystica (high PTH, high turnover), adynamic bone (oversuppressed PTH, low turnover, hypercalcemia) and osteomalacia (unmineralized osteoid; aluminum).
- Tertiary HPT: autonomous PTH with hypercalcemia after long-standing CKD or a transplant; usually surgical.
- KDIGO 2017: phosphate toward normal, avoid hypercalcemia, limit calcium binders, PTH about 2–9 times normal on dialysis, calcimimetic or active vitamin D when needed, parathyroidectomy if refractory, no aluminum.
- Imaging: radial-sided subperiosteal resorption of the middle phalanges, salt-and-pepper skull, rugger-jersey spine, brown tumors.
Sources
- KDIGO 2017 Clinical Practice Guideline Update for CKD-MBD: Executive Summary — KDIGO (2017)
- KDIGO Clinical Practice Guideline for CKD-MBD, with definitions of CKD-MBD and renal osteodystrophy — KDIGO (2009)
- Chronic Kidney Disease — Merck Manual Professional Edition (2026)
- Hyperphosphatemia — Merck Manual Professional Edition (2025)
- Hypercalcemia — Merck Manual Professional Edition (2025)
- Mineral & Bone Disorder in Chronic Kidney Disease — NIDDK
- Chronic Kidney Disease–Mineral and Bone Disorder (CKD-MBD): Current Perspectives — International Journal of Nephrology and Renovascular Disease (2019)
- Adynamic bone disease: bone and beyond — NDT Plus, Oxford Academic (2008)
- Advances in the treatment of secondary and tertiary hyperparathyroidism — Frontiers in Endocrinology (2022)
- Sensipar (cinacalcet) prescribing information — DailyMed
- Xphozah (tenapanor) prescribing information — DailyMed
- Prolia (denosumab) prescribing information, boxed warning — DailyMed
- Renal osteodystrophy — Radiopaedia
- Brown tumour — Radiopaedia
- Calciphylaxis — DermNet
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
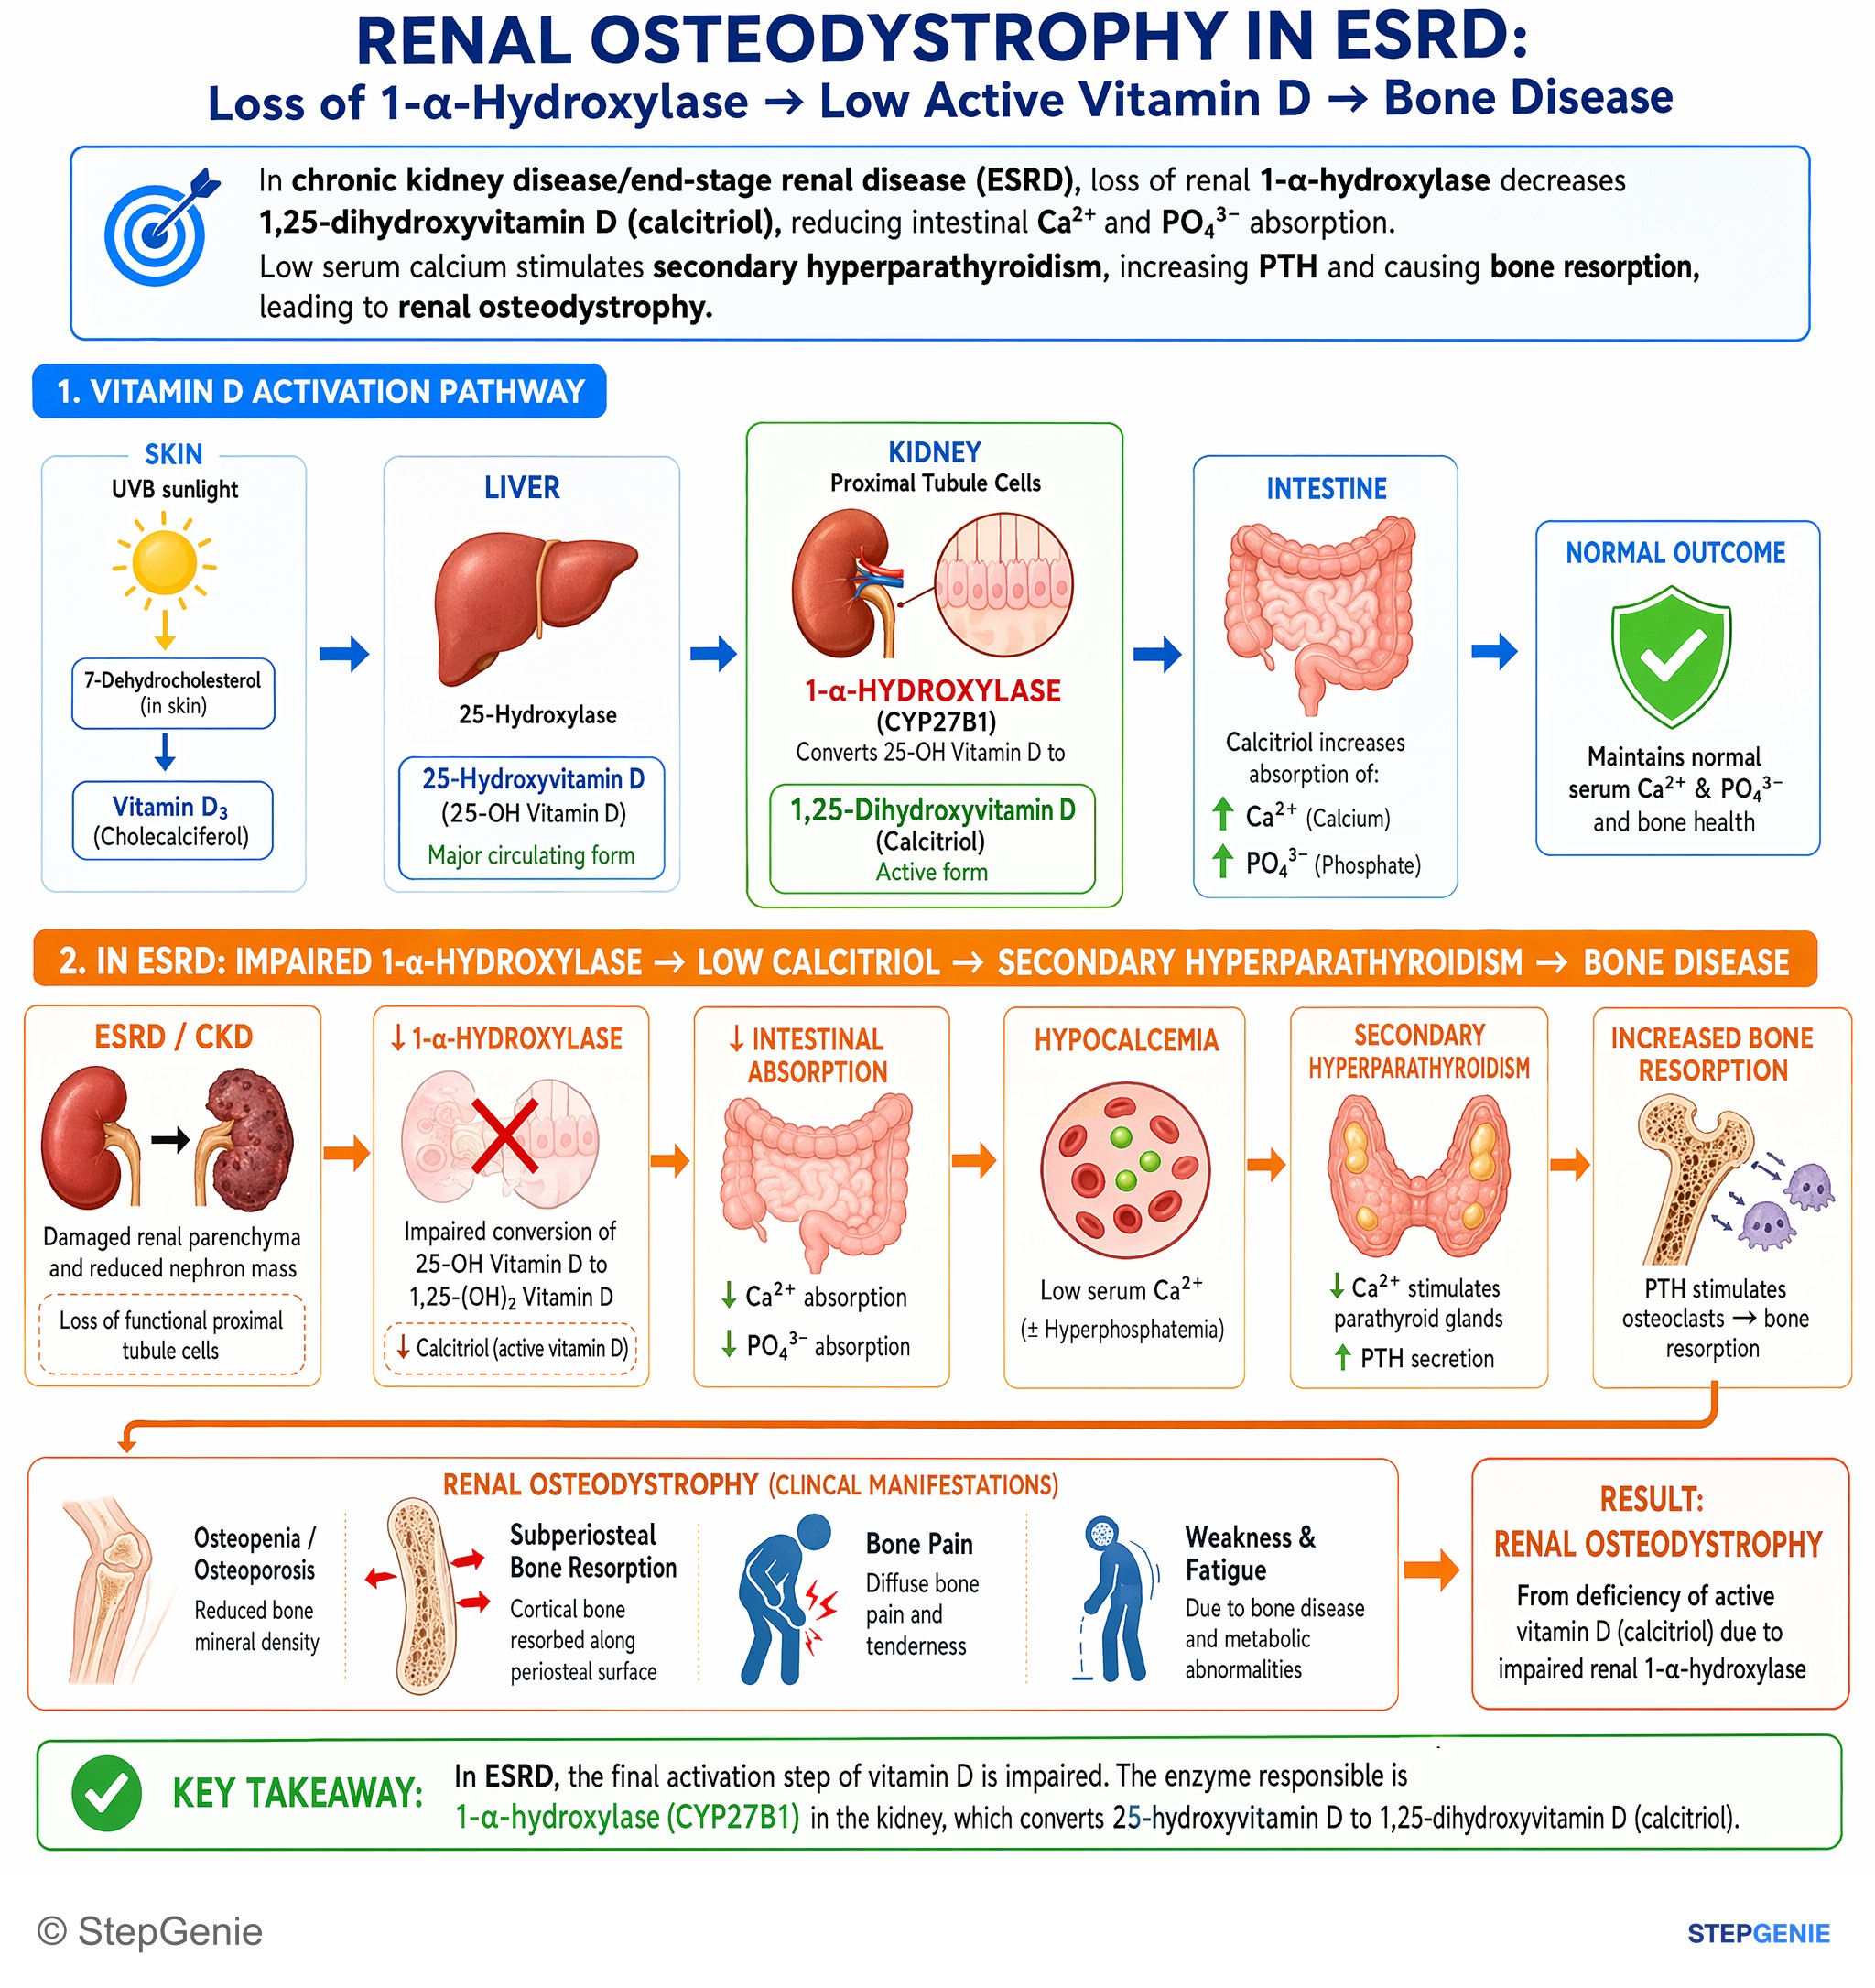
Renal osteodystrophy from ESRD causes deficiency of active vitamin D; final activation step is renal 1-α-hydroxylase converting 25-OH to…
USMLE Step 1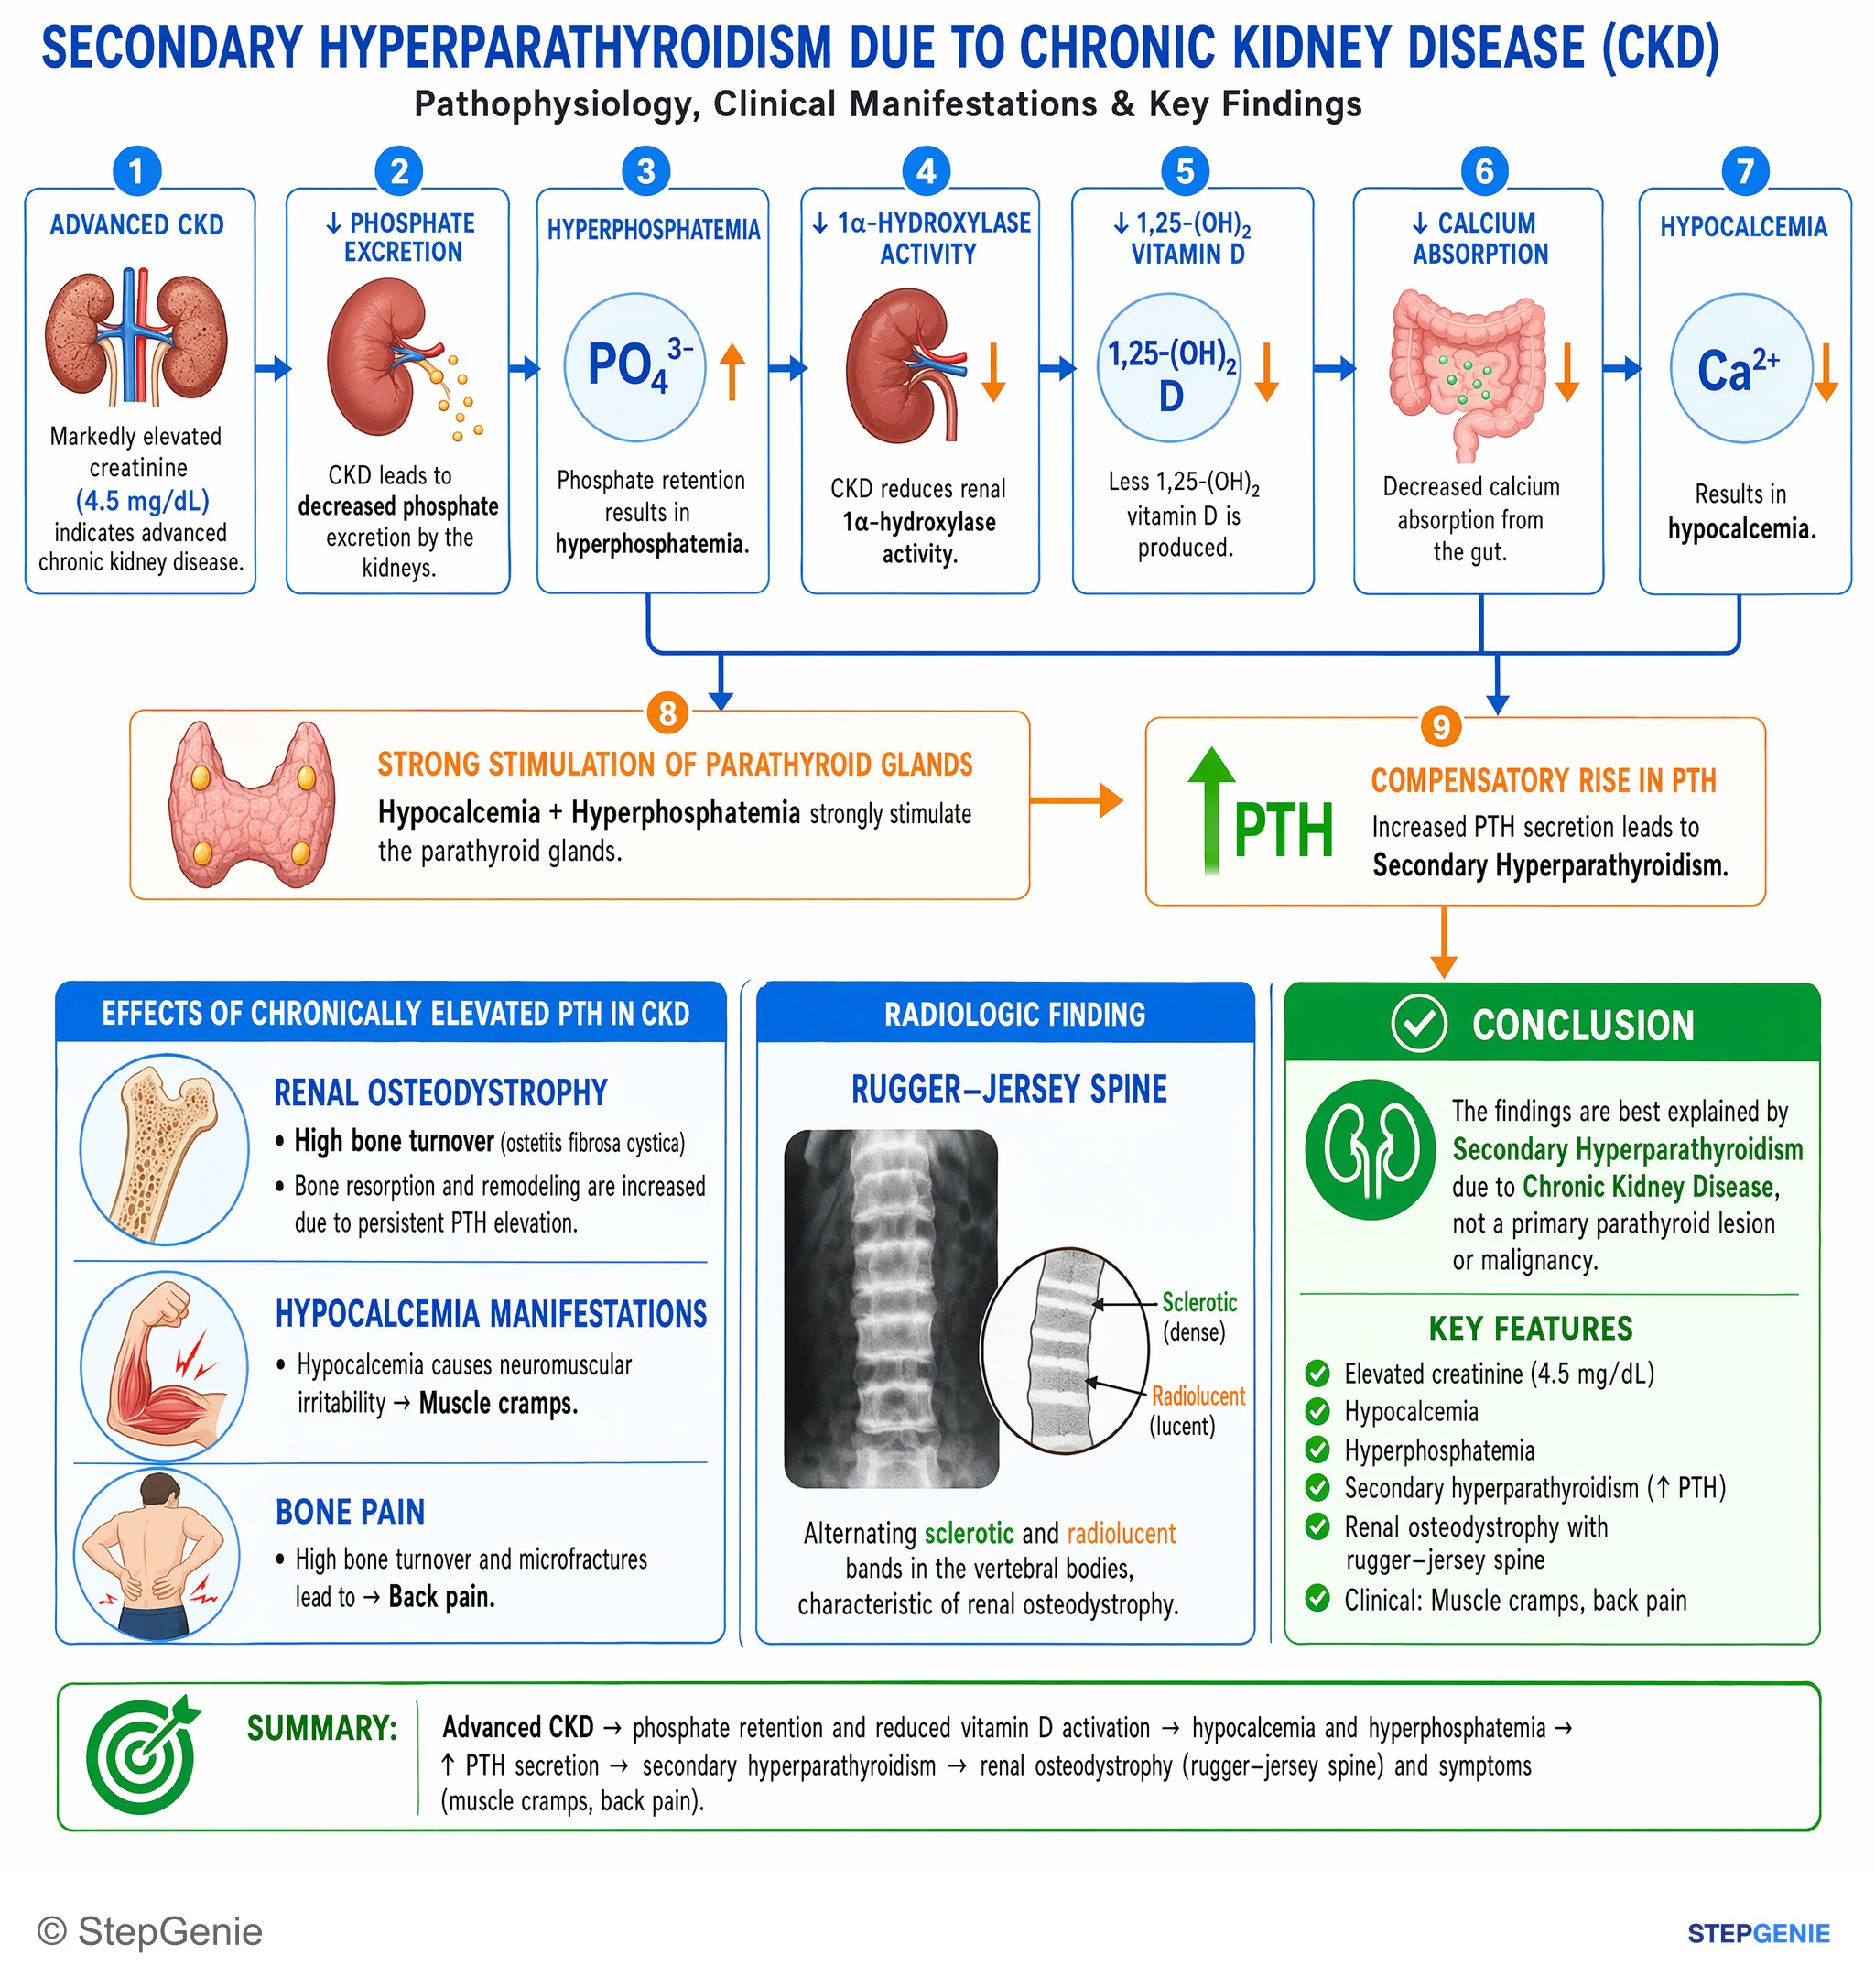
Secondary hyperparathyroidism due to chronic kidney disease → hypocalcemia, hyperphosphatemia, renal osteodystrophy with alternating…
USMLE Step 1Frequently Asked Questions
What is renal osteodystrophy?
Renal osteodystrophy is the abnormal bone of chronic kidney disease and the skeletal part of CKD-mineral and bone disorder (CKD-MBD). Failing kidneys retain phosphate and make less calcitriol, calcium falls and PTH rises, which remodels bone. It takes the form of high-turnover osteitis fibrosa cystica, low-turnover adynamic bone disease or osteomalacia, and bone biopsy is the definitive way to tell them apart.
What are the lab findings in renal osteodystrophy?
The typical pattern is high phosphate, high PTH, low 1,25-dihydroxyvitamin D and low or normal calcium, with alkaline phosphatase often high when bone turnover is high. FGF-23 rises early, typically before phosphate and PTH change, and overt hyperphosphatemia usually appears once GFR falls below about 30 mL/min. A high calcium in a dialysis patient points to tertiary hyperparathyroidism or to adynamic bone disease with calcium loading.
What is the difference between secondary and tertiary hyperparathyroidism?
Secondary hyperparathyroidism is the parathyroid glands' appropriate response to low calcium, low calcitriol and high phosphate in CKD, so calcium is low or normal. Tertiary hyperparathyroidism develops after years of stimulation, when hyperplastic, nodular glands secrete PTH autonomously and calcium becomes high. It is classically seen in long-standing dialysis or persisting after kidney transplantation and is usually treated with parathyroidectomy.
What is adynamic bone disease?
Adynamic bone disease is low-turnover renal osteodystrophy with few bone cells and no buildup of unmineralized osteoid. It follows oversuppression of PTH by calcium loads, high-dose active vitamin D, calcimimetics or parathyroidectomy, and it is more common with diabetes, peritoneal dialysis and older age. Because the bone cannot take up calcium normally, calcium loads cause hypercalcemia, and patients are prone to vascular calcification and fractures, which is why PTH is not driven down to normal in dialysis patients.
How is renal osteodystrophy treated?
The KDIGO 2017 guideline advises lowering high phosphate toward normal with diet, phosphate binders and dialysis, avoiding hypercalcemia and limiting calcium-based binders. In dialysis patients, intact PTH is kept at about 2 to 9 times the upper limit of normal with a calcimimetic such as cinacalcet or etelcalcetide, calcitriol or a vitamin D analog, or a combination. Parathyroidectomy is reserved for severe hyperparathyroidism that fails medical therapy, and aluminum binders are avoided.
What is rugger-jersey spine?
Rugger-jersey spine is a radiographic sign of renal osteodystrophy in which sclerotic bands along the upper and lower vertebral endplates alternate with less dense bone in the middle of each vertebral body, like the stripes of a rugby jersey. It reflects hyperparathyroid bone disease in CKD. Other imaging clues include subperiosteal resorption on the radial side of the middle phalanges, a salt-and-pepper skull and brown tumors.