SIADH and psychogenic (primary) polydipsia both cause euvolemic, hypotonic hyponatremia, and the urine osmolality tells them apart. In SIADH, ADH acts without a normal stimulus, so the urine is inappropriately concentrated (above 100 mOsm/kg) despite a low serum osmolality, the urine sodium is usually above 30 mEq/L and serum uric acid is low. In primary polydipsia, ADH is appropriately switched off, so the urine is maximally dilute (below 100 mOsm/kg); the sodium falls only because water intake outruns the kidneys' ability to excrete it. Both improve when water intake is limited, but severe symptoms need 3% saline, and Merck advises raising the sodium no more than 8 mEq/L in 24 hours to avoid osmotic demyelination.
Step 1: confirm the hyponatremia is hypotonic
Hyponatremia is a serum sodium below 135 mEq/L (Merck uses below 136). Before blaming water, check the serum osmolality, measured or estimated:
\text{Na}^+
- Low (below 275 mOsm/kg): true hypotonic hyponatremia, the kind that drives water into brain cells.
- Normal (pseudohyponatremia): severe hypertriglyceridemia or a paraprotein (for example, multiple myeloma) distorts the laboratory measurement.
- High (translocational): hyperglycemia or mannitol pulls water out of cells; sodium falls about 1.6 mEq/L for every 100 mg/dL rise in glucose.
Step 2: urine osmolality asks whether ADH is on
| Urine osmolality | ADH | Think of |
|---|---|---|
| Below 100 mOsm/kg (specific gravity below about 1.003) | Appropriately suppressed | Primary polydipsia: relative excess water intake |
| Above 100 mOsm/kg | Active | SIADH, but also hypovolemia, heart failure, cirrhosis, adrenal insufficiency, hypothyroidism and thiazides |
Step 3: volume status and urine sodium
- Hypovolemic, urine sodium below 10 mEq/L: extrarenal losses (vomiting, diarrhea, burns, third spacing) replaced with water.
- Hypovolemic, urine sodium above 20 mEq/L: renal losses: diuretics (especially thiazides), mineralocorticoid deficiency, salt-losing nephropathy, cerebral salt wasting.
- Euvolemic, urine sodium above 30 mEq/L: SIADH, once hypothyroidism, adrenal insufficiency and diuretic use are excluded.
- Hypervolemic, urine sodium usually below 10 mEq/L: heart failure, cirrhosis, nephrotic syndrome.
SIADH vs primary polydipsia and the look-alikes
| Feature | SIADH | Primary (psychogenic) polydipsia | Cerebral salt wasting | Hypovolemia from GI losses |
|---|---|---|---|---|
| Core problem | ADH released or acting without an osmotic or volume stimulus | Water intake exceeds what the kidneys can excrete | Renal sodium loss after brain injury, especially subarachnoid hemorrhage | Salt and water lost, water replaced |
| Volume status | Euvolemic (sometimes slightly expanded) | Euvolemic | Hypovolemic | Hypovolemic |
| Serum osmolality | Low | Low | Low | Low |
| Urine osmolality | Above 100 | Below 100 | Above 100, often above 300 | High |
| Urine sodium | Above 30 | Not the discriminator | Above 40 | Below 10 |
| Response to 0.9% saline | Does not correct it | Not needed | Corrects it | Corrects it |
| Treatment | Restrict fluid, treat the cause; salt tablets, oral urea, loop diuretic; vaptans | Stop the excess water; treat the psychiatric driver | Isotonic saline; do not fluid-restrict | 0.9% saline |
SIADH: definition, causes and clues
Merck defines SIADH as less-than-maximally-dilute urine in the presence of low serum osmolality, without volume depletion or overload, pain, nausea, stress or other ADH triggers, in a patient with normal cardiac, hepatic, renal, adrenal and thyroid function. Supporting clues are a urine sodium above 30 mEq/L, a fractional excretion of sodium above 1%, a low serum uric acid and a normal BUN and creatinine.
Causes: "small cell, sick CNS, stressed lungs, and meds."
- Cancer: especially small cell lung carcinoma; also lymphoma and cancers of the brain, duodenum and pancreas. See the paraneoplastic syndromes Q-bank.
- CNS disorders: stroke, subarachnoid or subdural hemorrhage, head trauma, meningitis, encephalitis, brain abscess, Guillain-Barré syndrome, pituitary surgery, acute psychosis.
- Lung disorders: pneumonia, tuberculosis, lung abscess, aspergillosis, positive-pressure ventilation.
- Drugs: SSRIs and venlafaxine, carbamazepine, antipsychotics, opioids and NSAIDs, cyclophosphamide and vincristine, chlorpropamide, MDMA; oxytocin and desmopressin act like ADH.
A chest radiograph looks for a mass or infiltrate. Some patients have a reset osmostat: ADH does switch off, but at a lower-than-normal sodium.
Primary polydipsia: when drinking beats the kidneys
- Normal kidneys can excrete up to about 25 L of urine a day, so drinking alone causes hyponatremia only with huge intakes or when water excretion is impaired, as in kidney disease.
- The typical patient has a psychiatric illness such as a psychotic disorder. Antipsychotics can also cause SIADH, so the two mechanisms can overlap.
- MDMA (ecstasy) does both: heavy drinking plus ADH release.
- Acute water intoxication (onset within 24 hours: acute psychogenic polydipsia, MDMA, endurance runners replacing sweat with hypotonic drinks, hypotonic fluids after surgery) carries the greatest risk of brain edema; Merck recommends hypertonic saline even when neurologic symptoms are mild.
- Polyuria workup: patients may drink and excrete up to 6 L a day, usually without nocturia. On a water deprivation test, long-standing polydipsia may not reach maximal urine concentration, but unlike central diabetes insipidus it shows no response to vasopressin. The comparison is in the diabetes insipidus overview.
- Watch the rise: ADH is already off and normal kidneys can excrete up to about 25 L a day, so the sodium can climb quickly once drinking stops; check it every few hours to stay within the 8 mEq/L limit.
Treatment and the speed limit
- Severe symptoms (seizures, coma, marked confusion): 3% saline. For acute-onset hyponatremia with neurologic symptoms, Merck gives 100 mL IV over 15 minutes, repeated once if symptoms persist, aiming for a rise of 4–6 mEq/L over the first hours.
- Limit: no more than 8 mEq/L in the first 24 hours (Merck). Many experts otherwise aim for about 1 mEq/L per hour, allowing up to 2 mEq/L per hour for the first 2–3 hours in a patient with seizures or marked confusion.
- SIADH: restrict fluids (Merck: severe restriction, such as 250–500 mL a day), treat the cause and stop offending drugs. Next options are salt tablets, oral urea (which Merck calls an effective and safe alternative) or a loop diuretic with salt. Vaptans block V2 receptors and cause water loss without sodium loss: conivaptan IV in hospital, or oral tolvaptan, limited to 30 days because of liver toxicity and avoided in liver disease. Demeclocycline is rarely used because it can cause acute kidney injury.
- Primary polydipsia: restrict water and treat the psychiatric cause; acute-onset or severely symptomatic cases need hypertonic saline.
- Overcorrection: stop the hypertonic saline; giving hypotonic fluid to bring the sodium back down may limit brain injury, and desmopressin can be used to prevent an unpredictable water diuresis.
Osmotic demyelination syndrome (formerly central pontine myelinolysis) appears days to weeks after too-rapid correction, with dysarthria, dysphagia and flaccid paralysis, sometimes a "locked-in" state; it is more common with alcohol use disorder, undernutrition or other chronic debilitating illness. Practice it with the central pontine myelinolysis case.
Exam traps
- A urine osmolality above 100 is not specific for SIADH; hypovolemia and edematous states also switch ADH on, so volume status and urine sodium decide.
- Check TSH and cortisol before calling it SIADH.
- Cerebral salt wasting is hypovolemic and responds to saline; fluid restriction can harm these patients.
- Thiazides, not loop diuretics, are the classic diuretic cause; a loop diuretic can even help treat SIADH.
- Hyperglycemia lowers the sodium without making the plasma hypotonic.
- New neurologic deficits days after correction mean osmotic demyelination.
Worked example
Vignette. A 32-year-old man with schizophrenia is brought from his group home after a generalized seizure. Staff say he has been drinking from the tap all day. His mucous membranes are moist, there is no edema and his blood pressure is normal. Serum sodium is 116 mEq/L, glucose is normal, serum osmolality is 242 mOsm/kg, urine osmolality is 58 mOsm/kg and TSH is normal. What is the best next step?
Answer: This is primary polydipsia with acute, symptomatic hyponatremia. Give 3% saline 100 mL IV over 15 minutes, repeated once if seizures continue, aiming for a 4–6 mEq/L rise. Then stop the free water and check the sodium every 2 hours: with ADH switched off, his dilute urine output can raise the sodium quickly once he stops drinking, and the rise should stay within 8 mEq/L in 24 hours.
Why not the others?
- Fluid restriction alone: right for mild, asymptomatic cases, but too slow for a patient who has had a seizure.
- Tolvaptan: vaptans can raise the sodium too fast and are reserved for severe or symptomatic hyponatremia that resists fluid restriction; a seizure needs hypertonic saline now, and a urine osmolality of 58 mOsm/kg shows the kidney is already making maximally dilute urine.
- SIADH: the urine would be concentrated (above 100 mOsm/kg); here the kidney is diluting maximally.
- 0.9% saline: used for hypovolemia; this patient is euvolemic and needs hypertonic saline for the seizure.
- Central diabetes insipidus: dilute urine comes from missing ADH, so the risk is dehydration, not dilutional hyponatremia, and nocturia is almost universal.
Key takeaways
- Confirm hypotonic hyponatremia first (serum osmolality below 275 mOsm/kg).
- Urine osmolality below 100 = ADH off = primary polydipsia; above 100 = ADH on, then sort by volume status and urine sodium.
- SIADH: euvolemic, urine sodium above 30 mEq/L, low uric acid; small cell lung cancer, CNS and lung disease, drugs; exclude hypothyroidism and adrenal insufficiency.
- Treat by severity: 3% saline for severe symptoms; fluid restriction, salt, urea or vaptans for chronic SIADH; water restriction for polydipsia.
- Speed limit: no more than 8 mEq/L in 24 hours (Merck), after an initial 4–6 mEq/L rise if symptoms are severe.
Sources
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
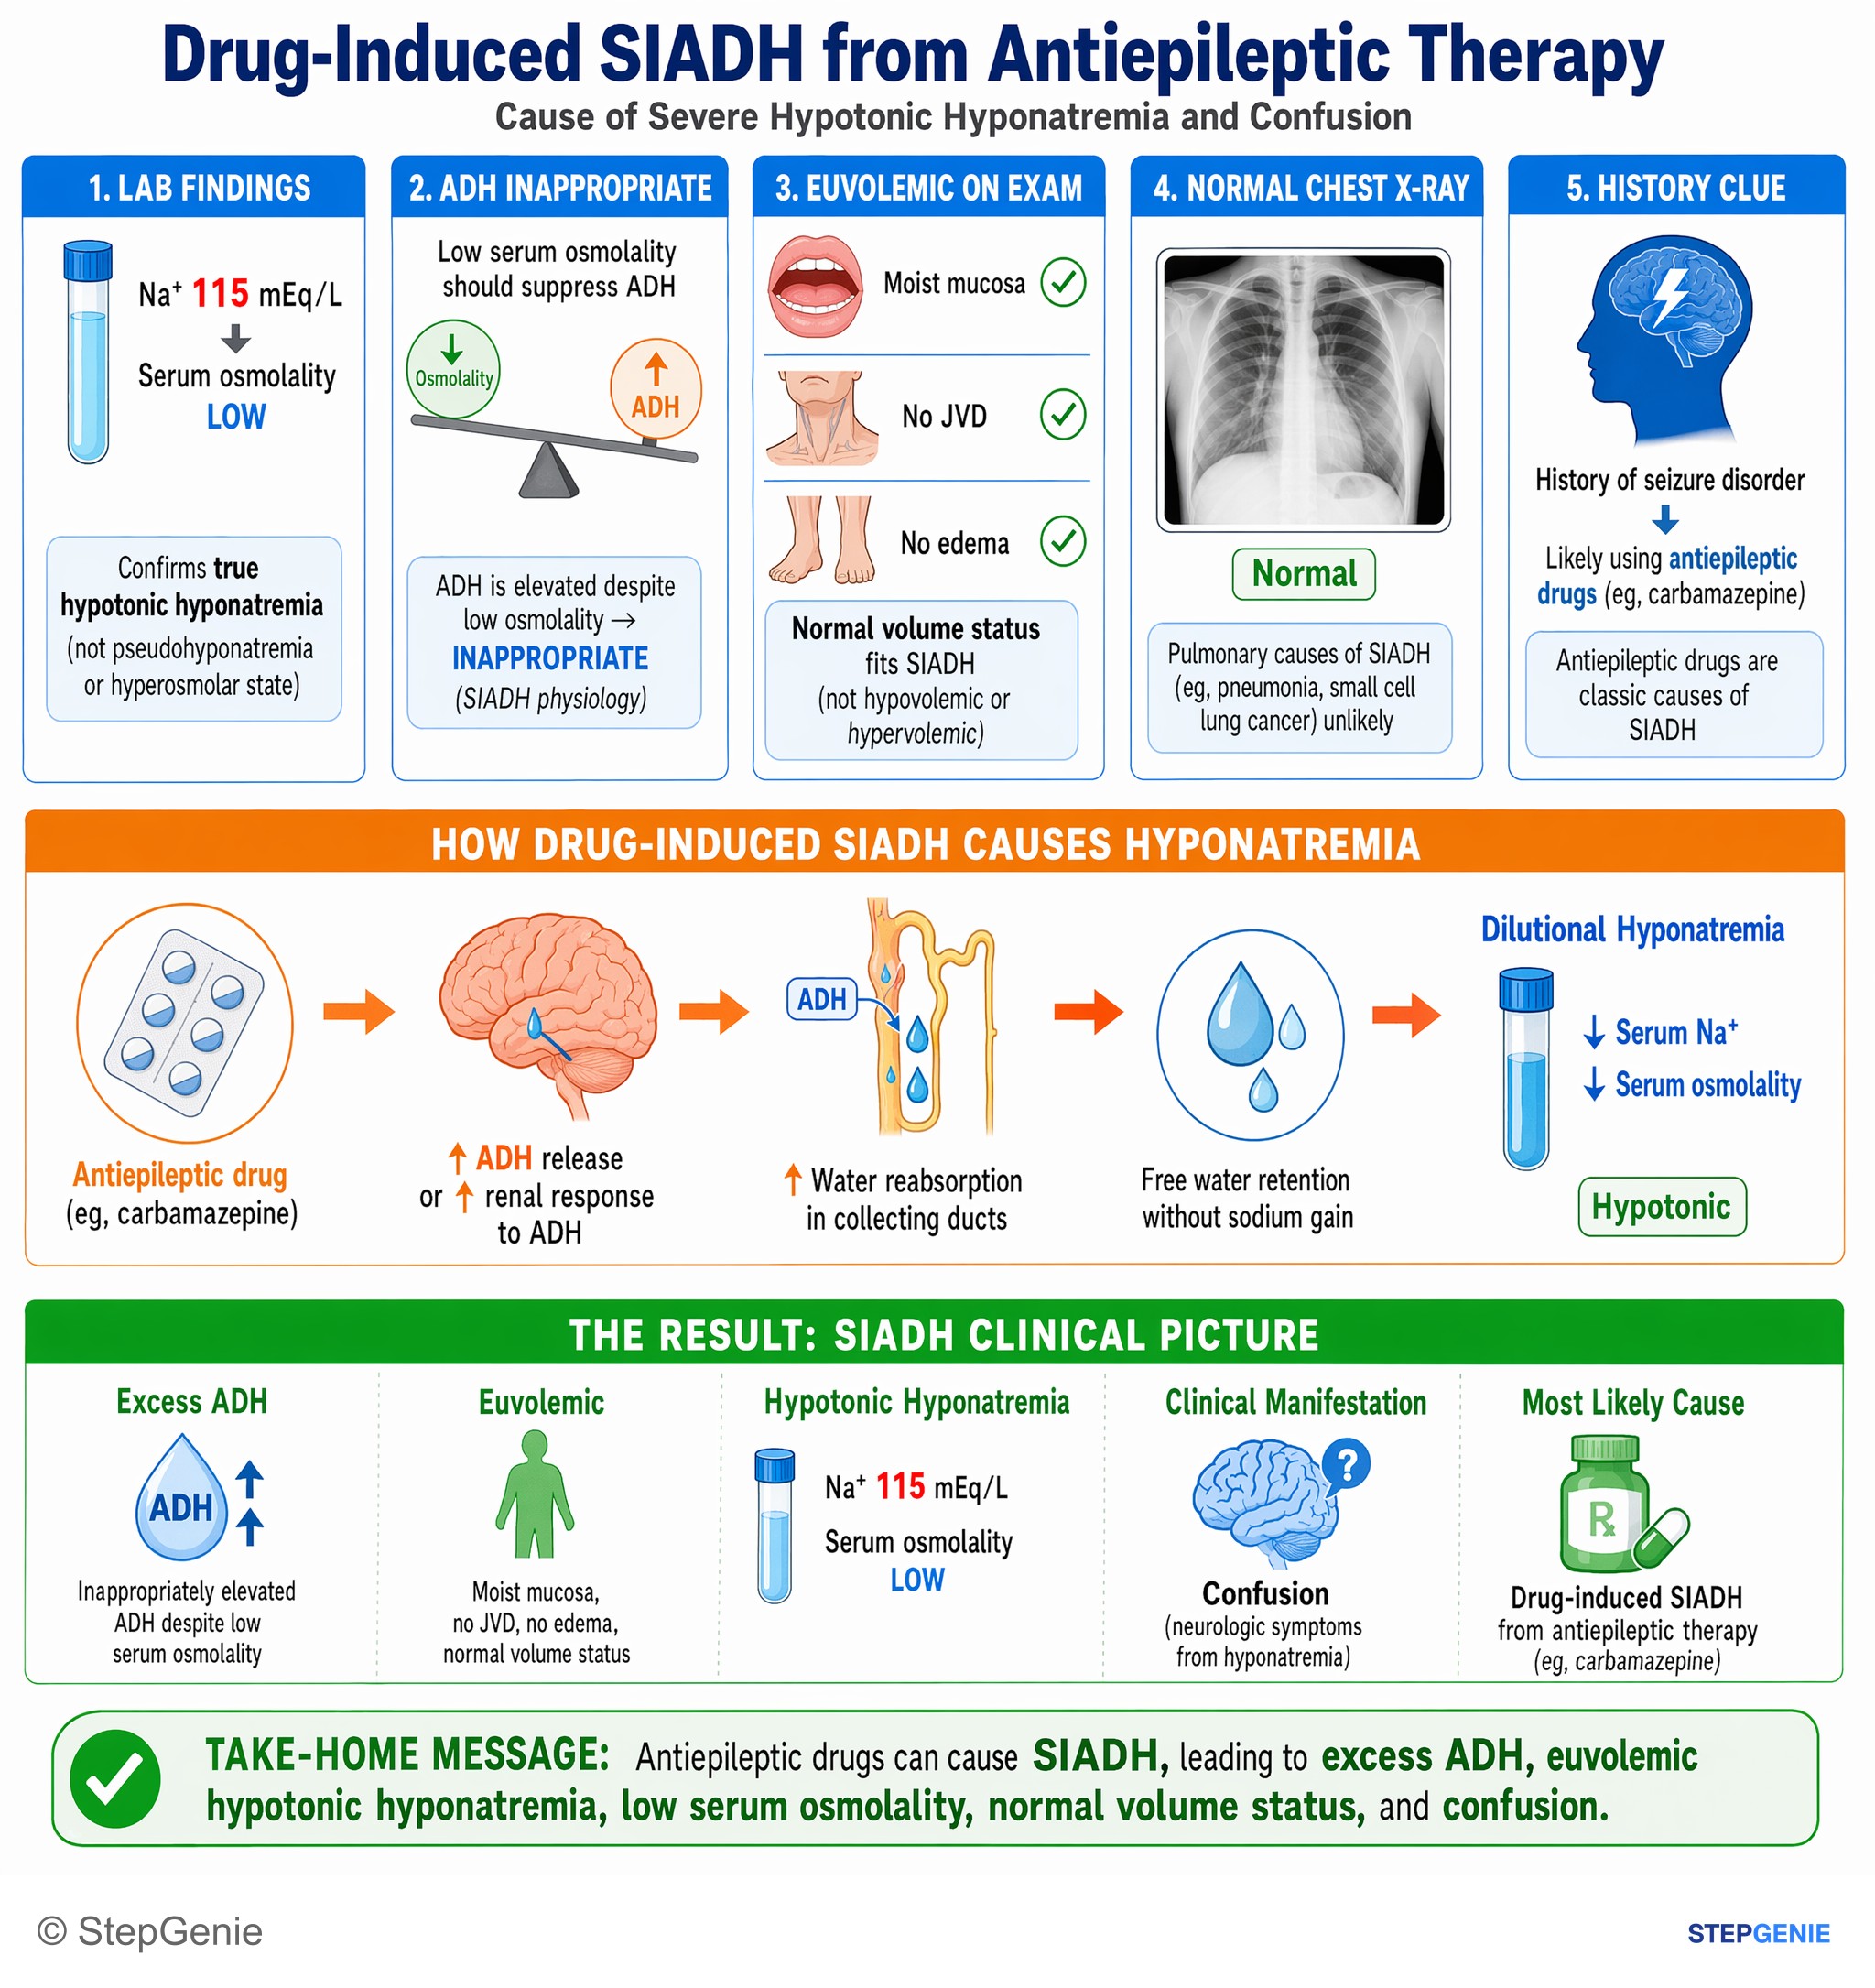
Drug-induced SIADH from antiepileptic therapy → excess ADH, euvolemic hypotonic hyponatremia, low serum osmolality, normal volume status…
USMLE Step 1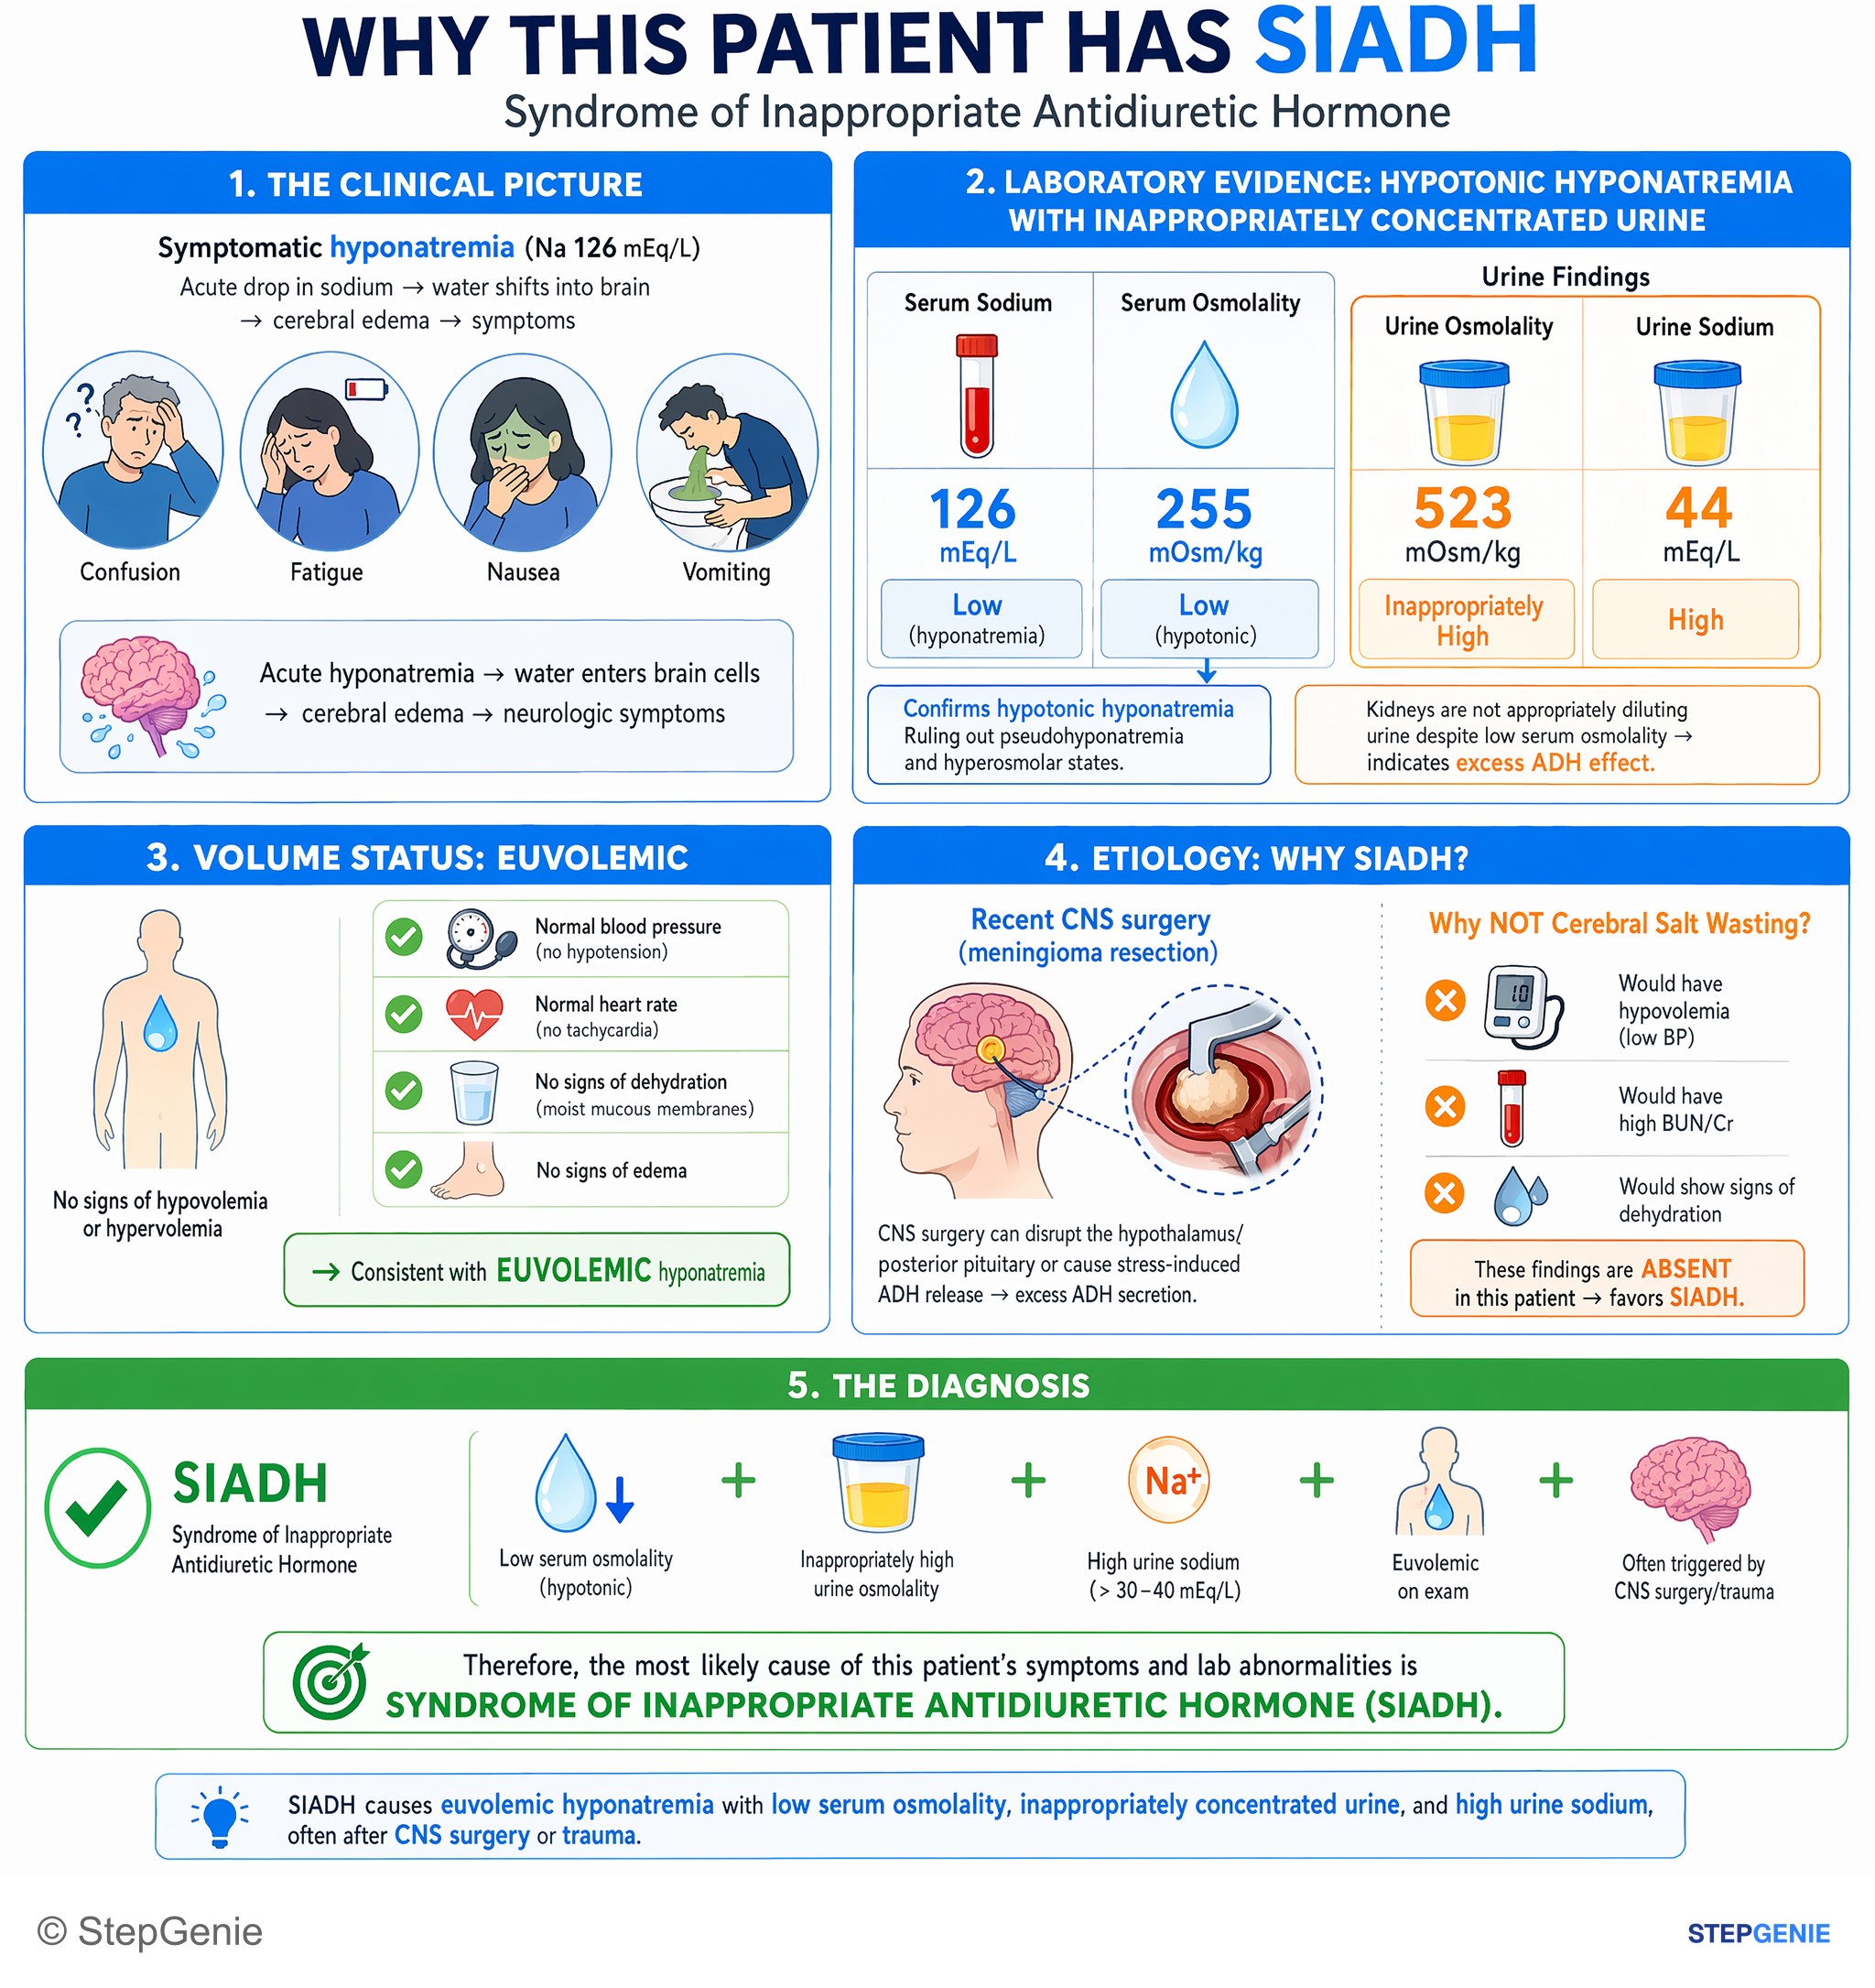
SIADH causes euvolemic hyponatremia with low serum osmolality, inappropriately concentrated urine, and high urine sodium, often after CNS…
USMLE Step 2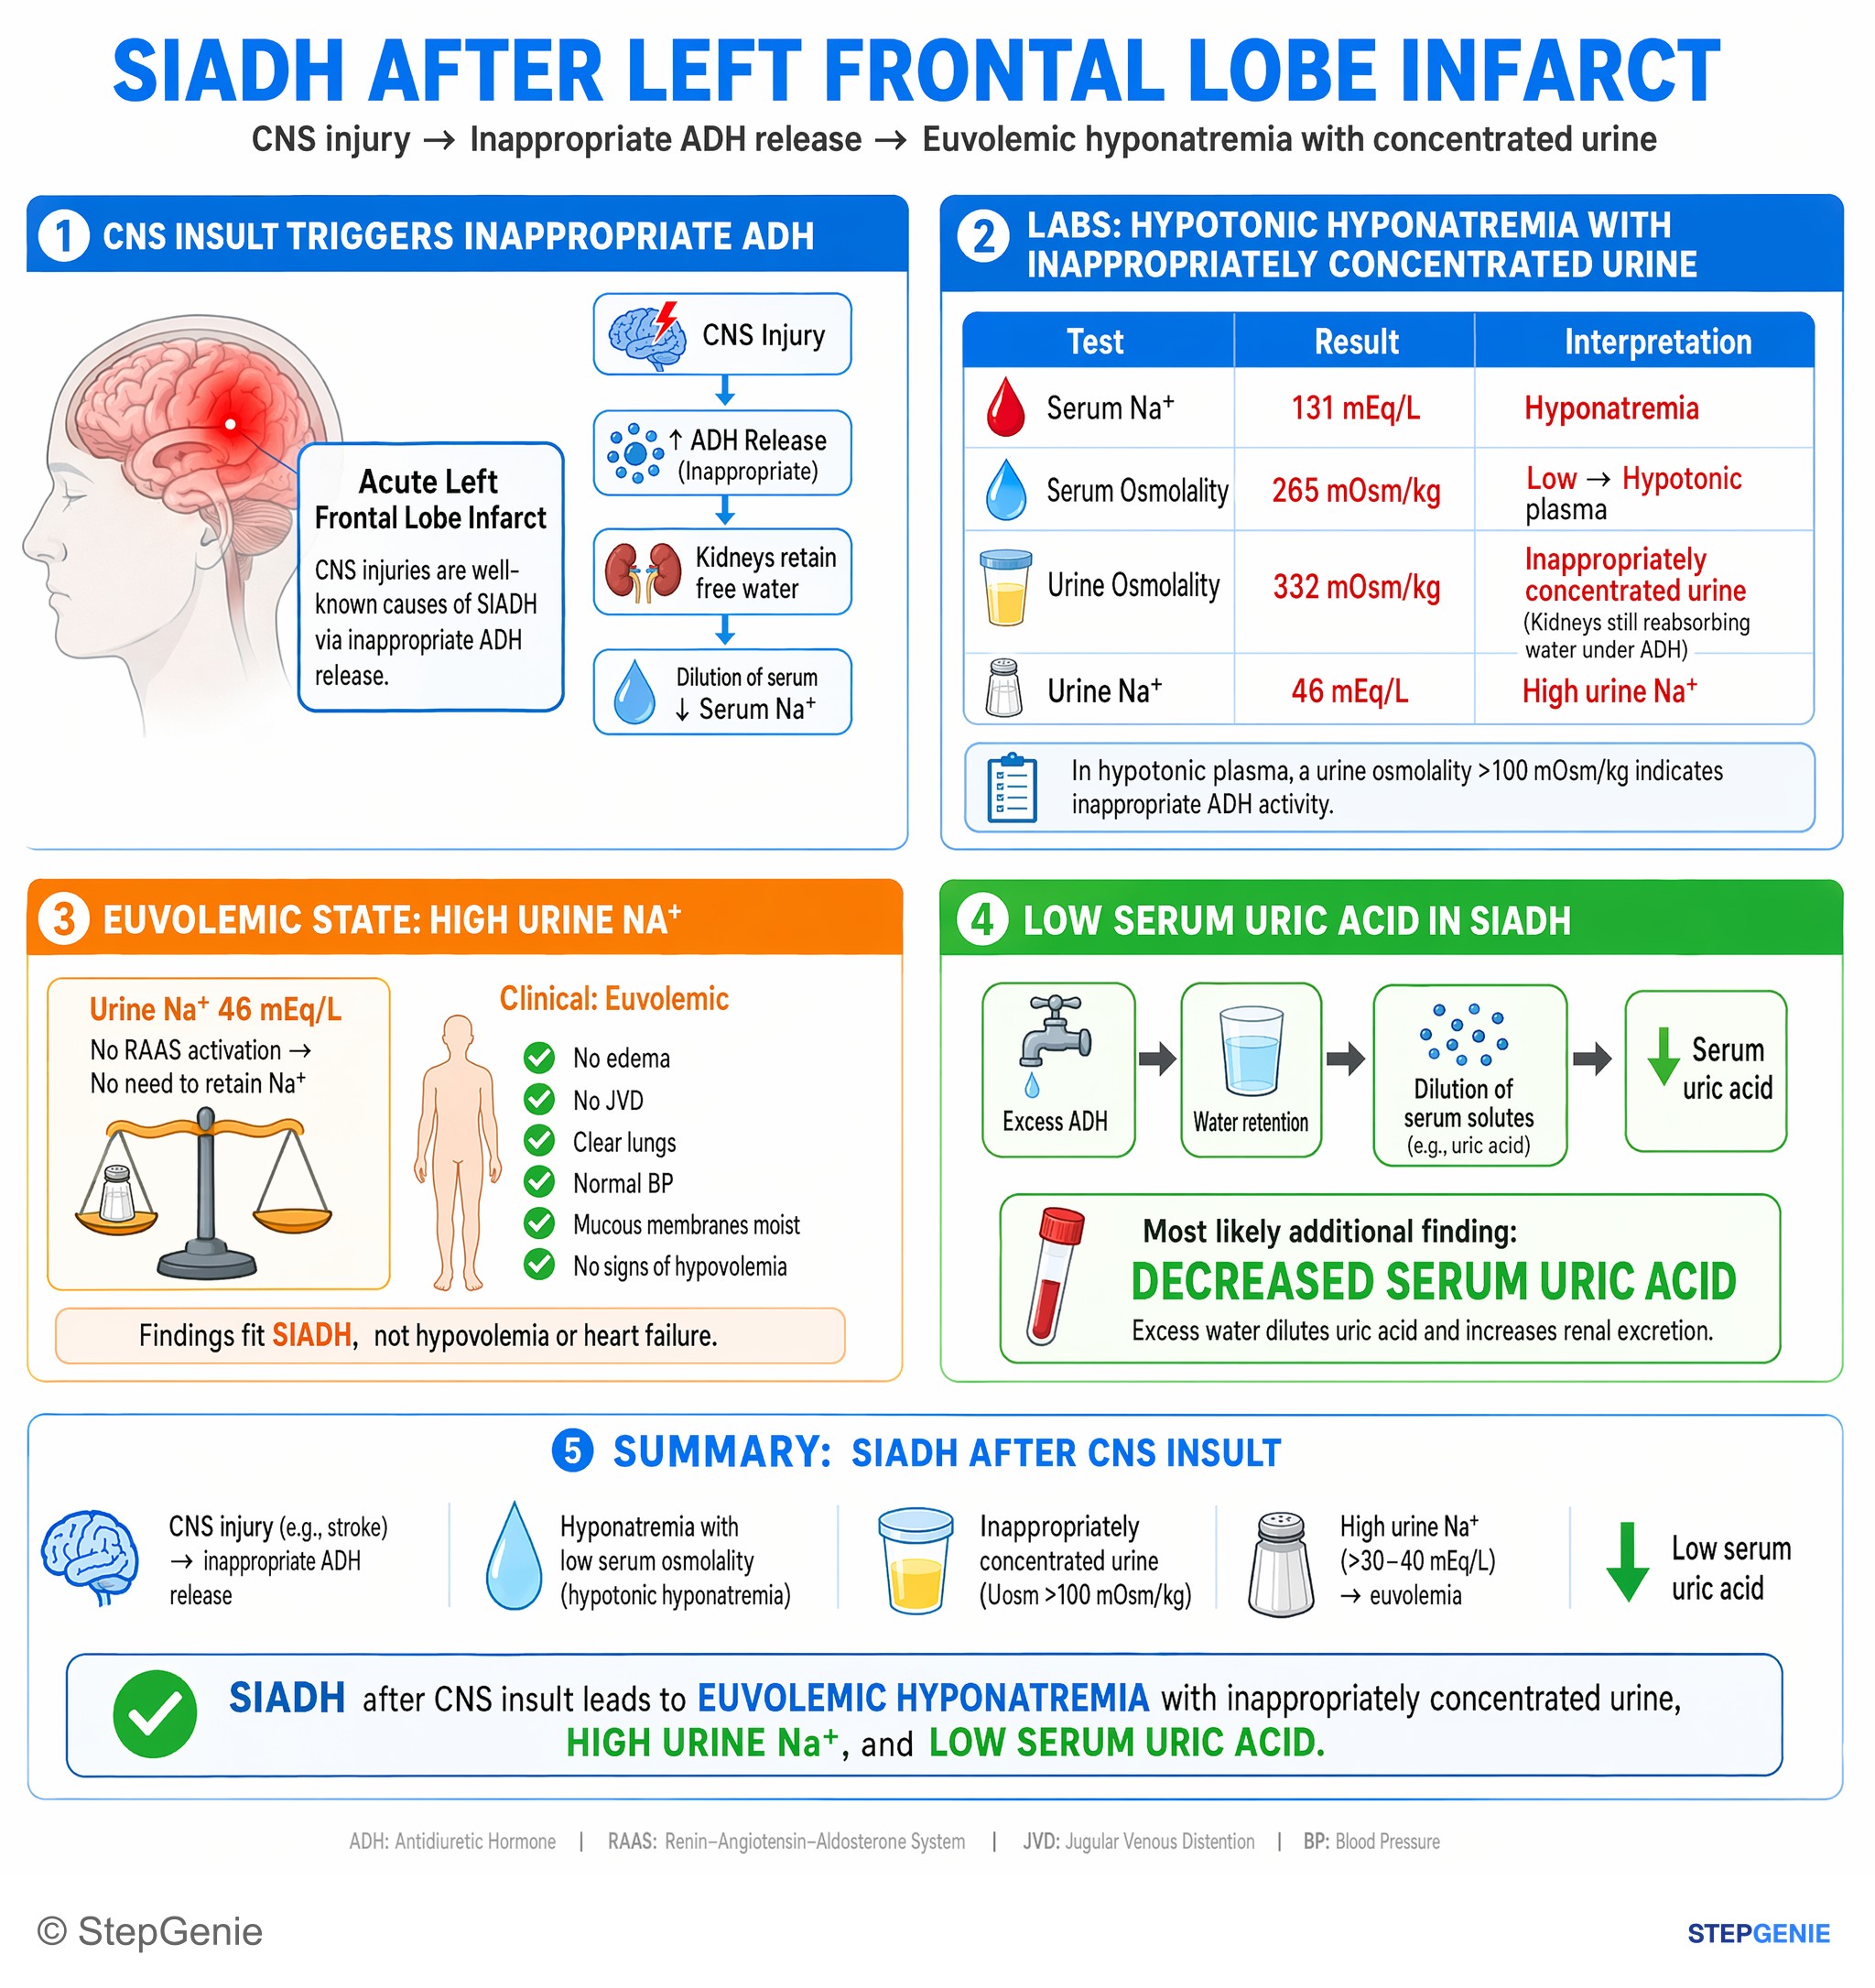
SIADH after CNS insult → euvolemic hyponatremia with inappropriately concentrated urine, high urine Na+, and low serum uric acid.
USMLE Step 2Frequently Asked Questions
How do you tell SIADH from psychogenic polydipsia?
Both cause euvolemic hyponatremia with a low serum osmolality, so the urine decides. In SIADH the urine is inappropriately concentrated, above 100 mOsm/kg, and the urine sodium is usually above 30 mEq/L. In primary polydipsia ADH is suppressed, so the urine is maximally dilute, below 100 mOsm/kg with a specific gravity below about 1.003. A history of compulsive drinking or psychosis supports polydipsia.
Why is urine sodium high in SIADH?
In SIADH the retained water slightly expands the extracellular volume while the patient keeps taking in salt, so the kidneys keep excreting sodium instead of conserving it as they would in hypovolemia. Urine sodium is therefore usually above 30 mEq/L, with a fractional excretion of sodium above 1%. A low urine sodium in a hyponatremic patient points instead to low effective circulating volume.
What are the most common causes of SIADH?
The main groups are cancers, especially small cell lung carcinoma; central nervous system disorders such as stroke, hemorrhage, head trauma, meningitis and encephalitis; lung disease such as pneumonia, tuberculosis, lung abscess and positive-pressure ventilation; and drugs. The drug classes most often implicated are opioids and NSAIDs, SSRIs and venlafaxine, carbamazepine, antipsychotics, and cytotoxics such as cyclophosphamide and vincristine.
How fast can hyponatremia be corrected?
Merck advises raising the serum sodium by no more than 8 mEq/L in the first 24 hours, generally at about 1 mEq/L per hour. Severe symptoms such as seizures still justify a prompt 4–6 mEq/L rise with 3% saline over the first few hours, after which correction is slowed to stay within the daily limit. Faster correction risks osmotic demyelination, especially with alcohol use disorder or undernutrition.
Why can psychogenic polydipsia correct too quickly?
In primary polydipsia ADH is already suppressed, and normal kidneys can excrete up to about 25 L of dilute urine a day. Once the patient stops drinking, that water keeps leaving, so the sodium can climb quickly, especially if hypertonic saline has also been given. Checking the sodium every few hours helps keep the rise within 8 mEq/L in 24 hours; if it overshoots, stopping hypertonic saline and giving hypotonic fluid can bring it back down.