Urgent dialysis is indicated when a complication of kidney failure cannot be controlled medically, remembered as AEIOU: refractory Acidosis, Electrolyte emergencies (mainly hyperkalemia with ECG changes or resistant to treatment), Intoxication with a dialyzable toxin (methanol, ethylene glycol, lithium, salicylates), fluid Overload unresponsive to diuretics, and symptomatic Uremia (pericarditis, encephalopathy, uremic bleeding). A BUN or creatinine value alone is not an indication. In CKD, maintenance dialysis starts when symptoms or uncontrollable complications appear, usually at an eGFR of about 5–10 mL/min/1.73 m².
AEIOU: the dialysis indications mnemonic
| Letter | Indication | What makes it a dialysis problem | Try first | Classic stem clue |
|---|---|---|---|---|
| A | Acidosis | Severe metabolic acidosis (pH below about 7.2) that does not respond to bicarbonate, or bicarbonate impossible because of volume overload | IV sodium bicarbonate; treat the cause | Bicarbonate of 8 in an oliguric, volume-overloaded patient |
| E | Electrolytes | Hyperkalemia with ECG changes, or K⁺ above about 6.5 mEq/L that persists despite medical therapy | Calcium, then insulin + glucose and a beta-2 agonist, then potassium binders or a loop diuretic | "Missed two dialysis sessions," peaked T waves |
| I | Intoxication | A dialyzable toxin causing severe toxicity | Antidote and supportive care (fomepizole for toxic alcohols) | New visual symptoms with acidosis (methanol); oxalate (ethylene glycol); confusion on chronic lithium |
| O | Overload | Pulmonary edema or hypertension from volume excess that diuretics cannot clear | Loop diuretics | Anuric patient with crackles and hypoxemia |
| U | Uremia | Pericarditis, encephalopathy (confusion, asterixis, seizures), neuropathy, uremic bleeding, intractable nausea and vomiting | Desmopressin for active uremic bleeding; otherwise nothing substitutes for dialysis | Friction rub, or confusion with asterixis |
The pattern to remember: A, E and O qualify when they are severe and resistant to medical therapy; I and U qualify once the toxicity or uremic complication is serious. The same five letters cover acute kidney injury (AKI) and decompensated chronic kidney disease (CKD).
Emergent dialysis vs planned dialysis: AKI and CKD compared
Students often treat "acute dialysis indications" and "indications for dialysis in CKD" as different lists. They overlap, but the decision rule differs.
| Question | AKI (acute, often ICU) | CKD G5 (maintenance) |
|---|---|---|
| What triggers it | A life-threatening AEIOU complication | Symptoms or signs of kidney failure, uncontrollable volume or blood pressure, malnutrition or cognitive decline |
| Role of the eGFR or BUN number | None on its own | Supports timing; most people start at an eGFR of about 5–10 |
| Evidence on starting early | STARRT-AKI and AKIKI: no survival benefit from pre-emptive starts | IDEAL: no survival benefit from starting at eGFR 10–14 rather than 5–7 |
| Usual modality | Intermittent hemodialysis; continuous kidney replacement therapy (CKRT, often still called CRRT) if hemodynamically unstable | Hemodialysis via an AV fistula, peritoneal dialysis, or pre-emptive transplant |
| Is it permanent? | Often temporary; reassess daily | Lifelong unless transplanted |
Hyperkalemia: best initial step vs definitive treatment
The ECG worsens in a predictable order, roughly with the level: peaked T waves (about 5.5–6.5 mEq/L) → flattened or absent P waves (6.5–7.5) → widened QRS (7–8) → sine wave, ventricular fibrillation or asystole (above 8). The speed of the rise matters more than the absolute number, so any ECG change is an emergency.
- Stabilize the myocardium with IV calcium (gluconate usually preferred). It protects the heart but does not lower potassium.
- Shift potassium into cells with regular insulin (commonly 10 units) plus glucose, and a high-dose inhaled beta-2 agonist; add bicarbonate only if the patient is acidotic. The effect is temporary.
- Remove potassium from the body: a loop diuretic if the patient makes urine, a binder (patiromer or sodium zirconium cyclosilicate; sodium polystyrene sulfonate is used less because of colonic necrosis risk), or dialysis, the definitive route in end-stage kidney disease or an anuric patient.
Exam trap: when a question with ECG changes asks for the next step, the answer is IV calcium, not dialysis. Dialysis is the definitive therapy after stabilization. For the causes and other potassium questions, see hypokalemia and hyperkalemia.
Intoxications: which poisons dialysis can and can't remove
Dialysis clears a toxin well when it is small, water-soluble and not heavily protein bound, with a small volume of distribution (it stays in body water instead of being stored in tissues). Lipid-soluble drugs that spread through the tissues barely move.
Mnemonic: BLAST — Barbiturates (long-acting, such as phenobarbital), Lithium, toxic Alcohols (methanol, ethylene glycol), Salicylates, Theophylline. Metformin (with lactic acidosis) and valproate are also removed. The international EXTRIP workgroup sets the triggers:
| Toxin | Stem clues | EXTRIP: extracorporeal treatment when |
|---|---|---|
| Lithium | Confusion or seizures, often chronic toxicity after volume depletion or lithium-induced diabetes insipidus | Impaired kidney function with Li⁺ above 4.0 mEq/L, or decreased consciousness, seizures or life-threatening dysrhythmias at any level; suggested above 5.0 mEq/L or with significant confusion |
| Salicylates | Acid–base disturbance (often mixed) with altered mental status | Altered mental status, acute lung injury (ARDS) needing oxygen, failing standard therapy, or a level above 100 mg/dL (above 90 mg/dL with impaired kidney function) |
| Methanol | Windshield washer fluid or some antifreezes; new visual deficits; acidosis with an osmolal gap | Coma, seizures, new visual deficits, pH 7.15 or lower, persistent acidosis despite antidotes, or very high levels |
| Ethylene glycol | Metabolized to glycolate and oxalate; acidosis, neurotoxicity, AKI | Severe features (coma, seizures, AKI), an anion gap above 27, or very high levels |
| Metformin | Severe lactic acidosis | Lactate above 20 mmol/L, pH 7.0 or lower, shock, or failure of standard measures |
| Valproate | Coma, hyperammonemia, cerebral edema | Level above 1,300 mg/L, cerebral edema or shock |
Not worth dialyzing: digoxin is only slightly dialyzable and extracorporeal treatment does not improve outcomes, so toxicity is treated with digoxin-specific antibody fragments; tricyclic antidepressants are not dialyzable. EXTRIP recommends against extracorporeal removal for both. For the acid–base side of these cases, see how to approach acid–base questions.
Uremia: the indications only dialysis fixes
- Uremic pericarditis: pleuritic chest pain and a friction rub in untreated kidney failure, usually with a BUN above 60 mg/dL (by definition, before or within 8 weeks of starting dialysis; later episodes are called dialysis-associated). The ECG often lacks the classic diffuse ST elevation, since fewer than 60% of patients show it. The danger is tamponade, which needs pericardiocentesis; the treatment is to start dialysis, or intensify it in someone already on it.
- Uremic encephalopathy: fatigue, somnolence and confusion early; asterixis, myoclonus, seizures, stupor and coma later. Symptomatic uremia warrants dialysis whatever the GFR.
- Uremic bleeding: uremic toxins impair platelet adhesion and function, so bleeding is common in kidney failure. IV desmopressin (DDAVP) improves platelet function within about an hour, but dialysis treats the cause.
- Other uremic signs: anorexia, nausea and vomiting, pruritus, muscle cramps, restless legs, neuropathy and uremic frost (urea crystals on the skin).
Timing in AKI: early is not better
The KDIGO AKI guideline frames the decision in two rules: start kidney replacement therapy emergently when life-threatening changes in fluid, electrolyte or acid–base balance exist, and otherwise weigh the broader clinical context and the trend of laboratory values rather than single BUN and creatinine thresholds. It also suggests CRRT rather than intermittent therapy for hemodynamically unstable patients and for those with acute brain injury or raised intracranial pressure. (KDIGO has released a draft 2026 AKI guideline for public review; the 2012 version remains the published one.)
Randomized trials then tested how long it is safe to wait in ICU patients with severe AKI but no urgent indication:
- STARRT-AKI (2020, about 3,000 patients): starting within 12 hours of eligibility did not lower 90-day mortality (43.9% vs 43.7%) compared with waiting for a conventional indication or 72 hours of persistent AKI. Early starters had more adverse events and, among survivors, more dialysis dependence at 90 days (10.4% vs 6.0%).
- AKIKI 2 (2021): once patients had more than 72 hours of oliguria or a BUN above 112 mg/dL, postponing further (until a mandatory indication or a BUN of 140 mg/dL) gave no extra dialysis-free days and was linked to higher 60-day mortality.
The exam message: start for a true AEIOU indication, do not start just because a number crossed a line, and reassess the need every day. For the AKI workup itself, see prerenal vs intrinsic vs postrenal AKI.
Starting dialysis in CKD: symptoms, not a number
Kidney failure is defined as an eGFR below 15 (CKD G5). The KDIGO 2024 CKD guideline advises starting dialysis on a composite assessment and when one or more of these is present: symptoms or signs of kidney failure (uremic neurologic symptoms, pericarditis or other serositis, anorexia, medically resistant acid–base or electrolyte abnormalities, intractable pruritus), volume or blood pressure that can't be controlled, or progressive malnutrition despite dietary intervention or cognitive impairment. This "often but not invariably" happens at an eGFR of 5–10.
In the randomized IDEAL trial, planned early starts (eGFR 10–14) did not improve survival over later starts (eGFR 5–7), and three-quarters of the late group started earlier anyway because symptoms appeared. KDIGO advises planning dialysis access or a pre-emptive transplant when the GFR falls below 15–20 or the 2-year risk of kidney replacement therapy exceeds 40%. The arteriovenous fistula is the preferred hemodialysis access. See CKD stages by GFR for the staging.
What dialysis doesn't fix, and what it causes
- It doesn't replace kidney hormones. Anemia of CKD still needs an erythropoiesis-stimulating agent; bone disease still needs phosphate binders and calcitriol or vitamin D analogs.
- Dialysis disequilibrium syndrome: headache, nausea, restlessness, confusion and, rarely, seizures or coma during or soon after the first sessions. Urea leaves the blood faster than the brain, so water moves into brain cells (cerebral edema). Risk is highest at the first treatment, with a very high BUN, at the extremes of age and with prior neurologic disease. Prevent it with short, gentle first sessions at low blood flow.
- Intradialytic hypotension and muscle cramps are common; slowing ultrafiltration helps both.
- Access infection: fever during a session suggests catheter or access infection. Staphylococcus aureus is the pathogen most often isolated from bloodstream infections in hemodialysis patients, and central venous catheters carry about six times the S. aureus bloodstream infection risk of fistulas.
- Dialysis-related amyloidosis: beta-2 microglobulin deposits cause carpal tunnel syndrome and arthropathy after years of dialysis.
Exam traps
- High creatinine, no AEIOU: a stable AKI patient with creatinine 8 but normal potassium, clear lungs and a clear sensorium needs the cause treated, not dialysis. For postrenal AKI, relieve the obstruction first.
- Hyperkalemia with ECG changes: give calcium before anything else.
- Uremic pericarditis: the answer is dialysis, not NSAIDs or colchicine.
- Digoxin or TCA overdose: dialysis is the wrong answer.
- Toxic alcohols: fomepizole blocks alcohol dehydrogenase, but severe acidosis, visual or neurologic signs, or AKI still need dialysis to clear the toxic acids.
- Hypotensive ICU patient who needs dialysis: choose CRRT over intermittent hemodialysis.
Worked examples
Vignette 1. A 61-year-old woman with CKD G5 from diabetic nephropathy, not yet on dialysis, has had 3 days of sharp chest pain that eases when she leans forward. A pericardial friction rub is heard. BUN is 128 mg/dL and potassium 5.3 mEq/L. The ECG shows no ST elevation, and she has no pulsus paradoxus. What is the most appropriate treatment?
Answer: Start hemodialysis for uremic pericarditis.
Reasoning: Pericarditis from untreated kidney failure is a U indication; the ECG often lacks diffuse ST elevation, and NSAIDs only relieve pain without treating the uremic cause.
Vignette 2. A 45-year-old man on long-term lithium presents with confusion and a creatinine twice his baseline after a week of vomiting. His lithium level is 4.6 mEq/L. Besides IV fluids, what is the next best step?
Answer: Hemodialysis.
Reasoning: Lithium is readily dialyzable; EXTRIP recommends extracorporeal treatment when kidney function is impaired and the level is above 4.0 mEq/L, or whenever consciousness is decreased.
Key takeaways
- AEIOU: refractory acidosis, electrolytes (hyperkalemia), intoxications, overload, uremia.
- Complications, not numbers, trigger dialysis; BUN or creatinine alone never does, and starting early helps neither AKI nor CKD.
- Hyperkalemia: calcium first, shift second, then remove (dialysis is definitive in anuria).
- Dialyzable = BLAST (barbiturates, lithium, toxic alcohols, salicylates, theophylline) plus metformin and valproate; digoxin and TCAs are not.
- Uremic pericarditis, encephalopathy and bleeding are treated by dialysis itself; for active uremic bleeding, give desmopressin first.
- In CKD, dialysis usually starts for symptoms at an eGFR of about 5–10; unstable ICU patients get CRRT.
More kidney reviews are collected on the nephrology topic hub.
Sources
- Hemodialysis — StatPearls, NCBI Bookshelf
- Hyperkalemia — StatPearls, NCBI Bookshelf
- Uremic Pericarditis — StatPearls, NCBI Bookshelf
- Dialysis Disequilibrium Syndrome — StatPearls, NCBI Bookshelf
- Uremia — StatPearls, NCBI Bookshelf
- Acute Kidney Injury — StatPearls, NCBI Bookshelf
- KDIGO 2012 Clinical Practice Guideline for Acute Kidney Injury
- STARRT-AKI Investigators. Timing of Initiation of Renal-Replacement Therapy in Acute Kidney Injury. N Engl J Med. 2020 (PubMed)
- Gaudry S, et al. AKIKI 2. Lancet. 2021 (PubMed)
- Cooper BA, et al. A randomized, controlled trial of early versus late initiation of dialysis (IDEAL). N Engl J Med. 2010 (PubMed)
- KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease
- Decker BS, et al. Extracorporeal Treatment for Lithium Poisoning: EXTRIP recommendations. Clin J Am Soc Nephrol. 2015 (PubMed)
- Juurlink DN, et al. Extracorporeal Treatment for Salicylate Poisoning: EXTRIP recommendations. Ann Emerg Med. 2015 (PubMed)
- Roberts DM, et al. Extracorporeal treatments in acute methanol poisoning: EXTRIP systematic review and consensus statement. Crit Care Med. 2015 (PubMed)
- Ghannoum M, et al. Extracorporeal Treatment for Ethylene Glycol Poisoning: EXTRIP recommendations. Crit Care. 2023 (PubMed)
- Calello DP, et al. Extracorporeal Treatment for Metformin Poisoning: EXTRIP recommendations. Crit Care Med. 2015 (PubMed)
- Ghannoum M, et al. Extracorporeal Treatment for Valproic Acid Poisoning: EXTRIP recommendations. Clin Toxicol. 2015 (PubMed)
- Mowry JB, et al. Extracorporeal Treatment for Digoxin Poisoning: EXTRIP recommendations. Clin Toxicol. 2016 (PubMed)
- Yates C, et al. Extracorporeal Treatment for Tricyclic Antidepressant Poisoning: EXTRIP recommendations. Semin Dial. 2014 (PubMed)
- Hemodialysis-associated Staphylococcus aureus bloodstream infections — CDC MMWR Vital Signs, 2023
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
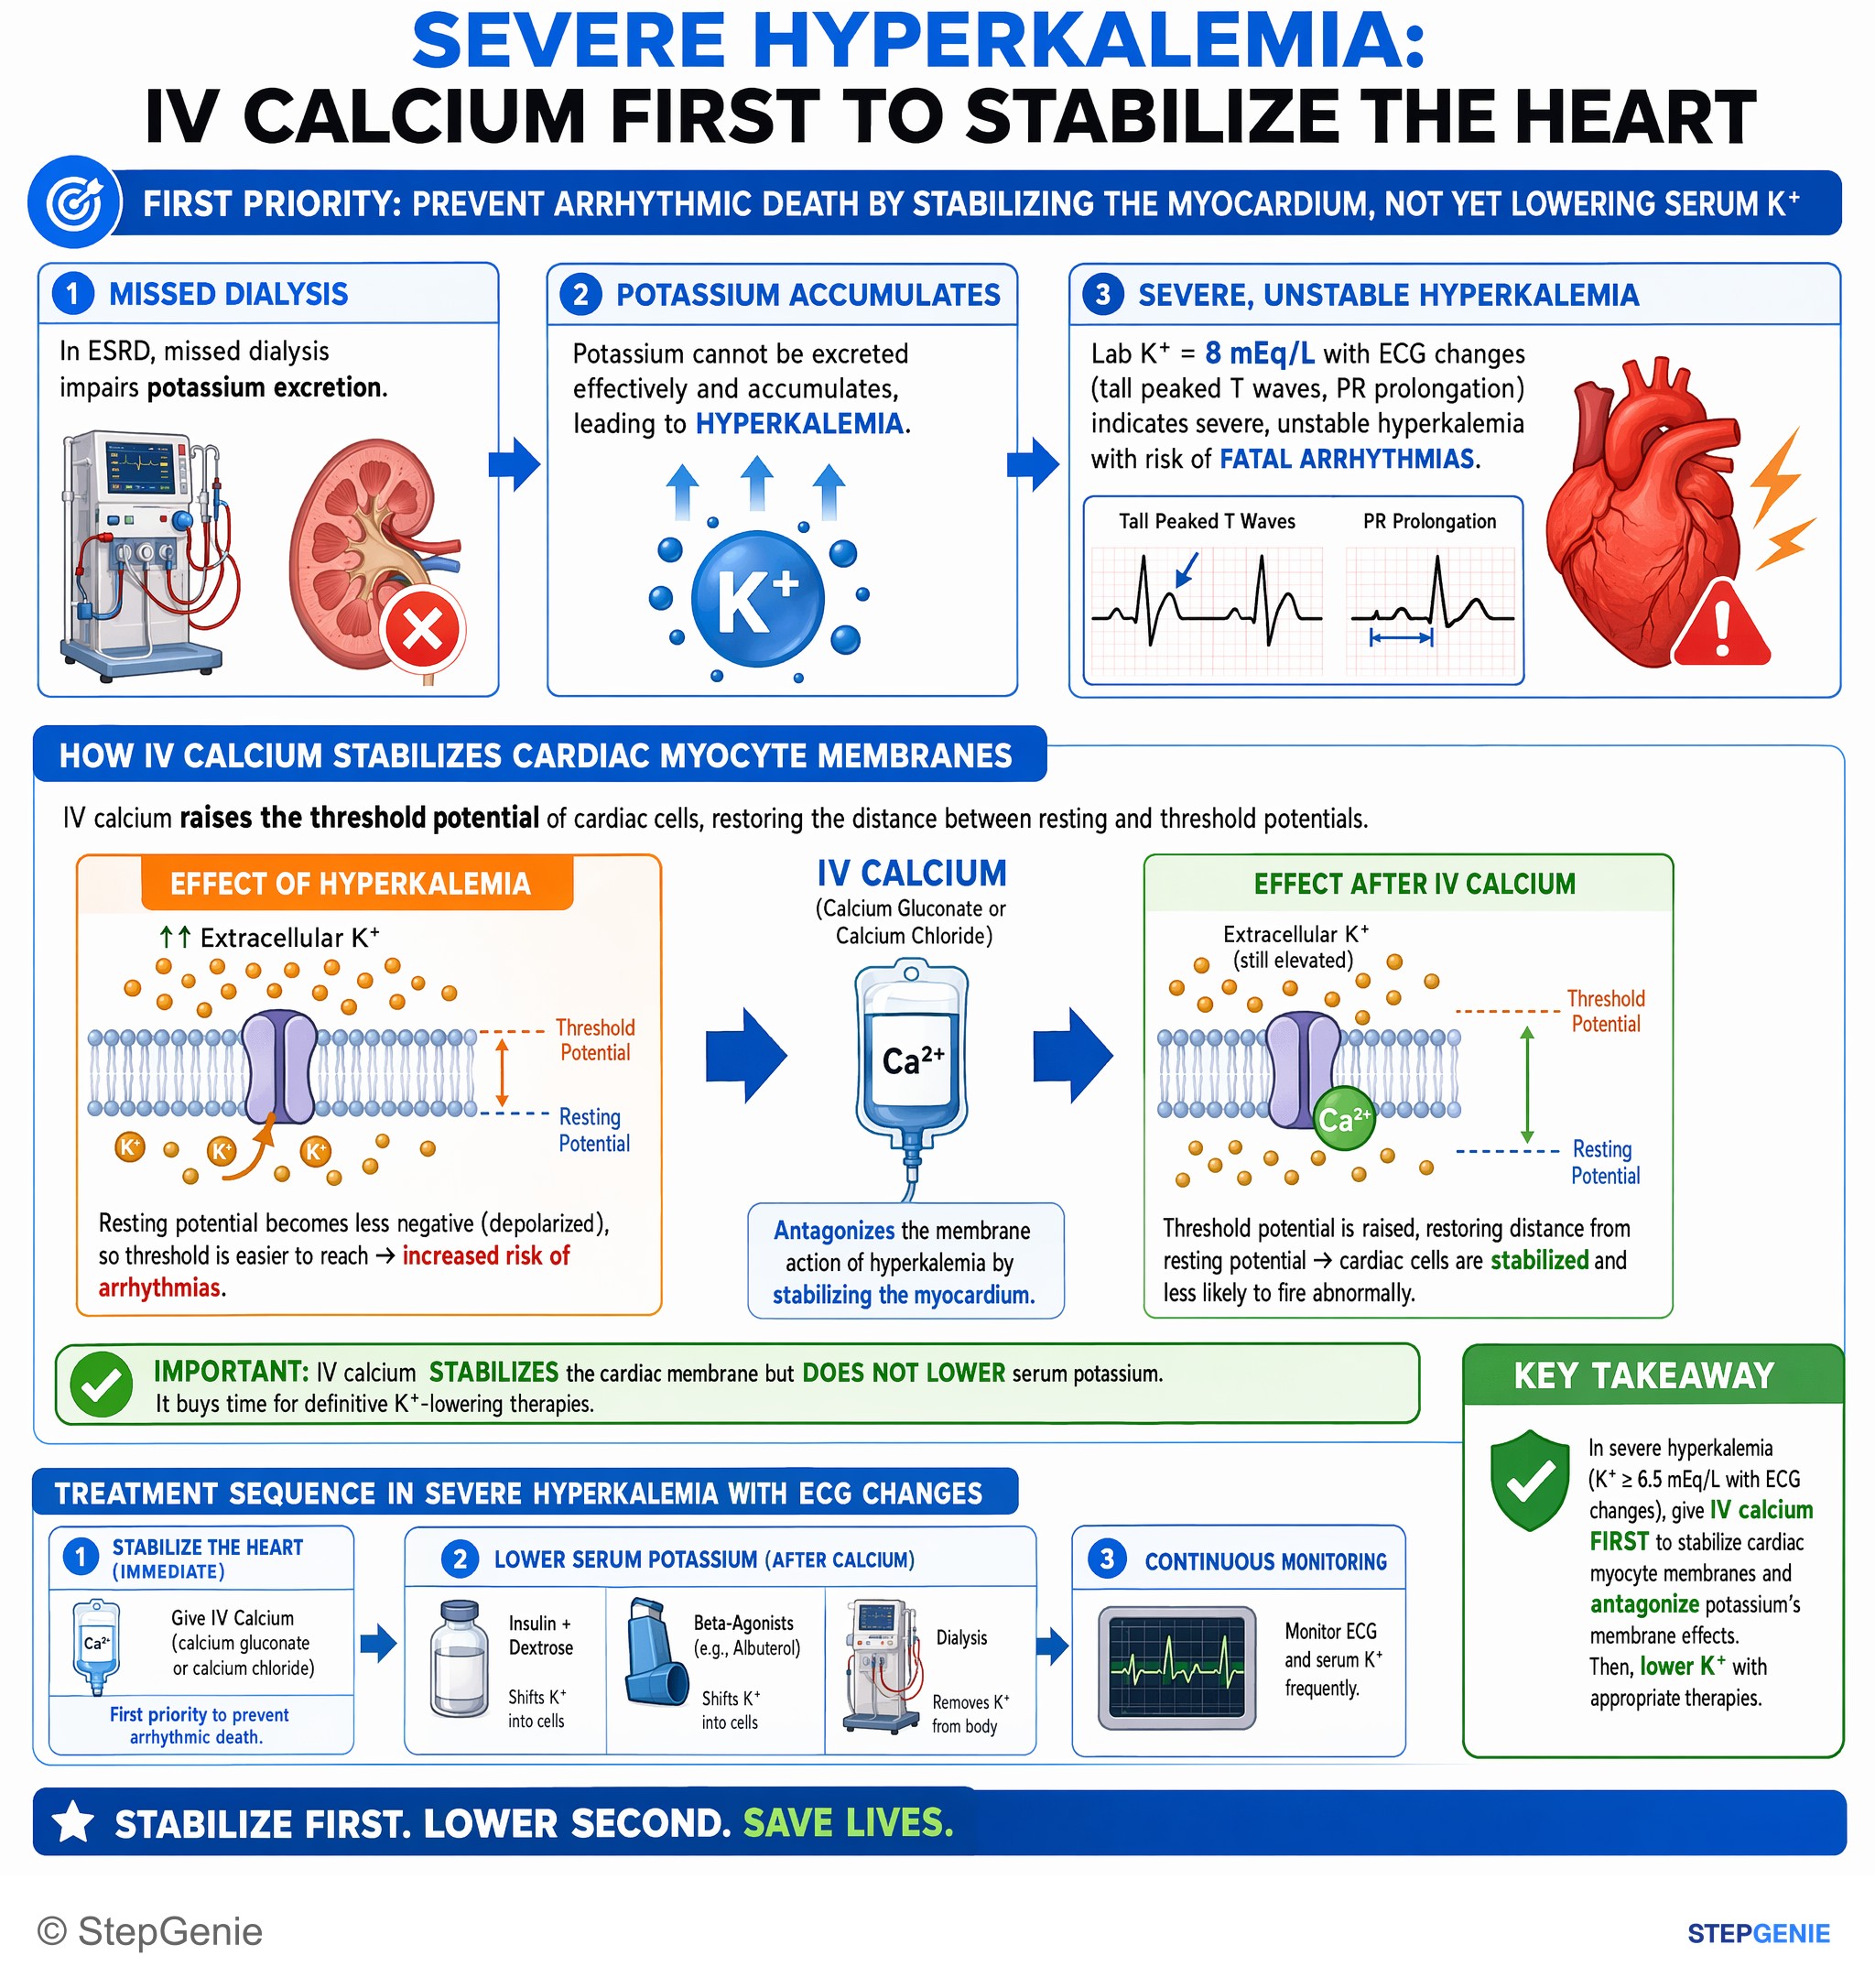
Severe hyperkalemia with ECG changes is treated first with IV calcium to stabilize cardiac myocyte membranes and antagonize potassium’s…
USMLE Step 1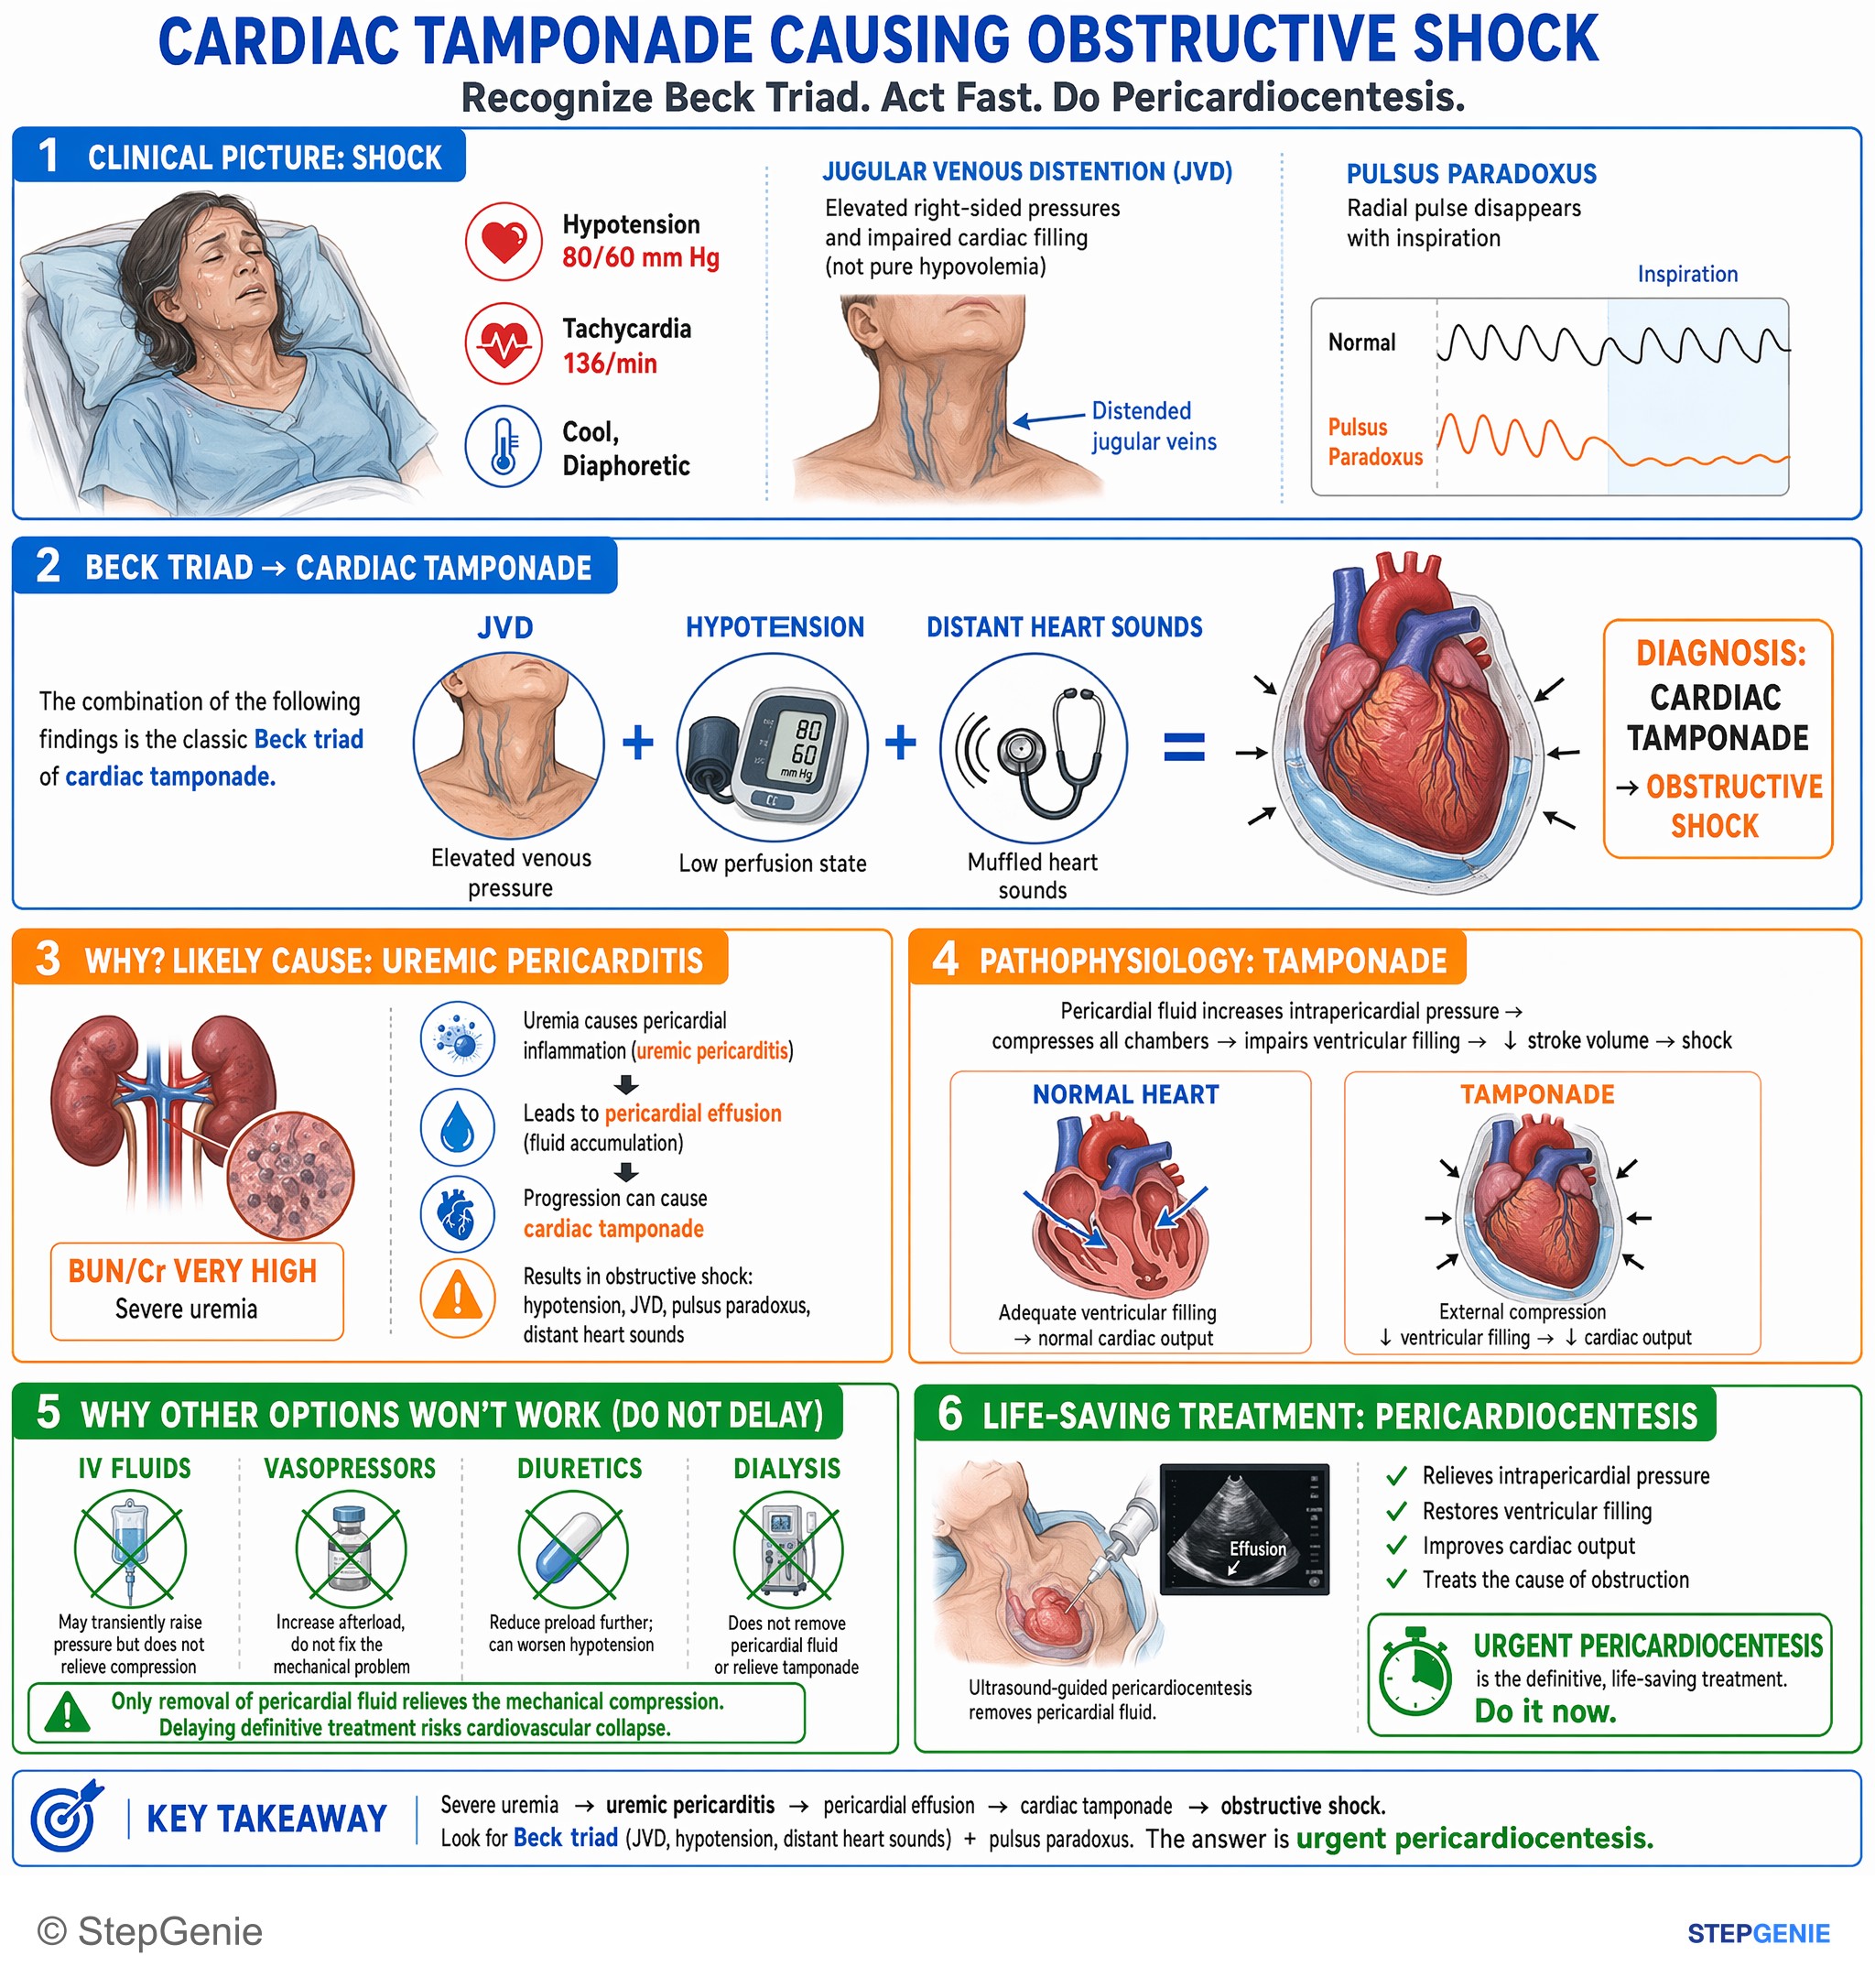
Cardiac tamponade from likely uremic pericarditis causing obstructive shock → hypotension, JVD, pulsus paradoxus, distant heart sounds →…
USMLE Step 2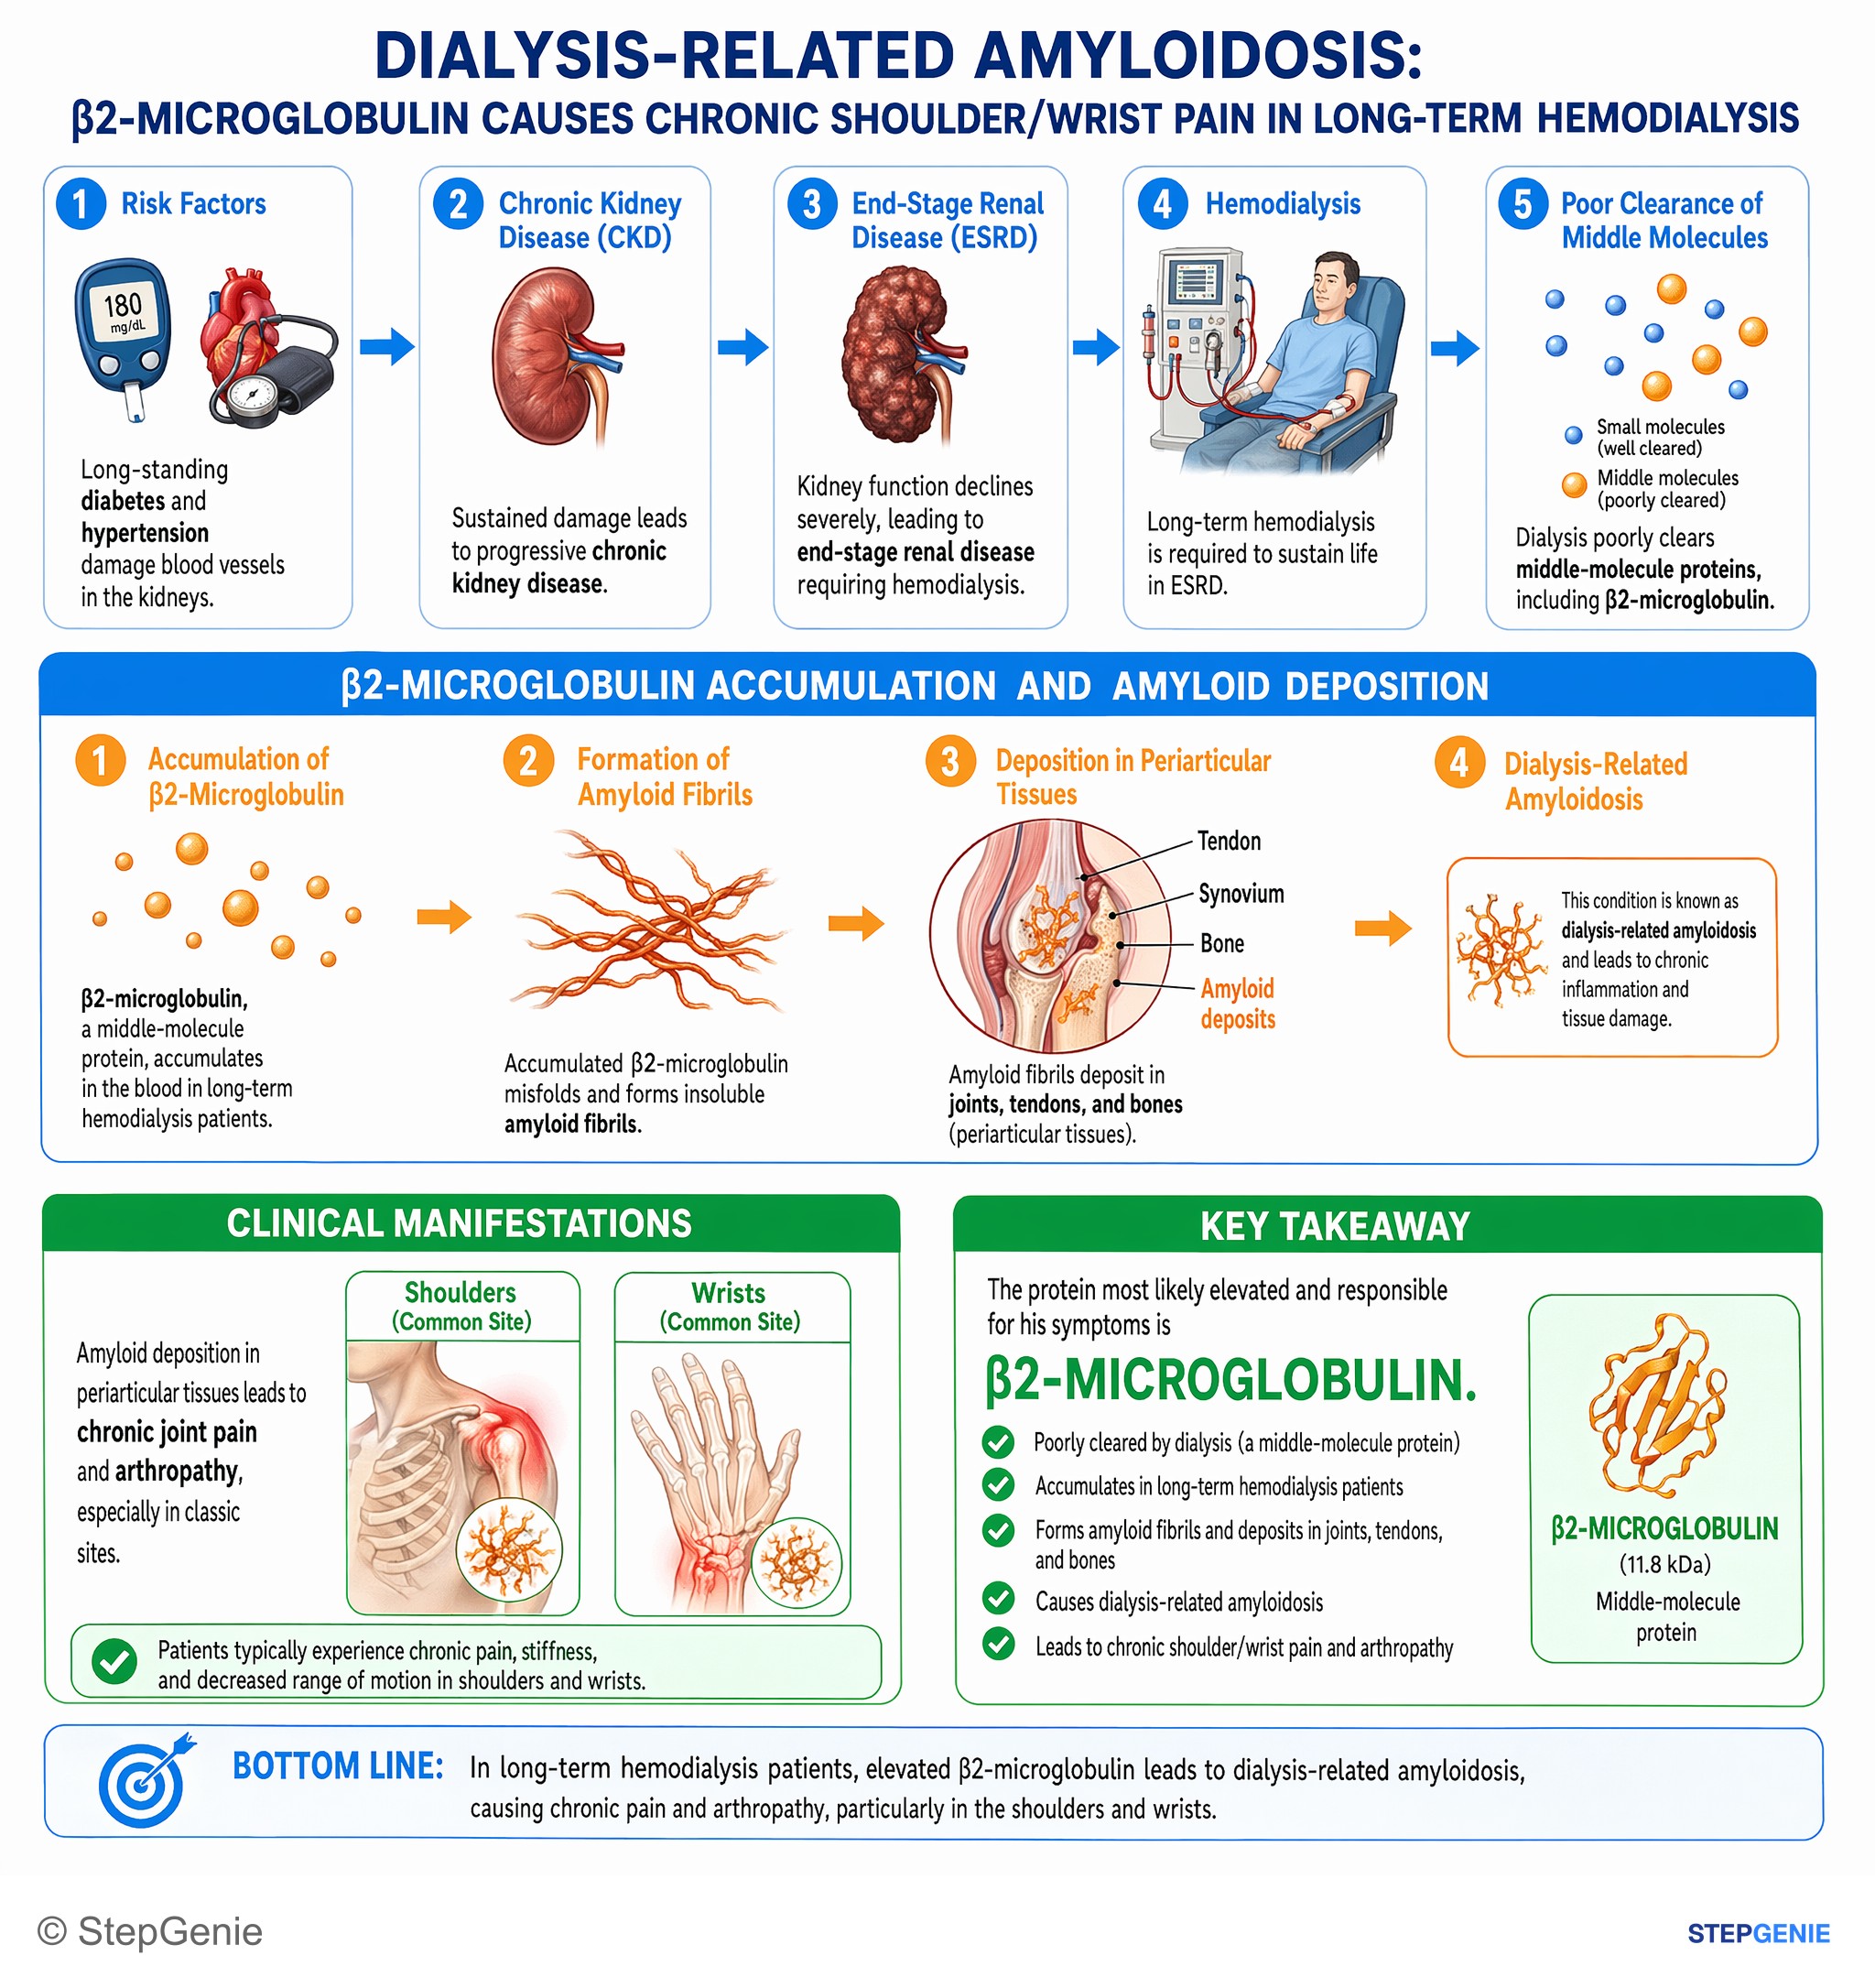
Dialysis-related amyloidosis from elevated β2-microglobulin causes chronic shoulder/wrist pain and arthropathy in long-term hemodialysis…
USMLE Step 1Frequently Asked Questions
What are the indications for urgent dialysis (AEIOU)?
AEIOU stands for acidosis, electrolyte abnormalities, intoxications, overload and uremia. Acidosis, hyperkalemia and volume overload count when they are severe and do not respond to medical treatment, while dialyzable poisonings and uremic complications such as pericarditis, encephalopathy or bleeding count once they are clinically significant. The same mnemonic applies to acute kidney injury and to decompensated chronic kidney disease.
What potassium level requires dialysis?
There is no single cutoff, but hyperkalemia with ECG changes, or potassium above about 6.5 mEq/L that persists despite medical therapy, is a common threshold. The first step is still IV calcium to stabilize the heart, followed by insulin with glucose and a beta-2 agonist to shift potassium into cells. Dialysis then removes potassium from the body, which matters most in patients who make little or no urine.
Which drugs and poisons can be removed by dialysis?
Small, water-soluble toxins that are not heavily protein bound and have a small volume of distribution are removed well, including lithium, methanol, ethylene glycol, theophylline and long-acting barbiturates such as phenobarbital. Salicylates and valproate are heavily protein bound at therapeutic levels but become removable in overdose, when binding is saturated: the EXTRIP workgroup rates salicylates dialyzable and valproate moderately dialyzable. EXTRIP also rates metformin moderately dialyzable, despite its large volume of distribution. Digoxin is only slightly dialyzable and tricyclic antidepressants are not dialyzable, so the EXTRIP workgroup recommends against dialysis for both; digoxin toxicity is treated with digoxin-specific antibody fragments.
Should dialysis be started early in acute kidney injury?
Not without a reason. In the STARRT-AKI trial of about 3,000 critically ill patients, starting within 12 hours of eligibility did not reduce 90-day mortality and caused more adverse events and more dialysis dependence among survivors. KDIGO advises starting emergently for life-threatening fluid, electrolyte or acid-base problems and otherwise judging the whole clinical picture rather than a single BUN or creatinine value.
At what GFR should a patient with CKD start dialysis?
There is no fixed GFR trigger. KDIGO advises starting dialysis when symptoms or signs of kidney failure appear, when volume or blood pressure cannot be controlled, or when nutrition or cognition deteriorates, which often happens at an eGFR between 5 and 10 mL/min/1.73 m². Kidney failure is defined as an eGFR below 15, and planning for dialysis access or a pre-emptive transplant should begin when the GFR is below 15 to 20.
What is dialysis disequilibrium syndrome?
It is a neurologic syndrome of headache, nausea, restlessness, confusion and occasionally seizures or coma during or shortly after the first dialysis sessions. Rapid urea removal lowers plasma osmolality faster than brain osmolality, so water moves into the brain and causes cerebral edema. It is prevented by making early sessions shorter and gentler, especially when the BUN is very high.