Anemia of chronic kidney disease (CKD) is one of those “quietly massive” Step 1 topics: it seems straightforward (low EPO → low RBCs), but the test loves to probe the why, the lab pattern, and the treatment nuances—especially how it overlaps with iron deficiency and anemia of chronic disease. If you can explain anemia of CKD cleanly from path to management, you’ll pick up easy points across renal, heme/onc, and pharm.
Where it fits in renal (big picture)
CKD causes systemic complications because the kidney isn’t just a filter—it’s also an endocrine organ. When functioning renal mass declines, you lose:
- Erythropoietin (EPO) production → normocytic anemia
- 1α-hydroxylation of vitamin D → hypocalcemia → secondary hyperparathyroidism → renal osteodystrophy
- Phosphate excretion → hyperphosphatemia
- Acid excretion → metabolic acidosis
- Salt/water handling → hypertension, edema
Anemia is among the earliest and most testable CKD complications, and it contributes heavily to fatigue, reduced exercise tolerance, and cardiovascular strain.
Definition (what Step expects you to say)
Anemia of CKD = a typically normocytic, normochromic anemia caused primarily by decreased EPO production from damaged kidneys (peritubular interstitial fibroblast-like cells), often compounded by inflammation-driven functional iron deficiency.
High-yield threshold: becomes more common and clinically significant as GFR declines, classically prominent in advanced CKD.
Pathophysiology (the “why” behind the labs)
1) Decreased EPO production (core mechanism)
- Site of EPO production: peritubular interstitial cells in the renal cortex/outer medulla
- CKD → interstitial fibrosis + loss of functioning renal mass → ↓ EPO
- ↓ EPO → ↓ RBC production in the bone marrow → anemia with a low reticulocyte response
Testable association: CKD anemia = low retic count (hypoproliferative marrow response).
2) Inflammation and hepcidin (why iron behaves weirdly)
CKD is a chronic inflammatory state → ↑ IL-6 → ↑ hepcidin (made by liver).
Hepcidin:
- Decreases iron absorption from gut
- Traps iron in macrophages and storage sites by inhibiting ferroportin
So even if total body iron is “okay,” the marrow can’t access it well → functional iron deficiency, overlapping with anemia of chronic disease patterns.
3) Uremia-related contributors (secondary, but fair game)
- Shortened RBC lifespan in uremic milieu
- Platelet dysfunction (uremia → impaired platelet adhesion/aggregation) can cause bleeding, indirectly worsening anemia
- Dialysis-related blood loss and frequent phlebotomy (especially in advanced CKD)
Clinical presentation (how it shows up in stems)
Symptoms of anemia (common stem clues)
- Fatigue, weakness, reduced exercise tolerance
- Dyspnea on exertion
- Lightheadedness
- Palpitations
- Headache
- Pica is not classic for CKD anemia (more iron deficiency)
CKD context clues
- History of diabetes, hypertension, polycystic kidney disease, chronic glomerulonephritis
- Uremic symptoms: nausea, pruritus, confusion (advanced)
- Signs of volume overload: edema, HTN
- Labs suggesting CKD: elevated BUN/Cr, hyperphosphatemia, metabolic acidosis
Diagnosis (what labs look like and why)
Step-style lab pattern
Anemia of CKD is typically:
- Normocytic, normochromic
- Low reticulocyte count (hypoproliferative)
- Often low serum iron with normal/low TIBC and normal/high ferritin (inflammation/hepcidin effect)
Key labs to order / interpret
- CBC + indices (MCV)
- Reticulocyte count
- Iron studies: ferritin, serum iron, TIBC, transferrin saturation (TSAT)
- B12/folate if macrocytosis or mixed picture
- Creatinine/eGFR to establish CKD severity
High-yield comparison table: CKD vs iron deficiency vs anemia of chronic disease
| Feature | Anemia of CKD | Iron deficiency anemia | Anemia of chronic disease (ACD) |
|---|---|---|---|
| MCV | Normal (often) | Low | Normal or low |
| Reticulocytes | Low | Low | Low |
| EPO | Low | High/normal | Low/normal |
| Serum iron | Low/normal | Low | Low |
| Ferritin | Normal/high | Low | High |
| TIBC | Normal/low | High | Low |
| Mechanism | ↓ EPO ± hepcidin | Low iron stores | Hepcidin-mediated iron sequestration |
Shortcut: CKD anemia behaves like EPO deficiency plus ACD-like iron restriction.
Treatment (USMLE loves mechanism + contraindications)
1) Correct iron deficiency (absolute or functional)
Even though CKD anemia is “about EPO,” iron status must be optimized before/during EPO therapy.
- Oral iron may be insufficient in advanced CKD (poor absorption, hepcidin effect, GI intolerance)
- IV iron is commonly used in dialysis or significant functional deficiency
2) Erythropoiesis-stimulating agents (ESAs): epoetin alfa, darbepoetin alfa
Mechanism: recombinant EPO analogs → stimulate erythroid progenitors in bone marrow.
Indication (Step framing):
- CKD with symptomatic anemia and inappropriately low EPO (after ensuring iron availability)
Expected response:
- Rise in reticulocytes (first), then hemoglobin
High-yield adverse effects:
- Hypertension (very commonly tested)
- Thromboembolic events (esp if Hb pushed too high)
- Rare: pure red cell aplasia due to anti-EPO antibodies (more niche)
Testable pitfall: ESAs won’t work well without adequate iron—stems may show “on epoetin but still anemic” with low TSAT/iron.
3) Transfusion (when needed, but not first-line chronically)
- For severe symptomatic anemia or acute needs
- In CKD, repeated transfusions carry risks (iron overload, volume overload, alloimmunization—important for transplant candidates)
High-yield USMLE associations & classic question patterns
Pattern 1: CKD patient with normocytic anemia + low retics
Stem: long-standing diabetes, elevated creatinine, fatigue, Hb low, MCV normal, retic low
Ask: “Most likely cause?” → decreased EPO production
Pattern 2: Iron studies look like ACD, but the kidney is the clue
Stem: CKD + low iron + high ferritin + low/normal TIBC
Interpretation: functional iron deficiency from inflammation/hepcidin + EPO deficiency
Pattern 3: Treatment question (mechanism + adverse effect)
Stem: CKD anemia treated with epoetin alfa; BP worsens
Ask: “Adverse effect?” → hypertension
or “MOA?” → stimulates erythroid progenitors via EPO receptor signaling
Pattern 4: “Why is reticulocyte count low?”
Because this is a hypoproliferative anemia: marrow isn’t being stimulated due to low EPO.
Pattern 5: Differentiating from hemolysis
CKD anemia is not primarily hemolytic:
- Expect no big LDH rise, no indirect bilirubin spike, no schistocytes unless another process exists.
First Aid cross-references (where to anchor it)
In First Aid for the USMLE Step 1, anemia of CKD typically appears across:
- Renal—Chronic kidney disease: complications include decreased EPO → normocytic anemia
- Hematology—Anemias: normocytic anemias include anemia of chronic disease and renal failure (↓EPO)
- Pharmacology—Hematopoietic drugs: epoetin alfa/darbepoetin (uses + adverse effects like hypertension)
Use these as your “mental hyperlinks”: CKD complications ↔ normocytic anemia list ↔ EPO drug page.
Rapid-fire high-yield recap (what to remember in 20 seconds)
- CKD anemia = normocytic, normochromic, low retic due to ↓ EPO
- Often overlaps with ACD-like iron restriction (↑ hepcidin → iron trapped)
- Treat with iron optimization + ESAs (epoetin/darbepoetin)
- ESA adverse effect: hypertension (plus thrombosis risk if overcorrected)
- Always interpret anemia in context: CKD clues + low retics = EPO problem until proven otherwise
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
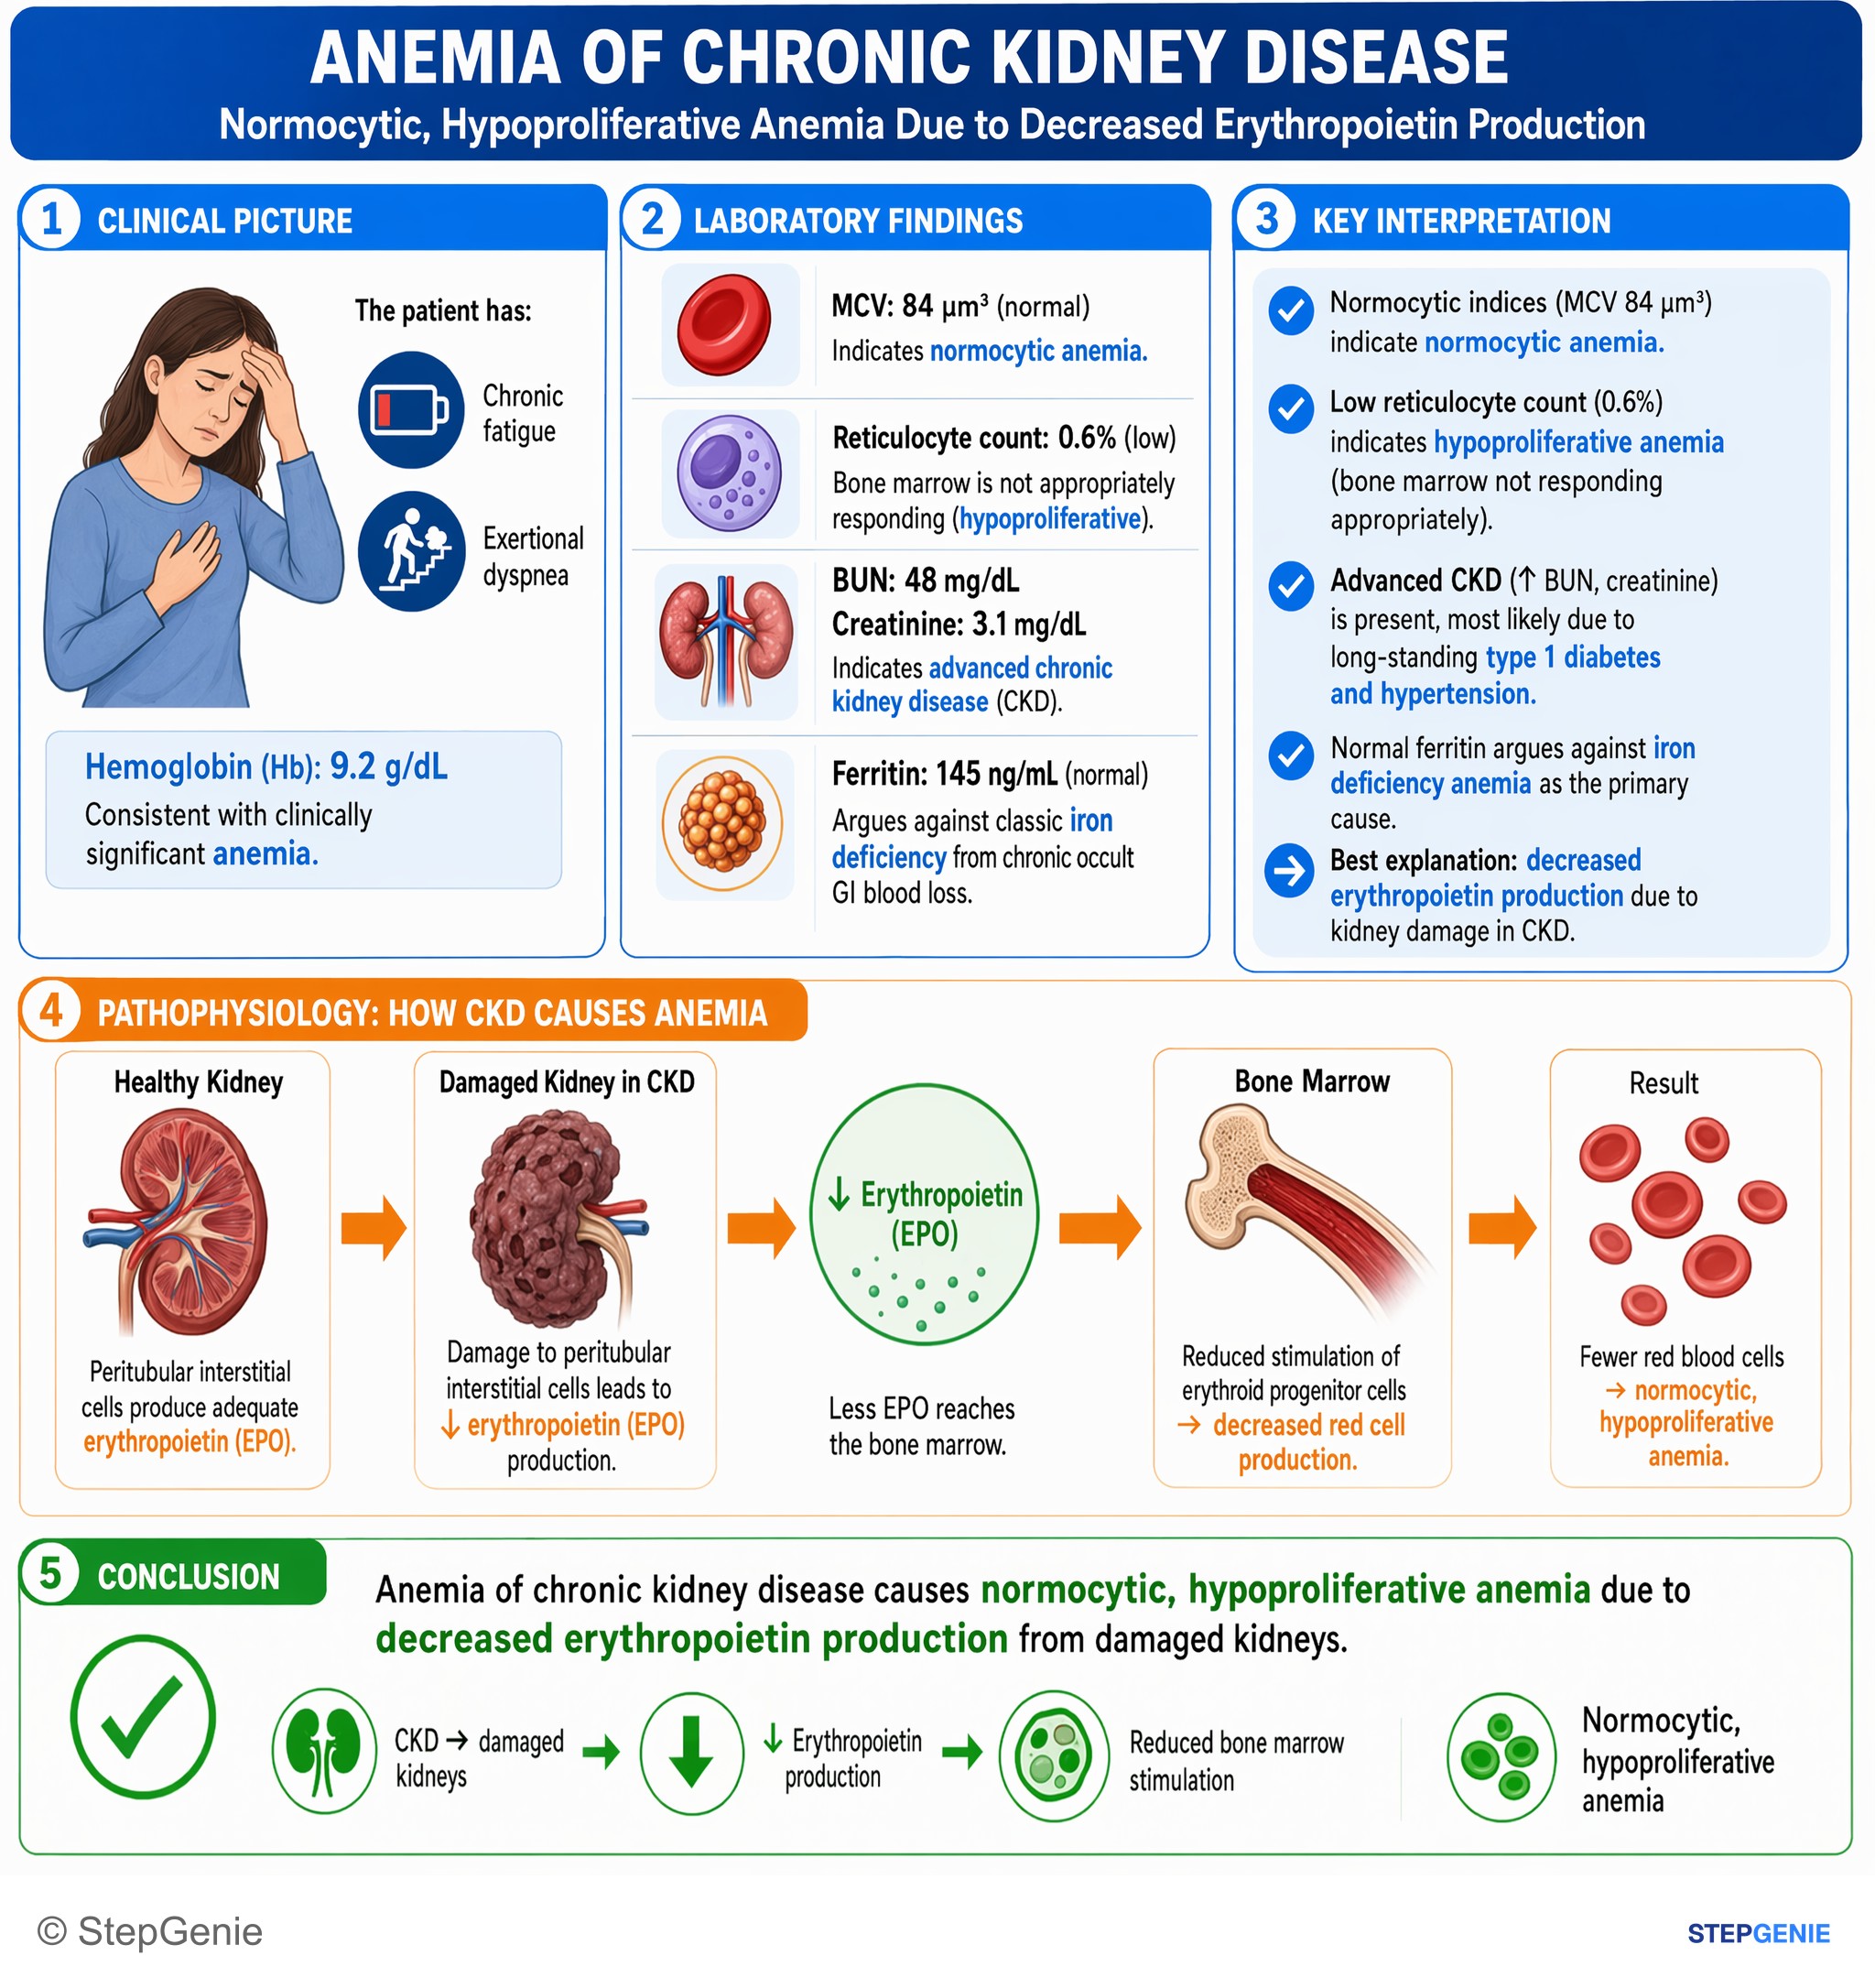
Anemia of chronic kidney disease causes normocytic, hypoproliferative anemia due to decreased erythropoietin production from damaged…
USMLE Step 2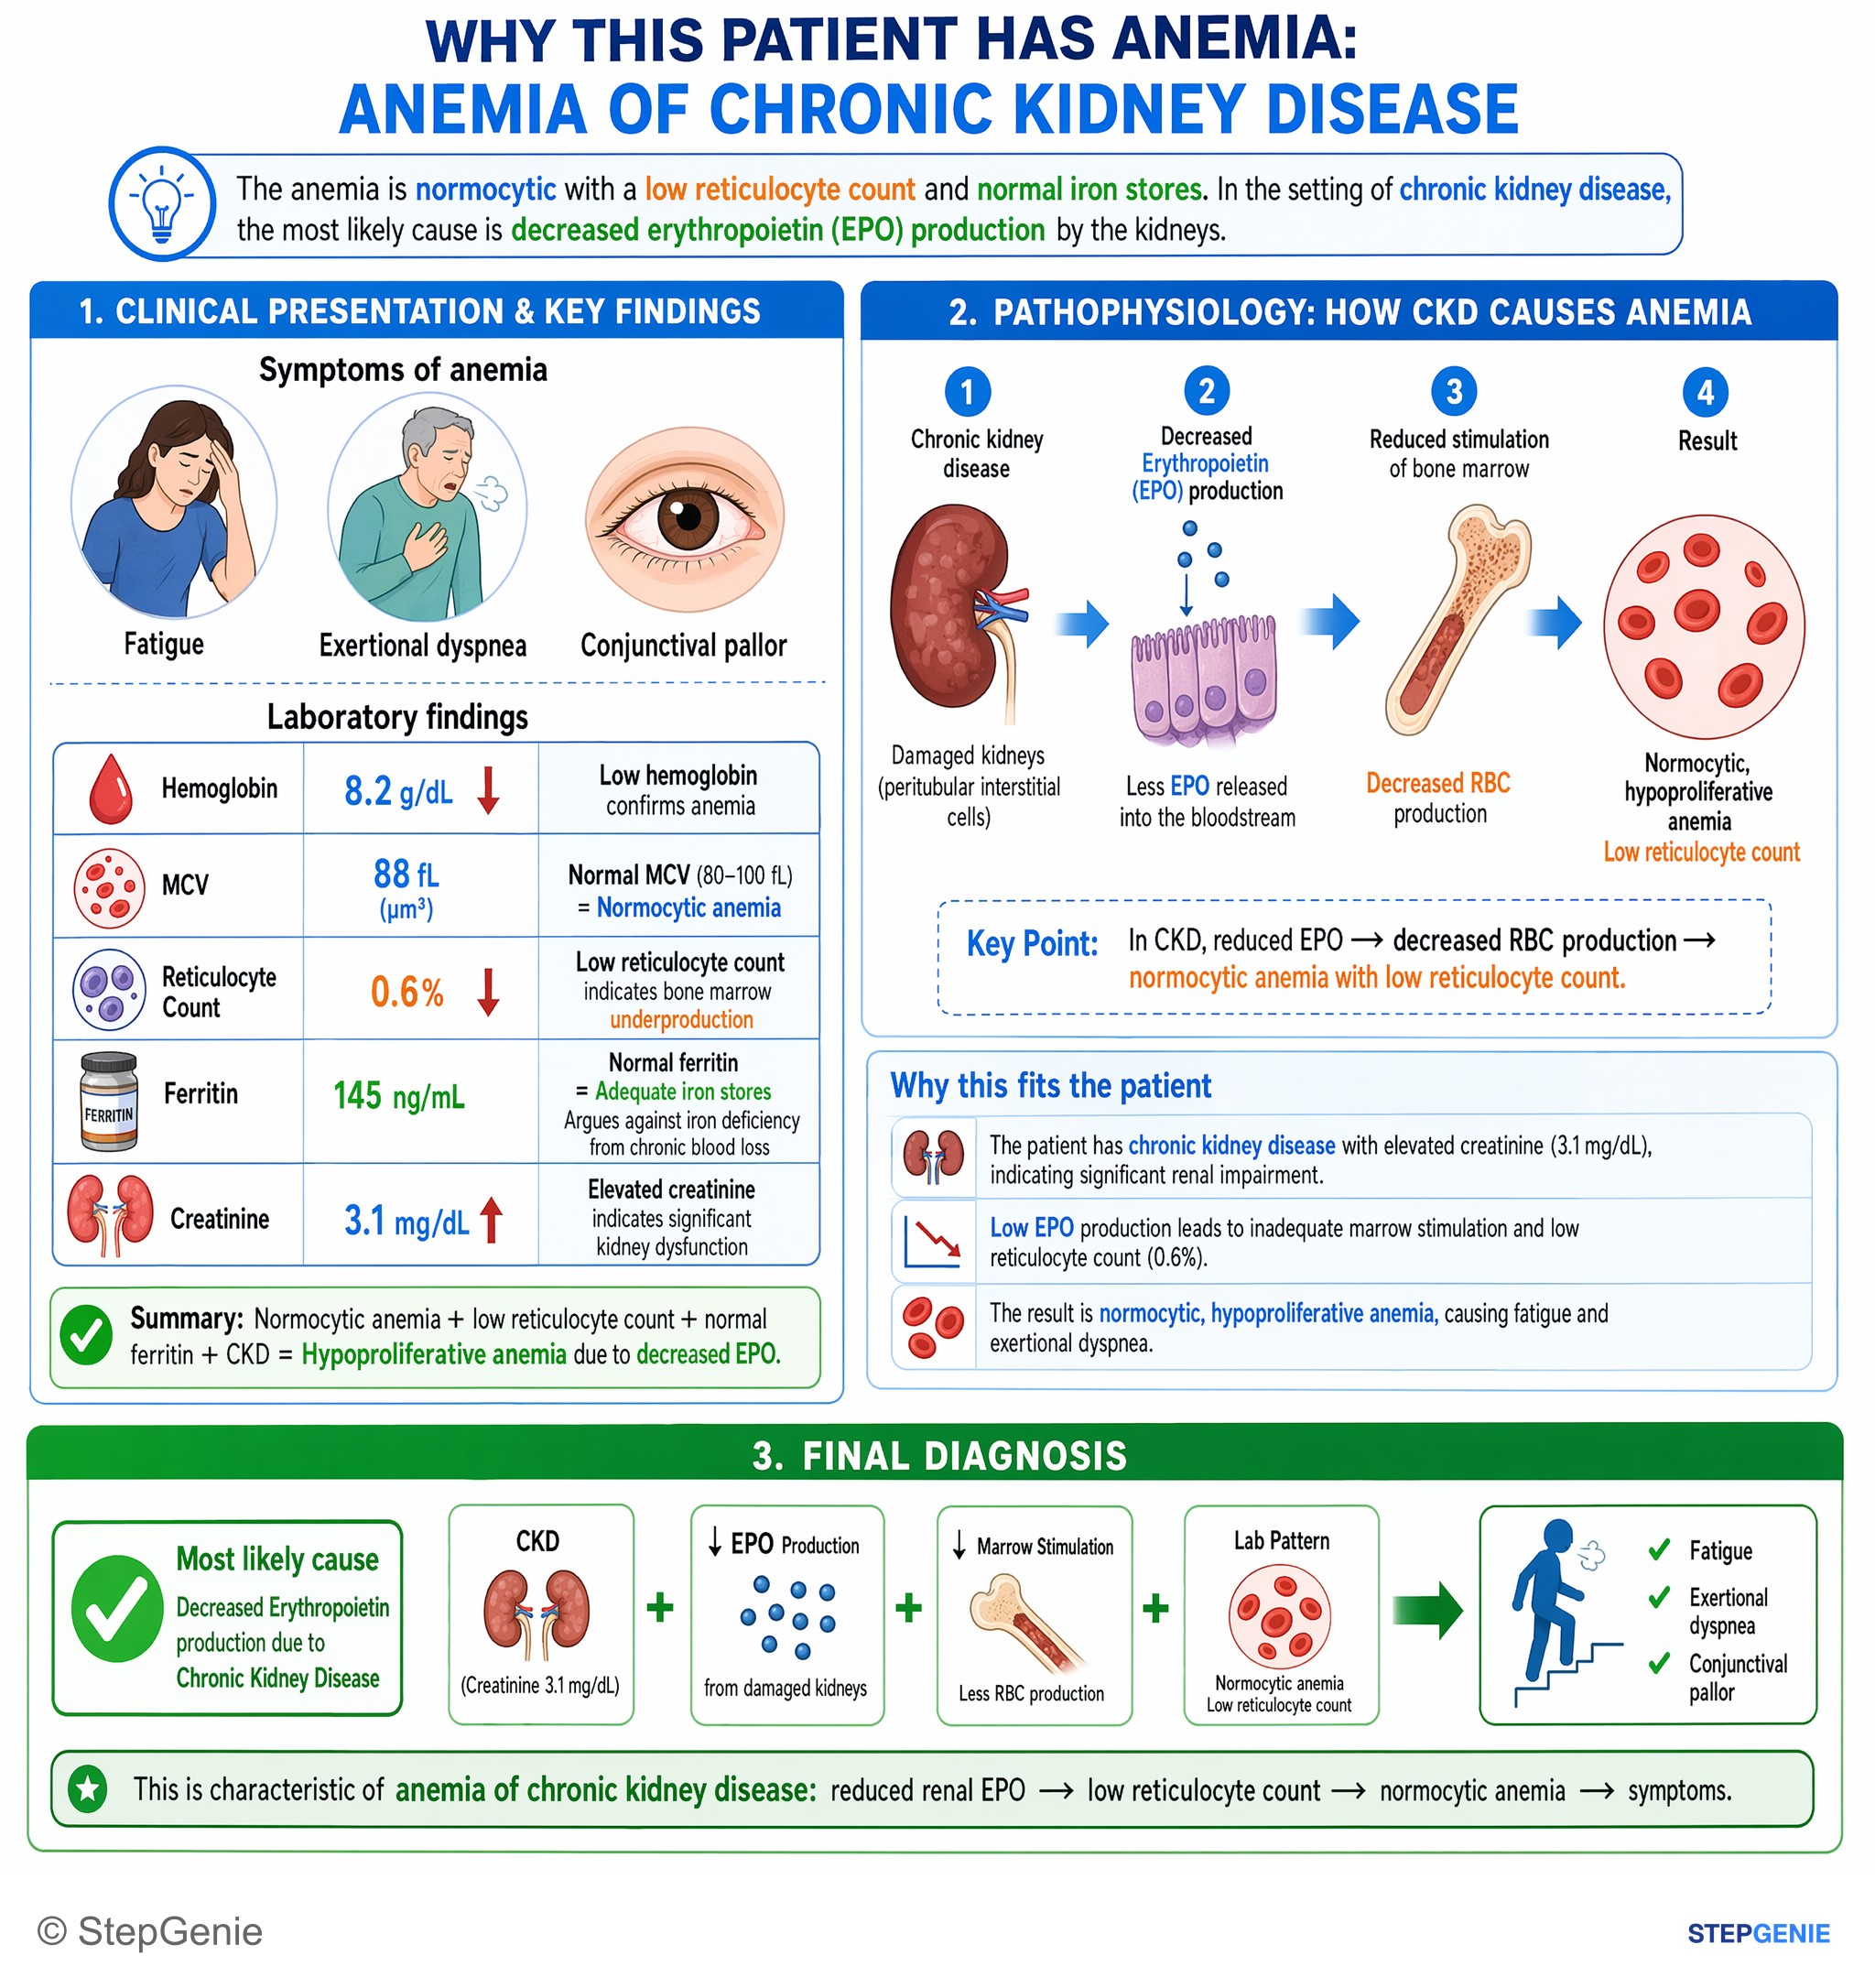
Anemia of chronic kidney disease: reduced renal EPO → low reticulocyte count, normocytic anemia causing exertional dyspnea and fatigue.
USMLE Step 1Frequently Asked Questions
Why does chronic kidney disease cause a normocytic anemia with a low reticulocyte count?
Chronic kidney disease causes a typically normocytic, normochromic anemia because damaged kidneys produce less erythropoietin. Erythropoietin is normally made by peritubular interstitial cells in the renal cortex and outer medulla, and it stimulates bone marrow red blood cell production. When renal mass declines and interstitial fibrosis develops, erythropoietin falls, so the marrow has a hypoproliferative response and the reticulocyte count is low.
How do you tell anemia of CKD from iron deficiency anemia on labs?
Anemia of CKD usually shows a normocytic anemia with a low reticulocyte count, low or normal serum iron, normal or high ferritin, and normal or low TIBC. Iron deficiency anemia more often has a low MCV, low serum iron, low ferritin, and high TIBC. A useful distinction is that CKD anemia reflects low erythropoietin with inflammation-related iron restriction, while iron deficiency reflects truly depleted iron stores.
Why can iron studies look abnormal in anemia of CKD even if total body iron is not low?
Iron studies can look abnormal in CKD because chronic inflammation increases IL-6, which raises hepatic hepcidin levels. Hepcidin decreases iron absorption from the gut and traps iron in macrophages and storage sites by inhibiting ferroportin. As a result, the marrow cannot access iron well, producing a functional iron deficiency pattern with low serum iron but often normal or high ferritin and normal or low TIBC.
What is the treatment approach for anemia of CKD, and why might epoetin not work well by itself?
Treatment starts by optimizing iron status, then using erythropoiesis-stimulating agents such as epoetin alfa or darbepoetin alfa when CKD causes symptomatic anemia with inappropriately low erythropoietin. Epoetin may not work well by itself because CKD often includes functional iron deficiency, so the marrow still lacks usable iron. Oral iron may be insufficient in advanced disease, and IV iron is commonly used in dialysis patients or those with significant functional deficiency.
What adverse effect of erythropoiesis-stimulating agents is most high-yield in CKD anemia?
Hypertension is the most commonly tested adverse effect of erythropoiesis-stimulating agents in CKD anemia. These recombinant erythropoietin analogs stimulate erythroid progenitors and should produce a rise in reticulocytes followed by hemoglobin, but they can also increase thromboembolic risk, especially if hemoglobin is pushed too high. A rarer but testable complication is pure red cell aplasia due to anti-erythropoietin antibodies.