Thiazide diuretics (hydrochlorothiazide, chlorthalidone, indapamide) block the Na⁺-Cl⁻ cotransporter (NCC) in the early distal convoluted tubule (DCT), causing a modest natriuresis. Their classic metabolic effects spell HyperGLUC: hyperglycemia, hyperlipidemia, hyperuricemia and hypercalcemia (urine calcium falls), plus hypokalemia, hypomagnesemia, hyponatremia and metabolic alkalosis. Uses: hypertension (a first-line class in the 2025 AHA/ACC guideline), mild edema, hypercalciuria with recurrent calcium stones, and nephrogenic diabetes insipidus. Two safety points: thiazides raise lithium levels, and their labels contraindicate them in people with hypersensitivity to sulfonamide-derived drugs.
The acronym: THIAZIDES
| Letter | Stands for | What to remember |
|---|---|---|
| T | Transporter: NCC in the early DCT | Blocks apical Na⁺-Cl⁻ reabsorption. Loss-of-function mutations in the same transporter cause Gitelman syndrome, a "genetic thiazide" |
| H | HyperGLUC | ↑ Glucose, ↑ Lipids (cholesterol and triglycerides), ↑ Uric acid, ↑ Calcium |
| I | Increased K⁺, H⁺ and Mg²⁺ loss | Hypokalemic metabolic alkalosis and hypomagnesemia |
| A | Antihypertensive, first line | Thiazide-type diuretic, ACE inhibitor/ARB or long-acting dihydropyridine CCB (2025 AHA/ACC) |
| Z | "Zips up" urine calcium | ↓ Urinary Ca²⁺, so they help prevent calcium stones in hypercalciuria (the opposite of loops) |
| I | Impaired urine dilution | Hyponatremia, far more often than with loop diuretics |
| D | Diabetes insipidus, nephrogenic | Paradoxically lowers urine output |
| E | Elevated lithium | Diuretics reduce renal lithium clearance and raise the risk of lithium toxicity |
| S | Sulfonamide | Contraindicated with sulfonamide-drug hypersensitivity; HCTZ can cause acute myopia and angle-closure glaucoma and raises non-melanoma skin cancer risk |
Picture the early DCT as a hallway with one NaCl door (NCC). Thiazides close that door: less NaCl is reabsorbed there, more Na⁺ and fluid flow on to the collecting duct, and calcium is held back in the body.
Mechanism: why each effect happens
- Modest diuresis. The DCT handles much less of the filtered NaCl than the thick ascending limb, so thiazides are weaker diuretics than loops. Some current labels still use the older name for this site, the "cortical diluting segment."
- Hypokalemia and metabolic alkalosis. More Na⁺ and fluid reach the collecting duct, where principal cells reabsorb Na⁺ and secrete K⁺. Volume loss adds secondary hyperaldosteronism (more K⁺ and H⁺ secretion), chloride depletion and contraction alkalosis (a fixed amount of bicarbonate in a smaller extracellular volume). More on urine chloride in the metabolic alkalosis question.
- Hypomagnesemia. Thiazides increase urinary magnesium excretion.
- Low urine calcium, mild hypercalcemia. The classic explanation is in the DCT: less Na⁺ enters the cell, so the basolateral Na⁺/Ca²⁺ exchanger moves more Ca²⁺ out into the blood and more Ca²⁺ is reabsorbed from the lumen. Mouse micropuncture work (Nijenhuis 2005) points to the proximal tubule instead: after the initial natriuresis, compensatory proximal Na⁺ reabsorption carries more Ca²⁺ with it passively, while distal Ca²⁺ reabsorption appeared unchanged. Either way, marked hypercalcemia on a thiazide may be hidden hyperparathyroidism.
- Hyponatremia. Thiazides reduce the kidney's diluting capacity while increasing sodium loss; volume depletion then triggers nonosmotic vasopressin release, and hypokalemia enhances it. Older adults are especially susceptible, and the effect can last up to 2 weeks after stopping. Loop diuretics cause hyponatremia much less often. (The math is in free water clearance.)
- Hyperuricemia and gout. Hyperuricemia may occur, and acute gout may be precipitated.
- Hyperglycemia and lipids. Latent diabetes can become manifest; cholesterol (mostly LDL) and triglycerides rise slightly. These are generally not reasons to avoid the drug.
Thiazides vs loop diuretics: calcium is the twist
| Feature | Thiazides | Loop diuretics |
|---|---|---|
| Site and target | Early DCT, NCC | Thick ascending limb, NKCC2 |
| Diuretic strength | Moderate | Strong |
| Urine calcium | ↓ (stone prevention) | ↑ ("loops lose calcium") |
| Hyponatremia | A common cause | Much less common |
| K⁺ and Mg²⁺ | ↓ | ↓ |
| Uric acid | ↑ | ↑ |
| Genetic look-alike | Gitelman syndrome (low urine calcium) | Bartter syndrome |
Gitelman syndrome is usually caused by SLC12A3 mutations (autosomal recessive) and gives hypokalemia, hypomagnesemia, low urinary calcium and metabolic alkalosis, exactly what a thiazide does. Loops are covered in the loop diuretics memory palace.
Uses, and what the current evidence says
Hypertension
- The 2025 AHA/ACC high blood pressure guideline keeps thiazide-type diuretics, long-acting dihydropyridine CCBs and ACE inhibitors/ARBs as first-line drugs, favors once-daily dosing and single-pill combinations, and sets an overall treatment goal below 130/80 mm Hg for all adults.
- Chlorthalidone vs hydrochlorothiazide. Merck prefers chlorthalidone and indapamide over HCTZ for their higher potency and longer duration of action (chlorthalidone half-life about 40 hours vs 5.6-14.8 hours for HCTZ). But in the Diuretic Comparison Project (NEJM 2022; 13,523 veterans aged 65 or older), switching to chlorthalidone did not lower major cardiovascular events or non-cancer deaths (10.4% vs 10.0%; HR 1.04) and caused more hypokalemia (6.0% vs 4.4%).
- Low GFR. Thiazides are classically taught to lose effect at low GFR, but Merck notes chlorthalidone improved blood pressure in patients with GFR below 30 mL/min (the CLICK trial in stage 4 CKD).
- All non-potassium-sparing diuretics cause significant potassium loss, so Merck advises measuring serum potassium monthly until it stabilizes.
Edema
HCTZ is labeled as adjunctive therapy for edema from heart failure, cirrhosis and corticosteroid or estrogen therapy; loops are the stronger choice when large fluid removal is needed.
Recurrent calcium stones with hypercalciuria
- The AUA guideline (2014, validity confirmed 2019): clinicians should offer thiazide diuretics to patients with high or relatively high urine calcium and recurrent calcium stones (Standard; Grade B).
- The evidence is now contested. In the double-blind NOSTONE trial (NEJM 2023; 416 patients with recurrent calcium-containing stones, enrolled without a high-urine-calcium requirement), recurrence with HCTZ 12.5, 25 or 50 mg daily did not differ substantially from placebo (no dose-response), and HCTZ caused more hypokalemia, gout and new-onset diabetes. For the exam, recurrent calcium stones + high urine calcium = thiazide remains the expected answer. See the kidney stone types.
Nephrogenic diabetes insipidus
Merck now calls this arginine vasopressin resistance (AVP-R). Thiazides (e.g., HCTZ 25 mg once or twice daily) paradoxically reduce urine output by reducing water delivery to the vasopressin-sensitive collecting tubules, alongside adequate free water and a low-salt, low-protein diet; NSAIDs or amiloride can also help. Lithium trap: if the cause is lithium, remember that thiazides raise lithium levels. Compare the types in central vs nephrogenic DI.
If you see this, think thiazide
| Stem clue | Thiazide link |
|---|---|
| New BP pill; now K⁺ 2.9 mEq/L and high bicarbonate | Hypokalemic metabolic alkalosis |
| Painful swollen big toe weeks after a new diuretic | Hyperuricemia precipitating gout |
| Recurrent calcium oxalate stones and high 24-hour urine calcium | Thiazide lowers urine calcium |
| Older adult on HCTZ with confusion and Na⁺ 122 mEq/L | Thiazide-induced hyponatremia |
| Calcium creeps up after starting a thiazide and stays high | Look for hidden primary hyperparathyroidism |
| Lithium patient with new tremor and ataxia after a diuretic is added | Lithium toxicity from reduced lithium clearance |
| Dilute polyuria that does not respond to desmopressin improves with a "diuretic" | Nephrogenic DI (AVP resistance) responding to a thiazide |
| Young adult, no drugs, low K⁺ and Mg²⁺, alkalosis, low urine calcium | Gitelman syndrome |
Practice question
A 61-year-old woman with hypertension returns 6 weeks after a second antihypertensive was added. She feels well. Serum: Na⁺ 132 mEq/L, K⁺ 3.2 mEq/L, Cl⁻ 95 mEq/L, HCO₃⁻ 31 mEq/L, calcium 10.6 mg/dL (previously 9.8 mg/dL), uric acid 8.1 mg/dL and fasting glucose 118 mg/dL. Her 24-hour urine calcium is low. Which drug was most likely added?
A. Amlodipine B. Furosemide C. Hydrochlorothiazide D. Lisinopril E. Spironolactone
Answer: C. Low K⁺, metabolic alkalosis, mild hyponatremia, a rise in serum calcium with low urine calcium, higher uric acid and higher glucose are the full thiazide fingerprint: hypokalemic alkalosis plus HyperGLUC.
- A: amlodipine, a dihydropyridine CCB, does not produce this electrolyte pattern.
- B: furosemide also causes hypokalemia and metabolic alkalosis, but it increases urinary calcium, so serum calcium would not rise with low urine calcium.
- D: lisinopril lowers aldosterone, so it tends to raise potassium, not cause hypokalemic alkalosis.
- E: spironolactone is potassium-sparing; it tends toward hyperkalemia and metabolic acidosis.
Key takeaways
- Site: NCC in the early DCT (Gitelman syndrome is the genetic version).
- HyperGLUC: ↑ glucose, lipids, uric acid, calcium; hypo-K, hypo-Mg, hypo-Na and metabolic alkalosis.
- Calcium: thiazides lower urine calcium; loops raise it.
- Uses: hypertension (first-line class in the 2025 AHA/ACC guideline), mild edema, hypercalciuric calcium stones (AUA; NOSTONE questions the benefit), nephrogenic DI; osteoporosis is another off-label use.
- Chlorthalidone vs HCTZ: longer acting, but no better cardiovascular outcomes and more hypokalemia in the Diuretic Comparison Project.
- Interactions and warnings: ↑ lithium levels; sulfonamide hypersensitivity; acute angle-closure glaucoma; non-melanoma skin cancer with HCTZ.
- Hyponatremia is a thiazide problem far more than a loop problem.
Sources
- Thiazide Diuretics — StatPearls, NCBI Bookshelf (2025)
- Hydrochlorothiazide Tablets: prescribing information — DailyMed, NLM (2026)
- Furosemide Tablets: prescribing information — DailyMed, NLM (2026)
- Medications for Hypertension — Merck Manual Professional Edition (2025)
- New in Clinical Guidance: High Blood Pressure Focus of New ACC/AHA Guideline — American College of Cardiology (2025)
- Chlorthalidone vs. Hydrochlorothiazide for Hypertension-Cardiovascular Events — N Engl J Med, PubMed (2022)
- Hydrochlorothiazide and Prevention of Kidney-Stone Recurrence — N Engl J Med, PubMed (2023)
- Medical Management of Kidney Stones: AUA Guideline — American Urological Association (2014, reviewed 2019)
- Arginine Vasopressin Resistance — Merck Manual Professional Edition (2026)
- Hyponatremia — Merck Manual Professional Edition (2025)
- Gitelman Syndrome — StatPearls, NCBI Bookshelf (2024)
- Enhanced passive Ca2+ reabsorption and reduced Mg2+ channel abundance explains thiazide-induced hypocalciuria and hypomagnesemia — J Clin Invest, PubMed (2005)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
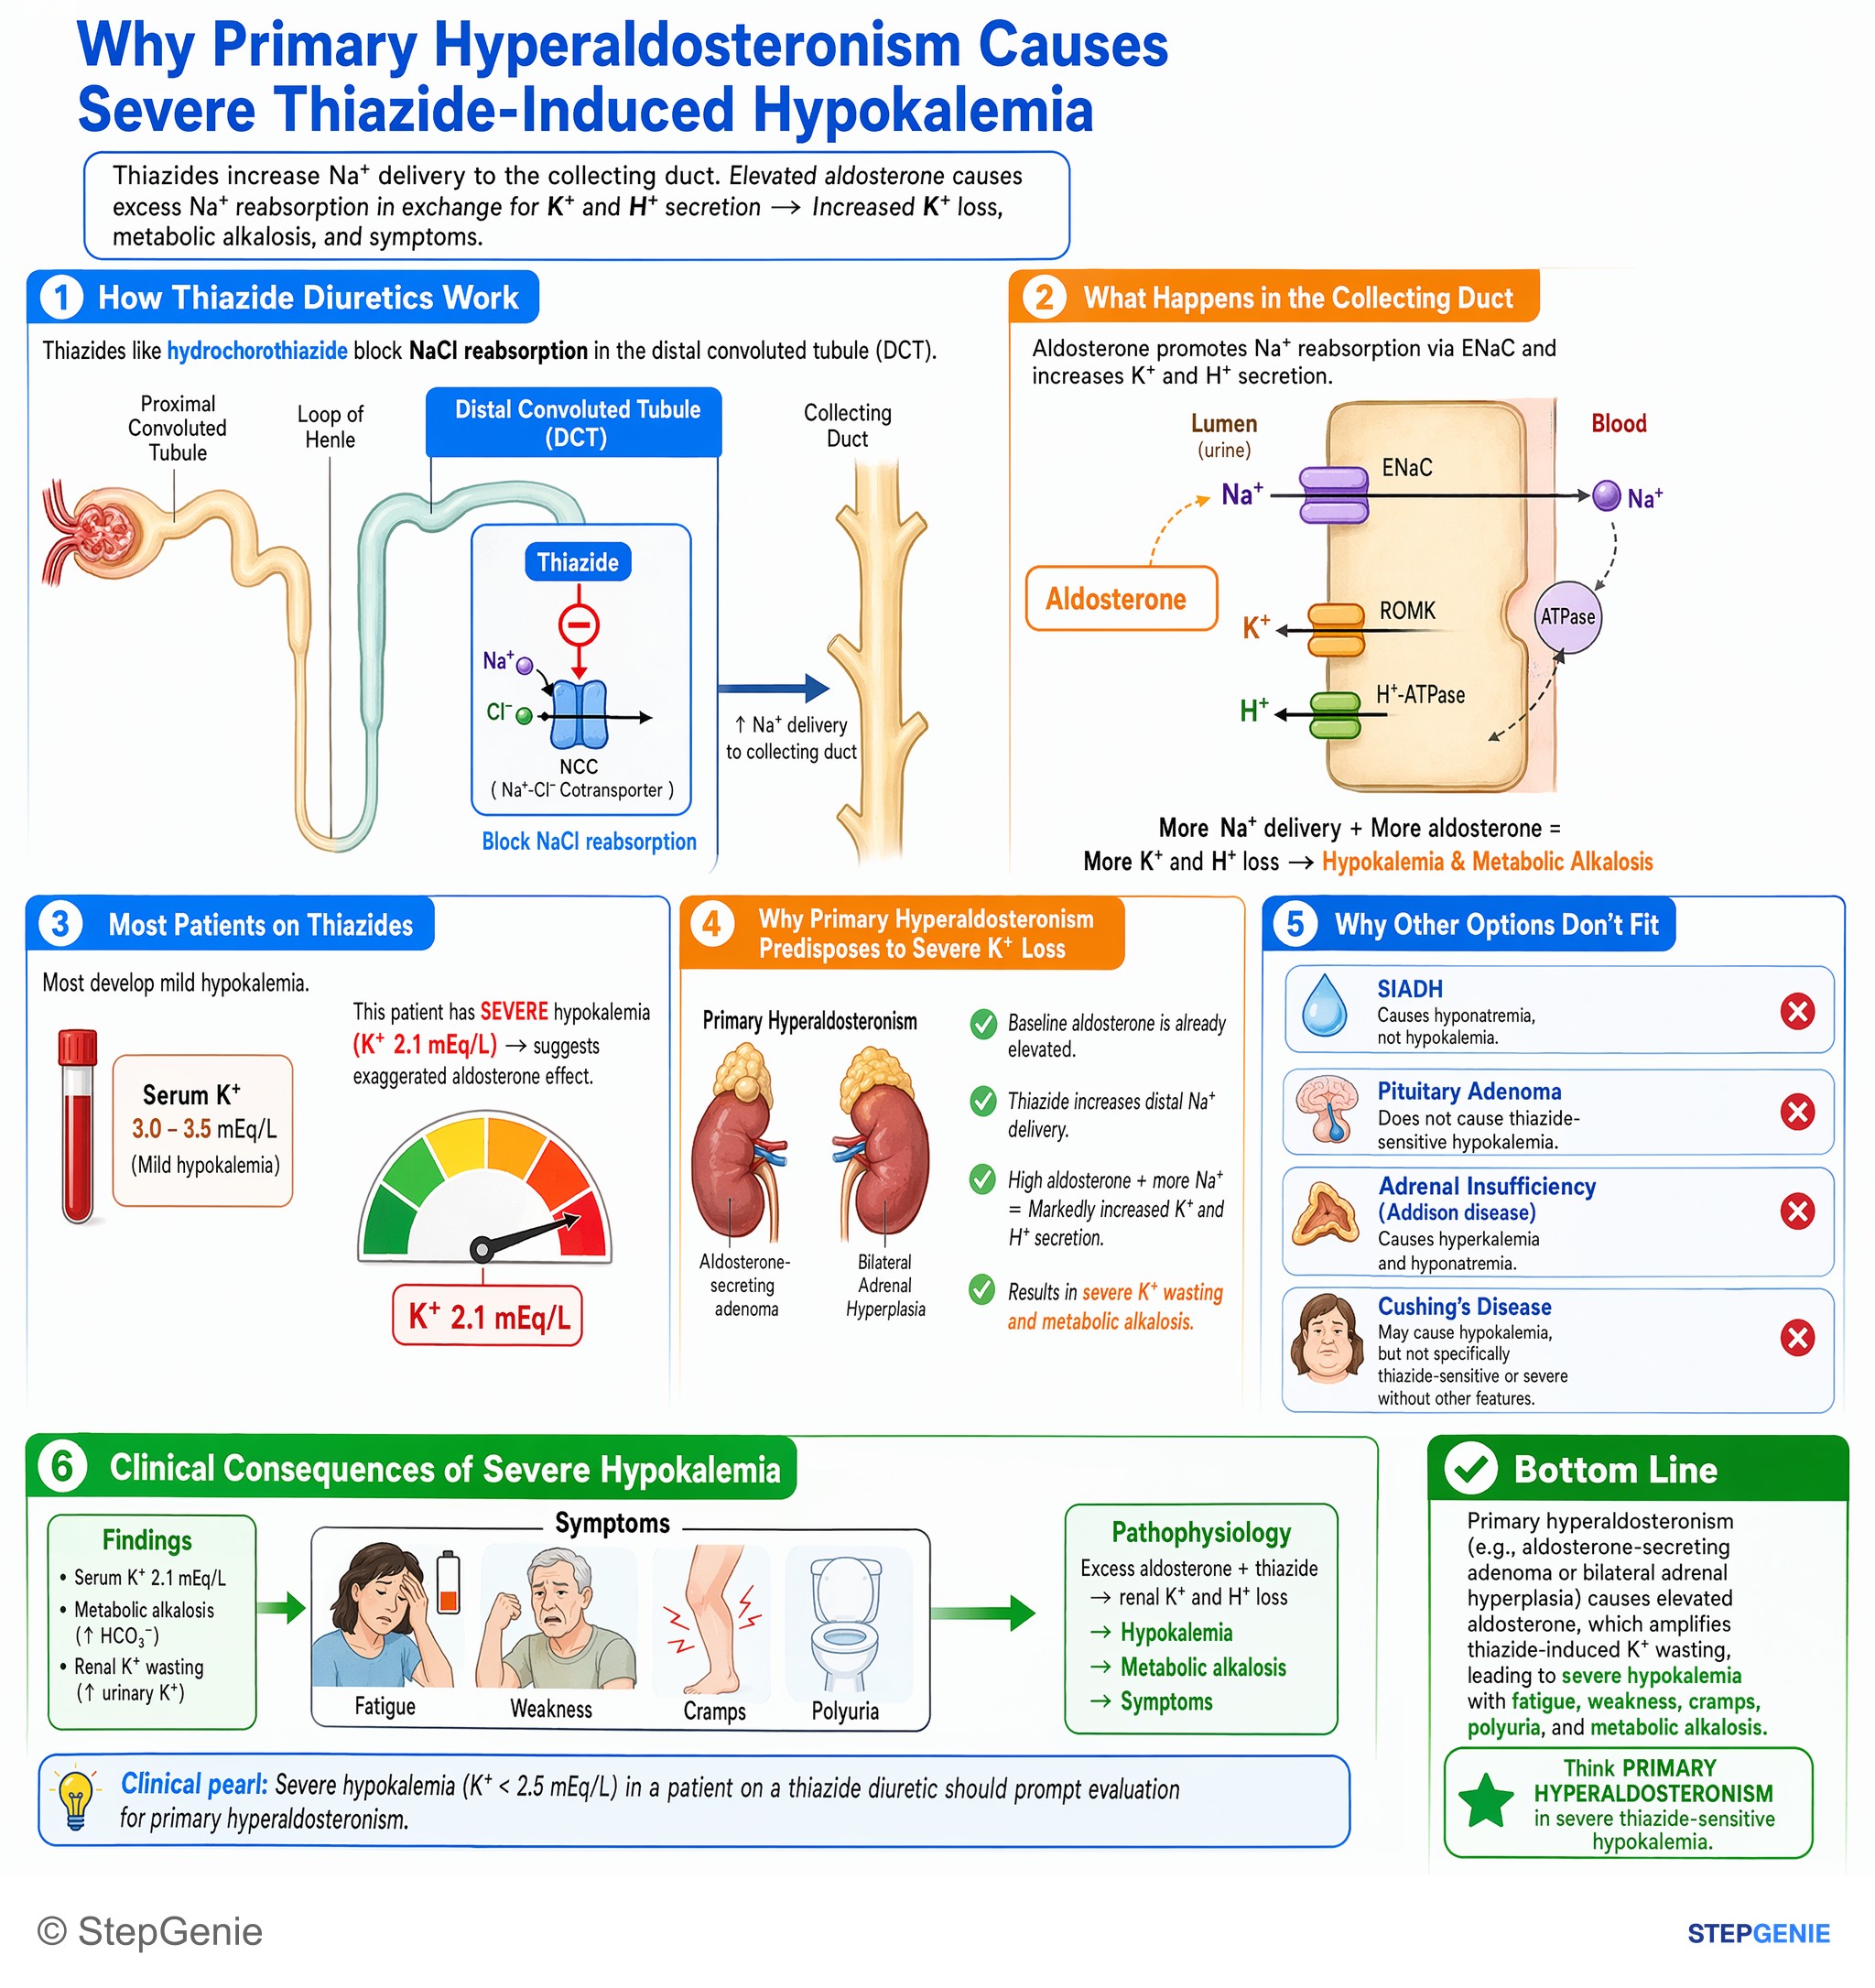
Primary hyperaldosteronism predisposes to severe thiazide-induced hypokalemia with fatigue, weakness, cramps, and polyuria due to renal K+…
USMLE Step 1Frequently Asked Questions
What is the HyperGLUC mnemonic for thiazides?
HyperGLUC lists the four values thiazide diuretics push up: hyperglycemia, hyperlipidemia (cholesterol and triglycerides), hyperuricemia and hypercalcemia. Pair it with the values they push down: hypokalemia, hypomagnesemia and hyponatremia, plus a metabolic alkalosis. Together these make the classic thiazide lab fingerprint, for example a patient on a new blood pressure pill with low potassium, high bicarbonate, a gout flare or a slowly rising calcium.
Where do thiazide diuretics act and what transporter do they block?
Thiazides act in the early distal convoluted tubule, where they block the apical sodium-chloride cotransporter (NCC). Some drug labels still use the older name for this region, the cortical diluting segment. Because the distal tubule reabsorbs much less filtered salt than the thick ascending limb, thiazides are weaker diuretics than loop diuretics. Inherited loss of the same transporter, usually from SLC12A3 mutations, causes Gitelman syndrome, which mimics chronic thiazide use.
Why do thiazides lower urinary calcium and help prevent kidney stones?
Thiazides increase calcium reabsorption, so less calcium reaches the urine and serum calcium can rise slightly. The classic explanation is that blocking sodium entry into the distal tubule cell drives more calcium out through the basolateral sodium-calcium exchanger; mouse studies point instead to increased passive calcium reabsorption in the proximal tubule after the initial volume loss. The AUA advises thiazides for recurrent calcium stones with high urine calcium, although the 2023 NOSTONE trial, which did not require high urine calcium, found no clear reduction in recurrence with hydrochlorothiazide.
Why do thiazides cause hypokalemic metabolic alkalosis?
Blocking salt reabsorption in the distal convoluted tubule sends more sodium and fluid to the collecting duct, where sodium is reabsorbed in exchange for potassium secretion. The resulting volume depletion causes secondary hyperaldosteronism, which increases potassium and hydrogen ion secretion. Chloride depletion and contraction alkalosis, a fixed amount of bicarbonate in a smaller extracellular volume, add to the rise in pH. Magnesium is lost in the urine as well.
Why do thiazides cause hyponatremia more often than loop diuretics?
Thiazides block salt reabsorption in a diluting segment of the nephron, which reduces the kidney's ability to make dilute urine, while also increasing sodium loss. Volume depletion then triggers vasopressin release, and hypokalemia enhances it, so water is retained. Older adults are especially susceptible, and the effect can last up to two weeks after stopping. Loop diuretics cause hyponatremia much less often.
Is chlorthalidone better than hydrochlorothiazide?
Chlorthalidone is more potent and much longer acting, with a half-life of about 40 hours compared with about 6 to 15 hours for hydrochlorothiazide, and Merck prefers it or indapamide for hypertension. However, the Diuretic Comparison Project, a pragmatic trial of 13,523 veterans aged 65 or older, found no significant difference in major cardiovascular events between the two drugs, and hypokalemia was more common with chlorthalidone (6.0% vs 4.4%).