Prerenal AKI means the kidneys are underperfused but the tubules still work, so they hold on to sodium and water: BUN:Cr >20:1, FENa <1%, urine sodium <20 mEq/L, urine osmolality >500 mOsm/kg, and a bland sediment or hyaline casts, and creatinine improves with IV fluids. Intrinsic AKI, most often acute tubular necrosis (ATN), damages the tubules, so they waste sodium and cannot concentrate urine: FENa >2%, urine sodium >40 mEq/L, urine osmolality usually <350, BUN:Cr 10–15:1, and muddy brown granular casts. Postrenal AKI is obstruction (benign prostatic hyperplasia is the most common cause in older men), diagnosed with a bladder scan, catheter and renal ultrasound for hydronephrosis, not with urine indices. On diuretics, FENa is unreliable; use FEUrea: <35% prerenal, >50% intrinsic.
The Q-bank vignette
A 74-year-old woman with hypertension treated with hydrochlorothiazide and lisinopril comes to the emergency department after 4 days of watery diarrhea and poor oral intake. She is lightheaded when she stands. Pulse is 108/min and blood pressure 96/58 mm Hg, falling further on standing; her mucous membranes are dry. The bladder is not palpable, and a bladder scan shows a post-void residual of 40 mL.
| Serum | Value | Urine | Value |
|---|---|---|---|
| Sodium | 134 mEq/L | Sodium | 70 mEq/L |
| Potassium | 5.1 mEq/L | Creatinine | 55 mg/dL |
| BUN | 58 mg/dL | Urea nitrogen | 330 mg/dL |
| Creatinine | 2.4 mg/dL (baseline 1.0) | Specific gravity | 1.022 |
| Microscopy | A few hyaline casts; no cells or other casts |
Her FENa is 2.3% and her FEUrea is 25%.
Which of the following is the most likely cause of her acute kidney injury?
- A. Acute interstitial nephritis
- B. Acute tubular necrosis
- C. Postrenal obstruction
- D. Prerenal azotemia from volume depletion
- E. Rapidly progressive glomerulonephritis
Answer: D. Prerenal azotemia. Diarrhea and poor intake have made her hypovolemic (tachycardia, orthostasis, dry mucosa), and the lisinopril blunts the efferent arteriolar constriction that normally props up GFR when perfusion falls. Her BUN:Cr ratio is 24, her urine is concentrated (specific gravity >1.020) and the sediment is bland. The FENa of 2.3% looks like ATN only because the thiazide raises urine sodium; the FEUrea of 25% (<35%) exposes the prerenal state. Treat with IV isotonic fluids and hold the thiazide and the ACE inhibitor; creatinine should fall. Untreated, prerenal azotemia can progress to ischemic ATN.
Follow-up: what is her KDIGO stage? Creatinine 2.4 mg/dL is 2.4 times her baseline of 1.0, so she is stage 2 (2.0–2.9 times baseline).
Why every other answer choice is wrong
A. Acute interstitial nephritis. Think of a drug started days to weeks earlier, or months earlier with NSAIDs (beta-lactams are the most common cause; NSAIDs and proton pump inhibitors are others) and an active sediment: sterile pyuria, WBCs and WBC casts. The fever, rash and eosinophilia triad appears in fewer than 10% of drug-induced cases, and urine eosinophils cannot make or exclude the diagnosis. Her sediment has no WBCs.
B. Acute tubular necrosis. The FENa is the bait. True ATN shows muddy brown granular casts, tubular epithelial cells or epithelial cell casts, a BUN:Cr ratio of 10–15:1, dilute urine (specific gravity ≤1.010), an FEUrea above 50%, and no rapid improvement with IV saline. Ischemic ATN (hypotension, sepsis) is the most common form, especially in the ICU; nephrotoxic ATN follows aminoglycosides, amphotericin B, cisplatin or radiocontrast. Work through it in the acute tubular necrosis Q-bank breakdown.
C. Postrenal obstruction. A 40-mL post-void residual makes bladder outlet obstruction very unlikely (Merck: a residual over 100 mL suggests incomplete emptying). Ureteral obstruction causes significant AKI only if both ureters are blocked or the patient has a single functioning kidney; renal ultrasound would look for hydronephrosis if obstruction were suspected.
E. Rapidly progressive glomerulonephritis. Glomerular injury gives a nephritic sediment: hematuria with dysmorphic RBCs and RBC casts plus proteinuria, often with edema and hypertension. She is hypotensive with a bland sediment.
Prerenal vs intrinsic (ATN) vs postrenal at a glance
| Finding | Prerenal | Intrinsic (ATN) | Postrenal |
|---|---|---|---|
| Core problem | Low renal perfusion; tubules intact | Tubular cell injury (ischemic or toxic) | Blocked urine outflow |
| BUN:Cr ratio | >20:1 | 10–15:1 | Variable; not diagnostic |
| FENa | <1% | >2% | Variable |
| FEUrea (useful on diuretics) | <35% | >50% | Variable |
| Urine sodium | <20 mEq/L | >40 mEq/L | Variable |
| Urine osmolality | >500 mOsm/kg | <450 (usually <350) | Variable |
| Specific gravity | >1.020 | ≤1.010 | Variable |
| Sediment | Normal or hyaline casts | Muddy brown granular casts, epithelial cells and casts | Often bland; a few cells or casts |
| Key test | Response to IV fluids | Urine microscopy; no response to fluids | Bladder scan, catheter, renal ultrasound (hydronephrosis) |
| Treatment | Restore perfusion; hold diuretics, NSAIDs, ACE inhibitors and ARBs | Remove the cause, supportive care | Relieve the obstruction |
Merck's caveats: these criteria may not apply in chronic kidney disease or after recent diuretic use, and urinary indices are not reliable in nonoliguric patients. Exact cutoffs also vary between references (Merck's AKI chapter lists urine sodium <10 mmol/L for prerenal AKI and a BUN:Cr ratio <10 for tubular injury), so read them as patterns. Prerenal causes include volume loss, heart failure, decompensated liver disease and drugs that impair glomerular pressure control (NSAIDs, ACE inhibitors, ARBs, calcineurin inhibitors); the physiology is in the renal blood flow autoregulation guide.
FENa and FEUrea: formulas and the diuretic trap
For the vignette: and (using BUN as plasma urea nitrogen).
- FENa <1%: tubules are reabsorbing sodium avidly, as in hypoperfusion. FENa >2%: tubules are wasting sodium, as in ATN. Values of 1–2% are indeterminate.
- Diuretics block tubular sodium reabsorption, so a prerenal patient can show a high urine sodium and FENa. Urea excretion is less affected, which is why FEUrea is more sensitive in patients taking diuretics.
- FENa measures tubular sodium handling. It does not diagnose or exclude obstruction; imaging does.
Intrinsic AKI: read the sediment
| Sediment | Points to | Classic stem |
|---|---|---|
| Muddy brown granular casts, tubular epithelial cells or casts | ATN | Hypotension or sepsis; aminoglycosides, amphotericin B, cisplatin, IV contrast |
| RBC casts, dysmorphic RBCs, proteinuria | Glomerulonephritis (nephritic syndrome) | Hematuria, edema, hypertension, rising creatinine |
| WBCs and WBC casts, sterile pyuria | Acute interstitial nephritis | New beta-lactam, NSAID or PPI; rash or fever sometimes |
| WBC casts with bacteriuria and fever | Pyelonephritis | Flank pain, costovertebral angle tenderness |
| Hyaline casts only | Nonspecific; concentrated urine in prerenal states | Volume depletion |
| Broad, waxy casts | Advanced kidney failure (CKD) | Small kidneys (usually <10 cm), anemia |
WBC casts signal inflammation only: Merck lists them in pyelonephritis, glomerulonephritis and noninfective tubulointerstitial nephritis.
KDIGO AKI definition and staging
AKI is present if any of these occurs (KDIGO 2012):
- Serum creatinine rises by ≥0.3 mg/dL within 48 hours
- Serum creatinine rises to ≥1.5 times baseline within the prior 7 days
- Urine output <0.5 mL/kg/h for 6 hours
| Stage | Serum creatinine | Urine output |
|---|---|---|
| 1 | 1.5–1.9 times baseline, or rise of ≥0.3 mg/dL | <0.5 mL/kg/h for 6–12 h |
| 2 | 2.0–2.9 times baseline | <0.5 mL/kg/h for ≥12 h |
| 3 | 3.0 times baseline, or creatinine ≥4.0 mg/dL, or renal replacement therapy started (or eGFR <35 in patients under 18) | <0.3 mL/kg/h for ≥24 h, or anuria for ≥12 h |
When creatinine and urine output point to different stages, use the higher stage. KDIGO's 2026 guideline on AKI and acute kidney disease has completed public review and was being prepared for publication as of September 2026, so check for changes; the 2012 criteria remain the published standard.
Worked example: the postrenal version
Vignette. A 79-year-old man with benign prostatic hyperplasia began taking diphenhydramine for sleep 3 days ago. He now passes only small amounts of urine and has suprapubic discomfort. The lower abdomen is distended and dull to percussion, and a bladder scan shows 900 mL. Creatinine is 3.4 mg/dL (baseline 1.1), potassium 5.6 mEq/L, and the urinalysis shows mild hematuria without casts. What is the most appropriate next step?
Answer: bladder catheterization. An anticholinergic drug has tipped an enlarged prostate into acute urinary retention. Catheter drainage both confirms and treats the obstruction; renal ultrasound can then look for hydronephrosis or a more proximal block. After decompression, watch for a brisk postobstructive diuresis: in many patients it is a physiologic response to fluid retained during the obstruction, but monitor urine output and electrolytes because large losses of sodium, potassium and magnesium can occur.
Why the distractors fail:
- IV fluid bolus: treats underperfusion, not a full bladder.
- Contrast-enhanced CT: not the first step, and it adds a nephrotoxin; a bladder scan and catheter answer the question at the bedside.
- Urgent hemodialysis: the usual triggers are hyperkalemia, pulmonary edema or metabolic acidosis that do not respond to treatment, or uremic symptoms, and relieving the obstruction may reverse this AKI. See the dialysis indications guide.
- Checking FENa first: it would not change management; urine indices neither confirm nor exclude obstruction.
Exam traps
- A high FENa on a diuretic is not proof of ATN. Check FEUrea.
- Uncorrected prerenal azotemia can become ischemic ATN, so fix perfusion fast.
- Unilateral ureteral obstruction rarely raises creatinine when the other kidney is normal.
- No hydronephrosis does not exclude obstruction in the first few days, in mild obstruction, or when tumor or retroperitoneal fibrosis encases the collecting system.
- Urine eosinophils cannot make or exclude interstitial nephritis.
- ACE inhibitors, ARBs and NSAIDs turn mild volume depletion into AKI; hold them.
Key takeaways
- Prerenal: BUN:Cr >20, FENa <1%, urine sodium <20, osmolality >500, specific gravity >1.020, hyaline casts; improves with fluids.
- ATN: BUN:Cr 10–15, FENa >2%, urine sodium >40, osmolality usually <350, muddy brown granular casts; no quick response to fluids.
- On diuretics: FEUrea <35% means prerenal; >50% means intrinsic.
- Postrenal: bladder scan and catheter first, renal ultrasound for hydronephrosis; watch for postobstructive diuresis.
- Casts: muddy brown = ATN, RBC = glomerulonephritis, WBC = interstitial inflammation or pyelonephritis, broad waxy = advanced CKD.
- KDIGO: creatinine ≥0.3 mg/dL in 48 h, ≥1.5 times baseline in 7 days or urine output <0.5 mL/kg/h for 6 h; stage by the worse of creatinine and urine output.
Sources
- KDIGO Clinical Practice Guideline for Acute Kidney Injury — Kidney International Supplements (2012)
- Acute Kidney Injury (AKI) guideline page and 2026 update status — KDIGO
- Acute Kidney Injury (AKI) — Merck Manual Professional Edition
- Acute Tubular Necrosis (ATN) — Merck Manual Professional Edition
- Mercado MG, Smith DK, Guard EL. Acute Kidney Injury: Diagnosis and Management — American Family Physician (2019)
- Tubulointerstitial Nephritis — Merck Manual Professional Edition
- Overview of Nephritic Syndrome — Merck Manual Professional Edition
- Obstructive Uropathy — Merck Manual Professional Edition
- Chronic Kidney Disease — Merck Manual Professional Edition
- Bacterial Urinary Tract Infections — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
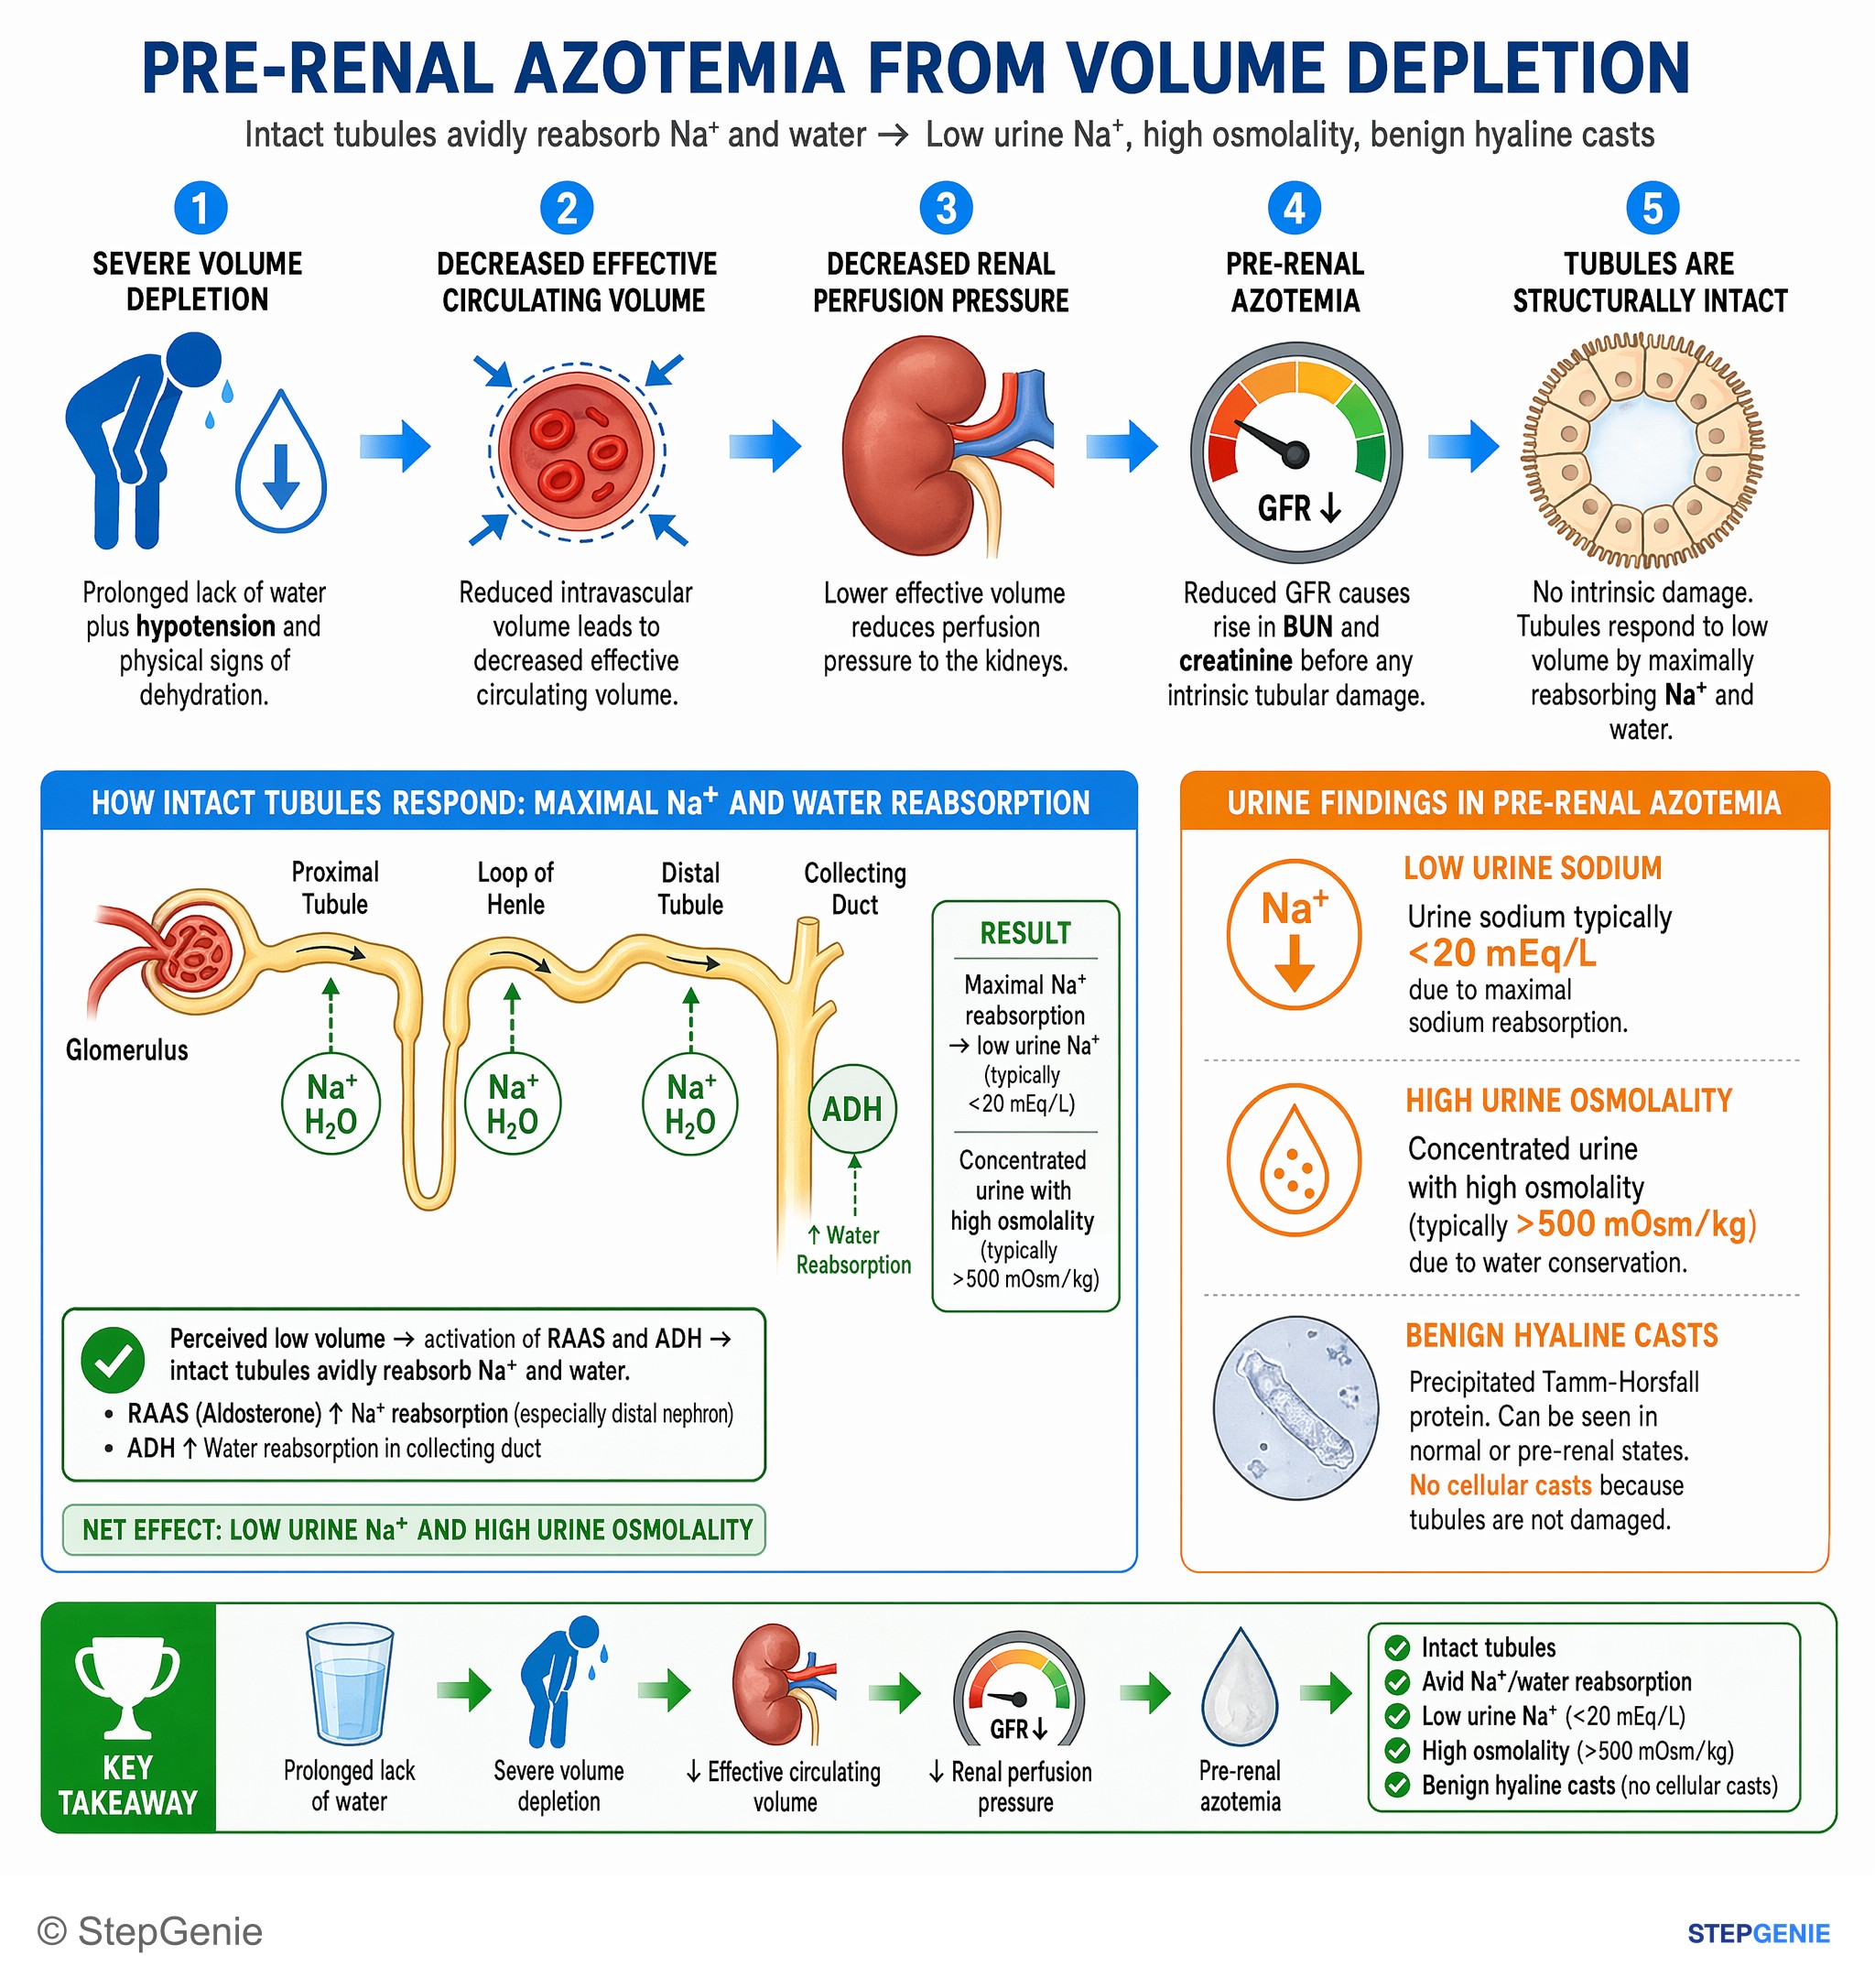
Pre-renal azotemia from volume depletion → intact tubules avidly reabsorb Na+/water → low urine Na+, high osmolality, benign hyaline casts.
USMLE Step 1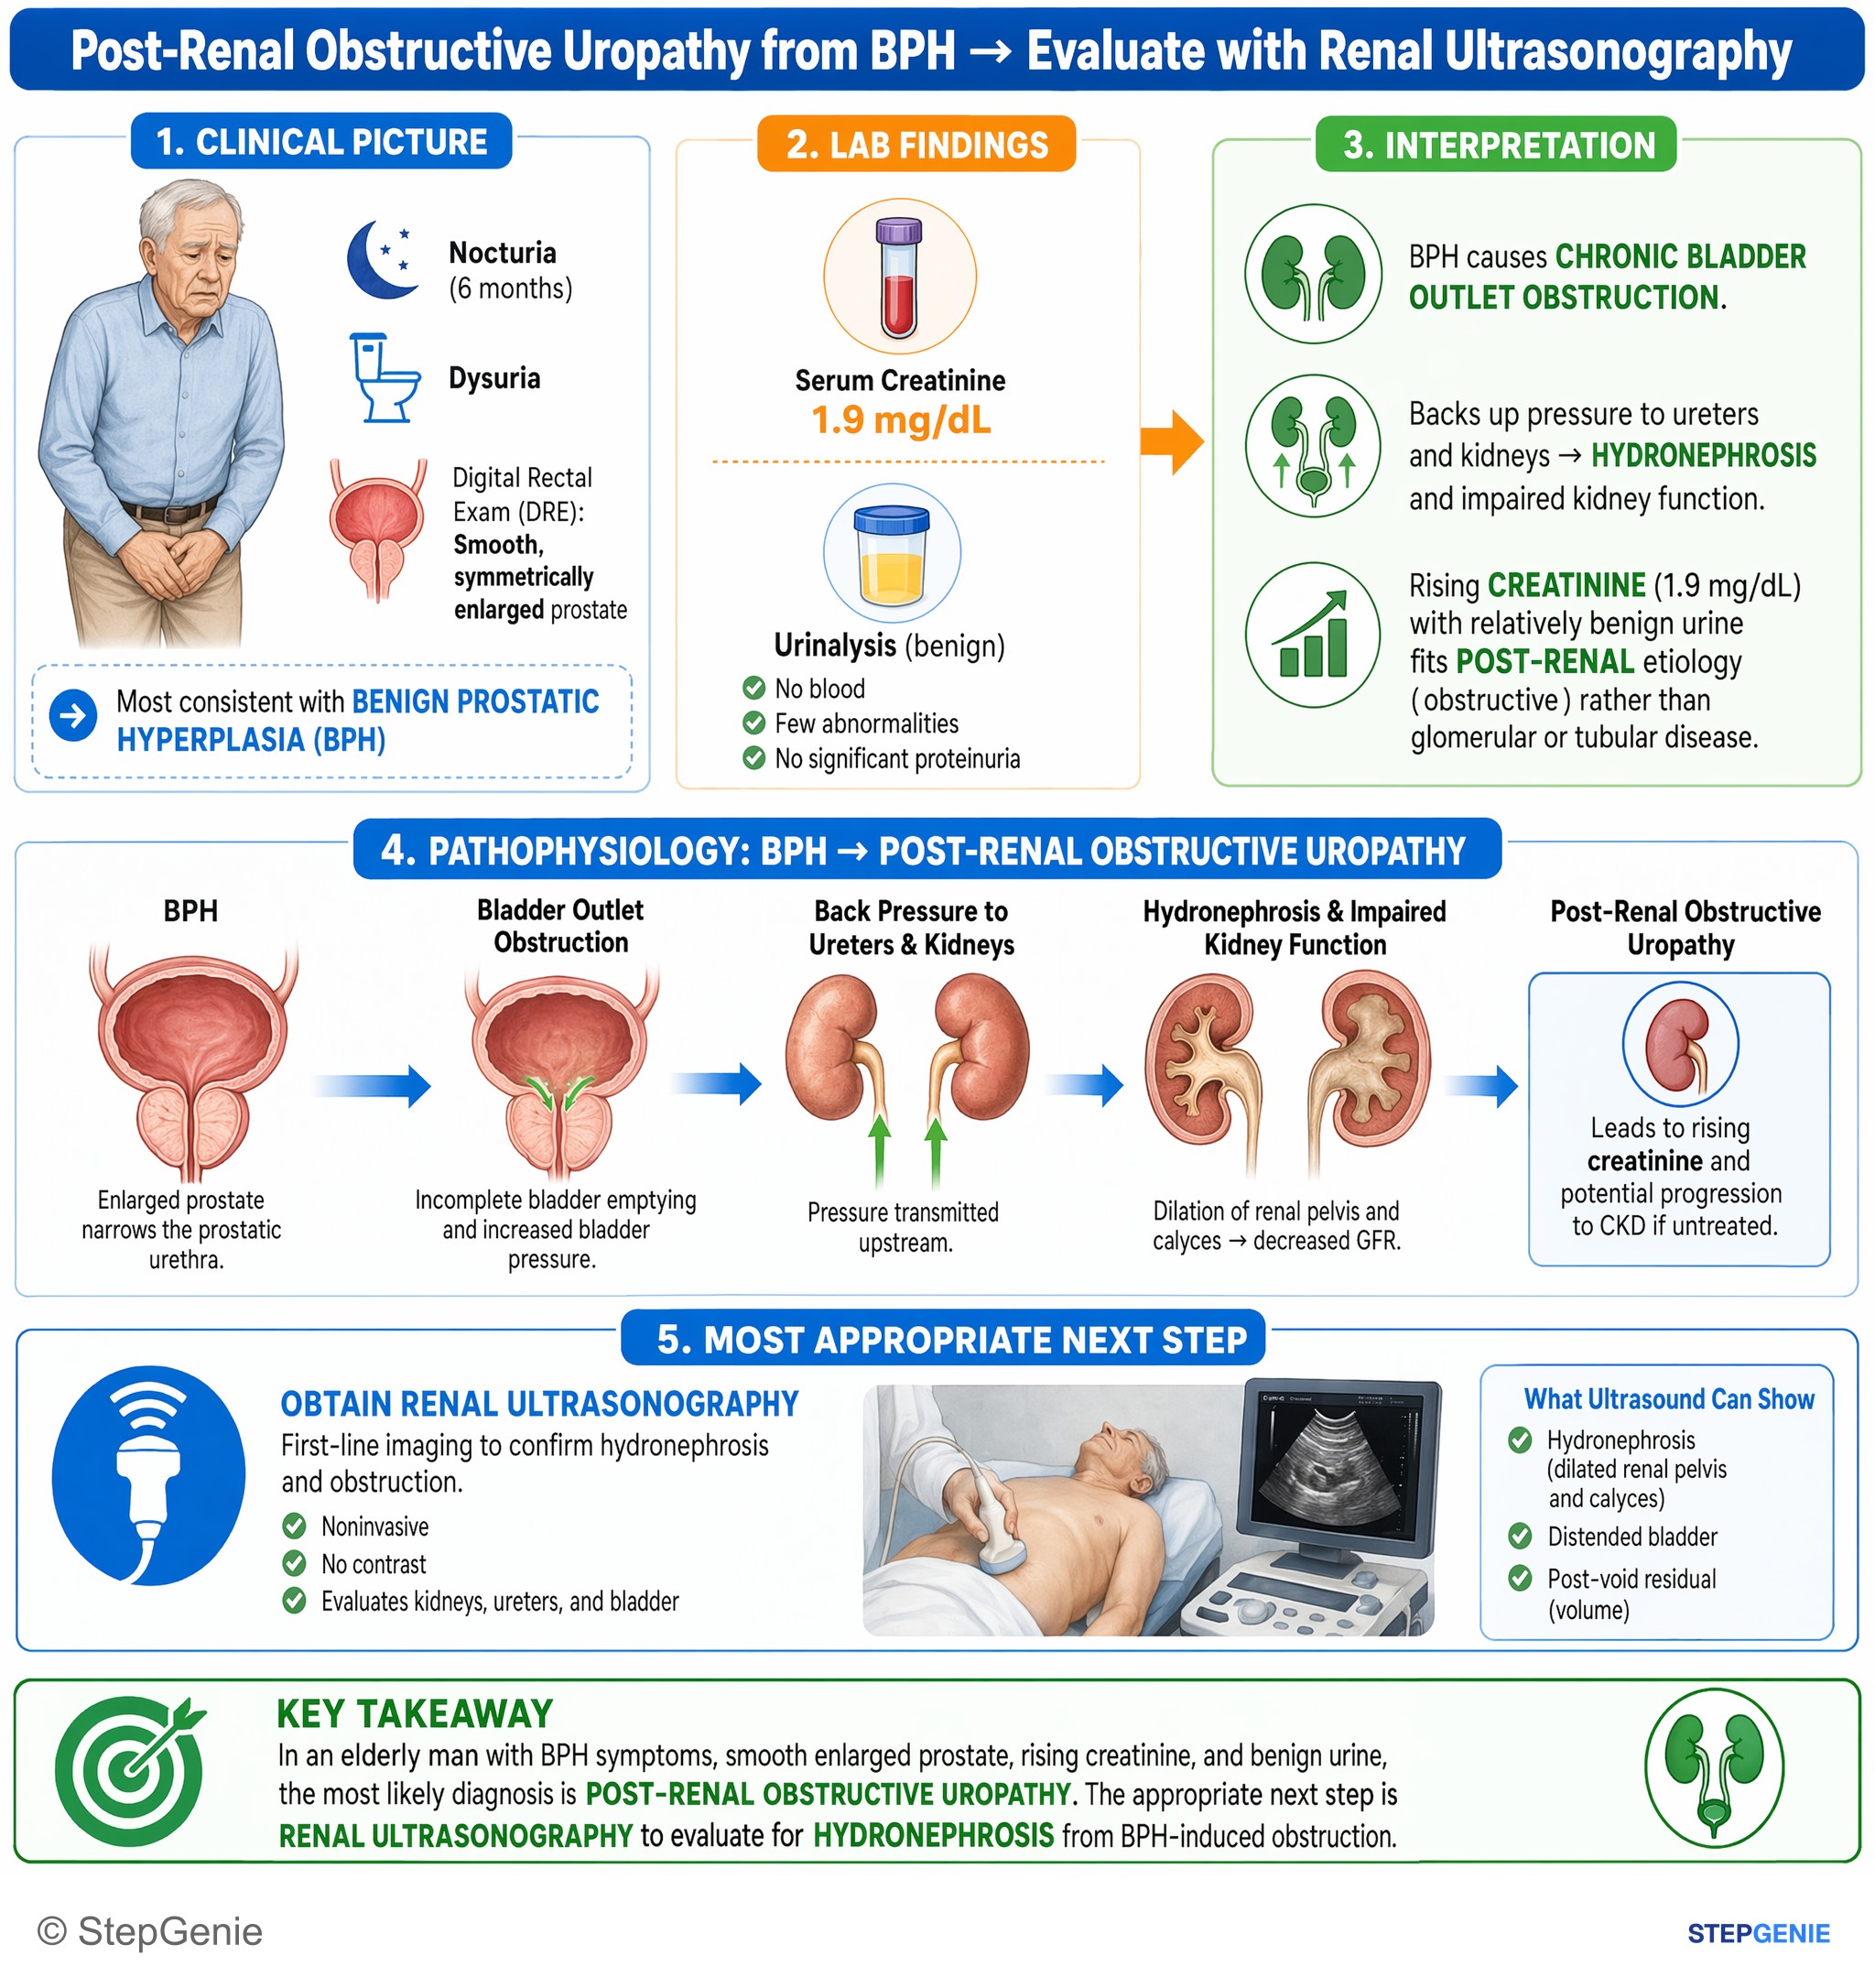
Post‑renal obstructive uropathy from BPH causing rising creatinine → evaluate for hydronephrosis with renal ultrasound.
USMLE Step 2Frequently Asked Questions
How do you tell prerenal from intrinsic AKI?
In prerenal AKI the tubules still work, so the BUN to creatinine ratio is above 20, FENa is below 1%, urine sodium is below 20 mEq/L, urine osmolality is above 500 mOsm/kg and the sediment is bland or shows hyaline casts. In acute tubular necrosis, the most common intrinsic cause, FENa is above 2%, urine sodium above 40 mEq/L, urine osmolality usually below 350 and the sediment shows muddy brown granular casts. Prerenal AKI improves quickly with IV fluids, while ATN does not.
What does a FENa less than 1% mean?
A fractional excretion of sodium below 1% means the tubules are reabsorbing sodium avidly, which suggests reduced kidney perfusion (prerenal AKI). A value above 2% suggests tubular injury, and 1 to 2% is indeterminate. FENa is less reliable after diuretics, in chronic kidney disease and in nonoliguric patients.
When should you use FEUrea instead of FENa?
Use the fractional excretion of urea when the patient is taking a diuretic, because diuretics raise urine sodium and can push FENa above 1% even in a prerenal state. An FEUrea below 35% suggests a prerenal cause, and one above 50% suggests an intrinsic cause.
What do muddy brown casts in the urine mean?
Muddy brown granular casts, often with tubular epithelial cells or epithelial cell casts, indicate acute tubular necrosis. RBC casts with dysmorphic red cells point to glomerulonephritis, WBC casts to interstitial inflammation such as acute interstitial nephritis or pyelonephritis, hyaline casts to concentrated urine in prerenal states, and broad waxy casts to advanced chronic kidney disease.
What are the KDIGO criteria for acute kidney injury?
KDIGO defines AKI as a serum creatinine rise of at least 0.3 mg/dL within 48 hours, a rise to at least 1.5 times baseline within 7 days, or urine output below 0.5 mL/kg/h for 6 hours. Stage 1 is 1.5 to 1.9 times baseline, stage 2 is 2.0 to 2.9 times baseline and stage 3 is 3 times baseline, a creatinine of at least 4.0 mg/dL or the start of renal replacement therapy. When creatinine and urine output point to different stages, the higher stage applies.
How is postrenal AKI diagnosed and treated?
Suspect obstruction in an older man with prostatic hyperplasia, a distended bladder or new anticholinergic drugs. A bladder scan and bladder catheterization confirm and relieve outlet obstruction, and renal ultrasound looks for hydronephrosis from a higher block, although it can be falsely negative in the first few days. After relief, monitor for postobstructive diuresis and electrolyte losses.