Membranoproliferative glomerulonephritis (MPGN) is a pattern of glomerular injury, not one disease: hypercellular, lobulated glomeruli with thickened, double-contoured capillary walls, the "tram track", where deposits and interposed cells split the capillary wall. Patients present with a mixed nephritic-nephrotic picture (hematuria with dysmorphic RBCs or RBC casts, proteinuria often in the nephrotic range, hypertension, rising creatinine), and complement is often low. KDIGO now classifies MPGN by immunofluorescence: immunoglobulin-positive (immune-complex) MPGN, classically from hepatitis C with type II mixed cryoglobulinemia (low C4), versus C3 glomerulopathy (C3-dominant: dense deposit disease and C3 glomerulonephritis), driven by alternative-pathway dysregulation such as C3 nephritic factor (low C3, normal C4).
The Q-bank vignette
A 52-year-old man with a history of injection drug use has had 3 weeks of leg swelling, fatigue, and aching hands and knees. Blood pressure is 164/98 mm Hg. He has palpable purpura over both shins and pitting edema to the knees. Creatinine is 2.1 mg/dL, albumin 2.7 g/dL and the urine protein-to-creatinine ratio 4.5 g/g; urine microscopy shows dysmorphic RBCs and RBC casts. HCV RNA is positive, rheumatoid factor is positive, C4 is very low, C3 is mildly low, and serum cryoglobulins are detected. Kidney biopsy shows hypercellular, lobulated glomeruli with double-contoured capillary walls and eosinophilic material plugging some capillary lumens. Immunofluorescence shows granular IgM, IgG and C3 along capillary walls, and electron microscopy shows large subendothelial deposits.
Which of the following is the most likely diagnosis?
- A. C3 glomerulopathy (dense deposit disease)
- B. IgA vasculitis nephritis
- C. Immune-complex MPGN from HCV-associated mixed cryoglobulinemia
- D. Lupus nephritis, class IV
- E. Poststreptococcal glomerulonephritis
Answer: C. In hepatitis C, glomerulonephritis is the most common kidney disease and MPGN is its most common form, usually reflecting type II mixed cryoglobulinemia: a monoclonal IgM with rheumatoid factor activity bound to polyclonal IgG. Every clue lines up with KDIGO's "typical presentation" list: hematuria, low C4, circulating cryoglobulins, rheumatoid factor and systemic signs of cryoglobulinemia (purpura, arthralgias, weakness). The eosinophilic plugs are cryoglobulin deposits occluding capillary lumens. Treatment (KDIGO 2022): direct-acting antivirals for everyone with HCV-associated GN; a cryoglobulinemic flare or rapidly progressive GN also gets immunosuppression, with or without plasma exchange; and for active disease that does not respond to antivirals, rituximab is the recommended first-line immunosuppressant.
Why every other answer choice is wrong
A. C3 glomerulopathy (dense deposit disease). Defined by C3-dominant immunofluorescence, with C3 at least 2 orders of magnitude brighter than any other immune reactant, so there is little or no IgM or IgG. The problem is the alternative pathway, so C4 is normal. Dense deposit disease shows dense deposits inside the GBM, not subendothelial immune complexes, and classic C3G is a disease of children and young adults.
B. IgA vasculitis nephritis. Purpura and arthralgias fit, but IgA vasculitis often brings abdominal pain too, complement is usually normal, and immunofluorescence shows granular mesangial IgA, not IgM, IgG and C3 along capillary walls. Cryoglobulins and rheumatoid factor point elsewhere.
D. Lupus nephritis, class IV. Diffuse lupus nephritis can mimic this biopsy (subendothelial deposits, low C3 and C4), but expect SLE features and anti-dsDNA, with immunofluorescence positive for IgG, IgA and IgM plus complement (the "full house"). Compare the classes in the lupus nephritis Q-bank breakdown.
E. Poststreptococcal glomerulonephritis. Follows streptococcal pharyngitis or skin infection by 6–21 days (up to 6 weeks), with positive ASO or anti-DNase antibodies. C3 falls but C4 stays normal or only minimally decreased, and C3 returns to normal within 6–8 weeks in 80% of cases. The electron microscopy hallmark is subepithelial "humps", not subendothelial deposits with tram tracks. Review it in the IgA nephropathy and post-strep GN guide.
Old types vs the current classification
KDIGO 2021 replaced the electron-microscopy "types" with a classification based on immunofluorescence and cause:
| Old name | Electron microscopy | Where it sits now |
|---|---|---|
| Type I MPGN | Subendothelial and mesangial deposits of immunoglobulin and C3 | Reclassified by immunofluorescence (usually immune-complex MPGN) |
| Type II MPGN | Very dense, predominantly intramembranous deposits of complement | Dense deposit disease, a form of C3 glomerulopathy |
| Type III MPGN | Subepithelial and subendothelial deposits | Reclassified by immunofluorescence |
The current scheme sorts biopsies by what lights up on immunofluorescence:
| Immunofluorescence | Category | Main causes | Complement (Merck) |
|---|---|---|---|
| Immunoglobulin plus C3 | Immune-complex MPGN | Chronic infection (HCV, HBV, endocarditis, shunt nephritis, abscess); autoimmune disease (SLE, Sjögren syndrome, rheumatoid arthritis); idiopathic cases are rare in adults | C4 low; C3 normal or mildly low |
| Monoclonal immunoglobulin | GN with monoclonal Ig deposits | Usually an indolent clone (monoclonal gammopathy of renal significance); less often myeloma, Waldenström macroglobulinemia or B-cell lymphoma | Variable |
| C3-dominant | C3 glomerulopathy: dense deposit disease and C3 glomerulonephritis | Alternative-pathway dysregulation: C3 nephritic factor, variants in factor H, factor I, CFHR proteins or C3; a monoclonal protein in many patients over 50 | C3 low, C4 normal (KDIGO: low complement in only about half of C3G) |
| Little or no Ig or C3 | MPGN-like pattern without deposits | Thrombotic microangiopathy (TTP, HUS), antiphospholipid syndrome | Normal |
Cryoglobulinemic GN straddles the first two rows: KDIGO's hepatitis C guideline calls HCV-related disease immune complex-mediated MPGN, while its 2021 glomerular guideline lists type I and type II cryoglobulinemic GN among the monoclonal-deposit diseases (type II cryoglobulins contain a monoclonal IgM).
The practical rule: immunoglobulin-positive → look for infection, autoimmune disease and a monoclonal protein; C3-dominant → evaluate the alternative complement pathway.
Why the tram tracks form
- Immune complexes or complement deposit beneath the endothelium (or, in dense deposit disease, within the GBM).
- Mesangial cell cytoplasm and inflammatory cells, including monocytes, push in between the endothelium and the original basement membrane (interposition).
- The capillary wall thickens and splits around them, so a silver stain shows two contours: the tram track.
- Mesangial and inflammatory cells expand the tuft, giving the lobular, hypercellular look.
KDIGO notes that an MPGN lesion implies the injury has been present for some time; depending on when the biopsy is taken, the same process can show other proliferative patterns, including crescents.
Complement: the fastest discriminator
| Disease | C3 | C4 | Other clue |
|---|---|---|---|
| Immune-complex MPGN (HCV cryoglobulinemia) | Normal or mildly low | Low | Cryoglobulins, rheumatoid factor, purpura |
| C3 glomerulopathy | Low (about half of cases) | Normal | C3 nephritic factor; drusen |
| Lupus nephritis | Low | Low | Anti-dsDNA, "full house" immunofluorescence |
| Poststreptococcal GN | Low, normal again within 6–8 weeks in 80% | Normal or minimally low | ASO or anti-DNase; subepithelial humps |
| IgA nephropathy or IgA vasculitis | Normal | Normal | Mesangial IgA; hematuria 1–2 days after a mucosal infection |
C3 nephritic factor and dense deposit disease
- C3 nephritic factor is an autoantibody that stabilizes the alternative-pathway C3 convertase (C3bBb), so C3 keeps being cleaved: low C3, normal C4. KDIGO describes classic C3G as nephritic factor-mediated dysregulation of the alternative pathway's enzyme complexes, and NORD notes that patients with dense deposit disease are more likely to carry C3 nephritic factors.
- Dense deposit disease has very dense, "sausage-like" deposits within the GBM; C3 glomerulonephritis has less dense mesangial and capillary wall deposits.
- Some patients develop drusen in the retina's Bruch membrane, which resembles the glomerular basement membrane.
- About half progress to kidney failure within 10 years (NORD).
- Rule out infection-related and postinfectious GN before diagnosing C3G, and look for a monoclonal protein in anyone first diagnosed at age 50 or older (KDIGO).
Treatment
- Treat the cause: direct-acting antivirals for HCV-associated GN (KDIGO 2022, strong recommendation); hematology evaluation, and clone-directed therapy where appropriate, for monoclonal disease.
- Supportive care for all: blood pressure control and renin-angiotensin system (RAS) blockade for proteinuria; indolent immune-complex disease without active inflammation on biopsy is managed with RAS inhibition alone.
- C3 glomerulopathy, moderate to severe, without a monoclonal gammopathy: mycophenolate mofetil plus glucocorticoids, then eculizumab if that fails (KDIGO 2021). Since then the FDA has approved iptacopan (factor B inhibitor) for adults with C3G, to reduce proteinuria, and pegcetacoplan (binds C3 and C3b) for patients 12 years and older with C3G or primary immune-complex MPGN. Both labels carry a boxed warning for serious infections with encapsulated bacteria (S. pneumoniae, N. meningitidis, H. influenzae type b) and call for vaccination, ideally at least 2 weeks before the first dose; these are the same organisms that threaten patients with inherited complement deficiencies.
Worked example: the C3 glomerulopathy version
Vignette. A 14-year-old girl has had cola-colored urine and puffy eyelids for 2 months; she had a sore throat 3 months ago. Blood pressure is 142/90 mm Hg, and urinalysis shows RBC casts and 3+ protein. C3 is low at presentation and still low 12 weeks later; C4 is normal. ASO and anti-DNase B titers and ANA are negative. Biopsy shows an MPGN pattern; immunofluorescence shows bright C3 with only trace immunoglobulin, and electron microscopy shows very dense deposits within the GBM. Which additional finding is most likely?
Answer: circulating C3 nephritic factor. This is dense deposit disease, a C3 glomerulopathy.
Why the distractors fail:
- Positive anti-dsDNA: lupus nephritis lowers both C3 and C4 and shows immunoglobulins on immunofluorescence.
- Rising ASO titer: post-streptococcal GN usually normalizes C3 within 6–8 weeks and shows subepithelial humps; the sore throat here was a red herring.
- Anti-PLA2R antibodies: they mark primary membranous nephropathy, which is nephrotic, with subepithelial deposits and silver-stained spikes rather than dense deposits within the GBM.
- Cryoglobulins with very low C4: immune-complex MPGN shows IgM, IgG and C3 on immunofluorescence.
Exam traps
- MPGN is a pattern. After "tram track," the next question is always which cause?
- Low C4 means classical pathway consumption (HCV cryoglobulinemia, lupus); low C3 with normal C4 points away from the classical pathway (C3G, post-strep GN).
- Low C3 that persists past 8 weeks does not fit typical post-strep GN.
- Deposit location: subendothelial (immune-complex MPGN, lupus class IV), intramembranous (dense deposit disease), subepithelial (post-strep humps, membranous spikes), mesangial (IgA).
- HCV plus purpura plus GN: treat the virus; add rituximab for severe cryoglobulinemic disease.
Key takeaways
- MPGN = hypercellular glomeruli + GBM double contours (tram tracks) + nephritic-nephrotic urine, often with low complement.
- Classify by immunofluorescence: immunoglobulin-positive (infection, autoimmune, monoclonal) vs C3-dominant (C3 glomerulopathy) vs neither (thrombotic microangiopathy).
- HCV is the classic cause: type II mixed cryoglobulinemia, rheumatoid factor, low C4, purpura and arthralgias; direct-acting antivirals first.
- C3 glomerulopathy: C3 nephritic factor or complement gene variants, often low C3 with normal C4, dense deposit disease with intramembranous deposits and drusen.
- Old type I, II, III map to deposit location; type II is now dense deposit disease.
- New drugs: iptacopan (adults, C3G) and pegcetacoplan (age 12 and older, C3G or primary immune-complex MPGN) block complement and require vaccination against encapsulated bacteria.
Sources
- KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases, Chapter 8: MPGN pattern of injury — Kidney International (2021)
- KDIGO 2022 Clinical Practice Guideline for Hepatitis C in Chronic Kidney Disease — Kidney International (2022)
- Membranoproliferative Glomerulonephritis — Merck Manual Professional Edition
- Postinfectious Glomerulonephritis (PIGN) — Merck Manual Professional Edition
- Immunoglobulin A Nephropathy — Merck Manual Professional Edition
- Lupus Nephritis — Merck Manual Professional Edition
- Membranous Nephropathy — Merck Manual Professional Edition
- C3 Glomerulopathy — National Organization for Rare Disorders (NORD) (2026)
- EMPAVELI (pegcetacoplan) prescribing information — DailyMed
- FABHALTA (iptacopan) prescribing information — DailyMed
- Mashayekhi M, et al. C3 Glomerulopathy Diagnosis, Current Treatments, and Emerging Therapies — Kidney Medicine (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
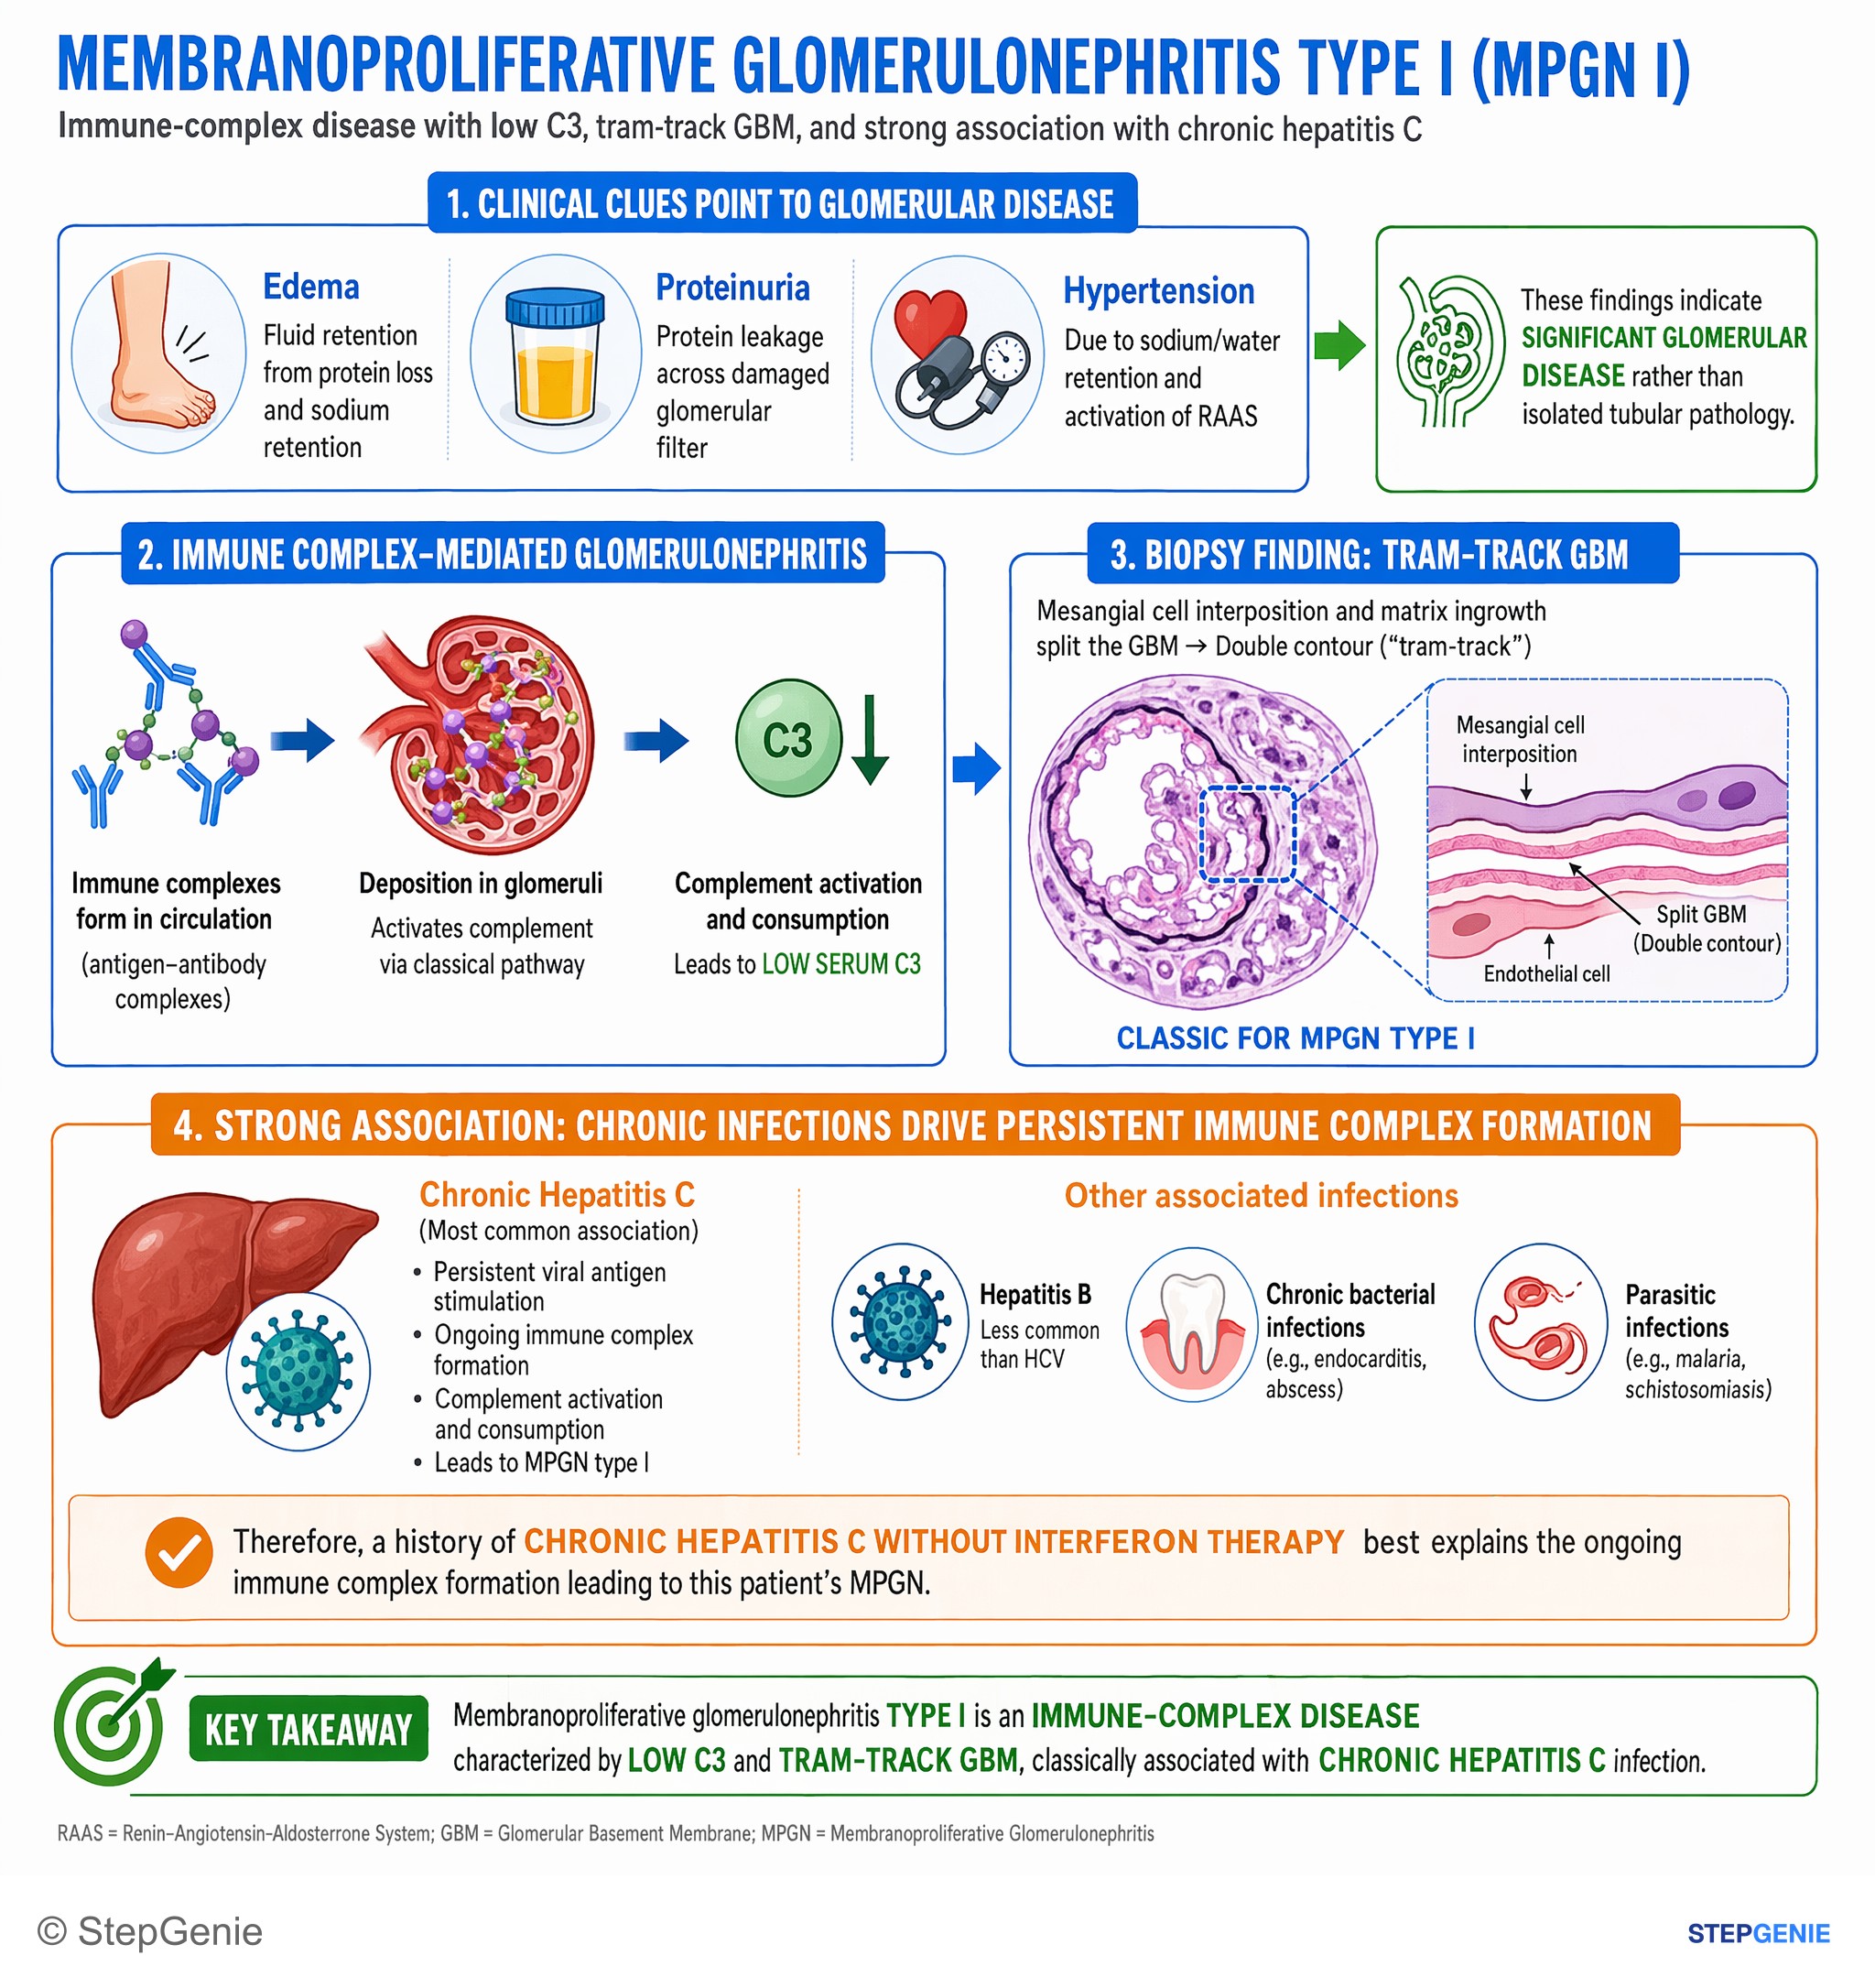
Membranoproliferative glomerulonephritis type I: immune-complex disease with low C3 and tram-track GBM, classically associated with…
USMLE Step 1Frequently Asked Questions
What is membranoproliferative glomerulonephritis?
Membranoproliferative glomerulonephritis (MPGN) is a pattern of glomerular injury rather than a single disease: hypercellular glomeruli with thickened capillary walls that show a double contour, or tram track. Patients usually have a mix of nephritic and nephrotic features, such as hematuria, proteinuria that is often nephrotic range, hypertension and reduced kidney function, and complement is often low. KDIGO classifies it by immunofluorescence into immunoglobulin-positive (immune-complex) MPGN and C3 glomerulopathy.
What causes the tram-track appearance in MPGN?
Immune complexes or complement deposit beneath the endothelium, and mesangial cell cytoplasm and inflammatory cells such as monocytes push in between the endothelium and the original glomerular basement membrane. The capillary wall thickens and splits around them, so a silver stain shows two parallel contours along the capillary wall. In dense deposit disease, the deposits sit within the basement membrane itself.
How is hepatitis C linked to MPGN?
Glomerulonephritis is the most common kidney disease in hepatitis C, and immune-complex MPGN is its most common form, usually reflecting type II mixed cryoglobulinemia, in which a monoclonal IgM with rheumatoid factor activity binds polyclonal IgG. Typical clues are hematuria, low C4, circulating cryoglobulins, a positive rheumatoid factor, and purpura, arthralgias and weakness. KDIGO recommends direct-acting antivirals for all patients, with immunosuppression such as rituximab for severe or refractory cryoglobulinemic disease.
What is C3 glomerulopathy?
C3 glomerulopathy is glomerulonephritis in which C3 staining on immunofluorescence is at least two orders of magnitude brighter than any other immune reactant. It includes dense deposit disease, with very dense deposits inside the basement membrane, and C3 glomerulonephritis, and it results from dysregulation of the alternative complement pathway, for example by C3 nephritic factor or variants in factor H or factor I. C3 is often low with a normal C4, and about half of patients progress to kidney failure within 10 years.
What is C3 nephritic factor?
C3 nephritic factor is an autoantibody that stabilizes the alternative pathway C3 convertase, so C3 is continuously cleaved and serum C3 falls while C4 stays normal. It is associated with C3 glomerulopathy and is more common in dense deposit disease, the old type II MPGN.
How do you tell MPGN from poststreptococcal glomerulonephritis?
Poststreptococcal glomerulonephritis follows a streptococcal throat or skin infection by about 6 to 21 days, with positive ASO or anti-DNase antibodies, and its low C3 returns to normal within 6 to 8 weeks in about 80% of cases. Its biopsy shows subepithelial humps. A C3 that stays low, tram-track basement membranes or subendothelial or intramembranous deposits point instead to MPGN or C3 glomerulopathy.