A USMLE stem about lupus nephritis usually points to class IV (diffuse proliferative) lupus nephritis: a patient with SLE, a nephritic urinalysis (hematuria with RBC casts), hypertension, a rising creatinine, a positive anti-dsDNA and low C3 and C4. On biopsy, class IV involves 50% or more of glomeruli, large subendothelial immune deposits create "wire loops" on light microscopy, and immunofluorescence is "full house" (IgG, IgA, IgM, C3 and C1q). It is the most common class and the most extensive active (proliferative) form. The ISN/RPS classification runs from class I (minimal mesangial) to class VI (advanced sclerosing), and class V (membranous) is the one that presents as nephrotic syndrome.
The vignette
A 24-year-old woman with fatigue, arthralgias and a photosensitive rash has had facial puffiness and dark urine for 2 weeks. Blood pressure is 158/92 mm Hg, and she has periorbital edema. Creatinine is 2.1 mg/dL (baseline 0.8). Urinalysis shows 2+ protein, many red cells and RBC casts; the spot urine protein-to-creatinine ratio is 2.8 g/g. ANA and anti-dsDNA are positive, and C3 and C4 are both low.
Question: What is the most likely renal pathology?
Answer: diffuse proliferative lupus nephritis (ISN/RPS class IV).
- Nephritic pattern: hematuria with RBC casts, hypertension and a rising creatinine mean active glomerular inflammation.
- Immune complexes consuming complement: low C3 and low C4 point to the classical pathway.
- SLE activity markers: a rising anti-dsDNA titer and falling C3 and C4 signal active disease, and complement is usually lowest when nephritis is active.
- Sub-nephrotic proteinuria does not argue against it: class IV usually causes hematuria and proteinuria and often causes nephrotic syndrome as well, so a mixed nephritic-nephrotic picture is typical.
What class IV looks like on biopsy
| Modality | Class IV finding | Board phrase |
|---|---|---|
| Light microscopy | Endocapillary (and sometimes extracapillary) hypercellularity in ≥50% of glomeruli; wire loops; hyaline thrombi; crescents in severe cases | "Diffuse proliferative," "wire loops" |
| Immunofluorescence | Granular deposits of IgG, IgA, IgM, C3 and C1q | "Full house" |
| Electron microscopy | Large subendothelial deposits, plus mesangial deposits | "Subendothelial deposits" |
Wire loops are large, confluent subendothelial deposits seen on light microscopy, and hyaline thrombi are immune aggregates inside capillary lumens. Both are active lesions. Biopsy reports also give an activity index (proliferation, necrosis, cellular crescents, wire loops, hyaline thrombi, leukocyte infiltration) and a chronicity index (glomerular sclerosis, fibrous crescents, tubular atrophy, interstitial fibrosis); the chronicity index predicts progression to kidney failure.
Lupus nephritis classes I–VI (ISN/RPS)
| Class | Name | Biopsy hallmark | Typical presentation |
|---|---|---|---|
| I | Minimal mesangial | Normal light microscopy; mesangial deposits on IF or EM | No kidney findings |
| II | Mesangial proliferative | Mesangial hypercellularity with deposits in the mesangium only | Possibly microscopic hematuria or mild proteinuria |
| III | Focal | Endocapillary ± extracapillary proliferation in <50% of glomeruli, usually segmental | Hematuria and proteinuria; sometimes hypertension, nephrotic syndrome, rising creatinine |
| IV | Diffuse | The same active lesions in ≥50% of glomeruli; wire loops | Hematuria and proteinuria; hypertension, nephrotic syndrome and rising creatinine are frequent; most common class |
| V | Membranous | Thickened GBM with subepithelial (and intramembranous) deposits; "spikes" on silver stain | Nephrotic syndrome; creatinine usually normal or slightly raised |
| VI | Advanced sclerosing | ≥90% of glomeruli sclerosed | Bland sediment with slowly rising creatinine or kidney failure |
Quick rule: I and II stay in the mesangium; III and IV proliferate (focal under 50%, diffuse at 50% or more); V goes membranous; VI is scar. Class V can coexist with III or IV and is then treated as proliferative disease, and a patient can move from one class to another over time. See how lupus nephritis fits the broader split in this nephrotic vs nephritic syndrome guide.
Why every answer choice matters
| Answer choice | Why it tempts | What rules it out here |
|---|---|---|
| Membranous nephropathy (primary, or lupus class V) | SLE can cause class V; edema and heavy proteinuria | Membranous disease is nephrotic, with subepithelial deposits and GBM spikes; RBC casts, a rising creatinine and low C3/C4 point to proliferative disease. Anti-PLA2R antibodies point to primary membranous nephropathy |
| Post-streptococcal GN | Nephritic syndrome with low C3 | Follows pharyngitis or impetigo by about 1–3 weeks (up to 6); ASO or anti-DNase titers; C3 falls but C4 stays normal or near normal; subepithelial "humps" on EM; C3 usually recovers within 6–8 weeks |
| IgA nephropathy | Young adult with hematuria | Gross hematuria 1–2 days after a mucosal infection ("synpharyngitic"); complement usually normal; mesangial IgA on IF |
| Anti-GBM disease | Nephritis with a falling GFR (RPGN pattern) | Antibodies against the α3 chain of type IV collagen; linear IgG on IF; hemoptysis when the lungs are involved (Goodpasture syndrome) |
| ANCA-associated GN | RPGN pattern with systemic inflammation | Pauci-immune: little or no immunoglobulin or complement on IF; PR3- or MPO-ANCA |
The unifying logic: low complement points to an immune-complex GN. Anti-GBM disease and pauci-immune ANCA disease do not work through circulating immune complexes, so a low C3 and C4 in a patient with SLE should keep you on lupus nephritis. The three immunofluorescence patterns of crescentic disease are compared in this rapidly progressive glomerulonephritis breakdown.
Diagnosis and management (Step 2 CK depth)
- Screen every patient with SLE with a urinalysis, serum creatinine and a urine protein-to-creatinine ratio; anti-dsDNA and C3/C4 help gauge activity.
- Biopsy when proteinuria is confirmed, the sediment is active or the GFR falls. The class, not the serology, decides treatment.
- Hydroxychloroquine for every patient with lupus nephritis unless contraindicated (KDIGO 2024).
- Active class III or IV (± V), per KDIGO 2024: glucocorticoids (often IV methylprednisolone pulses, then a prednisone taper) plus one of: mycophenolate; low-dose IV cyclophosphamide; belimumab with mycophenolate or low-dose cyclophosphamide; or mycophenolate with a calcineurin inhibitor (voclosporin or tacrolimus) when kidney function is not severely reduced. The classic board answer, "steroids plus mycophenolate or cyclophosphamide," is still correct.
- Maintenance: mycophenolate is the preferred drug, and the total course of immunosuppression (initial plus maintenance) should last at least 36 months. Azathioprine is the alternative when mycophenolate is not tolerated or available, and the preferred choice for a patient who wants to become pregnant.
- Class V: ACE inhibitor or ARB, blood pressure control and hydroxychloroquine; add immunosuppression when proteinuria reaches the nephrotic range.
- Class I or II: immunosuppression is guided by extrarenal disease, except for nephrotic syndrome from lupus podocytopathy, which is treated like minimal change disease.
- All classes: an ACE inhibitor or ARB for hypertension or proteinuria.
- Kidney failure: transplantation is the preferred replacement therapy, and recurrence in the graft is uncommon.
Lupus nephritis develops in 20–60% of patients with SLE over their lifetime, depending on the population. Every episode of active nephritis costs nephrons, which is why KDIGO 2024 pairs immunosuppression with blood pressure control, RAS blockade and flare prevention. For the extrarenal side of the disease, review the SLE overview for Step 1.
Exam traps
- Low C3 alone a few weeks after a sore throat is post-streptococcal GN. Low C3 and C4 with anti-dsDNA is lupus.
- Wire loops are subendothelial; spikes are subepithelial. Wire loops mean class III/IV; spikes mean class V.
- Nephrotic syndrome with a bland sediment and a normal creatinine in SLE is class V, not class IV.
- An RPGN picture in lupus still shows granular, full-house deposits. Linear IgG means anti-GBM disease.
- Anti-dsDNA and complement track activity. Anti-Smith is highly specific for SLE, but the markers followed for nephritis activity are anti-dsDNA titers and C3/C4.
- Class IV can look like membranoproliferative GN on light microscopy; in a patient with SLE, the answer is lupus nephritis.
- Class VI is scar, not active inflammation. KDIGO 2024 directs chronic lesions without activity to supportive CKD care rather than more immunosuppression.
Worked example
Vignette. A 31-year-old woman with SLE who takes hydroxychloroquine has had leg swelling for 2 months. Blood pressure is 126/78 mm Hg. Urinalysis shows 4+ protein, 0–2 red cells per high-power field and no casts. The urine protein-to-creatinine ratio is 5.6 g/g, serum albumin is 2.2 g/dL and creatinine is 0.8 mg/dL. A kidney biopsy is performed. Which finding is most likely?
Answer: Subepithelial immune deposits with GBM "spikes": membranous lupus nephritis (class V).
Why the distractors are wrong:
- Large subendothelial deposits (wire loops): class III/IV, which would bring an active sediment with RBC casts, hypertension and a rising creatinine.
- Mesangial deposits only: class I or II, which cause minimal urinary findings, not nephrotic syndrome.
- Linear IgG along the GBM: anti-GBM disease, a rapidly progressive nephritic illness.
- ≥90% sclerosed glomeruli: class VI, which presents with chronic kidney failure and a bland sediment.
Under KDIGO 2024 she needs an ACE inhibitor or ARB, blood pressure control and continued hydroxychloroquine, and because her proteinuria is in the nephrotic range, immunosuppression (glucocorticoids plus mycophenolate, a calcineurin inhibitor or cyclophosphamide).
Key takeaways
- SLE + RBC casts + low C3 and C4 + anti-dsDNA = class IV diffuse proliferative lupus nephritis, the most common class and the most extensive active lesion.
- Class III is <50% of glomeruli; class IV is ≥50%.
- Wire loops = subendothelial deposits; full house = IgG, IgA, IgM, C3 and C1q.
- Class V = membranous: nephrotic, subepithelial deposits, spikes.
- Distractors: post-streptococcal GN lowers mainly C3, IgA nephropathy has normal complement, anti-GBM is linear and ANCA disease is pauci-immune.
- KDIGO 2024: hydroxychloroquine for all; glucocorticoids plus mycophenolate, low-dose cyclophosphamide, belimumab-based or calcineurin inhibitor-based therapy for class III/IV; mycophenolate maintenance, with at least 36 months of total immunosuppression.
Sources
- Lupus Nephritis — Merck Manual Professional Edition
- KDIGO 2024 Clinical Practice Guideline for the Management of Lupus Nephritis — Kidney International
- Executive summary of the KDIGO 2024 Clinical Practice Guideline for the Management of Lupus Nephritis — Kidney International
- KDIGO 2024 Lupus Nephritis Guideline: Top 10 Takeaways for Clinicians — KDIGO
- Disease Week: Lupus Nephritis — Arkana Laboratories
- Systemic Lupus Erythematosus (SLE) — Merck Manual Professional Edition
- Postinfectious Glomerulonephritis — Merck Manual Professional Edition
- Immunoglobulin A Nephropathy — Merck Manual Professional Edition
- Membranous Nephropathy — Merck Manual Professional Edition
- Rapidly Progressive Glomerulonephritis — Merck Manual Professional Edition
- Anti-Glomerular Basement Membrane Disease — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
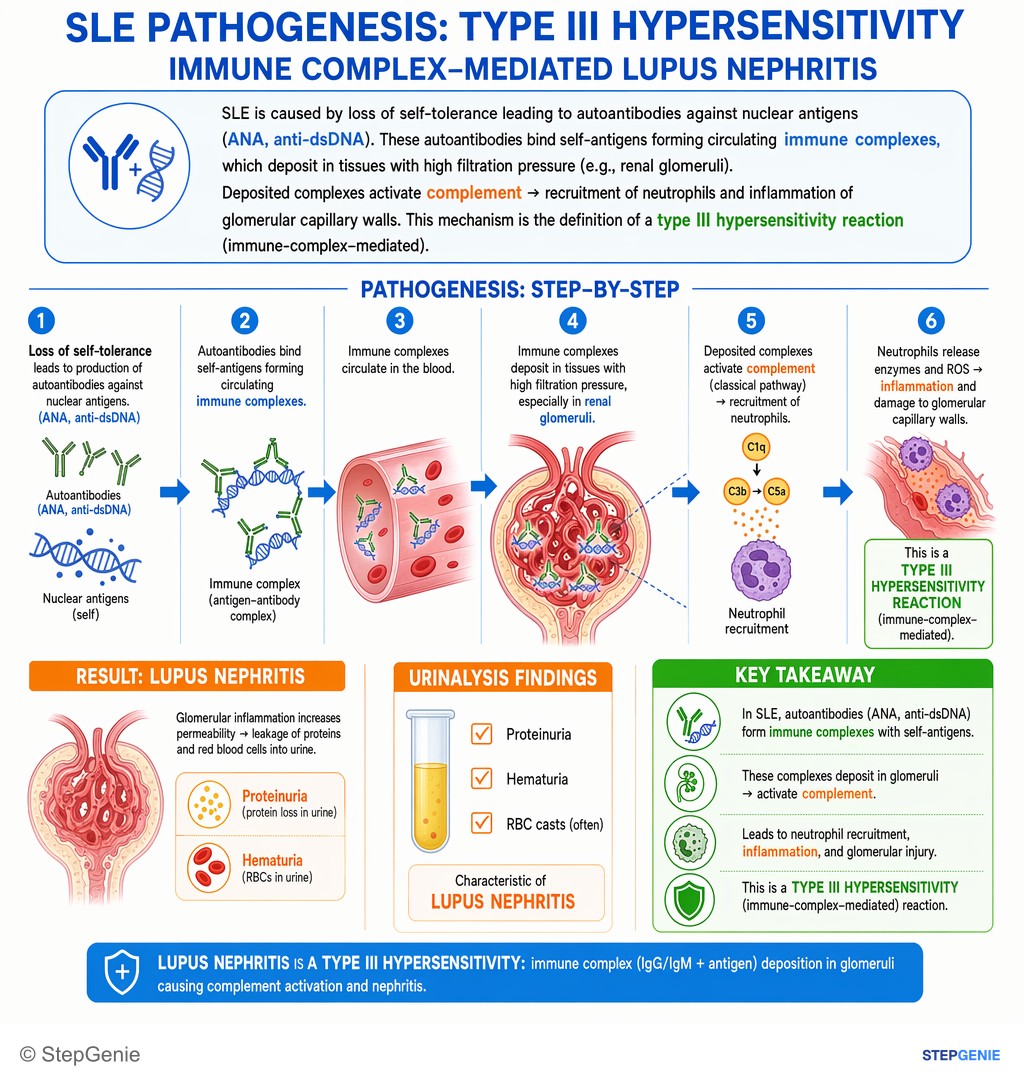
Lupus nephritis is a type III hypersensitivity: immune complex (IgG/IgM + antigen) deposition in glomeruli causing complement activation…
USMLE Step 1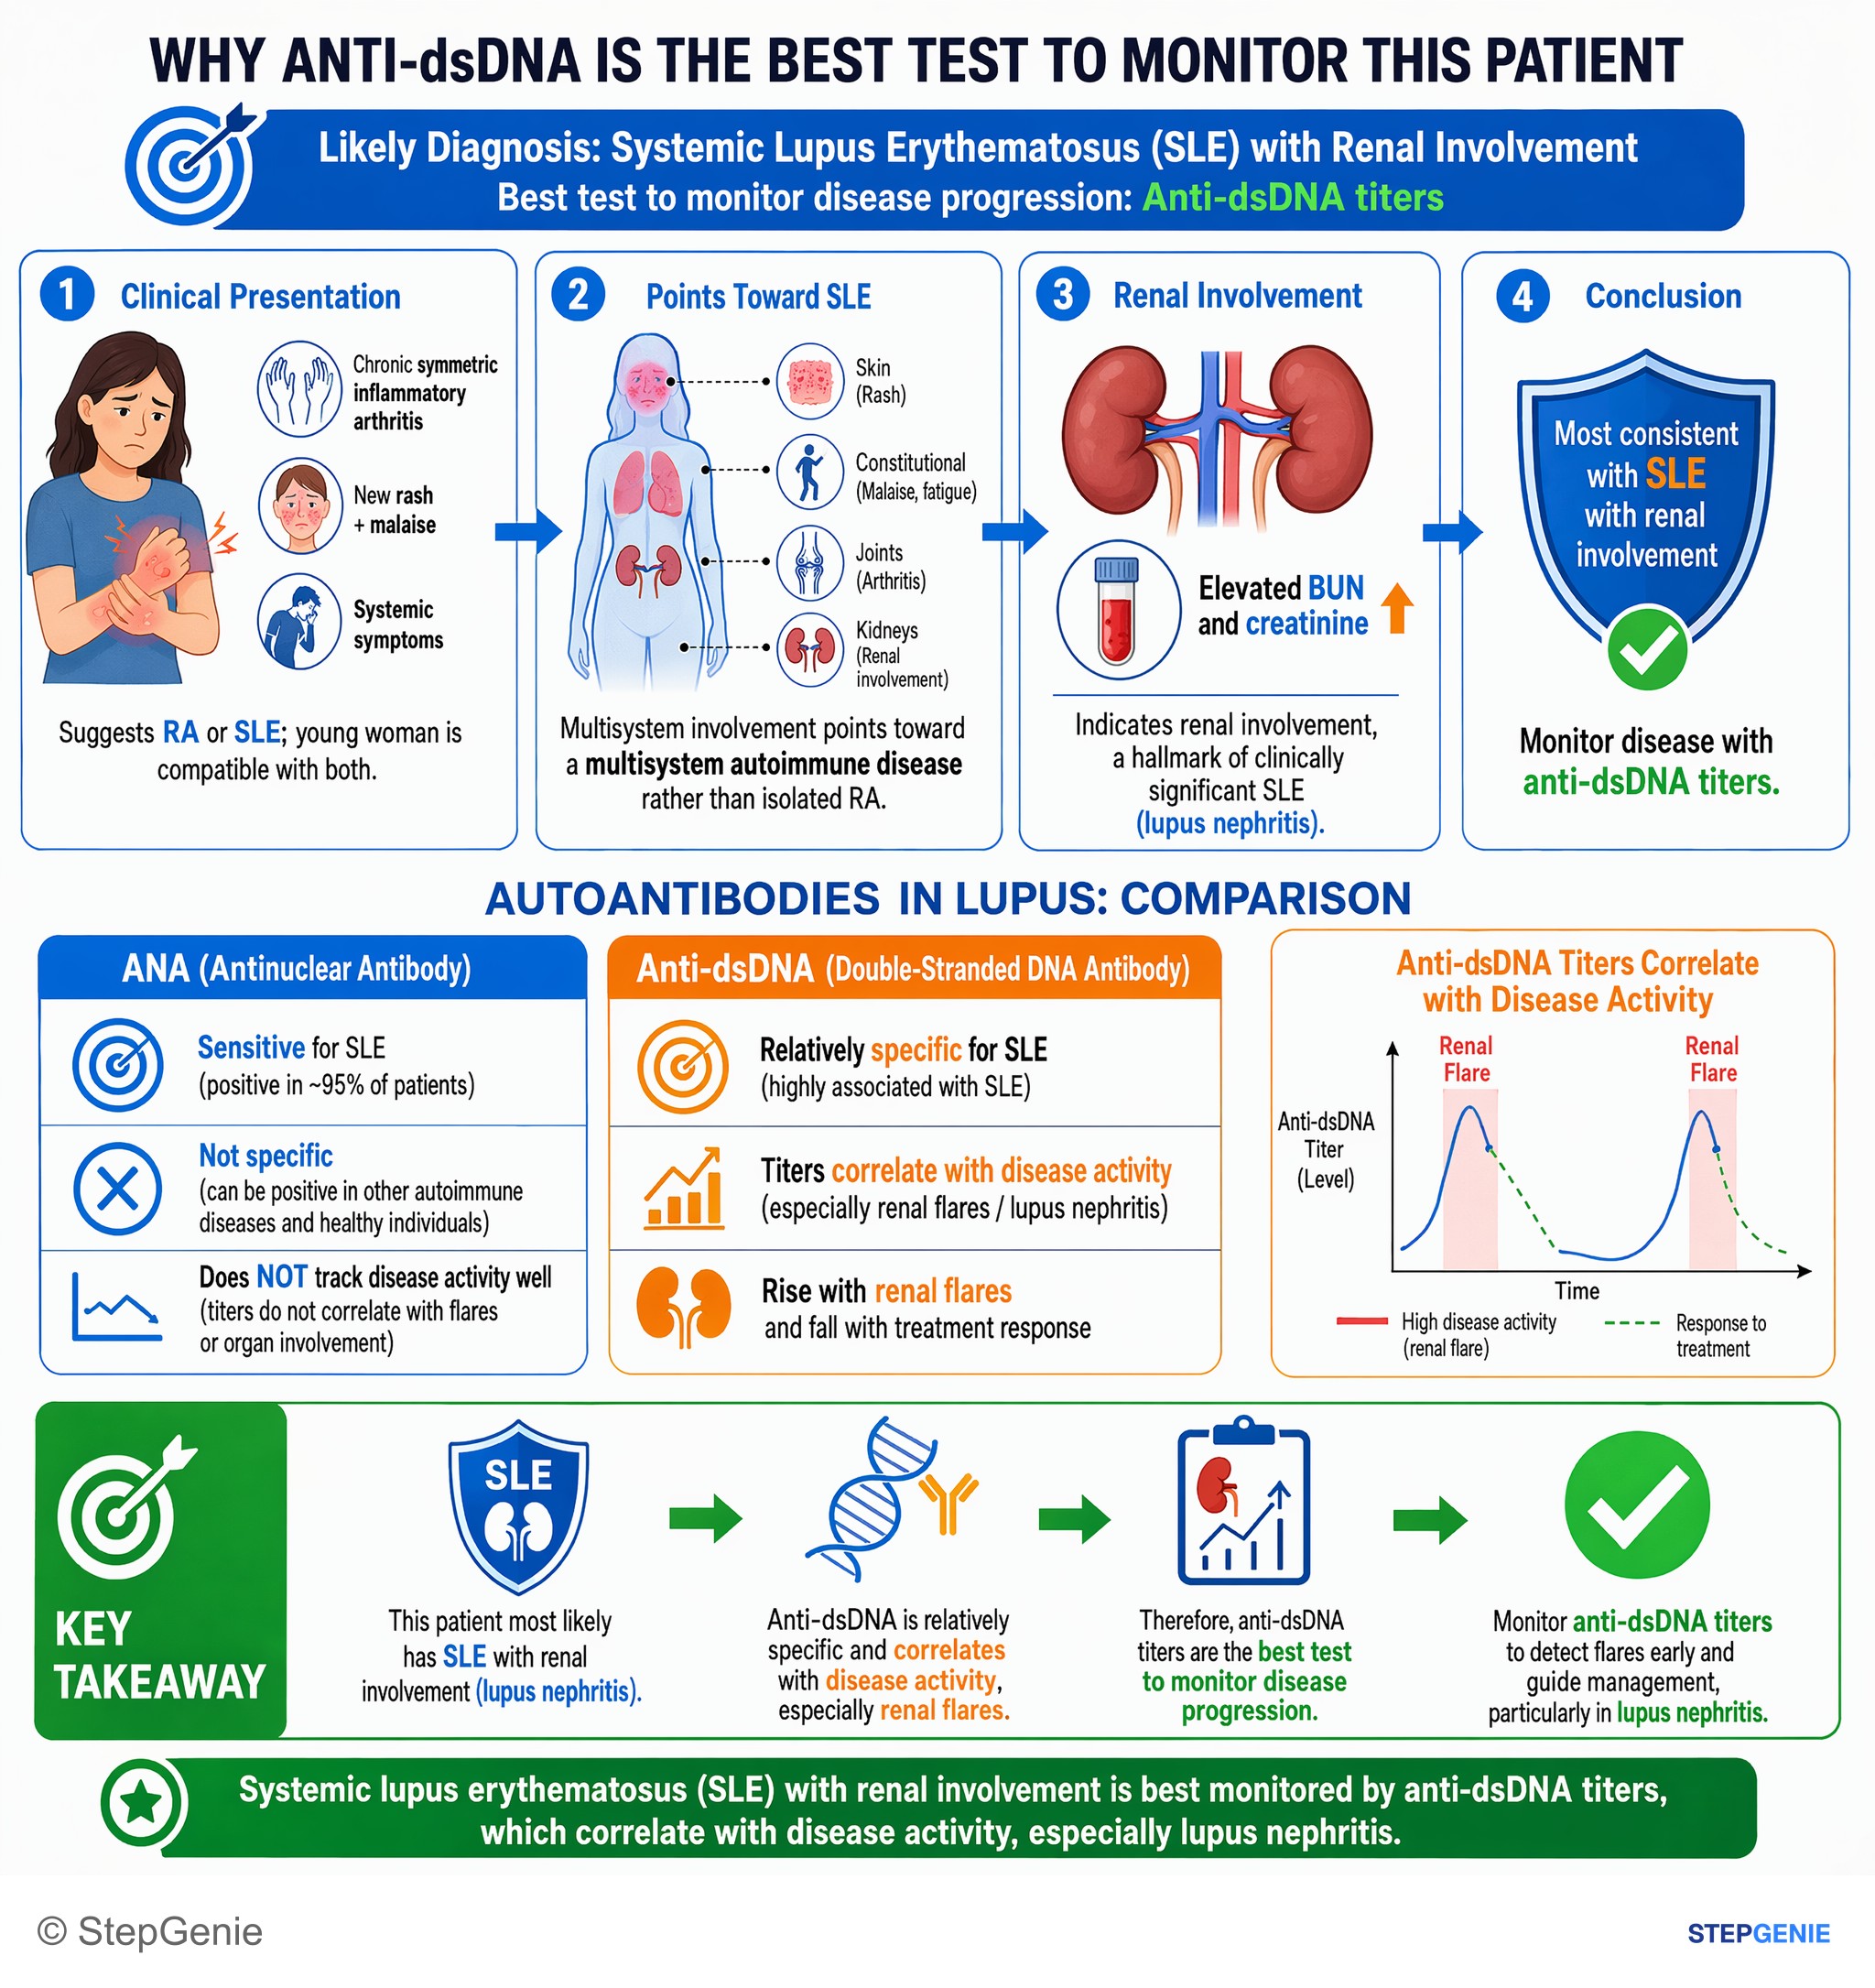
Systemic lupus erythematosus (SLE) with renal involvement is best monitored by anti-dsDNA titers, which correlate with disease activity…
USMLE Step 2Frequently Asked Questions
What are the classes of lupus nephritis?
The ISN/RPS classification has six classes. Class I (minimal mesangial) and class II (mesangial proliferative) stay in the mesangium. Class III (focal) and class IV (diffuse) are proliferative and involve fewer than 50% or at least 50% of glomeruli. Class V is membranous, with subepithelial deposits and nephrotic syndrome, and class VI (advanced sclerosing) means at least 90% of glomeruli are sclerosed. Class V can coexist with class III or IV.
What are wire loop lesions in lupus nephritis?
Wire loops are the light-microscopy appearance of large, confluent subendothelial immune-complex deposits in glomerular capillary walls. They are an active lesion of proliferative lupus nephritis (class III or IV), count toward the biopsy activity index and are classically tested with class IV disease. Deposits on the other side of the basement membrane, the subepithelial side, produce the spikes of membranous (class V) disease instead.
What does full-house immunofluorescence mean?
Full-house immunofluorescence means the glomerular deposits stain for all three immunoglobulins, IgG, IgA and IgM, plus the complement components C3 and C1q. It is typical of lupus nephritis, where immune complexes activate the classical complement pathway, and it fits with low serum C3 and C4. By contrast, anti-GBM disease shows linear IgG, and ANCA-associated glomerulonephritis shows little or no immunoglobulin or complement.
How is class IV lupus nephritis treated?
KDIGO 2024 recommends glucocorticoids plus one of four options: mycophenolate, low-dose IV cyclophosphamide, belimumab combined with mycophenolate or low-dose cyclophosphamide, or mycophenolate combined with a calcineurin inhibitor such as voclosporin when kidney function is not severely impaired. Every patient should also take hydroxychloroquine unless it is contraindicated, plus an ACE inhibitor or ARB for proteinuria or hypertension. Mycophenolate is the preferred maintenance drug, and total immunosuppression should last at least 36 months.
How is lupus nephritis different from post-streptococcal glomerulonephritis?
Both are immune-complex nephritic syndromes with low complement, but the patterns differ. Post-streptococcal glomerulonephritis follows pharyngitis or impetigo by about 1 to 3 weeks, comes with raised ASO or anti-DNase titers, lowers C3 while C4 stays normal or near normal, and shows subepithelial humps. Lupus nephritis occurs with SLE, anti-dsDNA antibodies and low C3 and C4, and its proliferative classes show subendothelial deposits with full-house immunofluorescence.