Alport syndrome is an inherited disorder of type IV collagen, specifically the α3α4α5 network found in the glomerular basement membrane (GBM), the cochlea and the eye. Most families have the X-linked form (COL4A5); the rest have autosomal recessive or autosomal dominant disease (COL4A3 or COL4A4). The classic course is persistent microscopic hematuria from early childhood, then proteinuria, hypertension and progressive CKD, with sensorineural hearing loss that is never congenital and eye signs such as anterior lenticonus. Electron microscopy shows a GBM that is thin early and later irregularly thickened, with a split, "basket-weave" lamina densa, and an ACE inhibitor started early delays kidney failure.
The vignette
A 16-year-old boy is evaluated for episodes of dark urine that began in early childhood. Over the past year he has had trouble hearing his teachers, and an audiogram shows high-frequency sensorineural hearing loss. Slit-lamp examination shows a conical forward bulge of the central anterior lens surface. His maternal uncle started dialysis at age 30, and his mother has microscopic hematuria. Blood pressure is 138/86 mm Hg. Urinalysis shows 3+ blood with dysmorphic red cells and 2+ protein. Serum C3 and C4 are normal, and creatinine is 1.4 mg/dL.
Which of the following is the most likely underlying cause?
A. Autoantibodies against the NC1 domain of the α3 chain of type IV collagen B. A pathogenic variant in COL4A5, which encodes the α5 chain of type IV collagen C. Mesangial deposition of IgA immune complexes D. Subepithelial immune-complex "humps" after a streptococcal infection E. A single heterozygous COL4A3 variant producing a uniformly thin GBM
Answer: B. X-linked Alport syndrome
Every clue lines up:
- Hematuria since early childhood. All males with X-linked Alport syndrome (XLAS) have persistent microscopic hematuria from early in life, and visible (gross) hematuria can occur.
- Hearing loss appearing in adolescence. The sensorineural loss affects higher frequencies, is never congenital and is usually detected in late childhood or early adolescence.
- Anterior lenticonus, the conical lens bulge, is virtually pathognomonic for Alport syndrome.
- The pedigree fits X-linked inheritance. A severely affected maternal uncle (dialysis at 30) and a mother with only microscopic hematuria, the typical carrier picture, with no male-to-male transmission. Heterozygous women with XLAS usually have microscopic hematuria and milder, slower disease.
- Normal complement argues against complement-consuming immune-complex disease such as poststreptococcal glomerulonephritis.
Why each distractor is wrong
A. Anti-α3(IV) NC1 autoantibodies = anti-GBM disease (Goodpasture). These antibodies bind a domain concentrated in glomerular and alveolar basement membranes and give linear IgG staining along the GBM. Expect rapidly progressive glomerulonephritis with or without pulmonary hemorrhage, often in a smoker, not lifelong familial hematuria with deafness. Compare immunofluorescence patterns in the rapidly progressive GN guide. Anti-GBM disease can, however, arise de novo in an Alport patient after a kidney transplant (below).
C. Mesangial IgA = IgA nephropathy. The most common glomerulonephritis worldwide. Gross hematuria usually starts 1-2 days after a febrile mucosal illness, immunofluorescence shows granular mesangial IgA, and complement is usually normal. Because complement is normal in both diseases, the hearing loss, the lens and the pedigree are what point to Alport. More in the IgA nephropathy and PSGN guide.
D. Subepithelial humps = postinfectious (poststreptococcal) glomerulonephritis. It follows the infection after a latency of about 6-21 days (up to 6 weeks), C3 and CH50 fall and normalize within 6-8 weeks in most patients, immunofluorescence shows granular IgG and C3, and EM shows subepithelial humps. It is acquired, not familial.
E. One heterozygous COL4A3 variant with a uniformly thin GBM = the "thin basement membrane nephropathy" pattern. This is the closest look-alike. These patients usually have isolated persistent microscopic hematuria, the GBM is diffusely thin (about 150-225 nm instead of the normal 300-400 nm), and inheritance is autosomal dominant. Hearing loss, when it occurs, comes late and eye involvement is rare, so it cannot explain a teenage boy with deafness, lenticonus and an X-linked family history. See the thin basement membrane disease breakdown.
Genetics: three inheritance patterns and where TBMN fits
| Form | Genotype | Kidney course (GeneReviews) | Ears and eyes |
|---|---|---|---|
| X-linked (XLAS) | COL4A5; hemizygous males, heterozygous females | Males: about 50% reach ESKD by age 35; 50% by 20 with truncating variants, 50% by 40 with missense variants. Females: hematuria very common, median age at ESKD 65 | Common in males; later and less frequent in females |
| Autosomal recessive (ARAS) | Two COL4A3 or two COL4A4 variants | Males and females alike: proteinuria in childhood, ESKD usually before 30 | Often present |
| Autosomal dominant (ADAS) | One COL4A3 or COL4A4 variant | Slower; ESKD often delayed until later adulthood; proteinuria becomes frequent with age | Hearing loss late; eye involvement rare |
| Digenic | Variants in two of the three genes | Variable | Variable |
- Proportions vary by source. GeneReviews (2025) attributes 80-85% of Alport syndrome to COL4A5, with COL4A3 and COL4A4 accounting for the rest; MedlinePlus Genetics gives about two-thirds X-linked, about 15% autosomal recessive and 20-30% autosomal dominant. MedlinePlus estimates Alport syndrome in about 1 in 50,000 newborns.
- The 2018 reclassification. The Alport Syndrome Classification Working Group (Kashtan et al., Kidney International 2018;93:1045-1051) proposed one classification for all genetic disorders of the collagen IV α345 molecule, because the old names were confusing and could delay nephroprotective treatment. Under this scheme a single (heterozygous) COL4A3 or COL4A4 variant, the genotype behind many cases once labeled thin basement membrane nephropathy (TBMN), is called autosomal dominant Alport syndrome, the term GeneReviews now uses.
- "Benign familial hematuria" is out. GeneReviews reports strong consensus against the term, because these patients have a higher risk of kidney failure than the general population; TBMN, "type IV collagen-associated kidney disease" and "Alport spectrum nephropathy" remain in use as alternative names.
- Exam framing: Merck still describes thin basement membrane disease as a separate, usually autosomal dominant condition with isolated microscopic hematuria, a uniformly thin GBM and an excellent prognosis for most, and exam stems use that framing. Choose it for isolated hematuria, a thin GBM and normal hearing, but remember that a thin GBM is also the earliest EM finding in Alport syndrome, so genetic testing separates them.
Pathophysiology: why kidney, ear and eye
COL4A3, COL4A4 and COL4A5 each encode one chain of the α3α4α5 type IV collagen network, a structural mesh of the mature GBM, the organ of Corti in the cochlea, the lens and the retina. The three chains assemble together, so one faulty gene removes the whole network: kidney biopsies from males with XLAS typically show no α3, α4 or α5 staining in the GBM, and in ARAS α3 and α4 are missing. Without it the GBM thins, then thickens and splits, leaks red cells first and protein later, and scars into glomerulosclerosis and CKD. Compare collagen types I-IV in the collagen types visual hack.
Clinical course: hematuria → proteinuria → CKD
- Kidney: persistent microscopic hematuria from early life, then microalbuminuria and overt proteinuria, hypertension and progressive loss of GFR to ESKD (timing by genotype in the table above).
- Ear: sensorineural hearing loss of the higher frequencies, never congenital, usually found in late childhood or early adolescence; less frequent and later in women with XLAS.
- Eye: anterior lenticonus (reported in about 25-50% of males with XLAS), perimacular "dot-and-fleck" retinopathy (whitish-yellow flecks around the macula; about 70% of males with XLAS), posterior polymorphous corneal dystrophy and recurrent corneal erosion. These eye changes seldom cause vision loss.
Diagnosis
- Genetic testing comes first: a multigene panel that includes COL4A3, COL4A4 and COL4A5 for anyone with persistent glomerular hematuria plus suggestive features or family history.
- Kidney biopsy, when needed: no immune-complex pattern on routine immunofluorescence, abnormal staining for collagen IV chains (absent in XLAS males, a patchy "mosaic" pattern in heterozygous females, α3 and α4 absent in ARAS), and the EM picture of diffuse thinning early, then a lamina densa split into interlacing strands ("basket-weave") with variable thickening and thinning.
- Skin biopsy: in about 80% of males with XLAS, staining for the α5 chain is absent from the epidermal basement membrane.
- Complement is normal, because this is a structural disease, not immune-complex nephritis.
Treatment and transplantation
- ACE inhibitor (or ARB if not tolerated), because early treatment delays ESKD. GeneReviews advises starting at diagnosis (once older than 12-24 months) in males with XLAS and in ARAS, and when microalbuminuria appears in women with XLAS and in ADAS. Review RAAS blocker side effects in the ACE inhibitor vs ARB mnemonic.
- Otherwise manage as CKD: good hydration, less loud-noise exposure, hearing aids, and genetic counseling for the family.
- Kidney transplantation is not contraindicated, and Alport syndrome does not recur in the graft because the donor kidney has a normal GBM. Relatives who carry a variant are generally unsuitable living donors (GeneReviews: a last resort only, and not before age 40 or with any kidney damage).
- Post-transplant anti-GBM nephritis is the classic twist. It is uncommon (StatPearls estimates about 3%), usually appears within the first post-transplant year, and is most likely in people who make no α345 network at all: the recipient's immune system meets normal α345 collagen in the donor GBM for the first time and makes antibodies against it, causing crescentic GN with linear IgG. GeneReviews advises monthly monitoring for it during the first year in males with truncating COL4A5 variants and in ARAS.
Alport vs its look-alikes
| Alport syndrome | TBMN pattern (one COL4A3/4 variant) | IgA nephropathy | Poststreptococcal GN | Anti-GBM disease | |
|---|---|---|---|---|---|
| Inheritance | X-linked (most), AR, AD | Autosomal dominant | Usually sporadic | Acquired | Acquired (autoimmune) |
| Hematuria | Persistent from childhood | Persistent, often isolated | Gross, 1-2 days after a mucosal infection | 6-21 days after infection | Rapidly progressive GN |
| Ears and eyes | Hearing loss, lenticonus, flecks | Usually normal | Normal | Normal | Normal (lungs may bleed) |
| C3 | Normal | Normal | Usually normal | Low, normal again in 6-8 weeks | Usually normal |
| Immunofluorescence | No immune complexes | No immune complexes | Granular mesangial IgA | Granular IgG and C3 | Linear IgG |
| EM | Thin, then thickened and split | Uniformly thin GBM | Mesangial deposits | Subepithelial humps | No deposits; crescents on light microscopy |
How USMLE tests it
- Boy with hematuria + sensorineural hearing loss (+ eye findings) → Alport syndrome, COL4A5, X-linked.
- "Basket-weave" or "split lamina densa" on EM → Alport syndrome.
- Isolated familial hematuria, uniformly thin GBM, normal hearing → thin basement membrane disease.
- Alport patient with a new kidney transplant and rapidly progressive GN with linear IgG → post-transplant anti-GBM disease.
- Best long-term drug? An ACE inhibitor, not steroids or immunosuppression.
- X-linked pedigree: affected males linked through their mothers, no male-to-male transmission (see the X-linked disorders flowchart).
Key takeaways
- Alport = defective α3α4α5 type IV collagen in the GBM, cochlea and eye; COL4A5 (X-linked) in most families, COL4A3/COL4A4 (recessive or dominant) in the rest.
- Hematuria from early childhood → proteinuria → CKD; about half of XLAS males reach ESKD by 35.
- Sensorineural hearing loss (never congenital), anterior lenticonus and dot-and-fleck retinopathy.
- EM: thin early, then thickened, split "basket-weave" lamina densa; immunofluorescence shows no immune complexes; complement is normal.
- Genetic testing first; ACE inhibitor early.
- Old "TBMN" with one COL4A3/COL4A4 variant = autosomal dominant Alport syndrome (2018 classification).
- After transplant, watch for anti-GBM nephritis.
Sources
- Alport Syndrome — GeneReviews, NCBI Bookshelf (2025)
- Alport syndrome — MedlinePlus Genetics (2023)
- Alport syndrome: a unified classification of genetic disorders of collagen IV α345: a position paper of the Alport Syndrome Classification Working Group — Kidney International (2018)
- Alport Syndrome — Merck Manual Professional Edition (2026)
- Thin Basement Membrane Disease — Merck Manual Professional Edition (2025)
- Immunoglobulin A Nephropathy — Merck Manual Professional Edition (2025)
- Postinfectious Glomerulonephritis (PIGN) — Merck Manual Professional Edition (2025)
- Anti-Glomerular Basement Membrane (Anti-GBM) Disease — Merck Manual Professional Edition (2025)
- Alport Syndrome — StatPearls, NCBI Bookshelf (2023)
- IgA Nephropathy (Berger Disease) — StatPearls, NCBI Bookshelf (2024)
- Anti-GBM nephritis — PathologyOutlines.com (2021)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
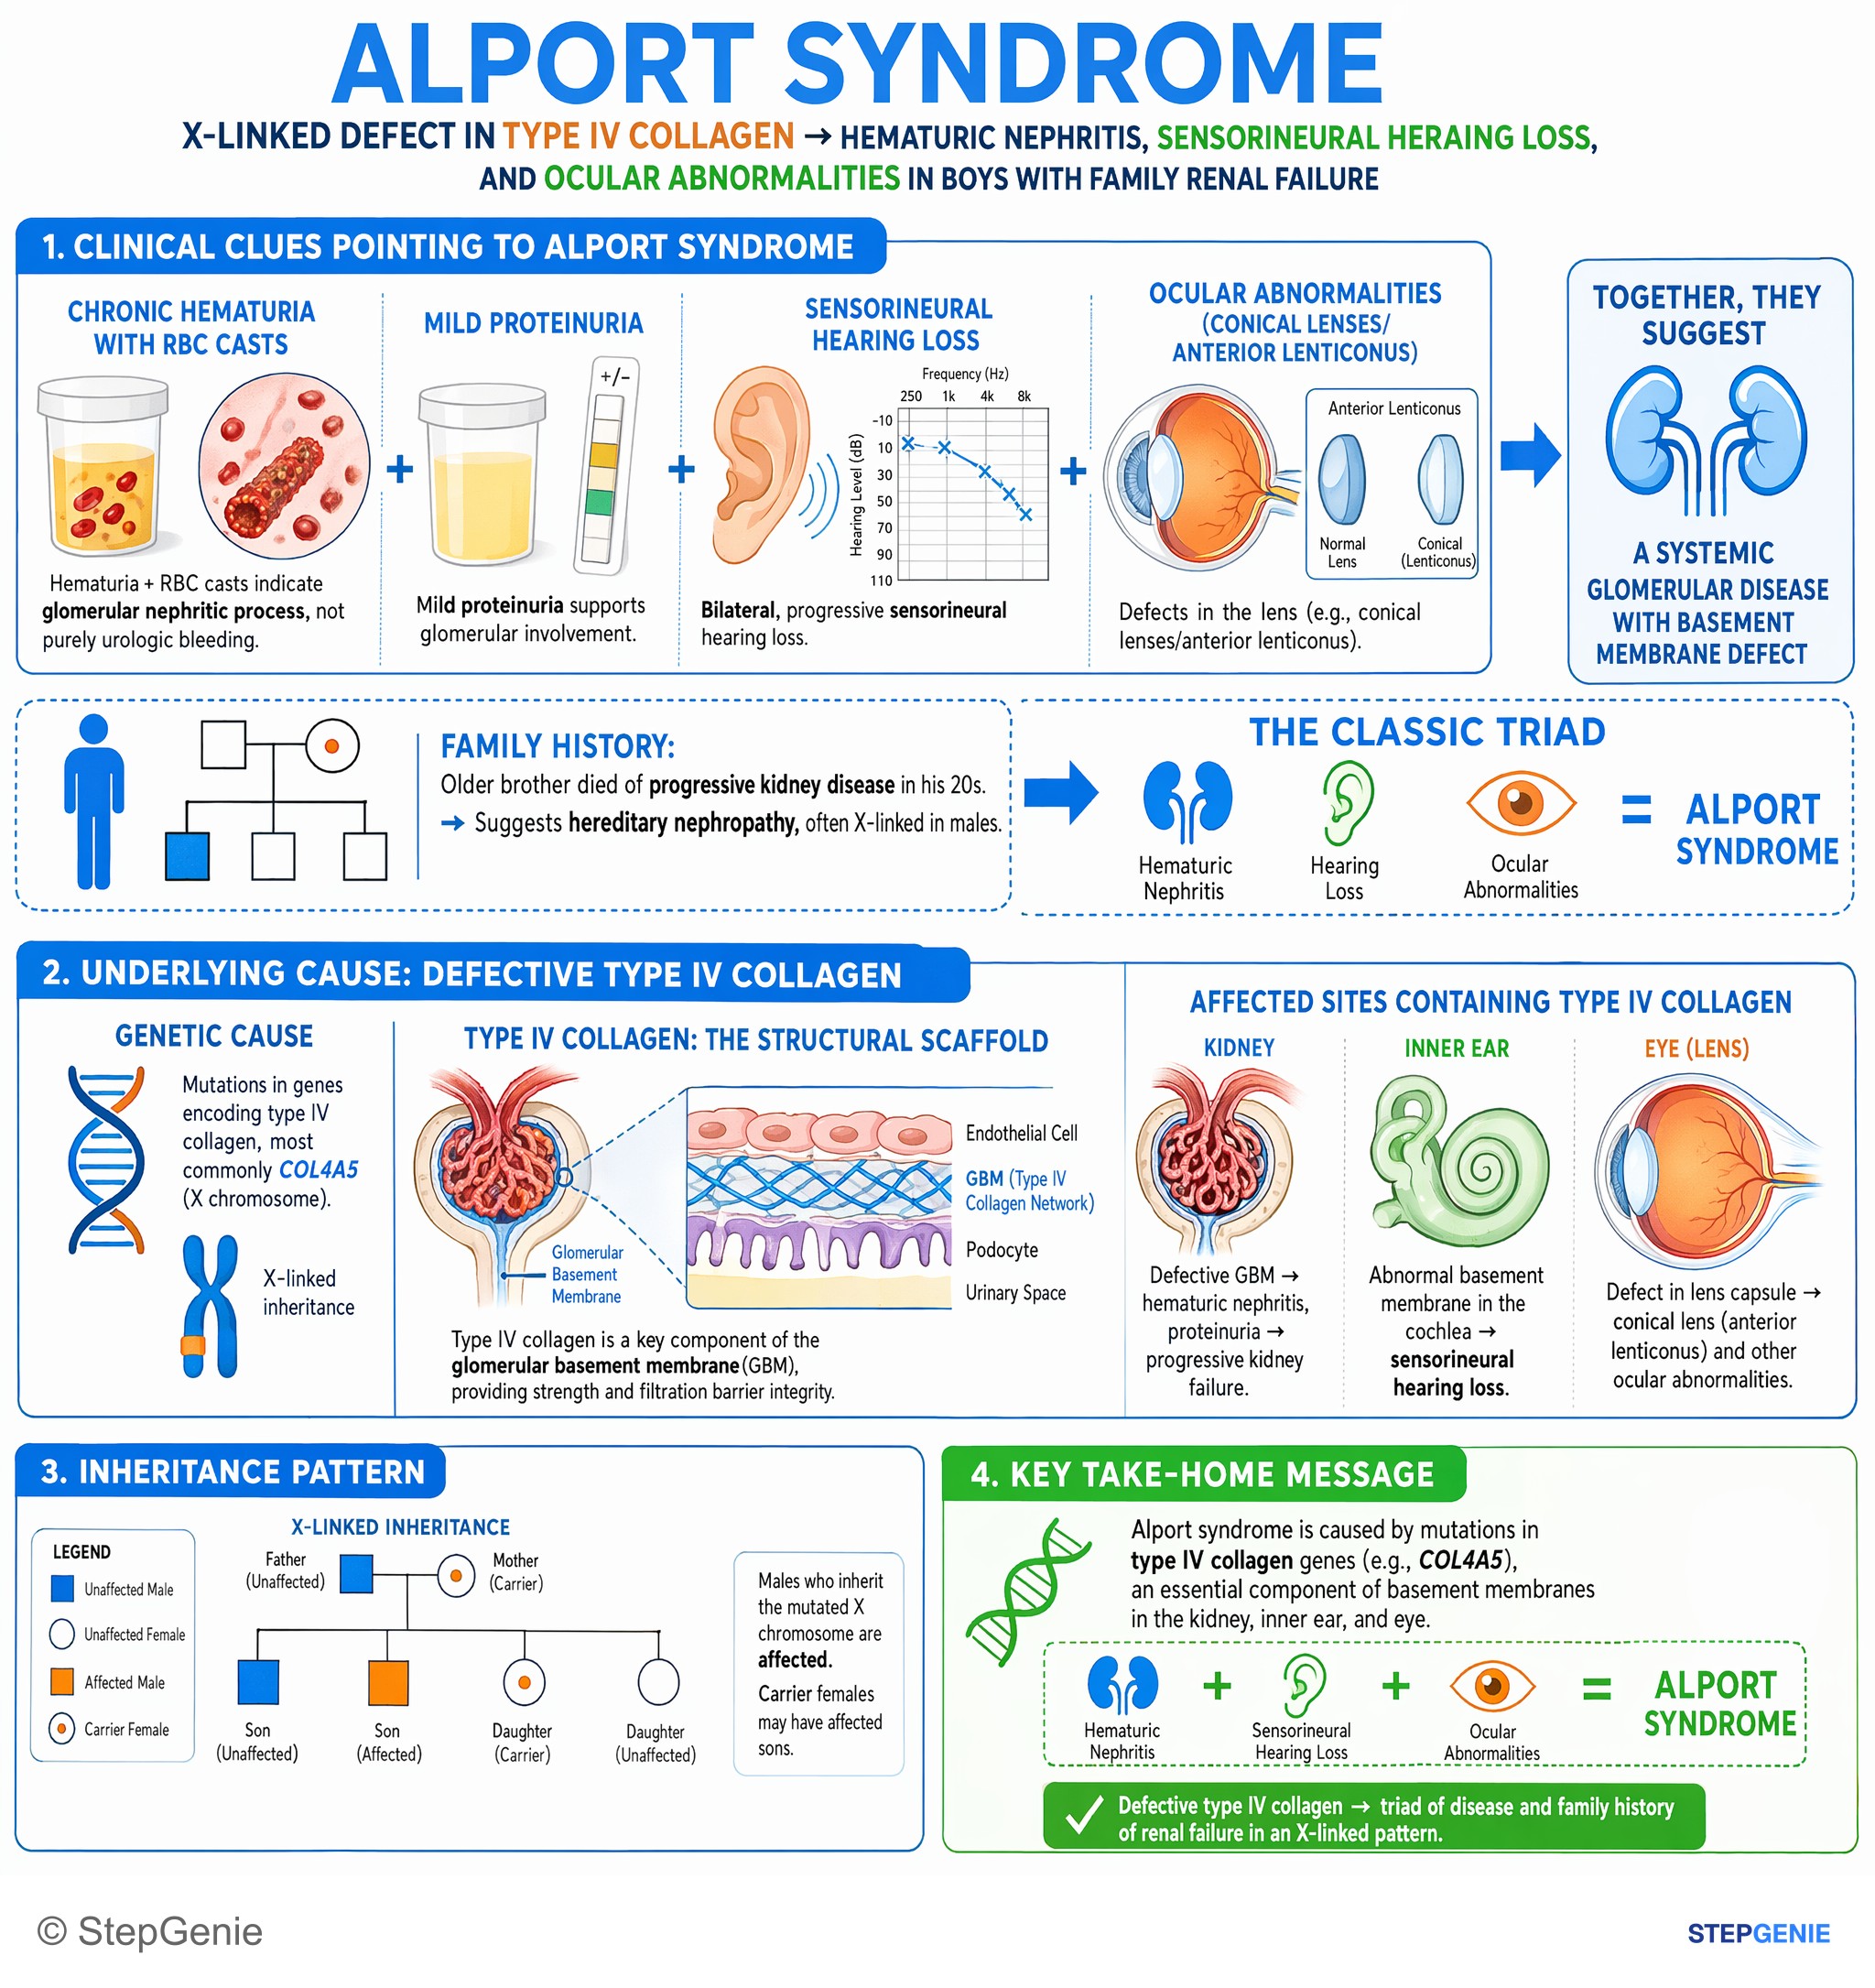
Alport syndrome: X-linked defect in type IV collagen → hematuric nephritis, sensorineural hearing loss, and ocular abnormalities in boys…
USMLE Step 1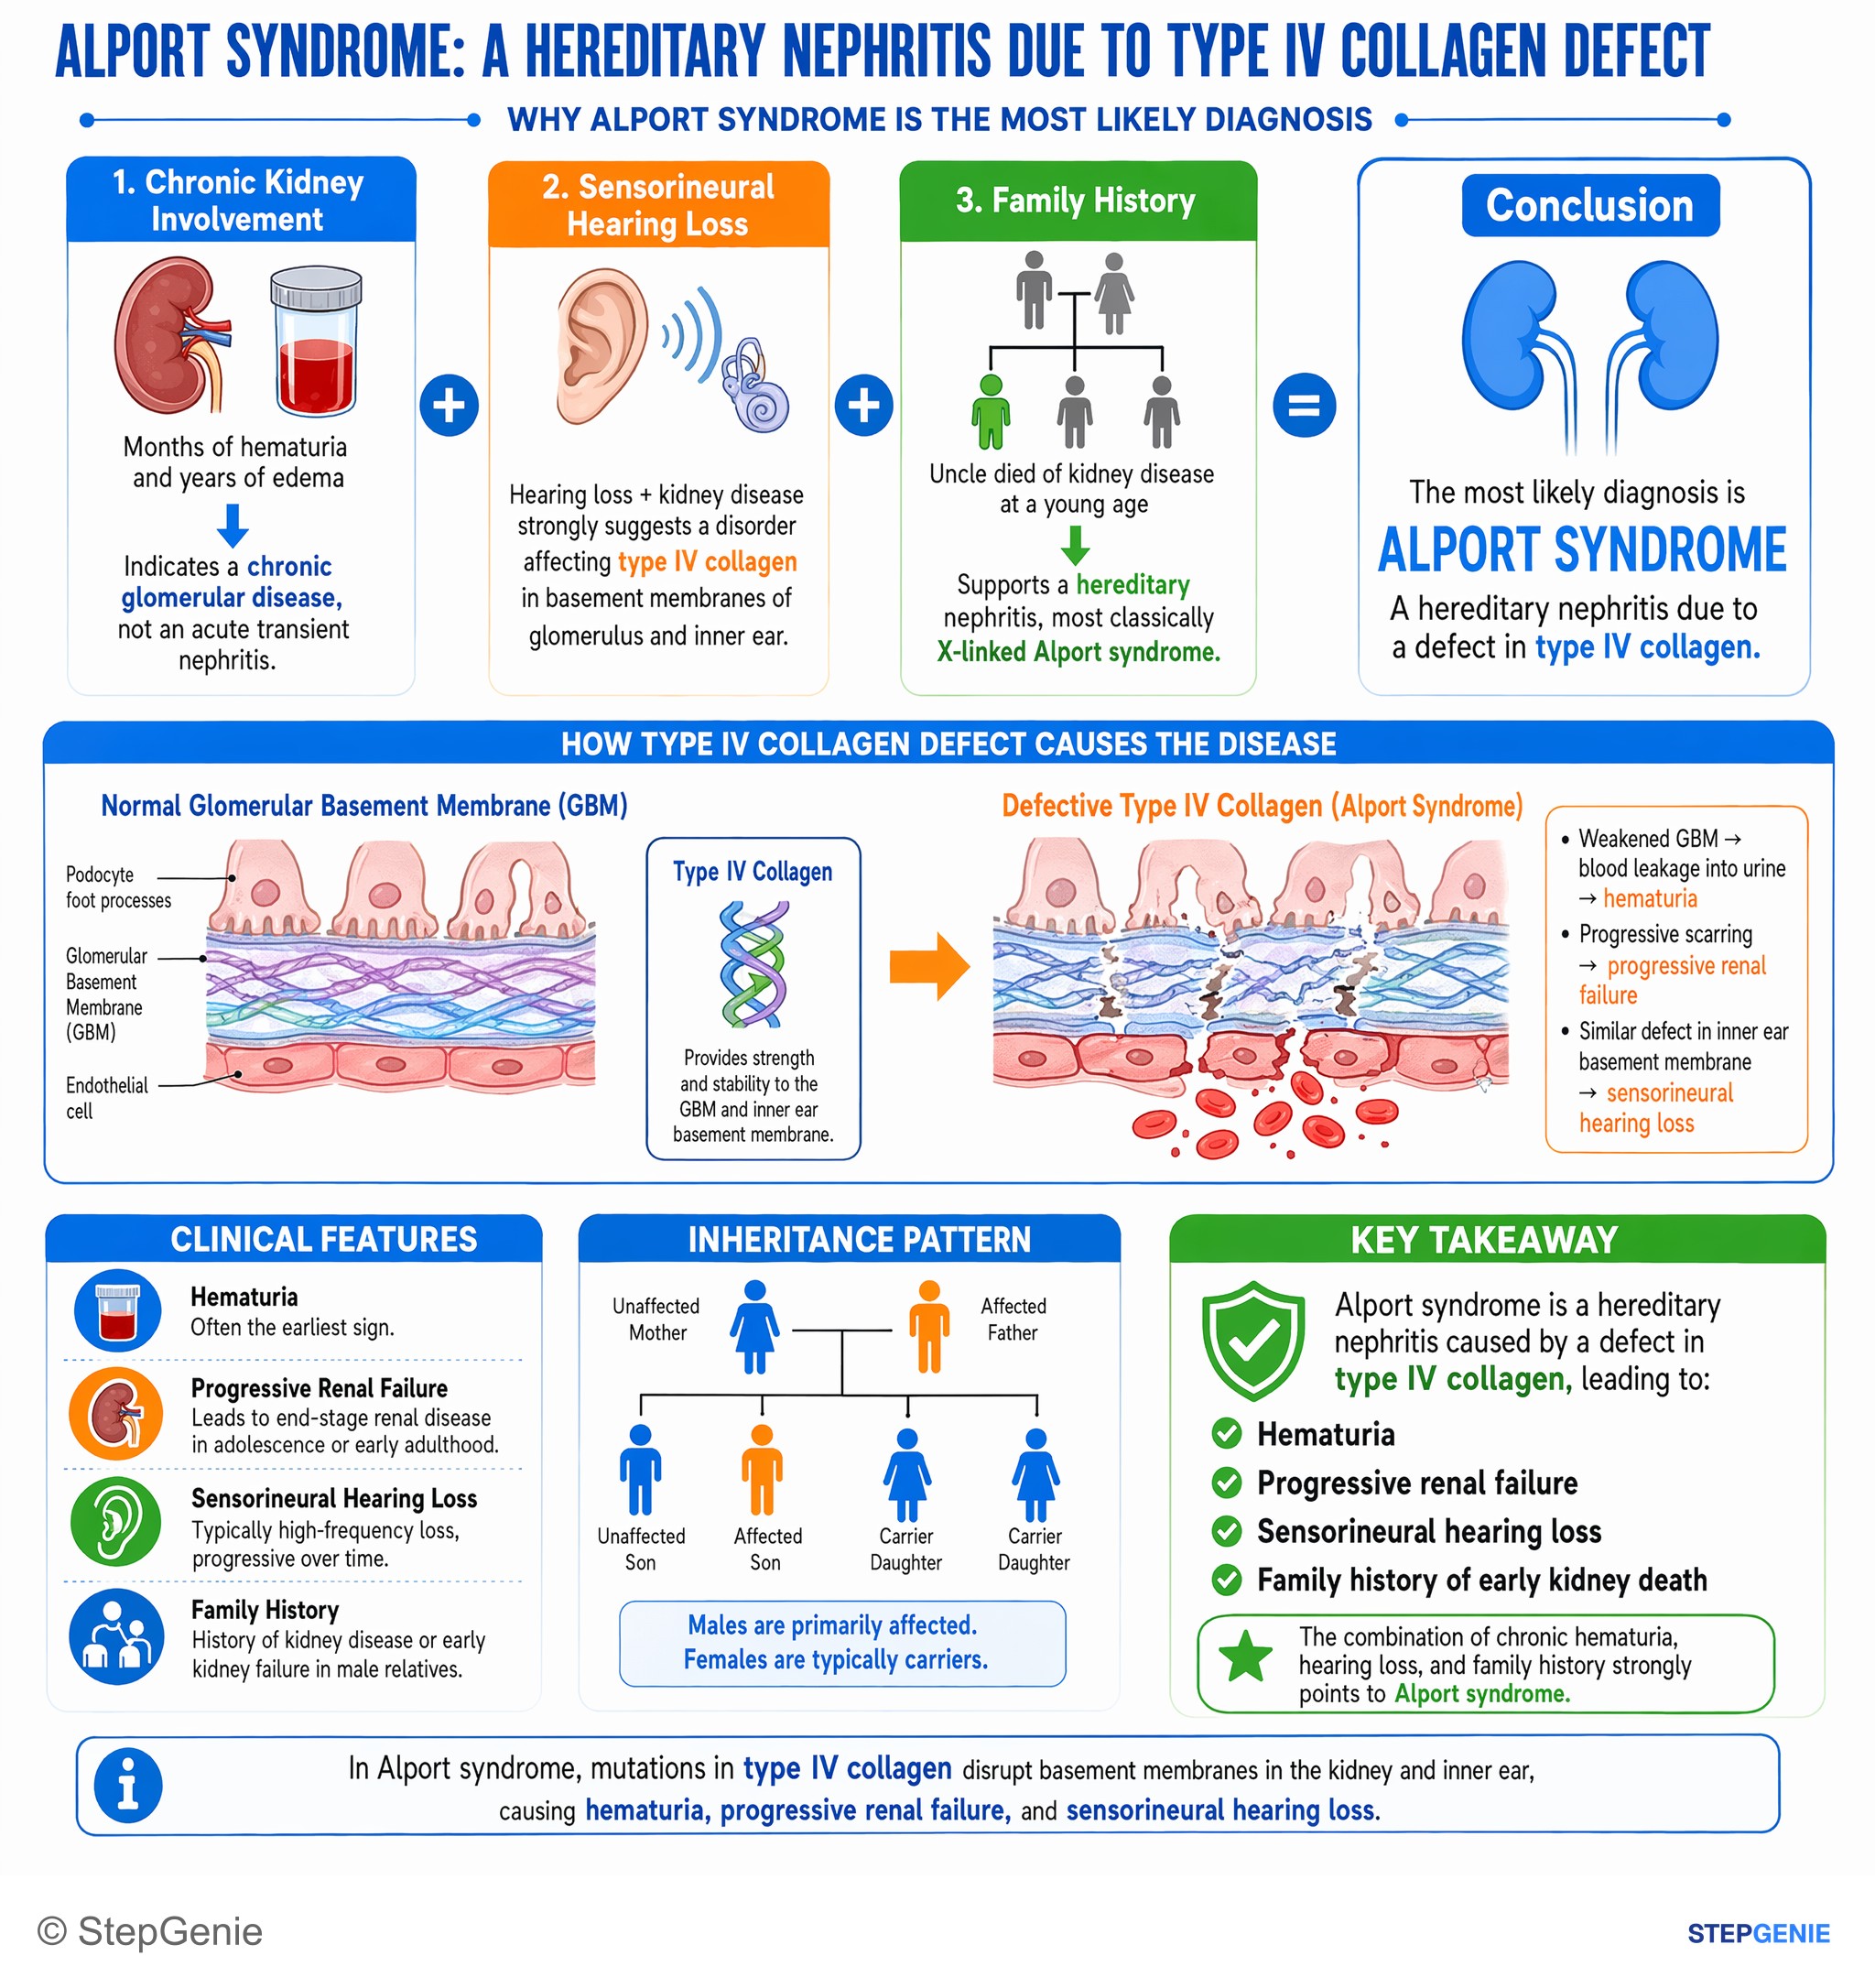
Alport syndrome: hereditary nephritis due to type IV collagen defect → hematuria, progressive renal failure, sensorineural hearing loss…
USMLE Step 1Frequently Asked Questions
What causes Alport syndrome?
Alport syndrome is caused by pathogenic variants in COL4A3, COL4A4 or COL4A5, the genes for the α3, α4 and α5 chains of type IV collagen. These chains form a network in the glomerular basement membrane, the cochlea and the eye, so one faulty chain weakens all three tissues. Most families have the X-linked form caused by COL4A5; others have autosomal recessive or autosomal dominant disease caused by COL4A3 or COL4A4, and a few have variants in two genes.
What is the classic triad of Alport syndrome?
The classic triad is kidney disease, sensorineural hearing loss and eye abnormalities. Kidney disease starts as persistent microscopic hematuria in early childhood and progresses to proteinuria, hypertension and chronic kidney disease. The hearing loss affects high frequencies, is never present at birth and usually appears in late childhood or early adolescence. Eye findings include anterior lenticonus, which is virtually pathognomonic, and dot-and-fleck retinopathy around the macula; these eye changes seldom cause vision loss.
What does Alport syndrome look like on kidney biopsy?
Routine immunofluorescence shows no immune-complex deposits, which separates Alport syndrome from IgA nephropathy, postinfectious glomerulonephritis and anti-GBM disease. Electron microscopy shows diffuse thinning of the glomerular basement membrane early on, then irregular thickening with the lamina densa split into interlacing strands, the basket-weave pattern. Collagen IV staining is typically absent for the α3, α4 and α5 chains in males with X-linked disease and patchy in heterozygous females. Genetic testing is now the first-line diagnostic test.
How is Alport syndrome different from thin basement membrane disease?
Thin basement membrane disease usually causes isolated, persistent microscopic hematuria with a uniformly thin glomerular basement membrane, autosomal dominant inheritance and normal hearing, and most patients do well long term. Many of these patients carry one COL4A3 or COL4A4 variant, so a 2018 expert classification groups them under autosomal dominant Alport syndrome. Classic Alport syndrome instead shows a thickened, split basement membrane, hearing loss, eye findings and progressive kidney failure, especially in males with X-linked disease.
How is Alport syndrome treated?
There is no cure, but an ACE inhibitor, or an angiotensin receptor blocker if an ACE inhibitor is not tolerated, delays kidney failure, and early treatment works best. GeneReviews advises starting at diagnosis in males with X-linked disease and in autosomal recessive disease once the child is older than 12 to 24 months, and when microalbuminuria appears in heterozygous women and in autosomal dominant disease. Hearing aids, standard CKD care, dialysis and kidney transplantation follow as needed.
Why can people with Alport syndrome get anti-GBM disease after a kidney transplant?
Many people with Alport syndrome, especially males with X-linked disease, never make normal α3α4α5 type IV collagen, so their immune system has never encountered it. A transplanted kidney has a normal glomerular basement membrane, and some recipients make antibodies against it, causing anti-GBM glomerulonephritis with linear IgG staining. It is uncommon (about 3% in one estimate), and Alport syndrome itself does not recur in the new kidney. Recipients at highest risk, males with truncating COL4A5 variants and people with autosomal recessive disease, are monitored monthly for anti-GBM antibodies during the first year.