Muddy brown granular casts are coarse, brown-pigmented granular casts made of sloughed, degenerating renal tubular epithelial cells and debris held in a uromodulin (Tamm–Horsfall protein) matrix; they are the urine sediment signature of acute tubular necrosis (ATN). They are highly specific for tubular injury (100% specificity and positive predictive value in a biopsy-checked series), but a sample without them does not rule ATN out.
ATN is tubular cell injury from ischemia (shock, sepsis, major surgery) or nephrotoxins (aminoglycosides, amphotericin B, cisplatin, iodinated contrast, heme pigments, ethylene glycol). Injured tubules can't conserve sodium or concentrate urine; the classic pattern is a FENa above 2%, urine sodium above 40 mEq/L, urine osmolality below 350 mOsm/kg and a BUN:creatinine ratio of 10–15:1, against a FENa below 1% and a bland or hyaline-cast sediment in prerenal azotemia. GFR falls through tubular obstruction, backleak of filtrate and afferent arteriolar constriction triggered by tubuloglomerular feedback.
What muddy brown granular casts are
A urinary cast forms inside a tubule lumen on a matrix of uromodulin, which the thick ascending limb makes in large amounts; uromodulin alone forms a hyaline cast. Tubular cells that slough into the lumen are trapped in this matrix and degenerate into granules, making a granular cast. In ATN these coarse granular casts are often pigmented and described as "muddy brown," usually alongside free tubular epithelial cells and epithelial cell casts. KDIGO counts them as clues to the cause of AKI, not as part of its definition.
They have to be looked for: in 25 patients with ATN, an automated analyzer reported granular casts in 24% of samples, against 72% when a nephrologist examined the sediment by hand. Not every pigmented cast is a muddy brown cast: myoglobin casts occur in rhabdomyolysis, bilirubin casts in liver failure.
How sensitive and specific are muddy brown casts?
A positive finding nearly clinches tubular injury; a negative one proves little.
| Study | Patients | Key result |
|---|---|---|
| Perazella 2008 | 267 inpatients with AKI | With ATN suspected, any granular cast or tubular cell gave a positive predictive value of 100% but a negative predictive value of 44%; with prerenal AKI suspected, a clean sediment had 73% sensitivity and 75% specificity for prerenal AKI |
| Varghese 2021 | 121 with stage ≥2 AKI | Of those whose first sample was non-diagnostic, 22–23% showed tubular injury on a repeat examination days later |
| Varghese 2022 | 270 AKI consultations | Muddy brown casts in 49%; 38% of those patients had a FENa below 1%; in the 49 biopsied patients, 100% specificity and positive predictive value but 78% sensitivity |
In septic AKI the evidence is weak: some reports describe muddy brown casts, others a normal sediment. Granular casts and tubular cells also appear in about 86% of acute interstitial nephritis (AIN), where white cells usually give it away. If AKI isn't recovering and the first sample was bland, repeat the microscopy.
Muddy brown casts vs other urine casts
| Sediment finding | Points to |
|---|---|
| Muddy brown granular casts, tubular epithelial cells and cell casts | ATN |
| Hyaline casts (uromodulin alone) | Prerenal states and dehydration (concentrated urine), strenuous exercise, fever |
| RBC casts, dysmorphic RBCs | Glomerulonephritis or vasculitis; occasionally AIN, rarely ATN |
| WBC casts, white cells | AIN (sterile pyuria; WBC casts in only 14% of biopsy-proven cases), pyelonephritis, glomerulonephritis |
| Waxy (broad, refractile, cracked) casts | Kidney failure, acute or chronic |
| Fatty casts, oval fat bodies ("Maltese cross" under polarized light) | Nephrotic-range proteinuria |
| Dipstick positive for blood, few or no RBCs | Myoglobin or hemoglobin: pigment nephropathy |
| Calcium oxalate crystals (also seen in normal urine) | Ethylene glycol poisoning, in context |
| Bland sediment | Prerenal or postrenal AKI; about 20% of AIN |
The glomerular patterns are drilled in nephrotic vs nephritic syndrome.
How ATN lowers GFR: tubular backleak, obstruction and afferent vasoconstriction
"Acute tubular necrosis" is a misnomer: outside rare necrotic cells, human biopsies show detached and sloughed cells, loss of the proximal brush border, casts and regenerating cells. Exams test three mechanisms for the fall in GFR; how much each contributes in patients is not settled.
| Mechanism | What happens | Why GFR falls |
|---|---|---|
| Tubular backleak | Ischemia disrupts tight and adherens junctions, and cells that lose their basement-membrane integrins detach | Filtrate leaks back into the interstitium and blood, so filtered markers return to the circulation; inulin injected into post-ischemic tubules in experiments reappeared in the other kidney's urine |
| Tubular obstruction | Detached cells clump and combine with uromodulin into casts | Pressure behind the plug opposes filtration |
| Tubuloglomerular feedback | Injured proximal tubules reabsorb less sodium, so more NaCl reaches the macula densa, which signals through adenosine A1 receptors | The afferent arteriole constricts and glomerular pressure falls |
The normal feedback loop is covered in renal blood flow autoregulation.
The Q-bank vignette
A 67-year-old man is admitted to the ICU with septic shock from pneumonia. He needs norepinephrine for 36 hours and is started on broad-spectrum antibiotics. Over the next 48 hours his urine output falls to about 15 mL/hour. He has no rash, and his eosinophil count is normal.
- BUN 45 mg/dL, creatinine 3.0 mg/dL (baseline 1.0), BUN:creatinine ratio 15
- Urine sodium 58 mEq/L, FENa 3%, urine osmolality 310 mOsm/kg
- Urine microscopy: many muddy brown granular casts and renal tubular epithelial cells; no white cells, no RBC casts, no WBC casts
- Urine dipstick negative for blood; serum creatine kinase normal
- Renal ultrasound: normal-sized kidneys, no hydronephrosis
- No iodinated contrast has been given
Which of the following is the most likely cause of this patient's acute kidney injury?
- A. Prerenal azotemia from hypovolemia
- B. Acute tubular necrosis from renal ischemia
- C. Drug-induced acute interstitial nephritis
- D. Rapidly progressive glomerulonephritis
- E. Postrenal obstruction from benign prostatic hyperplasia
- F. Pigment nephropathy from rhabdomyolysis
- G. Contrast-induced acute kidney injury
Correct answer: B, acute tubular necrosis from ischemia
Thirty-six hours of vasopressor-dependent shock is a classic ischemic insult, and every urine finding shows injured, not merely underperfused, tubules:
- Muddy brown casts and tubular cells: injured cells sloughing into the lumen.
- FENa 3%, urine sodium 58 mEq/L: sodium is no longer conserved.
- Urine osmolality 310 mOsm/kg, close to plasma: urine is no longer concentrated.
- BUN:creatinine 15: typical of ATN; prerenal states push it above 20:1.
A creatinine of 3.0 times baseline also makes this KDIGO stage 3 AKI.
Why every distractor is wrong
A. Prerenal azotemia from hypovolemia
Why it's tempting: Septic shock lowers renal perfusion, and prerenal physiology usually comes first.
Why it's wrong: Intact tubules conserve sodium and water (FENa below 1%, urine sodium below 20 mEq/L, osmolality above 500 mOsm/kg, BUN:creatinine above 20:1) and respond promptly to IV saline; his indices show the opposite. Untreated, prerenal azotemia can progress to ischemic ATN; see prerenal vs intrinsic vs postrenal AKI.
C. Drug-induced acute interstitial nephritis
Why it's tempting: He has just started antibiotics, and beta-lactams are the most common cause of drug-induced AIN.
Why it's wrong: Timing can't exclude AIN (onset ranges from 1 day with rifampin to 18 months with NSAIDs), and fever, rash and eosinophilia occur together in fewer than 10% of drug-induced cases, so the urine decides: AIN gives sterile pyuria and white cells, sometimes WBC casts, and urine eosinophils can neither make nor exclude it. He has none of these.
D. Rapidly progressive glomerulonephritis
Why it's tempting: A rapid creatinine rise with an abnormal sediment.
Why it's wrong: Glomerulonephritis gives hematuria with dysmorphic RBCs and RBC casts; his casts are granular and his dipstick is negative for blood.
E. Postrenal obstruction from benign prostatic hyperplasia
Why it's tempting: An older man whose urine output has fallen.
Why it's wrong: Obstruction shows on a bladder scan (a post-void residual over 100 mL suggests inadequate emptying) or as hydronephrosis on ultrasound. His ultrasound is normal (though it can miss very acute obstruction), and his urine shows tubular injury.
F. Pigment nephropathy from rhabdomyolysis
Why it's tempting: Myoglobin causes ATN, and critically ill patients can develop rhabdomyolysis.
Why it's wrong: Look for a dipstick positive for blood with few or no RBCs and a creatine kinase typically above 5 times the upper limit of normal; he has neither. Muscle pain, weakness and dark urine occur together in fewer than 10% of patients, so the labs matter more than the history.
G. Contrast-induced acute kidney injury
Why it's tempting: Iodinated contrast is a classic hospital nephrotoxin.
Why it's wrong: It needs a contrast exposure, with creatinine rising 24–48 hours later. He had none.
Ischemic vs nephrotoxic ATN
Ischemic ATN is the most common form, especially in the ICU; nephrotoxins are the other major cause.
| Cause | How it injures the tubule | Exam clues |
|---|---|---|
| Ischemia: septic or hemorrhagic shock, major surgery, pancreatitis | ATP depletion, worst in the outer medulla | Hypotension or vasopressors, then ATN indices |
| Aminoglycosides | Megalin uptake concentrates the drug in proximal tubule cells | Nonoliguric; creatinine rises later than after contrast; once-daily dosing |
| Amphotericin B | Tubular toxicity, including distal RTA | Hypokalemia, hypomagnesemia, nephrogenic diabetes insipidus |
| Cisplatin | Uptake into proximal tubule cells through OCT2 | Nonoliguric rise days after a dose, glycosuria, hypomagnesemia; saline prehydration |
| Iodinated contrast | Renal vasoconstriction plus direct tubular toxicity | Creatinine up 24–48 hours later; classic peak at 3–5 days, baseline by 7–10 days |
| Myoglobin (rhabdomyolysis) | Vasoconstriction, myoglobin–uromodulin casts in acidic, concentrated urine, heme-iron oxidant injury | CK above 5 times normal, heme-positive dipstick without RBCs, hyperkalemia, hypocalcemia |
| Hemoglobin (severe hemolysis) | Heme pigment injury | Heme-positive dipstick without RBCs, high LDH, falling hemoglobin |
| Ethylene glycol | Calcium oxalate deposits with tubular injury | High anion gap acidosis, osmolar gap, calcium oxalate crystals |
Others include vancomycin, colistin, calcineurin inhibitors, NSAIDs with poor renal perfusion, IV immunoglobulin and tenofovir. Go deeper with contrast nephropathy, rhabdomyolysis-induced AKI and toxic alcohols in anion gap metabolic acidosis.
Why the S3 segment and the medullary thick ascending limb fail first
- Little oxygen. The outer medulla runs at a pO2 of 10–20 mm Hg, against 50–60 mm Hg in the cortex.
- No glycolytic backup. Both segments are highly metabolically active but have limited glycolytic capacity, so ATP collapses when oxidative phosphorylation fails; medullary collecting duct cells keep about 60% of their ATP.
- Flow stays poor. Congested outer medullary capillaries and trapped leukocytes prolong hypoxia during the extension phase, while cortical proximal tubules recover.
- Cell death concentrates there. In a rat model, S1 and S2 injury was largely reversible and cell death localized to S3. In human ATN the S3 segment is generally viewed as the main site; the thick ascending limb's share is debated because biopsies rarely sample the medulla.
Nephrotoxins follow drug uptake instead (megalin, OCT2), mostly in the proximal tubule. Segment roles are reviewed in nephron anatomy and function.
Clinical course: initiation, maintenance and recovery
Pathophysiology reviews divide ischemic ATN into initiation (ATP depletion, cell injury), extension (ongoing medullary hypoxia and inflammation, GFR still falling), maintenance (GFR low but stable during repair) and recovery; StatPearls uses early injury, later injury, recovery and long-term outcomes. At the bedside:
- Prodromal phase: urine output usually normal.
- Oliguric phase: typically 50–500 mL/day for an unpredictable time, though many patients are never oliguric (aminoglycoside ATN typically isn't), and nonoliguric patients have lower mortality. Watch for hyperkalemia, pulmonary edema, metabolic acidosis (bicarbonate usually 15–20 mmol/L), hyperphosphatemia, hypocalcemia and uremia (bleeding, encephalopathy, pericarditis).
- Postoliguric (recovery) phase: urine output returns, but creatinine may not fall for several more days, and tubular dysfunction can last days to weeks: sodium wasting, polyuria unresponsive to vasopressin, hyperchloremic acidosis. Hypokalemia, hypomagnesemia, hypophosphatemia and hypocalcemia are common; in one series of 50 patients recovering from acute renal failure, 31 became hypomagnesemic.
In otherwise healthy patients creatinine usually returns to or near normal within 1 to 3 weeks, but ATN raises the long-term risk of CKD.
Urine indices: ATN vs prerenal AKI, and when they mislead
| Index | Prerenal azotemia | ATN |
|---|---|---|
| FENa | < 1% | > 2% |
| FEUrea (useful on diuretics) | < 35% | > 35% |
| Urine sodium (mEq/L) | < 20 | > 40 |
| Urine osmolality (mOsm/kg) | > 500 | < 450, usually < 350 |
| Urine specific gravity | > 1.020 | ≤ 1.010 |
| BUN:creatinine ratio | > 20:1 | 10–15:1 |
| Urine/plasma creatinine | > 40 | < 20 |
| Response to IV fluid | Output and creatinine improve | Little or no rapid change |
The exam expects these classic cut-offs; references differ at the margins (Merck's AKI chapter uses urine sodium below 10 for prerenal AKI and BUN:creatinine below 10 for tubular injury). The exceptions are tested too:
- Diuretics and glycosuria raise FENa in prerenal patients; use FEUrea. A 2026 meta-analysis (12 studies, 1,240 patients) found cut-offs of 30% to 40% (weighted mean 33.4%), pooled sensitivity 0.74 and specificity 0.78, with accuracy maintained on diuretics.
- A low FENa doesn't exclude ATN: it occurs early in contrast and pigment nephropathy, in ATN on top of heart failure or cirrhosis, and in 38% of patients with muddy brown casts in the 2022 cohort.
- Sepsis and critical illness scramble the indices: in 83 ICU patients with AKI, FENa was below 1% in 58%, septic or not.
- CKD and nonoliguria: advanced CKD may keep FENa above 1% despite hypoperfusion, and the indices are unreliable in nonoliguric AKI.
KDIGO AKI definition and staging
KDIGO 2012 defines AKI as any of: serum creatinine up by ≥0.3 mg/dL within 48 hours; creatinine ≥1.5 times baseline within the prior 7 days; or urine output below 0.5 mL/kg/h for 6 hours.
| Stage | Serum creatinine | Urine output |
|---|---|---|
| 1 | 1.5–1.9 times baseline, or rise of ≥0.3 mg/dL | < 0.5 mL/kg/h for 6–12 h |
| 2 | 2.0–2.9 times baseline | < 0.5 mL/kg/h for ≥12 h |
| 3 | 3.0 times baseline, or creatinine ≥4.0 mg/dL, or start of kidney replacement therapy (or eGFR < 35 mL/min/1.73 m² in patients under 18) | < 0.3 mL/kg/h for ≥24 h, or anuria for ≥12 h |
Use whichever criterion gives the higher stage. The 2012 guideline is still the published standard: KDIGO's 2026 guideline on AKI and acute kidney disease has been through public review, and on October 15, 2026 KDIGO's site says it is being prepared for publication.
Management and dialysis indications
- Restore perfusion, remove toxins: isotonic crystalloids rather than colloids, vasopressors with fluids in vasomotor shock, no nephrotoxins, renal dose adjustment.
- Don't chase urine output: KDIGO recommends against low-dose dopamine to prevent or treat AKI (grade 1A) and against diuretics to prevent it, and suggests against diuretics to treat it except for volume overload; there is no evidence for mannitol.
- Prevent the next hit: once-daily aminoglycosides with level monitoring; lipid amphotericin B, or an azole or echinocandin when equally effective; for contrast, the lowest dose of a low- or iso-osmolar agent plus IV isotonic fluid in high-risk patients (the ACR–NKF consensus calls saline indicated before IV contrast with AKI or an eGFR below 30, if not on dialysis).
- Hyperkalemia: IV calcium gluconate when the ECG shows lost P waves or a widened QRS, plus insulin with glucose; binders, diuretics or dialysis then remove potassium (hypokalemia and hyperkalemia).
Start dialysis emergently for life-threatening fluid, electrolyte or acid–base changes: potassium (e.g., above 6 mmol/L) that can't otherwise be controlled, pulmonary edema despite treatment, metabolic acidosis unresponsive to treatment, or uremic symptoms (vomiting, asterixis, encephalopathy, pericarditis, seizures), and for some poisonings such as ethylene glycol. BUN and creatinine alone are not reliable triggers; the AEIOU checklist is in the dialysis indications guide.
Two more Q-bank vignettes
Vignette 2: contrast vs prerenal. A 66-year-old woman with diabetes and CKD (baseline creatinine 1.6 mg/dL) has coronary angiography with a large contrast load. Thirty-six hours later her creatinine is 2.3 mg/dL; she is euvolemic and on no new drugs. FENa is 0.8%, the sediment shows granular casts and tubular cells, and she has no livedo or eosinophilia. Prerenal azotemia, contrast-induced AKI, atheroemboli or AIN?
Answer: Contrast-induced AKI, KDIGO stage 1.
Reasoning: Creatinine rose within 24–48 hours of a large dose in a high-risk patient, and the sediment shows tubular injury. FENa can be low early in contrast injury, so 0.8% doesn't prove hypovolemia. Atheroemboli suggest themselves with a rise after 48 hours, livedo, eosinophilia or low C3; AIN brings pyuria.
Vignette 3: rhabdomyolysis. A 34-year-old man is found on the floor about 18 hours after an overdose, with dark urine. CK is 62,000 U/L, creatinine 2.8 mg/dL, potassium 6.8 mEq/L with peaked T waves and a widened QRS, and calcium 7.4 mg/dL. The dipstick shows 3+ blood with 0–2 RBCs per high-power field; FENa is 0.7%. What explains the urine, and what comes first?
Answer: Myoglobin pigment nephropathy; IV calcium gluconate plus insulin with glucose for the ECG changes, with IV fluids to expand volume.
Reasoning: Heme-positive urine without red cells means myoglobin (or hemoglobin). FENa can be low early in pigment nephropathy, so 0.7% doesn't make this simple prerenal azotemia. Calcium is low early, and hypercalcemia can follow during recovery.
USMLE traps
| Trap | What's actually true |
|---|---|
| No casts, so no ATN | A single bland sample has a low negative predictive value; repeat it |
| Granular casts always mean ATN | They also appear in most AIN; look for white cells |
| FENa below 1% excludes ATN | Contrast, pigment, sepsis, heart failure and cirrhosis can lower it |
| FENa above 2% on furosemide means ATN | Diuretics raise FENa; FEUrea below 35% favors prerenal |
| Recovery is the safe phase | Polyuria brings sodium wasting, hypokalemia and hypomagnesemia |
| Dialysis starts at a set creatinine | Dialyze for refractory hyperkalemia, acidosis, overload, uremia or toxins |
More walkthroughs are on the Nephrology hub.
Key takeaways
- Muddy brown granular casts are pigmented casts of sloughed tubular cells: highly specific for ATN, but their absence doesn't exclude it.
- Other casts: hyaline (concentrated urine), RBC (glomerulonephritis), WBC (AIN, pyelonephritis), waxy (kidney failure), fatty (nephrotic).
- GFR falls through tubular backleak, obstruction and TGF-driven afferent constriction; the S3 segment and medullary thick ascending limb fail first.
- Classic indices: FENa above 2%, urine sodium above 40, osmolality below 350, BUN:creatinine 10–15:1; use FEUrea on diuretics.
- KDIGO 2012 is still the published standard; dialysis is for complications, not for a number.
Sources
- KDIGO Clinical Practice Guideline for Acute Kidney Injury — Kidney International Supplements (2012)
- KDIGO AKI Guideline Online Appendices A–F — KDIGO (2012)
- Acute Kidney Injury (AKI) and Acute Kidney Disease (AKD) guideline page — KDIGO (2026)
- Acute Renal Tubular Necrosis — StatPearls, NCBI Bookshelf (2025)
- Acute Tubular Necrosis (ATN) — Merck Manual Professional Edition (2024)
- Acute Kidney Injury (AKI) — Merck Manual Professional Edition (2026)
- Contrast Nephropathy — Merck Manual Professional Edition (2024)
- Rhabdomyolysis — Merck Manual Professional Edition (2026)
- Tubulointerstitial Nephritis — Merck Manual Professional Edition (2024)
- Metabolic Acidosis — Merck Manual Professional Edition (2025)
- Hyperkalemia — Merck Manual Professional Edition (2025)
- Basile DP, et al. Pathophysiology of Acute Kidney Injury — Comprehensive Physiology (2012)
- Perazella MA, et al. Diagnostic Value of Urine Microscopy for Differential Diagnosis of AKI in Hospitalized Patients — CJASN (2008)
- Varghese V, et al. Diagnostic Utility of Serial Microscopic Examination of the Urinary Sediment in AKI — Kidney360 (2021)
- Varghese V, et al. Concomitant Identification of Muddy Brown Granular Casts and Low Fractional Excretion of Urinary Sodium in AKI — Kidney360 (2022)
- Gaggar P, Raju SB. Diagnostic Utility of Urine Microscopy in Kidney Diseases — Indian Journal of Nephrology (2024)
- Pan HC, et al. Assessing the Utility of Fractional Excretion of Urea in Distinguishing Intrinsic and Prerenal AKI: A Systematic Review and Meta-analysis — BMJ Open (2026)
- Bagshaw SM, et al. Urine Biochemistry in Septic and Non-septic Acute Kidney Injury — Journal of Critical Care (2013)
- Satish R, Gokulnath G. Serum Magnesium in Recovering Acute Renal Failure — Indian Journal of Nephrology (2008)
- McWilliam SJ, et al. Aminoglycoside-Induced Nephrotoxicity in Children — Pediatric Nephrology (2017)
- Amphotericin B for Injection, USP prescribing information — FDA label via DailyMed (2020)
- Palmer BF, et al. Renal Tubular Acidosis and Management Strategies — Advances in Therapy (2021)
- Miller RP, et al. Mechanisms of Cisplatin Nephrotoxicity — Toxins (2010)
- Davenport MS, et al. Use of Intravenous Iodinated Contrast Media in Patients With Kidney Disease: ACR–NKF Consensus — Kidney Medicine (2020)
- Mohammed NM, et al. Contrast-induced Nephropathy — Heart Views (2013)
- Petejova N, Martinek A. Acute Kidney Injury Due to Rhabdomyolysis and Renal Replacement Therapy — Critical Care (2014)
- Luciano RL, Perazella MA. Crystalline-Induced Kidney Disease: A Case for Urine Microscopy — Clinical Kidney Journal (2015)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
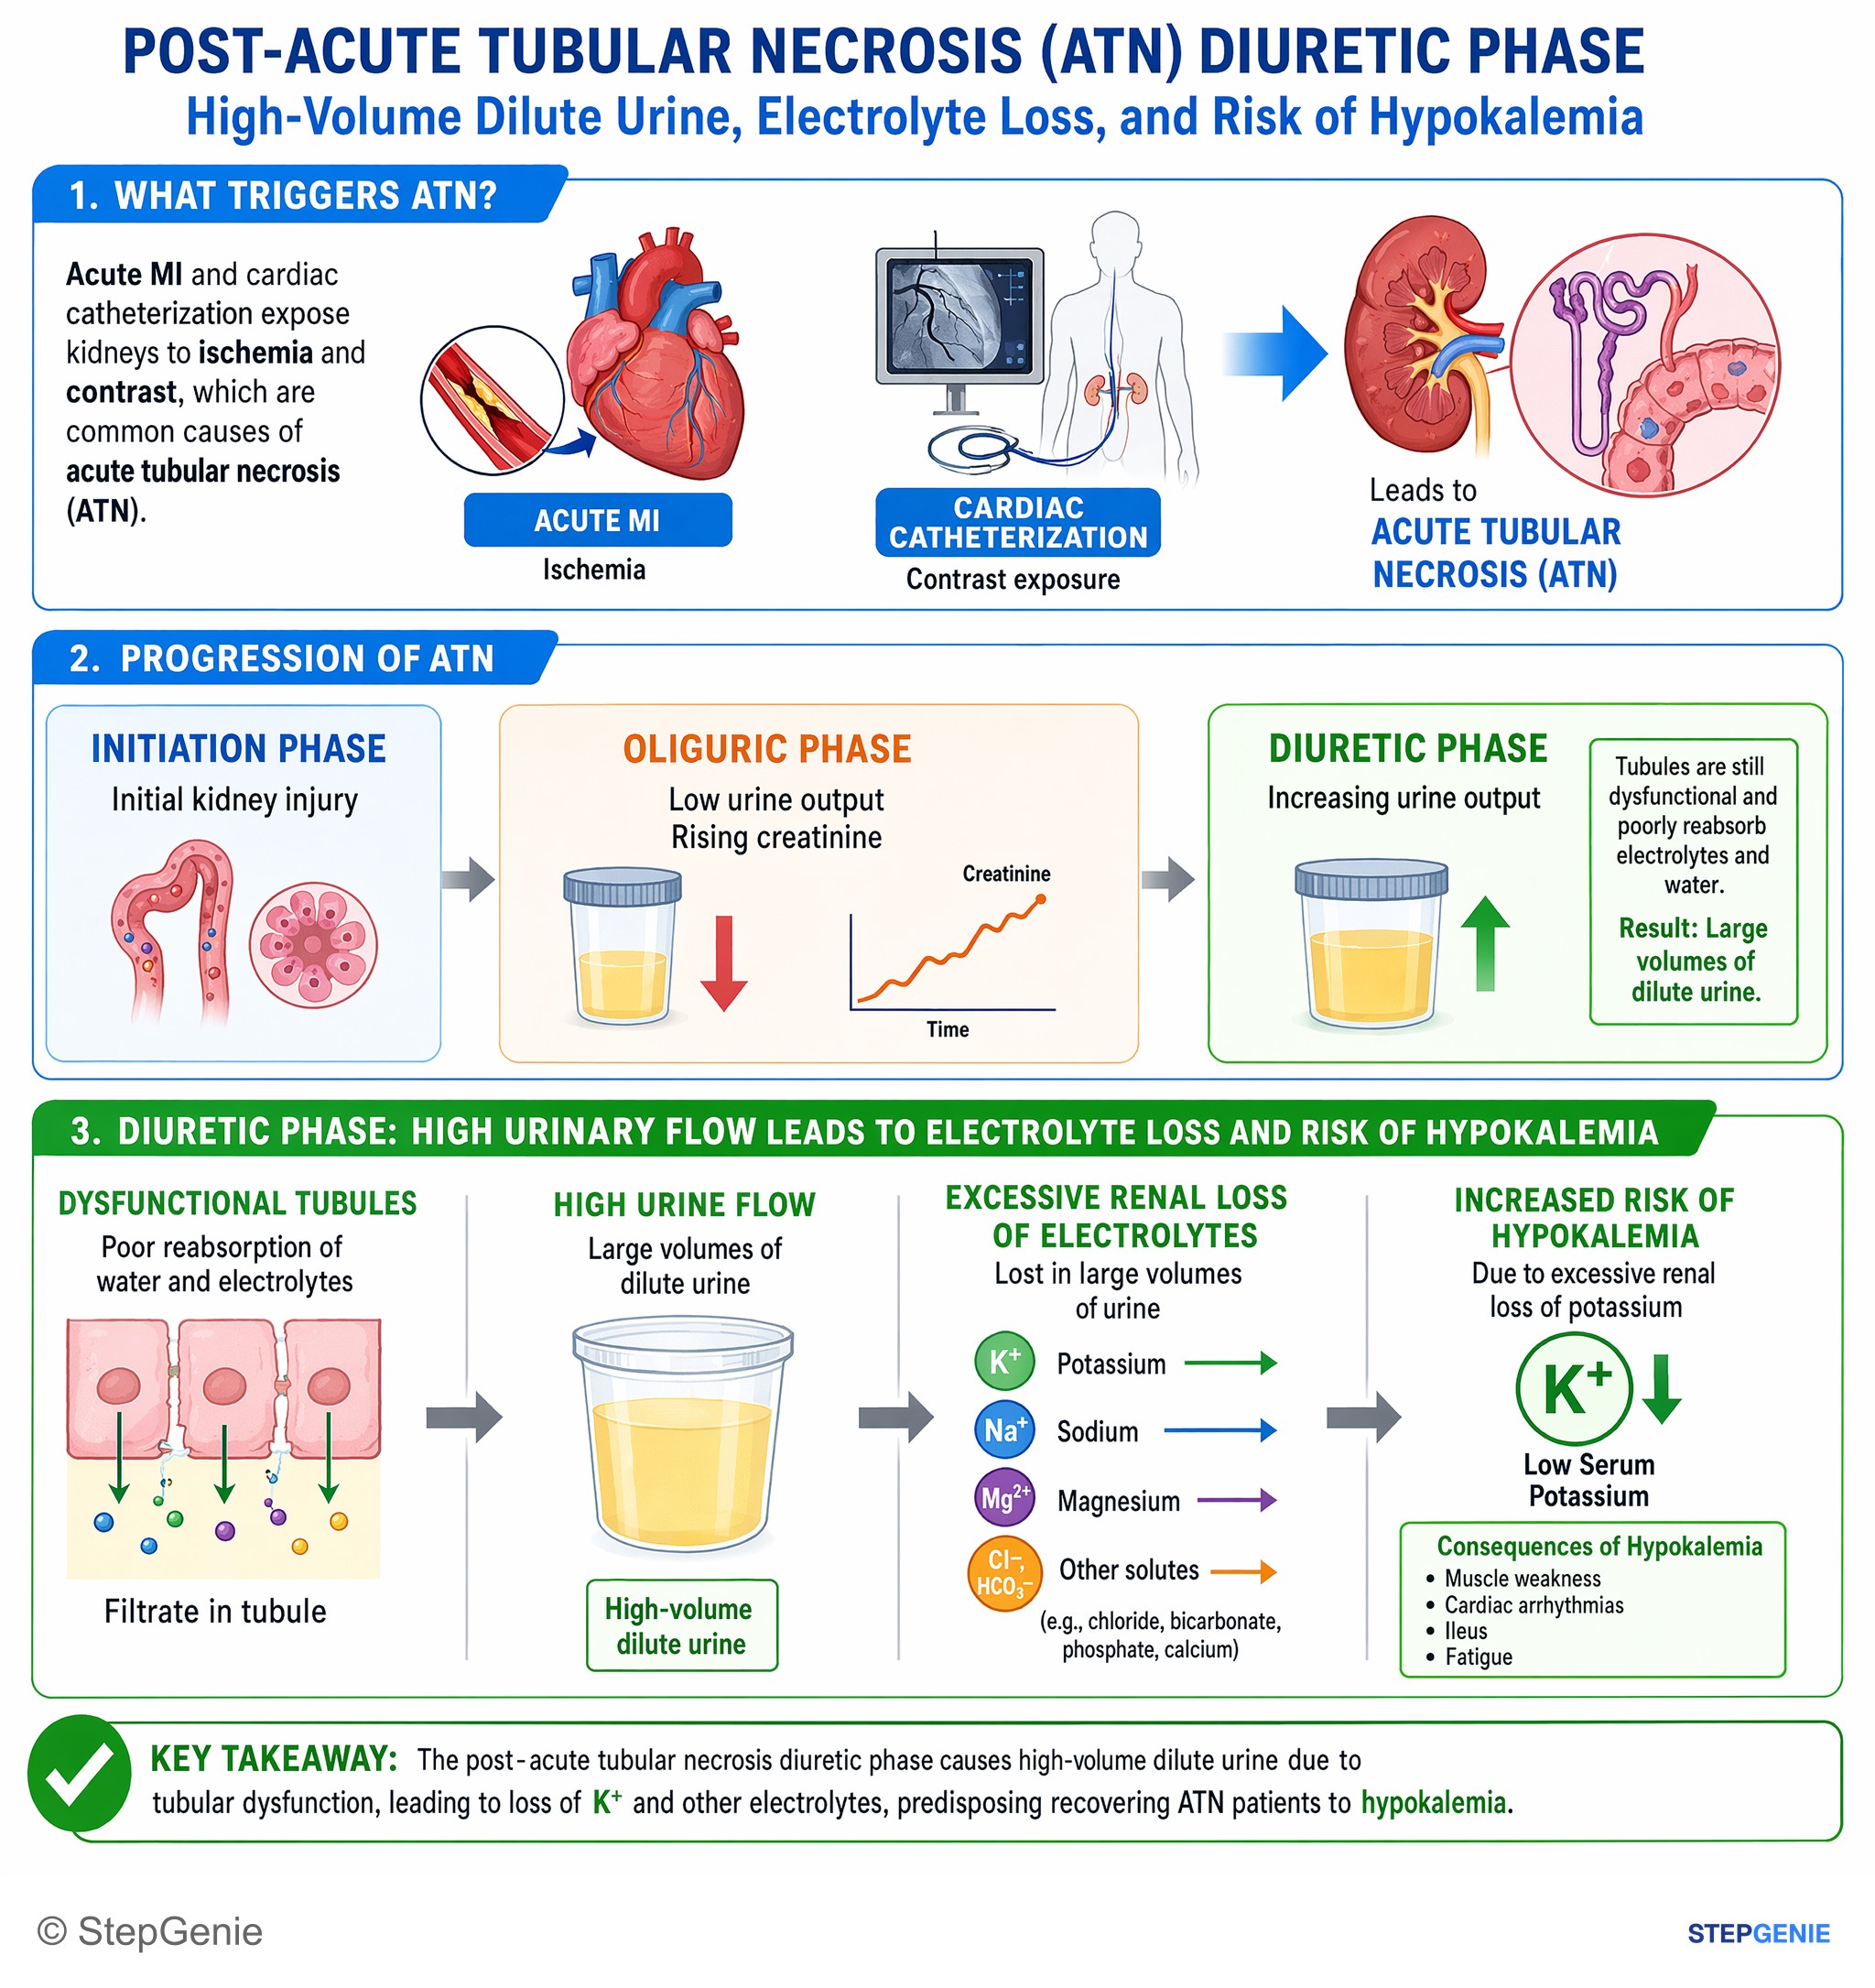
Post-acute tubular necrosis diuretic phase causes high-volume dilute urine with loss of K+ and other electrolytes, predisposing to…
USMLE Step 2Frequently Asked Questions
What are muddy brown granular casts?
Muddy brown granular casts are coarse, brown-pigmented granular casts that form when injured renal tubular epithelial cells slough into the tubule lumen, become trapped in a uromodulin (Tamm-Horsfall protein) matrix and degenerate into granules. They are the classic urine sediment finding of acute tubular necrosis and usually appear with free tubular epithelial cells and epithelial cell casts. They help identify the cause of acute kidney injury but are not part of the KDIGO definition.
How sensitive and specific are muddy brown casts for acute tubular necrosis?
They are highly specific but only moderately sensitive. In a 2022 study of 270 inpatients with acute kidney injury, muddy brown casts were found in 49%; in the 49 biopsied patients they had 100% specificity and positive predictive value but 78% sensitivity. When ATN was suspected, casts or tubular cells had a 100% positive but only 44% negative predictive value, and repeat microscopy found tubular injury in about one in five patients whose first sample was non-diagnostic.
What is tubular backleak in acute tubular necrosis?
Tubular backleak is the leak of glomerular filtrate back across injured tubular epithelium into the interstitium and blood. Ischemia disrupts tight and adherens junctions and makes tubular cells detach from the basement membrane, so filtered markers return to the circulation and measured GFR falls. It is one of three mechanisms of GFR loss in ATN, along with tubular obstruction by casts and afferent arteriolar constriction driven by tubuloglomerular feedback.
How do you tell ATN from prerenal azotemia?
Prerenal azotemia shows a FENa below 1%, urine sodium below 20 mEq/L, urine osmolality above 500 mOsm/kg, a BUN-to-creatinine ratio above 20:1 and a bland or hyaline-cast sediment, and it improves with fluids. ATN shows a FENa above 2%, urine sodium above 40 mEq/L, osmolality usually below 350, a ratio of 10-15:1 and muddy brown casts. On diuretics, a fractional excretion of urea below about 35% favors prerenal azotemia.
Why are the S3 segment and the thick ascending limb most vulnerable in ATN?
Both lie in the outer medulla, where oxygen tension is only about 10-20 mm Hg compared with 50-60 mm Hg in the cortex, and both are highly metabolically active with limited glycolytic capacity, so ATP collapses when oxidative phosphorylation fails. After ischemia, congested outer medullary capillaries keep the region hypoxic while cortical tubules recover. The S3 segment of the proximal tubule is generally viewed as the main site of injury in human ATN.
What are the phases of acute tubular necrosis?
Physiologically, ATN has initiation, extension, maintenance and recovery phases. Clinically, urine output is usually normal in a prodromal phase, falls to about 50-500 mL/day in an oliguric phase with risks of hyperkalemia, acidosis and fluid overload, then returns in a postoliguric recovery phase that can bring polyuria, sodium wasting, hypokalemia and hypomagnesemia while creatinine lags for days. Many patients are never oliguric, as is typical of aminoglycoside injury.