CKD stages are set by eGFR in mL/min/1.73 m²: G1 ≥90, G2 60–89, G3a 45–59, G3b 30–44, G4 15–29, G5 <15 (kidney failure), paired with albuminuria categories A1 <30, A2 30–300, A3 >300 mg/g. Memorize the stage floors as a countdown, 90, 60, 45, 30, 15, and remember that CKD requires an abnormality lasting at least 3 months; because an eGFR of 60 or more is not itself abnormal, G1 and G2 count as CKD only when there is kidney damage such as albuminuria.
CKD stages and GFR
| Stage | eGFR (mL/min/1.73 m²) | KDIGO term | What to expect and do |
|---|---|---|---|
| G1 | ≥90 | Normal or high | CKD only if a damage marker is present (albuminuria, hematuria, abnormal imaging or biopsy); treat the cause and albuminuria |
| G2 | 60–89 | Mildly decreased | Same rule: eGFR 60–89 alone is not CKD |
| G3a | 45–59 | Mildly to moderately decreased | PTH starts rising and calcitriol falls (FGF23 has already risen); check hemoglobin yearly; review renally cleared drug doses |
| G3b | 30–44 | Moderately to severely decreased | Anemia, mineral and bone disorder and acidosis become common; metformin not to be started |
| G4 | 15–29 | Severely decreased | Nephrology referral (eGFR <30); plan dialysis access or transplant once GFR is below 15–20 |
| G5 | <15 | Kidney failure | Dialysis when symptoms or uncontrollable complications appear, often at eGFR 5–10; for transplant candidates, pre-emptive transplant (ideally from a living donor) is preferred, at eGFR <10 or earlier with symptoms |
The GFR countdown mnemonic: 90-60-45-30-15
Each number is the floor of its stage. Start at 90, take one big step down to 60, then count down like a clock in quarter-hours: 45, 30, 15. Anything below 15 is G5. Stage 3 is the only stage split in two, at 45: "3a" is the upper half (45–59) and "3b" the lower half (30–44), and the risk table below shows why the split matters (with A1 albuminuria, which KDIGO calls normal to mildly increased, G3a is moderately increased risk but G3b is already high risk).
A second hook for the albuminuria cut-offs: 30 and 300, a factor of ten apart, the same numbers you will meet as the old microalbuminuria and macroalbuminuria thresholds.
Albuminuria: the "A" in CKD staging
| Category | Urine albumin-to-creatinine ratio | KDIGO term | Older name |
|---|---|---|---|
| A1 | <30 mg/g (<3 mg/mmol) | Normal to mildly increased | — |
| A2 | 30–300 mg/g (3–30 mg/mmol) | Moderately increased | Microalbuminuria |
| A3 | >300 mg/g (>30 mg/mmol) | Severely increased | Macroalbuminuria |
KDIGO stages CKD by Cause, GFR and Albuminuria (CGA), for example "diabetic kidney disease, G3a A2". Risk of progression, cardiovascular events and death rises with both a lower GFR and more albuminuria:
| GFR stage | A1 | A2 | A3 |
|---|---|---|---|
| G1–G2 | Low (not CKD without other markers) | Moderately increased | High |
| G3a | Moderately increased | High | Very high |
| G3b | High | Very high | Very high |
| G4–G5 | Very high | Very high | Very high |
The 3-month rule: how CKD is defined
KDIGO defines CKD as abnormalities of kidney structure or function present for at least 3 months, with implications for health. Either of these qualifies, as long as it persists for 3 months:
- Decreased GFR: eGFR <60 (G3a–G5).
- A marker of kidney damage: albuminuria (ACR ≥30 mg/g), urine sediment abnormalities, persistent hematuria, electrolyte abnormalities from tubular disorders, abnormal histology, structural abnormalities on imaging, or a history of kidney transplantation.
A single low eGFR could be acute kidney injury, so do not assume chronicity from one value. Chronicity can be proved by earlier eGFR or albuminuria results, imaging showing small kidneys with thin cortex, biopsy fibrosis and atrophy, or repeat testing beyond the 3-month mark.
How eGFR is estimated: creatinine, cystatin C and race
- Creatinine first. KDIGO 2024 recommends creatinine-based eGFR (eGFRcr) for initial assessment, using a validated equation applied consistently within a region (in the US, the race-free 2021 CKD-EPI equation).
- Add cystatin C when creatinine misleads. If cystatin C is available, the combined creatinine–cystatin C equation (eGFRcr-cys) should set the GFR category, and it is recommended whenever eGFRcr is less accurate and the result changes management: unusual muscle mass (above-knee amputation, bodybuilding, paralysis after spinal cord injury, muscle-wasting disease), unusual diets (high-protein or creatine supplements, low-protein, vegetarian) or illnesses such as cirrhosis and heart failure.
- No race coefficient. KDIGO states that race should not be used to compute eGFR; the 2021 CKD-EPI creatinine and creatinine–cystatin C equations omit it.
- What counts as a real change. A fall in eGFR of more than 20% on a later test exceeds normal variability and deserves evaluation; after starting a hemodynamically active drug (ACE inhibitor, ARB, SGLT2 inhibitor), only a fall of more than 30% does. A doubling of the ACR is also more than lab noise.
Causes of CKD mnemonic: DIG HOPS
- Diabetes: the most common cause.
- Interstitial disease: chronic tubulointerstitial damage, for example from kidney-toxic drugs.
- Glomerular disease: IgA nephropathy, FSGS, membranous nephropathy, lupus nephritis.
- Hypertension: the second most common cause.
- Obstruction: complicated kidney stones and other urinary tract obstruction.
- Polycystic kidney disease.
- Systemic disease: multiple myeloma, sickle cell disease, lupus, hemolytic uremic syndrome and TTP, infections.
Diabetes and hypertension are the leading causes of adult CKD. For the glomerular causes, see nephrotic vs nephritic syndrome.
CKD complications mnemonic: MAD HUNGER
| Letter | Complication | Mechanism and exam clue |
|---|---|---|
| MA | Metabolic acidosis | Failing kidneys excrete less acid; KDIGO suggests treating (usually with oral alkali) to keep serum bicarbonate from falling below about 18 mmol/L, without overshooting normal (the older KDIGO 2012 guideline suggested treating below 22 mmol/L, a cutoff some question banks still use) |
| D | Dyslipidemia | High cardiovascular risk; statin (or statin plus ezetimibe) for adults 50 or older with eGFR <60 not on dialysis |
| H | Hyperkalemia | Less potassium excretion, oliguria, tubular dysfunction; worsened by ACE inhibitors, ARBs and mineralocorticoid antagonists |
| U | Uremia | Nausea, anorexia, pruritus, pericarditis, asterixis, encephalopathy, platelet dysfunction |
| N | Na⁺ and water retention | Edema, hypertension, heart failure, pulmonary edema |
| G | Growth retardation | Children: poor growth despite nutrition and growth hormone is itself an indication for kidney replacement therapy |
| E | EPO deficiency | Anemia; see anemia of CKD |
| R | Renal osteodystrophy | CKD–mineral and bone disorder (chain below) |
Mineral changes start early in CKD, hemoglobin is checked at least yearly in G3, twice a year in G4 and every 3 months in G5, and complications become more frequent with each lower stage. When they can no longer be controlled, they become the dialysis indications (AEIOU).
The CKD-MBD chain
- FGF23 rises early, even before PTH. It increases urinary phosphate excretion but suppresses 1α-hydroxylase.
- Calcitriol falls once eGFR drops below about 60, so gut calcium absorption drops and calcium tends to fall; serum calcium and phosphate often stay normal until the eGFR is near 20.
- Low calcitriol, low calcium and later hyperphosphatemia drive secondary hyperparathyroidism, causing renal osteodystrophy, while vascular calcification begins early and increases as GFR falls.
- After years, parathyroid tissue can secrete PTH autonomously: tertiary hyperparathyroidism.
For lab patterns and treatment, see renal osteodystrophy.
Management by stage: what to start and when
The KDIGO 2024 guideline layers kidney-protective drugs on top of blood pressure and cause-specific treatment. Know the eGFR gate for each.
| Therapy | Who gets it | eGFR rule to remember |
|---|---|---|
| ACE inhibitor or ARB | CKD with albuminuria (A2–A3), hypertension or HFrEF | Highest tolerated dose; continue even when eGFR falls below 30 |
| SGLT2 inhibitor | Type 2 diabetes with CKD; any adult with ACR ≥200 mg/g or heart failure; suggested at eGFR 20–45 even with lower ACR | Start at eGFR ≥20; once started, it can be continued below 20 until dialysis |
| Nonsteroidal MRA (finerenone) | Type 2 diabetes, albuminuria above 30 mg/g despite maximal RAS blockade, normal potassium | eGFR above 25 |
| GLP-1 receptor agonist | Type 2 diabetes with CKD not at glucose goal on metformin and an SGLT2 inhibitor | Semaglutide (Ozempic) carries an FDA indication to reduce the risk of sustained eGFR decline, end-stage kidney disease and cardiovascular death in adults with type 2 diabetes and CKD |
| Statin or statin/ezetimibe | Age 50 or older with eGFR <60 (not on dialysis or transplanted) | Statin alone for age 50 or older at eGFR ≥60 |
| Blood pressure | Adults with CKD and high blood pressure | Target systolic BP <120 mm Hg when tolerated (standardized office reading) |
Referral and planning. KDIGO lists eGFR <30, a 5-year kidney failure risk of 3–5% or more on a validated equation (such as the Kidney Failure Risk Equation, KFRE), a sustained eGFR fall of more than 20%, an ACR consistently above 700 mg/g (or 300 mg/g or more with hematuria), refractory hypertension and uncontrolled complications as reasons to refer. Dialysis access or pre-emptive transplant planning starts when the GFR is below 15–20 or the 2-year risk of kidney replacement therapy exceeds 40%.
CKD vs AKI on a question stem
| Clue | CKD | AKI |
|---|---|---|
| Timeline | ≥3 months | Creatinine up ≥0.3 mg/dL in 48 h, or ≥1.5× baseline within 7 days, or urine <0.5 mL/kg/h for 6 h |
| Kidney size on ultrasound | Often small and echogenic with a thin cortex; normal-sized or large kidneys do not exclude CKD (they are enlarged in polycystic kidney disease) | Small, scarred kidneys argue against a purely acute process |
| Anemia and mineral–bone changes | Common from G3 onward | Their presence suggests a chronic component |
| Prior results | Old eGFR or ACR values already abnormal | Recently normal baseline |
Exam traps and practical tie-ins
- One eGFR is not CKD. Confirm chronicity with repeat testing over 3 months or with earlier results.
- eGFR 60–89 with no markers is not CKD G2, at any age.
- Creatinine-based eGFR misleads when muscle mass is unusual (amputation, bodybuilding, muscle wasting); add cystatin C to confirm.
- A creatinine bump after starting an ACE inhibitor or ARB is expected. KDIGO says to continue unless creatinine rises by more than 30% within 4 weeks. The small initial eGFR dip with an SGLT2 inhibitor is also not a reason to stop.
- Metformin: contraindicated below eGFR 30, not to be started at 30–45, and reassessed if eGFR falls below 45 (FDA labeling).
- Hyperkalemia on a RAS blocker is often managed by lowering potassium (diet review, diuretics, binders) rather than stopping the drug.
Worked examples
Vignette 1. A 58-year-old woman with type 2 diabetes has eGFR values of 38, 41 and 36 mL/min/1.73 m² over 8 months, and her urine albumin-to-creatinine ratio is 420 mg/g on two occasions. How is her CKD staged, and which two drug classes slow its progression first?
Answer: G3b A3 (very high risk). Start an ACE inhibitor or ARB at the maximally tolerated dose plus an SGLT2 inhibitor.
Reasoning: eGFR 30–44 is G3b and ACR >300 mg/g is A3, both persisting beyond 3 months; KDIGO recommends RAS blockade for CKD with albuminuria and an SGLT2 inhibitor when eGFR is at least 20. If albuminuria persists with normal potassium, finerenone is the next add-on.
Vignette 2. A 70-year-old man has an eGFR of 72 mL/min/1.73 m² on routine testing. His urine ACR is 12 mg/g, urinalysis is bland and a kidney ultrasound is normal. Does he have CKD?
Answer: No. An eGFR of 60–89 without albuminuria or another marker of kidney damage does not meet the definition of CKD.
Reasoning: G1 and G2 count as CKD only with a damage marker lasting 3 months; KDIGO keeps the same definition for younger and older adults.
Vignette 3. A 66-year-old man with type 2 diabetes and CKD G3b takes metformin, lisinopril at the maximum dose and empagliflozin, started 3 weeks ago. His eGFR has gone from 34 to 31 mL/min/1.73 m², his ACR is still 450 mg/g and potassium is 4.6 mEq/L. What is the best next step?
Answer: Continue the SGLT2 inhibitor and the ACE inhibitor, and add finerenone; review the metformin dose.
Reasoning: A fall of about 9% after starting a hemodynamically active drug is well inside the expected dip (only a fall above 30% needs evaluation). Persistent albuminuria above 30 mg/g on maximal RAS blockade with normal potassium and an eGFR above 25 is the KDIGO setting for a nonsteroidal MRA. Metformin needs a benefit–risk review once eGFR is below 45 and must stop below 30.
Key takeaways
- CKD stages by GFR: G1 ≥90, G2 60–89, G3a 45–59, G3b 30–44, G4 15–29, G5 <15; the countdown is 90-60-45-30-15.
- Albuminuria: A1 <30, A2 30–300, A3 >300 mg/g; stage every patient by cause, G and A.
- CKD needs ≥3 months of reduced GFR or kidney damage; G1–G2 need a damage marker.
- eGFR: creatinine first, add cystatin C when muscle mass or diet distort creatinine, never use race.
- Causes (DIG HOPS): diabetes first, hypertension second. Complications (MAD HUNGER) become more frequent as the stage advances.
- Kidney protection: RAS blockade, SGLT2 inhibitor from eGFR ≥20, finerenone or a GLP-1 receptor agonist in type 2 diabetes, statins, systolic BP <120 if tolerated.
- Dialysis is triggered by symptoms or uncontrollable complications (often at eGFR 5–10), not by the eGFR number itself.
More kidney reviews are collected on the nephrology topic hub.
Sources
- KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease
- KDIGO 2020 Clinical Practice Guideline on the Evaluation and Management of Candidates for Kidney Transplantation
- KDIGO 2026 Clinical Practice Guideline for the Management of Anemia in Chronic Kidney Disease
- Chronic Kidney Disease — StatPearls, NCBI Bookshelf
- Chronic Kidney Disease-Mineral Bone Disorder (CKD-MBD) — StatPearls, NCBI Bookshelf
- Causes of Chronic Kidney Disease — NIDDK
- Acute Kidney Injury — StatPearls, NCBI Bookshelf
- Ozempic (semaglutide) injection prescribing information — DailyMed, US National Library of Medicine
- Metformin hydrochloride tablets prescribing information — DailyMed, US National Library of Medicine
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
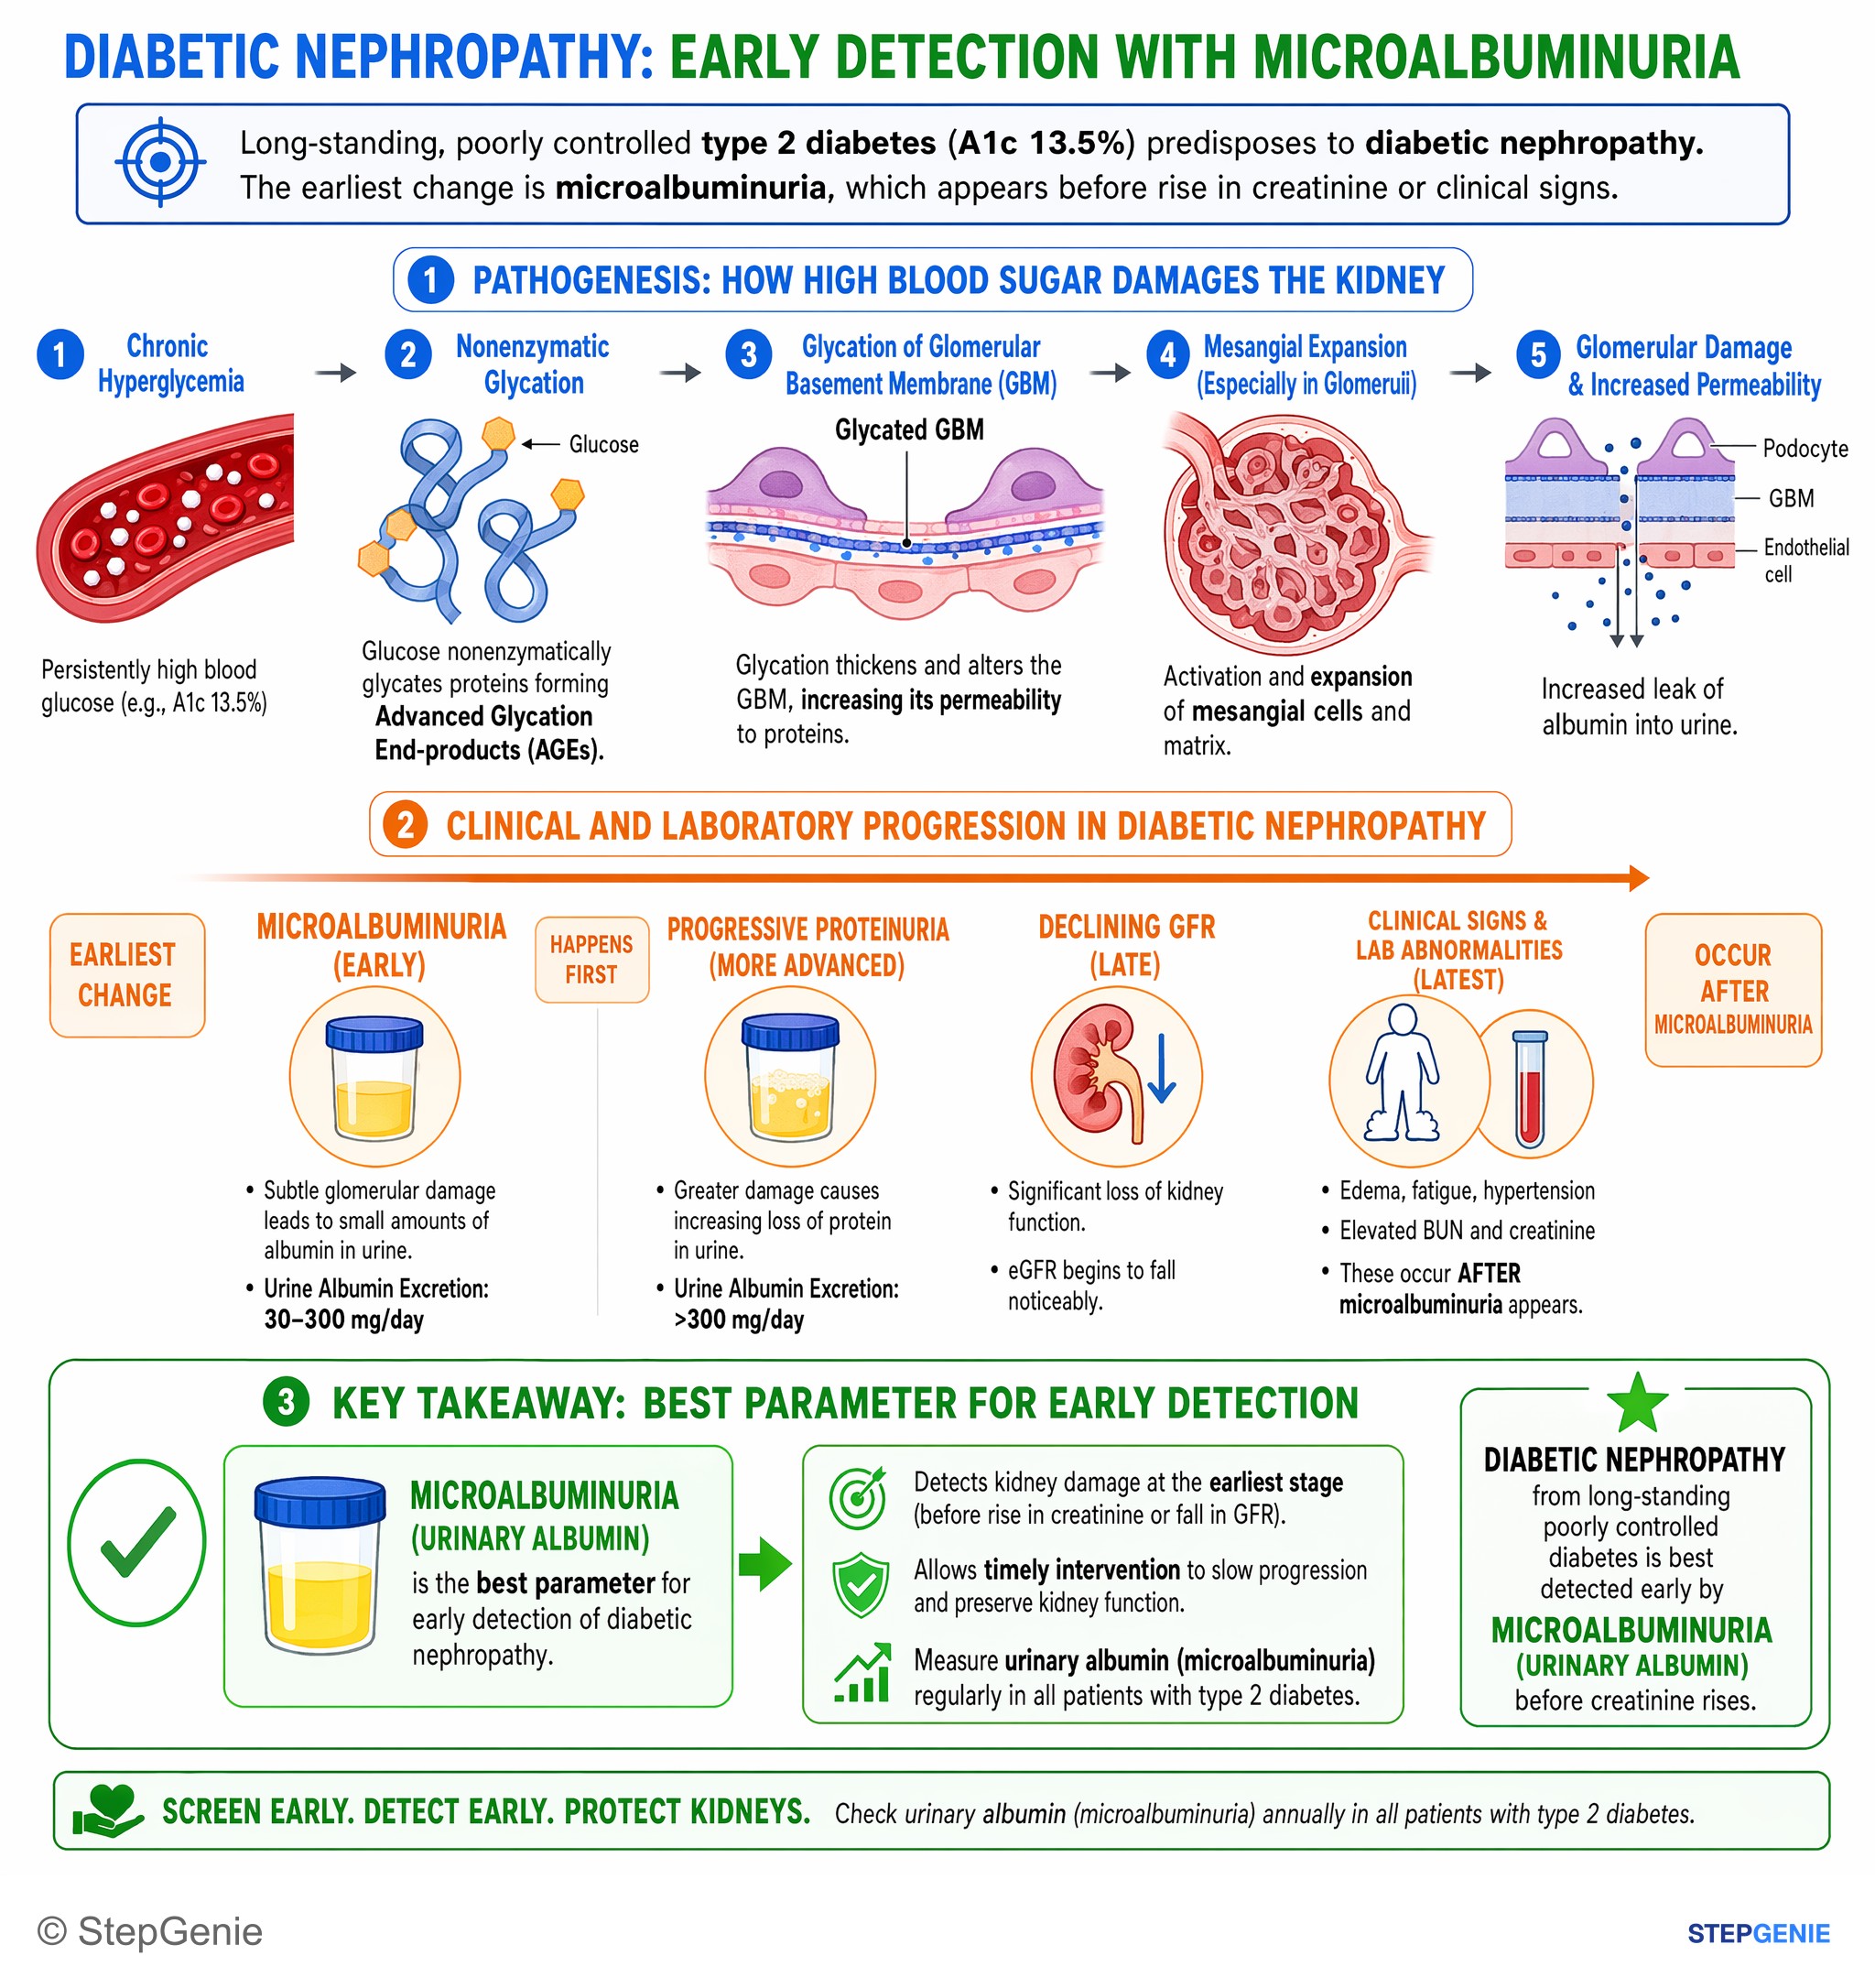
Diabetic nephropathy from long-standing poorly controlled diabetes is best detected early by microalbuminuria (urinary albumin) before…
USMLE Step 1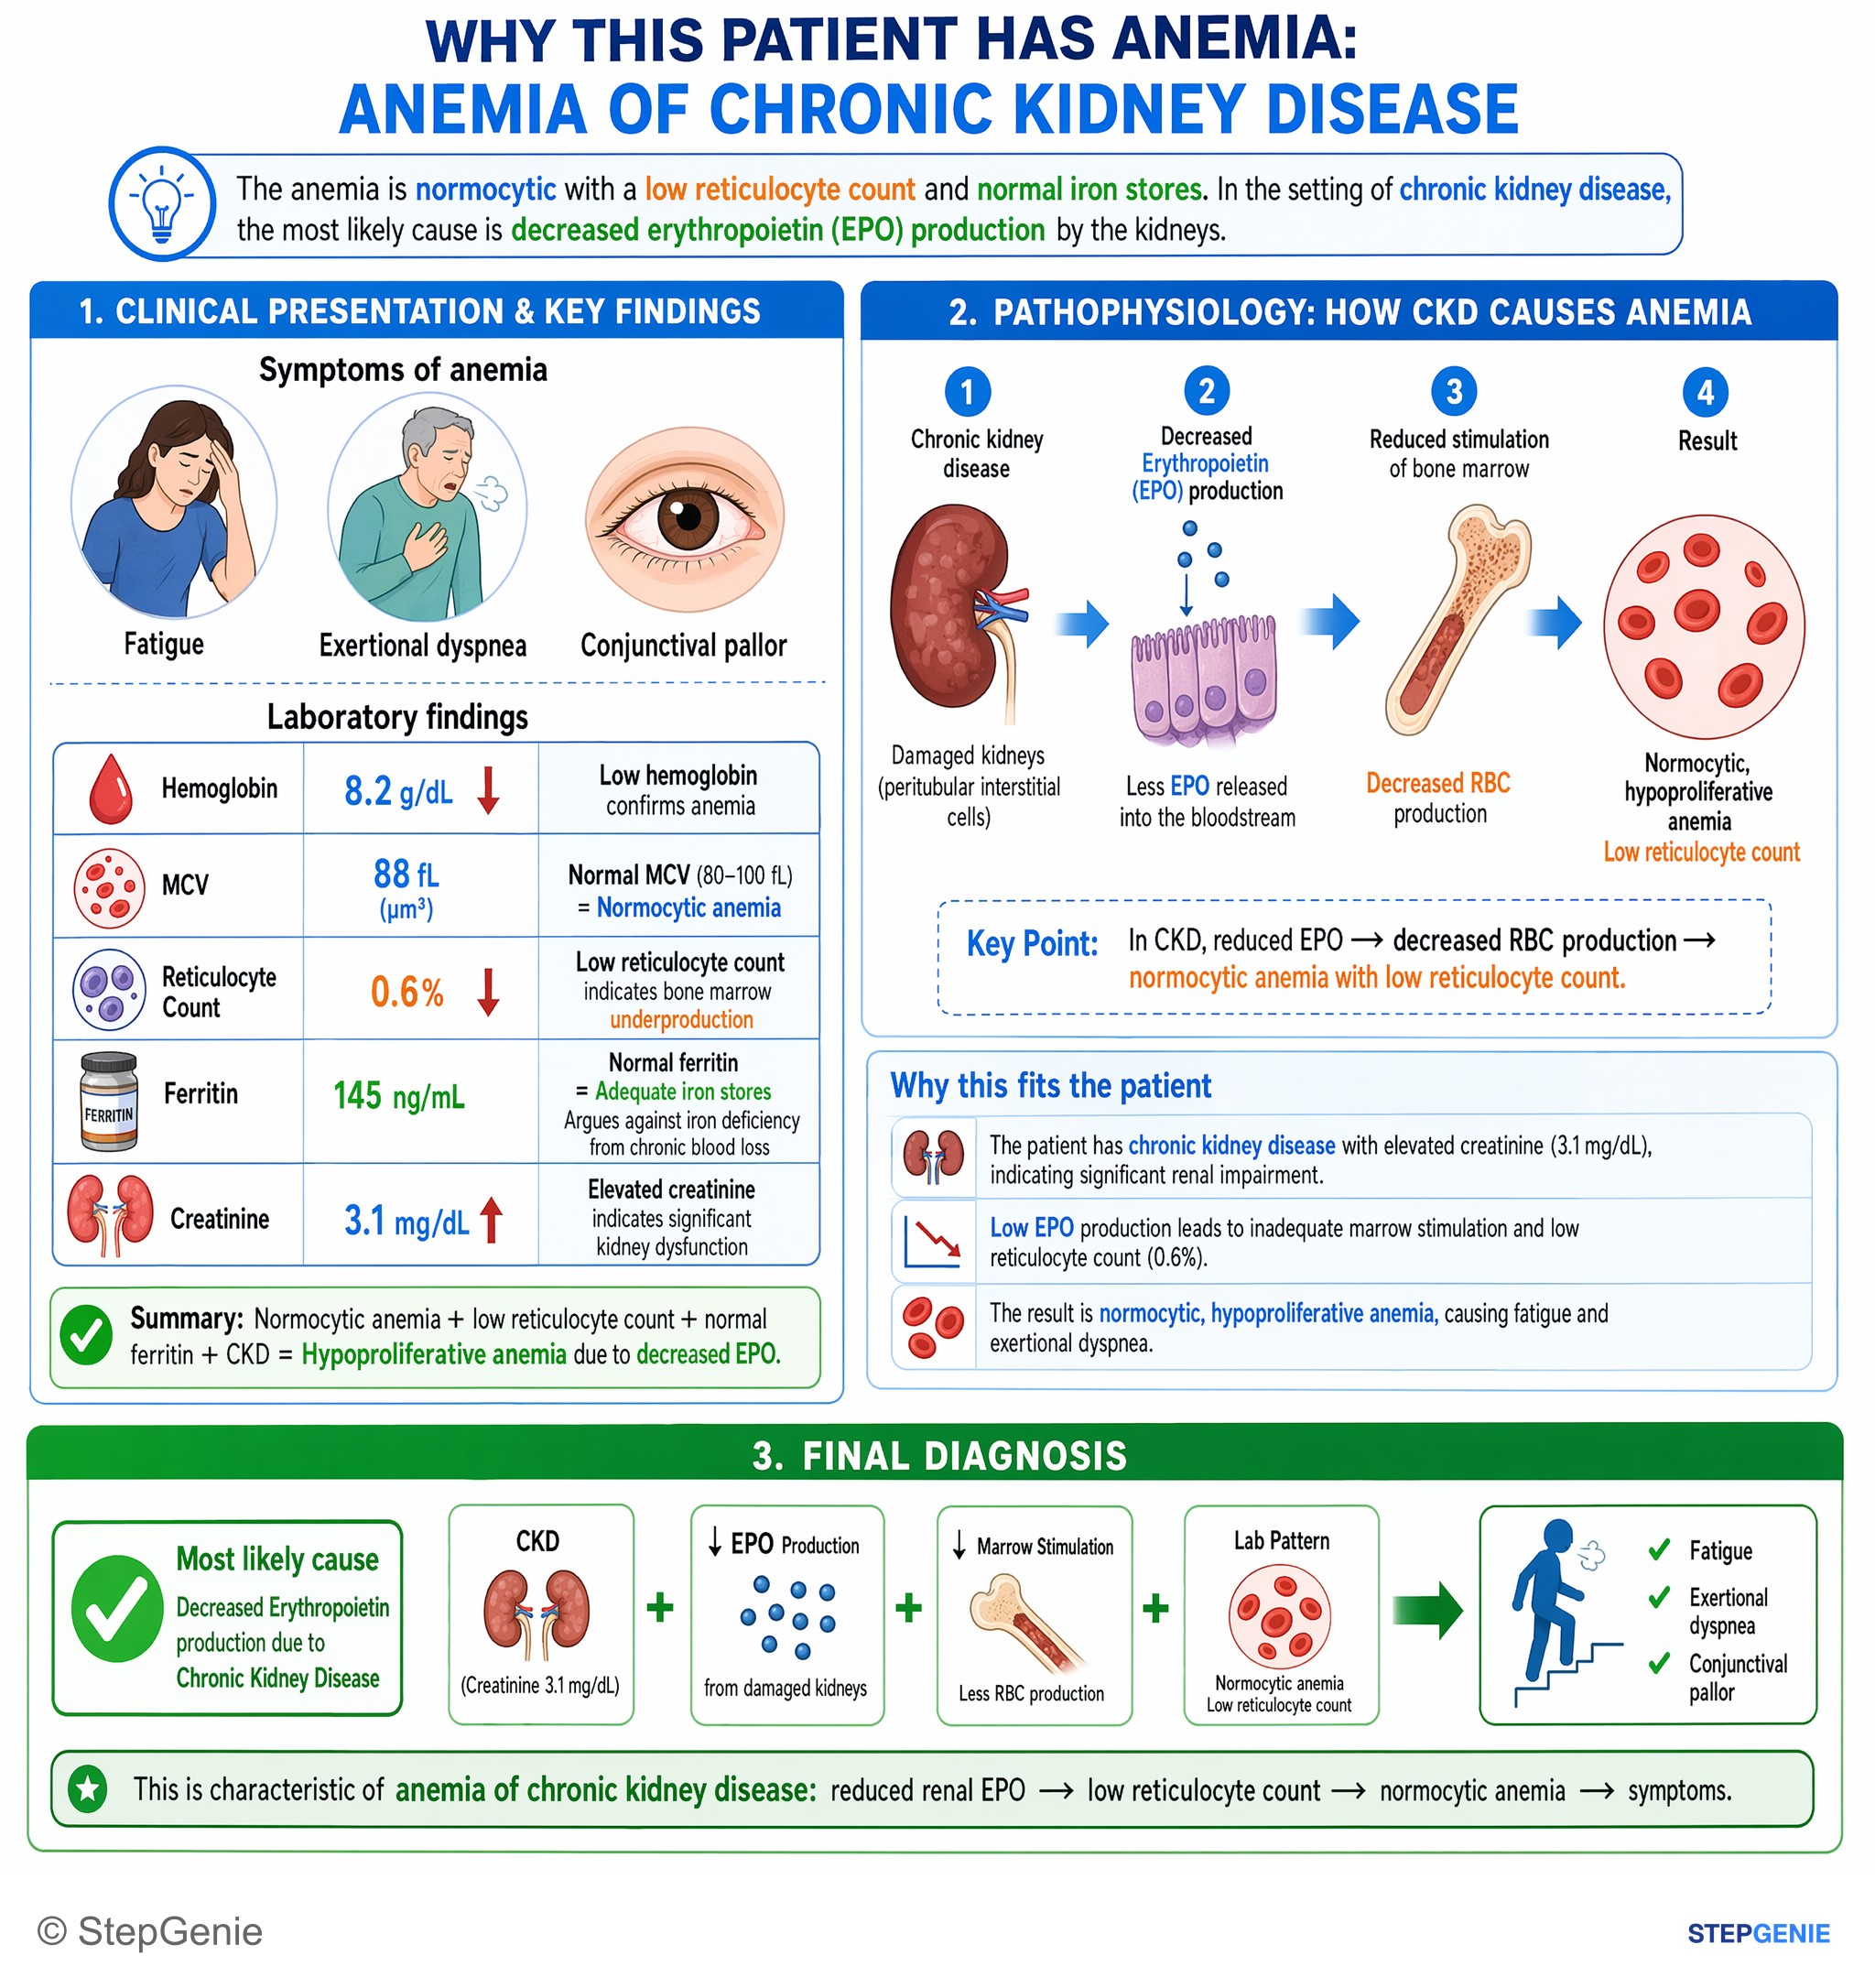
Anemia of chronic kidney disease: reduced renal EPO → low reticulocyte count, normocytic anemia causing exertional dyspnea and fatigue.
USMLE Step 1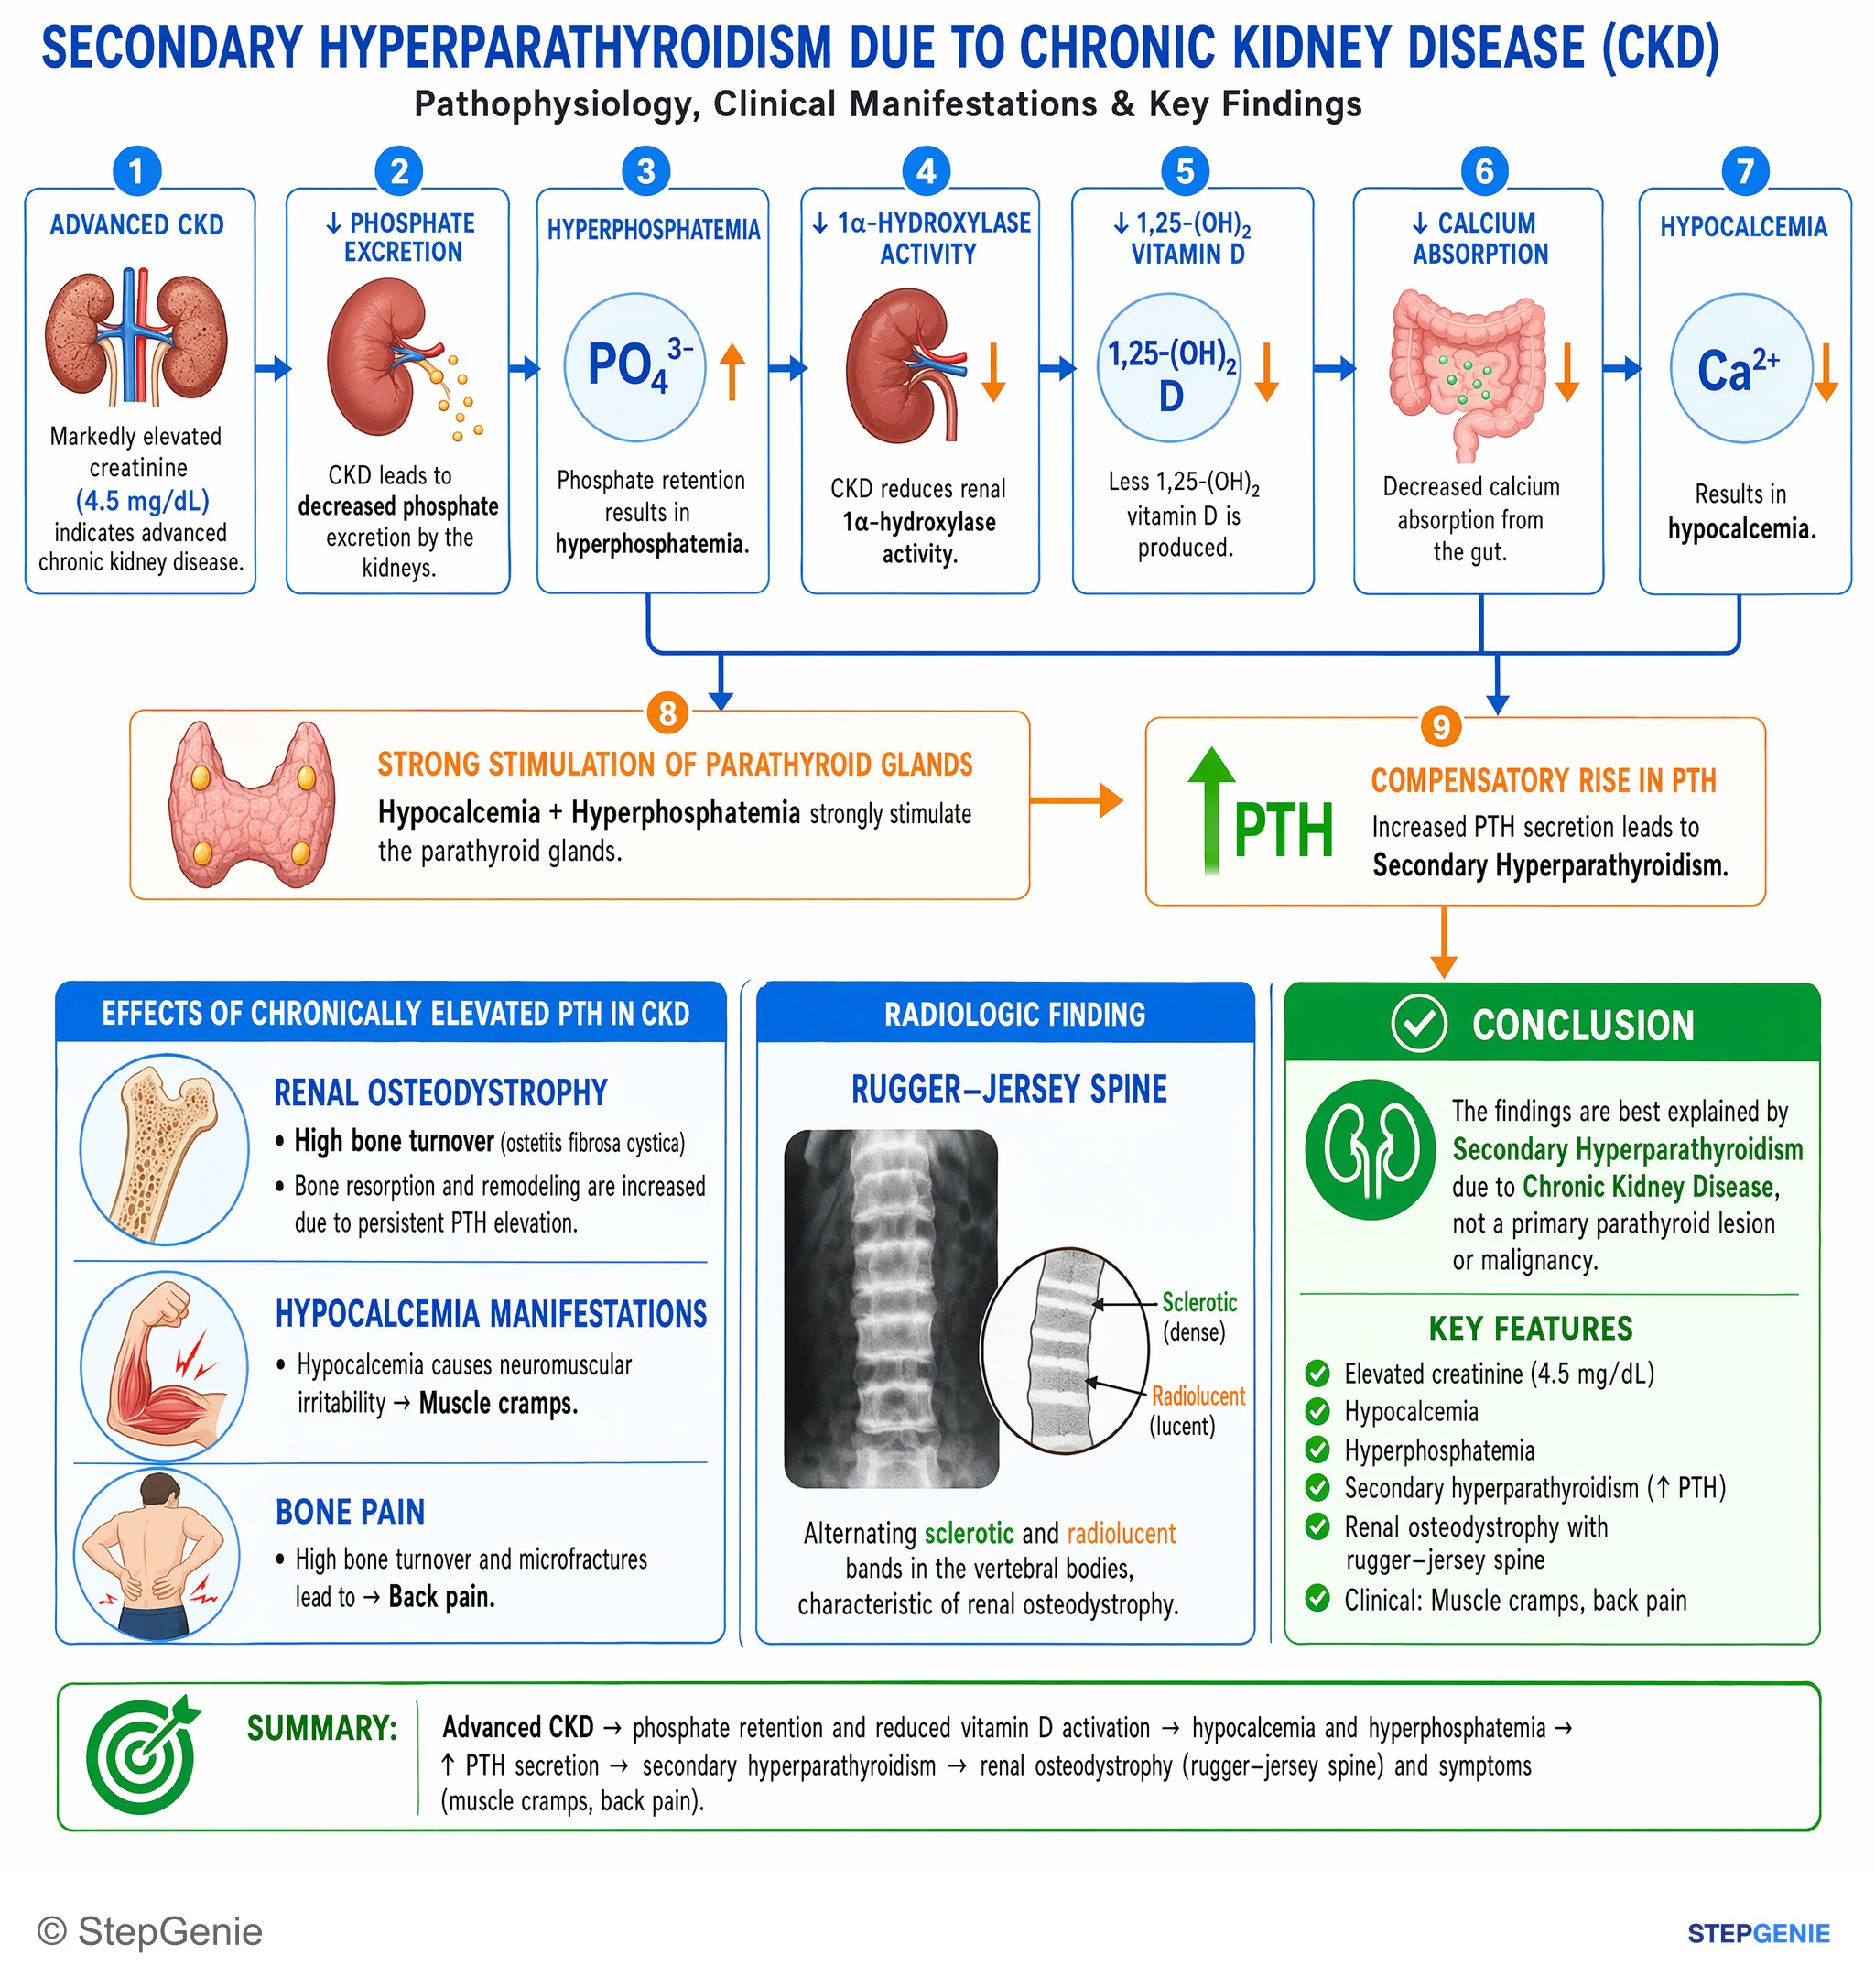
Secondary hyperparathyroidism due to chronic kidney disease → hypocalcemia, hyperphosphatemia, renal osteodystrophy with alternating…
USMLE Step 1Frequently Asked Questions
What are the stages of CKD by GFR?
KDIGO uses six GFR categories: G1 is 90 or higher, G2 is 60 to 89, G3a is 45 to 59, G3b is 30 to 44, G4 is 15 to 29, and G5 (kidney failure) is below 15 mL/min/1.73 m². G1 and G2 count as CKD only when a marker of kidney damage such as albuminuria is also present. Each stage is reported together with the cause and the albuminuria category (A1 to A3).
What is the difference between CKD stage 3a and 3b?
Stage 3a is an eGFR of 45 to 59 mL/min/1.73 m², and stage 3b is 30 to 44. The two halves carry different risks of progression, cardiovascular events and death: with A1 albuminuria (normal to mildly increased), G3a is moderately increased risk while G3b is already high risk, and G3b with albuminuria of 30 mg/g or more is very high risk. Complications such as mineral and bone disorder also become more frequent as the eGFR falls.
Is an eGFR of 60 to 89 chronic kidney disease?
Not by itself. An eGFR of 60 to 89 counts as CKD stage G2 only if there is also evidence of kidney damage, such as albuminuria of at least 30 mg/g, urine sediment abnormalities, persistent hematuria, structural abnormalities on imaging or abnormal biopsy findings, lasting at least 3 months. KDIGO applies the same rule to younger and older adults, so a mildly reduced eGFR without a damage marker is not labeled CKD.
What is the mnemonic for CKD complications?
MAD HUNGER: metabolic acidosis, dyslipidemia, hyperkalemia, uremia, sodium and water retention, growth retardation in children, erythropoietin deficiency and renal osteodystrophy. The complications come from lost excretion (acid, potassium, salt, water and uremic toxins) and lost kidney hormones (erythropoietin and calcitriol). Mineral changes begin early, and the other complications become more frequent as the eGFR falls through stages G3 to G5.
Which medications slow CKD progression?
An ACE inhibitor or ARB at the highest tolerated dose is the base for CKD with albuminuria, and KDIGO 2024 adds an SGLT2 inhibitor at an eGFR of at least 20 mL/min/1.73 m² for adults with CKD who have type 2 diabetes, an ACR of 200 mg/g or more, or heart failure, and suggests one at eGFR 20 to 45 even with a lower ACR. In type 2 diabetes, finerenone is suggested for persistent albuminuria with normal potassium and an eGFR above 25, and a GLP-1 receptor agonist such as semaglutide adds kidney and cardiovascular protection. Blood pressure control and statins complete the plan.
What are the most common causes of CKD?
Diabetes is the leading cause of chronic kidney disease in adults, and high blood pressure is second. Other causes include glomerular diseases such as IgA nephropathy and lupus nephritis, polycystic kidney disease, chronic tubulointerstitial disease, urinary obstruction, and systemic conditions such as multiple myeloma and sickle cell disease. The cause is part of every KDIGO stage label, alongside the GFR and albuminuria categories.