Renal blood flow (RBF) and glomerular filtration rate (GFR) stay relatively constant while renal perfusion pressure, which exams equate with the mean arterial pressure (MAP), varies between about 80 and 180 mm Hg. Two intrinsic mechanisms do this, mainly by adjusting afferent arteriolar resistance: the myogenic response (a stretched afferent arteriole constricts within seconds) and tubuloglomerular feedback (TGF: the macula densa senses NaCl through NKCC2 and triggers adenosine-mediated afferent constriction). Below the range, flow and filtration follow pressure; chronic hypertension shifts the curve to the right, and diabetes and chronic kidney disease (CKD) blunt it. NSAIDs (which remove prostaglandin dilation of the afferent arteriole) and ACE inhibitors or ARBs (which remove angiotensin II constriction of the efferent arteriole) lower GFR most when filtration depends on those hormones.
Renal autoregulation at a glance
| Feature | High-yield fact |
|---|---|
| What stays steady | RBF and GFR: relatively constant, not perfectly fixed |
| Range | Renal perfusion pressure (≈ MAP) of about 80–180 mm Hg |
| Main effector | Afferent arteriolar resistance |
| Fast mechanism | Myogenic response: stretch → afferent constriction within seconds |
| Slower mechanism | TGF: ↑ NaCl at the macula densa → adenosine (A1) → afferent constriction; joins in after about 5–10 seconds |
| Below the range | RBF and GFR fall with pressure: prerenal AKI, then ischemic ATN if prolonged |
| Above the range | Pressure reaches the glomerular capillaries: hypertensive injury |
| Shifted or blunted by | Chronic hypertension (rightward shift), sympathetic activation, diabetes, CKD |
Normal numbers: RBF, RPF, GFR and filtration fraction
The kidneys receive roughly 20–25% of cardiac output, about 1 L of blood per minute.
| Quantity | Typical adult value | How it is derived |
|---|---|---|
| Renal blood flow (RBF) | About 1,000–1,100 mL/min | About 20% of a 5 L/min cardiac output |
| Renal plasma flow (RPF) | About 550–650 mL/min | RBF × (1 − hematocrit); estimated by PAH clearance |
| GFR | About 125 mL/min in men (≈ 180 L/day), about 105 in women | Inulin clearance; usually estimated from creatinine |
| Filtration fraction (FF) | About 20% | GFR ÷ RPF |
| Net filtration pressure | About 10 mm Hg | 55 (glomerular capillary) − [15 (Bowman's space) + 30 (oncotic)] |
Worked numbers. 5,000 mL/min × 0.21 = 1,050 mL/min of RBF. With a hematocrit of 45%, RPF = 1,050 × 0.55 ≈ 578 mL/min. If 19% of that plasma is filtered, GFR ≈ 110 mL/min. Because only about 10 mm Hg of net pressure drives filtration, small changes in glomerular capillary pressure change GFR a lot. For PAH and inulin clearance, see renal clearance equations.
What the 80–180 mm Hg range means, and its limits
| Renal perfusion pressure (≈ MAP) | RBF and GFR | Afferent arteriole | Where it shows up |
|---|---|---|---|
| Below about 80 mm Hg | Fall as pressure falls | Maximally dilated; efferent angiotensin II props up GFR for a while | Shock, sepsis, hemorrhage, overdiuresis: prerenal AKI |
| About 80–180 mm Hg | Nearly constant (the plateau) | Constricts as pressure rises, dilates as it falls | Normal physiology |
| Above about 180 mm Hg | Rise with pressure | Cannot constrict further | Transmitted pressure injures the glomerular capillaries |
- It is a mean pressure, not a systolic one. MAP ≈ diastolic + ⅓(systolic − diastolic): at 100/60 mm Hg, MAP ≈ 73 mm Hg, already below the lower limit. Strictly, flow depends on the arterial-minus-venous pressure difference across the kidney; exams use MAP as the stand-in.
- "Constant" means relatively constant. On the plateau, RBF and GFR still change a little.
- The limits move. 80–180 mm Hg is the classic figure from animal experiments, mostly in anesthetized dogs and rats: the lower limit was about 65–80 mm Hg in dogs and 10–20 mm Hg higher in rats. In people the pressure–flow relationship is hard to measure and varies between patients. Increased renal sympathetic activity shifted the lower limit right by more than 25 mm Hg in dogs, and chronic hypertension shifts the whole curve right.
- Shock targets sit below it. Initial shock management aims for a MAP of about 65 mm Hg. In SEPSISPAM (776 patients with septic shock), a MAP target of 80–85 mm Hg instead of 65–70 mm Hg did not change mortality at 28 or 90 days and caused more atrial fibrillation. In the predefined subgroup with chronic hypertension, fewer patients in the higher-target arm had their creatinine double (38.9% vs 52.0%) or needed renal replacement therapy (31.7% vs 42.2%).
Mechanism 1: the myogenic response
The afferent arteriole's smooth muscle responds directly to stretch. When perfusion pressure rises, the stretched cells depolarize, voltage-gated (L-type) calcium channels open, calcium enters and the arteriole constricts, so the extra pressure does not reach the glomerulus. When pressure falls, the muscle relaxes. Calcium channel blockers blunt this response: verapamil, an L-type blocker, blocks it, and nifedipine abolished autoregulation in rats with reduced renal mass.
This is the fast arm, acting within seconds, quick enough to stop surges of systemic pressure from damaging the glomerular capillaries, which is the main physiological job of renal autoregulation.
Mechanism 2: tubuloglomerular feedback
The macula densa, a plaque of cells at the end of the thick ascending limb pressed against its own nephron's afferent arteriole, measures tubular NaCl through the luminal Na-K-2Cl cotransporter (NKCC2). It runs a negative feedback loop that stabilizes single-nephron GFR and distal salt delivery:
- GFR rises, so more NaCl arrives. The cells release ATP and adenosine; adenosine acts on A1 receptors and constricts the afferent arteriole, and renin release falls. GFR drifts back down.
- GFR falls, so less NaCl arrives. The afferent arteriole dilates and renin release rises; angiotensin II then constricts the efferent arteriole, propping up glomerular pressure.
Tested pearls:
- Adenosine constricts the afferent arteriole, the opposite of its dilator role in coronary autoregulation.
- Loop diuretics block the sensor. Furosemide inhibits NKCC2, including in the macula densa, so the cells cannot sense the extra NaCl reaching them: TGF is blunted, and because the macula densa reads "low NaCl", renin release rises.
- Diabetic hyperfiltration is TGF turned down. Hyperglycemia increases proximal sodium (with glucose) reabsorption, so less NaCl reaches the macula densa, and TGF is reset upward in early diabetes: the afferent arteriole dilates. SGLT2 inhibitors reverse this.
For the cell-by-cell anatomy, see the macula densa vs JG cells table.
| Feature | Myogenic response | Tubuloglomerular feedback |
|---|---|---|
| Sensor | Stretch of afferent arteriolar smooth muscle | Tubular NaCl at the macula densa (NKCC2) |
| Signal | Depolarization, Ca²⁺ entry through voltage-gated channels | ATP and adenosine → A1 receptors |
| Effector | Afferent arteriole | Afferent arteriole (plus renin → angiotensin II when NaCl is low) |
| Speed | Within seconds | After about 5–10 seconds |
Backup systems: angiotensin II, prostaglandins and sympathetic nerves
Renin is released from the juxtaglomerular apparatus in response to lower afferent arteriolar wall tension, less NaCl at the macula densa and sympathetic β-receptor stimulation; angiotensin II feeds back to inhibit it.
- Angiotensin II's efferent action props up GFR. It constricts both arterioles, but when perfusion falls its efferent constriction holds glomerular pressure up, so GFR falls less than plasma flow and FF rises; exams call this preferential efferent constriction. ACE inhibitors and ARBs remove that efferent tone. Angiotensin II plays only a minor part in autoregulation in healthy animals but may be essential for resetting the lower limit during hypotension.
- Vasodilator prostaglandins (prostacyclin, PGE2) dilate the afferent arteriole. With normal volume and renal blood flow they matter little; in volume depletion, heart failure, cirrhosis or CKD, renal function can depend heavily on them.
- Sympathetic nerves constrict the afferent arteriole and stimulate renin release. Under stress or blood loss this diverts blood from the kidneys, lowering RBF and GFR.
Afferent vs efferent arterioles: effects on RPF, GFR and FF
The rule: a change upstream of the glomerulus moves RPF and GFR in the same direction, a change downstream moves them in opposite directions, and FF = GFR ÷ RPF shows which side changed.
| Change | Example or mechanism | RPF | GFR | FF |
|---|---|---|---|---|
| Afferent constriction | NSAIDs (lost prostaglandin dilation), calcineurin inhibitors, sympathetic stimulation, adenosine in TGF | ↓ | ↓ | ≈ |
| Afferent dilation | Prostaglandins; early diabetes (TGF turned down) | ↑ | ↑ | ≈ |
| Efferent constriction | Angiotensin II (volume depletion, heart failure, renal artery stenosis) | ↓ | ↑ or maintained | ↑ |
| Efferent dilation | ACE inhibitors, ARBs | ≈ or ↑ | ↓ | ↓ |
| ↑ Plasma protein | Higher glomerular oncotic pressure opposes filtration | ≈ | ↓ | ↓ |
| Ureteral obstruction | Pressure backs up into Bowman's space | ≈ | ↓ | ↓ |
| Volume depletion | Sympathetic and angiotensin II activation | ↓ | ↓ (less than RPF) | ↑ |
Drugs that change glomerular hemodynamics
| Drug | Where it acts | Effect on GFR | Watch for |
|---|---|---|---|
| NSAIDs | Afferent: block dilator prostaglandins | ↓ | Volume depletion, heart failure, cirrhosis, CKD; combination with an ACE inhibitor/ARB plus a diuretic. Also a cause of interstitial nephritis |
| ACE inhibitors, ARBs | Efferent: remove angiotensin II constriction | ↓; KDIGO: continue unless creatinine rises more than 30% within 4 weeks of starting or a dose increase | Bilateral renal artery stenosis or stenosis to a solitary kidney; volume depletion |
| SGLT2 inhibitors | More NaCl reaches the macula densa, restoring TGF; intraglomerular pressure falls | Initial dip of about 4–6 mL/min/1.73 m²; KDIGO: generally not a reason to stop | Withhold during prolonged fasting, surgery or critical illness |
| Calcineurin inhibitors (cyclosporine, tacrolimus) | Afferent vasoconstriction | ↓ | Transplant recipients; hemodynamic, prerenal-type fall in GFR |
With SGLT2 inhibitors, type 1 diabetes studies point to afferent constriction, while in type 2 diabetes efferent dilation may also contribute; the evidence for this split is indirect. For other ACE inhibitor and ARB effects, see the ACE inhibitors vs ARBs mnemonic.
How chronic hypertension, diabetes and CKD change the curve
- Chronic hypertension shifts the curve to the right. The reset protects the glomeruli at higher pressures, but a MAP that is normal for most people can then sit below the patient's lower limit, so GFR falls when pressure is lowered quickly. In patients, a shifted lower limit has been shown in severe but not moderate hypertension, and hypertensive animals that fail to reset are the ones at higher risk of CKD. This is one reason a hypertensive emergency is treated with a 20–25% fall in MAP over the first 1–2 hours, not a rush to normal (see hypertensive emergency vs urgency).
- Diabetes resets and blunts it. Early diabetes resets TGF upward and drives hyperfiltration; impaired autoregulation has been reported in most rat models of type 2 diabetes and in people with type 2 diabetes.
- CKD erodes the reserve in both directions. Surviving nephrons work harder, and in rats with most of their renal mass removed, autoregulation was impaired, so more systemic pressure reached the remaining glomeruli and glomerulosclerosis tracked blood pressure. That is the rationale for blood pressure control and for drugs that lower intraglomerular pressure (ACE inhibitors, ARBs, SGLT2 inhibitors), whose small creatinine rises are expected. In the same rat model, nifedipine lowered blood pressure but abolished autoregulation and, unlike enalapril, did not prevent glomerulosclerosis. The same kidney tolerates low pressure poorly: patients with CKD are at greater risk of AKI.
Clinical correlations
The "triple whammy": NSAID + ACE inhibitor/ARB + diuretic
The diuretic shrinks plasma volume, the NSAID blocks afferent dilation, and the ACE inhibitor or ARB blocks efferent constriction, removing all three props at once. In a UK cohort of 487,372 users of antihypertensive drugs (nested case-control analysis of 2,215 AKI cases), current triple therapy carried a 31% higher rate of AKI (rate ratio 1.31, 95% CI 1.12–1.53), highest in the first 30 days of use (rate ratio 1.82, 1.35–2.46); double combinations with an NSAID did not raise the rate.
Renal artery stenosis and ACE inhibitors
Beyond a significant stenosis (lumen narrowed at least 70% with a poststenotic pressure gradient), the afferent arteriole is already dilated and GFR leans on angiotensin II at the efferent arteriole. An ACE inhibitor or ARB removes that prop, which matters most in bilateral stenosis or stenosis to a solitary kidney; with unilateral disease the other kidney usually keeps total GFR near normal. About 80% of cases are atherosclerotic (men over 50) and 20% fibromuscular dysplasia (younger patients, usually women). See the renal artery stenosis draw-it-out guide.
Hypotension below the range: prerenal AKI and ATN
Below the autoregulatory range (shock, sepsis, hemorrhage, overdiuresis, low cardiac output), RBF and GFR fall with pressure. The tubules are intact and reabsorb sodium and water avidly: FENa < 1%, urine sodium < 10 mmol/L, urine-to-plasma osmolality > 1.5, BUN:creatinine > 20 and a normal sediment. Improvement once perfusion is restored confirms a prerenal cause; severe or prolonged hypoperfusion progresses to ischemic ATN with tubular cells and many granular ("muddy brown") casts. The indices are unreliable when urine output is preserved. See prerenal vs intrinsic vs postrenal AKI.
Hepatorenal syndrome
In advanced cirrhosis with ascites, or alcoholic hepatitis, extreme splanchnic arterial vasodilation lowers central arterial volume, and neural and hormonal responses constrict the renal vessels, cutting renocortical blood flow and GFR. The kidneys are structurally normal, so the picture looks prerenal (low urine sodium, benign sediment) but does not resolve with a volume load. Treatment: vasoconstrictors (terlipressin, or midodrine plus octreotide; norepinephrine if refractory) with albumin, then liver transplantation if needed. Terlipressin (Terlivaz), a vasopressin analogue with twice the selectivity for V1 as for V2 receptors, is FDA-approved to improve kidney function in adults with hepatorenal syndrome with rapid reduction in kidney function; it carries a boxed warning for serious or fatal respiratory failure. See cirrhosis and portal hypertension.
Calcineurin inhibitors and contrast
Cyclosporine and tacrolimus constrict the afferent arteriole, like NSAIDs. Iodinated contrast adds a separate hit, with risk concentrated in preexisting kidney disease, diabetes with CKD, heart failure, age over 70 and dehydration; creatinine typically starts rising within 24 hours and peaks at 3–5 days.
How USMLE tests it: traps and look-alikes
| Look-alike pair | Key discriminator |
|---|---|
| Macula densa vs JG cells | Macula densa senses tubular NaCl (NKCC2); JG cells secrete renin and respond to afferent wall tension |
| NSAID vs ACE inhibitor/ARB | Afferent constriction, FF unchanged vs efferent dilation, FF falls |
| Prerenal AKI vs ATN | FENa < 1%, BUN:Cr > 20, normal sediment vs FENa > 1%, BUN:Cr < 10, granular casts |
| Prerenal AKI vs hepatorenal syndrome | Both have low urine sodium; hepatorenal syndrome does not resolve with volume |
| Unilateral vs bilateral renal artery stenosis on an ACE inhibitor | Creatinine usually near normal vs a sharp rise |
Worked vignettes
Vignette 1: the triple whammy. A 76-year-old woman with hypertension takes lisinopril and hydrochlorothiazide and starts ibuprofen 600 mg three times a day for knee osteoarthritis. Nine days later she is weak and light-headed: BP 104/62 mm Hg, creatinine 2.1 mg/dL (0.9 last month), BUN 48 mg/dL, urine osmolality 520 mOsm/kg (plasma about 290), urinalysis bland. What is the mechanism?
Answer: Prerenal AKI from three simultaneous hits on glomerular pressure.
Reasoning: Her MAP is 62 + (42 ÷ 3) ≈ 76 mm Hg, below the textbook lower limit. The thiazide contracted her volume, ibuprofen removed afferent prostaglandin dilation, and lisinopril removed efferent angiotensin II constriction: the kidney can neither open the inlet nor tighten the outlet. BUN:creatinine ≈ 23 and urine-to-plasma osmolality ≈ 1.8 fit a prerenal state; the bland sediment argues against ATN. Stop the NSAID, hold the other two and restore volume.
Vignette 2: lowering pressure too fast. A 70-year-old man with long-standing, poorly controlled hypertension (usual BP about 190/100 mm Hg; creatinine 1.2 mg/dL) has no acute organ damage. Several antihypertensives are given in quick succession; next morning his BP is 112/68 mm Hg and creatinine 1.6 mg/dL. No NSAIDs or contrast; urinalysis bland. What explains the creatinine rise?
Answer: A hemodynamic fall in GFR: his autoregulatory curve is shifted right, and the new pressure is below his lower limit.
Reasoning: MAP fell from 100 + (90 ÷ 3) = 130 to 68 + (44 ÷ 3) ≈ 83 mm Hg, a 36% drop overnight. A MAP of 83 is inside the textbook range but not inside his, so his RBF and GFR are now pressure-dependent. A bland urinalysis argues against ATN (granular casts) and glomerulonephritis (RBC casts). Lower his pressure gradually.
Vignette 3: filtration fraction in bilateral renal artery stenosis. A 68-year-old smoker with peripheral artery disease and an abdominal bruit has an inulin clearance of 80 mL/min and a PAH clearance of 380 mL/min. Ten days after starting lisinopril: inulin clearance 48 mL/min, PAH clearance 400 mL/min, creatinine 1.1 → 1.8 mg/dL. What happened to the filtration fraction?
Answer: FF fell from 80 ÷ 380 ≈ 21% to 48 ÷ 400 = 12%, the signature of efferent dilation; creatinine rose (1.8 − 1.1) ÷ 1.1 ≈ 64%, far past the 30% threshold.
Reasoning: With both renal arteries narrowed, GFR depended on angiotensin II constricting the efferent arterioles; lisinopril removed it, so plasma flow held while GFR fell. At steady state creatinine varies roughly inversely with GFR, so a 40% fall in GFR predicts about 1.67 times baseline (≈ 1.8 mg/dL). Stop the ACE inhibitor and evaluate for renal artery stenosis. An NSAID would have lowered RPF and GFR together, leaving FF near 20%.
Key takeaways
- RBF and GFR are autoregulated across a renal perfusion pressure (≈ MAP) of about 80–180 mm Hg: relatively, not perfectly, constant.
- Myogenic response: stretch → afferent constriction within seconds. TGF: macula densa NaCl (NKCC2) → adenosine (A1) → afferent constriction.
- RBF ≈ 20–25% of cardiac output; RPF = RBF × (1 − Hct); FF = GFR ÷ RPF ≈ 20%.
- Afferent constriction (NSAIDs, calcineurin inhibitors): RPF and GFR fall, FF unchanged. Efferent constriction (angiotensin II) raises FF; efferent dilation (ACE inhibitors, ARBs) lowers GFR and FF.
- A creatinine rise of up to 30% within 4 weeks of starting an ACE inhibitor or ARB is acceptable (KDIGO 2024); a larger rise warrants a search for volume depletion, NSAIDs or renal artery stenosis.
- NSAID + ACE inhibitor/ARB + diuretic raises AKI risk, most in the first 30 days.
- Chronic hypertension shifts the curve right; diabetes and CKD blunt it.
Sources
- Pollock DM, Banks RO. Perspectives on Renal Blood Flow Autoregulation — Proceedings of the Society for Experimental Biology and Medicine (1991)
- Post EH, Vincent JL. Renal autoregulation and blood pressure management in circulatory shock — Critical Care (2018)
- Griffin KA, Picken MM, Bidani AK. Deleterious effects of calcium channel blockade on pressure transmission and glomerular injury in rat remnant kidneys — Journal of Clinical Investigation (1995)
- SEPSISPAM: high versus low blood-pressure target in septic shock (Asfar et al., NEJM 2014) — The Bottom Line
- Koh ES, et al. Intrarenal Mechanisms of SGLT2 Inhibitors on Tubuloglomerular Feedback and Natriuresis — Endocrinology and Metabolism (2023)
- Lapi F, et al. Concurrent use of diuretics, ACE inhibitors and ARBs with NSAIDs and risk of acute kidney injury — BMJ (2013)
- KDIGO 2024 CKD Guideline: Executive Summary — KDIGO (2024)
- Acute Kidney Injury (AKI) — Merck Manual Professional Edition (2026)
- Renovascular Hypertension — Merck Manual Professional Edition (2025)
- Hypertension — Merck Manual Professional Edition (2026)
- Hypertensive Emergencies — Merck Manual Professional Edition (2026)
- Systemic Abnormalities in Liver Disease — Merck Manual Professional Edition (2026)
- TERLIVAZ (terlipressin) prescribing information — DailyMed (2026)
- 25.5 Physiology of Urine Formation — Anatomy and Physiology 2e, OpenStax (2022)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
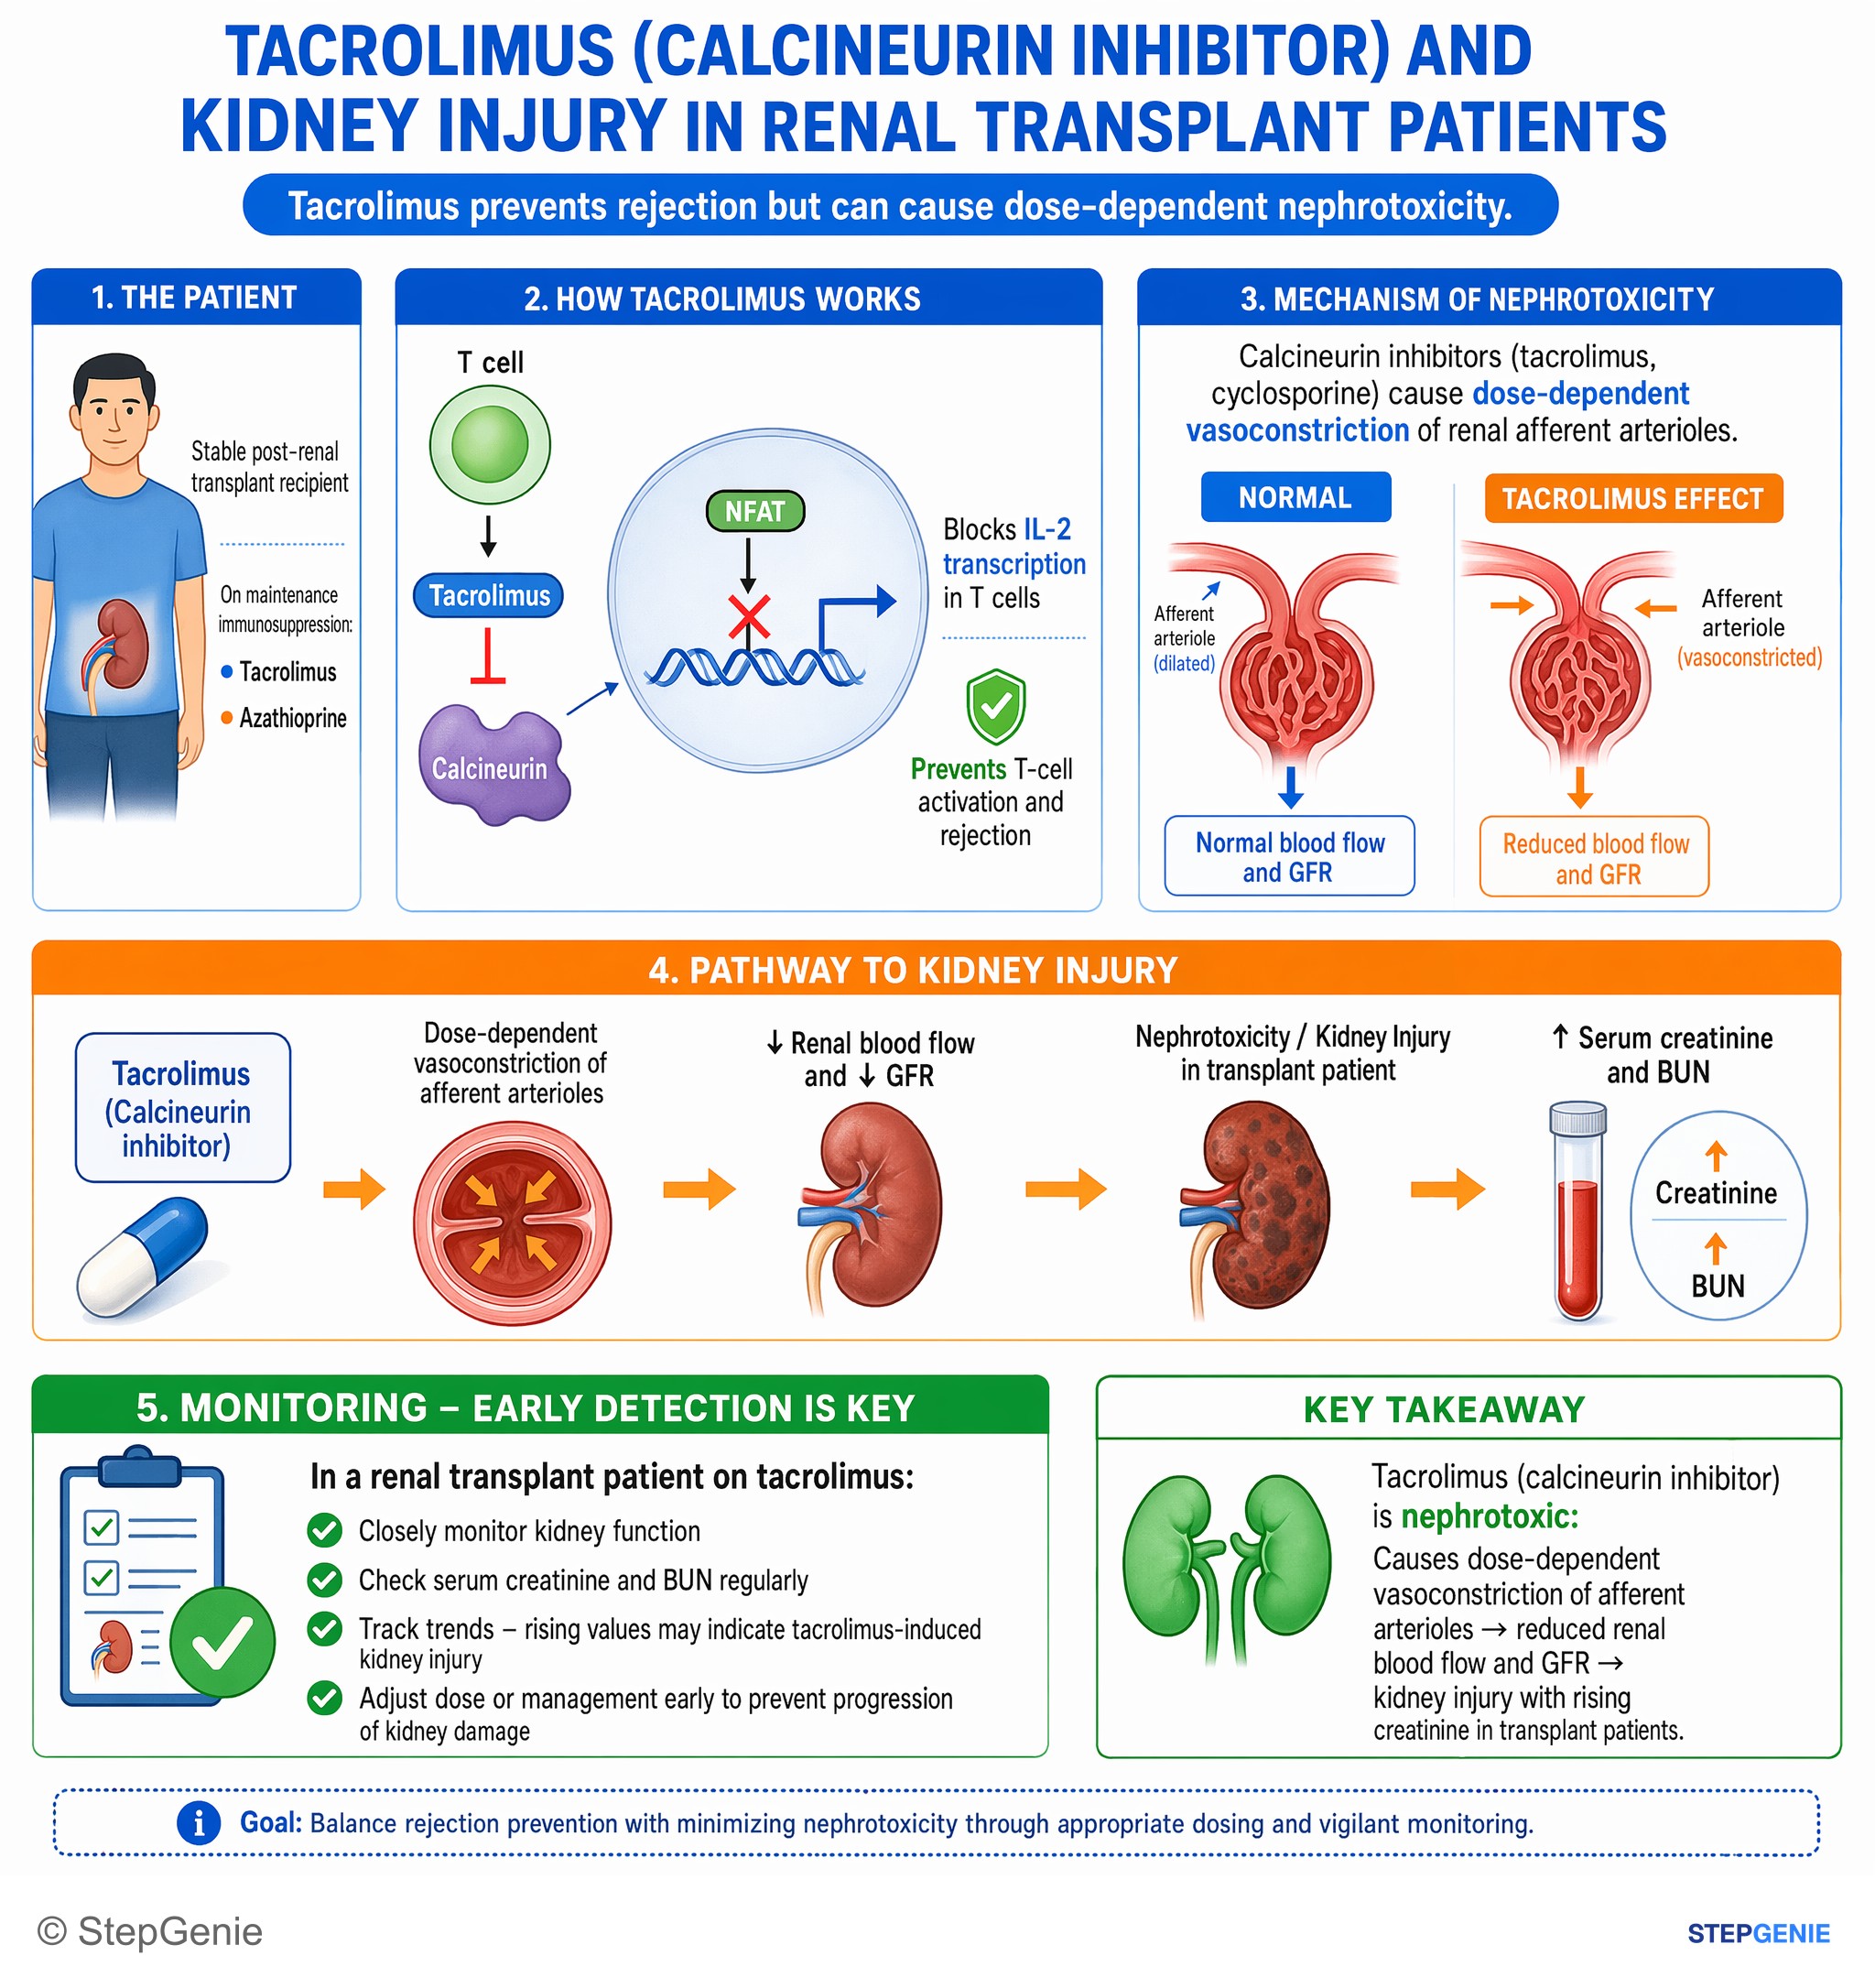
Tacrolimus (calcineurin inhibitor) is nephrotoxic: causes dose-dependent vasoconstriction of afferent arterioles → kidney injury in…
USMLE Step 2Frequently Asked Questions
What is the range of renal autoregulation?
Renal blood flow and GFR are autoregulated over a renal perfusion pressure, which exams equate with mean arterial pressure, of about 80 to 180 mm Hg. Within that plateau they stay relatively constant; below about 80 mm Hg they fall as pressure falls, and above about 180 mm Hg more of the pressure reaches the glomeruli. The figure comes mainly from animal experiments and the limits move: sympathetic activation and chronic hypertension shift the curve to the right, so pressures that are normal for most people can underperfuse some kidneys.
What are the two mechanisms of renal autoregulation?
The myogenic response and tubuloglomerular feedback. In the myogenic response, stretch depolarizes the smooth muscle of the afferent arteriole, calcium enters and the arteriole constricts within seconds. In tubuloglomerular feedback, the macula densa senses increased NaCl delivery through NKCC2 and releases ATP and adenosine, which constrict the afferent arteriole and bring GFR back down; this slower loop joins in after about 5 to 10 seconds. Both work mainly by changing afferent arteriolar resistance.
How does tubuloglomerular feedback work?
Macula densa cells at the end of the thick ascending limb sense NaCl through the Na-K-2Cl cotransporter (NKCC2). When GFR and NaCl delivery rise, adenosine acting on A1 receptors constricts the afferent arteriole and renin release falls. When NaCl delivery falls, the afferent arteriole dilates and renin release rises, and angiotensin II then constricts the efferent arteriole. Loop diuretics blunt the response because they block the sensor, and SGLT2 inhibitors restore it by sending more NaCl to the macula densa.
Why do NSAIDs and ACE inhibitors decrease GFR?
NSAIDs block the vasodilator prostaglandins that keep the afferent arteriole open, so less blood and pressure reach the glomerulus and renal plasma flow and GFR fall together. ACE inhibitors and ARBs remove angiotensin II's constriction of the efferent arteriole, so glomerular capillary pressure and GFR fall while plasma flow is maintained, which lowers the filtration fraction. Both effects matter most when the kidney depends on those hormones: volume depletion, heart failure, cirrhosis, CKD or bilateral renal artery stenosis.
How much can creatinine rise after starting an ACE inhibitor or ARB?
The KDIGO 2024 CKD guideline advises continuing an ACE inhibitor or ARB unless serum creatinine rises by more than 30% within 4 weeks of starting it or increasing the dose. Smaller rises reflect the intended fall in glomerular pressure from efferent arteriolar dilation. A larger rise should prompt a search for another cause, such as volume depletion, NSAID use or renal artery stenosis, classically bilateral or affecting a solitary kidney.
How do chronic hypertension and CKD affect renal autoregulation?
Chronic hypertension shifts the autoregulation curve to the right. This protects the glomeruli at higher pressures, but a mean arterial pressure that is normal for most people can then sit below the patient's lower limit, so GFR falls when blood pressure is lowered quickly. Autoregulation is impaired in type 2 diabetes and in experimental CKD, letting more systemic pressure reach the remaining glomeruli, and patients with CKD are at greater risk of AKI from hypotension, volume loss and drugs such as NSAIDs.