Rapidly progressive glomerulonephritis (RPGN) is a nephritic syndrome that destroys kidney function over days to a few months, and its biopsy signature is crescents filling Bowman space, classically in more than 50% of glomeruli. Immunofluorescence sorts it into three types: type I anti-GBM disease (linear IgG; Goodpasture syndrome when the lungs bleed), type II immune complex disease (granular deposits: post-infectious GN, lupus, IgA nephropathy) and type III pauci-immune disease (few or no deposits; ANCA vasculitis). It is an emergency: up to 90% of untreated patients progress to kidney failure, so glucocorticoids plus cyclophosphamide or rituximab start early, with plasma exchange for anti-GBM disease.
What RPGN is, and what a crescent is
- A syndrome, not one disease. Merck defines RPGN as progression to kidney failure within weeks to months with crescents in more than 50% of sampled glomeruli; StatPearls describes loss of function over days to weeks. Many diseases can produce it, and the immunofluorescence (IF) pattern tells you which one.
- How a crescent forms. Severe injury ruptures the glomerular basement membrane (GBM), and fibrin spills into Bowman space. Parietal epithelial cells proliferate, monocytes/macrophages and T cells move in, and myofibroblasts invade from the interstitium. The crescent-shaped mass compresses the capillary tuft, and filtration collapses.
- Cellular → fibrocellular → fibrous. Cellular crescents are active lesions; fibrous crescents are scar. StatPearls: when more than 50% of glomeruli are still normal, over 90% of patients recover kidney function at 5 years; when more than 50% are globally sclerosed, fewer than 25% do.
- Urine and blood. Hematuria is always present and RBC casts usually are, with dysmorphic RBCs; creatinine is high, anemia is usual and leukocytosis is common. Merck adds that about half of patients have edema, while hypertension is uncommon and rarely severe.
For the bigger nephritic vs nephrotic picture, see nephrotic vs nephritic syndrome.
The three types at a glance
| Type I: anti-GBM | Type II: immune complex | Type III: pauci-immune | |
|---|---|---|---|
| IF pattern | Linear IgG along the GBM | Granular ("lumpy-bumpy") deposits | Few or no immunoglobulin or complement deposits |
| What attacks the glomerulus | Antibodies to the α3 chain of type IV collagen (NC1 domain): type II hypersensitivity | Deposited antigen-antibody complexes: type III hypersensitivity | ANCA-associated necrotizing small-vessel vasculitis |
| Key blood test | Anti-GBM antibody | ASO, anti-DNA, cryoglobulins; C3/C4 | PR3-ANCA (c-ANCA) or MPO-ANCA (p-ANCA) |
| Serum complement | Normal | Often low (PSGN, lupus, MPGN, cryoglobulinemia); normal in IgA nephropathy | Usually normal |
| Prototype | Goodpasture syndrome (with lung hemorrhage) | PSGN, lupus nephritis, IgA nephropathy, IgA vasculitis, cryoglobulinemia | GPA, MPA, EGPA |
| Treatment | Plasma exchange + glucocorticoids + cyclophosphamide | Treat the underlying disease | Glucocorticoids + rituximab or cyclophosphamide |
How common is each type? Shares vary between sources. StatPearls: pauci-immune disease is the most common (40-50%) and is mainly a disease of adults, peaking at ages 60-85; immune complex disease makes up 25-30% and is the type often seen in children; anti-GBM disease makes up 10-15%. Some patients carry both ANCA and anti-GBM antibodies ("double-positive", sometimes called type IV).
Type I: anti-GBM disease (Goodpasture syndrome)
- Target: the noncollagenous (NC1) domain of the α3 chain of type IV collagen, which sits in both the GBM and the alveolar basement membrane. That shared antigen is why kidney and lung fail together.
- Mechanism: antibody-mediated type II hypersensitivity, seen on IF as linear IgG along the GBM.
- Who: about 0.5-1.8 cases per million per year, with a bimodal age distribution: a first peak around age 30 (slightly more men) and a second in the sixth decade (more women). HLA-DR2 is found in up to 80% of patients (StatPearls).
- Triggers: respiratory exposures may unmask alveolar collagen (Merck). StatPearls lists smoking, metal dust, organic solvents and hydrocarbons, influenza A, inhaled cocaine and shock wave lithotripsy.
- Lungs: alveolar hemorrhage in 40-60%; fewer than 10% have lung disease alone.
- Double-positive: 10-50% of patients with anti-GBM disease also have ANCA.
- Treatment (KDIGO 2021): start without waiting for confirmation, using glucocorticoids, plasma exchange and cyclophosphamide. Plasma exchange continues until anti-GBM antibodies are undetectable, cyclophosphamide runs 2-3 months and glucocorticoids taper over 6 months. No maintenance therapy is needed unless the patient is ANCA-positive, and relapse is rare.
- When the kidney is already lost: KDIGO suggests considering a conservative approach for dialysis-dependent patients with 85-100% crescents and no alveolar hemorrhage; in StatPearls, only 8% of dialysis-dependent patients had recovered kidney function at 1 year. Transplant waits until antibodies have been undetectable for at least 6 months.
Same collagen, different disease: Alport syndrome is an inherited type IV collagen defect (COL4A5, X-linked, in about two-thirds; COL4A3 or COL4A4 in the rest), causing hematuria, sensorineural hearing loss and eye changes. It is genetic, not autoimmune, and there is no linear IgG.
Type II: immune complex RPGN
- Mechanism: type III hypersensitivity: antigen-antibody complexes deposit, activate the classical complement pathway and recruit neutrophils and monocytes. IF shows granular deposits.
- Causes: post-infectious GN, lupus nephritis, IgA nephropathy, IgA vasculitis and cryoglobulinemia (StatPearls), plus membranoproliferative GN. Each disease keeps its own clues: see IgA nephropathy vs post-strep GN, lupus nephritis classes and MPGN.
- Complement is the clue. Hypocomplementemia is common in immune complex RPGN (Merck). Low complement points to PSGN, lupus, MPGN, cryoglobulinemia, infective endocarditis or shunt nephritis; IgA nephropathy and IgA vasculitis have normal complement (StatPearls).
- Workup: antistreptolysin O, anti-DNA antibodies, cryoglobulins and C3/C4 (Merck).
- Treatment: aimed at the underlying disease (for example, lupus nephritis regimens).
Type III: pauci-immune (ANCA) RPGN
Almost all patients have ANCA, usually anti-proteinase 3 (PR3) or anti-myeloperoxidase (MPO) (Merck). The biopsy shows necrotizing, crescentic GN with little or no immune deposit.
| GPA | MPA | EGPA | |
|---|---|---|---|
| ANCA | Most with active disease: c-ANCA / PR3 | At least 70% ANCA-positive, usually p-ANCA / MPO | 30-40%, mostly p-ANCA / MPO |
| Granulomas | Yes (necrotizing granulomatous inflammation) | No | Yes, with eosinophilic tissue infiltration |
| Airway clues | Sinusitis, epistaxis, saddle nose, lung nodules with or without cavitation, subglottic stenosis | Upper airway little or not at all; alveolar hemorrhage may occur | Adult-onset asthma, allergic rhinitis, nasal polyps, eosinophilia |
| Kidney | About 80% within 2 years (only 10-20% at presentation) | Up to 90% | Less often than in GPA or MPA |
- Complement: serum C3 and C4 are usually normal; in one 45-patient cohort, every C3 at diagnosis was within the normal range, although patients in the lower half of that range did worse.
- Treatment (KDIGO 2024): if a patient is deteriorating, don't wait for the biopsy. Induction is glucocorticoids plus rituximab or cyclophosphamide; lower glucocorticoid doses work as well, with less toxicity. Plasma exchange should be considered for creatinine above 3.4 mg/dL (300 µmol/L), dialysis or a rapidly rising creatinine, or alveolar hemorrhage with hypoxemia, and it is added for ANCA plus anti-GBM overlap. Maintenance is rituximab, or azathioprine with low-dose glucocorticoids.
- Course: untreated, about 80% die; treated, 5-year survival is about 75%, and about 40% relapse (StatPearls). More detail: GPA (Wegener).
How USMLE tests RPGN
| Clue in the stem | Think |
|---|---|
| Young adult smoker, hemoptysis + RBC casts, linear IgG | Anti-GBM disease (Goodpasture), type II hypersensitivity |
| Sinusitis or saddle nose, cavitating lung nodules, RBC casts, PR3-ANCA | GPA |
| RPGN ± alveolar hemorrhage, no granulomas or upper airway disease, MPO-ANCA | MPA |
| Asthma, eosinophilia, p-ANCA | EGPA |
| RPGN with low C3 | Immune complex cause: PSGN, lupus, MPGN, cryoglobulinemia |
| Hematuria + hearing loss + family history | Alport syndrome (not RPGN, not autoimmune) |
Pulmonary-renal syndrome (lung hemorrhage plus GN): think first of anti-GBM disease or ANCA vasculitis; serology and IF decide which.
Practice question
A 23-year-old man who smokes has had 1 week of cough with blood-streaked sputum and 3 days of dark urine and fatigue. Blood pressure is 136/84 mm Hg. Hemoglobin is 10.2 g/dL, and serum creatinine is 4.6 mg/dL (1.0 mg/dL six months ago). Urinalysis shows 3+ blood, 1+ protein, dysmorphic RBCs and RBC casts. Chest x-ray shows bilateral patchy alveolar infiltrates. Serum C3 is normal. Kidney biopsy shows crescents in most glomeruli, and immunofluorescence shows linear IgG along the glomerular basement membrane. The pathogenic antibodies are most likely directed against which of the following?
A. Double-stranded DNA B. M-type phospholipase A2 receptor C. Myeloperoxidase D. Noncollagenous domain of the α3 chain of type IV collagen E. Proteinase 3
Answer: D. Hemoptysis plus RPGN with linear IgG along the GBM is anti-GBM disease (Goodpasture syndrome), a type II hypersensitivity reaction against the α3 chain of type IV collagen, present in both glomerular and alveolar basement membranes. Treatment starts at once with plasma exchange, glucocorticoids and cyclophosphamide.
- A: anti-dsDNA antibodies point to lupus nephritis, an immune complex disease with granular deposits and often low complement.
- B: PLA2R is the main target antigen in primary membranous nephropathy, a common cause of nephrotic syndrome in adults, with granular IgG and subepithelial deposits.
- C: MPO-ANCA (p-ANCA) marks MPA, which can also cause lung hemorrhage plus RPGN, but its biopsy is pauci-immune, with no linear IgG.
- E: PR3-ANCA (c-ANCA) marks GPA: upper airway disease, cavitating nodules and pauci-immune GN.
Key takeaways
- RPGN = nephritic syndrome + kidney failure over days to months + crescents (classically in more than 50% of glomeruli).
- Crescents = fibrin, proliferating parietal epithelial cells and macrophages in Bowman space; cellular crescents are treatable, fibrous ones are scar.
- Linear = anti-GBM (type II hypersensitivity); granular = immune complex (type III); pauci-immune = ANCA.
- Low complement points to an immune complex cause; anti-GBM disease, IgA nephropathy and ANCA vasculitis usually have normal complement.
- c-ANCA/PR3 = GPA; p-ANCA/MPO = MPA (and EGPA).
- Anti-GBM disease: plasma exchange + glucocorticoids + cyclophosphamide, started without delay; relapse is rare.
- ANCA RPGN: glucocorticoids + rituximab or cyclophosphamide; consider plasma exchange for creatinine above 3.4 mg/dL, dialysis or alveolar hemorrhage with hypoxemia (KDIGO 2024).
Sources
- Rapidly Progressive Glomerulonephritis (RPGN) — Merck Manual Professional Edition (2025)
- Rapidly Progressive Glomerulonephritis — StatPearls, NCBI Bookshelf (2024)
- Goodpasture Syndrome — StatPearls, NCBI Bookshelf (2024)
- KDIGO 2024 ANCA-Associated Vasculitis Guideline: Top 10 Takeaways for Clinicians — KDIGO (2024)
- KDIGO 2021 Glomerular Diseases Guideline: Key Takeaways for Clinicians, Anti-GBM — KDIGO (2021)
- Granulomatosis With Polyangiitis (GPA) — Merck Manual Professional Edition (2025)
- Granulomatosis With Polyangiitis — StatPearls, NCBI Bookshelf (2024)
- Microscopic Polyangiitis (MPA) — Merck Manual Professional Edition (2025)
- Eosinophilic Granulomatosis With Polyangiitis (EGPA) — Merck Manual Professional Edition (2025)
- Glomerulonephritis — StatPearls, NCBI Bookshelf (2023)
- Low Serum Complement C3 Levels at Diagnosis of Renal ANCA-Associated Vasculitis Is Associated with Poor Prognosis — PLOS ONE (2016)
- Alport syndrome — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
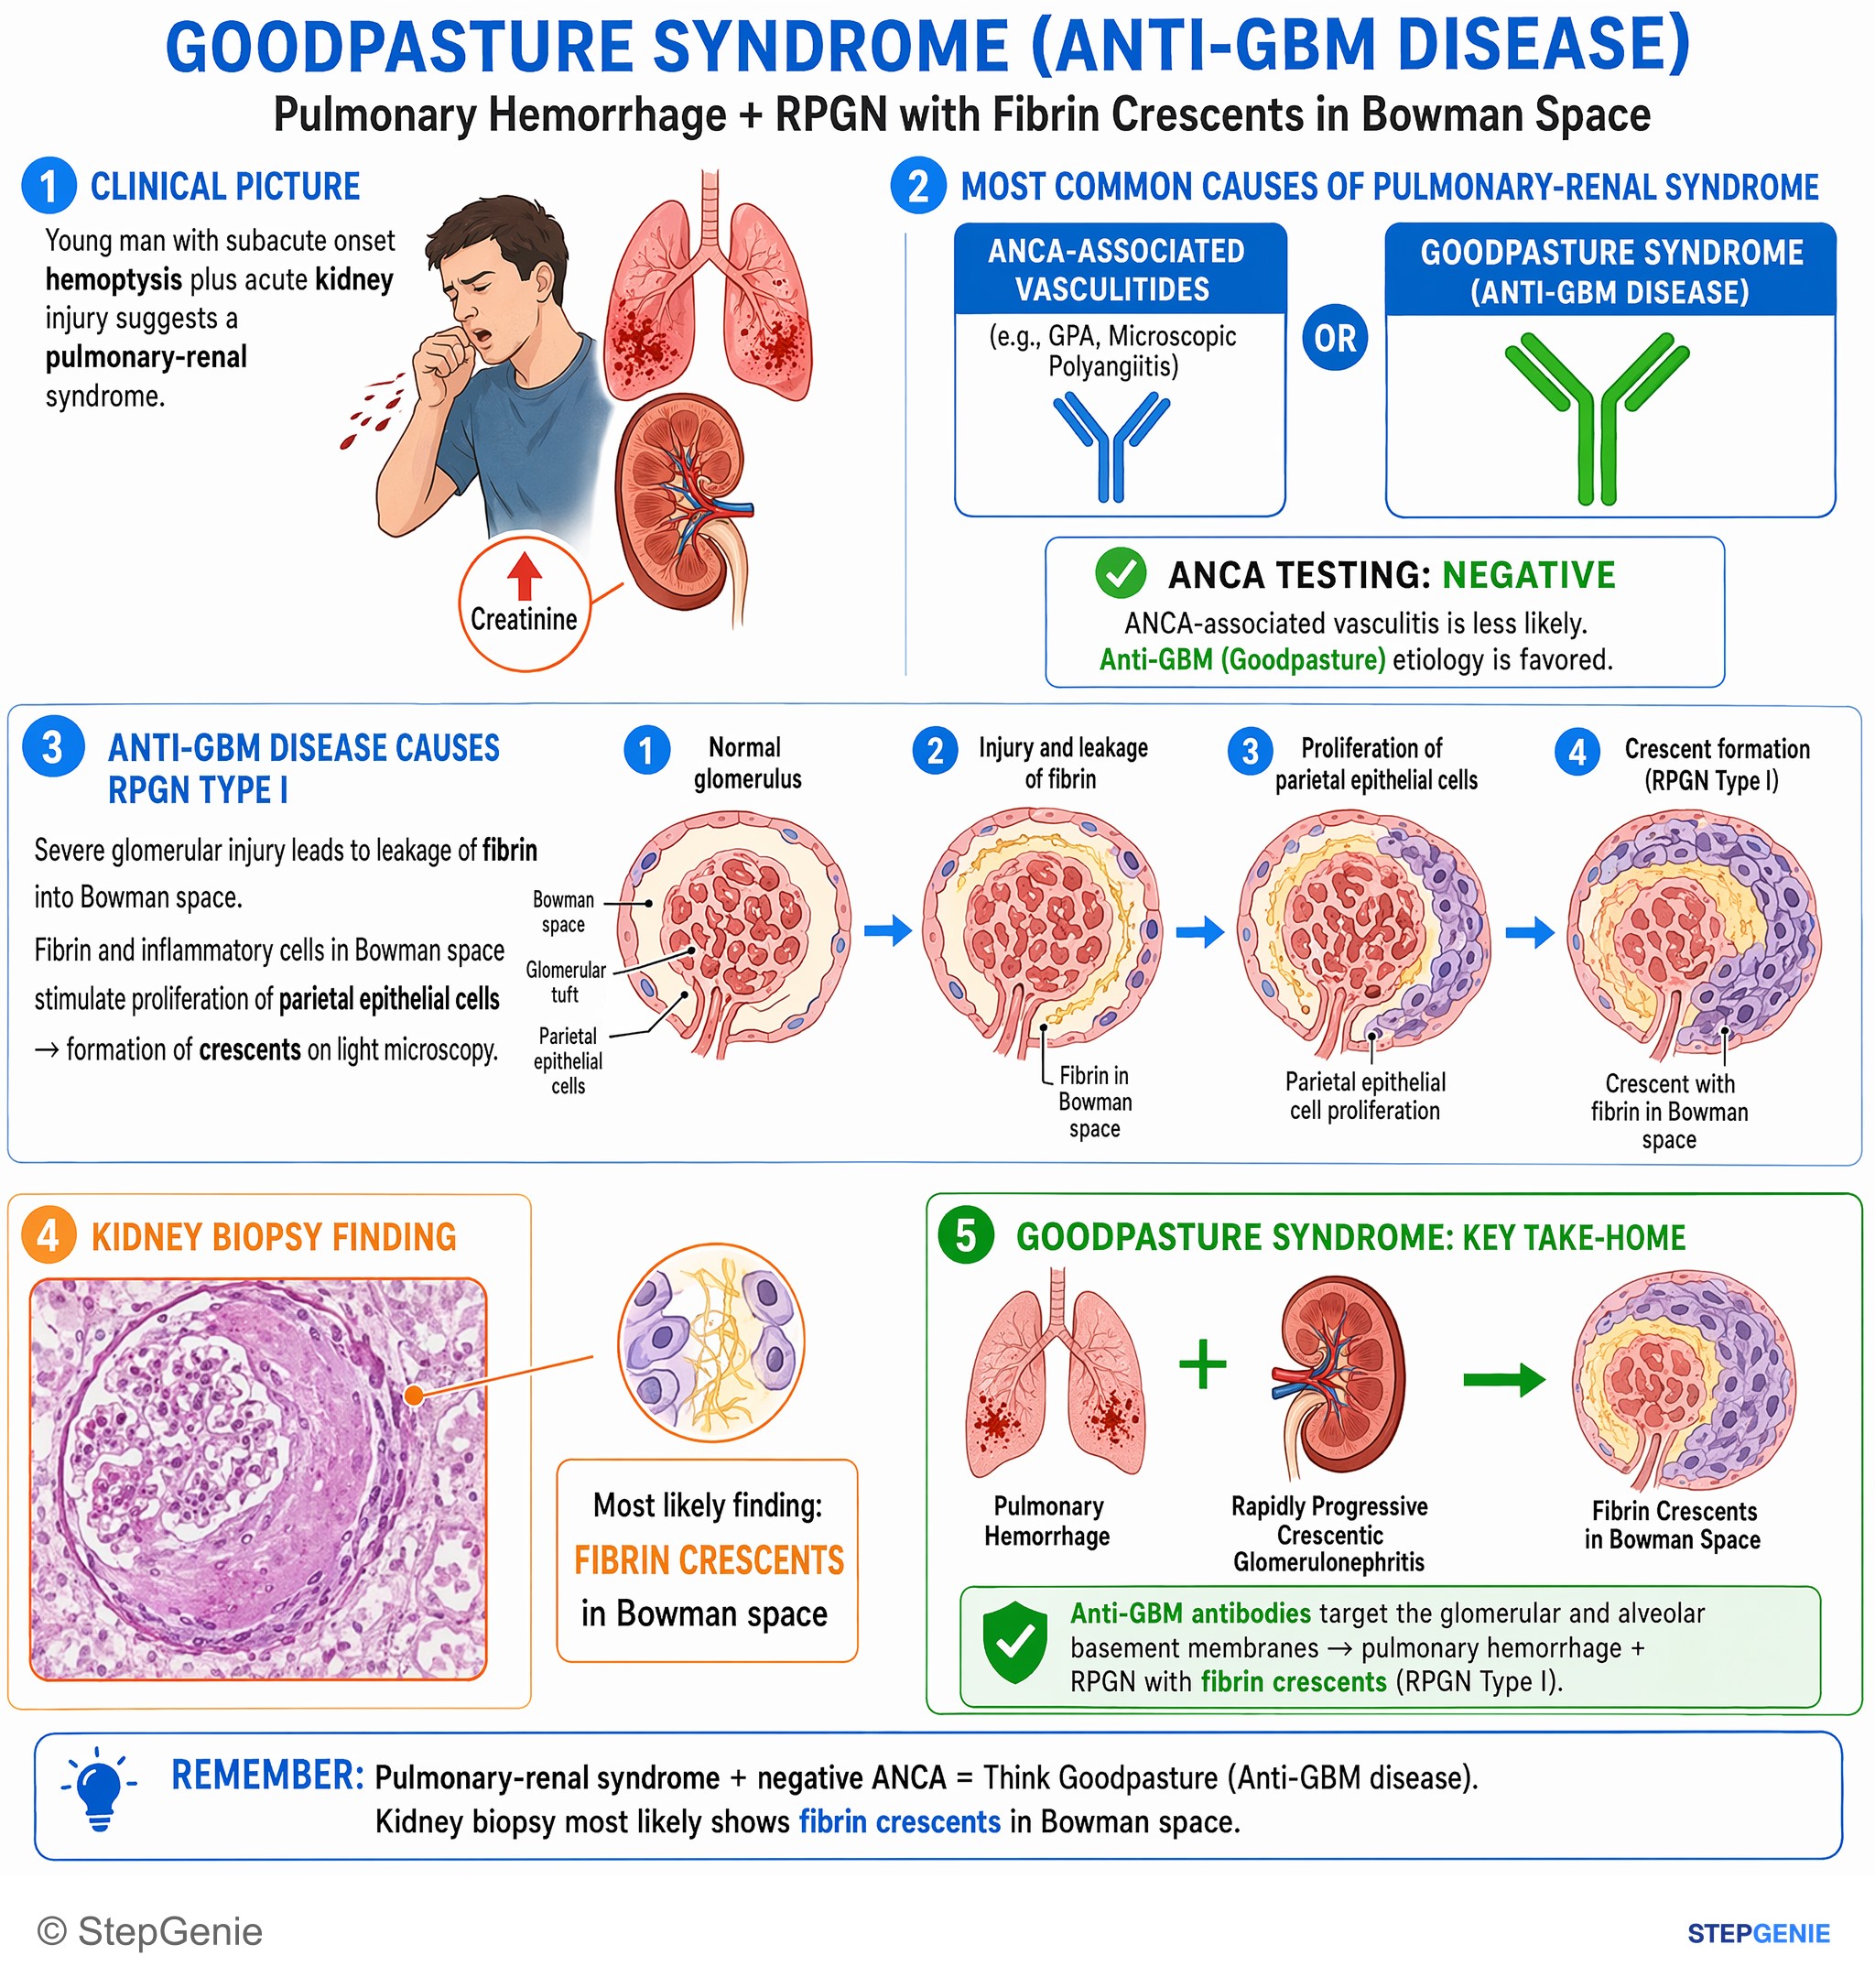
Goodpasture syndrome: anti-GBM disease causing pulmonary hemorrhage + rapidly progressive crescentic glomerulonephritis with fibrin…
USMLE Step 1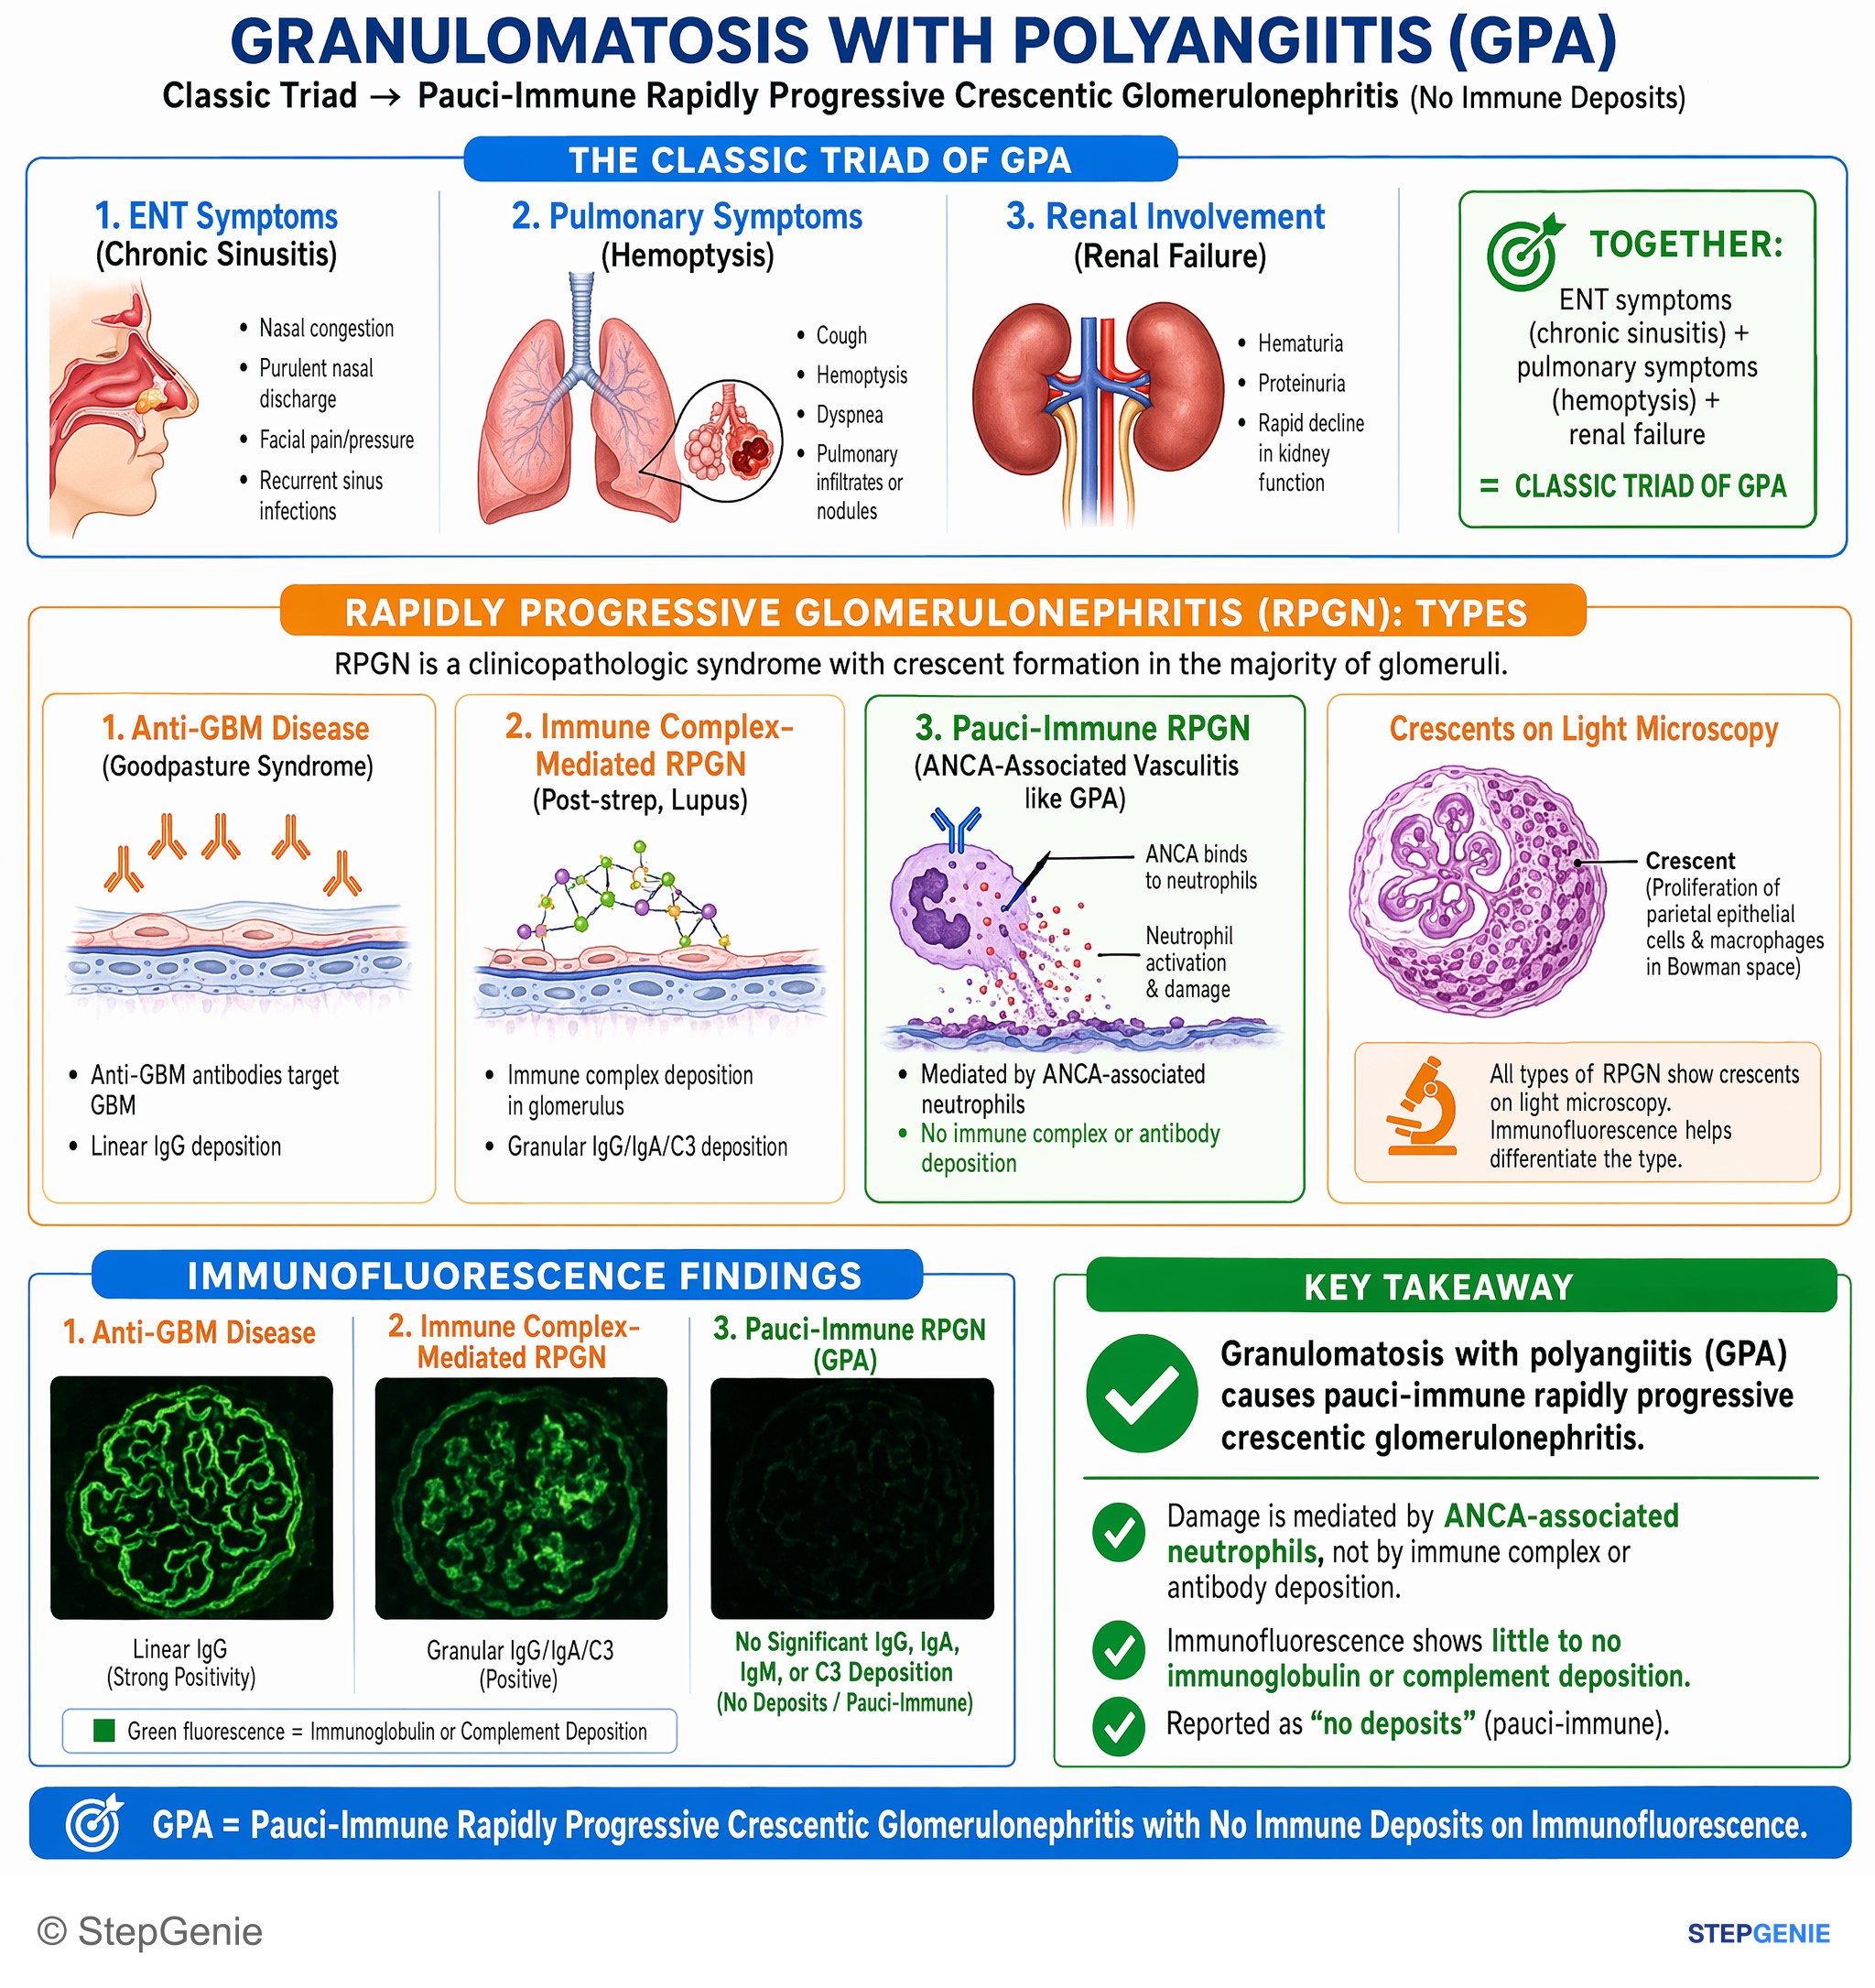
Granulomatosis with polyangiitis causes pauci-immune rapidly progressive crescentic glomerulonephritis with no immune deposits on…
USMLE Step 1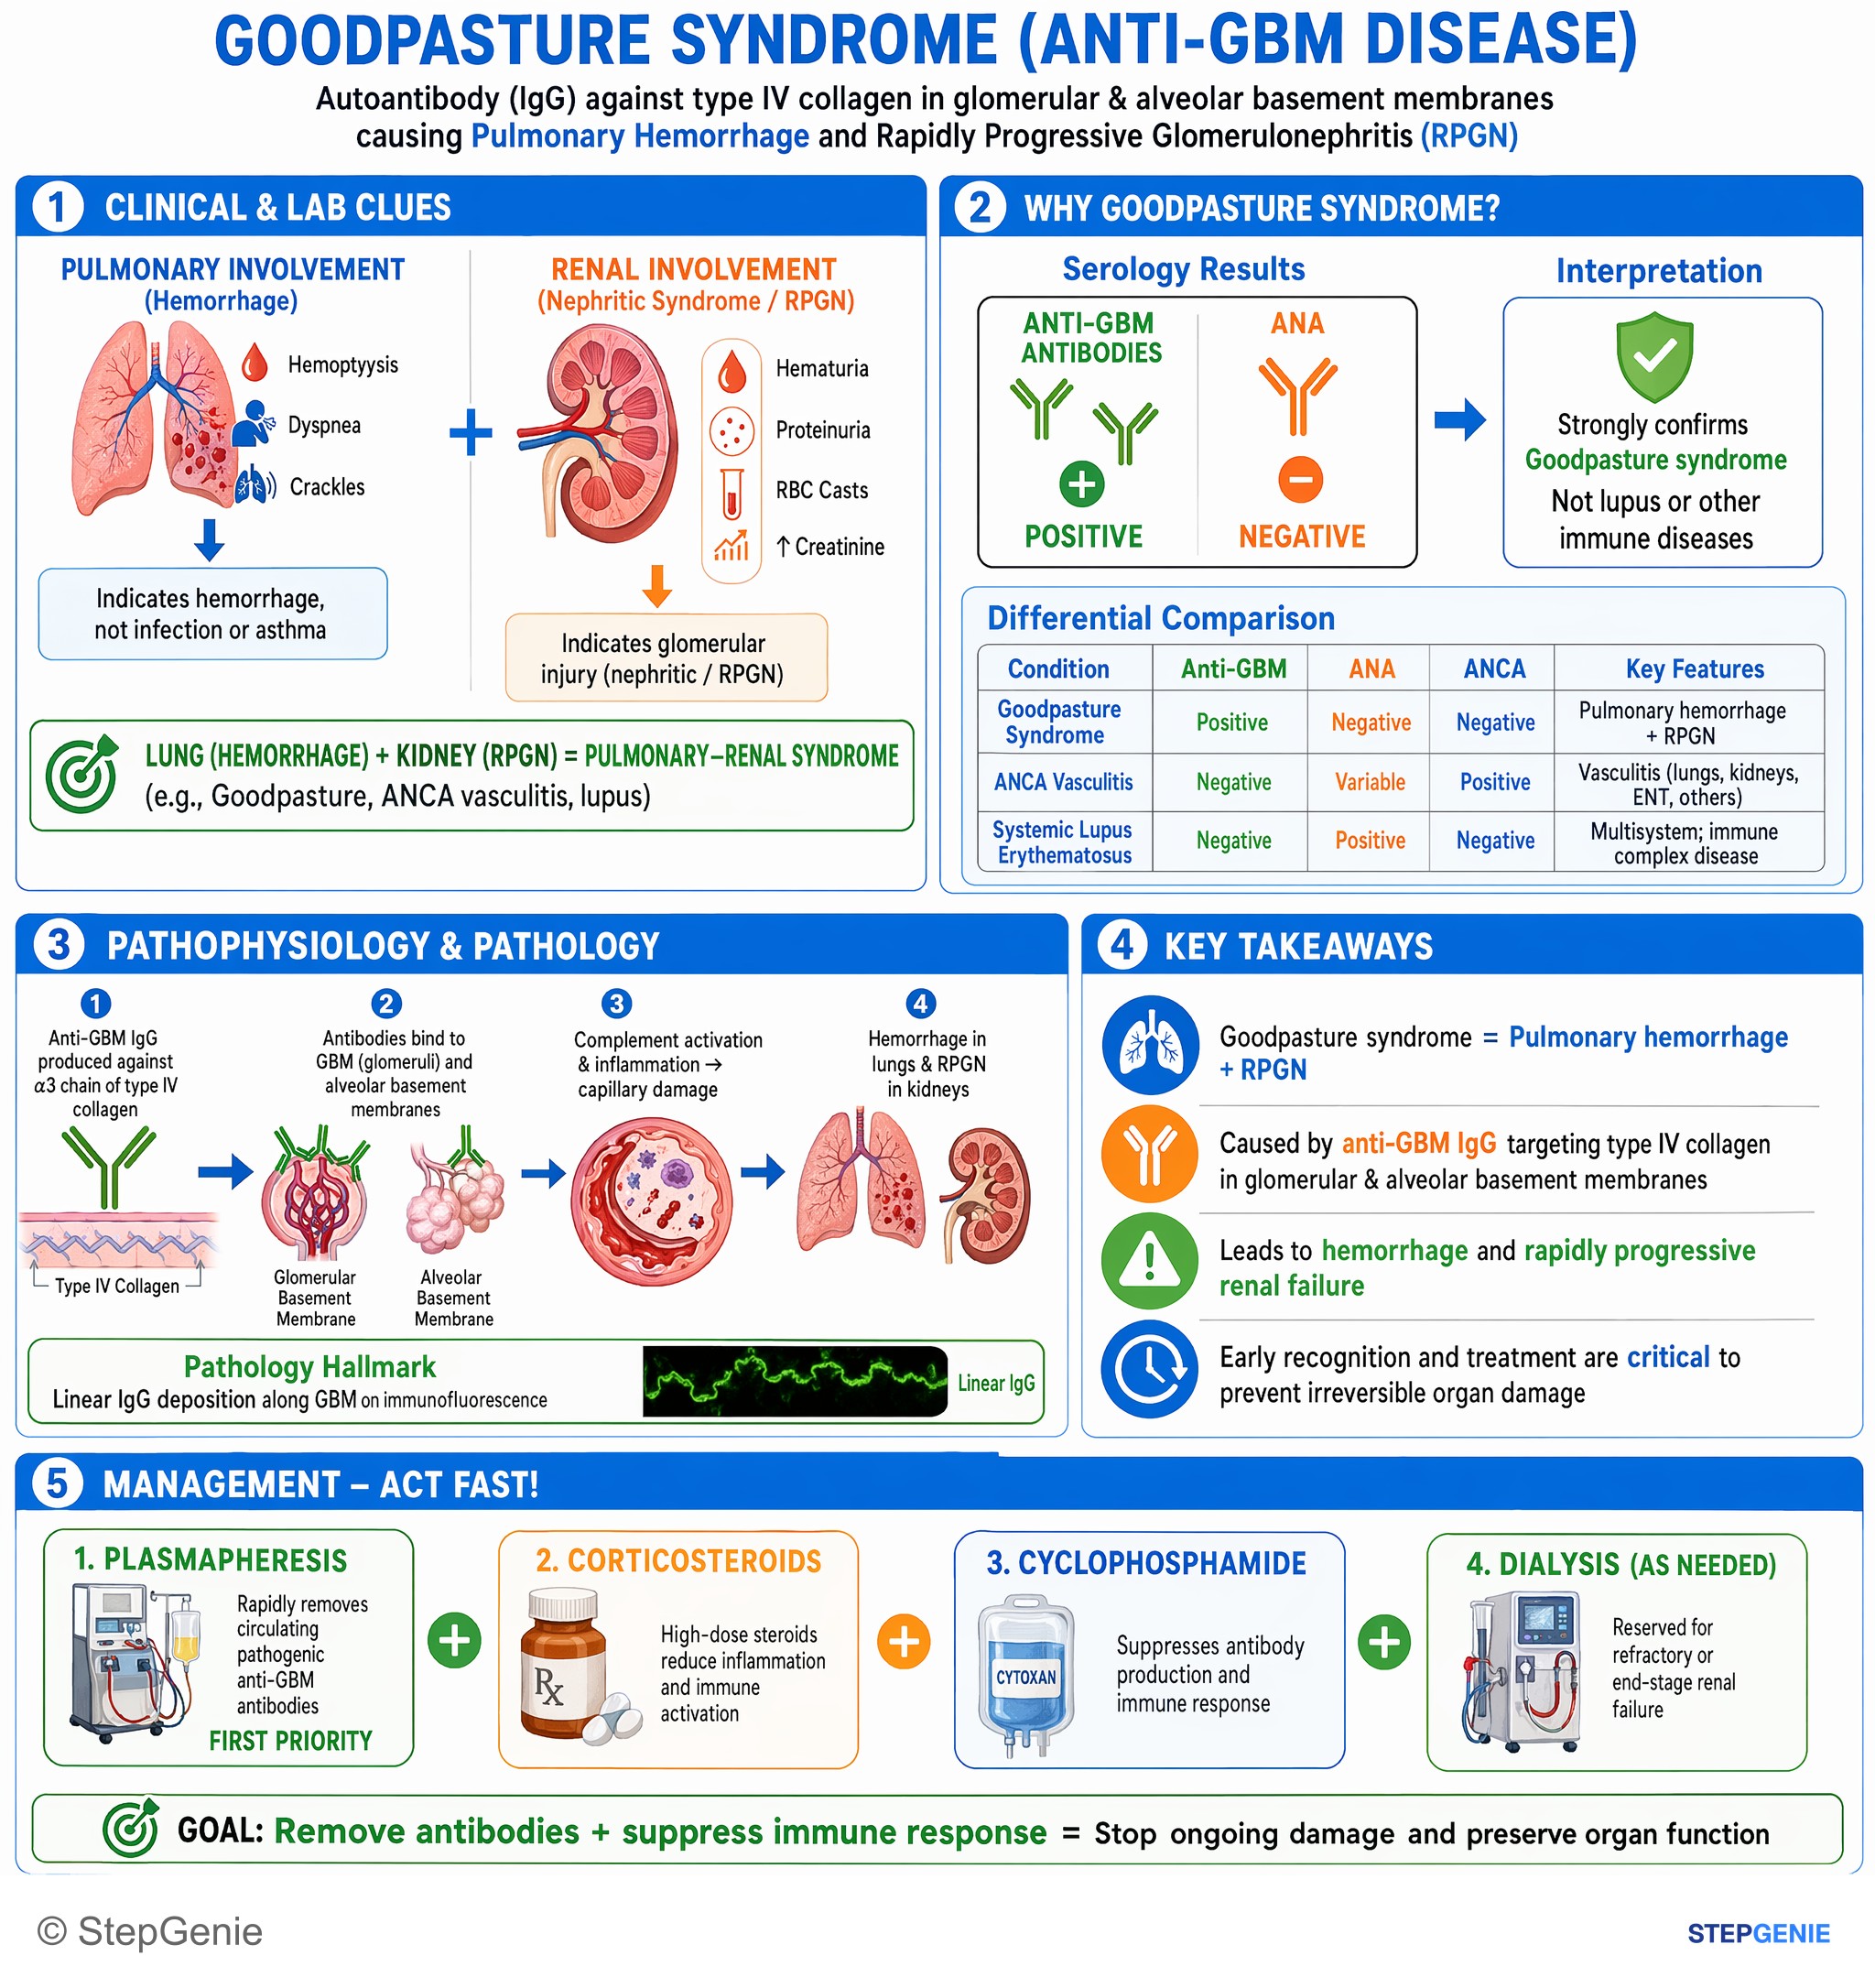
Goodpasture syndrome (anti-GBM disease) causes pulmonary hemorrhage + RPGN; treat urgently with plasmapheresis + steroids +…
USMLE Step 2Frequently Asked Questions
What is rapidly progressive glomerulonephritis?
Rapidly progressive glomerulonephritis (RPGN) is a nephritic syndrome in which kidney function falls over days to a few months, with crescents in Bowman space, classically in more than 50% of glomeruli on biopsy. Patients have hematuria, usually with red cell casts, and a rising creatinine. It is a syndrome with many causes, grouped by immunofluorescence into anti-GBM, immune complex and pauci-immune (ANCA) disease. Untreated, up to 90% of patients progress to kidney failure.
What are the three types of RPGN?
Type I is anti-GBM disease: antibodies against the alpha-3 chain of type IV collagen give linear IgG on immunofluorescence, and lung hemorrhage makes it Goodpasture syndrome. Type II is immune complex disease with granular deposits, caused by post-infectious GN, lupus nephritis, IgA nephropathy, IgA vasculitis or cryoglobulinemia. Type III is pauci-immune disease with few or no deposits, almost always from ANCA vasculitis such as granulomatosis with polyangiitis or microscopic polyangiitis.
What are crescents in glomerulonephritis made of?
A crescent forms when severe injury breaks the glomerular basement membrane and fibrin leaks into Bowman space. Parietal epithelial cells proliferate, monocytes, macrophages and T cells move in, and myofibroblasts invade from the interstitium, building a crescent-shaped mass that compresses the capillary tuft. Early cellular crescents are active lesions that can respond to treatment; over time they become fibrocellular and then fibrous, which is permanent scar.
Which types of RPGN have low complement?
Low C3 (and sometimes C4) points to an immune complex cause, such as post-streptococcal or other post-infectious GN, lupus nephritis, membranoproliferative GN, cryoglobulinemia, infective endocarditis or shunt nephritis. Complement is normal in IgA nephropathy and IgA vasculitis, and usually normal in anti-GBM disease and ANCA vasculitis. A clearly low C3 in a patient with RPGN therefore steers the workup toward an immune complex disease.
How is anti-GBM disease (Goodpasture syndrome) treated?
KDIGO advises starting treatment without waiting for confirmation, using plasma exchange, glucocorticoids and cyclophosphamide. Plasma exchange continues until anti-GBM antibodies are undetectable; cyclophosphamide is given for 2 to 3 months, and glucocorticoids are tapered over 6 months. Maintenance therapy is not needed unless ANCA is also positive, and relapse is rare. A conservative approach may be considered in dialysis-dependent patients with 85 to 100% crescents and no lung hemorrhage.
How is ANCA-associated (pauci-immune) RPGN treated?
The KDIGO 2024 guideline starts glucocorticoids with rituximab or cyclophosphamide, without waiting for a biopsy if the patient is deteriorating, and notes that lower glucocorticoid doses work as well with fewer side effects. Plasma exchange should be considered when creatinine is above 3.4 mg/dL, the patient needs dialysis or creatinine is rising fast, or there is alveolar hemorrhage with hypoxemia. Maintenance uses rituximab, or azathioprine with low-dose glucocorticoids.